Optimize Preop | Minimize Blood Loss | Transfuse Appropriately
- Preoperative anemia (Hb less than 130 g/L men, less than 120 g/L women) increases transfusion risk 3-4 fold
- Tranexamic acid (TXA) 15-20 mg/kg IV reduces transfusion by 30-50% without increasing VTE
- Restrictive transfusion threshold (Hb less than 70 g/L) is safe and reduces complications vs liberal (less than 100 g/L)
- Cell salvage contraindicated in malignancy, infection, bowel contamination
- Massive transfusion protocol: 1:1:1 ratio RBC:FFP:Platelets to prevent dilutional coagulopathy
- “CRASH-2 trial: TXA within 3h of trauma reduces mortality (not just blood loss)
- “Iron therapy takes 4-6 weeks - plan elective surgery timing accordingly
- “Jehovah's Witness patients: multi-modal approach (EPO, TXA, cell salvage, accept lower Hb)
- “Hypotensive anesthesia (MAP 50-60 mmHg) reduces blood loss but requires experienced anesthetist
Overview and Clinical Significance
The shift. Patient Blood Management (PBM) has replaced the old reactive "type and cross" model with a proactive one: detect and treat anaemia before surgery, minimise blood loss during it, and transfuse appropriately afterwards. Working this way reduces transfusion rates by 30-50% and improves outcomes.
The three pillars. The framework is WHO-endorsed and used across international PBM programmes.
- Optimise haematopoiesis - detect and treat preoperative anaemia
- Minimise blood loss - surgical technique, TXA, cell salvage
- Harness physiological reserve - restrictive transfusion thresholds
Why it matters. Preoperative anaemia is present in 30-40% of elective orthopaedic patients and increases the risk of transfusion three- to four-fold. Allogeneic transfusion in turn increases infection, length of stay and mortality; blood is a scarce resource with donor shortages worldwide, and one unit of red cells typically costs the equivalent of $500-1000 (USD) including administration.
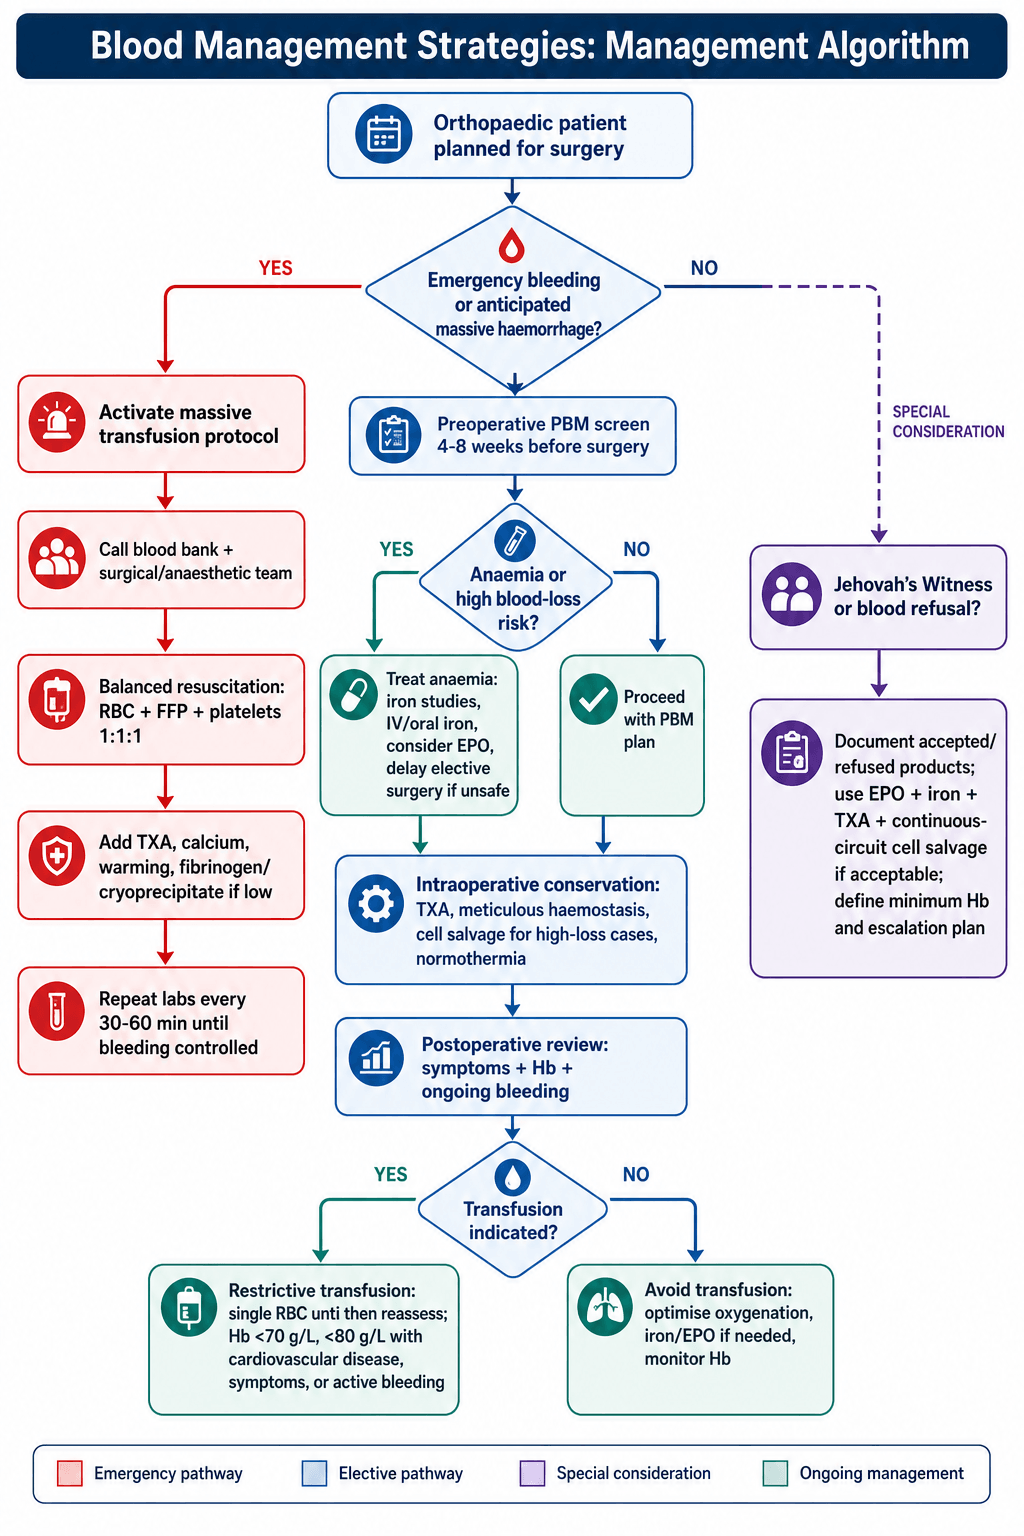
Site-specific companion. This page is the general PBM framework — the three pillars, transfusion thresholds and the Jehovah's Witness approach. Spine surgery has its own problems on top (the highest transfusion rate in orthopaedics, the epidural venous plexus, the hypotension-versus-cord-perfusion tension, and perioperative visual loss); those are set out in blood loss management in spine surgery.
Pathophysiology
Physiology of Haemostasis
The cascade. Tissue factor exposure drives the extrinsic pathway (VII → X), the primary initiator in surgical bleeding, while contact activation drives the intrinsic pathway (XII → XI → IX → VIII → X). Both feed the common pathway (X → V → thrombin → fibrinogen → fibrin clot), and the clot is later dismantled by fibrinolysis (plasminogen → plasmin → fibrin degradation), the step TXA blocks.
The response to blood loss. Blood loss is graded by the volume lost and what it does to the circulation.
- Hemodynamic Changes
- Minimal
- Symptoms
- None - compensated
- Hemodynamic Changes
- Tachycardia, narrow pulse pressure
- Symptoms
- Anxiety, delayed capillary refill
- Hemodynamic Changes
- Tachycardia, hypotension, tachypnea
- Symptoms
- Confusion, decreased urine output
- Hemodynamic Changes
- Severe hypotension, absent pulses
- Symptoms
- Lethargy, anuria, impending death
Oxygen Delivery Physiology
The equation. DO₂ = CO × CaO₂ = CO × (1.34 × Hb × SaO₂ + 0.003 × PaO₂). Haemoglobin is the primary oxygen carrier, at 1.34 mL O₂/g Hb.
The reserve. Normal DO₂ is 900-1100 mL/min against a VO₂ of 200-250 mL/min, and below a critical DO₂ of about 300 mL/min anaerobic metabolism ensues. The compensatory mechanisms are an increased cardiac output and a rising oxygen extraction ratio, which is why young healthy patients tolerate an Hb of 70 g/L and elderly or cardiac patients tolerate it less well.
Impact of Anaemia on Surgical Outcomes
What anaemia costs. Preoperative anaemia carries an increased 30-day mortality (OR 1.4-2.9 depending on severity), more postoperative complications (infections, AKI, cardiac events), and longer length of stay and readmission rates. It also triggers transfusion, which compounds the risks.
Perioperative coagulopathy. Hypothermia impairs enzyme function in the coagulation cascade, acidosis reduces clotting factor activity (at pH 7.2, 50% of activity), crystalloid and colloid resuscitation dilutes what is left, and massive haemorrhage consumes it. Hypothermia, acidosis and coagulopathy together are the lethal triad, and it carries a high mortality.
Differential Diagnosis
When a surgical patient is anaemic preoperatively or bleeding unexpectedly, the cause must be characterised before it can be treated. The two key differentials are the type of anaemia (which directs optimisation) and the cause of intraoperative coagulopathy (which directs product choice).
- Clue (indices/labs)
- Low ferritin, low transferrin saturation
- Typical Causes
- Iron deficiency, thalassaemia trait
- Key Action
- Treat iron deficiency; check ferritin to exclude thalassaemia
- Clue (indices/labs)
- Normal/high ferritin, raised CRP
- Typical Causes
- Anaemia of chronic disease/inflammation, renal impairment, acute blood loss
- Key Action
- Treat underlying disease; consider IV iron plus ESA if renal
- Clue (indices/labs)
- Low B12/folate, abnormal LFTs
- Typical Causes
- B12/folate deficiency, alcohol, hypothyroidism, myelodysplasia
- Key Action
- Replace B12/folate; investigate marrow if unexplained
- Clue (indices/labs)
- Raised LDH/bilirubin, low haptoglobin, positive DAT
- Typical Causes
- Autoimmune, hereditary spherocytosis, drug-induced
- Key Action
- Haematology referral; caution with transfusion crossmatch
- Distinguishing Feature
- Discrete bleeding point; normal coagulation
- Targeted Treatment
- Direct haemostasis - the primary remedy
- Distinguishing Feature
- Diffuse ooze after large-volume resuscitation
- Targeted Treatment
- Balanced FFP/platelets (1:1:1), limit crystalloid
- Distinguishing Feature
- Clot lysis on viscoelastic testing (ROTEM/TEG)
- Targeted Treatment
- Tranexamic acid
- Distinguishing Feature
- Fibrinogen less than 1.5 g/L
- Targeted Treatment
- Cryoprecipitate or fibrinogen concentrate
- Distinguishing Feature
- Drug history; raised INR/aPTT/anti-Xa
- Targeted Treatment
- Reverse: PCC/vitamin K (warfarin), specific agents for DOACs
- Distinguishing Feature
- Core temp less than 35C, pH less than 7.2 with ooze
- Targeted Treatment
- Active warming, correct acidosis, restore perfusion
Pillar 1: Preoperative Optimisation
Preoperative Anaemia Screening
The definition. The WHO calls it anaemia below 130 g/L in men, below 120 g/L in women and below 110 g/L in pregnancy.
International PBM guidelines (WHO-endorsed, and bodies such as the NHMRC/NBA, NICE and AABB) recommend screening haemoglobin and ferritin for ALL patients undergoing elective surgery with expected moderate-high blood loss (greater than 500 mL). This includes most major orthopaedic procedures.
- Interpretation
- Anaemia present
- Action
- Investigate cause, treat 4-6 weeks preop
- Interpretation
- Iron deficiency anaemia
- Action
- Oral iron 200 mg elemental iron daily
- Interpretation
- Functional iron deficiency
- Action
- Consider IV iron if time limited
- Interpretation
- Microcytic anaemia
- Action
- Iron deficiency vs thalassaemia - check ferritin
- Interpretation
- Macrocytic anaemia
- Action
- B12/folate deficiency - supplement
Which kind of iron deficiency. Order ferritin, transferrin saturation and CRP together. Ferritin alone is unreliable, because it is an acute-phase reactant and rises with any inflammation: a normal ferritin in an inflamed patient does not exclude iron deficiency.
- Absolute iron deficiency - a low ferritin. Iron stores are genuinely empty
- Functional iron deficiency, or anaemia of inflammation - a normal or high ferritin with a low transferrin saturation and a raised CRP. Stores exist, but hepcidin traps iron in the reticuloendothelial system and it cannot reach the marrow
Where the anaemia comes from. The commonest causes in elective orthopaedic patients are iron deficiency (chronic blood loss, poor intake), anaemia of chronic disease (inflammatory arthritis), and renal impairment (hip osteoarthritis patients are often elderly with CKD). Check FBC, ferritin, CRP and creatinine as a minimum.
Managing the patient's own antiplatelets and anticoagulants is the complementary half of blood management: stopping nothing risks bleeding, and stopping the wrong agent risks fatal thrombosis.
Aspirin. The bleeding-risk increase is modest for most major surgery and it is increasingly continued, especially for secondary cardiovascular prevention. Individualise - it is often continued through hip fracture surgery and arthroplasty.
P2Y12 inhibitors. Stop clopidogrel and ticagrelor about 5 days, and prasugrel about 7 days, before elective surgery. The overriding rule is the coronary stent: do NOT interrupt dual antiplatelet therapy within the mandatory window - defer elective surgery (bare-metal stent at least about 6 weeks, drug-eluting stent ideally about 6 months) and discuss with cardiology, because premature DAPT cessation causes catastrophic stent thrombosis.
Warfarin. Stop about 5 days pre-op and check the INR, targeting under about 1.5 for major surgery. Bridge with therapeutic LMWH only for high thrombotic risk - a mechanical mitral valve, VTE within 3 months, or atrial fibrillation with prior stroke - because routine bridging increases bleeding without benefit (BRIDGE trial). Urgent reversal is vitamin K plus four-factor PCC.
DOACs. Stop apixaban, rivaroxaban or dabigatran by drug, bleeding risk and renal function - typically 24-48 hours for high-bleeding-risk surgery, longer for dabigatran with renal impairment, with no routine bridging. Reversal is idarucizumab for dabigatran and andexanet alfa for factor Xa inhibitors, with PCC as an alternative.
Restart antithrombotics once haemostasis is secure, balancing rebleed against thrombosis. Exam point: never stop dual antiplatelet therapy within the post-stent window, bridge warfarin only for high thrombotic risk, and base DOAC stop-timing on renal function.
Pillar 2: Minimise Intraoperative Blood Loss
Tranexamic Acid (TXA) - Evidence and Protocols
TXA is a lysine analogue that competitively inhibits plasminogen activation, preventing fibrinolysis. It stabilises formed clot by blocking plasmin from degrading fibrin. The effect lasts 3-4 hours. It does NOT increase clot formation (it is not pro-thrombotic), it prevents clot breakdown.
Where it is used. Give TXA in every major orthopaedic case unless contraindicated: primary THA and TKA, revision arthroplasty where blood loss is higher and TXA is highly effective, multi-level fusion and deformity correction in spine surgery, hip fracture, and trauma. It also reduces transfusion in cardiac surgery, in CABG and valve replacement.
- Loading Dose
- 15-20 mg/kg IV
- Maintenance
- Optional 1-2 mg/kg/h infusion
- Timing
- At induction before tourniquet
- Loading Dose
- 20 mg/kg IV
- Maintenance
- 2 mg/kg/h for 3-6 hours
- Timing
- At induction, continue postop
- Loading Dose
- 10-15 mg/kg IV
- Maintenance
- 1 mg/kg/h for duration
- Timing
- At incision, throughout case
- Loading Dose
- 1 g IV bolus
- Maintenance
- 1 g IV over 8 hours
- Timing
- Within 3 hours of injury (critical)
- Loading Dose
- 1-3 g in 50-100 mL saline
- Maintenance
- Leave in joint 5 min before closure
- Timing
- At closure before drain placement
The CRASH-2 trial (20,211 trauma patients) showed TXA within 3 hours of injury reduced all-cause mortality from 16% to 14.5% (NNT=67). Given between 3-8 hours, NO benefit. After 8 hours, HARM (increased mortality). Time is critical in trauma.
Contraindications. Four, and each is a reason to withhold rather than to reduce the dose, apart from the last.
- Active thromboembolic disease (DVT, PE, MI or stroke less than 3 months ago)
- A history of seizures - TXA crosses the blood-brain barrier, with a rare seizure risk at high doses
- Known allergy to TXA
- Renal impairment - reduce the dose if CrCl is less than 30, because the drug accumulates
Multiple meta-analyses (over 100 RCTs) show TXA does NOT increase VTE, MI, or stroke rates in orthopaedic surgery. The theoretical thrombosis risk is not seen in practice.
Pillar 3: Appropriate Transfusion Management
Restrictive vs Liberal Transfusion Thresholds
The TRICC trial (1999) and multiple subsequent trials showed restrictive transfusion (Hb less than 70 g/L) is as safe as liberal (Hb less than 100 g/L) and reduces transfusion-related complications. This changed practice worldwide. Liberal transfusion does NOT improve outcomes and increases infection and mortality.
- Transfusion Threshold
- Hb less than 70 g/L
- Evidence
- TRICC, FOCUS trials - safe, reduces transfusion
- Transfusion Threshold
- Hb less than 80 g/L
- Evidence
- Subset analysis suggests higher threshold safer
- Transfusion Threshold
- Hb less than 80 g/L or symptoms
- Evidence
- MINT trial - restrictive non-inferior
- Transfusion Threshold
- Symptoms (dyspnoea, tachycardia, angina)
- Evidence
- Transfuse for symptoms regardless of Hb
- Transfusion Threshold
- Transfuse to maintain Hb greater than 70-80 g/L
- Evidence
- Replace ongoing losses
Reading the table against the trials. TRICC tested 70 against 100 g/L in critically ill patients. FOCUS, the largest transfusion trial in orthopaedics, tested a threshold of 80 g/L or symptoms in elderly hip-fracture patients with cardiovascular disease or risk factors, and found no difference in death or independent walking at 60 days. So 70 g/L is the general trigger, and the 80 g/L figure is the one tested in patients whose hearts were already at risk.
Transfusion triggers are GUIDELINES, not absolutes. Symptoms of anaemia (dyspnoea, tachycardia, chest pain, confusion) are an indication for transfusion regardless of Hb. A patient with Hb 75 g/L who is asymptomatic does NOT need transfusion. A patient with Hb 85 g/L with angina DOES need transfusion.
The symptoms that count. These are the findings that argue for transfusion whatever the haemoglobin is.
- Tachycardia (HR greater than 100 at rest) not explained by pain or anxiety
- Dyspnoea or increased work of breathing
- Chest pain or ECG changes of ischaemia
- Postural hypotension or dizziness
- Confusion or altered mental state
- Oliguria (less than 0.5 mL/kg/h)
Jehovah's Witness Patient Management
Ask, do not assume. Jehovah's Witness patients refuse allogeneic blood transfusion on religious grounds, but acceptance of the other strategies varies from patient to patient. Discuss and document individual preferences preoperatively, including the acceptable minimum Hb; do NOT assume that all patients refuse all products.
Usually acceptable
- Erythropoietin preoperatively and iron, oral or intravenous
- Tranexamic acid
- Cell salvage, if the circuit is continuous
- Crystalloid and colloid, with albumin often accepted
- Hypotensive anaesthesia
- Accepting a lower Hb of 60-70 g/L postoperatively
Usually refused
- Allogeneic RBC transfusion, fresh frozen plasma, platelets, cryoprecipitate and whole blood
- Cell salvage, in some patients, if the circuit is not continuous
- Albumin or factor concentrates, in some patients
The plan. A multi-modal strategy, running from weeks before the operation to the days after it.
Preoperative optimisation - screen Hb, start EPO 40,000 units weekly x 4 + IV iron 1000 mg. Goal: Hb greater than 130 g/L preop.
Document preferences - which products are acceptable (cell salvage, EPO, TXA, albumin?). Document in the chart and the consent form.
Minimise blood loss - meticulous haemostasis, TXA (20 mg/kg load + infusion), cell salvage, hypotensive anaesthesia, consider staged procedures if bilateral.
Tolerate the anaemia - continue EPO postop if needed, supplemental oxygen, mobilise early, recheck Hb daily.
Obtain informed consent documenting that the patient refuses transfusion even if the situation is life-threatening. Have the patient sign a specific Jehovah's Witness refusal form. Document the discussion of risks, including death, if severe blood loss occurs. Consider having a witness to the consent. Respect patient autonomy.
If a Jehovah's Witness patient presents for a high blood loss procedure (revision THA, spine tumour resection) with a preoperative Hb less than 100 g/L and refuses transfusion, consider: (1) delaying surgery to optimise with EPO and iron, if elective, (2) a frank discussion of mortality risk, (3) declining surgery if the risk is unacceptable. Document the decision-making thoroughly.
Guidelines, Registries and Global Practice
Across the major guideline bodies the message is remarkably consistent: screen and treat preoperative anaemia, give tranexamic acid, use cell salvage for high-loss cases, and transfuse restrictively (single-unit, Hb-triggered). Patient Blood Management (PBM) is endorsed by the WHO as a global standard of care. The principal differences between countries lie in funding/reimbursement of IV iron and erythropoiesis-stimulating agents, not in the core clinical recommendations.
Global Epidemiology
- Present in approximately 30% of major non-cardiac surgical patients worldwide (227,425-patient NSQIP cohort)
- Independently raises 30-day mortality (adjusted OR 1.42) and morbidity (OR 1.35)
- In elective hip and knee arthroplasty, reported prevalence ranges roughly 15-40%, driven by iron deficiency and anaemia of inflammation
- Anaemia is the strongest modifiable predictor of perioperative allogeneic transfusion
- Allogeneic red cells are a finite, donor-dependent resource with periodic shortages in most health systems
- O-negative (universal donor) is chronically scarce - only about 7-9% of most populations
- PBM programmes reduce red-cell utilisation by 20-40% without harm
- Low- and middle-income countries face the greatest supply constraints, magnifying the value of TXA and cell salvage
Side-by-Side Guideline Comparison
- Anaemia / Iron
- Endorses PBM; treat anaemia preop
- Tranexamic Acid
- Supports antifibrinolytics
- Transfusion Threshold
- Restrictive, evidence-based triggers
- Anaemia / Iron
- Screen and treat all elective major surgery
- Tranexamic Acid
- Recommended (cell salvage too)
- Transfusion Threshold
- Restrictive; transfuse for Hb less than 70 g/L or symptoms
- Anaemia / Iron
- Offer iron before/after surgery if iron-deficient
- Tranexamic Acid
- Offer TXA for expected major blood loss
- Transfusion Threshold
- Threshold Hb 70 g/L (80 g/L if ACS); single-unit
- Anaemia / Iron
- PBM and anaemia management endorsed
- Tranexamic Acid
- Supported in surgery
- Transfusion Threshold
- Restrictive 70 g/L (75 g/L cardiac surgery)
- Anaemia / Iron
- Detect and treat iron-deficiency anaemia
- Tranexamic Acid
- Strongly recommended
- Transfusion Threshold
- Restrictive; individualise in cardiac disease
- Anaemia / Iron
- Preop optimisation pathway for arthroplasty
- Tranexamic Acid
- Routine in THA/TKA unless contraindicated
- Transfusion Threshold
- Restrictive, symptom-guided
The recommendations for TXA (Level I, multiple meta-analyses and CRASH-2) and restrictive transfusion (Level I, TRICC/FOCUS and the Cochrane transfusion-threshold review) are among the most robust in perioperative medicine. Preoperative anaemia treatment rests largely on high-quality observational data (Musallam) plus RCTs of IV iron with more variable transfusion-outcome effects, hence guideline wording is often "offer/consider" rather than "must".
Registry and Programme-Level Evidence
- National and statewide PBM programmes have reported large reductions in red-cell, plasma and platelet use alongside reduced length of stay and in-hospital mortality - the strongest real-world endorsement of PBM.
- Arthroplasty registries (AOANJRR, NJR, AJRR) do not collect transfusion as a core variable but track the revision and infection outcomes that transfusion-associated immunomodulation can influence, reinforcing the rationale for blood conservation.
Practice Variation
- IV iron and ESA funding differ markedly: many systems restrict erythropoiesis-stimulating agents to chronic kidney disease and chemotherapy, leaving elective-surgery use hospital- or patient-funded.
- Topical versus intravenous TXA preference varies by unit; both are effective, with combined regimens used in some high-loss cases.
- Cell salvage availability is resource-dependent and concentrated in higher-volume centres.
Most national blood services rely on voluntary, non-remunerated donors and issue periodic shortage alerts. This finite supply - not just patient outcomes - is a core driver of Patient Blood Management: conserve product, transfuse appropriately, and minimise waste.
MCQ Practice Points
Q: What is the evidence-based transfusion threshold for hemodynamically stable patients following major orthopaedic surgery?
A: Hb 70 g/L (7 g/dL) for most patients. The FOCUS, TRACS, and TRICC trials demonstrated no benefit of liberal (100 g/L) over restrictive (70-80 g/L) transfusion thresholds. Exceptions requiring higher thresholds (80-100 g/L): acute coronary syndrome, symptomatic anaemia, ongoing significant bleeding. Single unit transfusion is appropriate unless ongoing hemorrhage.
Q: What dose of tranexamic acid (TXA) is recommended for total joint arthroplasty and what is its mechanism?
A: 1-2g IV given preoperatively (10-15mg/kg), with optional repeat dose at wound closure. TXA is an antifibrinolytic that competitively inhibits plasminogen activation, preventing clot breakdown. Reduces blood loss by 30-50% and transfusion risk by 50%. Contraindicated in active thromboembolic disease. NOT contraindicated in patients with DVT/PE history with adequate thromboprophylaxis.
Q: What are the key elements of a Patient Blood Management (PBM) program in orthopaedic surgery?
A: Three pillars: (1) Optimize red cell mass preoperatively - treat iron deficiency (IV iron if Hb under 130), EPO in selected cases. (2) Minimize blood loss - surgical technique, TXA, controlled hypotension, cell salvage. (3) Optimize physiological tolerance - restrictive transfusion thresholds, multimodal analgesia, early mobilization. Major bodies including the WHO and the National Blood Authority publish specific PBM guidelines for surgery.
Q: When is intraoperative cell salvage indicated in orthopaedic surgery?
A: Expected blood loss greater than 1000-1500mL (or anticipated need for greater than 2 units allogeneic blood). Common indications: revision arthroplasty, major spine surgery, pelvic/acetabular trauma, bilateral TKA. Cell salvage reinfuses the patient's own washed red cells. Contraindicated in malignancy (relative) and infection (absolute). Processing removes activated clotting factors.
Q: What is the recommended management of anticoagulation in a patient on warfarin requiring urgent hip fracture surgery?
A: Reverse with IV Vitamin K 5-10mg + Prothrombin Complex Concentrate (PCC, 25-50 IU/kg) for INR greater than 1.5. Surgery can proceed once INR under 1.5. Fresh frozen plasma (FFP) is second-line if PCC unavailable. Do NOT delay surgery more than 48 hours waiting for INR to normalize with vitamin K alone. Bridging with LMWH is NOT recommended for most hip fracture patients.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 72-year-old woman is listed for elective TKA in 6 weeks. Preoperative Hb is 105 g/L, ferritin 18 mcg/L, CrCl 55 mL/min. How would you manage her preoperatively?”
“You are performing revision THA for aseptic loosening. During acetabular component removal, the patient develops massive hemorrhage from pelvic vessels. BP drops to 70/40, HR 130. Anesthetist estimates 2L blood loss in 10 minutes. How do you manage this?”
“A 68-year-old Jehovah's Witness patient presents for bilateral TKA. Preoperative Hb is 118 g/L. She refuses all blood products. How would you counsel and manage this patient?”
Three Pillars of Patient Blood Management
- Pillar 1 - OPTIMIZE: detect and treat preoperative anaemia with iron and EPO
- Pillar 2 - MINIMIZE: reduce intraoperative blood loss with TXA, cell salvage and technique
- Pillar 3 - MANAGE: transfuse appropriately, using a restrictive threshold of Hb less than 70 g/L
Preoperative Anemia Management
- Screen: Hb less than 130 g/L in men or less than 120 g/L in women defines anaemia - check ferritin, CRP and creatinine
- Oral iron: 200 mg elemental iron daily for 4-6 weeks, raising Hb by 10-20 g/L
- IV iron: ferric carboxymaltose 1000 mg as a single dose, raising Hb 10-30 g/L within 1-2 weeks - use when time is limited
- EPO: 40,000 units subcutaneously weekly for 3-4 weeks with iron, raising Hb 20-40 g/L - for chronic kidney disease, severe anaemia, or a Jehovah's Witness patient
- Recheck the Hb one week preoperatively to confirm the response
Tranexamic Acid (TXA)
- Mechanism: inhibits plasminogen activation, preventing fibrinolysis and stabilising the clot
- Dosing: 15-20 mg/kg IV loading dose at induction, with optional 1-2 mg/kg/h maintenance
- Evidence: a 30-50% reduction in transfusion, with NO increase in VTE, myocardial infarction or stroke
- CRASH-2 regimen: 1 g bolus plus 1 g over 8 hours in trauma - reduces mortality if given within 3 hours
- Use: all major orthopaedic cases (THA, TKA, spine, trauma) unless contraindicated
Cell Salvage
- Indications: expected blood loss greater than 500-1000 mL (revision THA or TKA, spine, pelvis)
- Mechanism: collects shed blood, washes the red cells, and reinfuses autologous blood at a haematocrit of 50-60%
- Contraindications, the MIB triad: Malignancy, Infection, Bowel contamination - all absolute
- Effect: a 30-40% reduction in allogeneic transfusion
- Jehovah's Witness patients: many accept cell salvage if a continuous circuit is used
Transfusion Thresholds
- Restrictive: transfuse below Hb 70 g/L in asymptomatic stable patients - SAFE, and it reduces complications
- Liberal: transfusing below Hb 100 g/L was the old practice - NO benefit, and it increases complications
- Cardiovascular disease: use a slightly higher threshold of Hb less than 80 g/L
- Symptomatic anaemia: transfuse for symptoms such as dyspnoea, tachycardia or angina regardless of the Hb
- Evidence: the TRICC and FOCUS trials showed restrictive transfusion is as safe as liberal, with fewer transfusions
Massive Transfusion Protocol
- Definition: loss of one blood volume in 24 hours, OR more than 4 units in 1 hour
- The 1:1:1 ratio: red cells, fresh frozen plasma and platelets in equal amounts, preventing dilutional coagulopathy
- TXA: 1 g IV bolus then 1 g over 8 hours (the CRASH-2 protocol, within 3 hours of injury)
- The lethal triad: hypothermia, acidosis and coagulopathy - monitor and correct all three
- Laboratory monitoring: Hb, INR, fibrinogen and platelets every 30-60 minutes
Jehovah's Witness Management
- Discuss: individual beliefs vary - many patients accept EPO, TXA and cell salvage on a continuous circuit
- Document: a signed refusal form, the documented risks including death, and a witness to the consent
- Optimize: EPO 40,000 units weekly for 4 weeks plus IV iron 1000 mg, aiming for a preoperative Hb above 130 g/L
- Minimize: TXA, cell salvage, meticulous haemostasis, hypotensive anaesthesia, and consider staging bilateral procedures
- Accept: a lower postoperative Hb of 60-70 g/L, with supplemental oxygen and early mobilisation
Key Trials and Evidence
- CRASH-2 (2010): TXA in trauma reduced mortality from 16.0% to 14.5% when given within 3 hours; given after 8 hours it was harmful
- TRICC (1999): restrictive (Hb less than 70) versus liberal (less than 100) - restrictive was safe and reduced transfusions
- FOCUS (2011): in hip fracture patients, a restrictive threshold (Hb less than 80) was safe even in the elderly with comorbidities
- Cochrane TXA review (2015): 60 orthopaedic randomised trials - TXA reduced transfusion by 30-50% with NO increase in VTE
- NBA/NHMRC PBM Guidelines (2012): a foundational, evidence-graded standard - optimize, minimize, and manage transfusion appropriately
Key Evidence and Trials
CRASH-2 Trial (2010)
- All-cause mortality 16.0% to 14.5% (RR 0.91, p=0.0035)
- Greatest benefit when given within 3 hours of injury
- No excess myocardial infarction, stroke or thromboembolism
- Dosing: 1 g bolus then 1 g over 8 hours
TRICC Trial (1999)
- Restrictive threshold 70 g/L vs liberal 100 g/L
- 30-day mortality 18.7% vs 23.3% (not significant)
- Restrictive at least as effective and possibly superior
- Possible exception: acute MI / unstable angina
FOCUS Trial (2011)
- Largest transfusion RCT in orthopaedic (hip-fracture) patients
- Restrictive threshold approx 80 g/L (or symptoms)
- No difference in death or independent walking at 60 days
- Restrictive strategy safe even in high cardiovascular-risk elderly
Preoperative Anaemia and Surgical Outcomes (2011)
- Preoperative anaemia present in ~30% of surgical patients
- 30-day mortality OR 1.42 (1.31-1.54) after adjustment
- Even mild anaemia is independently harmful
- Justifies routine preoperative anaemia screening
IV TXA Safety in Major Orthopaedic Surgery (2018)
- 73 RCTs in major orthopaedic surgery
- VTE 2.1% (TXA) vs 2.0% (control) - not significant (RR 1.067)
- Confirms TXA reduces blood loss and transfusion safely
- Supports routine intravenous TXA in arthroplasty
National Blood Authority Patient Blood Management Guidelines (Module 2: Perioperative)
- Three pillars: optimise red-cell mass, minimise blood loss, manage anaemia/tolerance
- Routine preoperative anaemia screening and treatment
- TXA and cell salvage recommended
- Restrictive transfusion thresholds endorsed