Osteochondromas Throughout the Skeleton
- EXT1/EXT2: Tumour-suppressor genes.
- Malignant Transformation: 0.5-5% to secondary peripheral chondrosarcoma - but do not quote one flat figure, since EXT1 carriers are at substantially higher risk than EXT2.
- Warning Signs: New growth, pain, cartilage cap greater than 2cm in adults.
- Forearm Deformity: Common (ulnar shortening).
- Excision: For symptomatic lesions.
- “EXT1/EXT2 mutations
- “0.5-5% malignant transformation, higher with EXT1
- “Pain/growth in adults = concerning
- “Forearm deformity common
Overview and Epidemiology
Multiple hereditary exostoses (MHE) is characterised by multiple osteochondromas. It is inherited as an autosomal dominant condition and is caused by mutation of EXT1 or EXT2, which are tumour-suppressor genes. The incidence is 1 in 50,000.
Genotype and severity. EXT1 mutations (chromosome 8) typically cause a more severe phenotype than EXT2 mutations (chromosome 11). The genotype also bears on malignant risk, which is set out under Outcomes.
Natural history. The lesions grow until skeletal maturity and then stop. The risk of malignancy does not stop with them; it persists lifelong.
Pathophysiology and Mechanisms
The lesion. An osteochondroma is a cartilage-capped bony outgrowth arising from the metaphysis, with its cortex and medulla continuous with those of the host bone. It grows away from the adjacent joint, which is important for diagnosis. In an adult the cartilage cap is normally less than 1 cm thick.
Where lesions arise. The common sites are:
- Distal femur, the most common
- Proximal tibia
- Proximal humerus
- Distal ulna and radius, where lesions cause forearm deformity
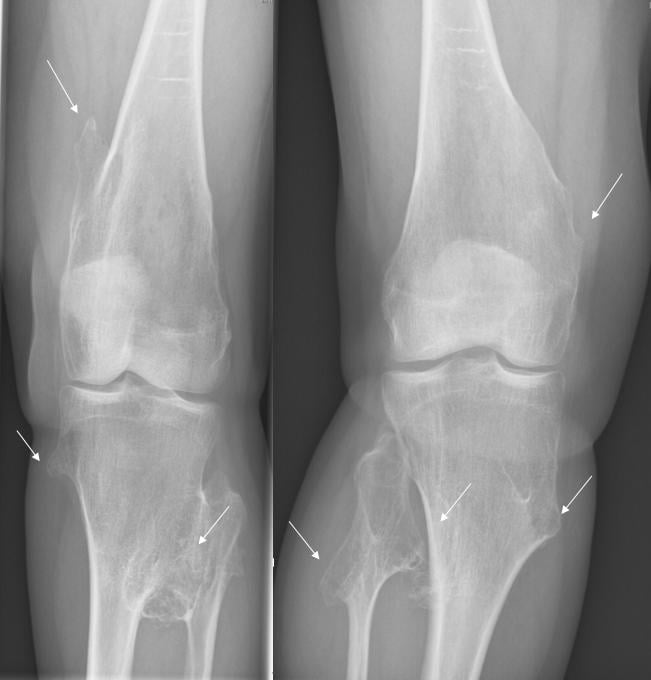
Why deformity occurs. An osteochondroma tethers the growth plate beside it. At the distal ulna this shortens the ulna, and ulnar shortening leads to bowing of the radius. Fibular lesions work the same way at the ankle and produce ankle valgus.
Molecular Mechanism: EXT → Heparan Sulphate → Hedgehog Signalling
From gene to signalling. EXT1 and EXT2 form a complex of glycosyltransferases that synthesise and elongate heparan-sulphate (HS) chains on heparan-sulphate proteoglycans. HS proteoglycans act as a scaffold that shapes the gradient and signalling of growth-plate morphogens, most importantly Indian Hedgehog (Ihh), and also FGFs, BMPs and Wnts. In the normal physis the Ihh/PTHrP negative-feedback loop sets the pace of chondrocyte proliferation and keeps proliferating chondrocytes in orderly longitudinal columns.
From signalling to osteochondroma. Loss of EXT function leads to abnormal cartilage growth at the physes. Defective HS disrupts Ihh signalling, so chondrocytes at the periphery of the growth plate lose their normal polarity and proliferate laterally, escaping the perichondrial groove of Ranvier to form a cartilage-capped outgrowth. The osteochondroma then grows by endochondral ossification from its own cartilage cap and, because it is driven by the physis, ceases at physeal closure.
The second hit. Because EXT1 and EXT2 are tumour suppressors, osteochondromas behave as clonal lesions arising after a somatic "second hit", the loss of the remaining wild-type EXT allele in a cartilage-cap cell. Progression to secondary peripheral chondrosarcoma involves further genetic change in that clone, and this is the molecular basis of the lifelong transformation risk.
Classification Systems
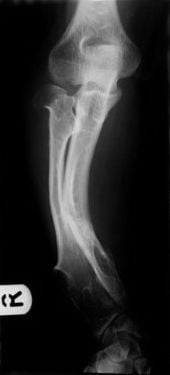
Two classifications are in use: Masada's for the forearm deformity, and a severity grading for the disease as a whole.
- Type I - ulnar shortening with bowing of the radius, secondary to a distal ulnar osteochondroma (most common)
- Type IIA - dislocation of the radial head with an osteochondroma of the proximal radius
- Type IIB - dislocation of the radial head secondary to more distal involvement, with no proximal radial lesion
- Type III - relative radial shortening due to osteochondromas at the distal radius
Clinical Assessment
History. Ask the age at which the first lesion appeared, and take a family history. Establish which lesions are symptomatic, whether through pain, cosmesis or nerve compression. Any new pain or growth in an adult raises concern for malignancy.
Examination. Look at the lesions and at what they are doing to the limb:
- Palpable masses, typically at the metaphyses
- Deformity: the forearm (short ulna) and the ankle (valgus)
- Range of motion, limited by impingement
- Neurovascular status, for example the peroneal nerve at the knee
Investigations
Radiographs show the multiple osteochondromas, which are broad-based or pedunculated. MRI is for the lesion in which malignancy is suspected, on the warning signs below. EXT1/EXT2 genetic testing is for the patient in whom the diagnosis is uncertain.
The warning signs of malignant transformation to chondrosarcoma are:
- New pain in a previously painless lesion
- Growth after skeletal maturity
- A cartilage cap greater than 2cm on imaging
- Irregular margins or scattered calcifications
Obtain an MRI. If it is concerning, biopsy or excise with wide margins.
PGSMalignant Warning Signs
Hook:PGS - Pain, Growth, Size.
Differential Diagnosis
Multiple Cartilaginous Lesions:
- Key Features
- Multiple osteochondromas
- Differentiator
- Continuous cortex, metaphyses, EXT mutation
- Key Features
- Multiple enchondromas
- Differentiator
- Medullary lesions, not cortical
- Key Features
- Enchondromas + hemangiomas
- Differentiator
- Soft tissue vascular lesions
- Key Features
- Osteochondromas + enchondromas
- Differentiator
- Both lesion types present
- Key Features
- Epiphyseal osteochondroma
- Differentiator
- Single limb, epiphysis involved
Key Distinguishing Points:
- MHE: Metaphyseal, cortex continuous with host bone.
- Enchondromas (Ollier): Medullary, radiolucent with stippled calcifications.
- DEH (Trevor Disease): Single limb, epiphyseal involvement.
- Malignancy risk: MHE 0.5-5% (higher in EXT1), Ollier 25-30%, Maffucci 25-30%.
Management Algorithm
Observation. Asymptomatic lesions are watched, with regular clinical follow-up and education about the warning signs of malignancy.
Excision. Symptomatic lesions are excised, for pain, nerve compression, impingement or cosmesis. A lesion suspected of malignancy needs wide en-bloc excision instead.
Forearm deformity. Ulnar shortening causes radial bowing, and the radial head may dislocate. Surgery is indicated for progressive deformity, limited forearm rotation or radial head instability, and combines osteochondroma excision, ulnar lengthening and radial osteotomy.
Timing. Early intervention is intended to prevent radial head dislocation. Whether it does, compared with observation until the deformity declares itself, remains debated (see Controversies).
Surgical Techniques
Osteochondroma excision. Excise the lesion marginally at its base and include the entire cartilage cap, because incomplete excision of the cap leads to recurrence. Take care of the adjacent neurovascular structures.
Forearm deformity correction. The procedures are:
- Osteochondroma excision at the distal ulna or radius
- Ulnar lengthening, gradual or acute
- Radial osteotomy for bowing
- Radial head reduction if dislocated
Chondrosarcoma excision. For confirmed or suspected malignant transformation, excise with wide margins, with limb salvage if possible and with oncology involvement. Chondrosarcoma is resistant to chemotherapy and radiation.
Lower-Limb Deformity & Guided Growth
The deformities. Beyond the forearm, MHE causes major lower-limb deformities, and these are high-yield. They arise from osteochondromas tethering or asymmetrically loading the peri-articular physes:
- Genu valgum, from peri-knee osteochondromas (and relative fibular overgrowth or tethering); one of the commonest MHE angular deformities
- Ankle valgus, the classic MHE ankle deformity, from relative distal fibular shortening (distal fibular or tibial lesions) producing lateral talar tilt
- Leg-length discrepancy and disproportionate (mesomelic) short stature, from physeal involvement
- Coxa valga and acetabular dysplasia at the hip
Guided growth first. While the physes remain open, guided growth (hemiepiphysiodesis with tension-band "8-plates") is the least-invasive first line for angular deformity. The plates go at the medial distal femur and/or proximal tibia for genu valgum, and at the medial distal tibia for ankle valgus.
When guided growth is not enough. Corrective osteotomy is for the deformity with insufficient growth remaining, or one that is severe or rigid; fibular lengthening is for marked ankle valgus. Leg-length discrepancy is managed as for other causes, by epiphysiodesis of the long limb or by lengthening.
What is specific to MHE. Guided growth, genu valgum correction and leg-length management follow standard principles. The difference is that a lesion tethering a physis may need excising before the deformity will respond to them.
Complications
- Context
- Lifelong risk, higher in EXT1
- Management
- Surveillance, wide en-bloc excision
- Context
- Incomplete excision
- Management
- Complete cartilage cap removal
- Context
- Peroneal at knee
- Management
- Careful dissection
- Context
- Childhood growth
- Management
- Early intervention
- Context
- Popliteal region
- Management
- Pre-op imaging
Postoperative Care
Aftercare depends on the operation:
- Simple excision - early mobilisation and wound care
- Forearm reconstruction - splinting and protected range of motion
- Lengthening - fixator care and daily adjustments
Whatever the operation, every patient continues surveillance of the other lesions.
Outcomes/Prognosis
Prognosis. Most lesions remain benign, although significant deformity may limit function. Malignant transformation occurs in 0.5 to 5%, the commonly cited range from the standard review (DOI), not 1 to 5%. That single number conceals the most useful thing known about this disease: the risk is not the same for every patient, and the genotype predicts it.
The genotype study. A prospective genotype-phenotype study of 172 individuals from 78 families, with mutations identified in 83% and each arm blinded to the other, found that EXT1 mutations carried significantly worse disease than EXT2 across stature, deformity and function (DOI, level II). Sarcomas clustered in the same group, 7 in EXT1 carriers against 1 in EXT2. The authors framed the EXT1 sarcoma risk as comparable to risks for which population screening programmes exist.
One figure is wrong in both directions. Give the pooled number to an EXT2 patient and you over-alarm someone whose personal risk sits at the bottom of the range. Give the same number to an EXT1 patient and you under-warn them, and may justify laxer surveillance than they need. That is why genotype belongs in the conversation.
What to do with it. Where genotyping has been done, let it shape surveillance intensity and the threshold for imaging a changing lesion. Where it has not, counsel with the range rather than a point estimate. Keep the clinical warning signs primary regardless of genotype, because a low-risk genotype never overrides a lesion that is behaving badly.
Guidelines, Registries & Global Practice
Global epidemiology
- Prevalence approximately 1 in 50,000 worldwide, with a male predominance (~1.5:1) and near-complete penetrance (~96%); roughly 10% of cases arise de novo without a family history.
- Mean number of osteochondromas per patient is 15-18; lesions appear and enlarge in the first decade and cease at physeal closure.
Consensus and society guidance (side by side)
- Position
- Confirm diagnosis clinically/radiologically; offer EXT1/EXT2 testing and genetic counselling; lifelong awareness of transformation; refer suspicious lesions to a bone-tumour centre
- Position
- Surveillance of accessible lesions; MRI for new pain or growth; biopsy/wide resection only for suspected malignancy
- Position
- Suspected secondary chondrosarcoma referred to a sarcoma MDT; en-bloc resection in a specialist centre
- Position
- Pediatric deformity correction in tertiary units; pooled registry/biobank data through European rare-disease networks
Registry and network evidence
- No dedicated arthroplasty-style registry exists; long-term data derive from population databases (e.g. Schmale's Washington kindreds), tertiary bone-tumour registries and rare-disease networks (Orphanet, EuroBoNeT/European sarcoma networks).
High- vs limited-resource practice
- Well-resourced settings: MRI surveillance, genetic testing, guided growth (8-plates), staged forearm reconstruction and limb salvage for transformation.
- Limited-resource settings: diagnosis is clinical/radiographic; emphasis on educating patients about warning signs (new pain, growth after maturity, enlarging cartilage cap) and timely referral when malignancy is suspected, since chondrosarcoma is chemo- and radio-resistant and depends on adequate surgical margins.
Controversies and Areas of Uncertainty
Routine surveillance imaging. There is no consensus on whether asymptomatic adults need scheduled whole-body MRI or screening. Some advocate baseline imaging of axial and proximal lesions (pelvis, shoulder) that are hard to monitor clinically; others rely on symptom-driven imaging and patient education. Porter's data suggest EXT1 carriers may justify more proactive screening.
Timing of forearm reconstruction. Whether early excision and ulnar lengthening prevent radial head dislocation, compared with observation until the deformity declares itself, remains debated. High-quality comparative evidence is limited.
The true malignant transformation rate. Quoted figures range from 0.5% to 5%. Older series likely overestimated the risk through referral bias, while genotype (EXT1) and lesion location modify individual risk.
Guided growth or osteotomy. The optimal first-line correction of knee and ankle valgus, hemiepiphysiodesis or corrective osteotomy, depends on remaining growth and deformity magnitude, without firm thresholds.
Medical therapy. Heparan-sulphate pathway and palovarotene-type signalling research is experimental; no disease-modifying drug is established in practice.
MCQ Practice Points
Q: What genes are mutated in MHE? A: EXT1 and EXT2.
Q: What is the malignant transformation rate? A: 0.5-5% to secondary peripheral chondrosarcoma - and add that the risk is not uniform: EXT1 carriers are at substantially higher risk than EXT2.
Q: What are warning signs for malignancy? A: Pain, growth after skeletal maturity, cartilage cap greater than 2cm.
Q: What causes forearm deformity in MHE? A: Distal ulnar osteochondroma causes ulnar shortening, leading to radial bowing and potential radial head dislocation.
Q: What is the Masada classification used for? A: Forearm deformity in MHE. Types I-III based on ulnar shortening, radial deformity, and radial head status.
Q: Which nerve is commonly compressed at the knee in MHE? A: Common peroneal nerve (fibular head osteochondroma).
Self-Assessment Quiz
Additional Quiz Questions
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“30-year-old with known MHE. One of his knee lesions has become painful and appears to have grown over the past year.”
“10-year-old with MHE has progressive forearm deformity with limited pronation/supination.”
“12-year-old with MHE presents with foot drop. X-ray shows large osteochondroma at proximal fibula. How do you manage?”
GENETICS
- EXT1/EXT2
- Autosomal Dominant
- Tumor suppressors
- 1 in 50,000
CLINICAL
- Multiple osteochondromas
- Metaphyses
- Forearm deformity
- Knee most common
MALIGNANCY
- 0.5-5% transformation (EXT1 higher)
- Pain in adults
- Growth after maturity
- Cap greater than 2cm
TREATMENT
- Observe if asymptomatic
- Excise if symptomatic
- Wide excision if malignant
- Correct deformity
FOREARM
- Ulnar shortening
- Radial bowing
- Masada classification
- Early intervention prevents RH dislocation
NERVES
- Peroneal at fibular head
- Sciatic at hip
- Foot drop = excision
- Pre-op imaging
Evidence Base
Bovée
- Prevalence ~1 in 50,000; male predominance (~1.5:1); mean 15-18 osteochondroma sites
- EXT1/EXT2 germline mutations found in ~90% of patients (heparan sulphate glycosyltransferases)
- Secondary peripheral chondrosarcoma estimated at 0.5-5%; resect en-bloc with tumour-free margins
Stieber & Dormans
- Characteristic deformities: short stature, limb-length discrepancy, knee/ankle valgus, radial bowing with ulnar wrist deviation, radiocapitellar subluxation
- EXT mutations disrupt chondrocyte proliferation and maturation
- Surgery can prevent progression and correct selected deformities; slight sarcomatous risk
Masada et al
- 36 forearms in 30 patients classified into 3 types (the Masada classification)
- Type I ulnar shortening + radial bowing; Type II radial head dislocation (IIa/IIb); Type III distal radial involvement
- 92% satisfactory results after type-directed surgery (excision, ulnar lengthening, radial osteotomy)
Schmale et al
- Population database: 46 kindreds, 113 affected; prevalence at least 1 in 50,000; penetrance 96%
- Median age at diagnosis 3 years; 39% had obvious forearm deformity, 8% knee, 2% ankle
- Average of two operations per surgically treated patient
Porter et al
- Prospective genotype-phenotype study of 172 individuals (78 families); mutation identified in 83%
- EXT1 carriers significantly worse than EXT2 in stature, deformity and function
- 7 sarcomas in EXT1 carriers vs 1 in EXT2; EXT1 sarcoma risk comparable to screened breast-cancer risk
Masciocchi et al
- T2-weighted MRI best depicts and differentiates the cartilage cap from adjacent soft tissue
- Cap thickness is essential to assessing malignant transformation; CT shows matrix calcification and bone destruction
- MRI is the most reliable technique for locoregional staging of malignant cartilage tumours