The Finger Drop
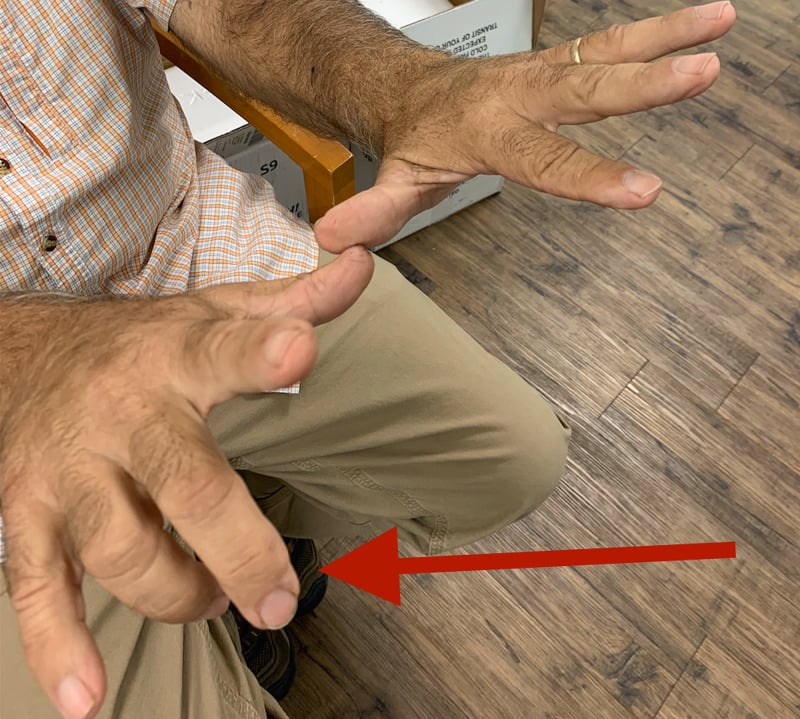
- PIN Syndrome presents as 'Finger Drop' but sparing of wrist extension (ECRL is intact).
- Wrist extends in radial deviation (Radio-Carpal extension via ECRL).
- No sensory loss (Superficial Radial Nerve branches off proximally).
- The most common compression site is the Arcade of Frohse (proximal edge of Supinator).
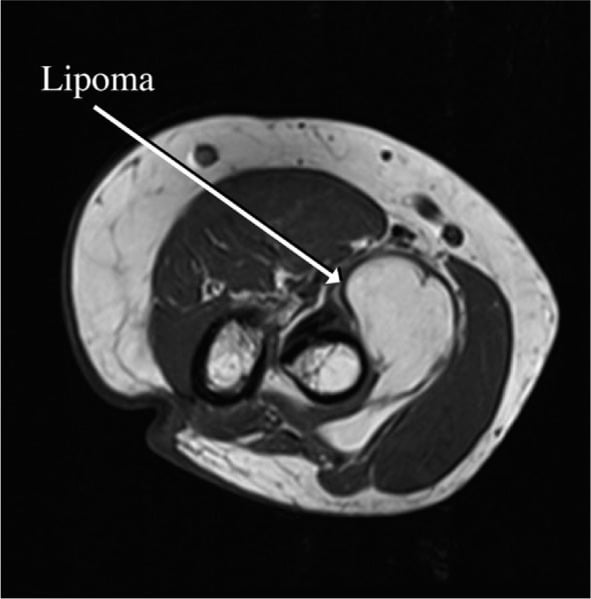
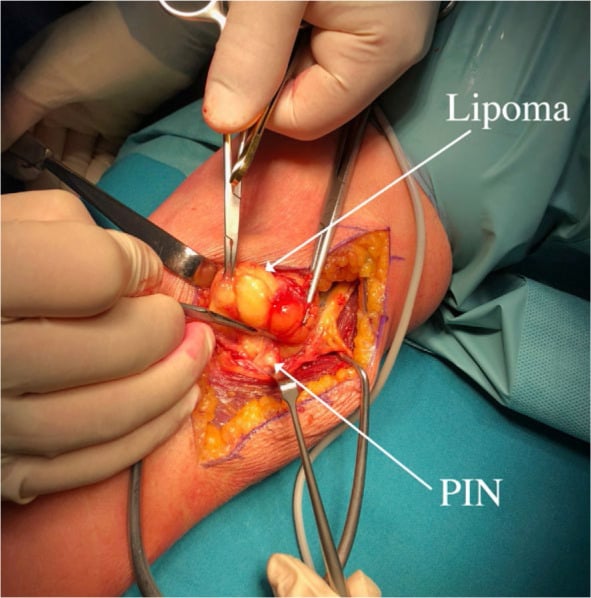
- Lipomas are a common cause of 'spontaneous' PIN palsy.
- Rheumatoid synovitis at the elbow can also compress the PIN.
- “If the patient has WRIST drop, the lesion is proximal to the PIN (High Radial Nerve).
- “In PIN palsy, the patient can extend the wrist (ECRL) but it deviates radially (due to ECU paralysis).
- “Pain alone is Radial Tunnel Syndrome, not PIN Syndrome.
Overview
Definition. Posterior interosseous nerve (PIN) syndrome is a compressive neuropathy of the deep motor branch of the radial nerve. It typically occurs in the proximal forearm within the radial tunnel, most commonly at the arcade of Frohse.
The clinical picture. It presents as weakness of finger and thumb extension, the finger drop. Wrist extension is preserved because ECRL is innervated proximal to the PIN, but the wrist deviates radially as it extends because ECU is paralysed.
Anatomy and Sites of Compression
The course. The radial nerve divides into its superficial (sensory) and deep (motor) branches at the level of the radiocapitellar joint; the deep branch is the PIN. It enters the radial tunnel under the edge of ECRB, then pierces the supinator between its two heads, passing beneath the proximal edge, the arcade of Frohse. It runs 4-5 cm within the supinator and exits distally to supply the deep extensor compartment.
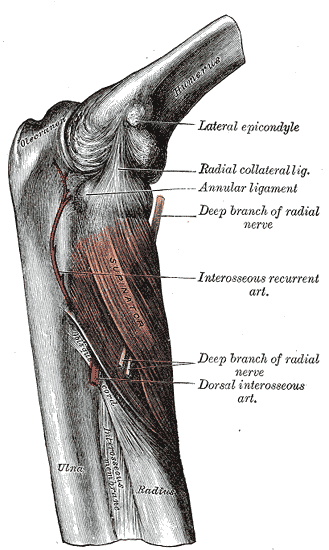
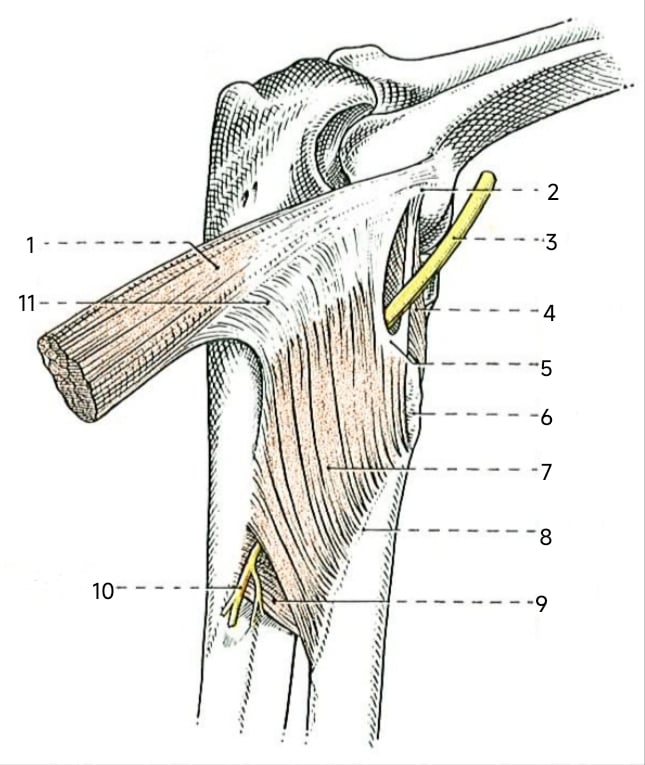
What the nerve supplies. The sequence of innervation helps localise the lesion. The PIN supplies the deep (distal) forearm extensors after innervating the supinator; the superficial wrist extensor, ECRL, is supplied by the radial nerve proximally and is spared.
- Radial nerve, proximal to the PIN: triceps, anconeus, brachioradialis, ECRL
- PIN, proximal to or within the supinator: ECRB (variable), supinator
- PIN, distal to the supinator: EDC, EDM, ECU, APL, EPB, EPL, EIP
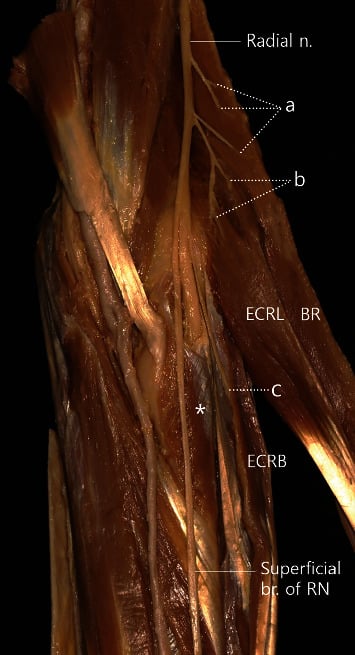
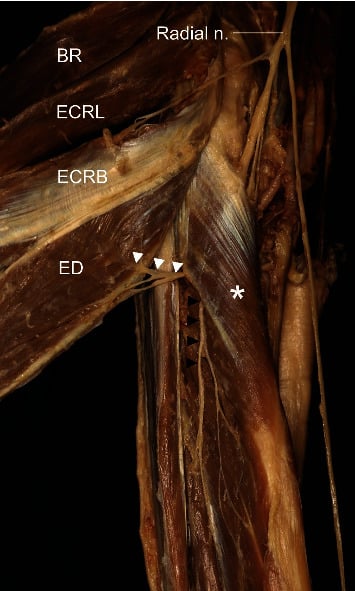
Where it is compressed. The "radial tunnel" is a misnomer; it is a muscular cleft. Five sites can compress the nerve, remembered as FREAS:
- Fibrous bands anterior to the radiocapitellar joint
- Recurrent vessels, the leash of Henry (branches of the radial recurrent artery)
- ECRB, its sharp medial tendinous edge
- Arcade of Frohse, the proximal tendinous arch of the supinator and the most common site; normal in 30%, fibrous in 70%
- Supinator, its distal edge
Classification Systems
Clinical types. PIN compression presents in one of three clinical types.
- Type I (complete PIN): all PIN muscles paralysed, giving finger drop, thumb drop and ECU paralysis
- Type II (partial PIN): only some muscles, such as the thumb or index alone
- Type III (radial tunnel): pain only, from dynamic compression
Type II mimics tendon rupture and often confuses the diagnosis.
Aetiology. Always consider inflammatory arthritis (RA) as a cause.
- Compressive: the arcade of Frohse (fibrous band)
- Space-occupying: lipoma (the commonest soft-tissue tumour here), ganglion, rheumatoid synovitis
- Traumatic: Monteggia fracture (radial head dislocation)
- Iatrogenic: radial head fixation or replacement
Clinical Assessment
Examination. Test the PIN muscles: EDC (MCP extension), EIP (index extension) and EPL (thumb extension). Check the tenodesis effect to rule out tendon rupture. The pain is a vague ache in the proximal forearm, unlike lateral epicondylitis, which is at the epicondyle; pain with weakness is PIN syndrome.
Special tests. Injection of local anaesthetic can also be diagnostic (and therapeutic).
- Middle finger test: resisted middle finger extension with the elbow extended. Pain in the proximal forearm is radial tunnel syndrome; weakness is PIN syndrome.
- Supinator compression: palpation 4 cm distal to the lateral epicondyle reproduces the symptoms.
A rheumatoid patient with dropped fingers may have EDC tendon ruptures (Vaughan-Jackson) or a PIN palsy from elbow synovitis, and missing the difference leads to the wrong operation. Tendon rupture comes with a sudden "ping", and the fingers drop one by one from ulnar to radial. PIN palsy usually comes on slowly, with all fingers affected together or in a specific pattern.
The tenodesis test settles it. Flex the wrist: if the fingers extend passively, the tendons are intact and the problem is the nerve; if they stay floppy and flexed, a tendon has ruptured. Ultrasound confirms.
Imaging and Electrodiagnostics
MRI. MRI is mandatory for any non-traumatic PIN palsy, to rule out a mass such as a lipoma or ganglion. The findings are a mass compressing the nerve and denervation oedema in the supinator and extensors. A fat-signal mass along the course of the PIN is a surgically treatable cause of progressive, otherwise "spontaneous" finger drop, and cross-sectional imaging defines a lesion's full extent before decompression and excludes an infiltrative mass. A negative MRI does not exclude dynamic compression.
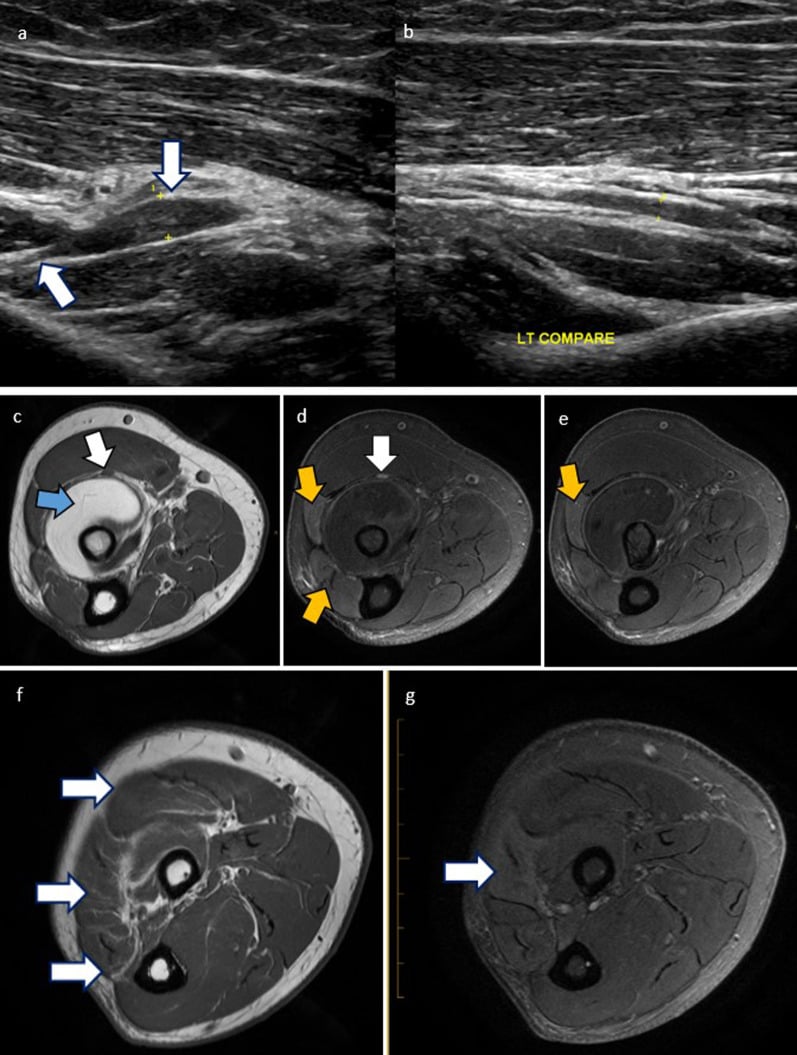
Ultrasound. Ultrasound is dynamic: it can show the nerve compressed during pronation and supination, and swelling of the nerve proximal to the arcade of Frohse (the "hourglass sign"). It establishes the relation of a ganglion to the radial nerve dynamically, and it confirms tendon continuity, which rules out rupture.
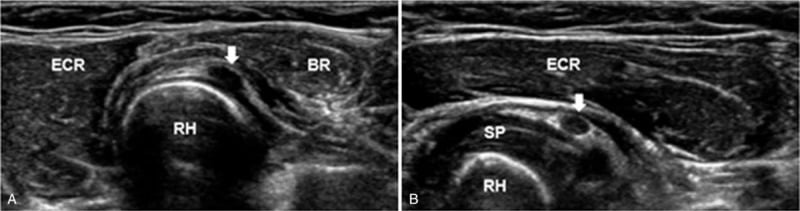
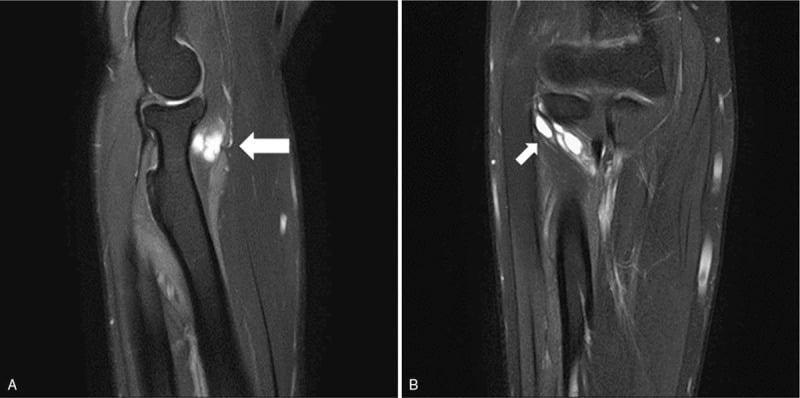
Nerve conduction and EMG. The superficial radial SNAP is normal, the point that causes most confusion. EMG shows denervation in the PIN muscles (EDC, ECU, EPL) while ECRL, brachioradialis and triceps are normal. If ECRL is affected, look proximally, at the high radial nerve.
Differential Diagnosis
A "dropped finger" or refractory lateral elbow pain has a wide differential. The decisive discriminators are motor weakness, the sensory status and the tenodesis effect. The sites of the four radial nerve syndromes: PIN and radial tunnel syndromes arise at the arcade of Frohse, Wartenberg syndrome at the forearm fascia, and a high radial palsy at the spiral groove.
- Motor weakness
- Yes (finger/thumb ext, ECU; ECRL spared)
- Sensory loss
- None
- Key discriminator
- Wrist extends but deviates radially; positive tenodesis (tendons intact)
- Motor weakness
- No true weakness (mechanical loss)
- Sensory loss
- None
- Key discriminator
- Negative tenodesis: fingers stay flexed on passive wrist flexion
- Motor weakness
- Yes plus wrist drop (ECRL/BR affected)
- Sensory loss
- Dorsal first webspace
- Key discriminator
- Wrist drop and sensory loss localise proximal to the elbow
- Motor weakness
- None (pain only)
- Sensory loss
- None
- Key discriminator
- Pain ~4 cm distal to lateral epicondyle; controversial entity
- Motor weakness
- None
- Sensory loss
- None
- Key discriminator
- Maximal tenderness AT the epicondyle, not over the supinator
- Motor weakness
- None
- Sensory loss
- Dorsoradial hand
- Key discriminator
- Pure sensory; positive Tinel over distal radial forearm
- Motor weakness
- Yes, often patchy/hourglass fascicular
- Sensory loss
- Variable
- Key discriminator
- Antecedent severe pain then palsy; MRI may be mass-negative
- Motor weakness
- Yes, myotomal (multi-nerve)
- Sensory loss
- Dermatomal
- Key discriminator
- Weakness crosses peripheral nerve territories; neck signs
- Motor weakness
- Yes, upper motor neuron pattern
- Sensory loss
- Variable
- Key discriminator
- Spasticity, hyperreflexia, non-segmental distribution
Management Algorithm
Non-operative. Suitable for neuritis (Parsonage-Turner), transient compression, and a palsy with no mass. A dynamic cock-up splint with an outrigger holds the fingers in extension and prevents overstretching, and the patient is observed for 3-6 months. Activity modification, avoiding pronation and supination, is key; steroids have a limited role unless the cause is inflammatory.
Surgical decompression. Decompress for a mass lesion such as a lipoma, for failure to recover after 3-6 months, and after trauma if the nerve is caught. The procedure releases the ECRB edge, the arcade of Frohse and the distal supinator, and complete release of all five sites is mandatory. The approach is anterior (Henry) or posterior (Thompson), described under Surgical Technique.
Tendon transfer. For a permanent palsy, greater than 1 year, tendon transfer is the salvage, and its outcome is generally better than nerve repair for gaps. The classic set is the Jones transfer:
- PT to ECRB - restores central wrist extension
- FCU to EDC - restores finger extension
- PL to EPL - restores thumb extension
Surgical Technique
Anterior approach (Henry). Stay on the nerve visually at all times.
- Volar curvilinear incision
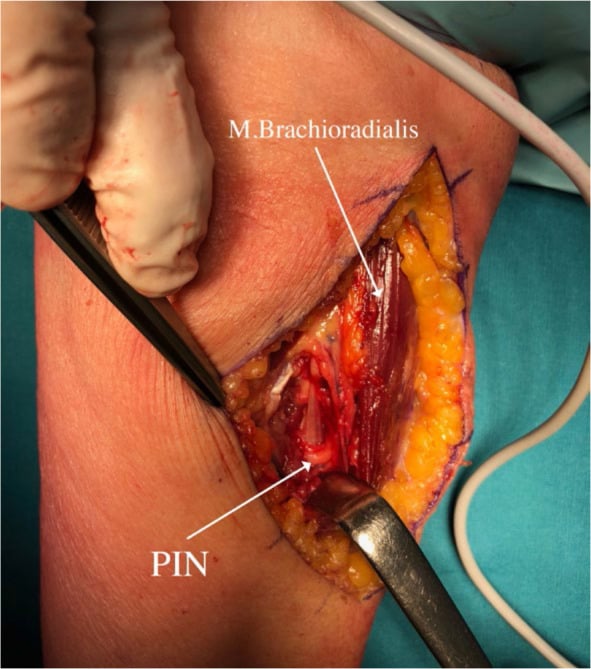
- Develop the interval between PT and brachioradialis
- Identify the radial nerve and trace it distally
- Ligate the leash of Henry, retract ECRB and identify the arcade of Frohse
- Divide the arcade and the superficial head of the supinator
Posterior approach (Thompson). A dorsal forearm incision through the interval between ECRB and EDC exposes the supinator directly. It suits tumours within the supinator and distal supinator pathology and gives a direct view of the nerve within the muscle, at the cost of less proximal control of the radial nerve at the elbow.
Choosing the approach. The choice depends on the level of pathology and surgeon preference. The anterior approach gives better visualisation of the arcade and better proximal control for arcade-level decompression; the posterior approach is favoured for supinator masses.
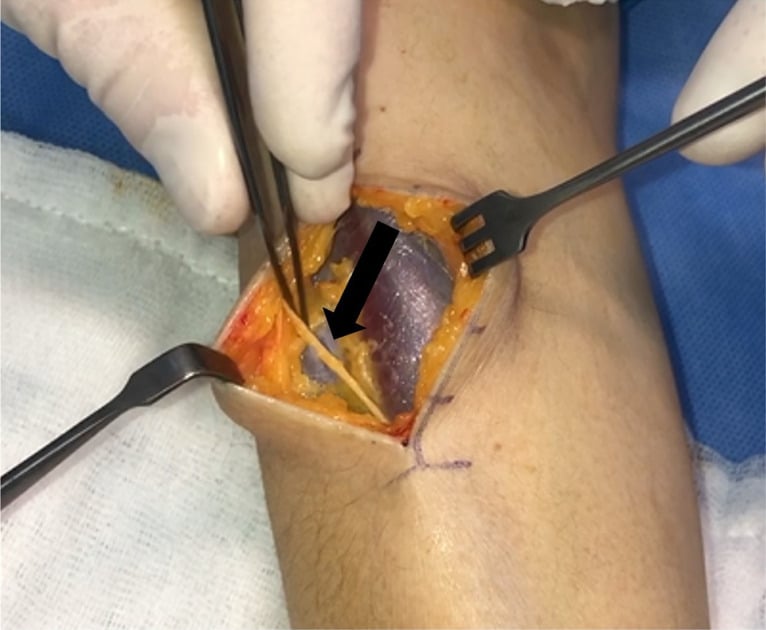
On the way in. Identify and protect the cutaneous nerve before deepening the interval; unrecognised traction or division creates an avoidable sensory neuroma.
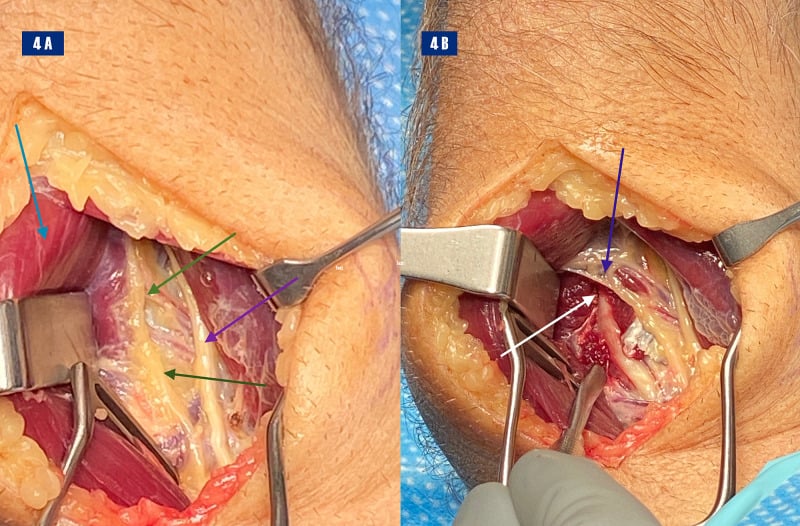
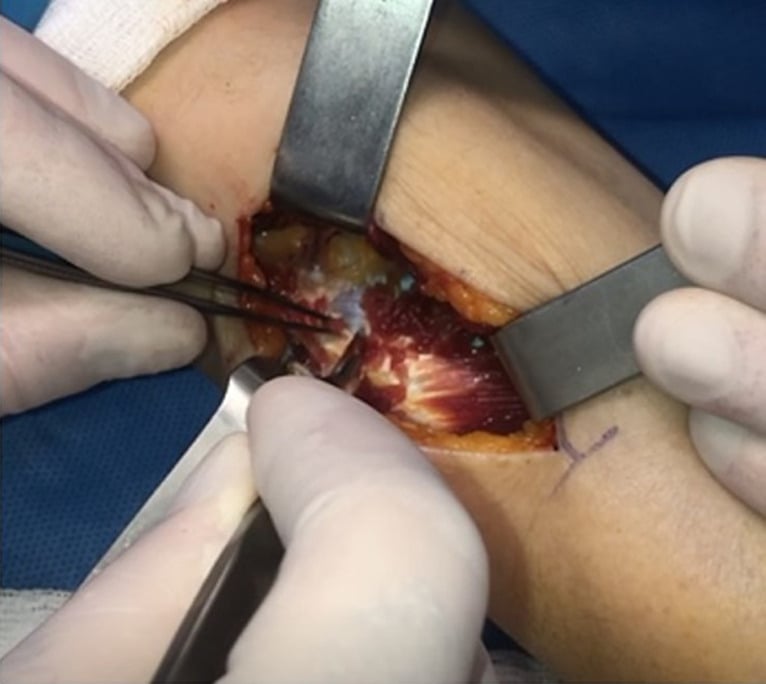
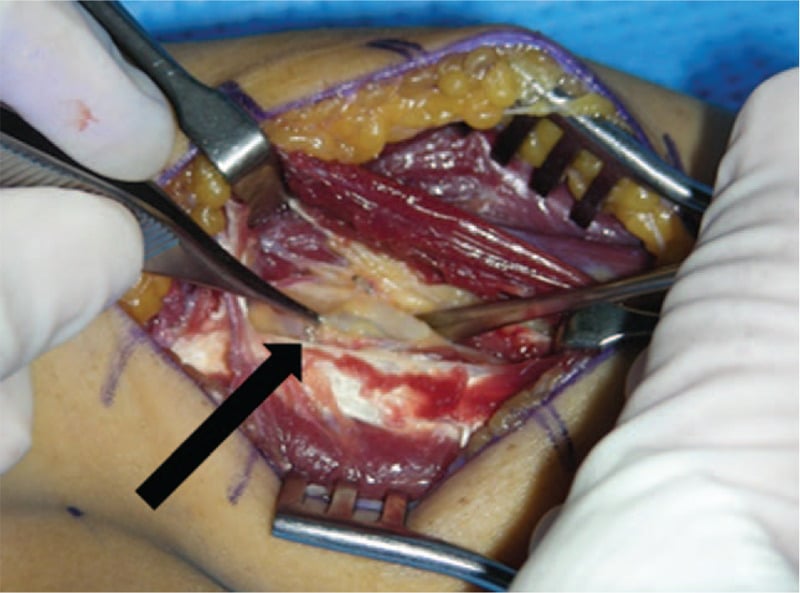
The release. Maintain direct visual control rather than dividing the supinator blindly. Open the fibrous edge of the arcade under direct vision with the nerve protected below; then trace the PIN distally through the supinator to exclude a second constriction. A final inspection confirms continuity, freedom from residual bands and the absence of a retractor-related injury.
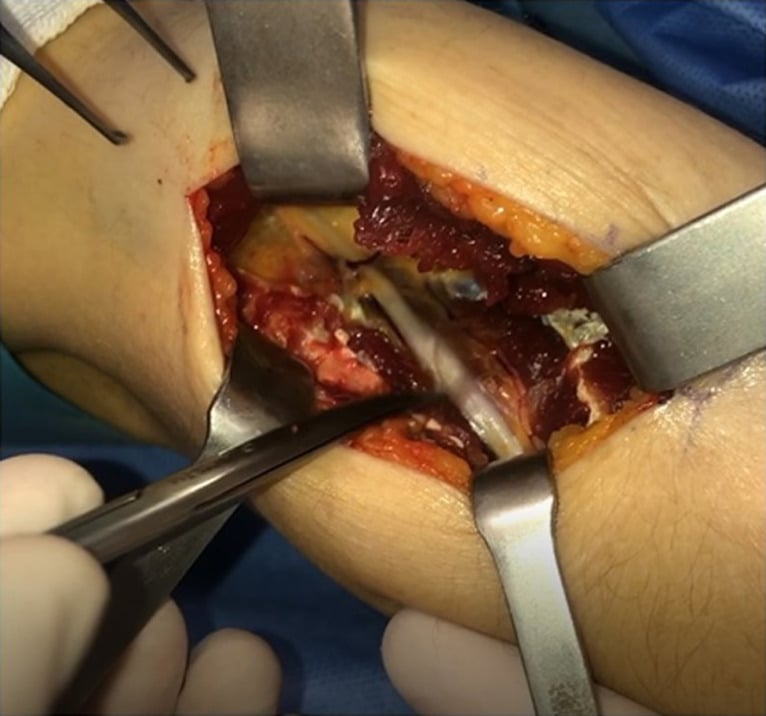
Mass lesions. The nerve should be identified proximally before circumferential tumour mobilisation. Excision of a ganglion should remove the cyst and its stalk while preserving the nerve and releasing any additional radial-tunnel constrictions. Once the mass is out, inspect the PIN along the former contact zone for hourglass narrowing, loss of continuity or residual compression before closure.
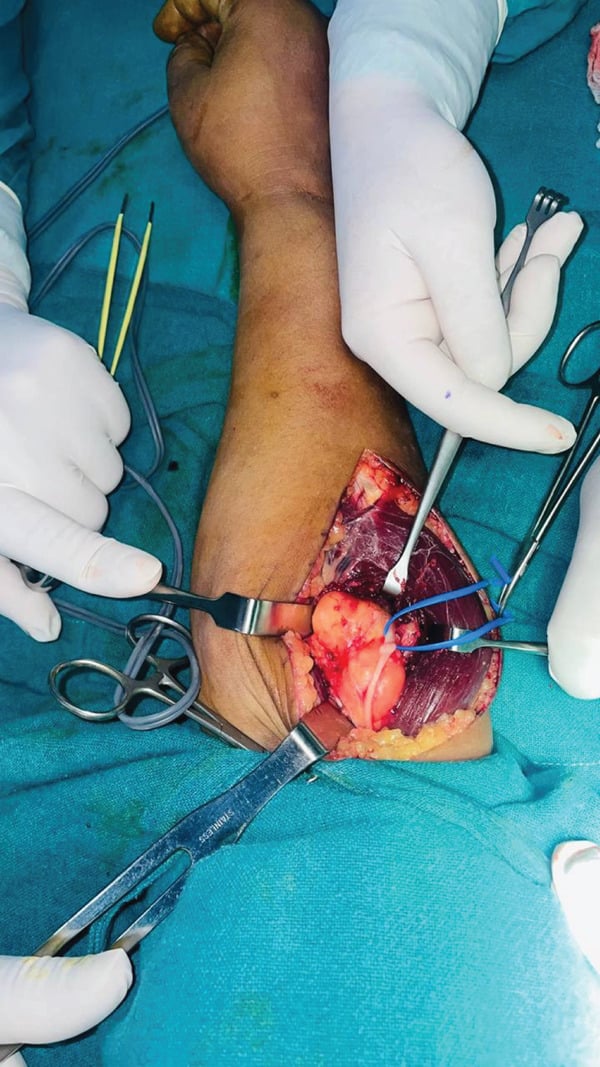
The Terminal Articular Branch and Wrist Denervation
Where the nerve ends. The PIN does not simply end in muscle. After supplying the deep extensors, its slender terminal continuation runs distally on the dorsal aspect of the interosseous membrane to the dorsal wrist capsule, where it becomes a purely articular (afferent) branch carrying pain and proprioceptive fibres from the dorsal radiocarpal and intercarpal joints. It is found in the floor of the fourth extensor compartment.
Partial wrist denervation. Selective neurectomy of the terminal PIN, classically combined with the terminal articular branch of the anterior interosseous nerve on the volar side, ablates the dorsal wrist joint pain afferents. It is a motion-preserving option for chronic dorsal wrist pain, particularly when a patient wishes to avoid or defer fusion or arthroplasty. Examples include degenerative SLAC or SNAC wrist, post-traumatic arthritis and a recalcitrant occult dorsal ganglion.
Predicting the response. A diagnostic local anaesthetic block of the terminal PIN over the dorsal distal forearm that relieves the pain predicts a good response before committing to neurectomy.
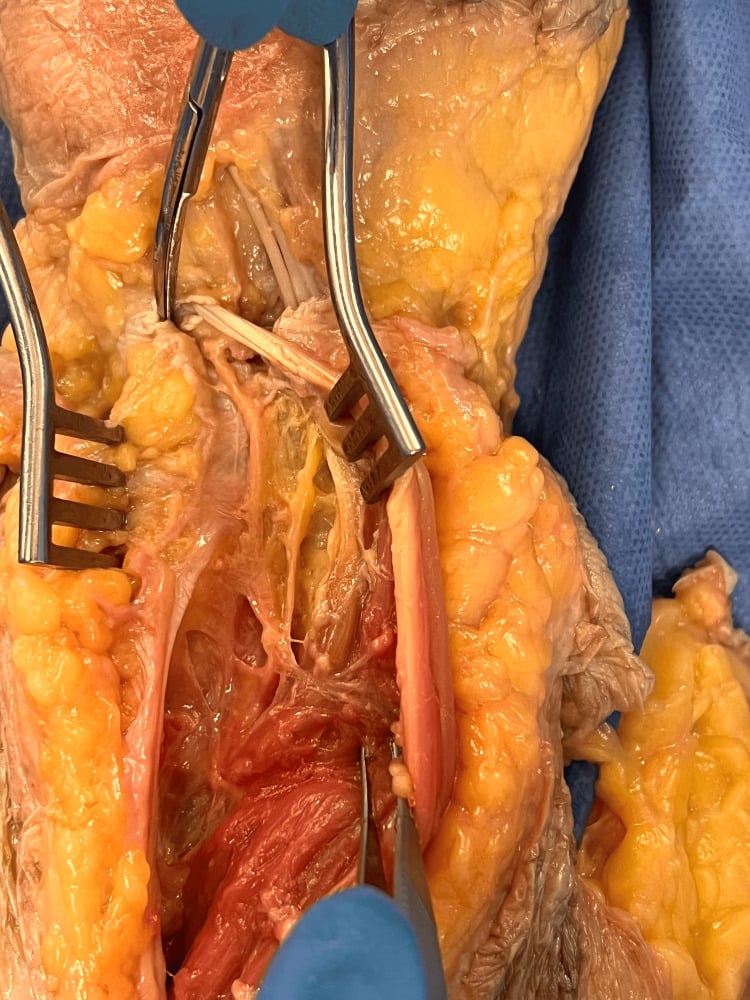
The terminal branch is purely articular: dividing it abolishes dorsal wrist pain but does not cause finger drop or any cutaneous sensory loss, while wrist and finger motor function are preserved. This is the opposite of a proximal PIN lesion (a motor palsy), and it catches candidates who assume any "PIN procedure" must weaken extension.
Iatrogenic Injury and the Surgical Safe Zone
Why it is at risk. Because it lies directly against the proximal radius within the supinator, the PIN is among the most frequently iatrogenically injured nerves of the forearm. It is at risk during any exposure of the proximal radius: radial head or neck fracture fixation or arthroplasty, Monteggia surgery, plating of the proximal radial shaft, and dissection towards the bicipital tuberosity.
Pronate the forearm. Pronation is the single most useful protective manoeuvre, and the one to use when working on the proximal radius or radial neck. It rotates the radius so that the PIN is carried medially and distally, away from the lateral operative field and the bicipital tuberosity, increasing the distance between the nerve and the radiocapitellar joint. Supination does the reverse, drawing the nerve anterolaterally, closer to the radiocapitellar joint and bicipital tuberosity and into the danger zone, and is avoided during lateral exposure.
The safe window. For lateral work it is the few centimetres immediately distal to the radiocapitellar joint; with the forearm pronated the nerve sits roughly two fingerbreadths beyond the joint. Keep subperiosteal dissection proximal to the bicipital tuberosity, avoid circumferential retractors around the radial neck, and positively identify the nerve whenever exposure must extend further distally. In the dorsal (Thompson) approach the PIN must be actively sought and protected within the supinator rather than relying on forearm position alone.
A new finger drop after radial head surgery is iatrogenic PIN injury until proven otherwise.
Complications
Intraoperative. Meticulous technique with loupe magnification is essential.
- Direct injury to the PIN during release, especially at the arcade of Frohse
- Damage to the leash of Henry (radial recurrent vessels), causing significant bleeding
- Incomplete release of the five compression sites, most commonly missing the distal supinator edge
- Unexpected ECRB weakness if its variable motor branch is damaged
- Injury to the superficial radial nerve during the anterior approach, causing sensory loss on the dorsal hand
Postoperative. Early mobilisation reduces scar formation around the nerve.
- Wound infection: low risk (1-2%) in clean surgery with appropriate prophylaxis
- Haematoma: may require evacuation if significant; compress during early recovery
- Recurrence: scarring around the nerve can cause recurrent symptoms (5-10%)
- Persistent weakness: may reflect irreversible nerve damage before decompression
- Traction neuropathy: over-aggressive retraction during exposure can worsen function
- Heterotopic ossification: rare, particularly after traumatic cases
Rehabilitation
The pace of recovery. Recovery progresses at 1 mm per day from the site of compression, and full recovery may take 6-12 months depending on severity. Sensory re-education is not required, because the PIN has no cutaneous territory. Recovery is serial, so document the return of individual muscles rather than relying on a single composite hand position.
The order of recovery. Recovery follows the order of innervation. In a PIN lesion, ECU recovers first, EDC next, and EPL and EIP last. In a high radial nerve lesion, brachioradialis and ECRL recover first, and the sequence runs brachioradialis, ECRL, ECRB, supinator, EDC, EPL.
- Dynamic splint, a low-profile radial nerve palsy splint with MCP extension assist: allows active flexion and passive extension and prevents extensor overstretching
- Keep the incision clean and dry; sutures out at 10-14 days
- Elevation and gentle active finger movements for oedema
- Active-assisted exercises to maintain joint mobility
- Silicone gel or massage once the wound has healed
- Continue splinting; night splinting is particularly important to prevent contractures
- Watch for a flicker of EDC as a sign of reinnervation
- Gentle isometrics, progressing to resistance as power returns
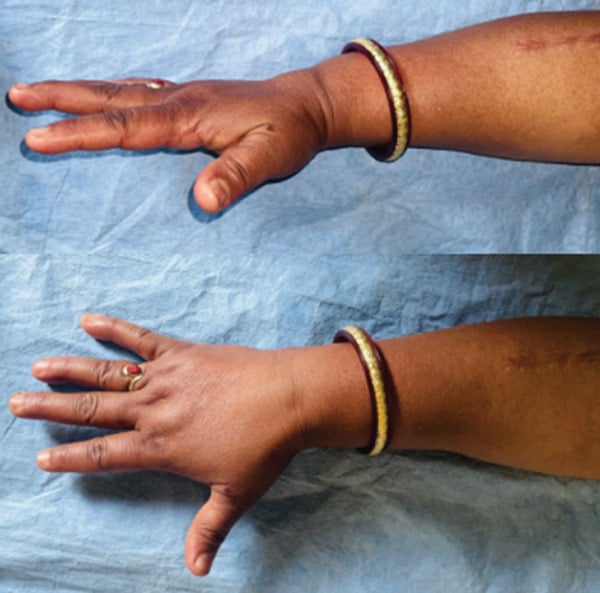
Prognosis
Outcome by cause. Expected outcomes differ by aetiology.
- Compression at the arcade: excellent recovery if decompressed within 6 months, with greater than 85% returning to full function
- Mass lesion (lipoma): excellent with excision and neurolysis; function returns 3-6 months after surgery
- Traumatic (Monteggia): variable, depending on mechanism and timing; neurapraxia recovers well, neurotmesis requires grafting
- Inflammatory (RA): good if synovectomy is performed early; ongoing disease may cause recurrence
- Radial tunnel syndrome: unpredictable, with 60-70% success for pain relief even with surgery
Prognostic factors. A shorter duration of symptoms (under 3 months) is associated with better recovery, partial palsies recover better than complete ones, and younger patients have better nerve regeneration capacity. Mass lesions with clear compression do better than inflammatory conditions. Decompression within 6 months maximises recovery potential, and early intervention correlates strongly with better outcomes.
Serial EMG. Reinnervation potentials at 3 months are a positive prognostic sign, and serial EMG monitoring helps guide the surgical decision.
Guidelines, Registries & Global Practice
PIN syndrome and radial tunnel syndrome are uncommon and have no dedicated society guideline or arthroplasty-style registry. The "evidence" is therefore best summarised as global epidemiology, where the major society positions converge or differ, and how practice changes with available resources.
Global Epidemiology:
- Compressive radial neuropathy at the elbow is rare relative to carpal and cubital tunnel syndrome; isolated spontaneous PIN palsy is described mainly in case series and reviews rather than population studies (McGraw, J Hand Surg Eur Vol 2019).
- No sex predominance is firmly established; reported cases span young adults (often neuralgic amyotrophy / Parsonage-Turner) to older adults (compressive and mass lesions).
- Recognised causes worldwide: the arcade of Frohse and supinator fibrous bands, space-occupying lesions (lipoma is the classic solid mass, also ganglion, synovial cyst, nerve sheath tumour), rheumatoid elbow synovitis, Monteggia and radial head fracture–dislocation, and iatrogenic injury during radial head or proximal radius surgery.
Side-by-Side Society Positions:
- Position relevant to PIN / radial tunnel
- Lateral elbow pain pathways emphasise distinguishing lateral epicondylitis from radial tunnel syndrome; surgery for pain-only radial tunnel is regarded as having a weak evidence base.
- Position relevant to PIN / radial tunnel
- Spontaneous finger drop is a red flag requiring imaging (MRI) and hand-surgery referral to exclude a compressive mass before labelling it neuritis.
- Position relevant to PIN / radial tunnel
- PIN at risk in Monteggia and radial head/neck injuries and during proximal radius approaches; advocates nerve identification and protection, especially with the posterolateral (Kocher) and Thompson exposures.
- Position relevant to PIN / radial tunnel
- Supports decompression for confirmed compressive motor palsy; recommends caution and shared decision-making for pain-only radial tunnel syndrome given controversial outcomes.
- A true motor PIN palsy with a compressive lesion warrants decompression; an imaging-negative palsy (possible neuralgic amyotrophy) is observed first.
- MRI is the key investigation for any non-traumatic PIN palsy to exclude a mass; ultrasound is a useful, operator-dependent adjunct and can be dynamic.
- Pain-only radial tunnel syndrome is the contested zone: most bodies advise exhausting non-operative care and counselling the patient that surgical results for pain relief are unpredictable.
- High-resource settings: ready access to MRI, high-resolution nerve ultrasound, and electrodiagnostics; reconstruction may include nerve transfer for recent lesions (Bertelli, J Hand Surg Am 2020) as well as tendon transfer.
- Limited-resource settings: diagnosis is more clinical (finger drop with preserved radial-deviated wrist extension and normal sensation), imaging may be confined to radiographs and ultrasound, and tendon transfer is the dominant, durable salvage because it needs no microsurgical infrastructure and gives reliable positional results (Cheah, Hand Clin 2016).
- Rehabilitation everywhere centres on a dynamic radial-nerve-palsy outrigger splint to maintain digital extension and prevent overstretching while reinnervation or healing proceeds; serial clinical and (where available) electrodiagnostic review guides the timing of surgery.
Controversies and Areas of Uncertainty
The original Roles and Maudsley concept (1972) framed refractory lateral elbow pain as a radial nerve entrapment by analogy to carpal tunnel syndrome. Rosenbaum (1999) argued this analogy is flawed and that true neurogenic compression should produce PIN motor weakness. Surgical decompression for pain alone has unpredictable results, and there are no high-quality randomised trials. State both positions in the viva.
Anterior versus posterior approach. No randomised data show superiority of the Henry over the Thompson exposure; the choice is driven by the level of pathology and surgeon familiarity, as set out under Surgical Technique.
Timing of surgery in compressive palsy. Common practice is to decompress a confirmed compressive lesion promptly and to observe an imaging-negative palsy for roughly 3 months, but the exact threshold is not standardised. Outcomes worsen with age over 50 and with delay (McGraw, 2019).
Nerve transfer versus tendon transfer. For recent lesions (under ~12 months), nerve transfer can give superior wrist motion and grip compared with tendon transfer (Bertelli, 2020), but tendon transfer remains the established, microsurgery-free salvage for late or irrecoverable palsy. The optimal algorithm is still debated.
Hourglass fascicular constriction. Increasingly recognised in spontaneous palsy, within the neuralgic amyotrophy spectrum. Whether to observe, perform neurolysis, resect and graft, or transfer is unresolved, and intraoperative findings often dictate the decision.
The role of imaging. MRI is favoured to exclude a mass, but high-resolution ultrasound increasingly detects fascicular constriction and dynamic compression; the comparative diagnostic accuracy for the specific question of operability is not well defined.
MCQ Practice Points
Q: What is the most common site of PIN compression? A: The Arcade of Frohse (proximal edge of Supinator).
Q: Why does the wrist deviate radially in PIN palsy? A: ECRL (Radial N) is intact, but ECU (PIN) is paralyzed.
Q: How do you differentiate PIN palsy from multiple tendon ruptures (Vaughan-Jackson)? A: Tenodesis test. Passive wrist flexion should extend the fingers if tendons are intact.
Q: What is Wartenberg's Syndrome? A: Compression of the Superficial Radial Nerve (Sensory only) causing dorsal hand paresthesia.
Q: What is the most common soft tissue mass causing spontaneous PIN palsy? A: Lipoma. Always order MRI for spontaneous PIN palsy to rule out a mass lesion.
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 45-year-old woman presents with inability to extend her fingers. It started gradually over 3 weeks. No trauma. Wrist extension is present but deviates. What is the diagnosis?”
“A child has a Monteggia fracture (Ulnar fracture, Radial head dislocation) reduced 6 weeks ago. Still cannot extend thumb.”
“A tennis player complains of lateral elbow pain. Treated as 'Tennis Elbow' for 6 months with no relief. Injections failed. Exam shows pain on resisted middle finger extension.”
“A 55-year-old woman with known rheumatoid arthritis develops progressive weakness of finger extension over 4 weeks. She has swelling around the elbow. How do you differentiate the cause?”
Anatomy
- FREAS (Fibrous, Recurrent, ECRB, Arcade, Supinator)
- Arcade of Frohse = #1 Site (70% fibrous)
- ECRL Spared (innervated by Radial Nerve proximally)
- PIN = pure motor branch of Radial nerve
- Supinator course: 4-5cm within muscle
Clinical
- Finger Drop (Not Wrist Drop = PIN vs High Radial)
- Radial Deviation on wrist extension (ECRL intact, ECU paralyzed)
- Tenodesis Test (rule out Vaughan-Jackson tendon rupture)
- Normal sensation (Superficial Radial branches off proximally)
- Middle Finger Test: pain/weakness 4cm distal to epicondyle
Treatment
- MRI mandatory (rule out lipoma/mass)
- Observe 3-6 months if no mass
- Release (Henry or Thompson approach)
- Transfers if no recovery at 1 year (PT-ECRB, FCU-EDC, PL-EPL)
- Splint (dynamic outrigger) prevents overstretching
Evidence Base
Arcade of Frohse: the anatomical basis of PIN compression
- Classic anatomical dissection study correlating the arcade of Frohse with PIN paralysis
- The proximal margin of the superficial supinator head is tendinous (a fibrous arcade) in a substantial proportion of adult specimens
- The arcade is membranous, not tendinous, in fetal and infant specimens, suggesting the fibrous arch is acquired with development and use
- Established the arcade of Frohse as the principal site of entrapment in spontaneous PIN palsy
Radial tunnel syndrome: resistant tennis elbow as a nerve entrapment
- Original description of radial tunnel syndrome as a cause of refractory lateral elbow pain ('resistant tennis elbow')
- Patients presented with proximal forearm pain and tenderness over the supinator, without motor deficit
- Reported symptomatic improvement after radial nerve decompression in a series of resistant cases
- Framed the entity by analogy to carpal tunnel syndrome — a comparison later disputed
Disputed radial tunnel syndrome
- Critical review arguing that true neurogenic radial tunnel syndrome is uncommon and is identifiable by focal PIN motor weakness
- Challenges the Roles and Maudsley concept that proximal forearm pain alone represents nerve entrapment
- Recommends reserving the term 'radial tunnel syndrome' for genuinely neurogenic cases
- Calls for controlled evaluation of surgery for 'persistent tennis elbow' rather than adoption by analogy to carpal tunnel syndrome
PIN discontinuity due to lipoma compression
- Two cases of severe PIN compression by a benign lipoma at the elbow producing near-transection (Sunderland grade V) of the nerve
- Proposed a 'sandwich' mechanism: the mass compresses from below while a fibrous supinator band (arcade of Frohse or distal supinator edge) compresses from above
- Demonstrates that an occult soft-tissue mass can cause profound, irreversible nerve injury
- Reinforces that lipoma is a classic and treatable cause of spontaneous PIN palsy
Isolated spontaneous PIN palsy: aetiology and management review
- Comprehensive review categorising spontaneous PIN palsy into compressive and non-compressive (e.g. neuralgic amyotrophy with hourglass fascicular constriction)
- Evidence supports surgical decompression for compressive palsy; conservative management first when no compressive lesion is seen on imaging
- Poorer prognosis with age over 50 years, delay to surgery, and long-standing compression with severe fascicular thinning
- Provides an evidence-based treatment algorithm where one was previously lacking
Nerve versus tendon transfer for radial nerve paralysis
- Comparative series: 14 patients with radial nerve lesions under 12 months underwent nerve transfer (AIN to ECRB branch, FCR branch to PIN); 13 with longstanding palsy underwent tendon transfer (PT-ECRB, FCU-EDC, PL-EPL)
- Nerve transfer gave better wrist flexion–extension range and grasp strength than tendon transfer
- Half of the tendon transfer patients had to flex the wrist to fully extend the fingers; permanent radial deviation occurred in 5 of 13
- A roughly 30-degree thumb MCP extension lag (poor EPL recovery) persisted after BOTH procedures
Radial nerve tendon transfers (technique and outcomes review)
- Review of tendon transfer reconstruction for irrecoverable radial nerve palsy (loss of wrist, finger and thumb extension)
- Common donors: pronator teres (to ECRB) for wrist extension, wrist flexors and finger flexors for digital extension
- Transfer sets are classified by the donor used to power the extensor digitorum communis (FCU, FCR or FDS variants)
- Good functional results are typical because these are positional transfers that do not demand high power
Ultrasound of the radial nerve in palsy: imaging–surgical correlation
- Prospective study of 11 patients with radial nerve palsy after humeral shaft fracture, with US compared against surgical inspection in 5 operated cases
- US correctly identified the damaged nerve in all 5 surgically explored patients (entrapment between fragments, transection, laceration, nerve riding on a fragment, nerve buried in callus)
- US confirmed nerve continuity in all 6 conservatively managed patients who recovered
- Established high-resolution ultrasound as a feasible, accurate tool for assessing radial nerve injury