Avulsions | Tendinopathy | Sciatic Nerve
- Anatomy: Semimembranosus origin is superolateral on the tuberosity; the conjoint tendon (semitendinosus + biceps long head) is posteromedial. Biceps short head (linea aspera) is spared.
- Mechanism: Forced hip flexion with the knee extended (waterskiing, doing the splits, slip on wet floor).
- Sciatic anatomy varies: identify the nerve and motor branches when the planned exposure or scar requires it; neurolysis is selective
- Surgery is not a 2-cm equation: tendon number/identity, function, symptoms, chronicity, nerve findings, patient goals and tissue quality all matter
- Earlier repair is usually technically easier, but there is no validated four-week point after which primary repair or benefit disappears
- Rehabilitation follows fixation and tissue response, not a universal six-week brace or six-month return
- “A reproduced mechanism, weakness and local findings raise suspicion; bruising is not pathognomonic
- “MRI defines morphology; ultrasound can provide a dynamic accessible alternative in expert hands
- “Describe which tendon is detached and the quality/length of remaining tissue
- “Chronic repair may require mobilisation, selective neurolysis or graft augmentation—but not automatically
Overview and Epidemiology
Proximal hamstring injuries range from minor strains to complete avulsions of the origin. A complete avulsion is a devastating injury in an athlete, and if it is missed it leaves significant weakness and loss of function.
Who. The pattern differs with age.
- Young athletes - apophyseal avulsions through the ischial apophysis
- Middle-aged adults - tendinous avulsions, on a background of degeneration
Where it sits. The proximal avulsion has to be told apart from the mid-substance strain and from the distal avulsion at the knee.
- Proximal Avulsion
- Forced Hip Flexion (Waterski)
- Mid-substance Strain
- Running/Sprinting
- Distal Avulsion
- Direct Blow/Cut
- Proximal Avulsion
- Ischial Tuberosity
- Mid-substance Strain
- Musculotendinous Junction
- Distal Avulsion
- Pes Anserinus/Fibula
- Proximal Avulsion
- Massive Posterior Thigh
- Mid-substance Strain
- Localised
- Distal Avulsion
- Knee region
- Proximal Avulsion
- Repair considered if functionally important and repairable
- Mid-substance Strain
- Conservative
- Distal Avulsion
- Depends on ligament
Pathophysiology and Mechanisms
Mechanism. A rapid eccentric contraction, with the hip forced into flexion while the knee is extended. The classic settings:
- Water skiing, getting up out of the water
- Bull riding
- Gymnastics, doing the splits
- Slipping on a wet floor into the splits
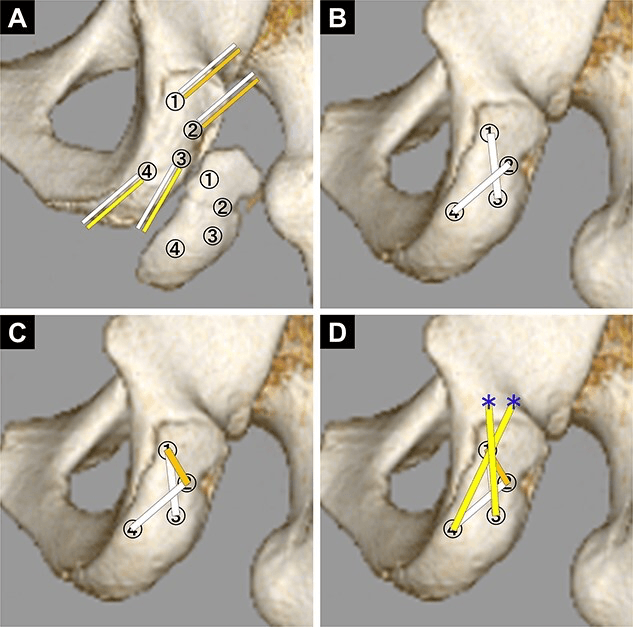
The origin. Semimembranosus, semitendinosus and the long head of biceps femoris all arise from the ischial tuberosity, which is divided into upper and lower facets. Semimembranosus takes the superolateral impression and has the largest footprint. Semitendinosus and biceps long head arise together as the conjoint tendon from the posteromedial impression.
The short head is spared. Biceps femoris short head arises from the linea aspera of the femur, not the ischium, so it survives an origin avulsion.
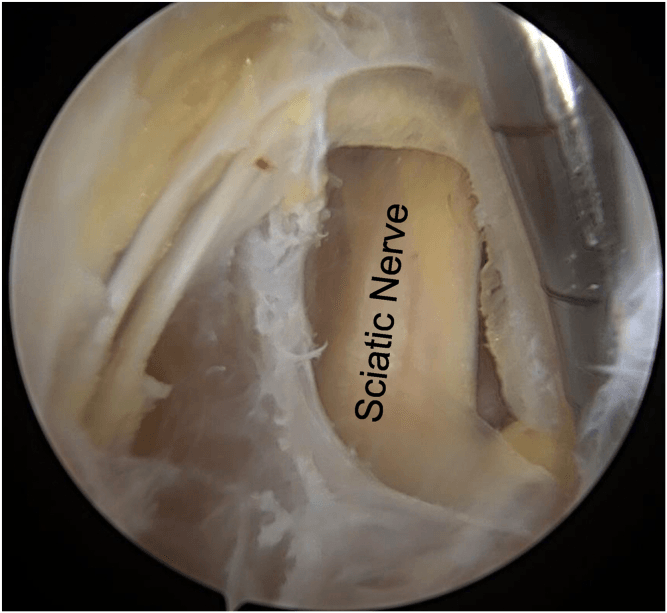
The sciatic nerve. It runs lateral and deep to the ischial origin, but its distance from the origin and its branching pattern vary. The tibial division supplies variable motor branches to semimembranosus, semitendinosus and biceps femoris long head. Retraction and chronic scar may tether or irritate the nerve, although the same symptoms can also come from deep-gluteal pathology.
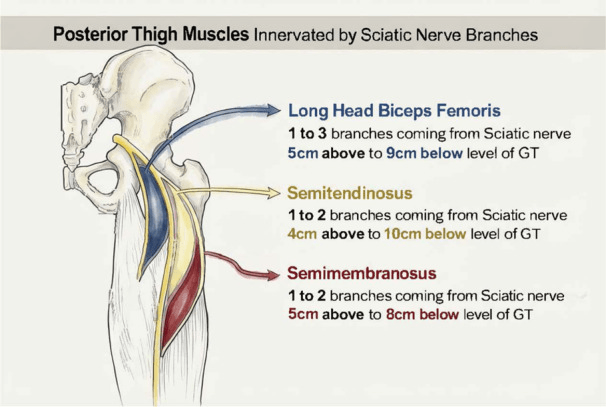
The posterior femoral cutaneous nerve. It crosses the operative region in a variable position, and injuring it can cause sensory symptoms in the posterior thigh. Document motor and sensory findings before treatment and after any intervention.
The sacral plexus. The sciatic nerve derives from the sacral plexus (L4-S3), the common peroneal portion from L4-L5 and the tibial portion from S1-S3. Proximal lesions may affect the hip abductors through the superior gluteal nerve, and a documented motor and sensory examination helps localise the level of injury.
Classification Systems
The Wood classification is MRI based, described by Wood and colleagues in their JBJS series of 72 reconstructions (2008).
- Type 1 - osteo-apophyseal (bony) avulsion, typically adolescent
- Type 2 - musculotendinous junction avulsion
- Type 3 - incomplete tendinous avulsion
- Type 4 - complete tendinous avulsion off bone with minimal or no retraction
- Type 5 - complete avulsion with significant retraction or sciatic nerve involvement, the most severe
Describe, then decide. The type is shorthand. Report the tendon identity and number, partial or complete continuity, measured retraction, tissue quality, atrophy, bone injury and nerve findings; these inform the operative decision rather than dictate it.
Clinical Assessment
History. The patient feels a "pop" or tearing in the buttock, and may describe a fall into the splits. Pain is immediate, and they cannot walk without a limp. Sciatic symptoms, numbness or foot drop, are rare but urgent.
Look and feel. The proximal contour of the posterior thigh is lost, the "hamstring droop". Extensive bruising tracks down towards the knee, but it takes days to appear. There is a tender defect at the ischial tuberosity.
Strength. Knee flexion and hip extension are weak. Knee flexion may still be present, because biceps short head, gracilis and sartorius are intact.
Bowstring sign. With the patient prone and the knee flexed to 90°, palpate the distal hamstring tendons. Absent or asymmetrical bowstringing suggests an avulsion.
Investigations
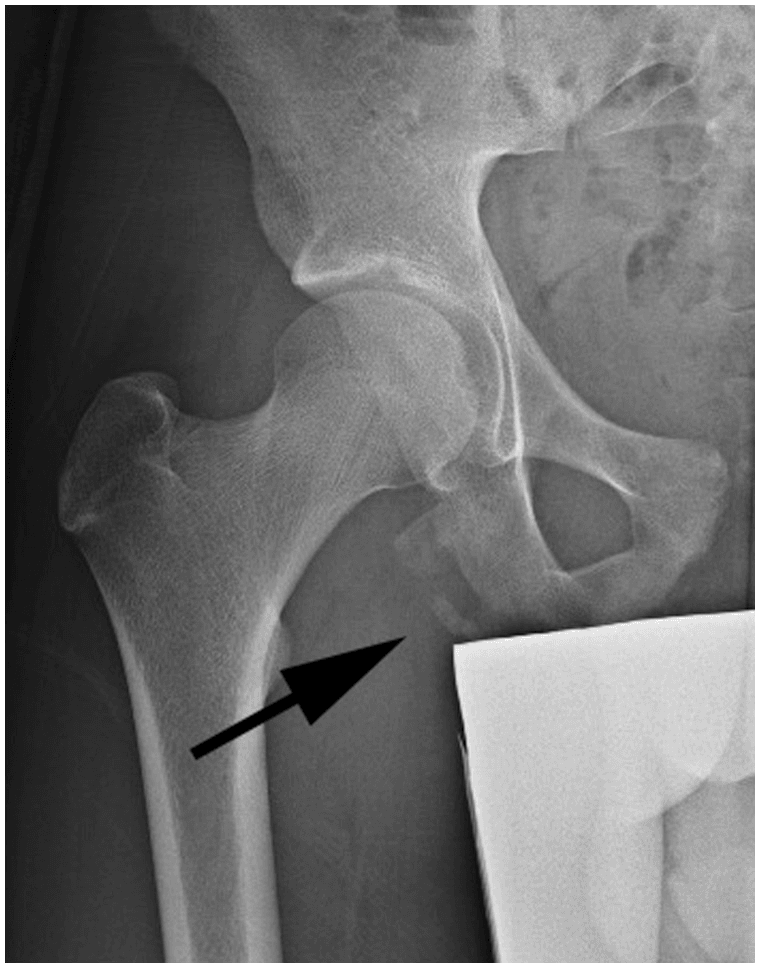
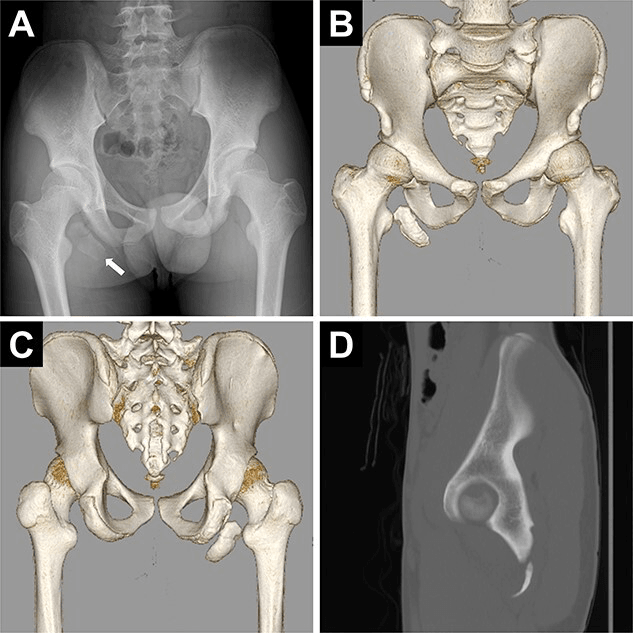
Radiographs. Obtain an AP pelvis in skeletally immature patients or whenever a bone injury is plausible. Add further views or CT when fragment morphology will change fixation planning.
MRI maps the ischial origin and the whole musculotendinous unit. The report should cover:
- which tendon is involved
- partial versus complete continuity
- retraction
- haematoma
- atrophy and fatty change
- bone injury, and the adjacent nerve and soft tissue
Image promptly when the result will alter an acute decision, but there is no universal two-week deadline.
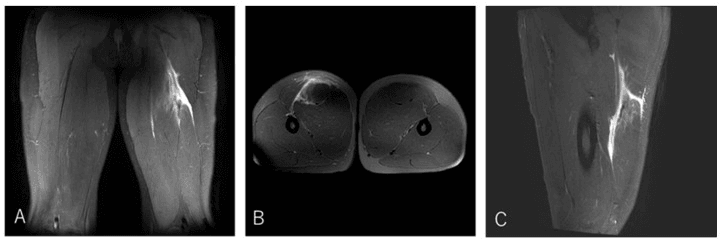
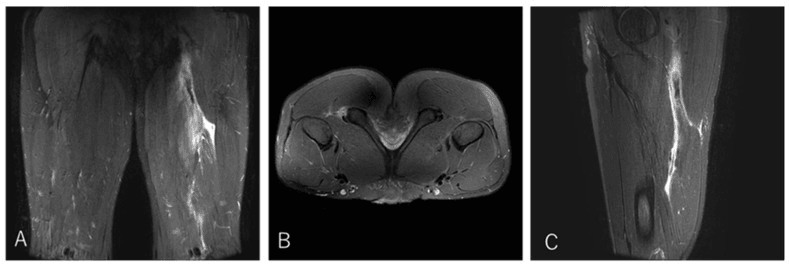
Ultrasound. In expert hands it assesses continuity and haematoma, shows dynamic tendon and nerve relations, and guides procedures. It is operator-dependent, and it complements MRI rather than automatically replacing it.
Differential Diagnosis
Buttock and posterior-thigh pain has several mimics, and these discriminators separate a true proximal avulsion from them.
- Key Discriminator
- Acute pop + extensive posterior-thigh ecchymosis, palpable ischial gap
- Best Test
- MRI (number of tendons + retraction)
- Key Discriminator
- Gradual deep buttock pain worse with sitting/sprinting, no acute pop
- Best Test
- MRI shows tendinosis, no full-thickness gap
- Key Discriminator
- Point tenderness over tuberosity, no strength loss
- Best Test
- MRI/US fluid at bursa
- Key Discriminator
- Sciatic-type leg pain, positive seated piriformis/slump
- Best Test
- MRI plus nerve assessment
- Key Discriminator
- Skeletally immature, bony fragment on X-ray
- Best Test
- AP pelvis radiograph
- Key Discriminator
- Musculotendinous junction tenderness, no ischial gap
- Best Test
- MRI shows oedema at MTJ
- Key Discriminator
- Back pain, dermatomal radiation, neuro deficit
- Best Test
- MRI lumbar spine
Proximal (High) Hamstring Tendinopathy
Presentation. Gradual deep buttock or ischial pain localised to the tuberosity, with no acute pop and no massive ecchymosis, which is what distinguishes it from an avulsion. The hallmark is pain worse on sitting, especially on hard surfaces, with hamstring stretch, and with loaded hip flexion: accelerating, lunging, downhill or fast running. Strength is largely preserved and there is no palpable gap.
The compression model. At end-range hip flexion the proximal tendon is compressed against the ischial tuberosity, which acts as a bony pulley. Tendinopathy here is therefore a combined tensile and compressive load problem, which is why deep hip flexion, sitting and aggressive static stretching all aggravate it, and why early management limits compression rather than stretching into it.
- Approach
- Tenderness over the ischial tuberosity; the Puranen-Orava test (standing, hip flexed near 90 degrees on a support with the knee extended), the bent-knee stretch and modified bent-knee stretch tests reproduce deep buttock pain
- Approach
- MRI shows origin tendinosis (thickening, increased signal) with peritendinous oedema and sometimes ischiogluteal bursitis, but no full-thickness avulsion gap; ultrasound can show the same
- Approach
- Reduce ischial compression first: modify sitting, avoid end-range hip-flexion loading and aggressive stretching early
- Approach
- Stage it: isometrics for pain, then heavy slow resistance or isotonic, then eccentric and finally energy-storage (running) loading; address gluteal and lumbopelvic strength and running mechanics
- Approach
- Extracorporeal shockwave therapy; image-guided peritendinous corticosteroid (short-term relief, used cautiously given proximity to the sciatic nerve); platelet-rich plasma has limited evidence; surgery (debridement) is rarely needed
Single-tendon semimembranosus tendinopathy and its specific footprint pathology are developed in the dedicated semimembranosus-tendinopathy topic.
Hamstring Syndrome (Deep Gluteal Sciatic Entrapment)
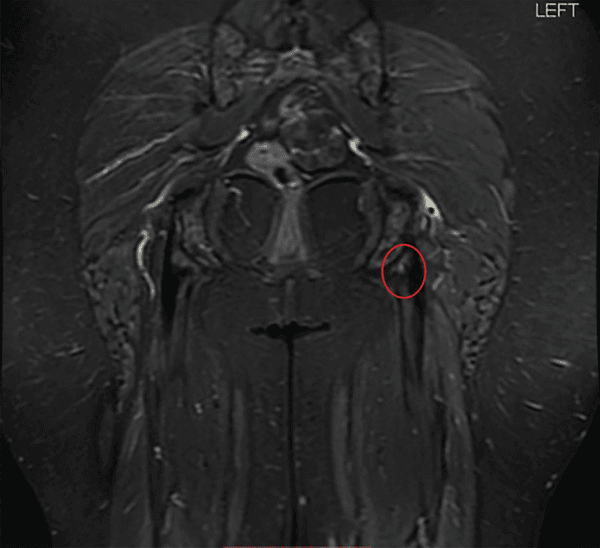
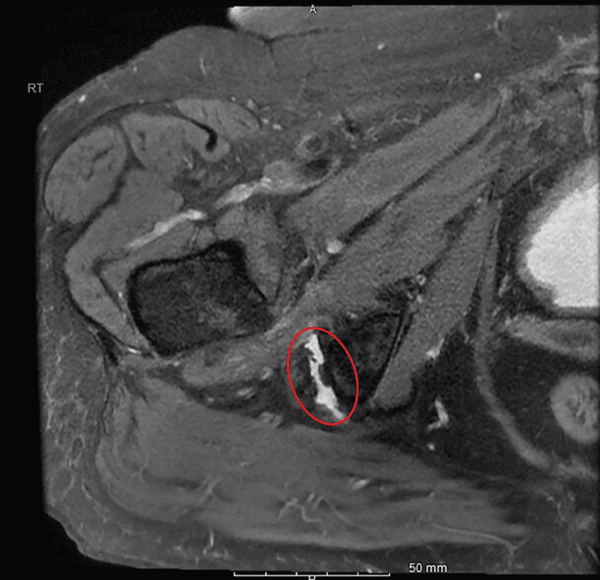
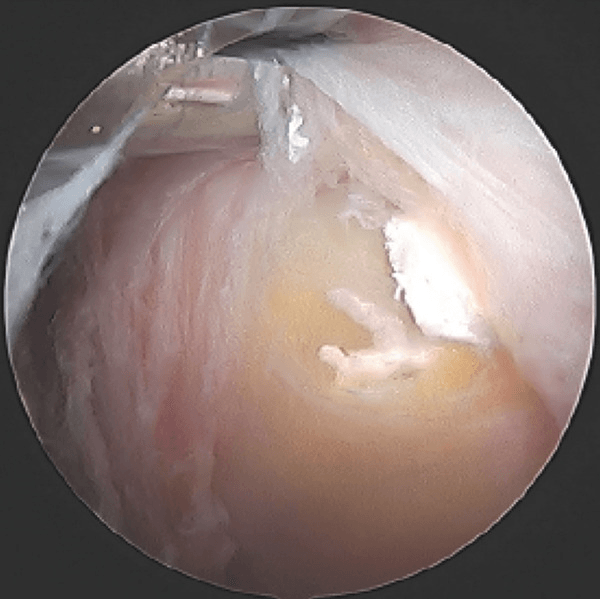
Definition. Hamstring syndrome, first described by Puranen and Orava, is extra-spinal entrapment of the sciatic nerve by tight tendinous or fibrous bands at the lateral ischial tuberosity, by the proximal hamstring origin, or by scar tethering after a healed avulsion or repair. Chronic sitting pain from a stump scarred to the nerve belongs here.
Where it sits. It falls within deep gluteal syndrome, extra-spinal sciatic entrapment in the subgluteal space, but it is a distinct cause from its neighbours and is kept separate in the viva.
- Site / cause
- Sciatic nerve tethered by tendinous bands or scar at the ischial origin
- What separates it clinically
- Pain is maximal at the ischial tuberosity and provoked by sitting and by stretching the hamstring; often follows a previous hamstring injury or repair
- Site / cause
- Nerve compressed at or under the piriformis
- What separates it clinically
- Tenderness sits higher and more laterally in the buttock, and pain is provoked by resisted external rotation and passive internal rotation rather than by hamstring stretch
- Site / cause
- Quadratus femoris pinched between the lesser trochanter and the ischium
- What separates it clinically
- Pain on extension, adduction and external rotation (the long-stride position), with oedema in quadratus femoris and a narrowed ischiofemoral space on MRI
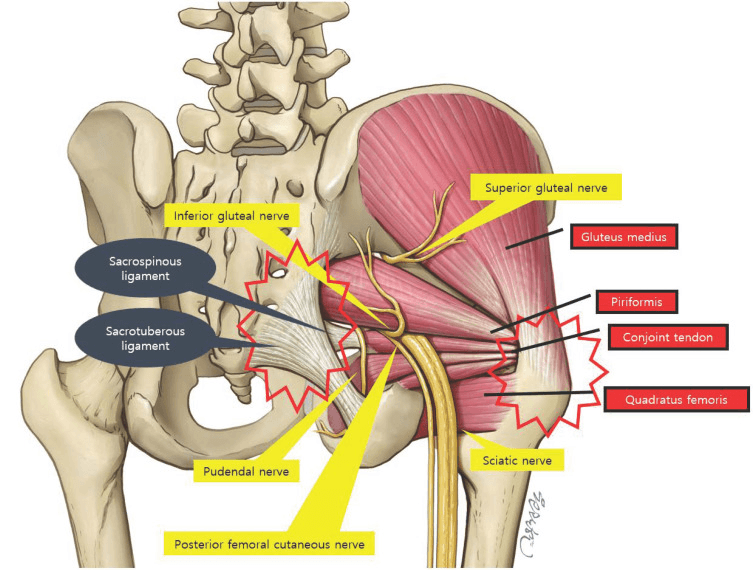
Presentation. Deep buttock pain radiates down the posterior thigh, worse on sitting and with stretching or sprinting, often with tenderness near the ischial tuberosity. It frequently coexists with proximal hamstring tendinopathy or follows a healed avulsion. The seated slump, Puranen-Orava and straight-leg-raise variants that tension the nerve reproduce the pain.
Investigation. MRI or MR neurography looks for perisciatic scarring and oedema at the ischium and excludes a space-occupying lesion. Lumbar radiculopathy (L5/S1) is the commonest mimic and must be excluded. An image-guided perineural injection of local anaesthetic is both diagnostic and therapeutic.
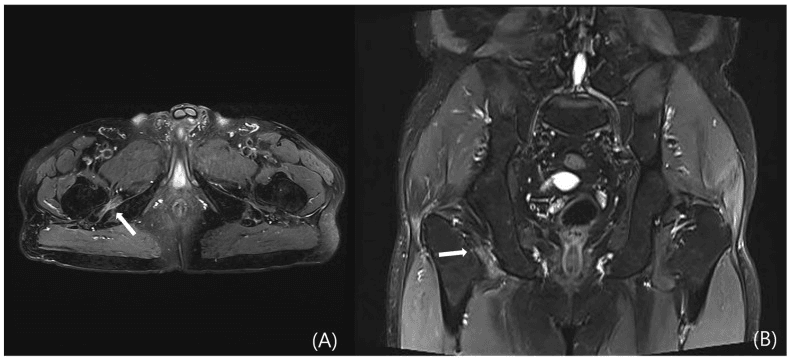
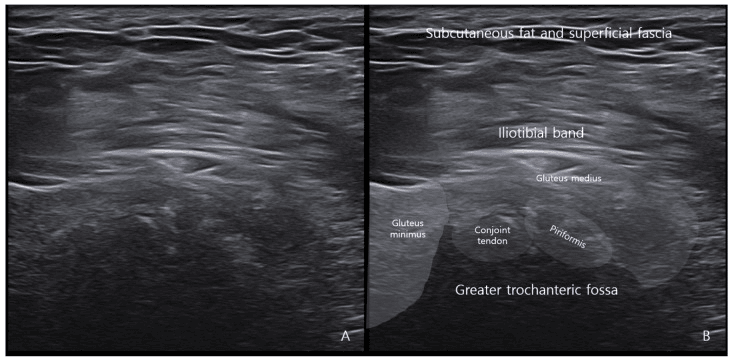
Management. Begin with diagnosis-specific rehabilitation, neural mobilisation when indicated, and load modification. Image-guided procedures are selective. Surgical decompression or neurolysis is reserved for demonstrated refractory nerve tethering or compressive pathology; chronic avulsion alone does not make neurolysis mandatory.
Management Algorithm
Group patients by the lesion and the person, not by a three-box calendar. The decision rests on repairability (tendon identity, quality, length and footprint), on activity and aims (the functional deficit, sport or work, and the patient's priorities), and on the rest of the picture: chronicity, nerve, bone, comorbidity and capacity to rehabilitate. Retraction alone does not decide it.
Timing is continuous. Retraction, shortening, scar and atrophy evolve over time, so later surgery is harder on average, and acute repair is technically easier (Wood 2020). Chronic repairs still improve SHORE scores (Wood 2020) and strength (Sallay 2008), and there is no validated cut-off beyond which repair becomes futile. Retraction, fatty atrophy and surgeon experience matter more than a calendar number, and calendar labels do not replace MRI morphology, repairability, nerve findings and goals.
Non-operative. Reasonable for many strains, partial or single-tendon injuries, selected complete tears, lower functional demands, and patients who prefer rehabilitation. Progressive loading is built around pain, strength and task tolerance; reassess if weakness, sitting pain or nerve symptoms persist.
Primary repair. Consider it for a functionally important, repairable proximal avulsion, after weighing the tendon pattern, retraction and tissue, the acute deficit, nerve symptoms, activity, comorbidity and goals. Earlier surgery may simplify mobilisation, but it is not an absolute eligibility window.
Chronic or revision. First define the scar, atrophy, repairability and any sciatic or posterior femoral cutaneous nerve pathology. Mobilisation may permit primary repair; graft augmentation and neurolysis are added only for a demonstrated gap or nerve tethering. Counsel about greater uncertainty and the morbidity of the procedure.
Surgical Technique
Open repair. The steps:
- Position prone, or in another configuration that permits safe access and controlled hip and knee motion
- Choose a transverse or longitudinal exposure from the tear level, retraction, body habitus, scar and planned nerve work
- Identify and protect the posterior femoral cutaneous and sciatic nerves as the exposure requires. Neurolysis is for tethering, scar or symptoms that justify the added dissection; unnecessary circumferential neurolysis is avoided
- Define the conjoint and semimembranosus components, mobilise viable tissue and prepare the ischial footprint without compromising bone
- Choose anchor number, configuration and suture pattern from the footprint, tendon quality and fixation strength rather than a universal count
- Reduce at safe tension, test fixation through the intended protected arc, and confirm the nerve is free before closure
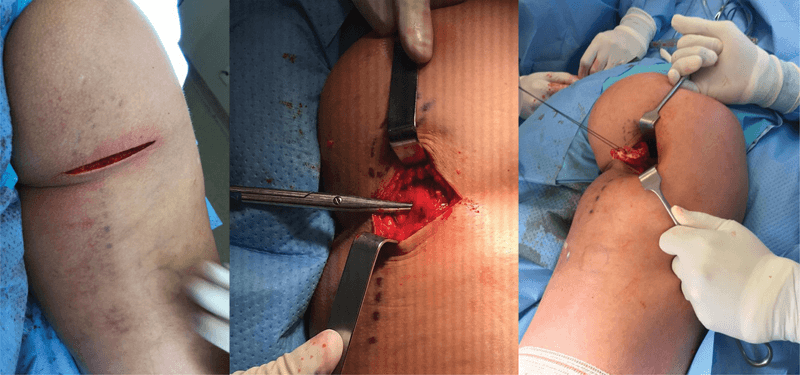
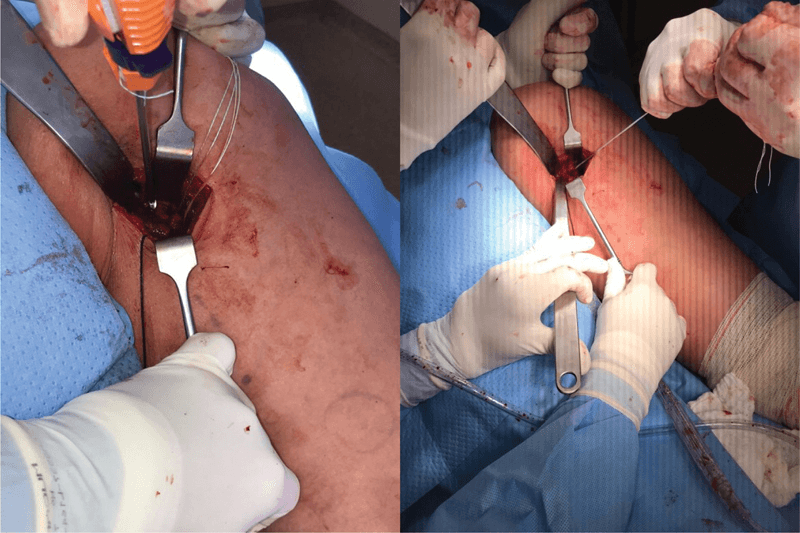
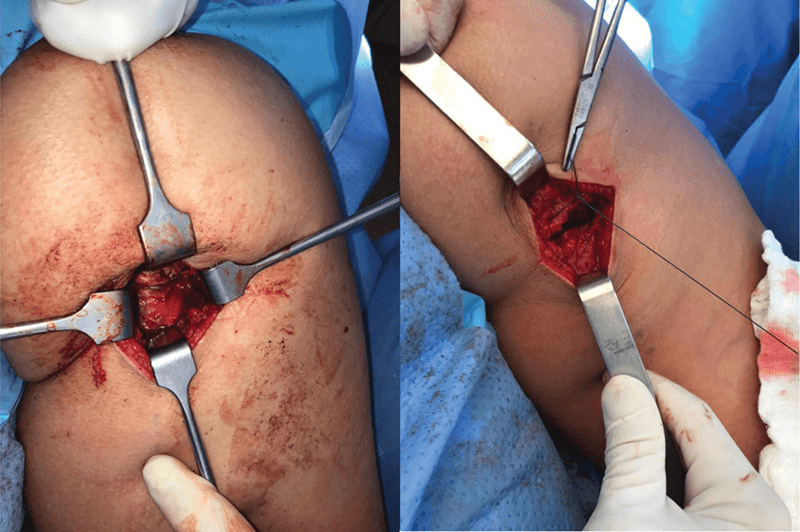
Chronic and revision repair. Mobilise scarred tissue carefully and judge whether it reaches the footprint without harmful tension. Autograft or allograft augmentation is added only when a real structural gap remains, with the graft and construct chosen on tissue, donor morbidity and surgeon expertise. Neurolysis is for adherent or symptomatic nerve pathology, not merely because the presentation is chronic.
Complications
- Sciatic nerve palsy - from stretch or direct injury, and most resolve. Its risk is unknown: the pooled figure for sciatic dysfunction after repair (Hillier-Smith and Paton, in the evidence below) depends on how each series counted it
- Recurrence - low, and a risk if rehabilitation is too aggressive
- Sitting pain - common, from scar tissue at the ischium (ischial bursitis)
- Wound breakdown - common; the gluteal fold is a high-tension, moist area
Postoperative Care
Rehabilitation is specific to the fixation, the tissue and the patient. The danger position is hip flexion combined with knee extension: while the repair is protected, rehabilitation avoids hip flexion beyond 90° and full knee extension, and does not combine them. Within that, the parameters are set case by case.
- Protection - weight-bearing, hip flexion, knee extension and brace use are set from repair tension, fixation strength, graft or nerve work and fall risk
- Motion - progress the combined hip-flexion and knee-extension arc without provoking repair pain or neural symptoms
- Load - move from low-load activation and isometrics to isotonic and eccentric strength, running and energy-storage tasks only when pain, control and strength permit
- Return - use task-specific strength, endurance, acceleration and confidence criteria rather than a universal six-month date
What to watch. Monitor the wound, sciatic and posterior femoral cutaneous nerve function, sitting tolerance, hip and knee motion, repair continuity and recurrence. A new or progressive neurological deficit, wound infection, loss of fixation or rerupture needs assessment of its specific cause, not an automatic three-month period of observation.
Outcomes and Prognosis
Outcomes vary with lesion definition, selection, chronicity, nerve involvement, tissue quality and rehabilitation. Most of the evidence is retrospective, and operative cohorts dominate it.
After repair. Many patients regain sport and useful strength, but pre-injury explosive performance is not guaranteed. Chronic repair can still improve pain and function.
After non-operative care. Appropriate patients can recover with progressive rehabilitation. Persistent weakness, cramping, sitting pain or nerve symptoms should prompt re-evaluation, rather than an assumption that every complete tear fails.
What predicts the result. Tendon identity, complete versus partial continuity, atrophy and fatty change, nerve injury, apophyseal nonunion and repair tension matter more than a single retraction distance.
What to measure. Track pain, sitting, strength and endurance, work or sport level, neurological symptoms, rerupture and the patient's goals, not only satisfaction or a return-to-sport percentage.
Guidelines, Registries & Global Practice
No AAOS, BOA or EFORT guideline defines a universal operative threshold, and national joint registries do not track proximal hamstring pathways. Evidence is dominated by retrospective series and meta-analyses with strong selection bias.
- Evidence-aware position
- MRI maps morphology; expert ultrasound is complementary
- Resource adaptation
- Ultrasound plus radiographs can triage when MRI access is limited
- Evidence-aware position
- Integrate anatomy, function, nerve and goals
- Resource adaptation
- Refer early when acute repairability may change
- Evidence-aware position
- Earlier is technically easier on average; no absolute expiry
- Resource adaptation
- Delayed cases need experienced repair/reconstruction assessment
- Evidence-aware position
- Brace/loading protocols follow construct and tissue
- Resource adaptation
- Criteria-based progression matters more than equipment
Controversies and Areas of Uncertainty
The two-tendon grey zone. A complete multi-tendon avulsion with substantial functional loss often prompts a discussion of repair, but tendon number and retraction do not create a universal threshold. Two-tendon and selected complete tears are decided on symptoms, demand, chronicity, nerve findings, tissue and patient preference.
To brace or not. Systematic-review data favour bracing for lower re-rupture (Wyatt 2024), yet brace-free accelerated protocols report acceptable results and better compliance. Protocols are so heterogeneous that the optimal regimen is not settled.
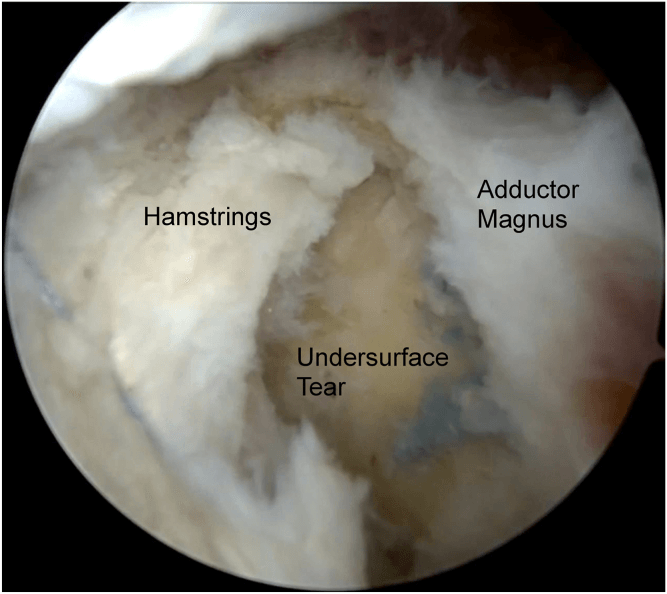
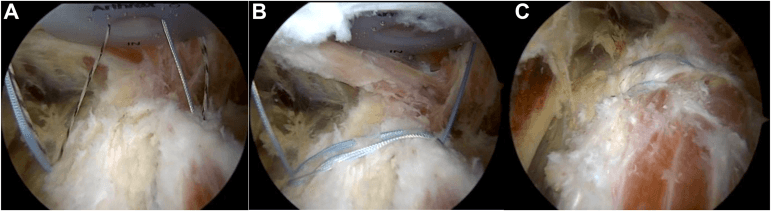
Endoscopic repair. Endoscopic and arthroscopic-assisted repair is emerging for partial and selected complete tears, but comparative evidence against open repair is limited and short-term. Open repair remains the reference standard for retracted complete avulsions.
MCQ Practice Points
Q: How should the sciatic nerve relation be described? A: It lies lateral/deep to the ischial origin, but distance, division and motor-branch patterns vary. Identify and protect it when the exposure or scar requires; do not memorise one centimetre value as universal.
Q: What must imaging report? A: Tendon identity, partial/complete continuity, retraction, tissue quality, haematoma, atrophy, bone injury and nerve-adjacent pathology. MRI is comprehensive; expert ultrasound adds dynamic assessment.
Q: What determines operative repair? A: Functional deficit, exact tendon pattern, repairability/tension, symptoms, chronicity, nerve findings, patient goals and rehabilitation capacity—not a universal tendon count or retraction distance.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“An active water-skier has an acute proximal hamstring avulsion with marked weakness and MRI-confirmed multitendon detachment. How do you decide treatment?”
“A runner has chronic proximal weakness and sitting pain with a retracted tendon stump. How do you plan?”
“An adolescent sprinter has an ischial apophyseal avulsion fracture. How do you choose between rehabilitation and fixation?”
Describe the Lesion
- Bone/apophysis versus tendon versus musculotendinous
- Conjoint and semimembranosus components
- Partial/complete continuity and tissue quality
- Retraction, atrophy and nerve-adjacent scar
Decision
- Functional deficit and symptoms
- Repairability and safe tension
- Activity/work goals and comorbidity
- No universal 2-cm or four-week rule
Surgery
- Protect sciatic and posterior femoral cutaneous nerves
- Restore exact components to footprint
- Use graft only for a structural gap
- Use neurolysis only for tethering or nerve pathology
Rehabilitation
- Protect the actual construct
- Restore hip-flexion/knee-extension arc progressively
- Build isotonic, eccentric and energy-storage capacity
- Return by task criteria, not a fixed month
Evidence Base
Avulsion of the Proximal Hamstring Origin (classification source)
- Complete avulsion is the dominant pattern (87.5%)
- Mean retraction 7cm (range 0-20cm)
- Delay makes repair harder and increases sciatic involvement and bracing need
- Source of the Wood classification used worldwide
Hamstring Injuries Among Water Skiers (landmark mechanism series)
- Defined the classic waterski mechanism
- Complete disruptions did worst non-operatively
- Persistent deficit drove delayed surgery in some
- Established the injury as functionally disabling
Operative vs Non-operative: Meta-analysis
- Repair beats non-operative on satisfaction and strength
- Acute repair superior to chronic
- Complication rate around 23% - counsel patients
- Non-operative comparison group was small (low certainty)
Outcomes of Surgical Management: Systematic Review and Meta-analysis
- Return to sport 84.5% at ~6.5 months
- Re-rupture only 1.2% overall
- Sciatic nerve dysfunction 3.5%, lower if acute
- Acute repair = quicker return, fewer re-ruptures
MRI vs Ultrasound for Avulsion Detection
- MRI sensitivity 16/16 for ischial avulsion
- Ultrasound less reliable (7/12)
- Imaging discriminates avulsion from strain
- Identifies who needs surgery vs conservative care
Timing of Repair (SHORE outcomes)
- Repair improves SHORE regardless of timing
- Earlier surgery = better recovery and more return to baseline
- Acute repair is shorter and technically easier
- Fewer neurological symptoms with acute repair
Bracing vs No Bracing After Repair
- Re-rupture much lower with bracing
- Higher satisfaction and return to sport when braced
- Evidence base is heterogeneous (level 4)
- Brace protocols remain the conservative default
Chronic and Acute Repair: Functional Recovery
- Strength keeps improving past 12 months
- Both acute and chronic repairs satisfied patients
- Suture-anchor fixation to ischium
- Chronic tears are still worth repairing