Criteria-Based | Psychological Readiness | Re-injury Prevention
- Criteria-based RTS is standard practice, but the often-quoted 84% reinjury reduction (Grindem 2016) was NOT statistically significant (p=0.075) - the significant findings were delay to 9 months and quadriceps symmetry
- Limb Symmetry Index (LSI) greater than 90% on hop tests and strength
- Hop test battery: single hop, triple hop, crossover hop, 6-metre timed hop
- Psychological readiness: ACL-RSI score greater than 70 associated with successful RTS
- Re-injury risk: Up to 25% in young athletes returning to high-level pivoting sport
- “Time alone is insufficient - criteria must be met
- “Fear of re-injury is major barrier to RTS
- “Quadriceps strength is most predictive single factor
- “ACL re-injury peak occurs 6-12 months post-RTS
Overview and Epidemiology
Return to sport (RTS) after orthopaedic injury or surgery is a decision that shapes re-injury risk and long-term outcome. Over the past two decades the traditional approach, clearing the athlete once enough time has passed, has given way to evidence-based, criteria-driven protocols. ACL reconstruction is the most extensively studied model, and its principles serve as the template for RTS across orthopaedic injuries.
The ACL model. ACL injury has a global incidence of roughly 30 to 80 per 100,000 person-years, several hundred per 100,000 in young pivoting-sport athletes, and the risk is 2 to 3 times higher in females. The return and re-injury rates that make the decision matter are set out under Complications and Prognosis.
A continuum, not an event. Return to sport runs through distinct phases:
- Return to participation: the athlete can take part in rehabilitation and modified training
- Return to sport: the athlete returns to sport activities, but may be at a reduced level
- Return to performance: the athlete performs at or above the pre-injury level
The summary above divides the same path into five phases, from injury through rehabilitation, return to training and return to competition to return to performance.
Time versus criteria. A time-based approach clears every patient on the same timeline, for example 9 months after ACL reconstruction, from clinical assessment and elapsed time; it often ignores or underemphasises psychological factors and rests on historical practice and weak evidence. A criteria-based approach clears the athlete when objective tests are met (LSI, hop tests, isokinetic strength, ACL-RSI), assesses psychology with validated scales, and is tailored to the individual's recovery. Its support comes from prospective studies, with the limits set out under Controversies.
Why time alone is insufficient. In multiple studies, time since surgery does not correlate with readiness:
- Athletes may achieve the criteria at different rates
- Tissue healing does not guarantee functional recovery
- Psychological readiness often lags behind physical recovery
Why time still counts. Criteria have not made the calendar irrelevant. Athletes who meet objective criteria before returning re-injure less, but the effect is softer than usually quoted, and in the cornerstone study the significant findings were delay to 9 months and quadriceps symmetry.
The significant findings were that reinjury fell 51% for each month RTS was delayed until 9 months and that quadriceps symmetry was protective. The famous 84% reduction from passing the criteria was a non-significant trend (HR 0.16, p=0.075).
Risk stratification. The activity the athlete is returning to sets how stringent the criteria must be before clearance, and helps set realistic expectations:
- High risk: pivoting sports (football, netball, basketball, skiing)
- Moderate risk: running, tennis, golf
- Low risk: swimming, cycling, gym work
Pathophysiology and Biological Rationale
The criteria-based timeline is grounded in tissue biology, neuromuscular recovery and psychological adaptation. Each lags behind symptomatic recovery, which is why "feeling ready" is insufficient.
Graft maturation. After ACL reconstruction the graft passes through avascular necrosis, revascularisation and remodelling (ligamentisation) over many months. Mechanical strength is lowest in the early remodelling phase, and the graft does not approach mature ligament properties until well beyond 12 months. This is the biological basis for why premature return, especially before 9 months, increases graft-rupture risk.
On MRI. Serial sagittal MRI at 6 weeks, 3 months, 6 months, 1 year and 2 years, compared with a native ACL, shows graft signal rising during early remodelling and then falling towards the native-ligament appearance.
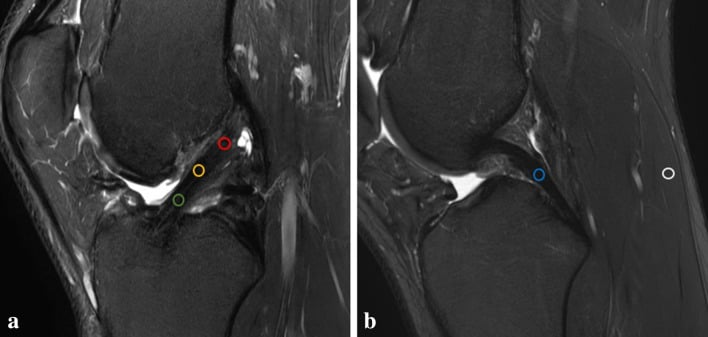
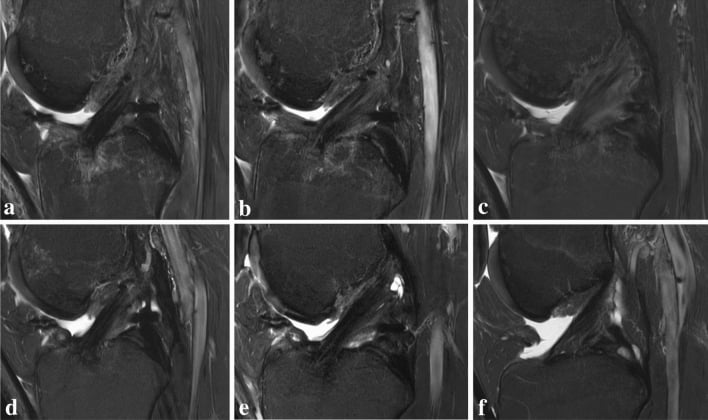
Neuromuscular deficits. Injury and surgery produce arthrogenic muscle inhibition and persistent quadriceps weakness, altered landing mechanics (dynamic knee valgus) and impaired postural control. These deficits independently predict second injury (Paterno 2010) and recover more slowly than range of motion or effusion.
Psychological adaptation. Fear of re-injury, reduced confidence and altered risk appraisal frequently persist after physical recovery and independently predict failure to return (Ardern 2013). Psychological readiness must therefore be tracked as a distinct biological-behavioural domain, not assumed from physical milestones.
Clinical Assessment and Functional Testing - The ACL Paradigm
Clinical examination. The following must be achieved before RTS is considered:
- Range of motion: full extension (0 degrees), flexion symmetric to the other side
- Effusion: none, the joint completely dry
- Stability: negative Lachman and negative pivot shift
- Pain: none with sport-specific activities
Functional milestones. Clinical recovery is followed by functional milestones:
- Full-speed running without symptoms
- Cutting and pivoting without apprehension
- Sport-specific drills at match intensity
- A completed graduated return-to-training programme
The hop battery. The four-hop test battery is the gold-standard functional assessment:
- Single hop for distance: maximum distance on a single-leg hop
- Triple hop for distance: total distance of three consecutive hops
- Crossover hop for distance: three hops crossing the midline alternately
- 6-metre timed hop: time to cover 6 metres hopping
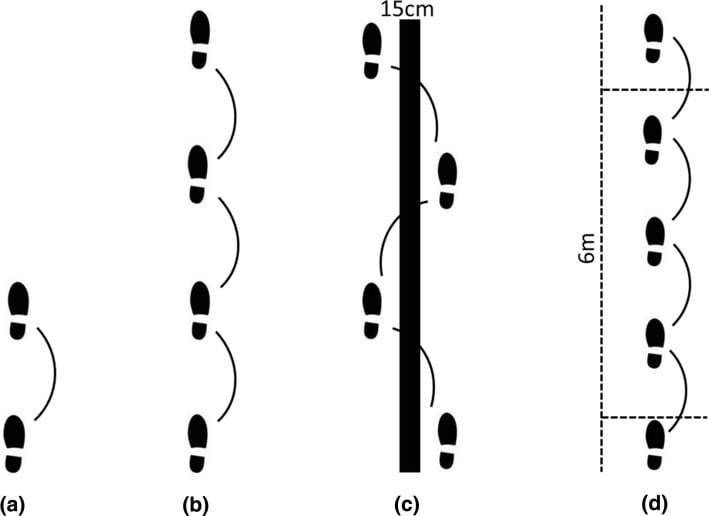
The Limb Symmetry Index. LSI is the involved leg divided by the uninvolved leg, times 100. The target is greater than 90% on all four hop tests, and greater than 95% is associated with lower re-injury rates. All four tests should be passed, not averaged.
Quantity is not quality. Hop tests measure how far and how fast, not how well. Movement-quality assessment (landing mechanics, valgus control) should supplement hop testing, and video analysis of the hop adds information about movement patterns.

Neuromuscular control. These tests evaluate neuromuscular control and proprioception, which are critical for injury prevention and should be part of comprehensive RTS testing:
- Y-balance test or Star Excursion Balance Test
- Drop-jump landing assessment (valgus control)
- Single-leg balance with perturbation
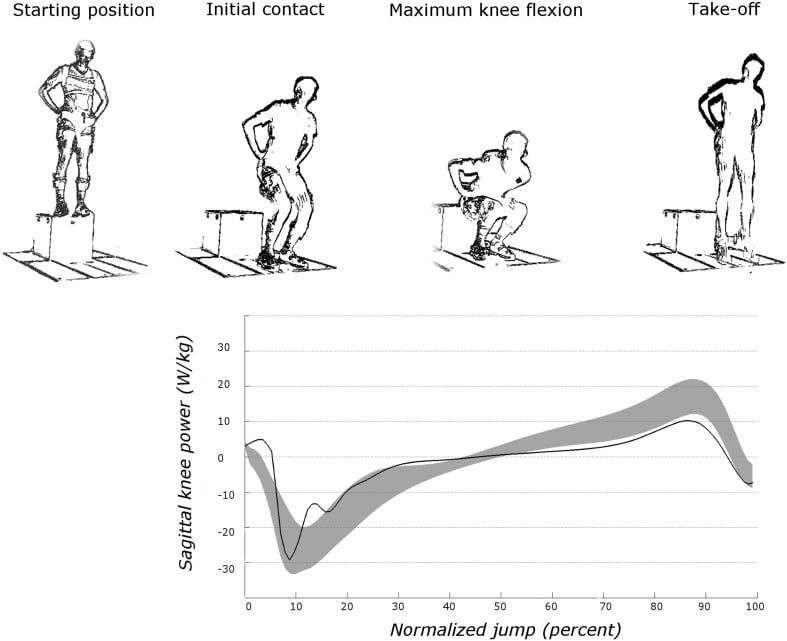
Strength. Isokinetic dynamometry gives an objective measure of quadriceps and hamstring peak torque at 60 degrees/second. The targets are a quadriceps LSI greater than 90% (ideally greater than 95%), a hamstring LSI greater than 90%, and a hamstring-to-quadriceps (H:Q) ratio greater than 60%. Quadriceps strength is the single most predictive factor for successful RTS, and quadriceps weakness at return is associated with both re-injury and osteoarthritis, so restoring it is critical.
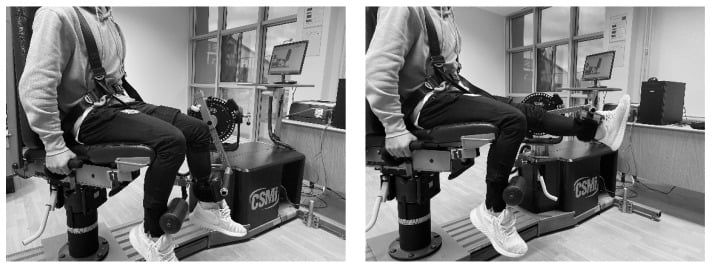
Without a dynamometer. When isokinetic testing is unavailable, clinical alternatives compare the limbs:
- Single-leg press one-repetition maximum
- Single-leg squat depth and quality
- Step-down tests with quality assessment
Both legs weak. LSI assumes the uninvolved limb is a valid reference, but after injury and surgery that limb often deconditions too (reduced training, cross-education effects). An athlete can therefore reach 90% symmetry while both limbs are weak, and LSI overestimates true recovery.
Avoiding the pitfall. Where possible, compare with pre-injury (baseline) values or an estimated pre-injury capacity, or with normative population data, and express strength relative to body mass (for example quadriceps peak torque in newton-metres per kilogram). Use LSI as a screen, confirm that the absolute strength and not just the symmetry is adequate, and always pair it with a movement-quality assessment.
The criteria gather into one mnemonic for the clinic and the viva.
SHARPRTS Criteria Components
Hook:SHARP criteria = SHARP return to sport without re-injury!
Investigation of Psychological Readiness
Psychological factors are increasingly recognised as critical determinants of successful return.
The ACL-RSI. The ACL Return to Sport after Injury scale is a 12-item validated questionnaire covering emotions (confidence, fear, frustration), confidence in performance, and risk appraisal (perceived re-injury risk). It scores 0 to 100, higher being more ready. A score greater than 70 is associated with successful RTS; a score less than 56 is associated with failure to return.
Using it. Administer it at rehabilitation milestones and track it longitudinally, both to identify athletes who need psychological intervention and to weigh it in the decision alongside the physical criteria. An athlete with a low score despite meeting the physical criteria should be considered for psychology referral and may benefit from a delayed return.
Fear of re-injury. Fear is the most commonly cited barrier to return and the most significant psychological one, given by 50% of athletes as their reason for not returning. It persists even after successful physical rehabilitation and is associated with altered, protective movement patterns (guarding), which may raise the actual re-injury risk through compensatory movement. Early identification of high-fear athletes allows targeted intervention and realistic counselling on the timeline.
The Tampa Scale of Kinesiophobia. A 17-item questionnaire measuring movement-related fear. It was developed for chronic pain populations and adapted for sports injury; higher scores mean greater kinesiophobia.
Improving readiness. Psychological readiness can be actively improved:
- Goal setting: short-term, achievable rehabilitation goals, process goals as well as outcome goals, and celebrating milestones through recovery
- Graded exposure: progressive exposure to sport-specific activities, and a graded return to training and then competition
- Imagery and visualisation: mental rehearsal of a successful return, positive visualisation of performance, and stress inoculation through imagined challenging scenarios
- Cognitive restructuring: addressing catastrophic thinking about re-injury, education towards a realistic appraisal of risk, and a focus on controllable factors (training, preparation)
- Team involvement: keeping the connection with teammates during rehabilitation, gradual reintegration into team training, coach and team support, and peer support from athletes who have returned successfully
Sports psychology referral is recommended for persistent fear, anxiety or depression during rehabilitation, particularly with low ACL-RSI scores.
Management and RTS Criteria Across Other Injuries
ACL reconstruction is the paradigm, but the same principles apply to other injuries with condition-specific modifications.
Operative or not. Surgical stabilisation in athletes has a lower recurrence rate, 10-15% against 50-70%. RTS is typically 4-6 months after Latarjet and 5-6 months after Bankart repair.
Criteria for return. They cover four domains:
- Range of motion: full and symmetric, especially external rotation
- Strength: isokinetic LSI greater than 90% (rotator cuff, deltoid)
- Apprehension: a negative apprehension test is critical
- Function: sport-specific overhead or contact activities
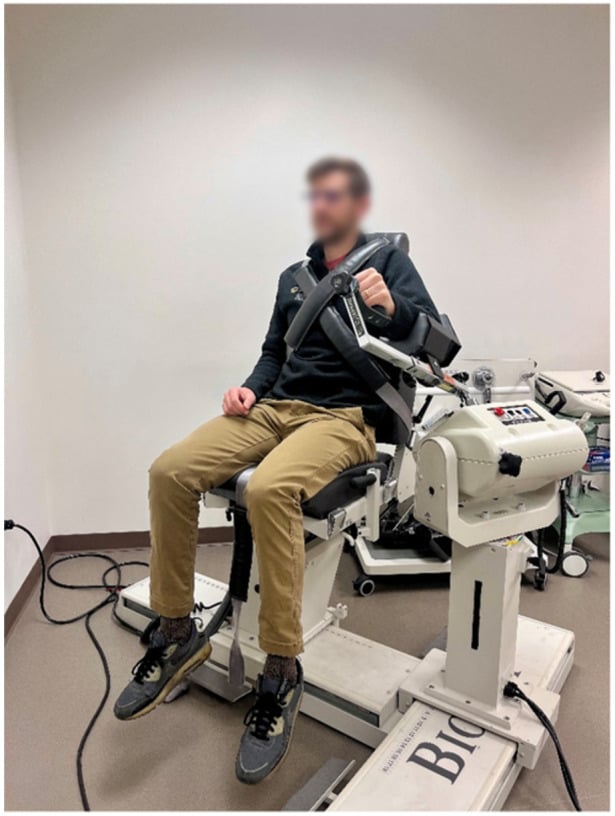
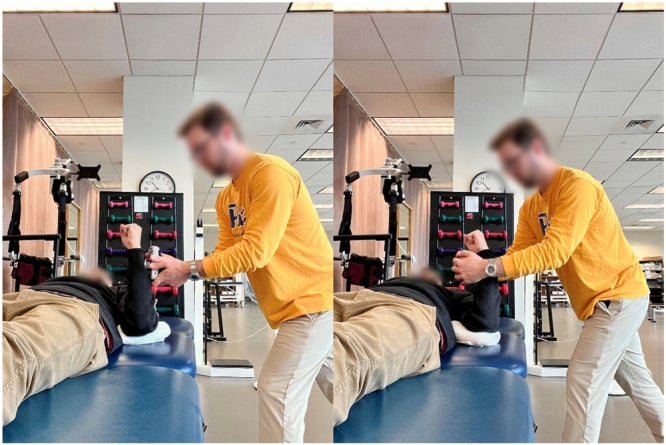
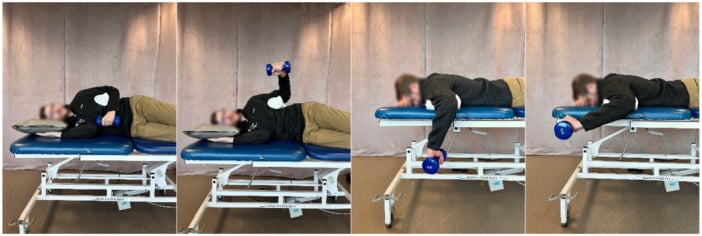


Outcome measures. Three scores are in use:
- Rowe score: a 100-point scale for shoulder instability outcomes
- WOSI (Western Ontario Shoulder Instability Index): a quality-of-life measure
- Athletic Shoulder Outcome Score (ASES)
The sport decides the emphasis. Overhead athletes (swimmers, throwers) need external rotation and overhead stability; contact athletes (rugby, football) need impact tolerance, and collision sports may require bracing at first. Psychological readiness is less studied in shoulder instability, but fear of the apprehension position should be addressed during rehabilitation.
Complications and Prognosis
Premature or poorly assessed return carries quantifiable harms; the prognosis after a well-executed criteria-based return is correspondingly better.
What goes wrong.
- Second ACL injury: graft rupture or a second ACL injury, ipsilateral or contralateral, in up to ~23% of young athletes returning to pivoting sport, nearly one in four (Wiggins 2016), and 4-fold higher if discharge criteria are not met (Kyritsis 2016)
- Contralateral ACL injury: roughly equal to the ipsilateral risk (~8% against ~7% overall; Wiggins 2016), reflecting systemic neuromuscular and biomechanical risk factors, not just the graft
- Post-traumatic osteoarthritis: persistent quadriceps weakness and repeated injury accelerate cartilage degeneration
- Failure to return: despite surgery, only about 65% reach their pre-injury level and ~55% return to competitive sport (Ardern 2014); psychological non-readiness is a leading driver
- Recurrent muscle strain: hamstring re-injury runs up to ~30% when return precedes restored eccentric strength and symmetry
Who re-injures. The risk factors for a second injury:
- Young age: under 20 years carries the highest risk
- Early return: before 9 months after ACL reconstruction
- Return to pivoting sport
- LSI below 90%
- Not meeting the criteria
Ready or not. The domains of the decision, side by side:
- Ready for RTS
- LSI greater than 90% (ideally greater than 95%)
- Not Ready (delay / intervene)
- LSI less than 90% - targeted strengthening, retest
- Ready for RTS
- All four tests LSI greater than 90%
- Not Ready (delay / intervene)
- Any single test LSI less than 90% (not averaged)
- Ready for RTS
- Controlled landing, no dynamic valgus
- Not Ready (delay / intervene)
- Dynamic knee valgus, hip drop, trunk lean
- Ready for RTS
- ACL-RSI greater than 70
- Not Ready (delay / intervene)
- ACL-RSI less than 56 - psychology referral, graded exposure
- Ready for RTS
- Full extension, no effusion, stable
- Not Ready (delay / intervene)
- Effusion, extension deficit, instability
- Ready for RTS
- Completed graded return to training at match intensity
- Not Ready (delay / intervene)
- Not yet exposed to cutting/pivoting at full intensity
Guidelines, Registries & Global Practice
Return to sport is a worldwide clinical problem. ACL injury - the most studied RTS model - has a global incidence of roughly 30 to 80 per 100,000 person-years, rising to several hundred per 100,000 in young athletes playing pivoting sports (football/soccer, basketball, netball, handball, alpine skiing, Australian football, rugby). Female athletes carry a 2 to 3 times higher ACL injury risk than males in equivalent sports. No single national approach dominates; recommendations converge on a criteria-based, biopsychosocial continuum.
Side-by-side guidance on RTS after ACL reconstruction:
- Key Position
- RTS is a continuum; use StARRT risk framework and a biopsychosocial model; shared decision between clinician, athlete and coach
- Key Position
- Supports rehabilitation and objective functional testing; notes limited high-level evidence for any single time-based threshold
- Key Position
- Endorses criteria-based progression, psychological readiness assessment and shared decision-making rather than fixed timelines
- Key Position
- Battery of discharge criteria (isokinetic strength, hop battery, running) before team training; basis of the Kyritsis 4x-risk data
- Key Position
- Emphasise standardised outcome reporting, shared decision-making and that no validated single criterion guarantees safe RTS
The common thread across AAOS, BOA, AO/AOSSM, EFORT-aligned European groups and the IOC is convergence on objective criteria plus psychological readiness, with explicit acknowledgement that the evidence base for precise thresholds remains limited.
Bern (international), AAOS, BOA/BASEM, Aspetar and IOC consensus all favour a criteria-based, biopsychosocial continuum over fixed time thresholds.
Hop battery, single-leg strength symmetry and the paper-based ACL-RSI deliver valid criteria-based RTS even without isokinetic dynamometry.
Related pages: ACL Injuries is the injury almost every criterion on this page was derived from, and the graft-maturation biology there is what the 9-month figure is really about. Meniscal Repair and Meniscal Root Tears change the timeline more than the ligament does - a repaired meniscus imposes its own loading restrictions that override a passed hop battery. Hamstring Injuries is the counter-example worth knowing: a muscle injury with high recurrence where the criteria are eccentric strength and length, not symmetry indices, and where returning on time rather than on criteria is most obviously punished. Lateral Ankle Sprains and Achilles Tendon Rupture show how differently the same framework behaves in a joint that heals fast and a tendon that does not. Concussion in Athletes is the one return-to-play pathway that is genuinely protocolised and mandatory rather than advisory, which is instructive about what a real graduated return looks like. Anterior Shoulder Instability and Patellofemoral Instability are the upper-limb and extensor-mechanism versions of the same recurrence problem in young athletes. Osteochondritis Dissecans of the Knee is the lesion that must be excluded before persistent post-return knee pain is attributed to deconditioning.
Controversies and Areas of Uncertainty
There is broad consensus on a criteria-based continuum, but several questions remain unresolved and are favourite viva discussion points.
- The LSI threshold: 90% is conventional, but the index can be falsely reassuring when both legs are weak (above), and some advocate comparison with pre-injury or normative values, or estimated pre-injury capacity, instead of simple limb symmetry
- No single validated battery: the commonly used criteria are not prospectively validated against a definitive threshold (Bern consensus, Kyritsis), and different centres use different cut-offs
- Timing against criteria: Grindem suggests both matter (delay to 9 months and criteria), so the relative weight of calendar time and function is debated
- Psychological cut-offs: the ACL-RSI thresholds (greater than 70 favourable, less than 56 unfavourable) are associations, not validated decision rules, and the best instrument is unsettled
- Imaging and graft maturation: MRI signal and ligamentisation status are not reliable RTS criteria, and their predictive value remains uncertain
- Generalisability beyond the ACL: hop and strength symmetry criteria are extrapolated to shoulder, ankle and muscle injuries with limited high-level evidence
- Lateral extra-articular tenodesis: whether adjunct procedures lower the young-athlete reinjury rate enough to alter RTS counselling continues to be studied
The StARRT Framework in Three Steps
StARRT (Strategic Assessment of Risk and Risk Tolerance, Shrier) structures the clearance decision. Steps 1 and 2 together define the risk of re-injury; step 3 modifies the decision, not the risk. The risk is then weighed against the tolerance in a shared decision.
- Tissue health: the medical and tissue factors, healing status, strength, range of motion, pain, effusion and, where relevant, imaging. How healthy is the tissue?
- Tissue stress: the load the specific sport, position and level would place on that tissue, and whether it can be protected (bracing, taping)
- Risk-tolerance modifiers: the non-medical factors that change how much risk is acceptable, namely timing (season, championship), pressure (athlete, coach, family), the ability to mask the injury (painkillers and injections are a hazard) and the decision-maker's conflict of interest
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 22-year-old netball player is 9 months post-ACL reconstruction with hamstring autograft. She wants to return to competitive netball. How do you assess if she is ready?”
“The same netball player has hop test LSI of 85% and quadriceps LSI of 82% at 9 months. She is frustrated and says her friend returned at 6 months. How do you counsel her?”
“A 25-year-old footballer has passed all physical criteria at 10 months post-ACL reconstruction but says he is terrified of re-injury and does not feel ready. His ACL-RSI score is 48. How do you manage this?”
Criteria-Based RTS (SHARP)
- Strength: Isokinetic quad LSI greater than 90%
- Hop tests: Single, triple, crossover, timed LSI greater than 90%
- Absence of symptoms: No pain, effusion, instability
- Range of motion: Full extension, symmetric flexion
- Psychological: ACL-RSI greater than 70
Psychological Readiness
- ACL-RSI scale: 0-100, target greater than 70
- Score less than 56 associated with failure to RTS
- Fear of re-injury most common barrier (50%)
- Tampa Scale of Kinesiophobia also used
Re-injury Risk Factors
- Young age (less than 20 years) highest risk
- Return to pivoting sports
- RTS before criteria met (4x risk)
- Up to 25% second ACL injury in young athletes
Evidence Base
Grindem et al (Delaware-Oslo ACL Cohort)
- Prospective 2-year cohort of 106 pivoting-sport athletes after ACL reconstruction
- SIGNIFICANT: returning to level I (pivoting) sport carried a 4.32-fold higher reinjury rate (p=0.048)
- SIGNIFICANT: the reinjury rate fell by 51% for each month RTS was delayed until 9 months - after which NO further risk reduction was seen
- SIGNIFICANT: more symmetrical quadriceps strength before return reduced the reinjury rate
- NOT SIGNIFICANT: 38.2% of those who failed the criteria reinjured versus 5.6% of those who passed - HR 0.16, p=0.075. The famous '84%' in the paper's title is 1 minus that hazard ratio, and it did not reach statistical significance
Kyritsis et al (Aspetar)
- 158 male professional athletes; 16.5% sustained graft rupture (mean 105 days after RTS)
- Not meeting all 6 discharge criteria gave a 4-fold higher graft-rupture risk (HR 4.1)
- Reduced hamstring-to-quadriceps ratio of the involved leg also raised rupture risk
- Criteria: isokinetic strength, running t-test, single/triple/triple-crossover hop