Retrograde Blood Supply | High Nonunion Risk | Anatomic Snuffbox Tenderness
- Retrograde blood supply - enters at the dorsal ridge near the waist, so the proximal pole is downstream of every waist and proximal pole fracture
- Waist fractures are most common (70%) and account for most nonunions in absolute numbers
- Proximal pole fractures have the highest nonunion and AVN rates
- Anatomic snuffbox and tubercle tenderness after a fall on the outstretched hand is a fracture until proven otherwise
- If suspected but X-ray negative - immobilise and re-image, or get an MRI
- “Dorsal carpal branch of the radial artery supplies 70-80% of the bone and the entire proximal pole
- “SWIFFT: waist fractures displaced 2mm or less do as well in a cast, with fixation reserved for confirmed nonunion
- “Displacement over 1mm, angulation over 15°, proximal pole, comminution or perilunate injury = unstable = fixation
- “Headless compression screw along the central axis allows early motion without a cast
Overview and Epidemiology
The scaphoid is the most common carpal fracture, about 70% of them, and the second most common fracture at the wrist after the distal radius. It matters out of proportion to its frequency because of its high risk of nonunion and avascular necrosis, and a nonunion eventually costs the whole wrist.
Mechanism. A fall on the outstretched hand with the wrist dorsiflexed and radially deviated. The load passes through the thenar eminence and compresses the scaphoid between the radius and the capitate.
- FOOSH - by far the most common
- Sports injuries - young males
- Motor vehicle accidents
Who. A young man aged 15-30, hurt playing sport or in a fall. In one large UK series 365 of 415 fractures were in males, peaking at 15-19 years. Be suspicious of any young person with radial-sided wrist pain after a fall.
Where. Location predicts prognosis:
- Waist - 70%. Most common, and the largest absolute number of nonunions simply because there are so many.
- Proximal pole - 20%. Highest nonunion and AVN rates. The blood supply explains why.
- Distal pole and tubercle - 10%. Almost always heal.
Anatomy and Blood Supply
The bone. Boat-shaped (Greek skaphe, a boat), set obliquely in both the coronal and sagittal planes, and about 80% covered by articular cartilage, which leaves few places for blood to enter. It links the proximal and distal carpal rows, so a scaphoid that shortens or fails to unite changes the mechanics of the whole carpus.
- Proximal: radius (scaphoid fossa)
- Distal: trapezium and trapezoid
- Ulnar side: lunate and capitate
- Forms the floor of the anatomic snuffbox; the tubercle is palpable on the palmar side
The blood supply. Branches of the radial artery enter through the dorsal ridge near the waist and supply 70-80% of the bone and the entire proximal pole. Palmar branches enter at the tubercle and feed only the distal 20-30%. The proximal pole has no vessel of its own: its blood arrives through the waist, flowing from distal to proximal, the reverse of most bones, which is what "retrograde" means.
Why it matters. A waist fracture lies across the only route into the proximal pole, so the proximal fragment is the one stranded, and the one that dies.
- The more proximal the fracture, the smaller the fragment downstream and the higher the risk of nonunion and AVN
- Displacement tears the intraosseous vessels as well, so displaced fractures heal less reliably
- The scaphoid takes longer to unite than its neighbours
- Collateral flow from the anterior interosseous artery is why many proximal pole fractures do not go on to necrosis (Gelberman): the retrograde supply raises the risk, it does not seal the fate
Blood enters at the dorsal ridge near the waist and flows proximally; the proximal pole has no direct supply, so every waist or proximal fracture puts it at risk, and the more proximal the fracture, the greater the risk.
Classification Systems
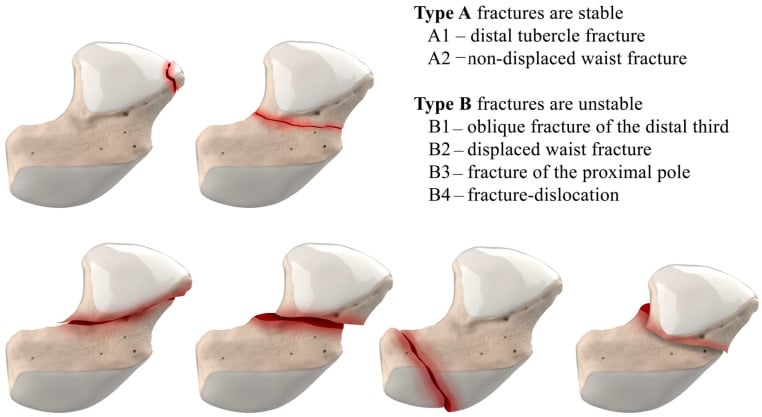
Herbert's classification is the shared language. The letter tells you the treatment: A is stable and can be cast, B is unstable and is fixed, C has failed to unite on time, D has failed altogether. It was published by the designer of the screw it was used to justify, without reliability testing, and observers disagree about exactly the A-versus-B boundary that drives the operative decision. Use it to describe the fracture, then decide on the fracture in front of you.
- Subtype
- Description
- Stable acute fractures
- Subtype
- A1
- Description
- Fracture of tubercle
- Subtype
- A2
- Description
- Incomplete fracture through waist
- Subtype
- Description
- Unstable acute fractures
- Subtype
- B1
- Description
- Distal oblique fracture
- Subtype
- B2
- Description
- Complete fracture of waist
- Subtype
- B3
- Description
- Proximal pole fracture
- Subtype
- B4
- Description
- Trans-scaphoid perilunate dislocation
- Subtype
- B5
- Description
- Comminuted fractures
- Subtype
- Description
- Delayed union
- Subtype
- Description
- Established nonunion
- Subtype
- D1
- Description
- Fibrous nonunion
- Subtype
- D2
- Description
- Pseudarthrosis
Type B is defined by any one of displacement, a proximal pole location, an oblique line, or an associated perilunate injury.
Clinical Presentation and Assessment
History. The mechanism is usually a fall on the outstretched hand. The answers that change management:
- Time since injury - delay costs union
- Hand dominance and occupation - decides what a long cast will cost the patient
- Smoking - impairs healing
- Previous wrist injury
Examination. Swelling is often slight, far less than a distal radius fracture produces, and the diagnosis rests on where it hurts. Snuffbox tenderness is the classic sign and about 90% sensitive, but the snuffbox is tender after many wrist injuries; tubercle tenderness is as sensitive and more specific. A patient with the right mechanism who is tender in both the snuffbox and over the tubercle has a scaphoid fracture until imaging says otherwise, whatever the first radiograph shows.
- Test
- Palpate between EPL and EPB/APL
- Significance
- Classic sign, 90% sensitive
- Test
- Palpate palmarly at wrist crease
- Significance
- Equally sensitive, more specific
- Test
- Compress thumb metacarpal
- Significance
- Scaphoid compression test
- Test
- Watson test component
- Significance
- Suggests scaphoid involvement
- Test
- Compare to contralateral
- Significance
- May indicate fracture
- Test
- Observe/palpate
- Significance
- Less obvious than other wrist fractures
Watson's test looks for scapholunate ligament injury or instability. Press on the scaphoid tubercle while bringing the wrist from ulnar to radial deviation; a clunk or pain is positive.
- Discriminating features
- Snuffbox AND tubercle tenderness, pain on axial thumb compression, FOOSH
- Key investigation
- Scaphoid-series radiographs; MRI if occult
- Discriminating features
- More diffuse swelling, dorsal/volar deformity, tenderness over distal radius not snuffbox
- Key investigation
- PA and lateral wrist radiographs
- Discriminating features
- Dorsal SL-interval tenderness, positive Watson test/clunk, SL gap on clenched-fist view
- Key investigation
- Stress/clenched-fist radiographs, MRI or arthroscopy
- Discriminating features
- Tenderness localised away from the scaphoid; dorsal triquetral flake on lateral view
- Key investigation
- Oblique/lateral radiographs, CT
- Discriminating features
- Pain at thumb base with grind test, distal to snuffbox
- Key investigation
- Thumb radiographs
- Discriminating features
- Subacute onset, no acute trauma, positive Finkelstein test, tenderness over first dorsal compartment
- Key investigation
- Clinical; ultrasound if uncertain
- Discriminating features
- Tenderness not localising to scaphoid or SL interval, normal advanced imaging
- Key investigation
- MRI to exclude occult fracture before labelling
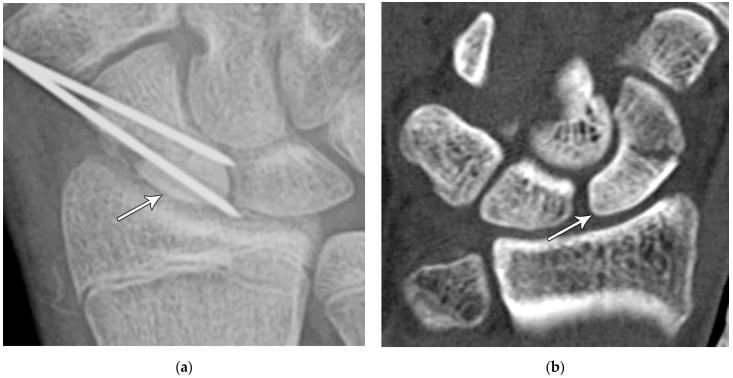
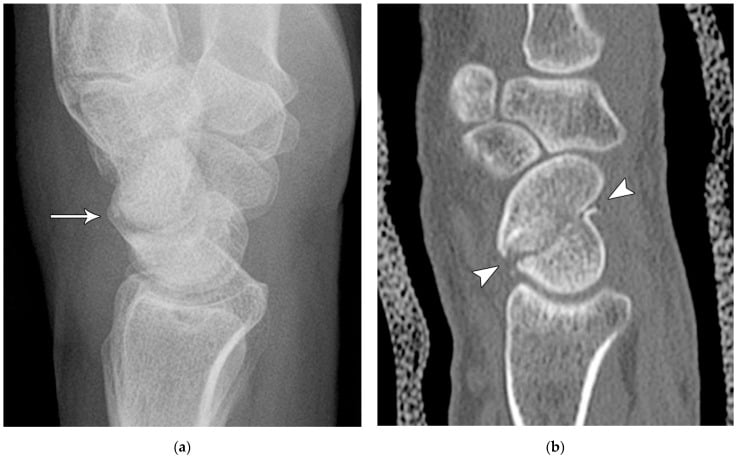
A two-piece scaphoid on the film of a tender wrist: acute fracture, old nonunion, or the rare and disputed congenital bipartite scaphoid? Calling a variant a fracture, or missing a real nonunion, both cause harm.
- Favours a true variant: bilateral and symmetrical; two fragments of roughly equal size with smooth, rounded, well-corticated margins and no lucent line between them; no sclerosis, cysts or marrow oedema; an asymptomatic patient in whom the finding is incidental.
- Favours a fracture or nonunion (the far commoner reality): a sharp or irregular uncorticated line; unequal fragments; sclerosis, cysts or resorption at the margins; oedema on MRI; a history of trauma; focal tenderness.
- The caution: most apparent bipartite scaphoids are old ununited fractures. If there is any doubt, and always if the wrist is symptomatic or the finding is unilateral, image the other wrist for comparison and obtain an MRI or CT before calling it a variant.
Investigations
Radiographs. Request a scaphoid series, not a wrist series. The fracture line moves in and out of view as the projection changes, which is why one view is never enough:
- PA in ulnar deviation - elongates the scaphoid
- Lateral - angulation and the DISI pattern
- 45° semi-pronated oblique - profiles the bone
- AP with clenched fist - shows displacement
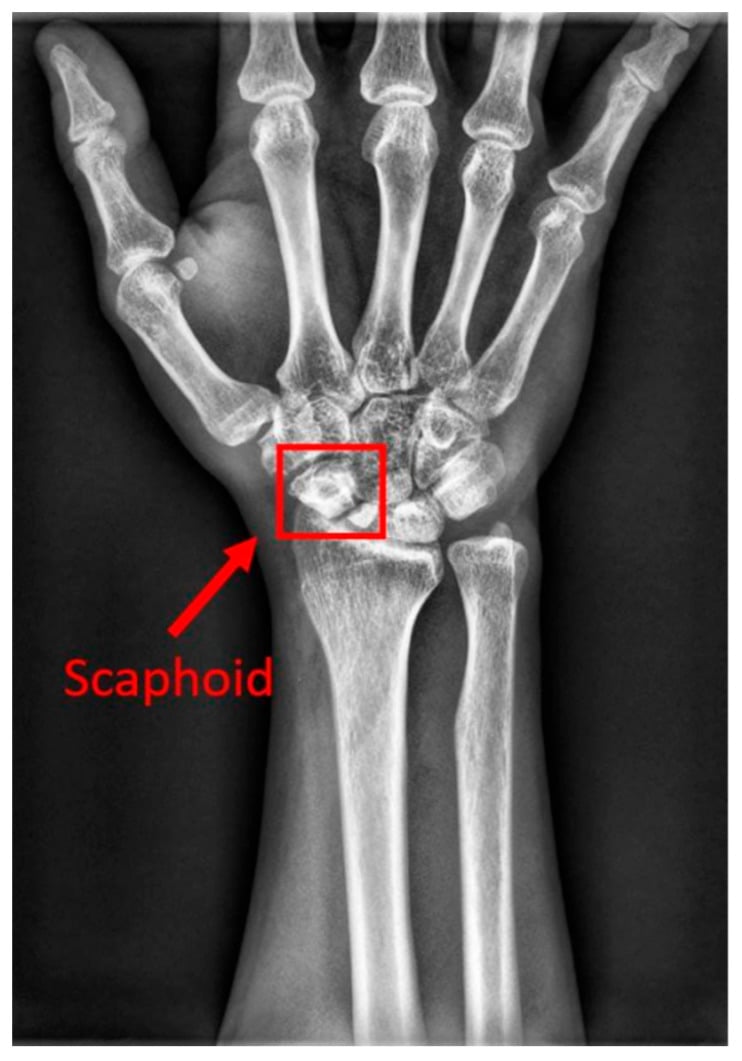

The occult fracture. Between 10 and 20% of scaphoid fractures are not visible on the first films. That fact shapes the whole pathway. When the mechanism and examination are convincing and the radiographs are normal, there are two honest options:
- Treat as a fracture: thumb spica, repeat films at 10-14 days, by which time resorption at the fracture edges has usually made the line visible
- Image now: MRI, or CT once a fracture is confirmed, to characterise it for treatment
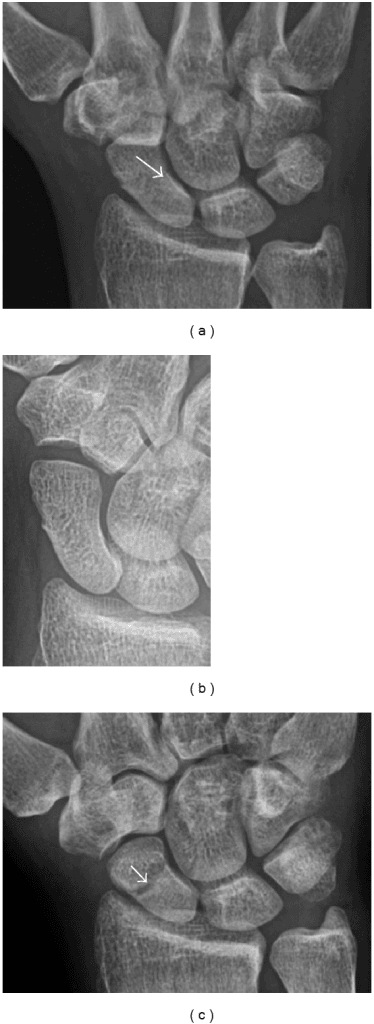
MRI is the practical first-line test for the occult fracture. It shows marrow oedema before any line appears, picks up the ligament injuries and other carpal fractures that mimic a scaphoid fracture, and with gadolinium can assess the vascularity of the proximal pole.
CT characterises a fracture you already know is there: displacement and angulation measured precisely, union or nonunion judged, and the planning study before surgery.
Bone scintigraphy is the most sensitive of the three and the least specific. It turns positive within about 72 hours, earlier than radiographic change, but that means it cannot be done at once, and it needs a radiotracer injection and carries a radiation dose.
A negative MRI does not definitively exclude a scaphoid fracture, and "MRI is 100% sensitive" is not what the evidence shows. The Cochrane review by Yin and colleagues pooled 11 studies of patients with a clinically suspected fracture and normal radiographs (DOI): 5 MRI studies (221 suspected fractures), 4 CT studies (277) and 6 bone-scintigraphy studies (543). Summary sensitivity was 0.88 for MRI (95% CI 0.64-0.97), 0.72 for CT (0.36-0.92) and 0.99 for bone scintigraphy (0.69-1.00). Specificity ran the other way: 1.00 for MRI (0.38-1.00), 0.99 for CT (0.71-1.00) and 0.86 for bone scintigraphy (0.73-0.94).
Read that in the right direction. A positive MRI can be trusted; a negative one misses roughly one fracture in eight, so a wrist that is still clinically convincing after a normal MRI stays immobilised and is reviewed rather than discharged. The authors' own arithmetic makes the trade-off concrete: in 1,000 suspected fractures, bone scintigraphy would miss 2 fractures but over-treat 112, whereas CT would over-treat only 8 but miss 56. The confidence intervals are wide for every test, the MRI sensitivity interval spanning 0.64 to 0.97, which is why clinical judgement rather than a single scan governs the decision to stop immobilising.
Cost. Modelling favours immediate MRI or CT over empiric casting with repeat radiographs: advanced imaging was cheaper overall and produced better outcomes, and empiric casting only won if the scan cost more than about $2000 or its sensitivity fell below 25-32%. Where advanced imaging is not readily available, thumb-spica immobilisation with re-imaging at 10-14 days remains common and acceptable practice.
- Lateral intrascaphoid angle (LISA): the angle between the proximal and distal articular surfaces. Normal is roughly thirty to forty degrees; an angle over about forty-five degrees indicates significant flexion (humpback) collapse.
- Dorsal cortical angle: measured along the dorsal cortex; normal is around 140 degrees, with a smaller (more acute) angle as the scaphoid flexes - a more reproducible measure than the LISA, which has high inter-observer variability.
- Height-to-length ratio: scaphoid height divided by length; a ratio over about 0.65 signals loss of length with dorsal collapse.
- Carpal alignment: a flexed (foreshortened) scaphoid drags the lunate into extension - a DISI pattern (radiolunate angle over about fifteen degrees, scapholunate angle over about sixty degrees) - which is the carpal consequence of the humpback.
Exam point: a flexed scaphoid with a LISA over forty-five degrees / height-to-length ratio over 0.65 / DISI malalignment is a true humpback deformity that needs length and alignment restored with a volar opening-wedge (Fisk-Fernandez) graft, not just a simple inlay graft.
Management
The decision. Stability, location and the patient. A stable fracture (Herbert A) heals in a cast; an unstable one heals unreliably in a cast and is fixed. The difficult middle ground is the undisplaced or minimally displaced waist fracture, and here the evidence has moved:
- The classic instability threshold is displacement over 1mm
- SWIFFT randomised 439 adults with bicortical waist fractures displaced 2mm or less to early screw fixation or a below-elbow cast with fixation of any confirmed nonunion, and found no difference in patient-rated wrist function at a year
- Surgery brought a 14% rate of potentially serious complications against 18% cast-related complications: a trade of one complication profile for another, not a choice between risk and safety
- For that group, cast first and fix the few that fail is the modern position. Displacement over 2mm, proximal pole, comminution and fracture-dislocation were not randomised, and the classic criteria still apply there
- Key Finding
- Extra-articular, very stable
- Treatment
- Splint 4-6 weeks, excellent prognosis
- Key Finding
- Stable incomplete fracture
- Treatment
- Scaphoid cast 8-12 weeks or consider screw
- Key Finding
- Unstable distal fracture
- Treatment
- Operative fixation recommended
- Key Finding
- Displaced greater than 1mm
- Treatment
- Operative fixation recommended
- Key Finding
- High AVN and nonunion risk
- Treatment
- Operative fixation strongly recommended
- Key Finding
- Complex carpal injury
- Treatment
- Urgent operative fixation
- Key Finding
- Failed to heal, often with AVN
- Treatment
- Surgery with bone graft +/- vascularized graft
Who. Herbert Type A fractures, undisplaced stable fractures generally, the patient who prefers a cast having understood the risks, and anyone unfit for surgery.
The cast. A thumb spica with the thumb IP joint free and the wrist in slight flexion and radial deviation, for a minimum of 8-12 weeks. Above versus below the elbow, and whether to include the thumb at all, has been argued for decades; a meta-analysis of four randomised trials found no difference in union, pain, grip or time to union between any configuration, so a below-elbow cast is reasonable.
The follow-up is not negotiable. Radiograph at 6 weeks. If healing, continue to 8-12 weeks. If not, CT and consider fixation. Proximal fractures in a cast may need up to 20 weeks.
- Scaphoid (thumb spica) cast, thumb IP joint free
- Wrist in slight flexion and radial deviation
- Below-elbow is reasonable; no cast configuration has proved superior
- Duration: 8-12 weeks minimum
- X-ray at 6 weeks
- If healing: continue cast to 8-12 weeks
- If not healed: CT to assess, consider surgery
- Proximal fractures may need up to 20 weeks
Surgical Technique
The screw. The headless compression screw, Herbert's design, is the gold standard fixation for the acute fracture. Herbert's original series reported union in every acute fracture, and most patients back at work within weeks.
- Variable pitch - the two threads differ, so advancing the screw draws the fragments together
- Buried entirely within bone - nothing stands proud of the articular surface
- Early motion - rigid fixation means no three months in plaster
- Placed along the central axis, perpendicular to the fracture: best compression, lowest cut-out risk. Fluoroscopy or navigation finds it
- K-wires as temporary reduction aids or adjuncts; mini-fragment screws rarely now
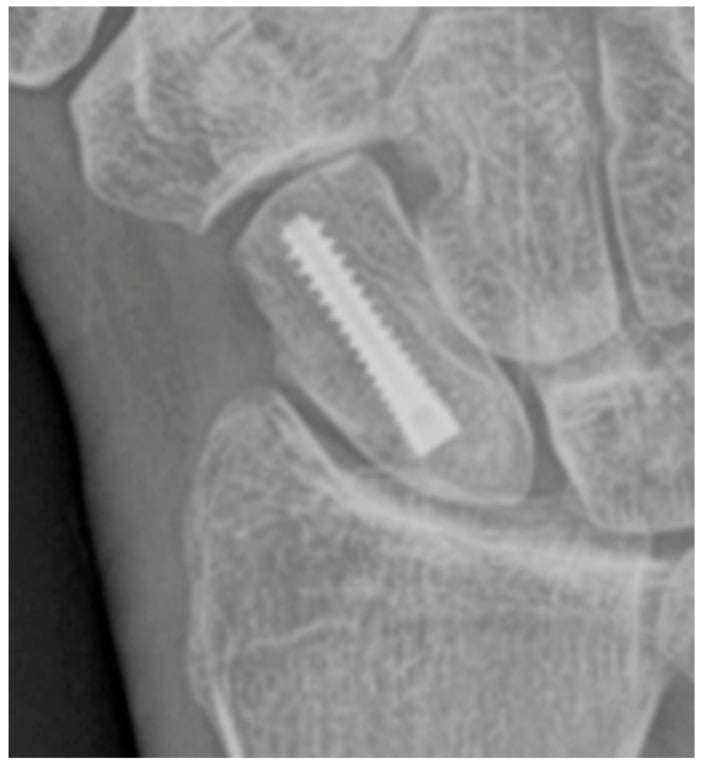
Volar approach - the default for waist and distal fractures. Through the floor of the flexor carpi radialis sheath, radial to the tendon, with the screw placed perpendicular to the fracture. Gelberman's anatomy is the reason it is the default: the vessels that feed the proximal pole enter dorsally, so a volar exposure disturbs them least, and he concluded explicitly that it was the least traumatic approach to the proximal pole's supply.
Dorsal approach - for the proximal pole. Between the third and fourth extensor compartments; it gives a better central-axis trajectory into a small proximal fragment. The trade-off is that it crosses the dorsal ridge, the sole entry point for that fragment's blood. Expose only what is needed, do not strip the soft tissues off the ridge, and accept that the fragment most at risk of necrosis is being approached through its own vascular pedicle.
Complications
- Incidence
- 5-15% (higher proximal)
- Management
- Surgery with bone graft
- Incidence
- 13-50% proximal pole
- Management
- Vascularized bone graft
- Incidence
- Variable
- Management
- Corrective osteotomy if symptomatic
- Incidence
- Progressive with nonunion
- Management
- Salvage procedures
- Incidence
- 10-20%
- Management
- Physiotherapy, rarely surgical
- Incidence
- Variable
- Management
- Screw removal
- Incidence
- Common
- Management
- High index of suspicion, MRI
The complication the whole topic is organised around avoiding. It is the commonest significant one, and it is not static: a scaphoid that has not united lets the carpus collapse, and the arthritis follows.
- Highest risk: proximal pole, displacement, delayed diagnosis, smoking
- Treatment: prepare the fracture site, correct the deformity, bone graft, stable fixation
- Vascularised graft whenever the proximal pole's blood supply is in doubt
Postoperative Care and Rehabilitation
The point of fixing a scaphoid is to be able to move it, so rehabilitation after a screw is built around early motion under protection. Fingers move from day one; the wrist starts gentle motion once initial healing allows, at 2-4 weeks; nothing is loaded until union is confirmed.
- Bulky dressing and thumb spica splint
- Elevation
- Finger motion immediately
- Wound check at 10-14 days
- Convert to removable thumb spica splint
- Begin gentle wrist ROM
- Active finger motion
- May remove splint for exercises
- X-ray/CT to assess healing
- If united: progressive ROM and strengthening
- If not united: continue protection
- Wean from splint as comfort allows
- Full activity after confirmed union
- Grip strengthening
- Return to sport/work
- Final outcome assessment
Principles
- Early finger motion is critical
- Confirm union before loading
- Grip strength returns over 6-12 months
Outcomes and Prognosis
Union rates fall as the fracture moves proximally and as it displaces, and they rise with fixation in exactly the groups where cast treatment does worst.
- Conservative Union
- Over 95%
- Operative Union
- N/A
- Notes
- Excellent prognosis
- Conservative Union
- 90-95%
- Operative Union
- 95%+
- Notes
- Cast reasonable
- Conservative Union
- 60-70%
- Operative Union
- 90-95%
- Notes
- Surgery recommended
- Conservative Union
- 60-70%
- Operative Union
- 85-90%
- Notes
- Surgery strongly recommended
What worsens the prognosis
- Proximal location
- Displacement over 1mm
- Delay to treatment - over 4 weeks significantly increases nonunion, which is the reason the radiograph-negative wrist is immobilised rather than reassured
- AVN
- Smoking
If in doubt, treat it as a scaphoid fracture.
Guidelines, Registries & Global Practice
Global Epidemiology
Scaphoid fractures are the most common carpal fracture, occurring predominantly in young, active males. In a large UK regional study the annual incidence was 12.4 per 100,000, with the highest rate in males aged 15-19 years; 64% were at the waist and 18% at the tubercle, and incidence was higher in more socially deprived groups and peaked in summer (Garala et al., Bone Joint J 2016 — DOI). The classic mechanism is a fall on the outstretched hand; sport and manual occupations dominate the risk profile, though low-energy injuries are increasingly recognised in older adults. The true prevalence among clinically suspected fractures is low — roughly 16% in consecutive suspected presentations, which is why over-treatment of the radiograph-negative wrist is a recognised problem (Jenkins et al., Injury 2008 — DOI).
Guidance & Evidence by Region
- Region
- UK / international
- Key recommendation
- Minimally displaced waist fractures (2mm or less): initial below-elbow cast, fix only confirmed nonunions
- Evidence basis
- Level I RCT (DOI)
- Region
- USA
- Key recommendation
- Displaced (over 1mm), proximal pole, unstable patterns: operative fixation; non-displaced waist: cast or fixation by shared decision
- Evidence basis
- Expert consensus + RCT/meta-analysis
- Region
- UK
- Key recommendation
- Clinical exam + dedicated scaphoid views; if radiograph-negative with ongoing suspicion, immobilise and re-image or proceed to MRI/CT rather than discharge
- Evidence basis
- Standard of care / diagnostic pathway
- Region
- International
- Key recommendation
- Central-axis headless compression screw; reserve volar approach for waist/distal and dorsal approach for proximal pole
- Evidence basis
- Technical consensus
- Region
- Europe
- Key recommendation
- Concur with cast-first for minimally displaced waist; advanced imaging for occult fractures
- Evidence basis
- Aligned with SWIFFT
Cost-effectiveness modelling supports immediate MRI or CT over empiric casting plus repeat radiographs for the occult fracture, as advanced imaging was the dominant strategy on both cost and outcome (Karl, Swart, Strauch, JBJS Am 2015 — DOI).
Global Practice Variation
- Casting configuration: No RCT evidence favours above- versus below-elbow casting or thumb inclusion (Doornberg, Buijze et al., J Trauma 2011 — DOI); below-elbow casting excluding the thumb is increasingly standard, though practice remains heterogeneous.
- Surgery vs cast for minimally displaced fractures: Rates of early fixation rose internationally before SWIFFT; the trial has shifted high-resource practice back toward cast-first with selective fixation, but operative thresholds still vary by surgeon and patient (athlete, manual worker) preference.
- Imaging access: In high-resource settings MRI/CT is used early for occult fractures; in limited-resource or remote settings empiric thumb-spica immobilisation with delayed re-imaging at 10-14 days remains common and acceptable.
- Reconstruction: Vascularised bone grafting and salvage procedures are typically concentrated in specialist hand units worldwide.
Registry Note
There is no dedicated international scaphoid-fracture registry; population-level epidemiology derives from national administrative and regional datasets (e.g. UK and German fracture surveillance), which consistently show a young-male predominance and a majority of waist fractures.
Be ready to discuss retrograde blood supply anatomy, the Herbert classification, the algorithm for the radiograph-negative but clinically suspected fracture, the SWIFFT message (cast-first for minimally displaced waist fractures), and nonunion treatment (vascularised vs non-vascularised graft indications). Smoking cessation materially improves union and should be addressed in every counselling answer. Medicolegal aspects of the missed scaphoid fracture are examined across boards.
MCQ Practice Points
Q: What is the blood supply pattern of the scaphoid? A: Retrograde - the dorsal carpal branch of the radial artery enters at the distal pole (dorsal ridge) and blood flows proximally. The proximal pole has no direct blood supply - it relies entirely on intraosseous vessels. This is why proximal pole fractures have highest AVN risk.
Q: In Herbert classification, what defines a Type B fracture? A: Unstable acute fractures. Subtypes: B1 (distal oblique), B2 (displaced waist), B3 (proximal pole), B4 (trans-scaphoid perilunate), B5 (comminuted). Type B fractures generally require operative fixation.
Q: What is the best investigation for a clinically suspected scaphoid fracture with negative X-rays? A: MRI. Its specificity approaches 100%, so a positive scan is highly trustworthy, but the pooled sensitivity is about 88% - a negative MRI in a still-convincing wrist means continued immobilisation and review, not discharge. It shows bone marrow oedema before any fracture line is visible on X-ray and can identify alternative diagnoses. CT is better for characterising a known fracture.
Q: Which scaphoid fracture location has the highest nonunion and AVN rate? A: Proximal pole - due to the retrograde blood supply, the proximal pole is entirely dependent on intraosseous vessels. Fractures here interrupt this flow, leading to highest rates of nonunion (up to 30-40%) and AVN (up to 50%).
Q: What is the indication for vascularized bone graft in scaphoid nonunion? A: Avascular necrosis of the proximal pole. Standard non-vascularized bone graft has high failure rate when the proximal pole is avascular. Vascularized grafts (1,2 ICSRA or medial femoral condyle) bring new blood supply to the dead bone.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 22-year-old man falls playing football, landing on his outstretched hand. He has anatomic snuffbox tenderness and scaphoid tubercle tenderness. X-rays are normal. How do you manage this patient?”
“A 28-year-old mechanic presents 2 days after a fall. X-rays show a displaced scaphoid waist fracture with 2mm displacement and carpal instability (DISI pattern). How do you manage this?”
“A 35-year-old presents with chronic wrist pain. He recalls an injury 2 years ago that was never treated. X-rays show scaphoid nonunion with humpback deformity and sclerosis of the proximal pole. How do you assess and manage this patient?”
BLOOD SUPPLY
- Retrograde - enters distally, flows proximally
- Dorsal carpal branch of radial artery
- Enters at dorsal ridge (waist level)
- Proximal pole has NO direct blood supply
HERBERT CLASSIFICATION
- Type A: Stable (A1=tubercle, A2=non-displaced waist)
- Type B: Unstable (B1-B5, see subtypes)
- Type C: Delayed union
- Type D: Established nonunion
OPERATIVE INDICATIONS
- Displacement greater than 1mm
- Proximal pole fractures
- Associated carpal instability
- Nonunion
- Relative: athlete, manual worker, patient choice
X-RAY NEGATIVE MANAGEMENT
- 10-20% not visible initially
- Option 1: Treat as fracture, repeat X-ray 10-14 days
- Option 2: MRI (first-line for occult fracture; near-perfect specificity, pooled sensitivity about 88% - a negative scan does not exclude)
- Never dismiss with clinical findings
NONUNION TREATMENT
- Assess proximal pole vascularity (MRI + gadolinium)
- Viable: non-vascularized bone graft (Fisk-Fernandez)
- AVN: vascularized bone graft (1,2 ICSRA, MFC)
- SNAC wrist: salvage procedures
KEY NUMBERS
- 70% waist fractures (most common)
- 20% proximal pole (highest AVN risk)
- 10-20% X-ray negative initially
- 5-15% nonunion rate overall
- greater than 1mm displacement = surgery
Evidence Base
Dias et al. SWIFFT Trial — surgery vs cast for scaphoid waist fractures
- Pragmatic multicentre RCT (31 UK hospitals, 439 adults) comparing early surgical fixation versus below-elbow cast (with immediate fixation if nonunion confirmed) for bicortical scaphoid waist fractures displaced by 2mm or less.
- No significant difference in patient-rated wrist evaluation (PRWE) at 52 weeks: surgery 11.9 vs cast 14.0 (adjusted difference -2.1, 95% CI -5.8 to 1.6, p=0.27).
- Serious surgical complications occurred in 14% of the surgery group versus 1% of the cast group; cast-related complications were higher in the cast group (18% vs 2%).
Herbert and Fisher. Management of the fractured scaphoid using a new bone screw
- Introduced the double-threaded (variable-pitch) headless compression screw and the eponymous classification of scaphoid fractures (Types A-D).
- Prospective series of 158 operations (1977-1981): union rate 100% for acute fractures and 83% overall, with most patients returning to work within a few weeks and a plaster cast rarely required.
Doornberg, Buijze et al. Nonoperative treatment for acute scaphoid fractures — systematic review and meta-analysis of RCTs
- Meta-analysis of four RCTs (523 patients) comparing cast variables (above- vs below-elbow, thumb inclusion, wrist position).
- No significant difference in union rate, pain, grip strength, time to union or osteonecrosis between any nonoperative casting method.
Gelberman and Menon. The vascularity of the scaphoid bone
- Cadaveric injection study (15 specimens) defining scaphoid vascular anatomy.
- 70-80% of intraosseous blood supply and the entire proximal pole derive from radial artery branches entering through the dorsal ridge; 20-30% (distal tuberosity) from volar radial branches.
- The volar operative approach was shown to be least traumatic to the proximal pole's blood supply.
Karl, Swart, Strauch. Diagnosis of occult scaphoid fractures — cost-effectiveness analysis
- Decision-analysis model comparing empiric cast immobilisation, immediate CT, and immediate MRI for suspected occult scaphoid fracture with negative radiographs.
- Advanced imaging (CT or MRI) was dominant — lower overall cost and better projected outcomes than empiric casting; MRI was marginally more cost-effective than CT but sensitive to local test performance and cost.
- Empiric casting would only become cost-effective if advanced imaging cost exceeded $2000 or sensitivity fell below 25-32%.
Garala, Taub, Dias. The epidemiology of fractures of the scaphoid
- Retrospective regional study of 415 confirmed scaphoid fractures: annual incidence 12.4 per 100,000, with the highest rate in males aged 15-19 years (365 of 415 fractures occurred in males).
- Waist fractures accounted for 64% and tubercle fractures for 18.1% of cases; incidence was higher in the most socially deprived groups and peaked seasonally in June.