High Revision Rates | Glenoid Loosening | Instability Risk | Infection Management
- Glenoid loosening is the leading cause of failure in anatomic TSA (20-30% radiolucency at 10 years)
- Instability is the most common complication of RSA (5-10%), often requiring revision
- Axillary nerve at highest risk during deltopectoral approach - check function preop and postop
- Infection requires a minimum of 6 weeks of antibiotics; single-stage revision controversial
- Subscapularis failure leads to anterior instability - repair integrity critical in anatomic TSA
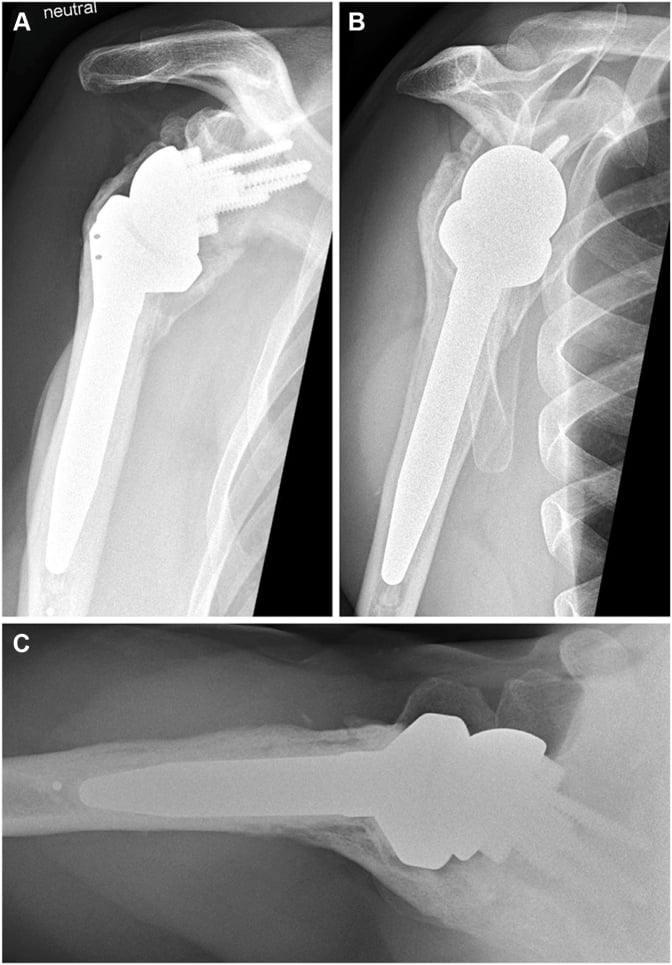
- “Glenoid baseplate failure in RSA often related to poor bone stock or scapular notching
- “Periprosthetic fractures classified by Vancouver system (adapted for shoulder)
- “Cutibacterium acnes is the most common organism in shoulder PJI (30-40%), ahead of Staphylococcus epidermidis (25-30%)
- “Notching is seen radiographically in 44-96% of RSA but is clinically significant in less than 10%
Overview and Epidemiology
Shoulder arthroplasty has the highest revision rate of all joint replacements, approximately 10% at 10 years for anatomic TSA and 15% for reverse shoulder arthroplasty (RSA). Registry data show complication rates increasing with time, so surveillance has to be long term.
What a complication costs. Outcome scores drop by 20-30 points after a complication, and patient satisfaction falls from 90% to under 60% when the complication is major. A revision procedure costs 2-3 times as much as the primary arthroplasty.
Pathophysiology of Complications
Complications arise from three mechanisms, and naming the mechanism guides both prevention and treatment.
Biological. Bacteria form a biofilm on the implant surface; Staphylococcus epidermidis and Cutibacterium acnes are the typical organisms. Polyethylene wear debris triggers macrophage activation and osteolysis. Bone is also lost to stress shielding from the humeral stem and to glenoid bone loss, and the soft tissues fail when a subscapularis repair gives way or rotator cuff disease progresses.
Mechanical. Instability follows insufficient soft-tissue tension or component malposition. Glenoid loosening follows eccentric loading and poor fixation. Impingement takes the form of scapular notching in RSA and subacromial impingement in TSA, and the metal-on-polyethylene articulation wears over time.
Technical. Malposition, sizing errors and nerve injury are the technical complications.
Eccentric glenoid loading in anatomic TSA creates asymmetric forces on the glenoid component with arm elevation. Superior loading during elevation makes the humeral head act as a fulcrum, rocking the glenoid component. The micromotion disrupts the cement-bone interface, producing radiolucent lines and progressive loosening. Prevention rests on optimal component positioning, cement pressurisation and patient selection.
- Primary Mechanism
- Bacterial contamination and biofilm
- Contributing Factors
- S. aureus most common, surgical factors, patient comorbidities
- Time Course
- Less than 4 weeks postoperative
- Primary Mechanism
- Indolent bacterial colonisation
- Contributing Factors
- C. acnes biofilm, male patients, low virulence organisms
- Time Course
- Over 3 months, often years
- Primary Mechanism
- Loss of soft tissue tension
- Contributing Factors
- Insufficient lateralisation, component malposition, subscapularis deficiency
- Time Course
- Early (less than 3 months) or late (after trauma)
- Primary Mechanism
- Eccentric loading and micromotion
- Contributing Factors
- Rocking horse phenomenon, poor cement technique, young active patient
- Time Course
- Progressive over 5-10 years
- Primary Mechanism
- Traction or direct trauma
- Contributing Factors
- Retractor pressure, arm positioning, anatomic proximity
- Time Course
- Immediate intraoperative
Classification of Complications
Complications are classified three ways: by when they appear, by which component fails, and by how severe they are. Timing is the key to the differential diagnosis, although instability can occur early or late.
- Complications
- Nerve injury, acute infection, dislocation
- Incidence
- 5-8% combined
- Key Management
- Early recognition, urgent intervention for infection
- Complications
- Instability, periprosthetic fracture, wound issues
- Incidence
- 3-5%
- Key Management
- Component assessment, revision if malpositioning
- Complications
- Aseptic loosening, periprosthetic fracture, late infection, subscapularis failure
- Incidence
- 5-10%
- Key Management
- Imaging surveillance, functional assessment
- Complications
- Component wear, osteolysis, cuff tears, subscapularis failure, scapular notching
- Incidence
- 15-20% by 10 years
- Key Management
- Monitor, revise when symptomatic or progressive
Clinical Presentation
Each complication has its own pain pattern, functional loss and signs, and the time since surgery narrows the list before the examination begins.
- Pain Pattern
- Constant, severe, worse at night
- Functional Loss
- Significant loss of function, unwilling to move
- Physical Findings
- Fever, wound drainage, erythema, warmth, tenderness
- Pain Pattern
- Persistent ache, not severe
- Functional Loss
- Moderate limitation, gradual decline
- Physical Findings
- Minimal external signs, may have normal exam
- Pain Pattern
- Sudden onset after trauma or motion
- Functional Loss
- Complete loss of function, arm held protectively
- Physical Findings
- Visible deformity, positive apprehension, neurovascular deficit possible
- Pain Pattern
- Progressive pain with activity, clicking
- Functional Loss
- Gradual loss of ROM and strength
- Physical Findings
- Crepitus, reduced ROM, mechanical symptoms
- Pain Pattern
- Variable - may be painless
- Functional Loss
- Deltoid weakness, inability to abduct
- Physical Findings
- Loss of deltoid contraction, lateral shoulder numbness
- Pain Pattern
- Acute pain after fall or trauma
- Functional Loss
- Sudden functional loss, unable to lift arm
- Physical Findings
- Deformity, crepitus, ecchymosis, pain with movement
The first two weeks. A nerve injury shows immediately after surgery as deltoid weakness or sensory loss. Acute infection declares itself with wound drainage persisting beyond 5 days, fever and a raised WBC, and early instability as failure to reach range-of-motion milestones or a feeling of subluxation.
Two weeks to three months. Wounds may heal slowly, keep draining or develop a superficial infection. Instability now presents as dislocation during therapy or after minor trauma, or as recurrent subluxation, and a fall during recovery brings the new pain and deformity of a periprosthetic fracture.
Three months to two years. Chronic infection shows as persistent pain despite an appropriate recovery, with a raised CRP. Component loosening gives progressive pain with loading and mechanical clicking, and subscapularis failure costs internal rotation and brings symptoms of anterior instability.
After two years. Glenoid loosening brings progressive pain and crepitus, with loss of previously good function. Polyethylene wear causes clicking, catching, reduced range of motion and metallosis symptoms, and a late cuff tear presents as pseudoparalysis after a period of good function.
- Acute pain and fever within the first month = infection until proven otherwise; fever with wound drainage within 4 weeks = acute infection
- Sudden loss of function after trauma, even minor = instability or periprosthetic fracture
- Complete deltoid paralysis postop = axillary nerve injury requiring EMG
- Persistent pain with CRP over 10 mg/L beyond 3 months = chronic infection
- Progressive pain or mechanical symptoms over months = component loosening requiring imaging
Differential Diagnosis of the Painful Shoulder Arthroplasty
The painful or poorly functioning replaced shoulder is a common exam scenario. The key discriminator is to exclude infection first in every case, then separate mechanical, neurological and extrinsic causes using timing, examination and targeted imaging.
- Discriminating features
- Rest/night pain, indolent in males, stiffness; may have normal CRP
- First-line test
- ESR/CRP then image-guided aspiration with prolonged culture
- Confirms / excludes
- Synovial cell count, alpha-defensin, multiple deep cultures (14-day hold)
- Discriminating features
- Progressive activity-related pain, mechanical clicking
- First-line test
- Serial radiographs (lucent lines, migration); CT
- Confirms / excludes
- Progressive radiolucency / component shift on CT
- Discriminating features
- Sudden loss of function, apprehension, often post-trauma (RSA anterior escape)
- First-line test
- AP and axillary radiographs; CT for version
- Confirms / excludes
- Dislocation/subluxation; component malposition
- Discriminating features
- Loss of internal rotation, anterior instability, pseudoparalysis
- First-line test
- Ultrasound or MARS MRI
- Confirms / excludes
- Cuff/subscapularis tear; intact tendon excludes
- Discriminating features
- Acute pain and deformity after fall
- First-line test
- AP and lateral radiographs
- Confirms / excludes
- Fracture line; assess component stability
- Discriminating features
- Focal weakness/numbness, often painless
- First-line test
- Clinical exam then EMG/NCS at 3-4 weeks
- Confirms / excludes
- Denervation on EMG; normal study excludes
- Discriminating features
- Adduction pain, deltoid-region tenderness, loss of elevation
- First-line test
- Radiographs (notch grade); CT or bone scan for stress fracture
- Confirms / excludes
- Notch grade 3-4; occult fracture on CT/bone scan
- Discriminating features
- Pain out of proportion, dermatomal or diffuse, normal implant imaging
- First-line test
- Cervical spine assessment, examination for CRPS features
- Confirms / excludes
- Cervical pathology or CRPS; normal arthroplasty workup
Investigations
First line. Radiographs in three views, AP, scapular Y and axillary lateral, show component position, lucent lines and fracture. Serial films compared with previous ones are essential for detecting progression. CRP and ESR are more useful as a trend than as absolute values, and the white cell count and differential are raised in acute infection.
Advanced imaging. Each modality answers a different question:
- CT: component version, bone defects and fracture characterisation
- MRI: rotator cuff integrity and soft-tissue assessment, within the limits of metal artefact
- Ultrasound: aspiration guidance, fluid collections and subscapularis integrity
- Nuclear medicine: Tc-99 bone scan or WBC scan if infection is suspected
- Essential Tests
- CRP, ESR, radiographs, joint aspiration
- Advanced Tests
- WBC scan, synovial markers (alpha-defensin), sonication
- Diagnostic Threshold
- Synovial WBC greater than 3000 or 2 positive cultures
- Essential Tests
- AP, scapular Y, axillary radiographs, neurovascular exam
- Advanced Tests
- CT scan for component version and position
- Diagnostic Threshold
- Dislocation on imaging, component malposition on CT
- Essential Tests
- Serial radiographs (periglenoid zones, graded 0-5), CRP to rule out infection
- Advanced Tests
- CT for bone defects, MRI for rotator cuff
- Diagnostic Threshold
- Progressive radiolucent lines over 2mm, symptoms
- Essential Tests
- Clinical exam (deltoid, biceps strength), sensory testing
- Advanced Tests
- EMG/NCS at 3-4 weeks, follow-up at 3 months
- Diagnostic Threshold
- Absent motor units on EMG, denervation potentials
- Essential Tests
- AP and lateral radiographs, component stability assessment
- Advanced Tests
- CT scan for fracture classification and surgical planning
- Diagnostic Threshold
- Fracture visible on radiographs, classify by Vancouver
The Infection Workup
The diagnostic criteria divide into major and minor. The major criterion is two positive cultures of the same organism; the minor criteria are a raised ESR or CRP, positive histology and purulence. The workup runs in order:
- Clinical suspicion (day 0). Persistent pain, fever, wound problems or raised inflammatory markers. Take a full blood count, ESR and CRP before antibiotics if possible, and radiographs for component position and lucent lines.
- Aspiration (days 1-2). Under ultrasound or fluoroscopic guidance, by an anterior approach. Send fluid for cell count with differential, aerobic and anaerobic cultures on a 14-day hold, and Gram stain. Over 3000 WBC with over 80% PMNs suggests infection.
- Culture results (days 5-14). Standard cultures report common organisms at 5 days; the extended hold is for slow-growing C. acnes. If cultures are negative, consider alpha-defensin, extended culture or surgical biopsy.
- Surgical confirmation. Take a minimum of 5-6 tissue samples from different sites and send removed components for sonication, which increases culture yield by 15-25%. On frozen section, more than 5 PMNs per high-power field suggests infection.
Cutibacterium acnes was renamed from Propionibacterium acnes in 2016; older sources and many reports still write "P. acnes". It needs a 14-day culture hold, and standard 5-day protocols miss 60% of cases. The infection is indolent and easily missed: symptoms may be limited to pain alone, often with a normal CRP and no fever. Consider it in any male patient with persistent pain after shoulder arthroplasty, even with normal inflammatory markers and no obvious signs of infection, and always request the extended hold when aspirating.
Radiographic Assessment
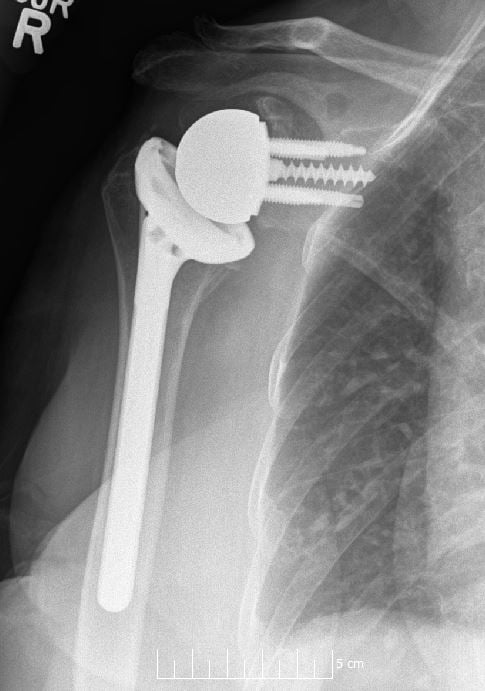
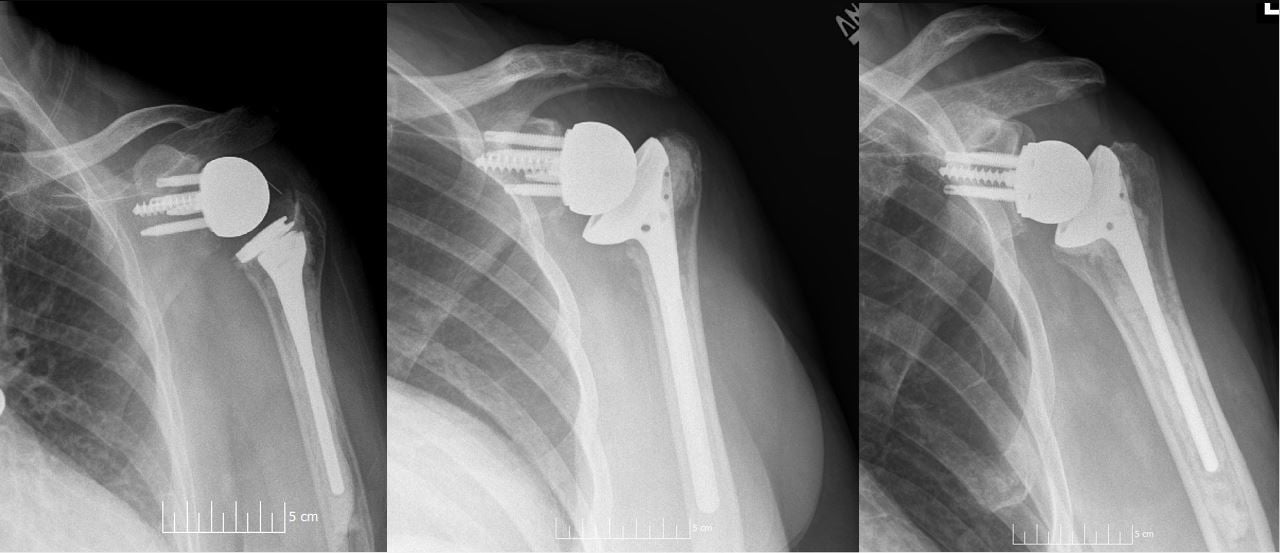
- Significance
- Component loosening - high specificity
- Action Required
- CT scan to assess bone defects, plan revision surgery
- Significance
- Common finding, often benign
- Action Required
- Serial radiographs every 6-12 months, monitor for progression
- Significance
- Definitive loosening
- Action Required
- Revision surgery planning, assess for infection
- Significance
- Osteolysis from wear debris or infection
- Action Required
- Rule out infection with aspiration, consider revision
- Significance
- Significant glenosphere-scapular impingement
- Action Required
- Monitor for baseplate loosening, consider revision if symptomatic
Management
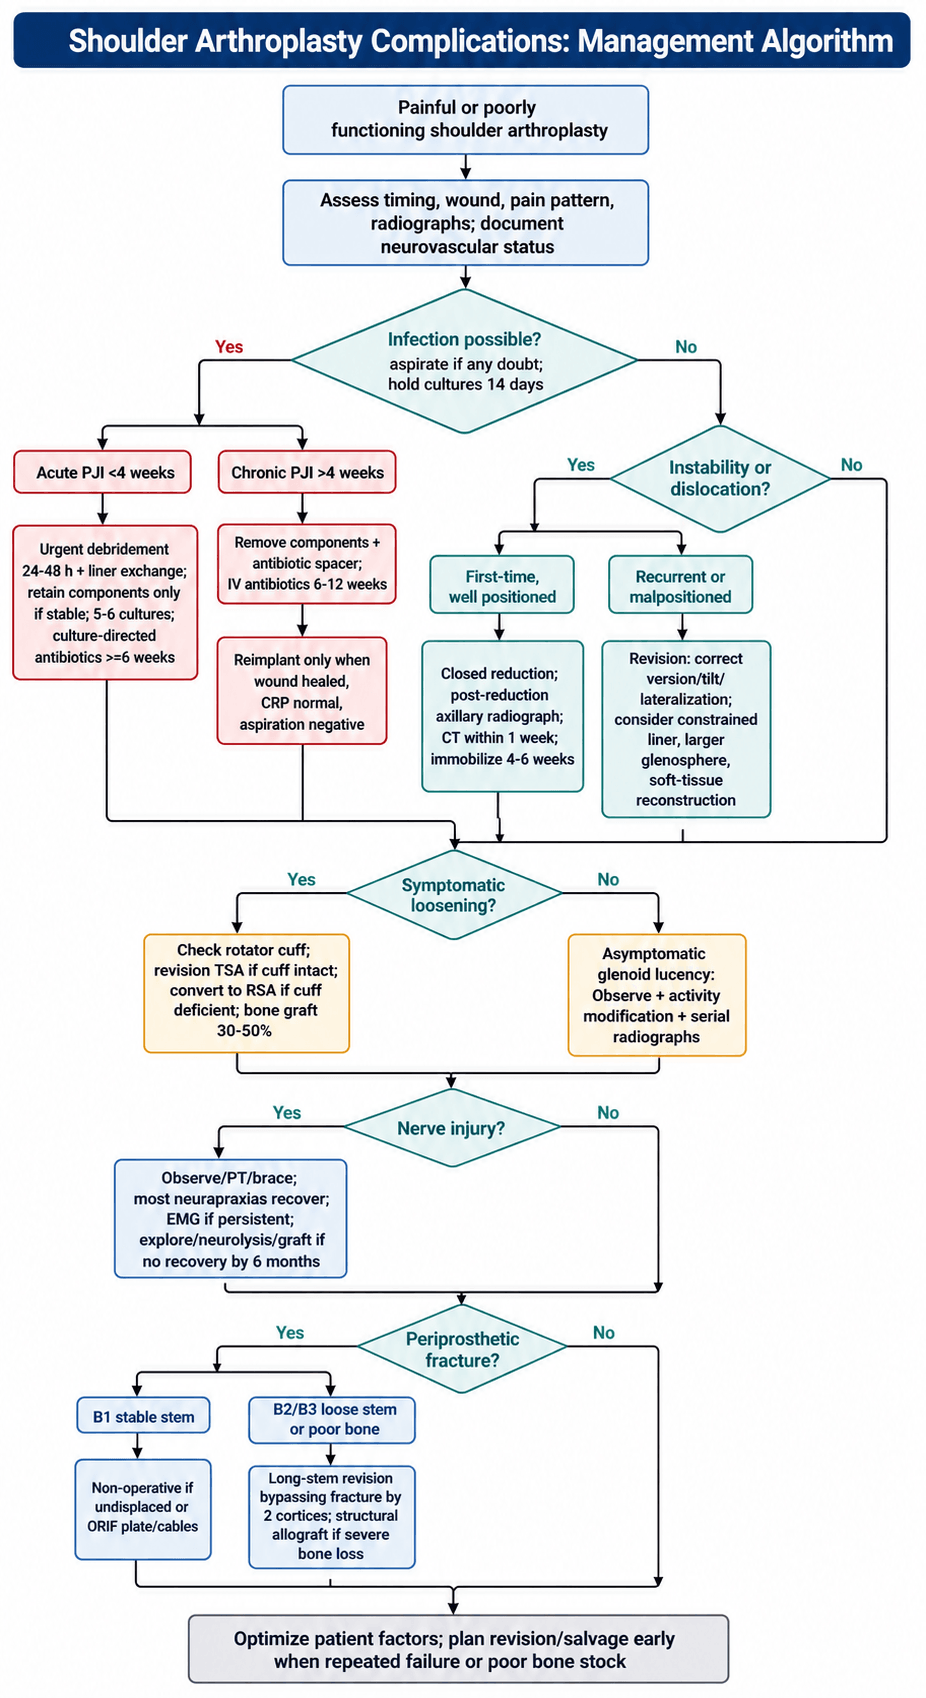
- Exclude infection in any complication, aspirating if there is any doubt
- Assess component position with CT if there is instability or unexplained pain
- Document neurovascular status before and after any intervention
- Optimise patient factors: nutrition, diabetes control, smoking cessation
- Consider salvage options early: resection arthroplasty, fusion, amputation in severe cases
Instability
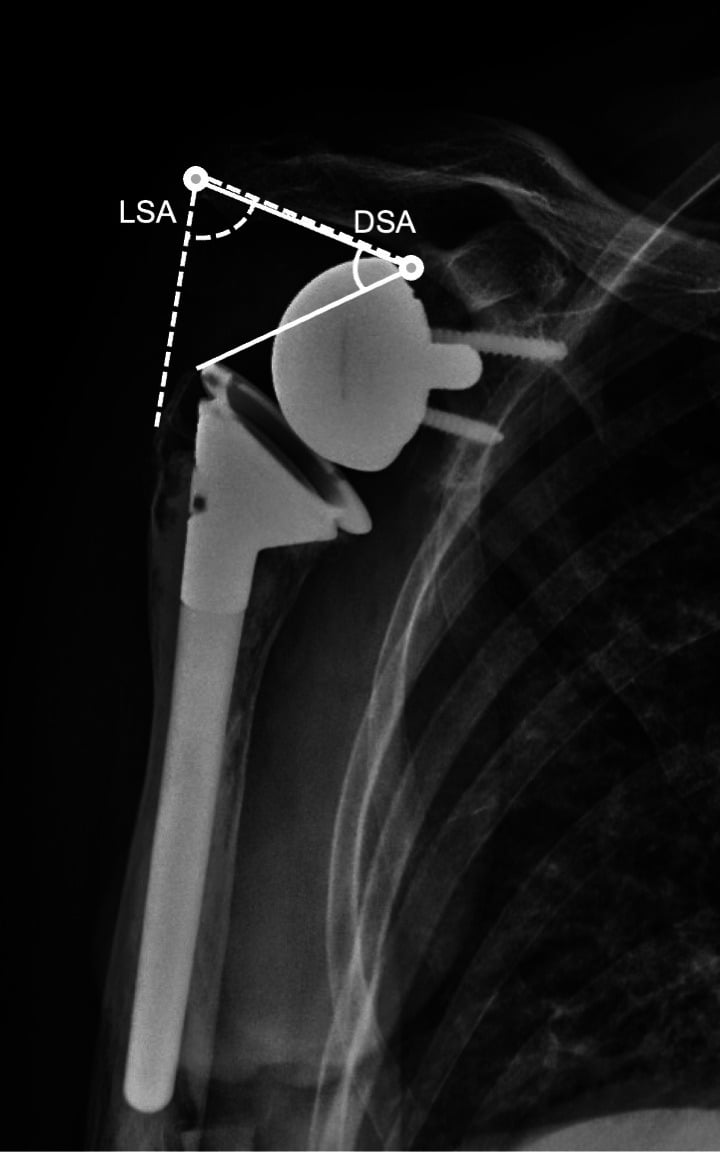
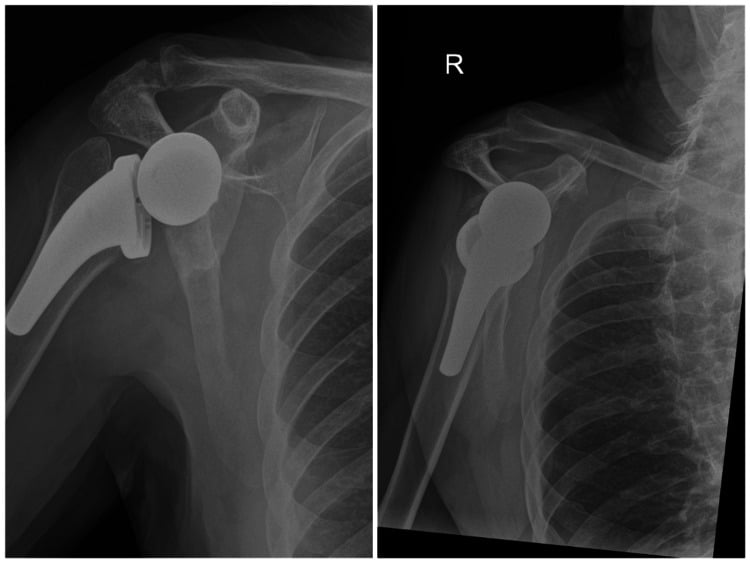
Incidence and direction. Instability is the most common complication of RSA, occurring in 5-10%, against 1-3% of anatomic TSA. In RSA it is characteristically anterior: the humeral cup escapes anterosuperiorly off the glenosphere. In anatomic TSA the direction follows the cause, anterior with subscapularis failure and posterior with glenoid retroversion and posterior wear (Walch B).
Risk factors. The subscapularis is the primary anterior stabiliser, so its deficiency or a failed repair is a leading risk for RSA instability. The positional and soft-tissue factors are in the table; revision surgery, arthroplasty for fracture sequelae, male sex, high BMI and deltoid or capsular insufficiency add to the risk.
- Mechanism
- Reduced deltoid tension, loss of stability arc
- Prevention Strategy
- Use lateralised glenosphere or BIO-RSA design
- Mechanism
- Posterior subluxation in neutral rotation
- Prevention Strategy
- Target 20-30 degrees retroversion, check with CT
- Mechanism
- Loss of anterior restraint, anterior instability
- Prevention Strategy
- Repair subscapularis if possible, consider anterior augment
- Mechanism
- Inferior subluxation or anterior instability
- Prevention Strategy
- Correct tilt with reaming or augmented baseplate
Recognition. The patient has sudden loss of function, pain, a visible deformity and holds the arm protectively. AP and axillary lateral radiographs confirm the direction of dislocation. Document axillary nerve function and the radial pulse before and after reduction.
Closed reduction. Reduce under conscious sedation. For an anterior RSA dislocation, apply traction with gentle adduction and internal rotation to lever the cup back over the glenosphere; muscle relaxation is usually needed because the construct is tensioned. An anterior TSA dislocation reduces with traction, abduction and external rotation. Afterwards the axillary view is essential to confirm a concentric reduction, and the stable arc of motion is assessed.
Component assessment. A CT scan within 1 week measures the component position against its targets:
- Glenoid version: 5-15° retroversion in RSA (target 10°), 5-10° in TSA
- Humeral retroversion: 20-30°
- Glenosphere lateralisation in RSA: minimum 25mm from the glenoid face
The decision. A first dislocation with well-positioned components is treated by immobilisation for 4-6 weeks with physiotherapy; open reduction, soft-tissue repair and a constrained liner if needed are the surgical options at this stage. Any recurrence, or malposition on CT, goes to revision, because once instability recurs non-operative management fails in over 70%. Revision corrects version, tilt or lateralisation and may add a constrained liner, a larger glenosphere, increased tension or soft-tissue reconstruction; soft-tissue deficiency calls for a constrained liner or an augmented glenosphere. In TSA the subscapularis is repaired, with allograft reconstruction if needed, and posterior instability may call for posterior capsular plication. Fusion is the salvage after multiple failed revisions.
Infection (Periprosthetic Joint Infection)
Incidence and organisms. Infection occurs in 2-6% of shoulder arthroplasties, more often after revision. The organisms, in order of frequency:
- Cutibacterium acnes, 30-40%: indolent, male patients
- Staphylococcus epidermidis, 25-30%: biofilm former; against the indolent C. acnes, it causes more acute presentations
- S. aureus, 15-20%: more acute presentation
- Culture-negative, 10-15%: consider C. acnes with extended culture
Acute or chronic. The dividing line is 4 weeks. Acute infection presents with wound drainage, erythema, fever and a raised WBC. Chronic infection presents with persistent pain, a CRP over 10 mg/L and mechanical symptoms. Positive cultures are part of the criteria for both.
Acute PJI (under 4 weeks). This is a surgical urgency with no conservative option. Debride urgently, within 24-48 hours: remove the polyethylene liner, debride the soft tissues aggressively, take 5-6 tissue cultures and send removed components for sonication. The components are retained only if they are stable, the infection is acute and the organism is known, and the polyethylene liner is exchanged. Antibiotics are culture-directed and continue for at least 6 weeks. If retention fails, the options are two-stage revision or resection arthroplasty.
Chronic PJI (over 4 weeks). Biofilm on the components requires their removal, and the standard is two-stage revision. Stage one removes all components, debrides and places an antibiotic spacer, either static (a cement block) or articulating (PROSTALAC design), made from cement with high-dose vancomycin (3-4g) and tobramycin (2-4g) per 40g. 6-12 weeks of IV antibiotics follow, and stage two reimplants new components once the infection has cleared. Suppressive antibiotics alone are reserved for patients who are not surgical candidates; permanent spacer, resection arthroplasty and fusion are the salvage options.
Single-stage or two-stage. Single-stage revision, which removes, debrides and reimplants at one sitting, remains controversial. It can be considered for a low-virulence organism such as C. acnes in a healthy patient with good soft tissue and bone stock. Two-stage suits a high-virulence organism such as S. aureus, poor bone stock or an immunocompromised patient. Resection arthroplasty is for insufficient bone stock or a patient who is not a surgical candidate.
Reimplantation. Stage two proceeds only when these conditions are met:
- Clinical: healed wound, no drainage, patient systemically well
- Laboratory: CRP normalised to less than 10 mg/L, with normal ESR and WBC
- Aspiration: negative cultures and synovial WBC less than 1500
Antibiotics. Start empirical vancomycin plus ceftriaxone until cultures are available, then treat the organism:
- C. acnes: penicillin G IV for 4 weeks, then oral amoxicillin for 2-6 months
- S. aureus (MSSA): cefazolin or nafcillin for 6 weeks
- Staphylococcal species: rifampicin is often added for biofilm cover
Glenoid Component Loosening
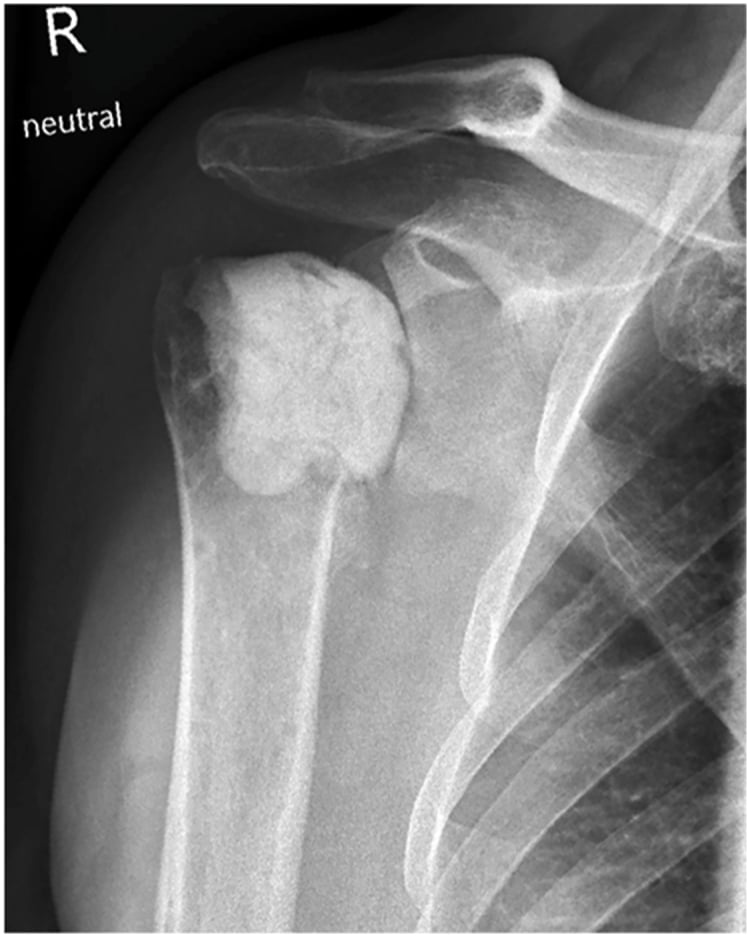
The scale of the problem. Glenoid loosening is the leading cause of anatomic TSA failure and accounts for 30-40% of all TSA revisions. Radiolucent lines develop in 20-30% of patients by 10 years, but only 5-10% become symptomatic and need revision. Symptomatic loosening presents late, over 5 years after surgery.
Presentation. Pain is progressive and worse with activity and loading. Mechanical symptoms of clicking, clunking and catching accompany a loss of motion, especially forward elevation and rotation, and weakness follows from pain and the mechanical block. Radiographs show periglenoid radiolucent lines and eccentric glenoid wear.
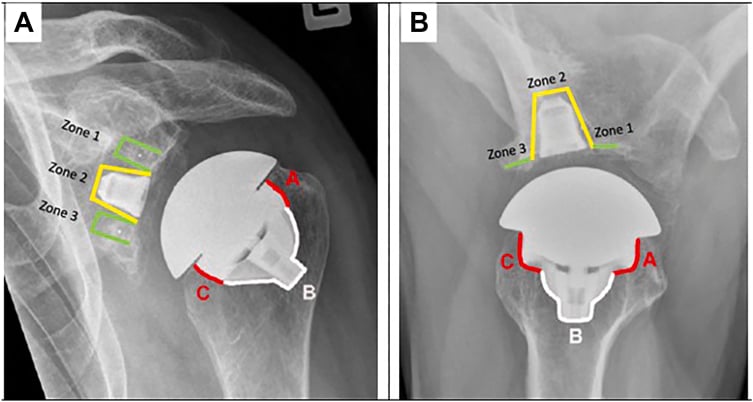
Reading the lines. Two things are recorded: the zone that locates the line around the component, and its grade on a 0-5 scale. A line under 1mm is often benign and stable, and a line over 2mm is concerning; a progressive line over 2mm, widening on serial films, indicates loosening. The all-polyethylene glenoid is the implant most commonly showing lucent lines, and lucency around the pegs is more predictive. It is progression and migration on serial films, together with symptoms such as pain, clicking and reduced range of motion, that signal failure, not the mere presence of a line.
- Location
- Superior quadrant of glenoid
- Significance
- High stress area, early indicator of loosening
- Action
- Monitor closely if greater than 1mm width
- Location
- Anterior half of glenoid
- Significance
- Common with anterior eccentric wear
- Action
- Consider revision if progressive and symptomatic
- Location
- Inferior quadrant
- Significance
- Associated with inferior tilt or subsidence
- Action
- High concern if complete lucency around pegs
- Location
- Posterior half of glenoid
- Significance
- May indicate posterior glenoid wear
- Action
- Assess glenoid version on CT
- Location
- Complete lucency around component
- Significance
- Gross loosening, likely symptomatic
- Action
- Revision surgery indicated
Management. Asymptomatic loosening is observed with activity modification and serial radiographs. Symptomatic loosening gets activity modification and analgesics only as a temporary measure; the definitive answer is revision, and the rotator cuff decides which. With an intact cuff the option is revision TSA; with a deficient cuff, conversion to RSA. CT defines the bone defects as cavitary or segmental, and bone grafting is needed in 30-50% of revisions. Resection arthroplasty is the salvage when bone stock is poor.
Nerve Injuries
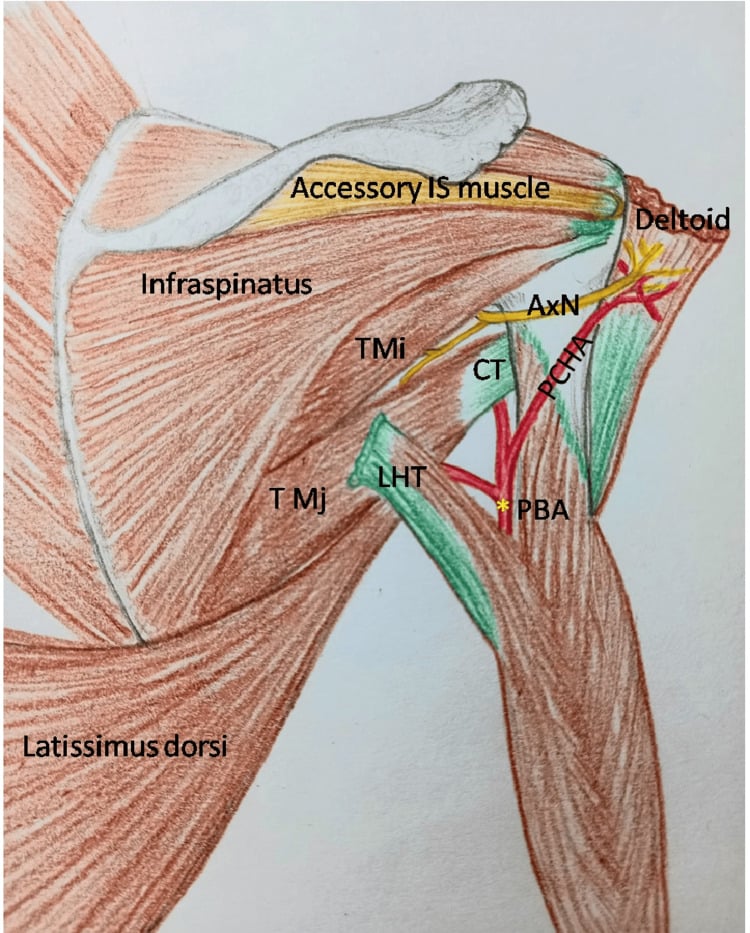
The axillary nerve is the nerve most at risk, injured in 1-4%. Most nerve injuries are neurapraxias that recover in 3-6 months.
- Incidence
- 1-4% (highest risk)
- Mechanism
- Traction during exposure, retractor pressure, direct injury
- Recovery
- 80-90% recover by 6 months
- Incidence
- 0.5-1%
- Mechanism
- Traction, especially with excessive arm abduction
- Recovery
- 85-95% recover by 6 months
- Incidence
- 0.5-2%
- Mechanism
- Stretch during glenoid exposure, baseplate screw penetration
- Recovery
- Variable - 60-80% recovery
- Incidence
- Less than 0.5%
- Mechanism
- Excessive arm extension or inferior retraction
- Recovery
- Good recovery in over 90%
- Incidence
- Less than 0.1%
- Mechanism
- Excessive traction, positioning injury, direct trauma
- Recovery
- Poor recovery - permanent deficit common
Recognition. Examine immediately after surgery and compare with the documented preoperative function. An axillary nerve injury shows as loss of deltoid contraction and numbness over the lateral shoulder; a musculocutaneous injury as a weak biceps and numbness of the lateral forearm; a suprascapular injury as weakness of external rotation (infraspinatus).
Management. The protocol runs by time since injury:
- Weeks 0-6. Observe, with physiotherapy to maintain range of motion and prevent contractures, a brace for protection, and reassurance about the high recovery rate.
- EMG/NCS at 3-4 weeks if there is no recovery. The baseline study establishes severity and localisation, and distinguishes axonotmesis from neurapraxia by recruitment and amplitudes.
- Repeat EMG at 3 months to look for reinnervation.
- Exploration if there is no recovery by 6 months, meaning complete paralysis with no EMG recovery. Identify the nerve, assess its continuity, and consider neurolysis or grafting. Late exploration, beyond 6 months, has poor outcomes.
- Permanent deficit. Tendon transfers or functional bracing.
Periprosthetic Fractures
Risk factors. Patient factors are osteoporosis, age over 70 and rheumatoid arthritis. Surgical factors are excessive reaming, press-fit stems and revision for cuff tear. Uncemented stems carry 3 times the risk of cemented ones, and falls are a risk, especially in RSA with its altered biomechanics.
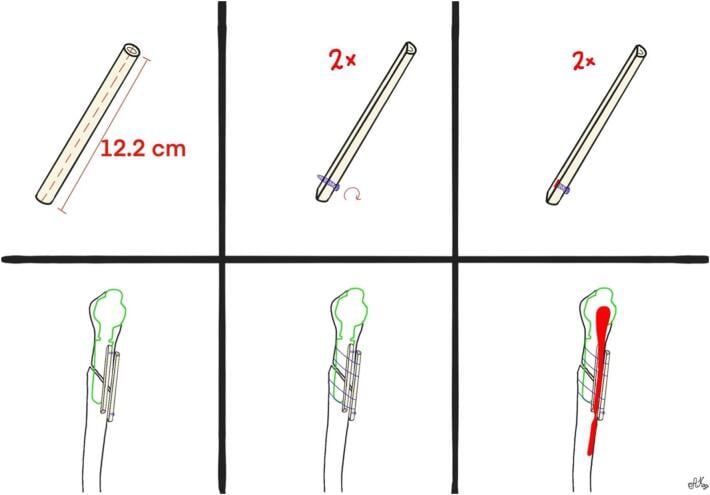
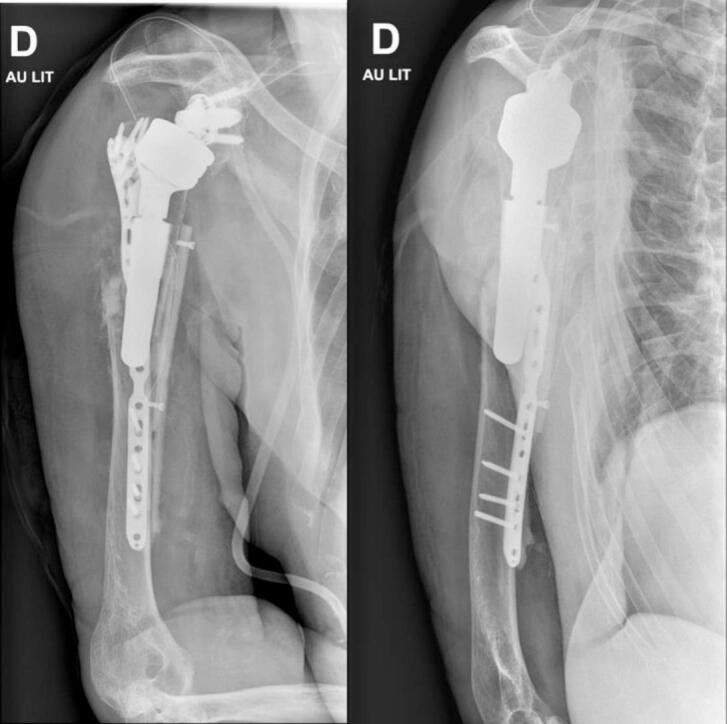
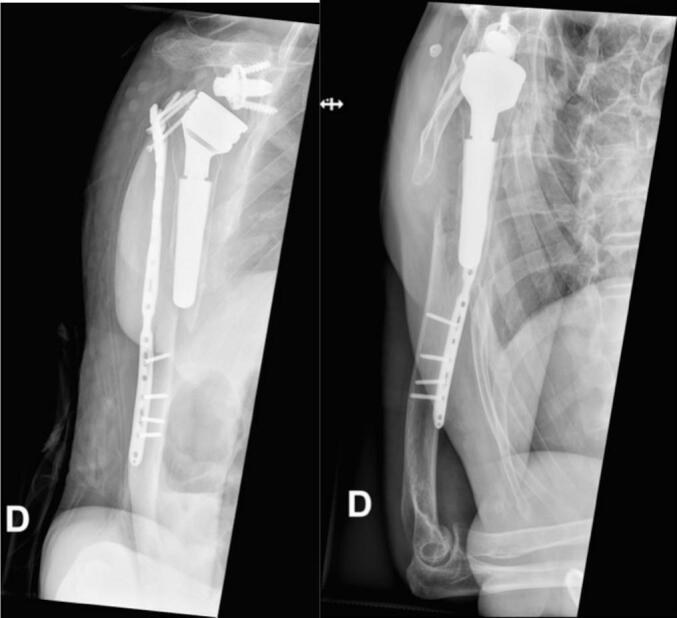
Classification and management. The Vancouver classification, adapted for the shoulder, is by fracture site, and for Type B by stem stability and bone stock:
- Type A, apophysis (greater or lesser tuberosity): sling immobilisation unless displaced over 5mm
- Type B1, around or just below a stable stem: ORIF with plate and cables preserving the component, or non-operative if undisplaced; revise if fixation fails
- Type B2, around a loose stem: revision to a long-stem prosthesis bypassing the fracture by 2 cortical diameters, with strut allografts
- Type B3, with poor bone stock: long-stem revision with structural or strut allograft
- Type C, well below the stem: treat as a native fracture, ORIF if displaced
Type B is the most common. An intraoperative tuberosity fracture is fixed with cerclage, and rehabilitation is delayed.
Humeral Stress Shielding and Bone Resorption
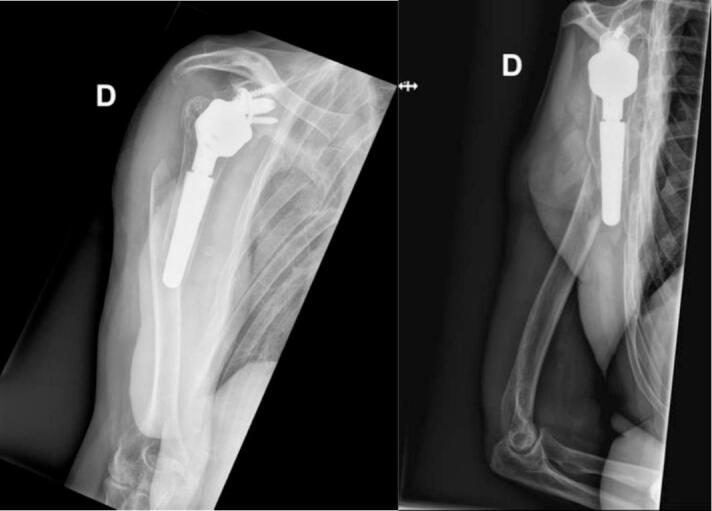
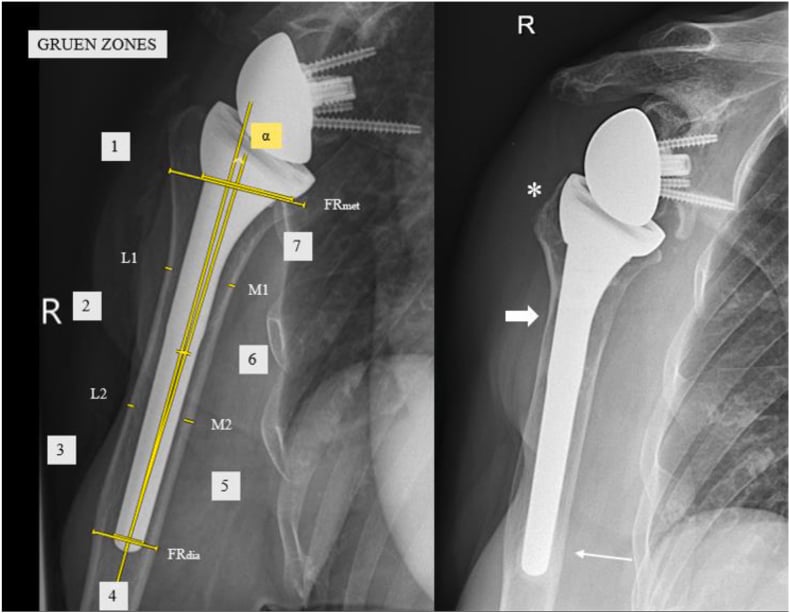
Mechanism. A stiff, well-fixed humeral stem carries load down the diaphysis and unloads the proximal humerus (Wolff's law), so the bypassed proximal bone resorbs. The signs are calcar and medial-metaphyseal resorption, greater-tuberosity osteopenia and cortical thinning, often with distal cortical hypertrophy and condensation lines around the stem tip.
Risk factors. Longer, larger-diameter, well-fixed stems carry the risk, especially cemented or extensively coated ones. Stress shielding is less marked with short-stem and stemless designs, which load the metaphysis more physiologically, and this is a major driver of the trend toward shorter humeral fixation.
Distinguishing it from loosening. Stress shielding is adaptive remodelling: proximal resorption with the stem still well fixed. Loosening shows a progressive, circumferential lucent line at the bone-implant interface, with component migration or subsidence. Humeral loosening is less common than glenoid loosening.
Why it matters. Stress shielding is usually asymptomatic and rarely mandates revision in itself. It does erode the bone stock needed at any future revision, and may predispose to periprosthetic fracture.
Surgical Technique
Exposure for revision. Use an extended deltopectoral approach for adequate exposure, and identify and protect the neurovascular structures; the axillary nerve is often scarred. Mobilise the subscapularis carefully, as it may need extensive release. Remove the components systematically, the humeral component first and then the glenoid.
- Technique
- Extended osteotomy or cement splitting osteotome
- Pitfalls to Avoid
- Spiral fracture, perforation, excessive bone loss
- Technique
- Metal cutting instruments, flexible osteotomes
- Pitfalls to Avoid
- Proximal bone destruction, shaft perforation
- Technique
- High-speed burr for cement, curettes for bone interface; preferential removal of cement to preserve bone stock
- Pitfalls to Avoid
- Anterior perforation, excessive medial reaming
- Technique
- Remove screws first, peripheral release with osteotomes
- Pitfalls to Avoid
- Central screw damage to vault, fracture
Bone defects. Once the components are out, assess the size and location of the defect, cavitary or segmental, and match the reconstruction to it:
- Cavitary defects: impaction bone grafting with morselised cancellous allograft
- Contained or segmental defects under 25% of the surface: eccentric reaming, cement filling or augmented components
- Large segmental defects over 25%: structural allograft wedge grafts or custom implants
- Glenoid vault deficiency: consider a metal augmented baseplate
- Severe bone loss: custom components, tumour prosthesis or salvage procedures
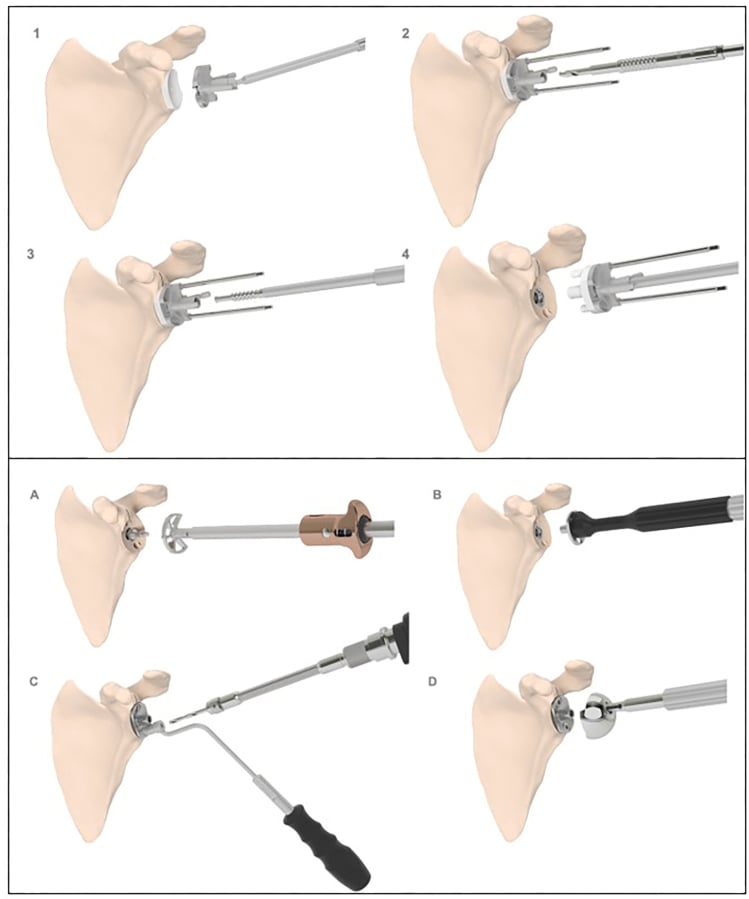
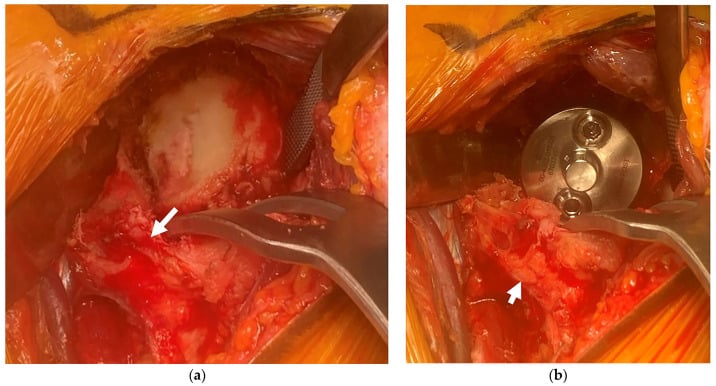
Complications Specific to Implant Type
- Incidence
- 44-96% (radiographic)
- Mechanism
- Inferior glenosphere impingement on scapular neck
- Management
- Usually asymptomatic - monitor for baseplate loosening
- Incidence
- 2-4%
- Mechanism
- Poor bone stock, insufficient screws, notching
- Management
- Revision with bone graft and larger baseplate
- Incidence
- 1-4%
- Mechanism
- Deltoid overstretching, stress fracture from altered loading
- Management
- Usually conservative - rest and immobilisation
- Incidence
- 3-5%
- Mechanism
- Increased dead space from lateralisation
- Management
- Drain use controversial - evacuate if symptomatic
Scapular notching. The inferior glenosphere impinges on the scapular neck during adduction. Notching is common but clinically significant in less than 10%. Worry when it progresses to Grade 3-4 (Nerot-Sirveaux), when baseplate screws loosen, or when the patient develops pain and loss of adduction. Prevention is by inferior glenosphere tilt, lateralisation or an inferior eccentric glenosphere.
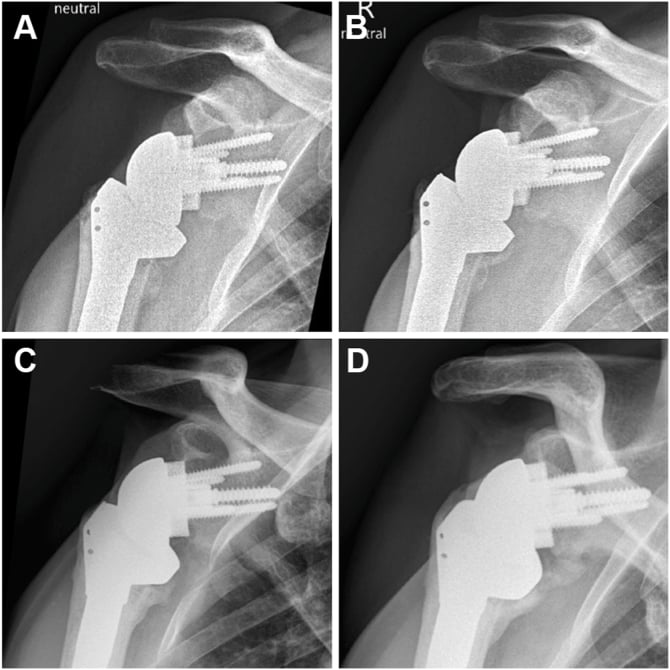
Acromial and scapular-spine stress fractures. These are a leading cause of unexplained pain and loss of elevation after a previously successful reverse arthroplasty. Reverse arthroplasty lengthens and tensions the deltoid by lowering and medialising the centre of rotation, and the repetitive deltoid pull fatigues the acromion or scapular spine into an insufficiency or stress fracture, most often in osteoporotic or rheumatoid bone.
Presentation and diagnosis. New superior or posterior shoulder pain with loss of previously gained active elevation and focal tenderness over the acromion or scapular spine, typically weeks to months after a satisfactory result. The fracture is frequently occult on plain radiographs, and a high index of suspicion with CT or bone scan is often required.
Levy (Crosby) classification by location:
- Type I: anterior acromion, anterior to the acromioclavicular joint (anterior deltoid origin)
- Type II: mid-acromion, posterior to the acromioclavicular joint and over the glenoid (middle deltoid origin)
- Type III: scapular spine
Type II and especially Type III cause the greatest functional loss. Management is predominantly non-operative, usually a sling or brace for 6-8 weeks with activity restriction. Internal fixation of the thin osteoporotic acromion or spine is technically difficult and unreliable, and outcomes after these fractures are often disappointing even when they unite.
Postoperative Care
The first six weeks after revision.
- Sling immobilisation for 6 weeks, against 2-4 weeks after a primary
- DVT prophylaxis, mechanical and chemical (aspirin or LMWH)
- Multimodal analgesia: regional block, paracetamol, NSAIDs, opioids as needed
- Daily wound inspection for drainage, erythema and dehiscence
- Timeframe
- 0-6 weeks
- Goals
- Protect repair, control pain, prevent stiffness
- Precautions
- Sling at all times, no active motion
- Timeframe
- 6-12 weeks
- Goals
- Restore passive motion
- Precautions
- Therapist-assisted only, respect tissue healing
- Timeframe
- 12-16 weeks
- Goals
- Active motion, begin isometrics
- Precautions
- No resisted exercises
- Timeframe
- 16-24 weeks
- Goals
- Progressive resistance, functional activities
- Precautions
- Avoid heavy lifting greater than 5kg
Slower than a primary. Rehabilitation after revision typically runs 4-6 weeks behind a primary, with strengthening delayed to 16-24 weeks against 12, and bone graft incorporation needs additional protection. The indication adjusts it further. After revision for instability, immobilisation may be prolonged to 8 weeks in the position of stability. After revision for infection, IV antibiotics continue as infectious disease guidance directs, typically for 6-12 weeks. After revision for fracture, activity is restricted until radiographic union.
Monitoring. CRP and ESR are checked weekly during IV antibiotics, then monthly for 3 months after an infection. Radiographs are taken at 6 weeks, 3, 6 and 12 months, then annually, and clinical review is 6-weekly in the first year, more often than after a primary arthroplasty.
Return to activity. Milestones after revision:
- Driving: 8-12 weeks, once an emergency manoeuvre is comfortable
- Sedentary work: 6-8 weeks
- Manual work: 4-6 months or longer, depending on healing
- Golf and swimming: 4-6 months at the earliest
Red flags. Urgent review is needed for new fever or wound drainage, sudden loss of range of motion, mechanical symptoms such as clunking or catching, and new neurological symptoms.
Revision Surgery: Principles and Outcomes
Preoperative planning.
- CT: bone stock, component position and version
- Infection workup: ESR, CRP, and aspiration if there is any concern
- Rotator cuff status by MRI or ultrasound, which determines revision to TSA or RSA
- Implant identification: know the existing system for its extraction tools
- Patient optimisation: nutrition (albumin over 3.5), diabetes (HbA1c under 7%), smoking cessation
The revision construct. On the glenoid side an RSA baseplate may give better fixation than a new TSA glenoid. On the humeral side a long-stem component is used if there is bone loss or fracture risk. Cemented fixation is preferred in the revision setting for immediate stability.
Converting failed anatomic TSA to RSA is now the most common revision scenario. The indications are glenoid loosening with rotator cuff deficiency, subscapularis failure, or an irreparable cuff tear. Glenoid bone loss, a humeral version mismatch (which may need osteotomy) and deltoid scarring are the challenges. Outcomes are 70-80% satisfactory against 85-90% for primary RSA.
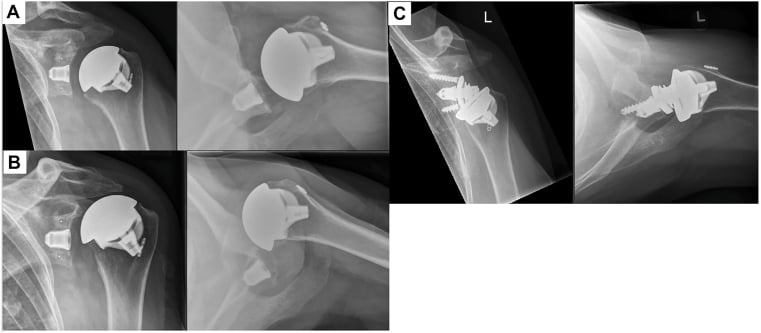
Counsel patients realistically. Revision shoulder arthroplasty has a 2-3x higher complication rate than primary surgery (15-20% against 5-8%) and 60-70% good to excellent outcomes against 85-90% for primary. Functional scores are typically 10-20 points lower on validated measures, and the risk of re-revision is 10-15% at 5 years. Recovery is slower, 6 months against 3-4 months, and return to the previous activity level is less predictable.
Outcomes
- Satisfactory Rate
- 70-80%
- Re-revision Rate
- 10-15% at 5 years
- Key Prognostic Factors
- Correct positioning, adequate soft tissue
- Satisfactory Rate
- 75-85%
- Re-revision Rate
- 8-12% at 5 years
- Key Prognostic Factors
- Bone stock, cemented fixation
- Satisfactory Rate
- 80-85%
- Re-revision Rate
- 5-10% at 5 years
- Key Prognostic Factors
- Organism virulence, host factors
- Satisfactory Rate
- 70-75%
- Re-revision Rate
- 12-18% at 5 years
- Key Prognostic Factors
- Bone quality, fracture pattern
- Satisfactory Rate
- 80-85%
- Re-revision Rate
- 8-12% at 5 years
- Key Prognostic Factors
- Deltoid function, glenoid bone stock
Function after revision. Active forward flexion averages 100-120°, against 140-150° after a primary RSA, and external rotation averages 20-30°. Patient satisfaction is 70-80%, against 85-90% after a primary. The ASES score improves by an average of 30-40 points, less than after a primary.
Prognostic factors. A single prior operation, adequate bone stock, an intact deltoid and a healthy patient predict a better result. Multiple prior revisions, massive bone loss, poor soft tissue and immunocompromise predict a worse one.
Registry signals (AOANJRR, NJR, Nordic).
- Reverse arthroplasty has a higher cumulative revision rate than anatomic TSA at comparable follow-up across the major registries
- Conversion of failed anatomic TSA to RSA generally outperforms revision RSA undertaken for failed RSA
- Instability or dislocation, infection and loosening or lysis are consistently the leading recorded reasons for revision
- Exact percentages vary by registry and report year and should be quoted from the current annual report rather than memorised
Survivorship. In typical reported ranges, primary TSA survives at approximately 90% at 10 years in cohort and registry series. Primary RSA survival is lower, broadly 85-90% depending on indication and design, and revision shoulder arthroplasty survivorship is markedly lower than primary.
Quality of life. Patients after a complication report lower satisfaction than after a primary. Persistent pain remains in 15-25% even after a successful revision, and anxiety about re-revision affects 30-40%.
Prevention Strategies
Infection.
- Optimise nutrition, control diabetes (HbA1c under 7%) and treat remote infections before surgery
- Cefazolin 2g (3g if over 120kg) within 60 minutes of incision
- Chlorhexidine-alcohol skin preparation, which is superior to povidone-iodine
- A benzoyl peroxide wash protocol for male patients, against C. acnes
- Iodine-impregnated drapes may reduce infection
Instability.
- Verify version and tilt intraoperatively with fluoroscopy, and ensure the minimum lateralisation in RSA
- Repair the subscapularis anatomically in TSA
- Trial-reduce and test stability through the arc before inserting the final components
- Avoid oversizing: the humeral component should not overstuff the joint
Glenoid loosening.
- Ream to cancellous bone and avoid anterior perforation
- Correct excessive retroversion to the target version
- Pressurise the cement with a finger or syringe
- The cemented all-polyethylene pegged glenoid is the standard component
- Consider RSA for young, high-demand patients
Nerve injury.
- Record preoperative nerve function as a baseline, which is also essential for medicolegal protection
- Avoid hyperextension and excessive abduction of the arm under anaesthesia
- Retract gently and avoid pressure on the neurovascular structures
- Release the inferior capsule under direct vision to protect the axillary nerve
- Avoid superior baseplate screws over 30mm long to protect the suprascapular nerve
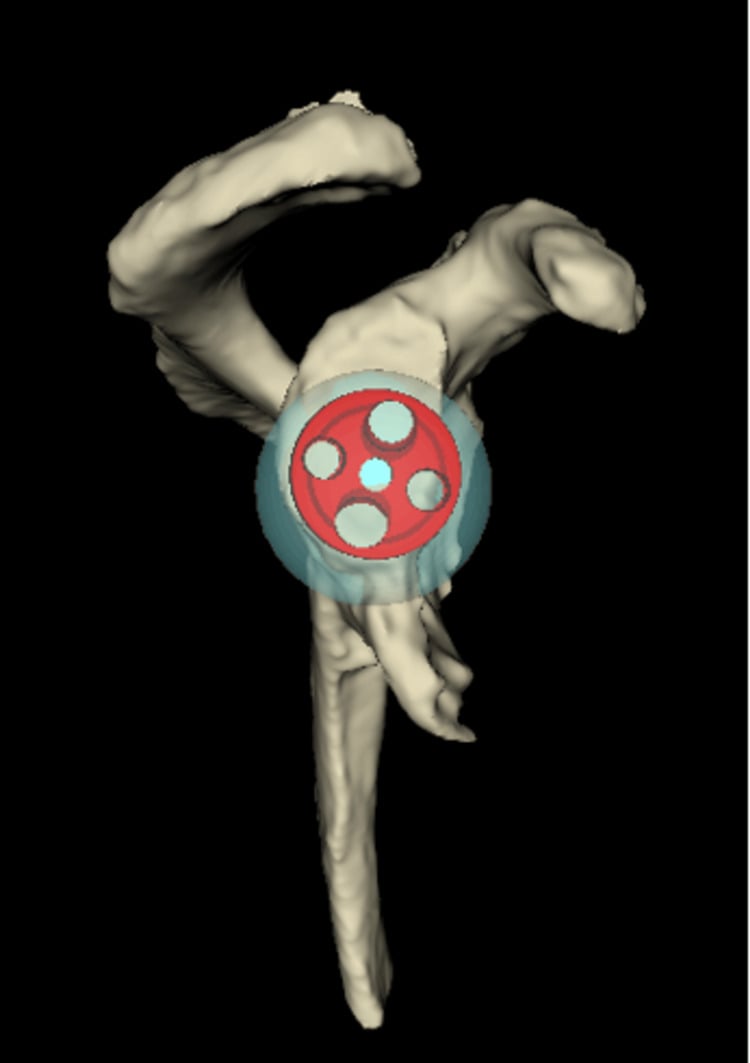
Templating and preoperative planning reduce complications by 30-40%. CT-based 3D planning assesses glenoid bone stock and version, plans the correction strategy, determines implant size and identifies anatomic variants. In complex cases (revision, massive bone loss, dysplasia), patient-specific instrumentation or guides may be beneficial.
Guidelines, Registries & Global Practice
Global epidemiology
Shoulder arthroplasty is one of the fastest-growing arthroplasty procedures worldwide, driven overwhelmingly by the expansion of reverse total shoulder arthroplasty (RSA) beyond cuff-tear arthropathy into osteoarthritis with cuff insufficiency, proximal humeral fracture, and revision of failed primaries. Population-based and registry analyses from North America, Europe and Australasia consistently show year-on-year increases in volume and a shift in case-mix toward RSA in older patients. Because indications and implant mix differ between regions, reported complication and revision rates must always be interpreted against the underlying population and implant design.
Major guidelines side by side
- Position relevant to complications
- Appropriate-use criteria and clinical practice guidance for glenohumeral OA and cuff arthropathy; emphasises shared decision-making and VTE prophylaxis; perioperative infection prevention per MSIS/ICM consensus
- Typical evidence level
- Mostly moderate/limited evidence; many consensus recommendations
- Position relevant to complications
- Generic surgical-site infection and prosthetic joint infection principles apply; BOAST standards stress prompt recognition and MDT management of infection and periprosthetic fracture; referral of suspected deep infection to a specialist unit
- Typical evidence level
- Consensus standards built on systematic review
- Position relevant to complications
- Periprosthetic and stem-related fracture classification and fixation principles (bridge the stem by adequate cortical diameters; revise loose stems); construct selection driven by component stability
- Typical evidence level
- Expert consensus and technique evidence
- Position relevant to complications
- Aligns with international PJI consensus (ICM) on diagnosis thresholds, prolonged culture for Cutibacterium, and staged versus single-stage revision; supports tailored, organism-led treatment
- Typical evidence level
- Consensus, level varies by question
The biggest international difference is in periprosthetic joint infection management for low-virulence Cutibacterium acnes: several European and shoulder-specialist groups now favour single-stage revision with prolonged targeted antibiotics for suitable cases, whereas much North American practice and classic teaching still defaults to two-stage revision. All major bodies agree on prolonged (14-day) culture incubation and a structured multi-criteria PJI diagnosis (synovial fluid analysis, multiple deep cultures, histology). Antibiotic prophylaxis is near-universal: a first-generation cephalosporin within 60 minutes of incision, with a glycopeptide for proven beta-lactam allergy or known MRSA colonisation.
Registry evidence (global)
- Contribution to complication knowledge
- Large, near-complete capture; reverse arthroplasty revised more than anatomic TSA; instability, infection and loosening lead revision causes; glenoid fixation type affects revision risk
- Contribution to complication knowledge
- Tracks implant-specific survivorship and revision indications for shoulder replacement, supporting outlier detection and implant benchmarking
- Contribution to complication knowledge
- Growing shoulder dataset; documents the dominance of RSA in contemporary US practice and associated revision patterns
- Contribution to complication knowledge
- Long follow-up; early registries highlighted high revision after hemiarthroplasty for OA and the influence of indication on outcome
Global practice variation
- Implant choice: RSA now predominates for cuff-deficient and fracture indications in high-resource settings; anatomic TSA is preferred for OA with an intact cuff and good glenoid bone stock. In limited-resource settings, hemiarthroplasty retains a larger role due to cost and implant availability, accepting a higher rate of glenoid erosion.
- Cutibacterium strategy: Routine prolonged culture and benzoyl-peroxide skin preparation are widely adopted in shoulder-specialist centres but inconsistently applied elsewhere.
- Revision pathway: Single-stage versus two-stage revision for low-virulence PJI varies by region and surgeon, reflecting genuine equipoise rather than a settled standard.
- Surveillance: Countries with mandatory or near-complete registries (Australia, Nordic countries, UK) provide the most reliable revision data; elsewhere, complication estimates rely on single-centre series and are more prone to under-reporting.
Key documentation requirements to reduce litigation risk:
-
Preoperative consent: Discuss specific complications (infection 2-6%, instability 1-10% depending on implant, nerve injury 1-4%, loosening requiring revision 10-15% by 10 years, need for future revision surgery). Document alternatives discussed (conservative management, arthroscopy, alternate implants).
-
Surgical site marking: Mark correct side with patient awake, verify with timeout before incision.
-
Implant tracking: Record implant type, size, lot numbers in medical record and registry. Keep implant stickers in patient chart.
-
Nerve function: Document preoperative axillary, musculocutaneous, radial nerve function. Reassess immediately postop and at all follow-ups. If deficit develops, obtain EMG at 3-4 weeks and document management plan.
-
Component positioning: Intraoperative fluoroscopy images showing component position. Consider postoperative CT for complex cases or instability.
-
Infection prevention: Document prophylactic antibiotic timing, dose, and agent. Note skin preparation technique. Record implant handling protocols.
-
Informed consent for revision: Higher complication rates (2-3x primary), lower functional outcomes (10-20 points on outcome scores), possibility of further revision surgery.
Common litigation issues: Nerve injury not documented preoperatively (difficult to prove timing), infection attributed to inadequate prophylaxis or poor technique, component malposition causing instability or loosening, failure to recognize and treat complications promptly, inadequate consent discussion of revision risk.
- Prophylaxis: First-generation cephalosporin (e.g. cefazolin) within 60 minutes of incision; weight-adjusted dosing
- Beta-lactam allergy / MRSA risk: Glycopeptide (vancomycin or teicoplanin), started early enough for adequate tissue levels
- Cutibacterium acnes PJI: Penicillin or amoxicillin-based regimens (high in-vitro susceptibility), prolonged duration for biofilm
- Staphylococcal PJI with retained implant: Add rifampicin-based combination per infection-specialist guidance
- Always confirm agent, dose and duration with local infection guidelines and antimicrobial stewardship
MCQ Practice Points
Q: Which nerve is at highest risk during deltopectoral approach for shoulder arthroplasty?
A: Axillary nerve (1-4% injury rate). The axillary nerve exits the quadrilateral space and travels along the inferior capsule and undersurface of the deltoid. It is at risk during inferior capsular release, deltoid retraction, and placement of inferior retractors. Always document preoperative deltoid function and sensory examination over lateral shoulder for medicolegal protection. Most injuries are neurapraxias recovering within 3-6 months.
Q: How are glenoid radiolucent lines assessed, and why does it matter?
A: Two separate things are recorded. The zones locate the line around the component: superior (Zone 1), anterior (Zones 2-3), inferior (Zone 4) and posterior (Zone 5). The Lazarus grade then scores its extent on an ordinal 0-to-5 scale (Lazarus et al., J Bone Joint Surg Am 2002;84:1174-82), where 0 is no radiolucency and 5 is gross loosening; Franklin described the original scheme for keeled components and Lazarus modified it for pegged ones. Lines less than 1mm are often benign and stable; lines greater than 2mm or progressive lines indicate loosening. Complete lucency in all zones suggests gross loosening requiring revision. This system helps standardize radiographic assessment and predict need for revision surgery.
Q: What is the optimal antibiotic regimen for Cutibacterium (formerly Propionibacterium) acnes shoulder PJI?
A: For P. acnes infection, the recommended regimen is penicillin G 18-24 million units/day IV for 4 weeks, followed by oral amoxicillin 2-6 months (total 6-12 weeks therapy). P. acnes is sensitive to penicillin in over 95% of cases. This indolent organism requires prolonged therapy due to biofilm formation. Cultures must be held 14 days as P. acnes is slow-growing and often missed with standard 5-day protocols.
Q: What is scapular notching in RSA and when is it clinically significant?
A: Scapular notching occurs when the inferior glenosphere impinges on the lateral scapular neck during adduction, causing bone erosion. It is very common (44-96% radiographically) but clinically significant in less than 10%. The Nerot-Sirveaux classification grades notching from Grade 1 (limited to pillar) to Grade 4 (extending to baseplate). Clinical significance occurs with Grade 3-4 notching causing pain, baseplate screw loosening, or loss of adduction. Prevention strategies include inferior glenosphere tilt, lateralization, and inferior eccentric glenosphere positioning.
Q: What do the major joint registries show about shoulder arthroplasty revision rates?
A: Across the large national registries (AOANJRR in Australia, NJR in England and Wales, AJRR in the USA, and the Nordic/Swedish registries), shoulder arthroplasty has among the higher revision burdens of the major joints, and reverse arthroplasty carries a higher cumulative revision rate than anatomic TSA at comparable follow-up. The leading recorded reasons for revision are consistently instability/dislocation, infection, and loosening/lysis. Glenoid fixation matters: registries have linked certain uncemented and metal-backed glenoid constructs to higher revision than cemented all-polyethylene designs. Quote exact percentages from the current annual report, as figures shift between reports.
Q: How do you manage a periprosthetic humeral shaft fracture (Vancouver Type B2) after shoulder arthroplasty?
A: Vancouver Type B2 indicates a fracture around or just below the stem with loose component. Management requires revision to a long-stem prosthesis (bypassing fracture by minimum 2 cortical diameters) with or without supplemental fixation (cables, cerclage wires, or plate). The fracture is typically addressed with cerclage cables proximally and a long-stem (150-200mm) cemented component for immediate stability. If bone quality is very poor (Type B3), structural allograft may be needed. Component retention (Type B1, stable component) can be managed with ORIF alone using cables and plate while preserving the stable prosthesis.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 72-year-old woman presents 6 weeks after reverse shoulder arthroplasty for rotator cuff arthropathy. She fell onto her operated shoulder yesterday and now has pain and inability to use her arm. X-rays show the humeral component dislocated anteriorly off the glenosphere. How do you assess and manage this patient?”
“A 58-year-old man presents with persistent shoulder pain 9 months after anatomic total shoulder arthroplasty for primary osteoarthritis. He describes constant aching pain that is worse at night and limits his function. He denies fever or wound issues. Inflammatory markers show CRP 18 mg/L (normal less than 5) and ESR 32 mm/hr (normal less than 20). Walk me through your diagnostic workup and management.”
“A 52-year-old active manual laborer presents 7 years after anatomic TSA for post-traumatic arthritis. He has progressive pain over 18 months, mechanical clicking, and reduced ROM. Radiographs show complete radiolucent lines around the glenoid component in all five periglenoid zones, with 5mm of superior tilt. CT shows cavitary bone loss posteriorly. How do you manage this case?”
Major Complications by Frequency
- Instability: 5-10% RSA (anterior escape), 1-3% TSA (anterior from subscap failure, posterior from retroversion)
- Glenoid loosening: 20-30% radiolucent lines by 10 years, 5-10% symptomatic revision
- Infection: 2-6% overall, P. acnes 30-40% (males, indolent), S. epi 25-30%
- Nerve injury: Axillary 1-4% (most common), musculocutaneous 0.5-1%, 80-90% recover
Classification and Timing
- Early (less than 3mo): Infection, nerve injury, instability, fracture
- Intermediate (3mo-2yr): Periprosthetic fracture, component loosening
- Late (over 2yr): Glenoid wear, osteolysis, subscapularis failure, cuff tear
- Periglenoid zones: Superior (1), anterior (2-3), inferior (4), posterior (5); then grade the line 0-5 (Lazarus) - assess width and progression
Management Algorithms
- Instability: CT to assess components, closed reduction if well-positioned, revise if malpositioned (insufficient lateralization less than 25mm, excessive retroversion over 30 degrees, superior tilt over 10 degrees)
- Infection: Aspiration with 14-day culture for P. acnes, debridement if acute less than 4wks, two-stage revision if chronic or biofilm
- Glenoid loosening: MRI for cuff integrity, revision TSA if cuff intact, convert to RSA if cuff deficient, bone graft in 30-50%
- Nerve injury: Document preop, EMG at 3-4wks if no recovery, explore if no recovery by 6mo
Surgical Pearls
- RSA instability prevention: Lateralization minimum 25mm, humeral retroversion 20-30 degrees, correct glenoid tilt (less than 10 degrees superior)
- Infection prevention: Cefazolin 2g (3g if over 120kg) within 60min, chlorhexidine alcohol prep, benzoyl peroxide for males (P. acnes)
- Glenoid loosening prevention: Cemented all-poly pegged glenoid, pressurize cement, correct version to 5-10 degrees retroversion
- Nerve protection: Gentle retraction, avoid hyperextension positioning, inferior capsule release under vision
Key Evidence and Registry Data
- Walch 2012 (PMID 22258001): 32% radiographic glenoid loosening in 518 keeled all-poly TSA at over 5 years (superior tilt, subsidence, posterior tilt)
- Zumstein 2011 (PMID 21134666): RSA complication rate ~44%, scapular notching most frequent finding
- Sirveaux 2004 (PMID 15125127): origin of the four-grade scapular notching classification; Constant 22.6 to 65.6
- Registries (AOANJRR/NJR/AJRR/Nordic): RSA revised more than anatomic TSA; instability, infection and loosening lead causes
- Revision outcomes generally inferior to primary with higher complication rates
Global Practice and Governance
- Near-complete registries (Australia, Nordic, UK) give the most reliable revision data; elsewhere rates rely on single-centre series
- Cutibacterium PJI: prolonged 14-day culture universal; single-stage vs two-stage revision varies by region (genuine equipoise)
- Prophylaxis: first-generation cephalosporin within 60 min; glycopeptide for proven allergy or MRSA
- Medicolegal: document preop nerve function, consent for revision risk, and implant tracking
Evidence Base and Key Trials
Complications of Shoulder Arthroplasty
- Comprehensive review updating the classic 2006 complication analysis, framing complications by component and implant type
- Glenoid component loosening remains the most frequently reported complication of anatomic total shoulder arthroplasty
- Instability, glenoid/baseplate problems, infection and neural injury are emphasised as the dominant reverse arthroplasty complications
- Highlights the rising share of reverse arthroplasty and its distinct complication profile compared with anatomic TSA
Problems, complications, reoperations, and revisions in reverse total shoulder arthroplasty: a systematic review
- Systematic review of 782 reverse arthroplasties pooled to define a complication taxonomy (problem, complication, reoperation, revision)
- Overall complication rate approximately 44% across 782 shoulders, with scapular notching the single most frequent finding
- That 44% is a DEFINITIONAL figure as much as a clinical one: it counts the full spectrum down to minor problems that never altered the final result, which is why later series quoting only clinically significant complications report roughly 15-24%
- Instability and infection were among the leading reasons for reoperation and revision
- Established the standard framework now used to report reverse arthroplasty adverse events
Complications in reverse total shoulder arthroplasty
- Narrative review of the complications unique to reverse arthroplasty as indications expanded beyond cuff arthropathy
- Lists the most common complications as neurologic injury, periprosthetic fracture, haematoma, infection, scapular notching, dislocation, baseplate failure and acromial fracture
- Notes the limited published evidence guiding best management of each complication
- Reinforces dislocation/instability as a leading early mode of failure