Perioperative Optimisation | Pharmacotherapy | Timing Strategies
- 4-8 weeks preoperative cessation cuts postoperative complications - pooled RCT relative risk reduction 41% (95% CI 15-59), with each additional week adding about 19% to the effect
- Nonunion risk roughly doubled in smokers (meta-analysis OR ~2.3; tibia 2.16, open fractures 1.95 - older single-site series quote up to 4-8x)
- Surgical site infection increased in smokers (large-registry adjusted OR ~1.4; older small series quote 3-6x)
- Varenicline most effective - triples quit rates compared to placebo
- Continue cessation postoperatively - 12+ weeks for bone healing
- “Even brief cessation (3-4 weeks) improves wound healing
- “Nicotine replacement does NOT increase complications
- “Document smoking status and counselling in notes
- “Cessation pharmacotherapy (varenicline, NRT, bupropion) is recommended and widely subsidised internationally
Overview and Epidemiology
Smoking is the single most modifiable risk factor for orthopaedic complications, and effective cessation strategies can dramatically improve outcomes in fracture healing, spinal fusion and arthroplasty. Surgeons have a duty to counsel every patient and to document smoking status.
Who smokes. About 20% of adults smoke globally (GBD 2019). Orthopaedic patients typically smoke more than the general population, particularly in trauma cohorts, where rates of 20-30% are quoted. Studies report a prevalence of 20-40% among patients presenting for fracture care or elective procedures [1].
What it costs. The global burden is enormous, trillions of dollars annually worldwide (WHO). In orthopaedics the cost arrives through complications: higher healthcare costs, longer hospital stays with smoking-related complications, and return to work delayed by healing complications.
What is available. Cessation pharmacotherapy (varenicline, NRT, bupropion) is subsidised in most national formularies, and telephone cessation counselling services operate in most countries.
There is a legal and professional responsibility to document:
- Current smoking status (pack-years)
- Cessation counselling provided
- Pharmacotherapy offered
- Patient response and quit plan
- Follow-up arranged
Failure to document may constitute substandard care.
Pathophysiology of Smoking on Orthopaedic Healing
Tobacco smoke is a mixture, and its components damage healing in different ways.
- Mechanism
- Alpha-adrenergic stimulation to vasoconstriction
- Orthopaedic Impact
- Tissue hypoxia, impaired healing
- Mechanism
- Binds haemoglobin, reduces O2 delivery
- Orthopaedic Impact
- Hypoxia, impaired cellular metabolism
- Mechanism
- Cytochrome oxidase inhibition
- Orthopaedic Impact
- Impaired cellular respiration
- Mechanism
- Oxidative stress, inflammation
- Orthopaedic Impact
- Chronic tissue damage
- Mechanism
- Osteoblast toxicity
- Orthopaedic Impact
- Reduced bone formation
Nicotine is the vasoconstrictor. Carbon monoxide, hydrogen cyanide and tar are combustion products, absent from nicotine replacement, and that distinction is why NRT is safe around surgery (see Intraoperative Considerations).
The osteoblast. Nicotine reduces osteoblast function and impairs vascular supply. Smoking reduces osteoblast proliferation and differentiation, lowers alkaline phosphatase activity and impairs bone matrix production. The cells also respond less to BMP-2 and other growth factors [2,3].
The callus blood supply. VEGF expression falls, fewer capillaries form in the fracture callus, the haematoma organises poorly and revascularisation is delayed [4]. Endothelial dysfunction and microvascular damage add to the impaired angiogenesis.
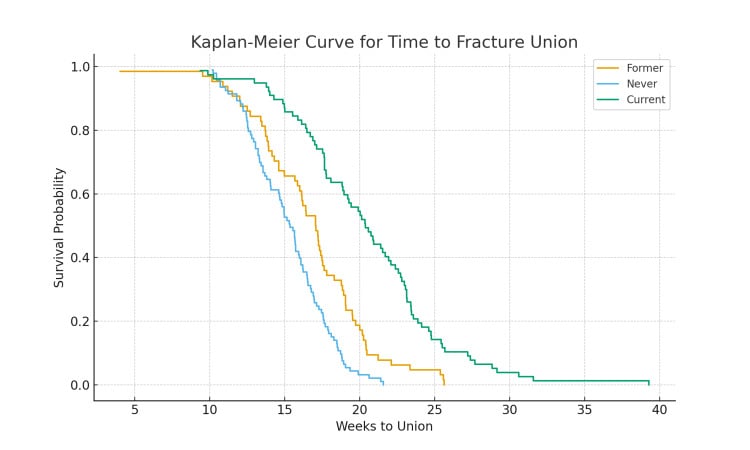
What that does to union. The callus is weaker and less stiff, and mineralisation is delayed. Radiographic union takes longer, and delayed union and nonunion are more common [5].
Tissue hypoxia. Nicotine vasoconstricts through alpha-adrenergic stimulation, and carbon monoxide reduces the blood's oxygen-carrying capacity. Tissue PO2 falls by 30-50% and cellular metabolism is impaired [6].
Immune function. Neutrophil chemotaxis and phagocytosis are reduced, complement activation is impaired, antibody production decreases and macrophage function is reduced [7].
Fibroblasts. Fibroblast proliferation and migration are reduced, synthesis of type I and III collagen falls, extracellular matrix deposition is impaired and epithelialisation is delayed [8].
What that does to the wound. Wound dehiscence is more common, healing is delayed and scarring can be hypertrophic. Surgical site infection is increased, but by less than the older literature suggests: small series quote rates 3-6 times higher, whereas the adjusted registry figure after arthroplasty is an odds ratio of about 1.4, and after fracture the increase did not reach significance (see Complications).
Around an implant. In arthroplasty smoking enhances biofilm formation, reduces antibiotic penetration and impairs host defences [9]. Osseointegration is impaired, bone quality around the implant is reduced and wear particle-induced osteolysis is accelerated, with higher revision rates at 10 years [10]. Other problems in smokers are an increased dislocation risk after THA, periprosthetic fracture, delayed mobilisation and a longer hospital stay.
Carbon monoxide. CO binds haemoglobin with roughly 200-250 times the affinity of oxygen (about 240 times), so even small inhaled amounts form substantial carboxyhaemoglobin (COHb), typically up to about 5-10% in smokers against 1-2% in non-smokers.
Two hits to oxygen delivery. COHb reduces oxygen-carrying capacity, because fewer haemoglobin sites are available for oxygen, and it left-shifts the oxyhaemoglobin dissociation curve, so the oxygen that is carried is released less readily to the tissues. Both come on top of nicotine's vasoconstriction.
Why quitting helps within a day. CO has a half-life of only about 4-6 hours breathing room air, shorter with supplemental oxygen, so COHb largely normalises within 12-24 hours of the last cigarette. That is the physiological basis for the immediate improvement in tissue oxygenation, well before any wound or bone effect.
Standard pulse oximetry cannot distinguish COHb from oxyhaemoglobin, so in a recent smoker the SpO2 reads falsely high. Co-oximetry, or an arterial blood gas with co-oximetry, is needed to measure the true oxygen saturation. Exhaled-CO monitoring exploits the same chemistry to verify recent smoking.
Classification
Smoking status. Classify every patient first by status, which sets both the risk and the intervention.
- Definition
- Smoked in past 30 days
- Risk Level
- Highest risk
- Intervention
- Intensive cessation intervention
- Definition
- Quit within past 12 months
- Risk Level
- Elevated risk, high relapse
- Intervention
- Relapse prevention, continued support
- Definition
- Quit greater than 12 months ago
- Risk Level
- Moderately elevated
- Intervention
- Positive reinforcement, monitor
- Definition
- Less than 100 cigarettes lifetime
- Risk Level
- Baseline risk
- Intervention
- No intervention needed
Pack-years. Pack-years = (cigarettes per day ÷ 20) × years smoked, so 20 cigarettes a day for 25 years is 25 pack-years. The bands below grade exposure and the urgency of cessation.
- Exposure
- Low
- Complication Risk
- Increased, at the lower end of the range (moderate complication risk)
- Cessation Urgency
- Moderate priority
- Exposure
- Moderate
- Complication Risk
- Increased (significant complication risk)
- Cessation Urgency
- High priority
- Exposure
- High
- Complication Risk
- Highest reported risk (major complication risk); consider delay
- Cessation Urgency
- Critical priority
- Exposure
- -
- Complication Risk
- Highest reported risk; current smoking matters more than cumulative exposure
- Cessation Urgency
- Immediate intervention
Be careful what you claim about dose. A dose-response relationship between smoking intensity and complications is consistently described, but the published effect sizes are pooled across all smokers, not stratified by pack-year band: nonunion adjusted OR 2.32 overall (Scolaro), SSI adjusted OR 1.41 after arthroplasty (Singh). Neither source reports a graded ladder of numbers, so quoting a specific multiplier for a specific band ("6-8x over 20 pack-years") attaches false precision to a real trend.
Status matters more than dose. In the arthroplasty registry data current smoking carried the clearest excess risk, with prior smokers showing smaller and mostly non-significant increases. Smoking status at the time of surgery is therefore a more useful stratifier than cumulative dose.
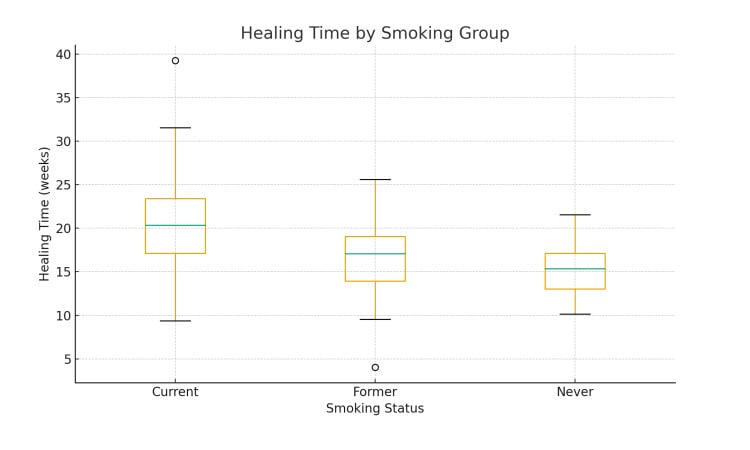
Dependence: the Fagerström test. Pack-years measure exposure; the Fagerström Test for Nicotine Dependence measures dependence. Its questions:
- How soon after waking do you smoke your first cigarette?
- Do you find it difficult to refrain from smoking in places where it is forbidden?
- Which cigarette would you hate most to give up?
- How many cigarettes per day do you smoke?
- Do you smoke more frequently in the first hours after waking?
- Do you smoke if you are so ill that you are in bed most of the day?
The score is read as 0-2 very low, 3-4 low, 5 medium, 6-7 high and 8-10 very high dependence.
Higher Fagerström scores predict more severe withdrawal and lower quit success. These patients may benefit from higher-dose NRT or combination pharmacotherapy (varenicline + NRT). A first cigarette within 30 minutes of waking is a key marker of high dependence.
Clinical Assessment
History. Record current status (current, former, never), cigarettes per day and pack-years, previous quit attempts and the methods used, and the reasons for any relapse. Ask about readiness to quit (stages of change) and household or social exposure to smoke.
Examination. Look for tobacco staining of the fingers and teeth, chronic cough or sputum production, signs of COPD (barrel chest, prolonged expiration) and signs of peripheral vascular disease. Note the quality of wound healing after any previous surgery.
Smoking-related comorbidities affect surgical risk:
- COPD - optimise with inhalers, consider pulmonary function testing
- Coronary artery disease - cardiac risk assessment
- Peripheral vascular disease - wound healing concerns
- Poor nutrition - common in heavy smokers
- Psychiatric comorbidity - depression, anxiety (affects cessation success)
Readiness to change. The stage the patient is in decides the intervention.
- Description
- Not considering quitting
- Intervention
- Motivational interviewing, 5 R's
- Description
- Thinking about quitting
- Intervention
- Explore ambivalence, discuss benefits
- Description
- Planning to quit soon
- Intervention
- Set quit date, prescribe pharmacotherapy
- Description
- Actively quitting
- Intervention
- Support, manage withdrawal
- Description
- Sustained abstinence
- Intervention
- Relapse prevention strategies
Risk stratification. Intensity and time since quitting combine into a working risk profile, and the profile sets the timing of elective surgery.
- Complication Risk
- Very high
- Recommended Action
- Intensive cessation, consider delay
- Surgical Timing
- Delay elective 8+ weeks
- Complication Risk
- High
- Recommended Action
- Standard cessation intervention
- Surgical Timing
- Delay elective 4-8 weeks
- Complication Risk
- Moderate-high
- Recommended Action
- Continue support, avoid relapse
- Surgical Timing
- Proceed with monitoring
- Complication Risk
- Moderate
- Recommended Action
- Continue support, reinforce
- Surgical Timing
- Proceed with standard care
- Complication Risk
- Low-moderate
- Recommended Action
- Positive reinforcement
- Surgical Timing
- Proceed with standard care
When healing fails. In a smoker whose fracture or wound will not heal, smoking is rarely the only contributor. The examiner expects a structured differential, so that smoking is not used as a lazy catch-all and reversible co-factors are not missed.
- Key Examples
- Smoking, diabetes, malnutrition, vitamin D deficiency, NSAIDs, steroids
- Distinguishing Features
- Multiple modifiable factors; smoking confirmed by history/cotinine
- How It Changes Management
- Optimise all factors, not smoking alone; glycaemic and nutritional correction
- Key Examples
- Inadequate fixation, excessive fracture gap, instability, malreduction
- Distinguishing Features
- Hardware loosening or motion on imaging; gap visible on radiographs
- How It Changes Management
- Revision fixation or grafting - not solved by cessation alone
- Key Examples
- Open/high-energy injury, soft-tissue stripping, atrophic nonunion, AVN
- Distinguishing Features
- Avascular bone ends, atrophic callus on imaging
- How It Changes Management
- Biological augmentation (graft, BMP), vascularised options
- Key Examples
- Septic (infected) nonunion, low-grade biofilm infection
- Distinguishing Features
- Pain, raised inflammatory markers, sinus, positive cultures
- How It Changes Management
- Debridement, targeted antibiotics, staged reconstruction
- Key Examples
- Hypothyroidism, hyperparathyroidism, hypogonadism
- Distinguishing Features
- Abnormal metabolic bone screen
- How It Changes Management
- Treat underlying endocrinopathy before revision
Investigations
Self-report. Asking is the standard in clinical practice, and self-report is generally accurate when the patient trusts the provider. It may under-report in settings where there are consequences, which is where biochemical markers come in.
- Sample
- Breath
- Detection Window
- 4-6 hours
- Sensitivity
- High for recent use
- Use
- Point-of-care
- Sample
- Blood/urine/saliva
- Detection Window
- 3-4 days
- Sensitivity
- Very high
- Use
- Gold standard
- Sample
- Blood
- Detection Window
- 1-2 weeks
- Sensitivity
- Moderate
- Use
- Research only
Reading a cotinine. Below 10 ng/mL (serum or urine) indicates a non-smoker, 10-100 ng/mL a light smoker or heavy secondhand exposure, and over 100 ng/mL an active smoker. Passive smoke exposure can elevate levels and renal impairment affects clearance.
Cotinine and NRT. NRT use causes a positive cotinine. Anabasine, a tobacco-specific alkaloid that is not present in NRT, differentiates NRT use from continued smoking, but it is more expensive and less widely available.
Routine biochemical verification is NOT required in clinical practice. Consider testing when:
- Research protocol requires verification
- High-stakes situation (surgery contingent on cessation)
- Strong suspicion of non-disclosure
- Medicolegal documentation needed
Preoperative workup. The smoking history guides what else to request:
- Chest X-ray, if over 20 pack-years or symptoms
- Spirometry, if COPD is suspected
- ECG, if there are cardiac risk factors
- Blood gas or SpO2 at rest, if there are respiratory symptoms
Management
The principle. A minimum of 4 weeks of preoperative cessation reduces complications, and 8+ weeks is optimal. For bone-healing procedures cessation continues for 12+ weeks after surgery. The time available before theatre decides the approach.
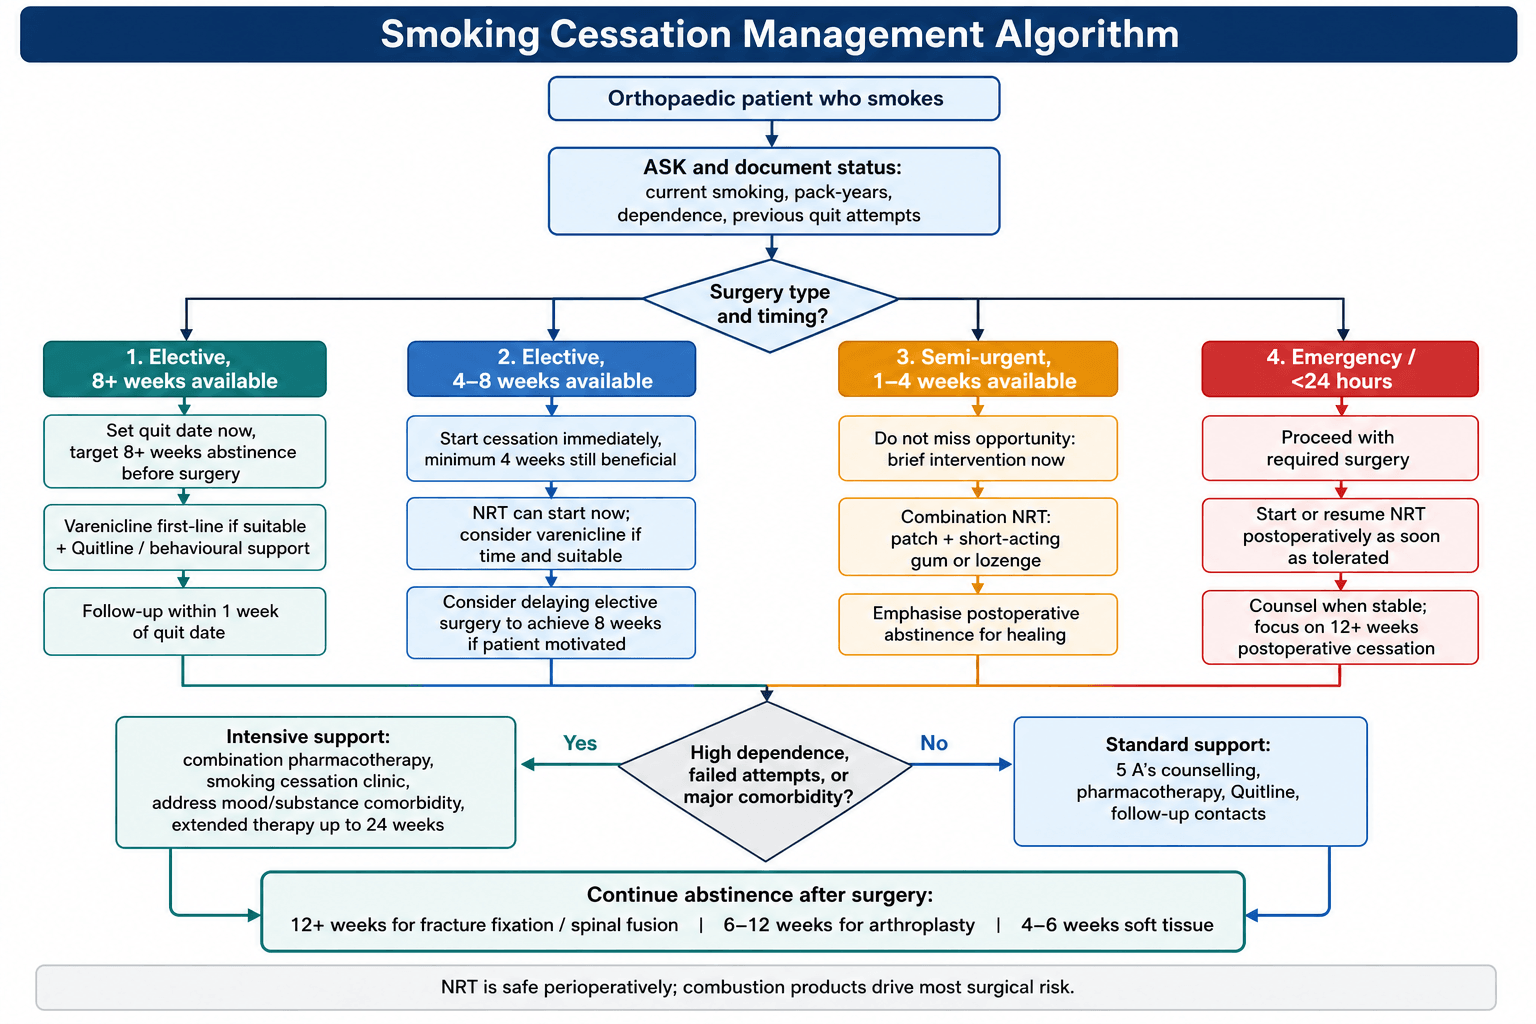
- Time to Surgery
- 8+ weeks
- Pharmacotherapy
- Varenicline (first-line)
- Behavioural Support
- Telephone support + regular follow-up
- Time to Surgery
- 4-8 weeks
- Pharmacotherapy
- NRT (immediate start)
- Behavioural Support
- Brief intervention + telephone support
- Time to Surgery
- 1-4 weeks
- Pharmacotherapy
- NRT (patch + short-acting)
- Behavioural Support
- Brief intervention, postop focus
- Time to Surgery
- Less than 24 hours
- Pharmacotherapy
- NRT postoperatively
- Behavioural Support
- Counselling when stable, 12-week postop focus
Timing by procedure. The procedure sets how long cessation should run on each side of surgery. Bone-healing procedures need the longest postoperative abstinence.
- Preoperative Cessation
- 8+ weeks ideal
- Postoperative Duration
- 12+ weeks (fusion consolidation)
- Priority
- Critical - highest pseudarthrosis risk
- Preoperative Cessation
- 4-8 weeks
- Postoperative Duration
- 12+ weeks (complete bone healing)
- Priority
- Critical - nonunion adjusted OR 2.32
- Preoperative Cessation
- 4-8 weeks
- Postoperative Duration
- 6-12 weeks (wound healing and osseointegration)
- Priority
- High - SSI adjusted OR 1.41, pneumonia OR 1.53
- Preoperative Cessation
- 4 weeks
- Postoperative Duration
- 2-4 weeks (tissue healing)
- Priority
- Moderate - lower but measurable risk
- Preoperative Cessation
- 4 weeks
- Postoperative Duration
- 4-6 weeks (wound healing completion)
- Priority
- Moderate - wound complications
The first-line approach. For every smoker listed for surgery:
- Brief counselling (5 A's framework)
- Pharmacotherapy - offer to ALL motivated smokers
- Telephone cessation counselling referral
- Set quit date - ideally 8+ weeks before surgery
- Follow-up - within 1 week of quit date
Stepped care, level 1: brief intervention for all smokers. Ask, Advise, Refer, in less than 5 minutes, and prescribe pharmacotherapy or refer.
Level 2: standard care for motivated smokers. Full 5 A's counselling, a pharmacotherapy prescription, telephone cessation counselling referral and 2-4 follow-up contacts.
Level 3: intensive support for high dependence or failed previous attempts. Combination pharmacotherapy (varenicline + NRT or bupropion + NRT), smoking cessation clinic referral, multiple behavioural sessions and extended pharmacotherapy (24 weeks). Comorbidities are addressed as well: depression, anxiety, other substance use.
Pregnancy: Behavioural counselling first-line; NRT if behavioural fails (benefits likely outweigh risks); avoid varenicline/bupropion.
Mental health conditions: Can and should quit; may need higher doses or combination therapy; coordinate with psychiatry; quitting improves long-term mental health.
Intraoperative Considerations
Anaesthesia. Smokers have increased airway reactivity, with a higher risk of bronchospasm, and impaired mucociliary clearance, so secretions need managing. They may need higher oxygen concentrations, and because carbon monoxide displaces oxygen, oxygenation should be optimised. Monitor for bronchospasm during intubation and extubation.
Monitoring. SpO2 may be falsely elevated in recent smokers by carboxyhaemoglobin (see Pathophysiology). Consider an arterial blood gas if there is concern about tissue oxygenation.
Surgical technique. Wound healing is impaired, so haemostasis must be meticulous. Consider tissue-sparing approaches when possible, avoid excessive tension on the wound closure, and place incisions thoughtfully, away from pressure points.
Nicotine replacement through surgery. The patch stays on throughout:
- Recommendation
- Apply nicotine patch as usual
- Recommendation
- Continue patch (or apply new one)
- Recommendation
- Leave patch in place
- Recommendation
- Monitor, continue NRT
- Recommendation
- Resume/continue all NRT forms as tolerated
Why it stays on. Continuing NRT brings no increase in wound complications, reduces withdrawal symptoms and agitation, and decreases postoperative relapse risk. Some anaesthetists request stopping NRT preoperatively; this is not evidence-based and increases relapse risk.
The toxic effects of smoking come primarily from combustion products (carbon monoxide, tar, hydrogen cyanide), NOT nicotine alone. Nicotine without them is relatively safe, and the harm from combustion products far exceeds any theoretical nicotine concern. NRT does not increase perioperative complications and is safe and recommended [11].
Complications
- Setting
- Meta-analysis, 19 cohort studies
- Adjusted Effect
- OR 2.32 (95% CI 1.76-3.06)
- Source
- Scolaro 2014
- Setting
- Meta-analysis subgroup
- Adjusted Effect
- OR 2.16 (95% CI 1.55-3.01)
- Source
- Scolaro 2014
- Setting
- Meta-analysis subgroup
- Adjusted Effect
- OR 1.95 (95% CI 1.3-2.9)
- Source
- Scolaro 2014
- Setting
- 357 instrumented L4-S1 fusions
- Adjusted Effect
- 26.5% smokers vs 14.2% non-smokers
- Source
- Glassman 2000
- Setting
- 33,336 primary THR/TKR
- Adjusted Effect
- OR 1.41 (95% CI 1.16-1.72)
- Source
- Singh 2011
- Setting
- 33,336 primary THR/TKR
- Adjusted Effect
- OR 1.53 (95% CI 1.10-2.14)
- Source
- Singh 2011
- Setting
- 33,336 primary THR/TKR
- Adjusted Effect
- OR 2.61
- Source
- Singh 2011
- Setting
- 33,336 primary THR/TKR
- Adjusted Effect
- OR 1.63 (95% CI 1.31-2.02)
- Source
- Singh 2011
- Setting
- Meta-analysis, 19 studies
- Adjusted Effect
- Trend only - NOT significant (p=0.13, p=0.33)
- Source
- Scolaro 2014
- Setting
- Rotator cuff repair
- Adjusted Effect
- Increased risk
- Source
- Mallon 2004
Where the risk concentrates. Nonunion risk is roughly doubled in smokers, and pseudarthrosis after lumbar fusion likewise. Smoking is particularly critical in tibial, femoral neck and scaphoid fractures, and wound complications are particularly high-risk after total joint arthroplasty and in open fractures. Older single-site series quote nonunion multipliers of up to 4-8x in tibial and open fractures; the meta-analytic figures above are the ones to quote.
Absolute rates are not in the table. Apart from the fusion rates Glassman actually observed, there are no paired smoker-versus-non-smoker percentages, because the pooled sources report adjusted odds ratios, not absolute rates. Inventing a baseline to sit beside them manufactures precision that no study supports.
Infection after fracture is not significant. Scolaro's meta-analysis found only a non-significant trend. The confident infection multipliers often quoted for fracture surgery come from the arthroplasty literature, where the effect is significant but is closer to 1.4 than to 3-6.
Nonunion in a smoker. Address smoking before any revision surgery, and keep a higher index of suspicion at follow-up. Bone stimulation may help, though the evidence is limited, and biologics (BMP, bone graft) should be considered.
Wound infection in a smoker. Have a lower threshold for deep samples, expect that a longer antibiotic course may be needed, and add wound healing support measures.
When complications occur in a patient who continued smoking despite counselling:
- Document prior counselling in original consent/notes
- Counsel again about cessation before any revision surgery
- Do not be punitive but be clear about the cause
- Consider second opinion for complex revision scenarios
- Maintain non-judgemental therapeutic relationship
Postoperative Care
The first days (day 0-3). Continue or resume NRT as soon as tolerated; if the patch was removed for surgery, reapply it in PACU. Provide short-acting NRT for breakthrough cravings, and acknowledge how difficult quitting is during recovery.
On the ward. The smoke-free hospital environment supports abstinence. Treat pain adequately, because pain increases relapse risk, offer ongoing behavioural support and consider an inpatient smoking cessation consultation.
How long. Abstinence runs for the procedure-specific duration in the timing table under Management.
The postoperative period is critical - bone healing and fusion consolidation occur over 12+ weeks. Patients must understand that their surgical outcome depends on maintaining abstinence through this entire period, not just until discharge.
When relapse threatens. The first 1-2 weeks carry the highest risk. Hospital discharge returns the patient to their triggers, pain crises bring back smoking as a way of coping, and recovery brings stress and boredom.
Preventing it. Continue pharmacotherapy through the healing period (minimum 12 weeks), and consider extended pharmacotherapy (24 weeks) for high-risk patients. Schedule follow-up contact specifically for cessation support, identify triggers and develop coping strategies, and engage family and social support.
Follow-up.
- Week 1-2: Phone or in-person check on cessation status
- Week 6: Surgical review + reinforce cessation
- Week 12+: Review healing + celebrate sustained cessation
- Ongoing: Continue offering support at all visits
Outcomes
Complications fall. Pooling 6 RCTs, preoperative cessation produced a 41% relative risk reduction in postoperative complications (95% CI 15-59), with a relative risk of 0.76 in the observational data (Mills 2011). Theadom (2006) found a significant reduction in intraoperative complications with any cessation.
The Møller trial. The largest orthopaedic contributor reported the strongest single result: a 6-8 week intervention of cessation plus NRT cut overall complications to 18% from 52% in controls, and wound complications to 5% from 31%.
Fusion depends on postoperative abstinence. Note the direction of Glassman's key finding. Nonunion was not significantly affected by the quantity smoked preoperatively or by the duration of preoperative abatement, whereas patients who quit for more than 6 months after surgery fell to 17.1%, approaching the 14.2% non-smoker rate, and returned to work at 75% versus 53% in continuing smokers. Preoperative cessation is still worth pursuing for wound and pulmonary risk, but for fusion it is the postoperative abstinence that carries the evidence.
Quit rates with intervention, at 1 year:
- Brief advice alone: 3-5%
- Varenicline: 25-30%
- NRT: 15-20%
- Combination (behavioural + pharmacotherapy): 30-40%
Benefit accrues with time. Wound healing starts to benefit at 2-3 weeks, with improved tissue oxygenation.
- Physiological Benefits
- CO levels normalise, O2 delivery improves
- Physiological Benefits
- Circulation improves, nicotine eliminated
- Physiological Benefits
- Wound healing approaches non-smoker
- Physiological Benefits
- Bone healing capacity improved
- Physiological Benefits
- Risk approximates non-smoker for many outcomes
Beyond the index surgery. Quitting reduces the lifetime orthopaedic complication risk and cardiovascular risk (by 50% at 1 year), and improves pulmonary function. Cancer risk falls, slowly but significantly, and life expectancy rises: quitting at 40 gains about 9 years, at 60 about 3. Sustained cessation is best: permanent cessation eliminates long-term risks.
Surgery creates a "teachable moment" - patients are more motivated to quit when faced with concrete surgical risks. Surgeons who capitalise on this opportunity can achieve higher quit rates than typical primary care interventions. This benefit extends far beyond the immediate surgical outcome.
Pharmacotherapy for Smoking Cessation
First-Line Pharmacological Options
- Mechanism
- Partial nicotinic agonist
- Efficacy (vs Placebo)
- 3x quit rate (NNT=10)
- Adverse Effects
- Nausea, vivid dreams, rare mood changes
- Subsidy / Access
- Commonly subsidised (often restricted)
- Mechanism
- Nicotine replacement
- Efficacy (vs Placebo)
- 2x quit rate (NNT=20)
- Adverse Effects
- Local irritation, insomnia
- Subsidy / Access
- Commonly subsidised; also OTC
- Mechanism
- Antidepressant, dopamine/NE reuptake inhibitor
- Efficacy (vs Placebo)
- 2x quit rate (NNT=20)
- Adverse Effects
- Insomnia, dry mouth, seizure risk
- Subsidy / Access
- Commonly subsidised (often restricted)
- Mechanism
- Patch + short-acting NRT
- Efficacy (vs Placebo)
- Higher than single NRT
- Adverse Effects
- Similar to single NRT
- Subsidy / Access
- Commonly subsidised
Varenicline (Champix)
- Partial agonist at alpha-4 beta-2 nicotinic acetylcholine receptors
- Reduces craving and withdrawal (partial agonist effect)
- Blocks rewarding effects of nicotine (competitive antagonism)
- Most effective pharmacotherapy available
- Triples quit rates compared to placebo (30% vs 10% at 1 year) [22]
- Superior to bupropion and single-agent NRT [23]
- NNT = 10 (number needed to treat to achieve one additional quitter)
- Standard course: 12 weeks
- Start 1 week before quit date
- Days 1-3: 0.5mg once daily
- Days 4-7: 0.5mg twice daily
- Day 8 onwards: 1mg twice daily
- Can extend to 24 weeks for relapse prevention
- Nausea (30% - usually transient, dose with food)
- Vivid dreams or insomnia (20%)
- Headache (15%)
- Neuropsychiatric concerns: Rare mood changes, depression (FDA black box warning removed 2016 after safety review)
- Severe renal impairment (dose reduction required)
- Pregnancy (insufficient data - use only if benefit outweighs risk)
- History of serious psychiatric illness (use with caution, monitor closely)
This completes the varenicline section.
Behavioral Counseling and Support
The 5 A's Framework
Screen all patients for tobacco use at every clinical encounter.
- "Do you currently smoke or use tobacco?"
- "How many cigarettes per day? For how many years?"
- Calculate pack-years (packs per day multiplied by years)
- Document in medical record
Strongly urge all smokers to quit with clear, personalized message.
- "Quitting smoking is the single most important thing you can do to improve your surgical outcome."
- Relate to specific orthopaedic risks: "Smoking increases your risk of nonunion/infection by 4-6 times."
- Be direct but empathetic
Determine willingness to make a quit attempt.
- "Are you willing to quit smoking before your surgery?"
- Assess readiness to change (precontemplation, contemplation, preparation, action)
- If not ready: use motivational interviewing techniques
- If ready: proceed to assist
Help develop quit plan and provide resources.
- Set quit date (ideally 8+ weeks before surgery)
- Recommend pharmacotherapy (varenicline, NRT, bupropion)
- Provide behavioral support (telephone cessation counselling referral)
- Address triggers and develop coping strategies
- Enlist social support (family, friends)
Schedule follow-up to support cessation effort.
- First follow-up within 1 week of quit date
- Regular contact during first month (highest relapse risk)
- Monitor at preoperative visits
- Continue support postoperatively through healing period
- Celebrate successes, troubleshoot challenges
Brief Intervention (Under 5 minutes)
For time-limited clinical encounters, use Ask-Advise-Refer model:
- Ask: Screen for smoking status
- Advise: Clear personalized message to quit
- Refer: Refer to telephone cessation counselling service and/or prescribe pharmacotherapy
Effectiveness: Even brief interventions (under 3 min) increase quit rates by 30-40% when combined with pharmacotherapy. [25]
Motivational Interviewing Techniques
For patients not ready to quit:
- "What do you like about smoking?"
- "What concerns do you have about smoking?"
- Elicit change talk - patient's own reasons to quit
- Relevance: Personalize risks to patient's situation
- Risks: Short-term (surgical) and long-term (cancer, COPD, CVD)
- Rewards: Benefits of quitting (better healing, save money, health)
- Roadblocks: Identify barriers (withdrawal, weight gain, stress)
- Repetition: Repeat intervention at each visit (don't give up!)
Telephone Cessation Counselling
Telephone cessation counselling services - free in many countries:
- Evidence-based behavioral support
- Trained counselors
- Multiple callback sessions
- Free NRT starter packs in some jurisdictions
- Effective: Increases quit rates by 50-100% [26]
Referral process:
- Give patient the local service number
- Encourage active call
- Consider fax/electronic referral (patient consent) - service calls patient
Perioperative Smoking Cessation Protocol
Preoperative Optimization Protocol
- Screen all patients for smoking status
- Document pack-years in medical record
- Provide 5 A's counseling (Ask, Advise, Assess, Assist, Arrange)
- Explain orthopaedic-specific risks (nonunion, infection)
- Set quit date (target 8+ weeks before surgery)
- Prescribe pharmacotherapy (varenicline first-line)
- Refer to telephone cessation counselling service
- Provide written information
- Start varenicline 1 week before quit date (or NRT/bupropion on quit date)
- Patient quits smoking
- First follow-up within 1 week (phone or in-person)
- Address withdrawal symptoms
- Reinforce behavioral strategies
- Monitor pharmacotherapy adherence and side effects
- Highest relapse risk period - frequent contact essential
- Troubleshoot challenges (cravings, withdrawal, side effects)
- Adjust pharmacotherapy if needed (dose, combination therapy)
- Reinforce benefits already achieved
- Continue behavioral support
- Minimum 4 weeks, optimal 8 weeks achieved
- Patient physiologically optimized for surgery
- Complications reduced by around 41% (pooled RCT relative risk reduction)
- Continue pharmacotherapy through surgery
- DO NOT stop NRT perioperatively - safe and reduces relapse risk
- Verify abstinence (patient report, consider cotinine testing if high-stakes)
- Document cessation duration in preoperative note
- Confirm plan for postoperative continuation
- Consider incentive spirometry teaching (reduce pulmonary complications)
Intraoperative and Postoperative Management
- Continue NRT through surgery - apply patch morning of surgery
- Safe for wound healing (no combustion products)
- Reduces postoperative relapse risk
- For non-patch users: restart short-acting NRT as soon as tolerated postop
- Critical period: Bone healing takes 12+ weeks for fractures/fusions
- Continue pharmacotherapy for minimum 12 weeks (standard), longer for bone healing procedures
- Regular follow-up at postoperative visits
- Monitor for relapse (pain, stress, boredom in hospital)
- Address pain adequately (inadequate pain control increases relapse risk)
- Identify high-risk situations (alcohol, social settings, stress)
- Develop coping strategies for cravings
- Enlist social support
- Consider extended pharmacotherapy (24 weeks vs 12 weeks) for relapse prevention
- Long-term cessation reduces lifetime orthopaedic complication risk
Guidelines, Registries & Global Practice
Global Epidemiology
The Global Burden of Disease Study 2019 estimated 1.14 billion current smokers worldwide in 2019, consuming 7.41 trillion cigarette-equivalents. Smoking accounted for 7.69 million deaths and 200 million disability-adjusted life-years, and was the leading risk factor for death among males (20.2% of male deaths). Age-standardised prevalence has fallen significantly since 1990 (males 27.5% reduction, females 37.7% reduction), but population growth means the absolute number of smokers has risen from 0.99 billion in 1990. [27]
- Approximate Prevalence
- Falling but ~20% in many regions
- Source
- GBD 2019
- Approximate Prevalence
- ~10-13% current or daily smoking
- Source
- AIHW NDSHS 2022-23 / ONS / NHS data
- Approximate Prevalence
- 20-40% (higher than general)
- Source
- Scolaro 2014 and cohort series
- Approximate Prevalence
- ~35-40% (much higher)
- Source
- AIHW / national surveys
Side-by-Side Guideline Comparison
- Core Recommendation
- Brief intervention (Ask-Advise-Help) for all smokers; offer pharmacotherapy plus behavioural support
- First-line Pharmacotherapy
- Varenicline, NRT, or combination NRT
- Evidence Level
- Strong (Grade A)
- Core Recommendation
- Offer cessation support at every contact; varenicline/NRT/cytisine as options; treat tobacco dependence in all settings
- First-line Pharmacotherapy
- Varenicline or combination NRT (cytisine an option)
- Evidence Level
- Strong
- Core Recommendation
- 5 A's; counsel and treat all surgical smokers; document status
- First-line Pharmacotherapy
- Varenicline or combination NRT
- Evidence Level
- Strong (RCT-supported)
- Core Recommendation
- Population-level control plus brief advice and pharmacotherapy access
- First-line Pharmacotherapy
- NRT, varenicline, bupropion, cytisine
- Evidence Level
- Strong
- Core Recommendation
- Varenicline most effective single agent; safe in stable psychiatric disease; combination NRT effective
- First-line Pharmacotherapy
- Varenicline; combination NRT
- Evidence Level
- Level I
The core principles converge globally: screen every patient, deliver brief advice, offer pharmacotherapy (varenicline or combination NRT first-line) plus behavioural support, and continue cessation through the bone-healing period. Variation lies mainly in reimbursement and access - publicly funded, out-of-pocket, or insurance-based models - rather than in the underlying clinical recommendation. Cytisine is widely available and inexpensive in parts of Eastern Europe and increasingly elsewhere, but availability varies internationally and it is not marketed in all countries.
Registry and Outcome Data
No dedicated smoking-cessation registry exists for orthopaedics, but national joint replacement registries inform the smoking-outcome link:
- The Australian Orthopaedic Association National Joint Replacement Registry (AOANJRR) and the National Joint Registry (NJR, UK) capture revision and infection outcomes against which modifiable risk factors such as smoking are analysed.
- Large cohort and registry-linked studies (e.g. Singh 2011, 33,336 arthroplasties) consistently show higher adjusted surgical site infection and mortality in current smokers, supporting preoperative cessation pathways.
Special Clinical Scenarios
Acute Trauma and Urgent Surgery
Challenge: Limited time for preoperative cessation in acute fractures or urgent procedures.
- Still counsel to quit even if surgery imminent
- Emphasize postoperative cessation for bone healing (12+ weeks)
- Initiate pharmacotherapy immediately (NRT can start same day)
- Even brief cessation provides benefit - every day counts
- For urgent surgery (within 24-48 hours): focus on postoperative plan
- Quitting at time of injury still reduces complications vs continued smoking
- 12-week postoperative cessation critical for fracture union
- Provide intensive support during hospitalization (captive audience)
- Open fractures: Infection risk paramount - aggressive cessation counseling
- Tibial fractures: nonunion adjusted OR 2.16 - emphasize critical importance
- Femoral neck: AVN and nonunion risk - strongly advise cessation
This covers urgent/trauma scenarios.
Verification of Smoking Status
Objective Verification Methods
- Marker
- Nicotine metabolite
- Sensitivity
- Very high
- Specificity
- Very high
- Half-Life
- 16-20 hours
- Clinical Use
- Gold standard for verification
- Marker
- Carbon monoxide
- Sensitivity
- High
- Specificity
- Moderate
- Half-Life
- 4-6 hours
- Clinical Use
- Point-of-care, immediate result
- Marker
- Nicotine metabolite
- Sensitivity
- Very high
- Specificity
- Very high
- Half-Life
- 16-20 hours
- Clinical Use
- Non-invasive alternative
- Marker
- Tobacco alkaloid
- Sensitivity
- High
- Specificity
- Very high
- Half-Life
- Variable
- Clinical Use
- Distinguishes tobacco from NRT
- Research studies (standard requirement)
- High-stakes situations (e.g., prerequisite for elective surgery in some protocols)
- Suspected non-disclosure
- Generally NOT required for routine clinical care - patient self-report adequate
- Cutoff typically under 10 ng/mL = non-smoker
- Detects smoking in past 3-4 days
- False positives: Heavy secondhand smoke exposure
- Important: NRT use will cause positive cotinine (use anabasine to differentiate)
- Handheld device (e.g., Bedfont Smokerlyzer)
- Cutoff typically under 6-8 ppm = non-smoker
- Immediate result at point-of-care
- Short half-life (4-6 hours) - only detects very recent smoking
- False positives: Air pollution, COPD
Self-Report vs Verification
Evidence: Self-report of abstinence is reasonably accurate in most clinical settings. Biochemical verification adds little in routine practice but may be considered for:
- Research protocols
- Programs where cessation is prerequisite for intervention
- Suspected deception
Approach: Trust but verify when stakes are high (e.g., delaying elective surgery contingent on cessation).
MCQ Practice Points
Q: What is the minimum recommended duration of preoperative smoking cessation to reduce wound healing complications?
A: Minimum 4 weeks (ideally 6-8 weeks). Wound complications (infection, dehiscence) are reduced by 50% after 4 weeks cessation. Carbon monoxide levels normalize within 24-48 hours, improving tissue oxygenation. Nicotine's vasoconstrictive effects persist for 2-4 weeks after cessation. Longer cessation periods show incremental benefit, but even brief cessation (24-48 hours) improves oxygenation.
Q: By what factor does smoking increase the risk of nonunion following fracture fixation?
A: Smoking doubles (2x) the risk of nonunion. Studies show nonunion rates of 6-12% in smokers vs 3-6% in non-smokers. The mechanism involves impaired osteoblast function, reduced bone blood flow, and altered growth factor expression. The effect is dose-dependent. Smoking also increases infection risk (2x), DVT/PE (3-4x), and delays wound healing.
Q: What is the most effective pharmacological intervention for smoking cessation in the perioperative period?
A: Varenicline (Champix) is most effective (quit rate approximately 25-30% at 12 months) but requires 1-2 week lead time. It is a partial nicotinic receptor agonist that reduces cravings and withdrawal symptoms. Nicotine replacement therapy (NRT) is second-line but can be started immediately. Bupropion is an option for patients with depression. Combination NRT (patch + rapid-acting) equals varenicline efficacy.
Q: What is the impact of smoking on total hip arthroplasty outcomes?
A: Smokers have 2-3x higher risk of revision at 10 years. Specific complications: higher infection rate (superficial and deep), increased aseptic loosening, more frequent dislocation (due to poor soft tissue healing), and greater wound complications. Current smokers have worse patient-reported outcomes (PROMs). Smoking cessation before THA improves outcomes even with short cessation periods.
Q: What counseling approach is recommended for smoking cessation intervention by orthopaedic surgeons?
A: Brief intervention using the 5A's model: Ask (smoking status), Advise (clear advice to quit), Assess (readiness to quit), Assist (pharmacotherapy referral, telephone cessation support), Arrange (follow-up). Brief advice (3-5 minutes) doubles quit rates. Documenting preoperative smoking status is mandatory. Linking cessation to surgical outcomes enhances motivation ("teachable moment").
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are seeing a 52-year-old male smoker (40 pack-years, currently 1 pack per day) with degenerative spondylolisthesis L4/5 in your clinic. You have recommended L4/5 posterolateral fusion. How do you counsel him about smoking?”
“A 35-year-old male smoker presents to the emergency department with a closed mid-shaft tibial fracture after a motorcycle accident. He smokes 15 cigarettes per day. You are planning surgical fixation with intramedullary nailing. How does his smoking status affect your management and counseling?”
“A 60-year-old female patient is scheduled for total knee arthroplasty in 3 months. She smokes 10 cigarettes per day and is motivated to quit. She has a history of depression treated with an SSRI and had a seizure 20 years ago related to alcohol withdrawal, but no seizures since. What pharmacotherapy do you recommend for smoking cessation?”
“You have counseled a 45-year-old male smoker about the need to quit before his elective rotator cuff repair. He states he does not want to quit and becomes frustrated that you keep bringing it up. How do you proceed?”
Key Statistics to Memorize
- Fracture nonunion: OR 2.32 in smokers (tibia OR 2.16) - Scolaro meta-analysis
- Lumbar fusion nonunion: 26.5% persistent smokers vs 14.2% nonsmokers (Glassman)
- Arthroplasty SSI: adjusted OR 1.41 in current smokers (Singh, n=33,336)
- Cessation: 41% relative risk reduction in postop complications (Mills RCT pooled)
- Minimum cessation: 4 weeks, optimal 8+ weeks preoperatively
- Postoperative cessation: 12+ weeks for bone healing procedures
- Varenicline: most effective single agent (RR 2.24 vs placebo, NNT ~11); NRT/bupropion double quit rate
- Smoking prevalence: 1.14 billion globally (GBD 2019); ~10-13% in high-income adult surveys; 20-40% ortho trauma
Mechanisms of Smoking Harm
- Osteoblast dysfunction: reduced proliferation, decreased alkaline phosphatase
- Vasoconstriction: nicotine causes alpha-adrenergic stimulation and tissue hypoxia
- Carbon monoxide: reduced oxygen delivery (competes with O2 for hemoglobin)
- Impaired angiogenesis: reduced VEGF expression
- Fibroblast impairment: reduced collagen synthesis
- Immune dysfunction: reduced neutrophil function, complement activation
- Dose-response: worse outcomes with higher pack-years
5 A's Framework
- ASK: Screen all patients for tobacco use at every visit
- ADVISE: Strongly urge to quit with personalized message
- ASSESS: Determine willingness to make quit attempt
- ASSIST: Help develop quit plan, provide pharmacotherapy, telephone cessation support referral
- ARRANGE: Schedule follow-up within 1 week of quit date
Pharmacotherapy Quick Reference
- First-line: Varenicline (most effective, 3x quit rate, NNT=10)
- Varenicline dosing: Start 1 week before quit date, 0.5mg to 1mg BID
- Varenicline contraindications: Severe renal impairment, pregnancy
- NRT: Safe perioperatively, continue through surgery, double quit rate
- Combination NRT (patch + gum/lozenge) more effective than single
- Bupropion: Contraindicated in seizure disorder, eating disorder
- Widely subsidised in most national formularies (varenicline/bupropion often restricted; NRT general)
Procedure-Specific Approach
- Spinal fusion: 8 weeks preop + 12+ weeks postop, highest pseudarthrosis risk
- Fracture fixation: 4-8 weeks preop + 12+ weeks postop (bone healing period)
- TJA: 4-8 weeks preop + 6-12 weeks postop; SSI adjusted OR 1.41, pneumonia OR 1.53
- Acute trauma: Counsel to quit immediately, focus on 12-week postop period
- Rotator cuff repair: Increased re-tear and infection risk
Documentation Essentials
- Current smoking status and pack-years in every note
- 5 A's counseling provided (Ask, Advise, Assess, Assist, Arrange)
- Procedure-specific risks discussed with patient
- Pharmacotherapy prescribed (drug, dose, duration)
- Telephone cessation support referral offered
- Patient response: willing to quit / attempted / refused
- If refused: informed consent about increased complication risk
High-Yield Exam Answers
- Q: Most effective pharmacotherapy? A: Varenicline (3x quit rate)
- Q: Minimum preop cessation? A: 4 weeks (optimal 8 weeks)
- Q: Is NRT safe perioperatively? A: Yes - no combustion products, reduces relapse
- Q: Patient refuses to quit - proceed? A: Yes if medically necessary, document counseling and informed consent
- Q: Mechanism of smoking harm? A: Tissue hypoxia (vasoconstriction + CO), osteoblast dysfunction, impaired angiogenesis, immune dysfunction
- Q: Evidence for cessation? A: 50% complication reduction with 6-8 week preop cessation + NRT
Evidence Base for Cessation
Evidence by Procedure Type
Spinal Fusion Outcomes
- Glassman et al. (2000): instrumented lumbar fusion nonunion 26.5% in persistent smokers vs 14.2% in nonsmokers, falling to 17.1% in those who quit greater than 6 months postoperatively [12]
- Andersen et al. (2001): smoking an independent predictor of negative outcome (impaired fusion) in lumbar spinal fusion [13]
- Møller et al. (2002): Intensive smoking cessation intervention reduced overall complications from 52% to 18% (RCT in hip/knee arthroplasty) [14]
- Pseudarthrosis rates 2-4x higher in smokers
- Effect most pronounced in posterolateral fusion (uninstrumented)
- Interbody fusion somewhat more resistant but still affected
- Dose-dependent effect - heavier smokers worse outcomes
- 4-8 weeks preoperative cessation reduces pseudarthrosis risk
- 12+ weeks postoperative continuation essential for fusion consolidation
- Even brief cessation provides measurable benefit
This completes the spinal fusion evidence.
Timing of Cessation: Critical Evidence
Some benefit but suboptimal. Still strongly recommend - better than continued smoking.
Improved tissue oxygenation beginning. Insufficient for maximal complication reduction.
50% reduction in pulmonary complications. Measurable improvement in wound healing. Minimum acceptable for elective procedures. [21]
60% reduction in all complications. Approaching non-smoker baseline for some outcomes. Target for elective surgery. [14]
Essential for fracture union and spinal fusion. Continue cessation through healing period.
Minimum 4 weeks, optimal 8 weeks preoperative cessation is the evidence-based standard. Shorter durations provide some benefit but do not maximize complication reduction. For elective procedures, consider delaying surgery to achieve 8-week cessation if patient is motivated.
The Minimum-Timing Controversy: Is Short-Term Cessation Harmful?
- The old concern (Warner): early observational work raised the theoretical worry that stopping in the few weeks immediately before surgery might transiently increase sputum and cough (as mucociliary clearance recovers) and so fail to reduce - or even briefly raise - pulmonary complications. This produced the once-quoted, now largely abandoned idea of an "8-week rule" below which quitting was supposedly not worthwhile.
- The modern position: larger and pooled data have not confirmed any real increase in complications from short-term cessation. The meta-analysis in this topic's evidence base (Mills) shows a clear dose-response - each additional week of preoperative cessation increases the benefit by roughly 19%, with trials of at least 4 weeks showing a significantly larger effect - but no signal of net harm from quitting closer to surgery.
- The practical rule: quitting at any time before surgery is net beneficial and should always be encouraged; longer is better (target 4-8 weeks for elective surgery), but a short lead time or an urgent/trauma presentation is never a reason to advise against quitting. Manage airway-secretion concerns with chest physiotherapy and incentive spirometry rather than by delaying cessation.
The historical worry (Warner) that cessation in the 1-4 weeks before surgery might transiently increase pulmonary secretions and complications has not been borne out by pooled evidence. The dose-response is real (Mills: benefit rises about 19% per additional week, larger at 4+ weeks) but there is no net harm from quitting close to surgery - so advise every smoker to quit now, whatever the time to theatre, while still targeting 4-8 weeks where elective timing allows.
Key Evidence for Smoking Cessation
Glassman et al. - Smoking Cessation and Spinal Fusion
- Retrospective review of 357 patients undergoing instrumented posterior lumbar fusion (L4-L5 or L4-S1)
- Nonunion 14.2% in nonsmokers vs 26.5% in patients who continued to smoke after surgery (p less than 0.05)
- Patients who quit for greater than 6 months postoperatively had a nonunion rate of 17.1%
- Return-to-work: 71% nonsmokers, 53% persistent smokers, 75% quitters; preoperative smoking quantity did not predict nonunion
Møller et al. - Preoperative Smoking Intervention (RCT)
- Multicentre RCT across three Danish hospitals: 120 patients undergoing elective hip or knee replacement randomised 6-8 weeks before surgery, 12 later excluded for postponed or cancelled operations, leaving 56 intervention and 52 control analysed
- Overall complication rate 18% (intervention) vs 52% (control), p=0.0003
- Wound complications 5% vs 31% (p=0.001) - the one component difference that reached significance
- Cardiovascular complications 0% vs 10% and secondary surgery 4% vs 15% both favoured intervention but did NOT reach significance (p=0.08 and p=0.07); median stay 11 versus 13 days
- Intervention was counselling plus nicotine replacement, aiming for cessation or at least 50% reduction
Scolaro et al. - Smoking and Fracture Healing (Systematic Review)
- Systematic review and meta-analysis of 19 cohort studies (7 prospective, 12 retrospective) on long-bone fractures
- Adjusted odds ratio of nonunion 2.32 (95% CI 1.76-3.06) in smokers overall
- Tibial fracture nonunion OR 2.16 (95% CI 1.55-3.01); open fracture nonunion OR 1.95
- Mean healing time longer in smokers (30.2 vs 24.1 weeks; not statistically significant)
Cahill et al. - Nicotine Receptor Partial Agonists (Cochrane)
- Cochrane review of 39 varenicline trials (25,290 participants)
- Varenicline (standard dose) vs placebo: pooled RR 2.24 (95% CI 2.06-2.43; high-quality evidence)
- Varenicline vs bupropion RR 1.39; varenicline vs NRT RR 1.25; number needed to treat ~11
- Nausea most common adverse effect; early neuropsychiatric concerns not confirmed (see EAGLES)
- The safety finding usually left off this card: Cochrane reports a possible 25% increase in SERIOUS adverse events on varenicline (RR 1.25, 95% CI 1.04-1.49; 29 trials, 15,370 people; high-quality evidence). These were largely infections, cancers and injuries that trialists judged unrelated to treatment, and higher control-group losses to follow-up probably under-count control events - but the signal belongs in the consent conversation rather than being omitted
Singh et al. - Smoking and Arthroplasty Outcomes (Veterans)
- National Veterans Affairs cohort of 33,336 patients undergoing elective primary THA/TKA (2001-2008), multivariable-adjusted 30-day outcomes
- Current smokers vs never smokers: surgical site infection OR 1.41 (95% CI 1.16-1.72)
- Pneumonia OR 1.53, stroke OR 2.61, and 1-year mortality OR 1.63 in current smokers
- Prior smokers also had increased pneumonia, stroke, and urinary tract infection
Anthenelli et al. (EAGLES) - Neuropsychiatric Safety of Cessation Drugs
- Double-blind RCT of 8,144 smokers (half with stable psychiatric disorders) across 16 countries
- No significant excess of moderate-to-severe neuropsychiatric adverse events with varenicline or bupropion vs patch or placebo
- Varenicline most effective for confirmed abstinence (OR 3.61 vs placebo; 1.68 vs patch; 1.75 vs bupropion)
- Bupropion and nicotine patch both superior to placebo
Mills et al. - Cessation Reduces Postoperative Complications (Meta-analysis)
- Systematic review of 6 RCTs and 15 observational studies of preoperative smoking cessation
- Pooled RCT data: 41% relative risk reduction in postoperative complications (95% CI 15-59%)
- Each additional week of cessation increased the treatment effect by ~19%
- Trials of at least 4 weeks cessation showed significantly larger benefit; observational RR for total complications 0.76
References
-
Nolan J, Jenkins DH, Kurz LT, Horwitz DS. The acute management of the open fracture. J Orthop Trauma. 2009;23(suppl 1):S76-S91.
-
Fang MA, Frost PJ, Iida-Klein A, Hahn TJ. Effects of nicotine on cellular function in UMR 106-01 osteoblast-like cells. Bone. 1991;12(4):283-286.
-
Chen Y, Guo Q, Pan X, Qin L, Zhang P. Smoking and impaired bone healing: will activation of cholinergic anti-inflammatory pathway be the bridge? Int Orthop. 2011;35(10):1555-1561.
-
Silverstein P. Smoking and wound healing. Am J Med. 1992;93(1A):22S-24S.
-
Hernigou J, Schuind F. Tobacco and bone fractures: A review of the facts and issues that every orthopaedic surgeon should know. Bone Joint Res. 2013;2(11):255-265.
-
Jensen JA, Goodson WH, Hopf HW, Hunt TK. Cigarette smoking decreases tissue oxygen. Arch Surg. 1991;126(9):1131-1134.
-
Holt PG. Immune and inflammatory function in cigarette smokers. Thorax. 1987;42(4):241-249.
-
Mosely LH, Finseth F. Cigarette smoking: impairment of digital blood flow and wound healing in the hand. Hand. 1977;9(2):97-101.
-
Singh JA, Houston TK, Ponce BA, et al. Smoking as a risk factor for short-term outcomes following primary total hip and total knee replacement in veterans. Arthritis Care Res (Hoboken). 2011;63(10):1365-1374.
-
Namba RS, Inacio MC, Paxton EW. Risk factors associated with deep surgical site infections after primary total knee arthroplasty: an analysis of 56,216 knees. J Bone Joint Surg Am. 2013;95(9):775-782.
-
Lee SM, Landry J, Jones PM, Buhrmann O, Morley-Forster P. Long-term quit rates after a perioperative smoking cessation randomized controlled trial. Anesth Analg. 2015;120(3):582-587.
-
Glassman SD, Anagnost SC, Parker A, Burke D, Johnson JR, Dimar JR. The effect of cigarette smoking and smoking cessation on spinal fusion. Spine (Phila Pa 1976). 2000;25(20):2608-2615.
-
Andersen T, Christensen FB, Laursen M, Høy K, Hansen ES, Bünger C. Smoking as a predictor of negative outcome in lumbar spinal fusion. Spine (Phila Pa 1976). 2001;26(23):2623-2628.
-
Møller AM, Villebro N, Pedersen T, Tønnesen H. Effect of preoperative smoking intervention on postoperative complications: a randomised clinical trial. Lancet. 2002;359(9301):114-117.
-
Hernigou J, Schuind F. Smoking as a predictor of negative outcome in diaphyseal fracture healing. Int Orthop. 2013;37(5):883-887.
-
Scolaro JA, Schenker ML, Yannascoli S, Baldwin K, Mehta S, Ahn J. Cigarette smoking increases complications following fracture: a systematic review. J Bone Joint Surg Am. 2014;96(8):674-681.
-
Calori GM, Albisetti W, Agus A, Iori S, Tagliabue L. Risk factors contributing to fracture non-unions. Injury. 2007;38 Suppl 2:S11-S18.
-
Singh JA, Houston TK, Ponce BA, Maddox G, Bishop MJ, Richman J, et al. Smoking as a risk factor for short-term outcomes following primary total hip and total knee replacement in veterans. Arthritis Care Res (Hoboken). 2011;63(10):1365-1374.
-
Singh JA. Smoking and outcomes after knee and hip arthroplasty: a systematic review. J Rheumatol. 2011;38(9):1824-1834.
-
Mallon WJ, Misamore G, Snead DS, Denton P. The impact of preoperative smoking habits on the results of rotator cuff repair. J Shoulder Elbow Surg. 2004;13(2):129-132.
-
Warner DO. Perioperative abstinence from cigarettes: physiologic and clinical consequences. Anesthesiology. 2006;104(2):356-367.
-
Cahill K, Lindson-Hawley N, Thomas KH, Fanshawe TR, Lancaster T. Nicotine receptor partial agonists for smoking cessation. Cochrane Database Syst Rev. 2016;(5):CD006103.
-
Anthenelli RM, Benowitz NL, West R, et al. Neuropsychiatric safety and efficacy of varenicline, bupropion, and nicotine patch in smokers with and without psychiatric disorders (EAGLES): a double-blind, randomised, placebo-controlled clinical trial. Lancet. 2016;387(10037):2507-2520.
-
Ramon JM, Nerin I, Comino A, Pinet C, Abella F, Carreras JM, et al. A multicentre randomized trial of combined individual and telephone counselling for smoking cessation. Prev Med. 2013;57(3):183-188.
-
Stead LF, Buitrago D, Preciado N, Sanchez G, Hartmann-Boyce J, Lancaster T. Physician advice for smoking cessation. Cochrane Database Syst Rev. 2013;(5):CD000165.
-
Stead LF, Hartmann-Boyce J, Perera R, Lancaster T. Telephone counselling for smoking cessation. Cochrane Database Syst Rev. 2013;(8):CD002850.
-
GBD 2019 Tobacco Collaborators. Spatial, temporal, and demographic patterns in prevalence of smoking tobacco use and attributable disease burden in 204 countries and territories, 1990-2019: a systematic analysis from the Global Burden of Disease Study 2019. Lancet. 2021;397(10292):2337-2360.
Additional Guideline and Survey Sources
- Royal Australian College of General Practitioners (RACGP). Supporting smoking cessation: A guide for health professionals. Updated 2014.
- Australian Therapeutic Guidelines (eTG). Smoking Cessation. Accessed December 2025.
- Australian Institute of Health and Welfare (AIHW). National Drug Strategy Household Survey 2022.
Suggested Further Reading
- Møller AM, Pedersen T, Villebro N, Nørgaard P. Impact of lifestyle on perioperative smoking cessation and postoperative complication rate. Prev Med. 2003;36(6):704-709.
- Theadom A, Cropley M. Effects of preoperative smoking cessation on the incidence and risk of intraoperative and postoperative complications in adult smokers: a systematic review. Tob Control. 2006;15(5):352-358.
- Mills E, Eyawo O, Lockhart I, Kelly S, Wu P, Ebbert JO. Smoking cessation reduces postoperative complications: a systematic review and meta-analysis. Am J Med. 2011;124(2):144-154.
This comprehensive topic on smoking cessation for orthopaedic surgery is now complete.