ASIA Classification | MAP 85-90 | Steroids Not Routine | Early Surgery
- ASIA classification is THE standard for neurological assessment in SCI
- MAP 85-90mmHg for 5-7 days improves outcomes in incomplete SCI
- Methylprednisolone is not standard of care - but 'never' is too strong. AANS/CNS recommend against routine steroids; the 2017 AOSpine guideline suggests a 24-hour infusion may be OFFERED as an option within 8 hours of injury, and recommends against starting after 8 hours and against any 48-hour regimen
- Early surgery (within 24h) for incomplete SCI improves outcomes
- Complete SCI (ASIA A) has poor prognosis regardless of treatment
- “Neurogenic shock = bradycardia + hypotension (loss of sympathetic tone)
- “Spinal shock = transient areflexia, NOT hypotension
- “Sacral sparing = incomplete injury (better prognosis)
- “Bulbocavernosus reflex return signals end of spinal shock
Overview and Epidemiology
Spinal cord injury (SCI) is damage to the spinal cord that causes temporary or permanent change in motor, sensory or autonomic function below the level of injury. The distinction between a complete injury (ASIA A) and an incomplete one (ASIA B-D) is crucial for prognosis.
Mechanism. The causes, in order of frequency:
- Motor vehicle accidents - 39%
- Falls - 31%, and increasing in the elderly
- Violence - 14%, predominantly gunshot wounds
- Sports - 8%, with diving injuries common
- Medical and surgical complications - 5%
Level. By region:
- Cervical - 55%, with the worst outcomes
- Thoracic - 30%, from high-velocity injuries
- Lumbar - 15%, often with burst fractures
Age. The distribution has two peaks: young adults aged 15-29 injured in trauma, and people over 65 who fall onto a cervical spine with pre-existing stenosis. The elderly are a growing proportion of SCI patients.
Global burden. Traumatic SCI occurs in roughly 8 to 50 per million people per year, with the highest rates in regions carrying a heavy burden of road-traffic injury and falls.
Anatomy and Pathophysiology
The cord. The spinal cord ends at L1-L2 as the conus medullaris. It has two enlargements for the limbs: cervical (C4-T1) for the upper limb and lumbar (L1-S2) for the lower. In cross-section the grey matter is central, motor anteriorly and sensory posteriorly, and the white matter tracts lie peripherally around it.
- Function
- Motor - voluntary movement
- Location
- Lateral column
- Clinical Syndrome
- Weakness below level
- Function
- Pain and temperature
- Location
- Anterior-lateral
- Clinical Syndrome
- Contralateral loss
- Function
- Proprioception, vibration
- Location
- Posterior column
- Clinical Syndrome
- Ipsilateral loss
- Function
- Sympathetic/parasympathetic
- Location
- Intermediolateral
- Clinical Syndrome
- Neurogenic shock
Primary injury. The mechanical disruption at the moment of trauma, by compression, contusion or transection. It is not reversible.
Secondary injury. The damage that follows over hours to days, and the part that can be prevented:
- Ischaemia from hypotension
- Oedema and inflammation
- Excitotoxicity from glutamate release
- Apoptosis (programmed cell death)
The goal of acute SCI management is to prevent secondary injury. That means holding the MAP target, early decompression if the cord is compressed, avoiding hypoxia and maintaining normothermia. The primary injury is done; the effort goes into preventing further damage.
Classification
The ASIA Impairment Scale is the standard classification for SCI worldwide. It grades completeness; the ISNCSCI examination, in the last tab, defines the level.
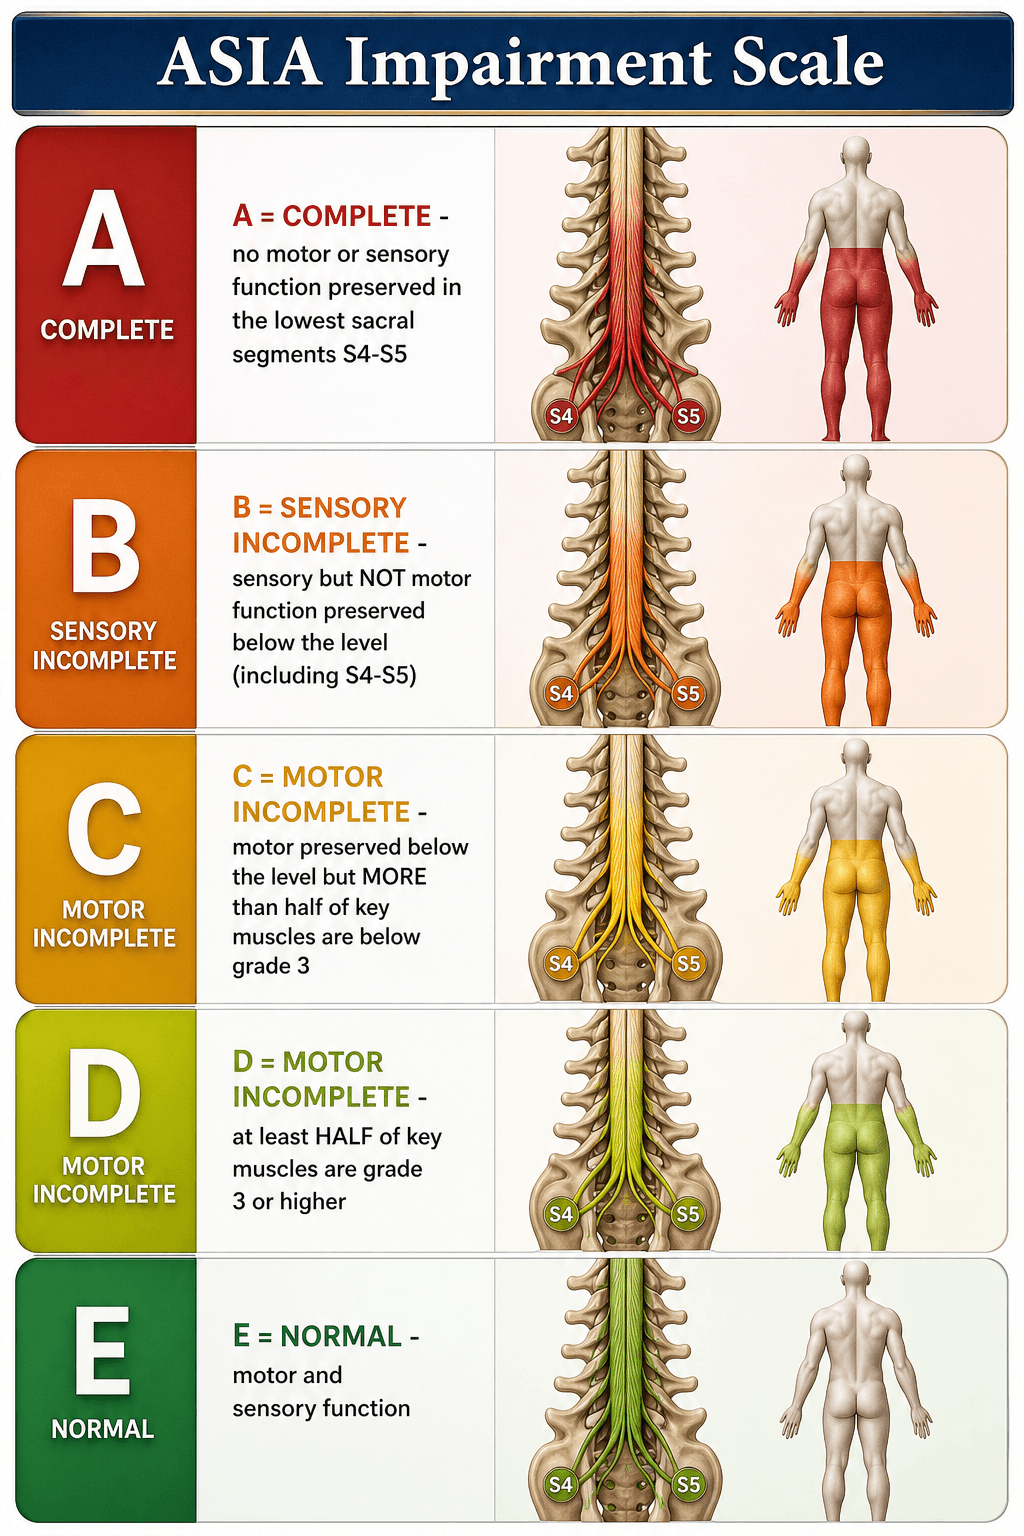
Grades B to D are the incomplete injuries, defined by sacral sparing.
- A - Complete. No motor or sensory function in the sacral segments S4-S5: no voluntary anal contraction and no perianal sensation.
- B - Sensory incomplete. Sensory function preserved below the level, including S4-S5, with no motor function below the level.
- C - Motor incomplete. Motor function preserved below the level, but more than half of the key muscles below it have grade less than 3.
- D - Motor incomplete. Motor function preserved below the level, with half or more of the key muscles grade 3 or greater.
- E - Normal. Full motor and sensory function, although the reflexes may be abnormal.
Clinical Assessment
Primary survey. Assessment starts with the primary survey, the cervical spine controlled throughout:
- Airway - intubation may be needed
- Breathing - diaphragm function (C3-5) and respiratory assessment
- Circulation - is there neurogenic shock, with bradycardia and hypotension?
- Disability - GCS, pupils and gross neurology
- Exposure - complete spinal examination with a log roll
The ASIA examination. Test the 10 key muscles on both sides on the 0-5 scale, and light touch and pinprick in 28 dermatomes. Test the bulbocavernosus reflex for spinal shock, examine the sacral segments, and document the neurological level and ASIA grade clearly.
Always check for sacral sparing - perianal sensation and voluntary anal contraction. Any sacral function preserved means incomplete injury (ASIA B or better), which has significantly better prognosis than complete injury.
Neurogenic shock is cardiovascular. Loss of sympathetic vascular tone causes hypotension, with warm, dry peripheries from vasodilation, and the unopposed parasympathetic supply to the heart causes bradycardia. It occurs with lesions above T6.
Spinal shock is neurological, and it is not the same thing. Below the injury level there is transient areflexia and flaccid paralysis, not yet spasticity, even if the injury is complete; anal tone is lost and the bulbocavernosus reflex is initially absent. It typically resolves over 24-72 hours, and the return of the bulbocavernosus reflex signals its end.
Investigations
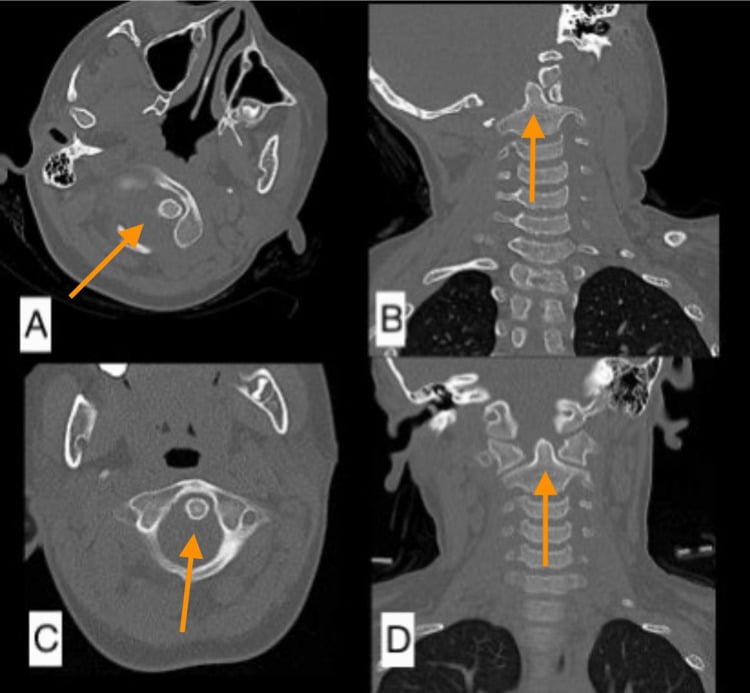
CT defines the bony injury.
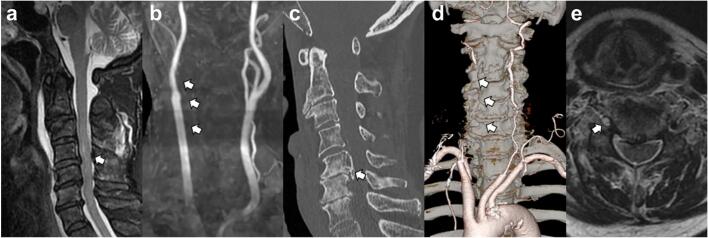
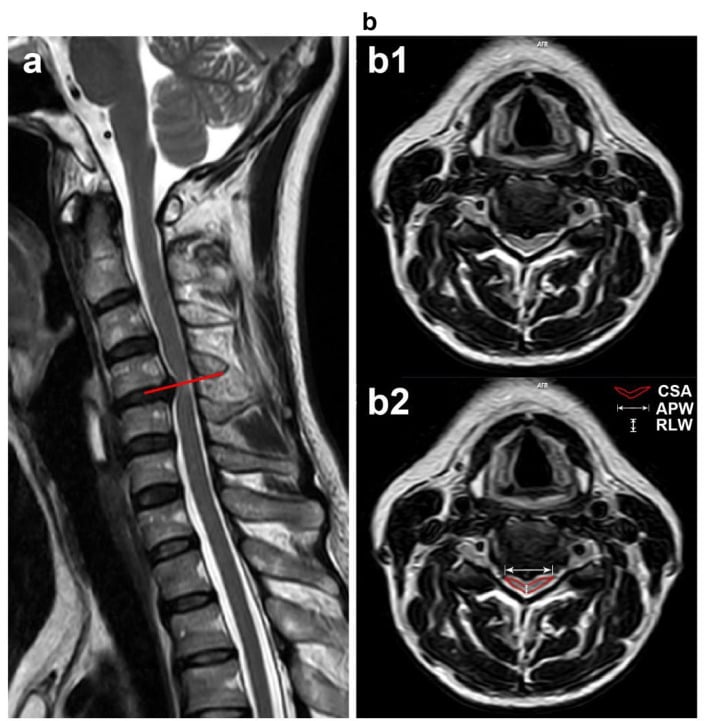
MRI timing. MRI should not delay resuscitation or surgery in an unstable patient. For an incomplete injury with unclear pathology, MRI within 24 hours helps guide surgical planning. What the cord looks like predicts how it will do:
- Description
- T1 hyperintense, T2 variable
- Prognostic Significance
- Poor prognosis - irreversible damage
- Description
- T2 hyperintense, normal T1
- Prognostic Significance
- Better prognosis - may recover
- Description
- Complete cord disruption
- Prognostic Significance
- Complete injury, no recovery
- Description
- Mechanical compression, normal cord
- Prognostic Significance
- Best prognosis if decompressed
Differential Diagnosis
The patient who cannot move their limbs after trauma is not always a structural cord injury. Distinguishing true SCI from its mimics changes management entirely, and confusing complete with incomplete patterns alters prognosis and surgical urgency.
- Key Distinguishing Features
- No motor or sensory below level, including S4-S5
- Sacral Function
- Absent
- Imaging / Test
- MRI: cord disruption, haemorrhage
- Key Distinguishing Features
- Any preserved function below level
- Sacral Function
- Preserved (sacral sparing)
- Imaging / Test
- MRI: oedema, compression, partial signal
- Key Distinguishing Features
- Transient global areflexia and flaccidity
- Sacral Function
- May be temporarily absent
- Imaging / Test
- Clinical: BCR returns as it resolves
- Key Distinguishing Features
- Neurological deficit with normal radiographs/CT
- Sacral Function
- Variable
- Imaging / Test
- MRI shows cord signal change
- Key Distinguishing Features
- LMN signs, saddle anaesthesia, retention; lesion below L1-L2 conus
- Sacral Function
- Often impaired
- Imaging / Test
- MRI: canal compression below conus
- Key Distinguishing Features
- Mixed UMN/LMN, early bladder/bowel, symmetrical
- Sacral Function
- Impaired early
- Imaging / Test
- MRI: T12-L2 cord/conus lesion
- Key Distinguishing Features
- No trauma; infection, tumour, infarct, transverse myelitis
- Sacral Function
- Variable
- Imaging / Test
- MRI with contrast; CSF; bloods
- Key Distinguishing Features
- Non-anatomical, inconsistent, normal reflexes/tone
- Sacral Function
- Preserved
- Imaging / Test
- Normal MRI; inconsistent examination
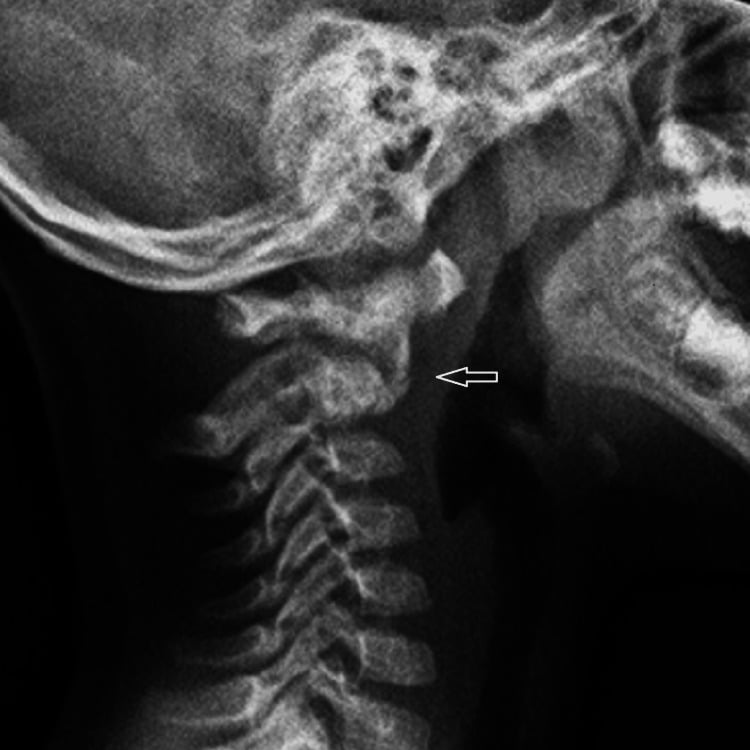
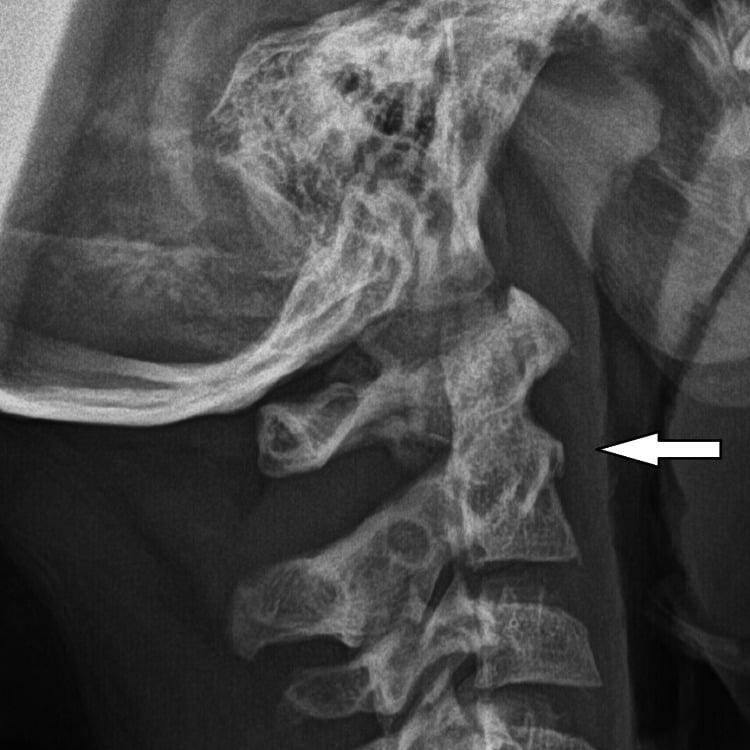
Spinal Cord Injury WithOut Radiographic Abnormality is classically a paediatric phenomenon (ligamentous laxity, large head, horizontal facets) but also occurs in adults with pre-existing cervical stenosis. Plain films and CT are normal; MRI is mandatory and may show cord oedema or haemorrhage. A normal CT does NOT exclude cord injury in a patient with neurological signs.
Management
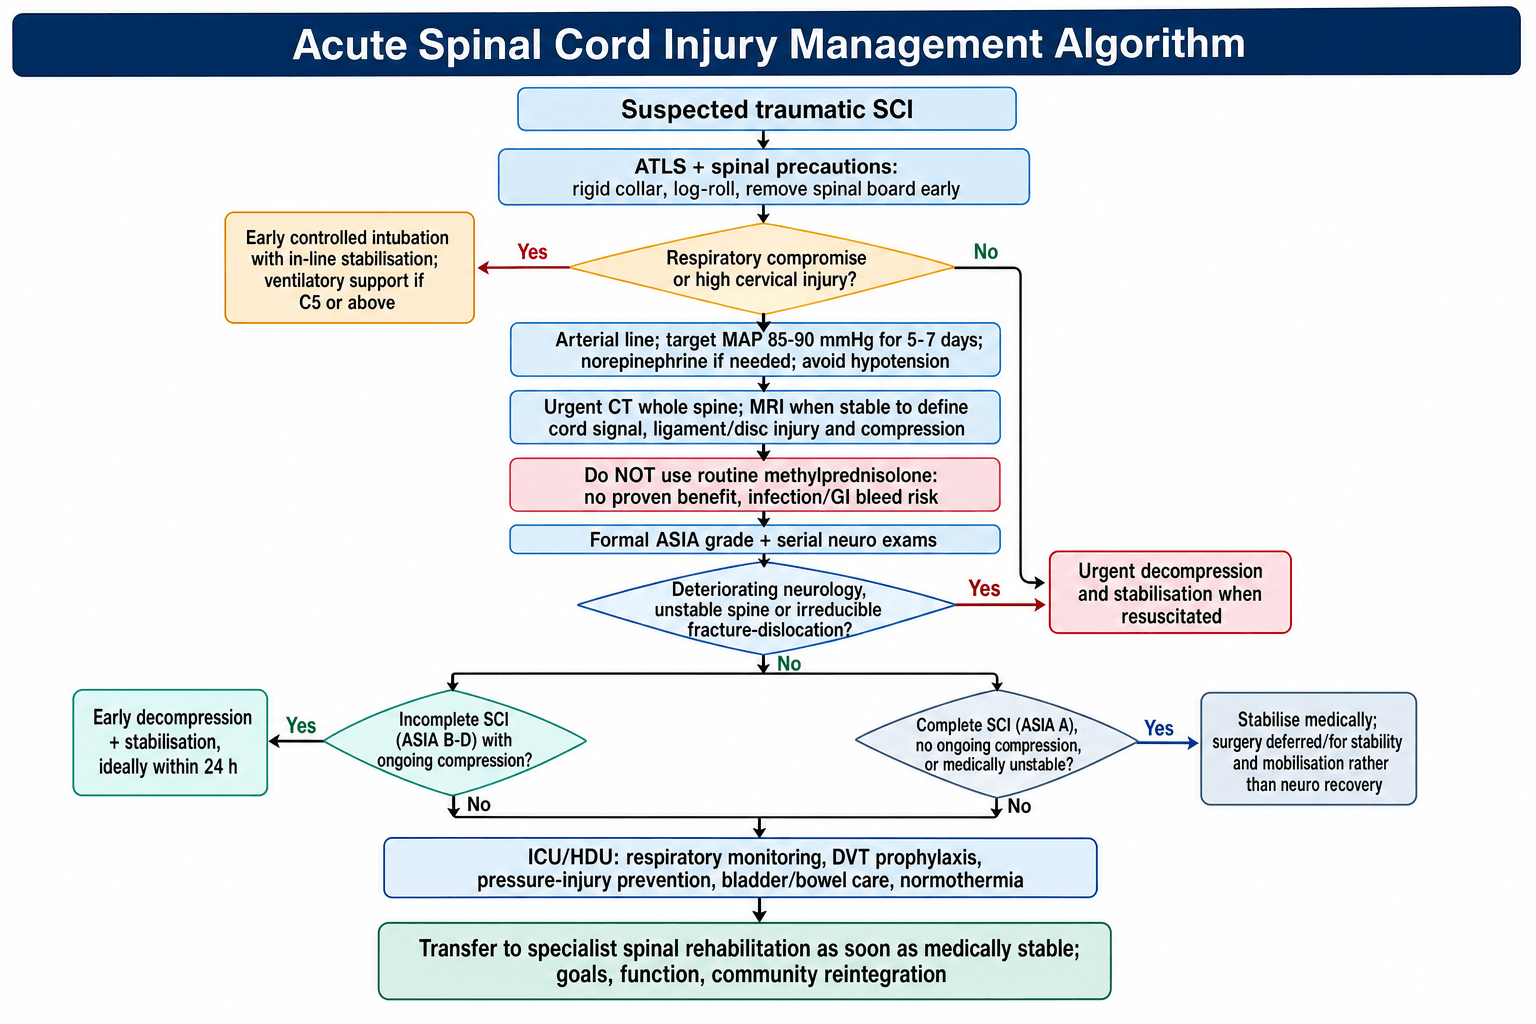
Immobilisation. A rigid cervical collar until the spine is cleared, and log-roll precautions. The spinal board is for transport only, because of the risk of pressure injury.
Airway and breathing. Intubate early if the GCS is impaired or breathing is compromised; injuries at C5 and above may need ventilatory support. Avoid neck extension during intubation, using a fibre-optic technique if available.
Circulation. Hypotension causes secondary injury and is to be avoided at all costs. In incomplete SCI the target is a MAP of 85-90mmHg for 5-7 days, to keep the cord adequately perfused. Monitor it continuously through an arterial line and use vasopressors if needed, norepinephrine first line.
Methylprednisolone. Steroids were once given on the strength of the NASCIS trials, but NASCIS II showed no overall benefit, and its within-8-hours result was a post-hoc subgroup rather than the primary analysis. The two major guidelines disagree, so know both:
- AANS/CNS, like most bodies, recommend against routine steroids, citing no proven benefit and real harm: infection and GI bleeding, and more severe sepsis and pneumonia in the 48-hour arm of NASCIS III
- The 2017 AOSpine guideline suggests a 24-hour high-dose infusion may be offered as an option within 8 hours of injury, and recommends against starting after 8 hours and against any 48-hour regimen
Steroids are not standard of care, but they are not universally prohibited either. Do not give them reflexively, never start them late and never run 48 hours; if they are given at all, it is a 24-hour course started within 8 hours, as an option after an explicit risk discussion rather than a protocol.
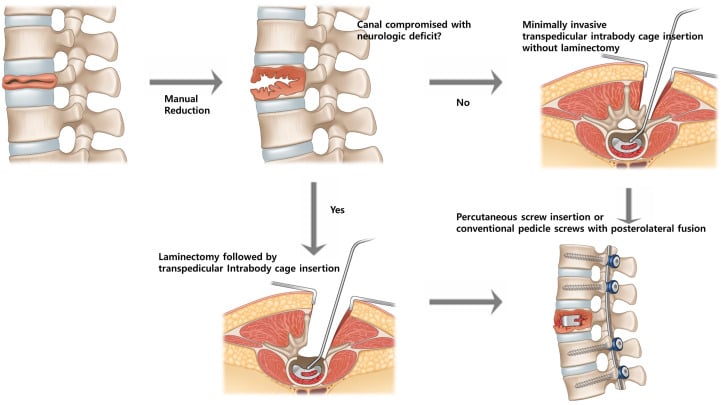
Surgical Technique
Indications. Anterior cervical decompression and fusion is used for:
- Anterior compression (disc herniation, vertebral body)
- Corpectomy required
- Kyphotic deformity
Technique. Position supine with the head neutral and approach through the Smith-Robinson interval, medial to sternocleidomastoid. Perform a discectomy or corpectomy as required and decompress the cord under the microscope. Place a structural graft or cage, apply an anterior plate and confirm alignment on fluoroscopy.
Trade-offs. The approach decompresses directly from the front and restores lordosis. Its risks are recurrent laryngeal nerve injury, oesophageal injury and dysphagia.
Complications
- Timeframe
- Acute
- Prevention/Management
- Early intubation if C5+, pulmonary toilet
- Timeframe
- Days to weeks
- Prevention/Management
- LMWH + mechanical, IVC filter if needed
- Timeframe
- Days to weeks
- Prevention/Management
- Turn q2h, specialty mattress, early mobilisation
- Timeframe
- Chronic (T6+)
- Prevention/Management
- Identify and remove noxious stimulus
- Timeframe
- Weeks to months
- Prevention/Management
- NSAIDs prophylaxis, radiation if high risk
- Timeframe
- Chronic
- Prevention/Management
- Physiotherapy, baclofen, botulinum toxin
Medical emergency in chronic SCI above T6. Caused by a noxious stimulus below the injury (full bladder, constipation). Presents with hypertension, bradycardia, headache and sweating. Sit the patient upright and identify and remove the trigger; antihypertensives may be needed if it is severe.
Neurogenic bladder. The pattern of bladder dysfunction depends on whether the lesion is above or at or below the sacral micturition centre (S2-S4), a high-yield distinction with direct consequences for management.
- Suprasacral (UMN) lesion
- Above the conus / S2-S4 centre
- Sacral / cauda equina (LMN) lesion
- Conus or cauda equina (S2-S4 or below)
- Suprasacral (UMN) lesion
- Overactive / spastic (reflex bladder, once spinal shock resolves)
- Sacral / cauda equina (LMN) lesion
- Acontractile / flaccid (areflexic)
- Suprasacral (UMN) lesion
- High-pressure reflex voiding, often with detrusor-sphincter dyssynergia (DSD) leading to reflux and upper-tract damage
- Sacral / cauda equina (LMN) lesion
- Retention with overflow incontinence; low-pressure but incomplete emptying
- Suprasacral (UMN) lesion
- Antimuscarinics / beta-3 agonist to relax detrusor + clean intermittent catheterisation; botulinum toxin if refractory
- Sacral / cauda equina (LMN) lesion
- Clean intermittent catheterisation (mainstay); Valsalva/Crede with caution
The dangerous combination is the UMN bladder with detrusor-sphincter dyssynergia - the detrusor contracts against a closed sphincter, generating high intravesical pressures that transmit to the kidneys (vesicoureteric reflux, hydronephrosis, renal failure, the historic leading late cause of death in SCI). Clean intermittent catheterisation plus pressure-lowering therapy protects the upper tracts; long-term indwelling catheters are avoided where possible (stones, infection, squamous-cell bladder cancer). Acutely (during spinal shock) the bladder is flaccid regardless of level, so an indwelling catheter is used first, transitioning to intermittent catheterisation when the patient is stable, as the reflex pattern emerges.
Postoperative Care
Rehabilitation. Transfer to a spinal rehabilitation unit as soon as the patient is medically stable. Multidisciplinary care from physiotherapy, occupational therapy, psychology and social work significantly improves functional outcomes.
Outcomes and Prognosis
Recovery by grade. Most neurological recovery occurs in the first 6-12 months, and how much depends on the ASIA grade:
- ASIA A - less than 5% regain functional ambulation. Recovery plateaus within 1 year, and the focus is on maximising function at the level of injury
- ASIA B - 50% regain some walking ability. The prognosis is better than for a complete injury, and early surgery may improve outcomes
- ASIA C - 75% improve at least one ASIA grade, and most will achieve some ambulation
- ASIA D - 95% maintain community ambulation, an excellent functional prognosis
Cord haemorrhage on MRI is the strongest predictor of poor outcome, regardless of the initial ASIA grade.
Guidelines, Registries & Global Practice
Global Epidemiology
- Reported incidence of traumatic SCI varies widely, roughly 8 to 50 per million population per year, reflecting differences in road safety, violence and ascertainment.
- Bimodal age distribution: young adults (high-energy trauma) and an expanding elderly group (low-energy falls on a stenotic, often degenerate cervical spine).
- Worldwide the cervical spine is the commonest level injured, and males predominate, though the elderly fall cohort narrows this gap.
- High-income settings have seen falling SCI prevalence (Global Burden of Disease 2017 reported a decline in US SCI prevalence), while road-traffic SCI remains a major and rising burden in many low- and middle-income countries.
Major Guidelines Side by Side
- AOSpine / AANS-CNS (2017)
- AOSpine: 24h within 8h is an option only, no 48h. AANS/CNS: not recommended
- Practical Global Position
- Not standard of care anywhere; if used, only a 24h course within 8h with informed consent
- AOSpine / AANS-CNS (2017)
- Early decompression (within 24h) suggested regardless of level
- Practical Global Position
- Decompress within 24h where resources allow; ultra-early (under 12h) increasingly favoured for cervical injury
- AOSpine / AANS-CNS (2017)
- Maintain MAP to support cord perfusion (commonly 85-90 mmHg, 5-7 days)
- Practical Global Position
- Avoid hypotension and hypoxia above all; individualise duration
- AOSpine / AANS-CNS (2017)
- Recommended to assess cord, ligaments and compression
- Practical Global Position
- Obtain MRI before or soon after surgery where available; never delay resuscitation
- AOSpine / AANS-CNS (2017)
- Pharmacological prophylaxis recommended once safe
- Practical Global Position
- Combined mechanical and LMWH; very high VTE risk in SCI
High-Resource vs Limited-Resource Practice
- Rapid pre-hospital retrieval to a dedicated spinal cord injury unit
- Around-the-clock MRI and emergency decompression capability
- ICU haemodynamic monitoring and arterial-line MAP targeting
- Multidisciplinary rehabilitation and long-term community reintegration
- Emphasis on prevention (road safety, fall prevention) and safe transfer
- Decompression timing constrained by theatre and imaging access
- Pressure-injury and bladder care become dominant survival determinants
- Outcomes hinge on basic nursing, catheter care and contracture prevention
Early transfer to a specialised spinal cord centre improves outcomes worldwide. Contact retrieval services early for cervical and complete injuries, maintain spinal precautions and MAP support in transit, and document a clear baseline neurological examination for handover.
Controversies and Areas of Uncertainty
SCI management contains several genuinely unresolved questions, the steroid debate under Management among them. Examiners reward a candidate who can argue both sides rather than recite a single dogmatic answer.
How early is early surgery? STASCIS supports decompression within 24 hours. Emerging data and meta-analyses argue for an even tighter "ultra-early" window of under 8 to 12 hours, especially for cervical injuries. The counter-argument is logistical feasibility and the risk of operating on a haemodynamically unstable patient.
The MAP target and its duration. The 85-90mmHg for 5-7 days target is widely cited but rests on small case series, not RCTs. Some argue the threshold should be individualised using spinal cord perfusion pressure (MAP minus intrathecal pressure) measured through an intrathecal catheter, an investigational approach.
Timing in central cord syndrome. Traditional teaching favoured conservative management, given good spontaneous recovery. The 2017 AOSpine guideline now suggests early surgery as an option even in central cord syndrome, though on low-quality evidence, and practice remains genuinely divided.
Riluzole, hepatocyte growth factor, anti-Nogo antibodies, cell-based therapies and CSF drainage are all under investigation. None is established standard of care. A safe exam answer: "Current management is supportive and surgical; pharmacological neuroprotection and regenerative therapies remain experimental."
MCQ Practice Points
Q: What defines an ASIA A spinal cord injury? A: Complete injury with no motor or sensory function below the level, including S4-S5. Less than 5% will regain functional ambulation regardless of treatment timing.
Q: What is the clinical significance of sacral sparing after spinal cord injury? A: Sacral sparing indicates incomplete injury (ASIA B or better). Check perianal sensation, deep anal pressure, and voluntary anal contraction. Prognosis is significantly better than complete injury.
Q: What is the difference between neurogenic shock and spinal shock? A: Neurogenic shock = cardiovascular (hypotension + bradycardia from sympathetic loss). Spinal shock = neurological (areflexia and flaccidity below level). They often coexist but are distinct entities.
Q: What is the target MAP in acute spinal cord injury and for how long? A: MAP 85-90 mmHg for 5-7 days to optimize spinal cord perfusion and prevent secondary ischemic injury. Norepinephrine is preferred vasopressor.
Q: What is the current recommendation regarding methylprednisolone in acute SCI? A: NOT recommended. NASCIS trials were methodologically flawed with post-hoc analysis only. Current AANS/CNS guidelines recommend against routine steroid use.
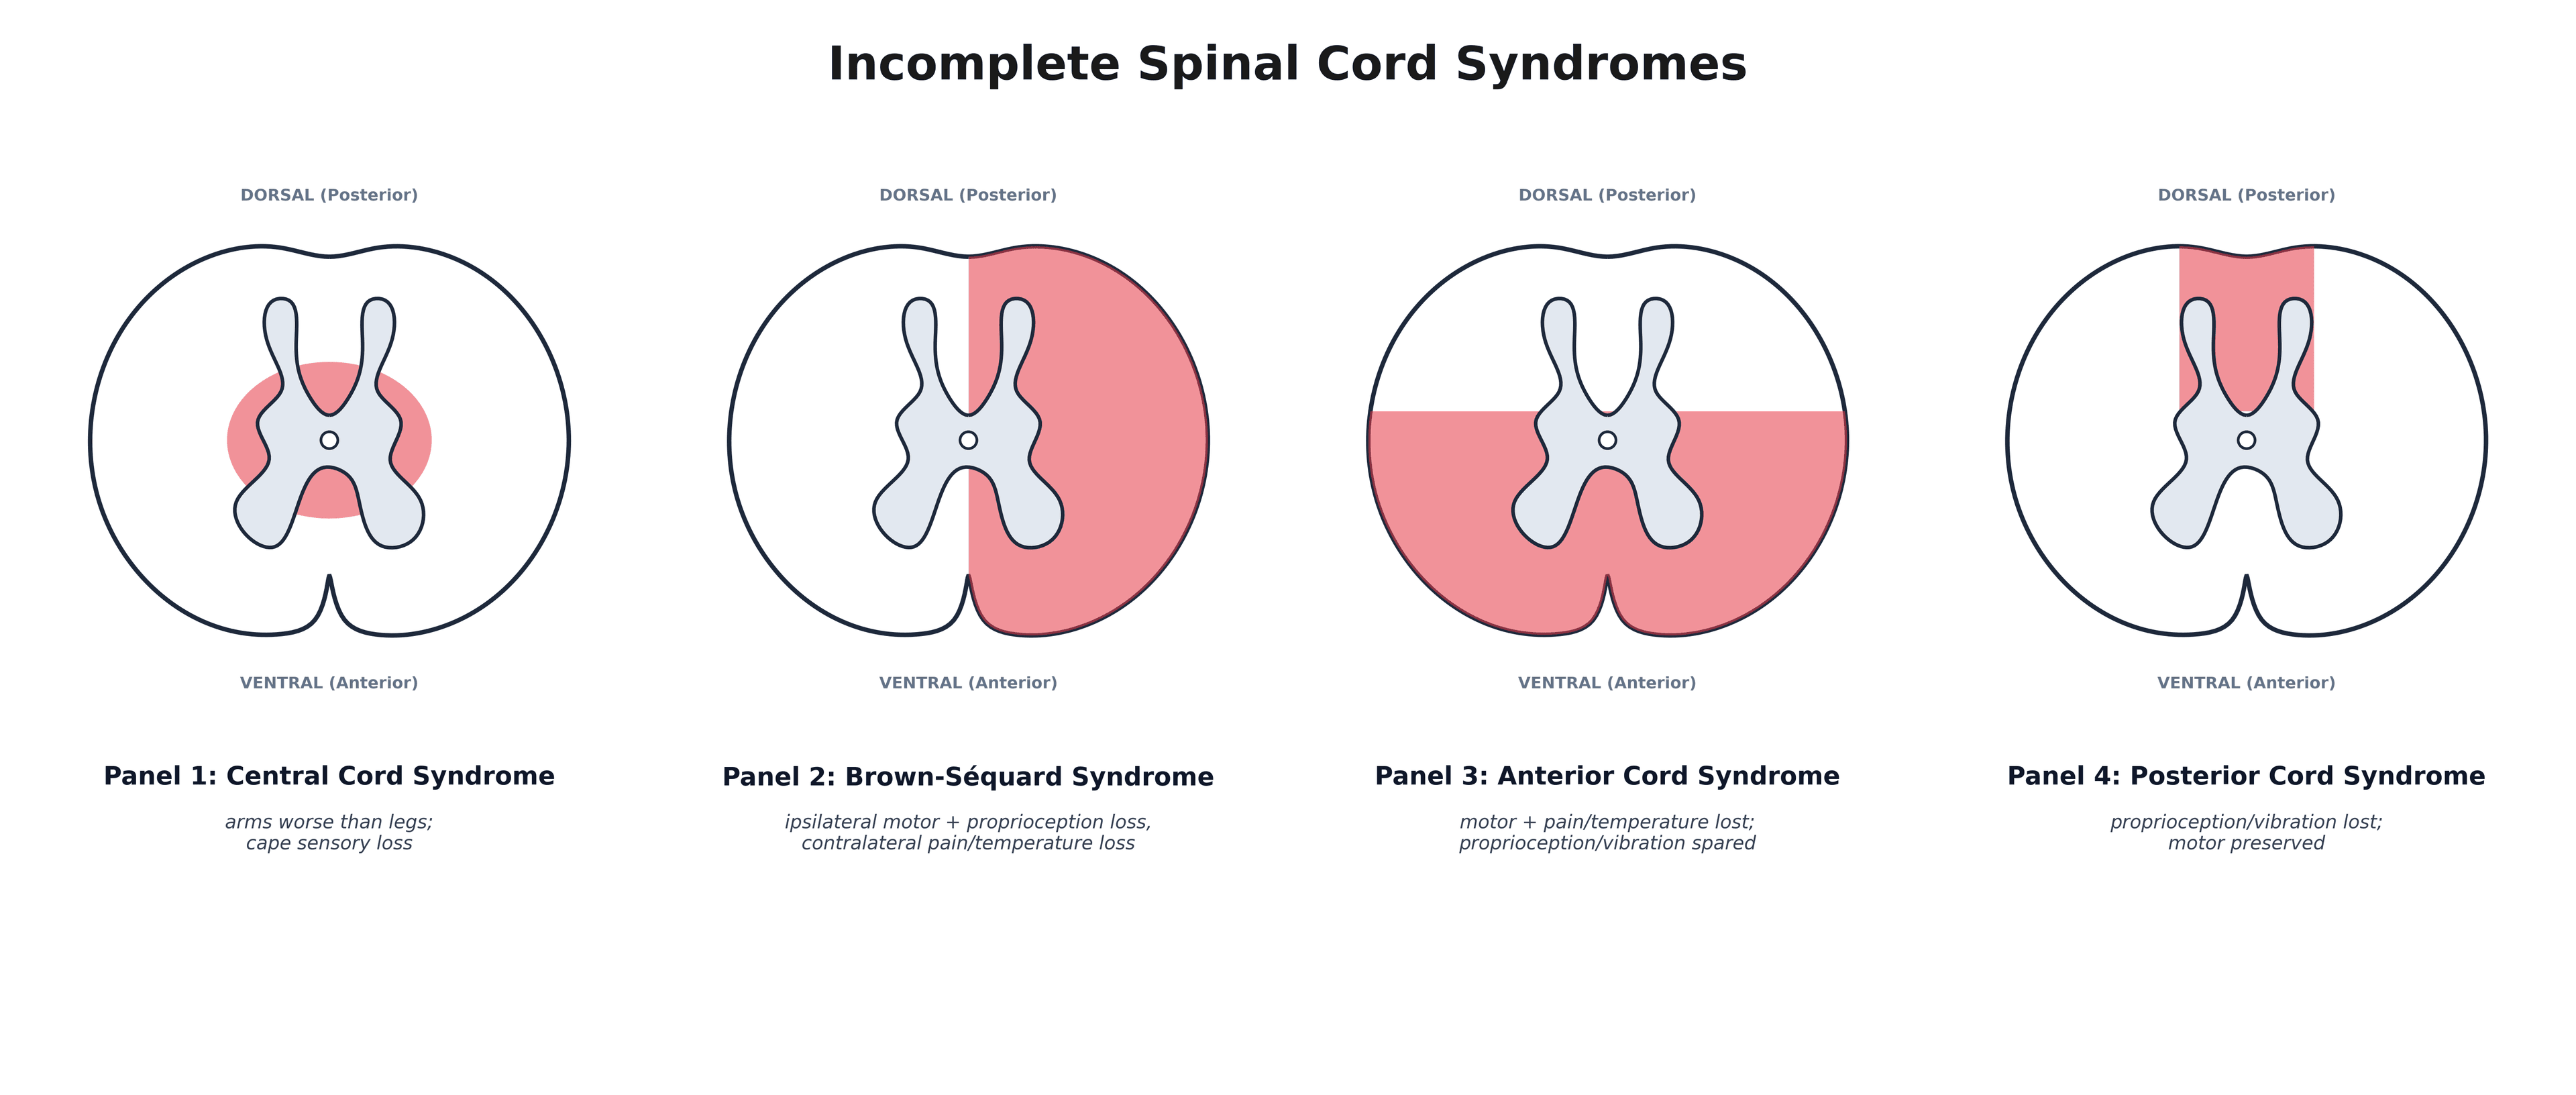
Q: Which incomplete SCI syndrome has the best and worst prognosis? A: Best: Brown-Sequard syndrome (90% ambulatory). Worst: Anterior cord syndrome (only 10-20% recovery; only dorsal columns spared). Central cord has intermediate but favorable prognosis.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 25-year-old male is brought to ED after a diving accident. He has no motor or sensory function below C5 level. His BP is 80/50 and heart rate is 48. How would you manage this patient?”
“A 68-year-old man with known cervical spondylosis falls backwards and presents with weakness affecting his upper limbs more than lower limbs. Describe the syndrome and management.”
“Discuss the evidence for and against methylprednisolone in acute spinal cord injury.”
“A 30-year-old man with a chronic complete T4 spinal cord injury presents with a sudden severe pounding headache, flushing and sweating above the level of injury, and a blood pressure of 200/110. What is happening and how do you manage it?”
ASIA Classification
- A = Complete (no motor/sensory S4-S5)
- B = Sensory only incomplete
- C = Motor incomplete (less than grade 3)
- D = Motor incomplete (grade 3+)
- E = Normal
Neurogenic vs Spinal Shock
- Neurogenic: Hypotension + bradycardia (cardiovascular)
- Spinal: Areflexia below level (neurological)
- Spinal shock ends when bulbocavernosus returns
- Neurogenic shock occurs with T6 and above injuries
Acute Management
- MAP 85-90mmHg for 5-7 days
- Steroids not routine (NASCIS benefit was post-hoc); AOSpine 2017 allows a 24h course within 8h as an option only
- Early surgery within 24h for incomplete SCI
- DVT prophylaxis essential
Incomplete Syndromes
- Central cord: UL worse than LL, favourable ambulation prognosis
- Brown-Sequard: Hemisection, good prognosis
- Anterior cord: Worst prognosis (dorsal spared)
- Posterior cord: Rare, proprioception loss
Prognosis by ASIA Grade
- ASIA A: Less than 5% functional ambulation
- ASIA B: 50% regain walking
- ASIA C: 75% improve one grade
- ASIA D: 95% maintain community walking
Evidence Base and Key Trials
NASCIS II: Methylprednisolone or Naloxone in Acute SCI
- Multicentre double-blind RCT: 487 patients (162 methylprednisolone, 154 naloxone, 171 placebo)
- Primary analysis: no overall benefit of methylprednisolone or naloxone
- Post-hoc subgroup: benefit only when methylprednisolone started within 8 hours
- Mortality and major morbidity similar across groups
NASCIS III: 24h vs 48h Methylprednisolone vs Tirilazad
- Double-blind RCT: 499 patients across 16 North American SCI centres
- All received a 30 mg/kg bolus; then 24h or 48h methylprednisolone, or 48h tirilazad
- 48h regimen gave modest motor gains only in the post-hoc 3-8 hour subgroup
- 48h regimen increased severe sepsis and severe pneumonia
STASCIS: Early vs Delayed Decompression in Cervical SCI
- Prospective multicentre cohort: 313 patients with acute cervical SCI
- Early (less than 24h, mean 14.2h) vs late (mean 48.3h) decompression
- At 6 months, 19.8% of early vs 8.8% of late patients improved by 2 or more AIS grades
- Adjusted odds of 2-grade AIS improvement 2.8 times higher with early surgery; complication rates similar
AOSpine Guideline: Methylprednisolone in Acute SCI
- GRADE-based systematic review and multidisciplinary guideline
- No difference in motor score change overall with methylprednisolone vs no steroid
- Suggests NOT offering 24h high-dose MPSS to patients presenting after 8 hours
- Suggests a 24h infusion MAY be offered within 8 hours as an option; recommends against any 48h regimen
AOSpine Guideline: Timing of Decompression (incl. Central Cord)
- GRADE-based guideline on surgical timing (24h or less vs over 24h)
- Suggests early surgery be offered as an option for acute SCI regardless of level
- Suggests early surgery be considered as an option in traumatic central cord syndrome
- Quality of evidence rated low for both recommendations