Progressive Motor Neuron Disease
- SMN1 Gene: Survival motor neuron gene mutation.
- Four Types: Based on age of onset and motor milestones.
- Scoliosis: effectively universal in untreated Type I/II and common in Type III - but say UNTREATED, because early disease-modifying therapy is already reducing curve severity and the natural history is being rewritten.
- New Therapies: Gene therapy and antisense oligonucleotides.
- Respiratory Care: Primary cause of mortality.
- “Know the SMA types and motor milestones
- “Scoliosis is nearly universal
- “Gene therapy has changed prognosis
- “Respiratory failure is the main cause of death
Overview/Epidemiology
Spinal muscular atrophy (SMA) is a progressive neuromuscular disorder in which the anterior horn cells of the spinal cord degenerate. Before gene therapy it was the leading genetic cause of infant death, and new disease-modifying therapies have since changed its prognosis dramatically.
Genetics. Inheritance is autosomal recessive, from a mutation or deletion of SMN1 (survival motor neuron 1) on chromosome 5q. Incidence is approximately 1 in 11,000 live births, the international consensus figure, and the carrier frequency roughly 1 in 40-60.
Pathophysiology
The lesion. The anterior horn cells, the lower motor neurons, degenerate and the skeletal muscles they supply are denervated. Weakness is proximal more than distal, and the lower limbs are typically weaker than the upper.
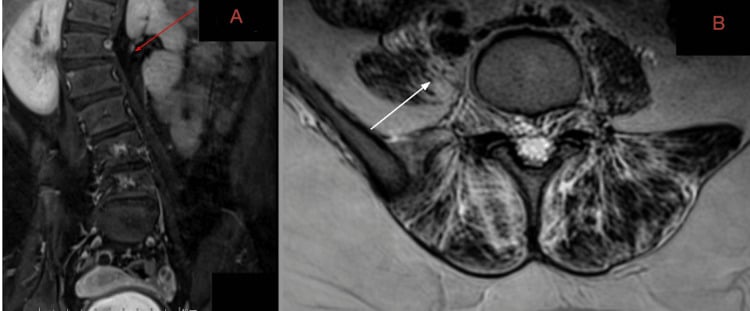
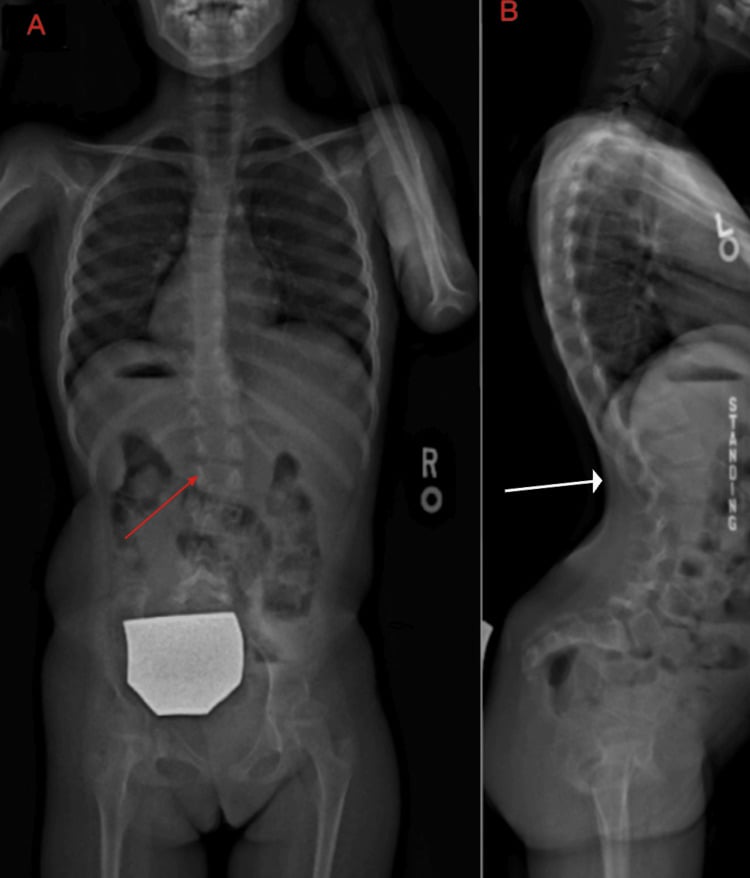
Why scoliosis develops. Trunk weakness and loss of antigravity control allow a long, flexible neuromuscular curve to progress. Scoliosis is universal in untreated Type I and II, and pelvic obliquity and poor sitting balance are common in non-ambulant children. Curves are often long thoracolumbar sweeps, but configuration varies, so do not define SMA by a single mandatory C-shaped pattern.
Treatment is changing the curve. Disease-modifying therapy is changing the onset and progression of scoliosis, so follow each child's radiographic and functional trajectory. Orthopaedic manifestations may still occur after early treatment, but they are less severe.
SMN1/SMN2 Molecular Biology
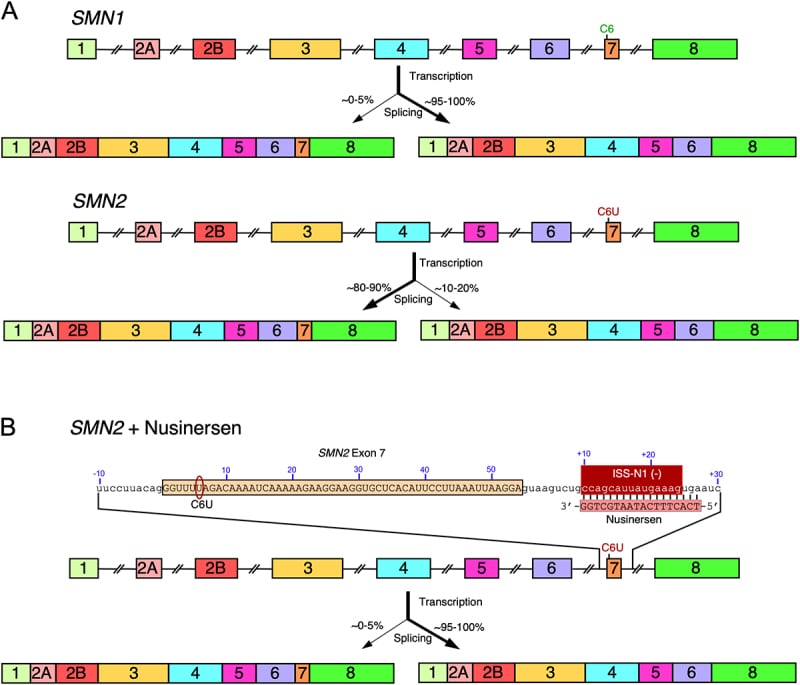
Two genes, one protein. SMN1 is the primary gene producing full-length, functional survival motor neuron (SMN) protein, and homozygous loss or mutation of SMN1 causes SMA. SMN2 is a near-identical paralogue in the same chromosome 5q region. It differs from SMN1 by a single translationally silent C-to-T nucleotide change within exon 7.
The splicing defect. That single base change disrupts an exonic splicing enhancer, so most SMN2 transcripts skip exon 7 and produce a truncated, rapidly degraded protein (SMNΔ7). Only roughly 10 to 15 percent of SMN2 output is full-length functional SMN.
Why copy number is prognostic. SMN2 is present in variable copy number, from 1 to 4 or more. Each extra copy adds a little more full-length SMN and partially compensates for the absent SMN1, so more copies correlate with a milder phenotype. Typical copy numbers by type:
- Type I: 1 to 2 copies
- Type II: 3 copies
- Type III: 3 to 4 copies
Copy number predicts severity at a population level but is not an absolute individual guarantee.
Every therapy raises SMN. All the disease-modifying therapies target the same bottleneck, the supply of functional SMN. Nusinersen, an antisense oligonucleotide, and risdiplam, a small molecule, both promote exon-7 inclusion so that SMN2 makes more full-length protein. Onasemnogene abeparvovec instead delivers a replacement SMN1 transgene in an AAV9 vector. The principles of the gene-replacement platform itself are covered in the gene therapy and tissue engineering topic.
Classification Systems
The four types are defined by age at onset and the best motor milestone reached.
- Onset
- Birth to 6 months
- Motor Milestones
- Never sits
- Features
- Severe hypotonia, frog-leg posture, paradoxical breathing
- Prognosis
- Death by 2 years without treatment (respiratory failure)
- Onset
- 6-18 months
- Motor Milestones
- Sits, never walks independently
- Features
- Proximal weakness, tremor (minipolymyoclonus), scoliosis
- Prognosis
- Survives into adulthood with respiratory support
- Onset
- After 18 months (typically 2-17 years)
- Motor Milestones
- Walks (may lose the ability later)
- Features
- Proximal weakness, waddling gait, Gowers' sign
- Prognosis
- Normal or near-normal lifespan
- Onset
- Adulthood
- Motor Milestones
- Walks
- Features
- Mild, slowly progressive weakness
- Prognosis
- Normal lifespan
Treatment has rewritten Type I. With gene therapy, survival in Type I has improved dramatically and many children are achieving motor milestones. Early treatment, before symptom onset, leads to the best outcomes.
Clinical Assessment
History. Establish the age of symptom onset, the motor milestones achieved and those since lost, the family history and the respiratory status.
Examination. The findings to look for:
- Hypotonia, the floppy infant of Type I
- Weakness, proximal greater than distal and symmetric
- Reflexes absent or diminished
- Tongue fasciculations, which are characteristic
- The spine, for scoliosis
- The hips, for dysplasia and contractures
Investigations
Genetic testing. An SMN1 deletion or mutation confirms the diagnosis, and the SMN2 copy number gives the prognosis. EMG and nerve conduction studies show a denervation pattern but are rarely needed now that genetic testing is available.
Pulmonary function. Monitor the forced vital capacity (FVC).
Spine radiographs. Obtain seated or standing whole-spine radiographs according to motor status, curve progression and treatment planning. Assess pelvic obliquity and sagittal alignment, not the Cobb angle alone.
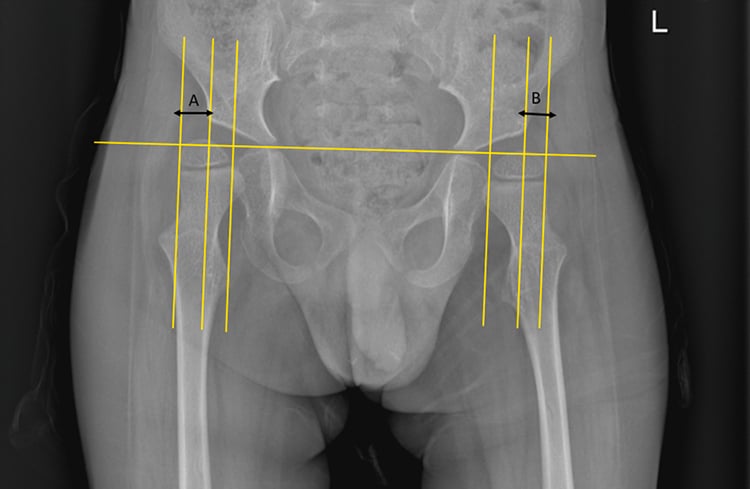
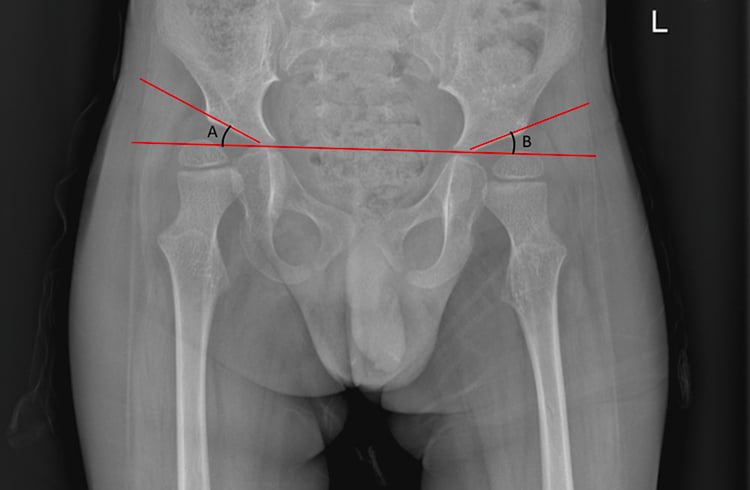
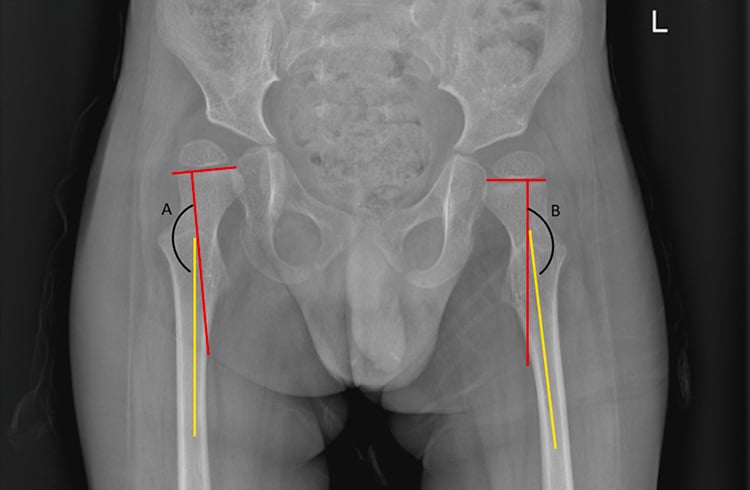
Hip radiographs. Pelvic radiographs are symptom- and surveillance-driven. When hip displacement is being followed, document three measurements, and follow them together when progressive displacement is being considered for intervention:
- Migration percentage (Reimer), the proportion of each femoral head lateral to Perkin's line. Use reproducible serial measurements to follow displacement rather than describing the hip simply as located or dislocated.
- Acetabular index, measured between Hilgenreiner's line and the acetabular roof. It records acetabular dysplasia separately from femoral-head migration, which helps explain why identical migration percentages may represent different hip morphology.
- Head-shaft angle, which quantifies proximal-femoral valgus.
Differential Diagnosis
- Inheritance / Cause
- Autosomal recessive, SMN1 deletion (5q)
- Discriminating Features
- Tongue fasciculations, absent reflexes, normal/mildly raised CK, SMN1 testing confirmatory
- Inheritance / Cause
- X-linked, dystrophin gene
- Discriminating Features
- Boys, markedly elevated CK, calf pseudohypertrophy, Gowers sign, preserved early reflexes
- Inheritance / Cause
- Various (e.g. nemaline, central core)
- Discriminating Features
- Static or slowly progressive, normal/mildly raised CK, characteristic muscle biopsy/genetics
- Inheritance / Cause
- Autosomal dominant, DMPK repeat (maternal)
- Discriminating Features
- Facial diplegia, myotonia, maternal symptoms, polyhydramnios history
- Inheritance / Cause
- Tumour, syrinx, cord compression
- Discriminating Features
- Sensory level, asymmetry, sphincter involvement; MRI differentiates
- Inheritance / Cause
- Enzyme deficiency (e.g. Pompe)
- Discriminating Features
- Exercise intolerance, cardiomyopathy (Pompe), specific enzyme/genetic assays
Key Differentiators for SMA: SMN1 genetic testing is confirmatory; tongue fasciculations are characteristic; CK is normal or only mildly elevated; reflexes are absent or diminished.
Management Algorithm
Disease-modifying therapy. Three agents are in use:
- Onasemnogene abeparvovec (Zolgensma): gene therapy, a single IV dose in infants
- Nusinersen (Spinraza): intrathecal injections every 4 months
- Risdiplam (Evrysdi): an oral SMN2 splicing modifier
Respiratory and nutritional care. Respiratory failure is the primary cause of death, and respiratory care is the primary focus of treatment: BiPAP, cough assist and suctioning. A gastrostomy is placed if swallowing is impaired.
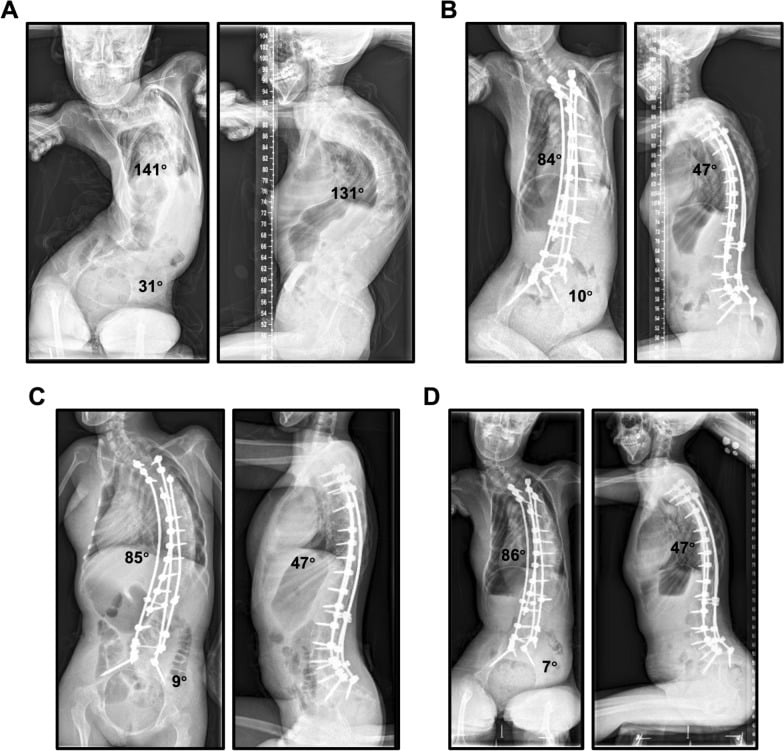
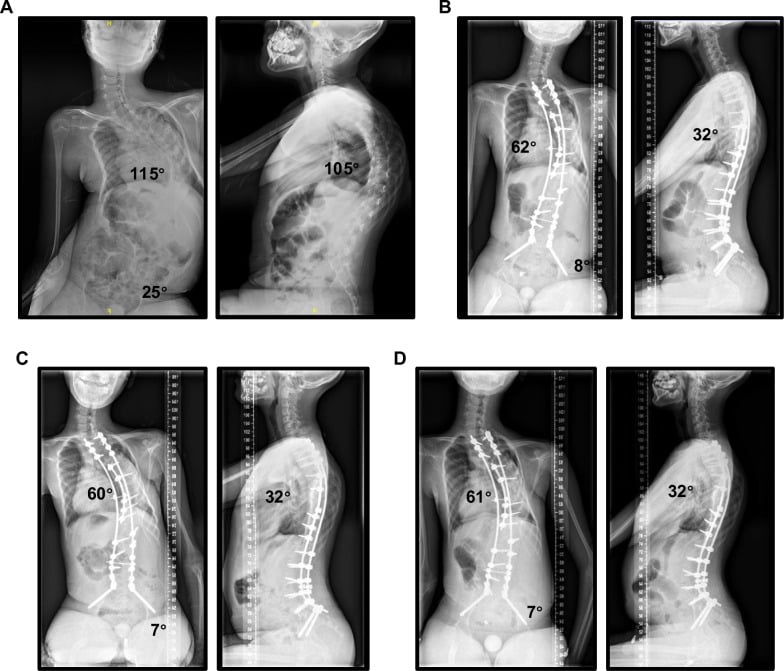
Scoliosis. Seating systems and braces support posture and function but do not reliably halt structural progression. Surgery is for progressive deformity that compromises sitting balance, pelvic level, pain, care or respiratory mechanics despite non-operative support. Decide from the combined picture of progression, growth remaining, sitting balance, pelvic obliquity, pain, care difficulty and respiratory trajectory rather than a single Cobb-angle or FVC threshold; the Cobb angle informs timing but is not a stand-alone trigger.
Hip displacement. Displacement is common in Type I and II and is usually observed. Many painless displaced hips are managed this way, especially when reduction would not improve function or seating. Monitor symptoms, migration and pelvic obliquity, and escalate for pain, progressive displacement, loss of function or care difficulty through a multidisciplinary, goal-directed plan.
Contractures. Contractures at the hips, knees, ankles and feet affect positioning and function. Preserve comfortable range with positioning, stretching, splinting and therapy, and operate selectively, with releases, when a contracture blocks function, hygiene, seating or orthotic use.
Surgical Techniques
Growth-friendly surgery. In younger children, traditional growing rods, magnetically controlled rods and other growth-friendly strategies trade repeated procedures or implant complications against preservation of thoracic growth. Selection depends on age, curve magnitude and flexibility, chest growth, bone quality, respiratory reserve and family goals. Some children later undergo definitive fusion; others follow different paths as disease-modifying therapy changes growth and motor function.
Posterior spinal fusion. For sitters, the guidance summarised below recommends a long fusion to the pelvis once growth is adequate. Even so, fusion extent and whether to include the pelvis depend on curve flexibility, pelvic obliquity, ambulatory potential, bone quality and fixation strategy. Iliac and S2-alar-iliac fixation are both established options, and pelvic fixation is not mandatory for every child.
Anaesthetic & Perioperative Considerations
Scoliosis surgery in SMA carries a high perioperative risk and needs an experienced team. The airway and ventilation, not the spine, are what threaten the patient.
Respiratory reserve. Intercostal weakness produces restrictive lung disease with a low and falling FVC, and a low pre-operative FVC predicts post-operative ventilatory dependence. A low FVC increases risk but should prompt planning rather than act as an isolated exclusion.
Preparation. Treat any chest infection, support nutrition, and train the child with non-invasive ventilation (NIV/BiPAP) and mechanical cough assist before surgery. Long instrumented fusions carry significant blood loss, so plan cross-match, cell salvage and blood management, with neuromonitoring and pressure protection.
Extubation. Plan for elective post-operative NIV and aggressive secretion clearance rather than reactive re-intubation. Protocolised extubation directly onto NIV reduces re-intubation after scoliosis fusion.
Airway and drugs. Bulbar weakness and impaired cough mean a real aspiration risk, so airway protection and secretion management need care. Avoid depolarising neuromuscular blockers (suxamethonium): denervated, atrophic muscle carries up-regulated extrajunctional acetylcholine receptors and risks life-threatening hyperkalaemia. Expect heightened and prolonged sensitivity to non-depolarising relaxants and to opioids and sedatives; titrate carefully, use quantitative neuromuscular monitoring and ensure full reversal.
A classic examiner trap: SMA is a denervating motor-neuron disease and is not associated with malignant hyperthermia, so volatile agents are not contraindicated on MH grounds. Suxamethonium is still avoided, for the hyperkalaemia risk in chronically denervated muscle. (The MH syndrome itself, its triggers and dantrolene management, is dealt with in the malignant hyperthermia topic, and the general conduct of anaesthesia in the general anaesthesia in orthopaedics topic.)
Postoperative Care
The child is admitted to intensive care after scoliosis surgery and may require prolonged ventilation. Analgesia is multimodal, and the child sits early in the wheelchair. Bracing is discontinued after fusion, while respiratory and nutritional support continue long term.
Outcomes/Prognosis
What fusion gives. Scoliosis surgery transforms sitting balance and quality of life: independent sitting rose from 22.7% to 77.3% in one severe-deformity series.
What it does not. Respiratory function is preserved rather than gained. Mean FVC remained stable in that series, but all six SMA patients in a separate pulmonary-function series lost vital capacity after fusion (see the evidence below). The honest consent line is that surgery does not reverse the respiratory decline and may reduce vital capacity.
Guidelines, Registries & Global Practice
Global epidemiology
- Incidence approximately 1 in 11,000 live births; pan-ethnic, with carrier frequency roughly 1 in 40-60.
- SMN2 copy number is the principal genetic modifier worldwide: 2 copies predict the most severe phenotype, while 3 or more copies predict milder disease.
Major guidelines, side by side
- Scope
- Diagnosis, orthopaedic, rehabilitation, nutrition
- Key recommendation
- Manage by functional status (non-sitter/sitter/walker); growth-friendly instrumentation early, fusion to pelvis once growth adequate
- Scope
- Pre-symptomatic detection
- Key recommendation
- Population SMN1 screening enables treatment before motor-neuron loss; best outcomes when treated pre-symptomatically
- Scope
- Disease-modifying therapy
- Key recommendation
- Three approved DMTs (onasemnogene, nusinersen, risdiplam); choice driven by age, weight, SMN2 copies and access
- Scope
- Surgical timing
- Key recommendation
- Long fusion to pelvis for sitters; preserve intrathecal access if continuing nusinersen
Registries & access
- No single global SMA implant registry; outcome data come from national neuromuscular registries (e.g. TREAT-NMD, SMArtCARE in Europe, Cure SMA in North America) and tertiary-centre series.
- Newborn screening for SMA is now established across much of North America, Europe and parts of Asia-Pacific, but coverage remains uneven globally.
High- vs limited-resource practice variation
- High-resource settings: newborn screening, early disease-modifying therapy, MAGEC/growth-friendly constructs, intrathecal-access-preserving fusion, ICU-supported neuromuscular spine surgery.
- Limited-resource settings: diagnosis often clinical or delayed; disease-modifying drugs frequently unaffordable; management centres on respiratory support, seating, contracture care, and fusion where safe perioperative care exists.
Controversies & Areas of Uncertainty
- Spinal surgery in the gene-therapy era: Disease-modifying therapy is reducing curve severity in early-treated children, but it is unclear whether it will eliminate the need for fusion or merely delay it. Long-term natural history of the treated cohort is still being defined.
- Timing of fusion vs growth-friendly constructs: When to convert magnetically controlled growing rods to definitive fusion, and whether early definitive fusion in older children is preferable, remains debated; both strategies show durable correction in current series.
- Preserving intrathecal access: Nusinersen requires repeated intrathecal injection, so "skip" or fenestrated constructs and laminotomy windows are used to keep access; the optimal technique and whether oral risdiplam removes this constraint are unresolved.
- Pulmonary outcome of fusion: Fusion reliably improves sitting and halts deformity, but vital capacity often falls rather than improves after surgery — the respiratory benefit is mainly preservation, not gain.
- Lower FVC threshold for surgery: There is no universally agreed FVC cut-off; very low FVC raises perioperative risk but is not an absolute contraindication when seating and quality of life are at stake.
- Hip management: Whether asymptomatic hip subluxation/dislocation ever warrants reconstruction in non-ambulators is contested; most centres observe because reconstruction has high redislocation rates and limited functional gain.
MCQ Practice Points
Q: What gene is mutated in SMA? A: SMN1 (Survival Motor Neuron 1) on chromosome 5q.
Q: A child who can sit but never walks has which SMA type? A: Type II.
Q: What correlates with disease severity? A: SMN2 copy number - more copies = milder phenotype.
Q: What is the mechanism of nusinersen (Spinraza)? A: Antisense oligonucleotide that increases SMN2 expression.
Q: What is the extent of fusion in SMA scoliosis surgery? A: T2 to pelvis with pelvic fixation (S2-alar-iliac or iliac screws).
Q: How should hip dysplasia in SMA be managed? A: Observation - surgery rarely indicated due to high failure rate and minimal functional benefit.
Self-Assessment Quiz
Additional Quiz Questions
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“8-month-old with confirmed SMA Type I. Has received gene therapy. Now developing thoracolumbar scoliosis of 30 degrees.”
“14-year-old with SMA Type II. Wheelchair-dependent. Thoracolumbar scoliosis of 80 degrees with pelvic obliquity. FVC 35%.”
“Same patient also has bilateral hip subluxation on X-ray. Is this an indication for surgery?”
GENETICS
- SMN1 Mutation
- Autosomal Recessive
- SMN2 Copies = Prognosis
- Chromosome 5q
TYPES
- I: Never sits
- II: Sits, never walks
- III: Walks
- IV: Adult onset
ORTHO ISSUES
- Scoliosis (universal)
- Hip Dysplasia
- Contractures
- Pelvic Obliquity
SCOLIOSIS SURGERY
- T2 to Pelvis Fusion
- Pelvic Fixation Essential
- High Perioperative Risk
- ICU Postop Care
MEDICAL THERAPY
- Onasemnogene (Gene Therapy)
- Nusinersen (Intrathecal)
- Risdiplam (Oral)
- Early Treatment Best
EXAM PEARLS
- Tongue Fasciculations
- 100% Scoliosis in Type I/II
- Hip Surgery Rarely Indicated
- FVC Monitoring Critical
Evidence Base
Mendell et al (AVXS-101 Phase 1)
- Single IV dose of AAV9-SMN gene therapy in 15 infants with SMA type 1
- All 15 alive and event-free at 20 months vs 8% survival in a historical cohort
- High-dose cohort: CHOP INTEND rose 15.4 points by 3 months; 11 of 12 sat unassisted, 2 walked
- Transient transaminitis attenuated by prednisolone
Finkel et al (ENDEAR)
- Randomised, double-blind, sham-controlled phase 3 trial of intrathecal nusinersen in infantile-onset SMA
- Motor-milestone response 51% (37/73) vs 0% (0/37) in controls
- Hazard ratio for death or permanent ventilation 0.53 (P=0.005)
- Trial stopped early at interim analysis for efficacy
Masson et al (FIREFISH Part 2)
- Open-label trial of oral risdiplam in 41 infants with type 1 SMA (2 SMN2 copies)
- At 24 months, 44% (18/41) sat without support for at least 30 seconds vs a 5% natural-history threshold
- No infant achieved standing or independent walking
- Most common serious adverse events were pneumonia (39%) and respiratory distress
Mercuri et al (International SMA Standard of Care, Part 1)
- Consensus update on diagnosis, rehabilitation, orthopaedic/spinal and nutritional care
- SMA incidence approximately 1 in 11,000 live births
- Spinal management framed by functional status (non-sitter / sitter / walker)
- Recommends growth-friendly instrumentation in young children and definitive fusion to pelvis once growth is adequate
Sun et al (severe scoliosis with pelvic obliquity)
- 22 SMA patients with curves over 100 degrees and pelvic obliquity over 20 degrees, one-stage PSF with pelvic fixation
- Independent sitting improved from 22.7% preoperatively to 77.3% postoperatively (P less than 0.001)
- Mean FVC remained stable; 50% improved
- Perioperative complications in 27.3% (pneumonia, epiglottic oedema, delayed wound healing); none needed reoperation
Gaume et al (MCGR vs PSF, T-construct)
- 26 SMA type 2 patients: 17 magnetically controlled growing rods (MCGR), 9 posterior spinal fusion (PSF)
- Major curve correction 44% (MCGR) and 55% (PSF); pelvic obliquity under 5 degrees in all at follow-up
- Pelvic fixation by T-construct (2 sacral plus 2 iliac screws); lung function unchanged by either procedure
- Low complication rate; all patients improved sitting ability
Konigsberg et al (skip constructs)
- Modified PSF skipping a thoracolumbar level to preserve intrathecal access for nusinersen
- 8 patients, mean curve correction 35.2 degrees, 4-year follow-up
- No rod breakage or loss of correction; one revision for bony overgrowth at the skipped level
Farber et al (PFT after fusion)
- Pulmonary function before and after PSF in neuromuscular disease
- All 6 SMA patients lost vital capacity (mean loss 0.63 L)
- Contrasts with merosin-deficient dystrophy, which gained VC