Midfoot Degenerative Joint Disease | Triple Joint Complex | Surgical Challenge
- TN joint is critical for hindfoot-forefoot motion and inversion/eversion
- Arthritis commonly involves adjacent joints - check subtalar and calcaneocuboid
- Isolated TN arthrodesis spares the subtalar and calcaneocuboid cartilage but abolishes most hindfoot motion (Astion cadaver data: about 2 degrees residual)
- Triple arthrodesis indicated when multiple hindfoot joints involved
- Adult-acquired flatfoot (PTTD Stage 3) commonly leads to TN arthritis
- “TN joint contributes 50% of hindfoot inversion/eversion
- “Beaking on dorsal navicular = chronic TN arthritis hallmark
- “Beware posterior tibial tendon dysfunction coexistence
- “Isolated TN fusion: consider ball-and-socket ankle contraindication
Overview and Epidemiology
Talonavicular arthritis is degeneration of the articulation between the talar head and the navicular. The joint is the apex of the medial longitudinal arch, so its failure profoundly affects foot biomechanics: the arch collapses, the forefoot abducts and the gait pattern changes.
It rarely exists in isolation. Isolated talonavicular arthritis is uncommon, 10-15% of cases. The joint usually fails as part of triple-complex pathology, often alongside posterior tibial tendon dysfunction (PTTD), so the subtalar and calcaneocuboid joints are assessed in every patient.
- PTTD stage 3 - the most common association
- Subtalar arthritis - coexists in 60-70%
- Calcaneocuboid arthritis - involved in 30-40%
- Ankle valgus - a secondary deformity
- Hallux valgus - forefoot compensation
Causes. Post-traumatic arthritis is the most common.
- Trauma - midfoot fracture or dislocation
- Rheumatoid and inflammatory arthropathy - erosive changes are common
- Adult-acquired flatfoot (PTTD) - stage 3 disease causes talonavicular degeneration
- Undercorrected clubfoot - the residual deformity leads to arthritis
- Hindfoot malalignment, varus or valgus - abnormal loading patterns
- Avascular necrosis of the navicular - Müller-Weiss disease in adults
- Systemic causes - gout, septic and neuropathic arthritis, all less common
The Ball-and-Socket Ankle: A Contraindication to Isolated TN Fusion
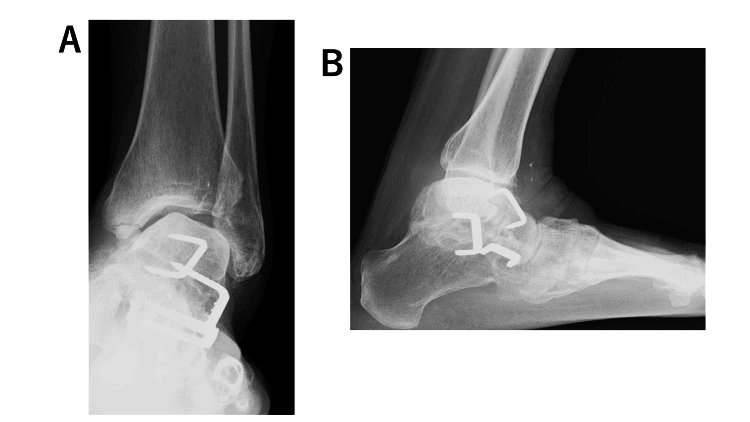
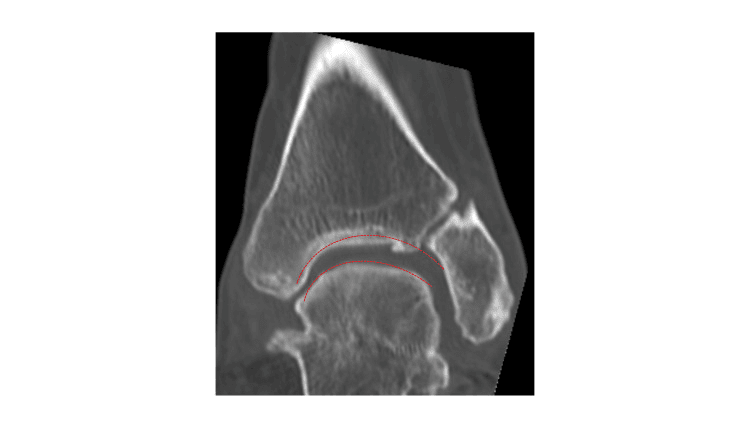
A ball-and-socket ankle - a rounded, domed talar body articulating with a congruent concave tibial plafond - is a compensatory adaptation that develops when native subtalar and transverse-tarsal (inversion/eversion) motion is congenitally absent or lost early in life. The ankle assumes the coronal-plane motion normally shared across the hindfoot. Spotting it on a mortise radiograph should trigger a search for its cause and stop you before offering an isolated talonavicular fusion.
Where it comes from. The ball-and-socket ankle is most classically associated with tarsal coalition, especially talocalcaneal, with congenital longitudinal limb deficiencies such as fibular hemimelia, and with previously operated or fused hindfeet.
Never fuse the talonavicular joint alone in its presence. The reasons:
- The hindfoot already offloads onto the ankle for inversion and eversion; a stiffening TN fusion pushes even more demand onto that single joint, accelerating ankle degeneration
- The "spared" subtalar joint is not truly mobile when a coalition underlies the adaptation, so the motion-sparing rationale for isolated fusion collapses
- The primary pathology is unaddressed, whether coalition or deficiency, so deformity and symptoms recur
What to do instead. Treat a ball-and-socket ankle as a red flag for an underlying coalition and investigate accordingly (see the dedicated tarsal coalition topic). Plan around the whole abnormal hindfoot, not the talonavicular joint in isolation, and counsel that the ankle is the motion reserve, to be protected rather than further loaded.
Pathophysiology and Mechanisms
The joint. A ball and socket: the talar head is the ball and the concavity of the navicular the socket. It is the keystone at the apex of the medial longitudinal arch, and with the subtalar and calcaneocuboid joints it forms the triple joint complex, which functions as an integrated unit. That is why isolated pathology is rare.
What it does. The talonavicular joint lies on the oblique axis of the hindfoot and is the primary site of midfoot motion, contributing 50% of total hindfoot inversion and eversion. It also carries the jobs that make the foot both adaptable and rigid:
- Inversion - 50% of total hindfoot inversion (20-30 degrees)
- Eversion - 50% of total hindfoot eversion (10-15 degrees)
- Forefoot locking - critical for a rigid lever during push-off, giving stability at toe-off
- Shock absorption - hindfoot adaptability on uneven ground
- Hindfoot-forefoot coupling - transmits forces between the segments
The medial restraints. The spring ligament complex gives plantar support from the calcaneus to the navicular; when it fails, the talar head subluxes plantarwards. The posterior tibial tendon inserts on the navicular tuberosity and is intimately related to talonavicular stability, and its dysfunction causes medial column collapse and stresses the joint.
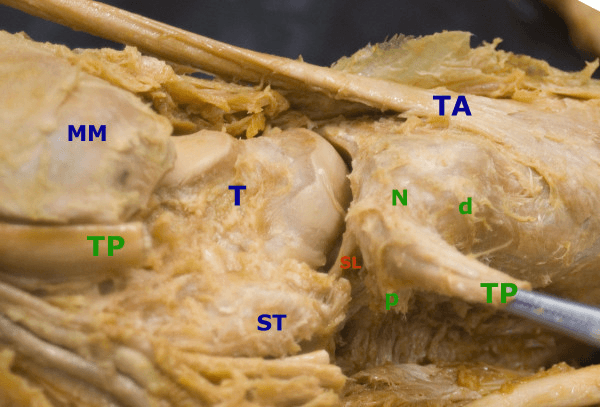
When the joint fails. Loss of talonavicular function shifts motion demands onto the adjacent subtalar, ankle and calcaneocuboid joints, potentially accelerating their degeneration. Within the joint, cartilage loss is progressive, abnormal loading produces subchondral sclerosis, and osteophytes form, with dorsal beaking the characteristic one. As the keystone support goes the arch collapses and the forefoot abducts, a compensatory malalignment.
Classification and Grading
Two things are graded: how severe the arthritis is on radiographs, and how far it has spread across the hindfoot and midfoot. The severity grade guides the choice between conservative and operative care; understanding the distribution pattern helps determine the surgical strategy and predict outcome.
- Radiographic Findings
- Joint space narrowing under 50%, minimal osteophytes
- Clinical Correlation
- Mild pain with activity, preserved function
- Management
- Conservative management preferred
- Radiographic Findings
- 50-75% joint space loss, moderate osteophytes, subchondral sclerosis
- Clinical Correlation
- Moderate pain limiting activity
- Management
- Surgical candidates after failed conservative
- Radiographic Findings
- Bone-on-bone, large osteophytes, deformity, dorsal beaking
- Clinical Correlation
- Severe pain at rest, functional limitation
- Management
- Arthrodesis or arthroplasty indicated
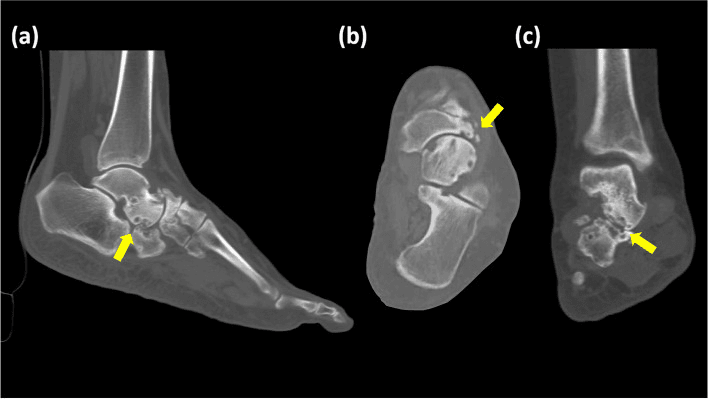
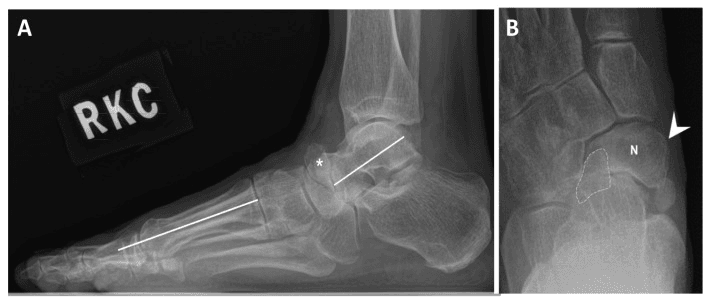
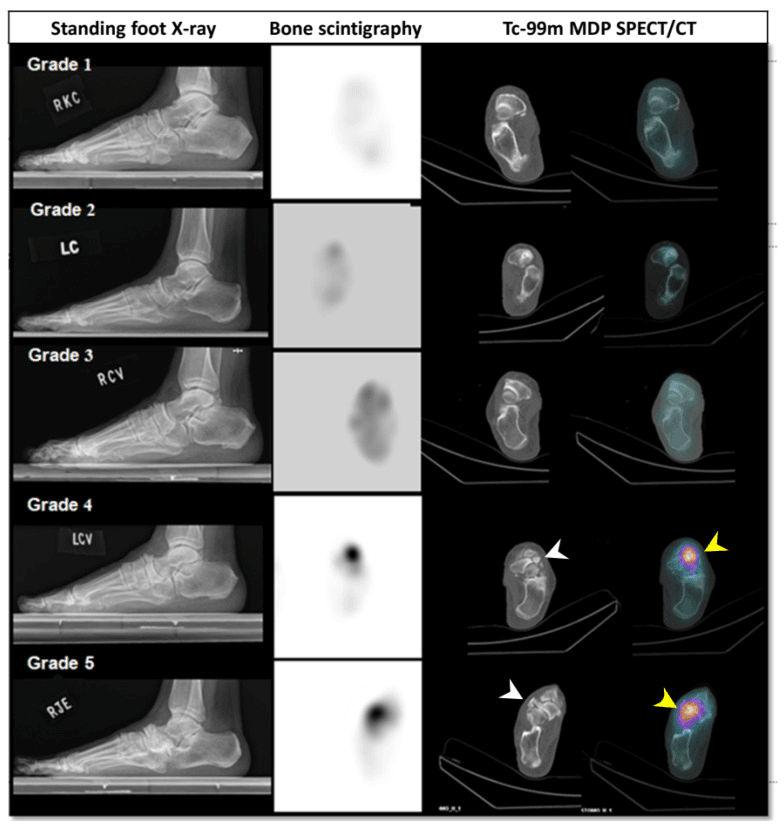
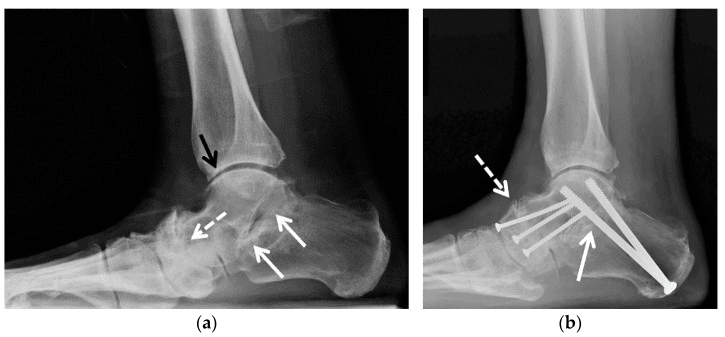
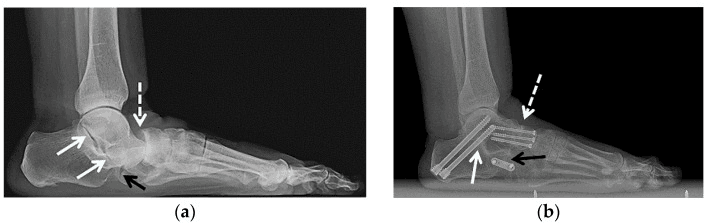
Müller-Weiss disease has its own staging, Maceira's, shown in the two figures below.
Clinical Assessment
History. The pain is dorsomedial, over the navicular: an ache at rest and sharp with activity, made worse by walking, stairs and uneven ground. Patients notice the arch collapsing and the forefoot drifting into abduction, and the functional cost is walking distance and an altered gait. Ask about previous midfoot trauma and ankle sprains.
Examination. Work through the foot in a fixed order:
- Standing - medial arch height, collapsed or normal; forefoot abduction; hindfoot alignment, where valgus suggests PTTD and varus suggests other pathology; the too-many-toes sign, lateral toes visible from behind, indicating flatfoot
- Single heel rise - the patient stands on the affected leg and rises onto the toes. Inability to rise or hold the position means PTT dysfunction, and the heel, which normally inverts during the rise, does not invert in PTTD
- Palpation - talonavicular joint tenderness and dorsal osteophytes
- Hindfoot motion - stabilise the talus and move the navicular, looking for crepitus and pain; hindfoot inversion and eversion are reduced. Compare subtalar motion with the contralateral side, judge whether the deformity is rigid or flexible, which affects the surgical options, and check the ankle and first-ray mobility
- Provocative tests - direct pressure over the joint (TN stress test) reproduces the pain; forefoot abduction stress worsens it if the joint is unstable; in the tiptoe test, pain stops the patient reaching or holding tiptoe
- Gait - antalgic, with loss of push-off power
Up to 70% of TN arthritis cases have coexisting PTTD. Failure to address PTT dysfunction leads to recurrent deformity after TN fusion. Always perform single heel rise test and assess for too-many-toes sign. Stage the PTTD appropriately as it may alter surgical planning.
Investigations
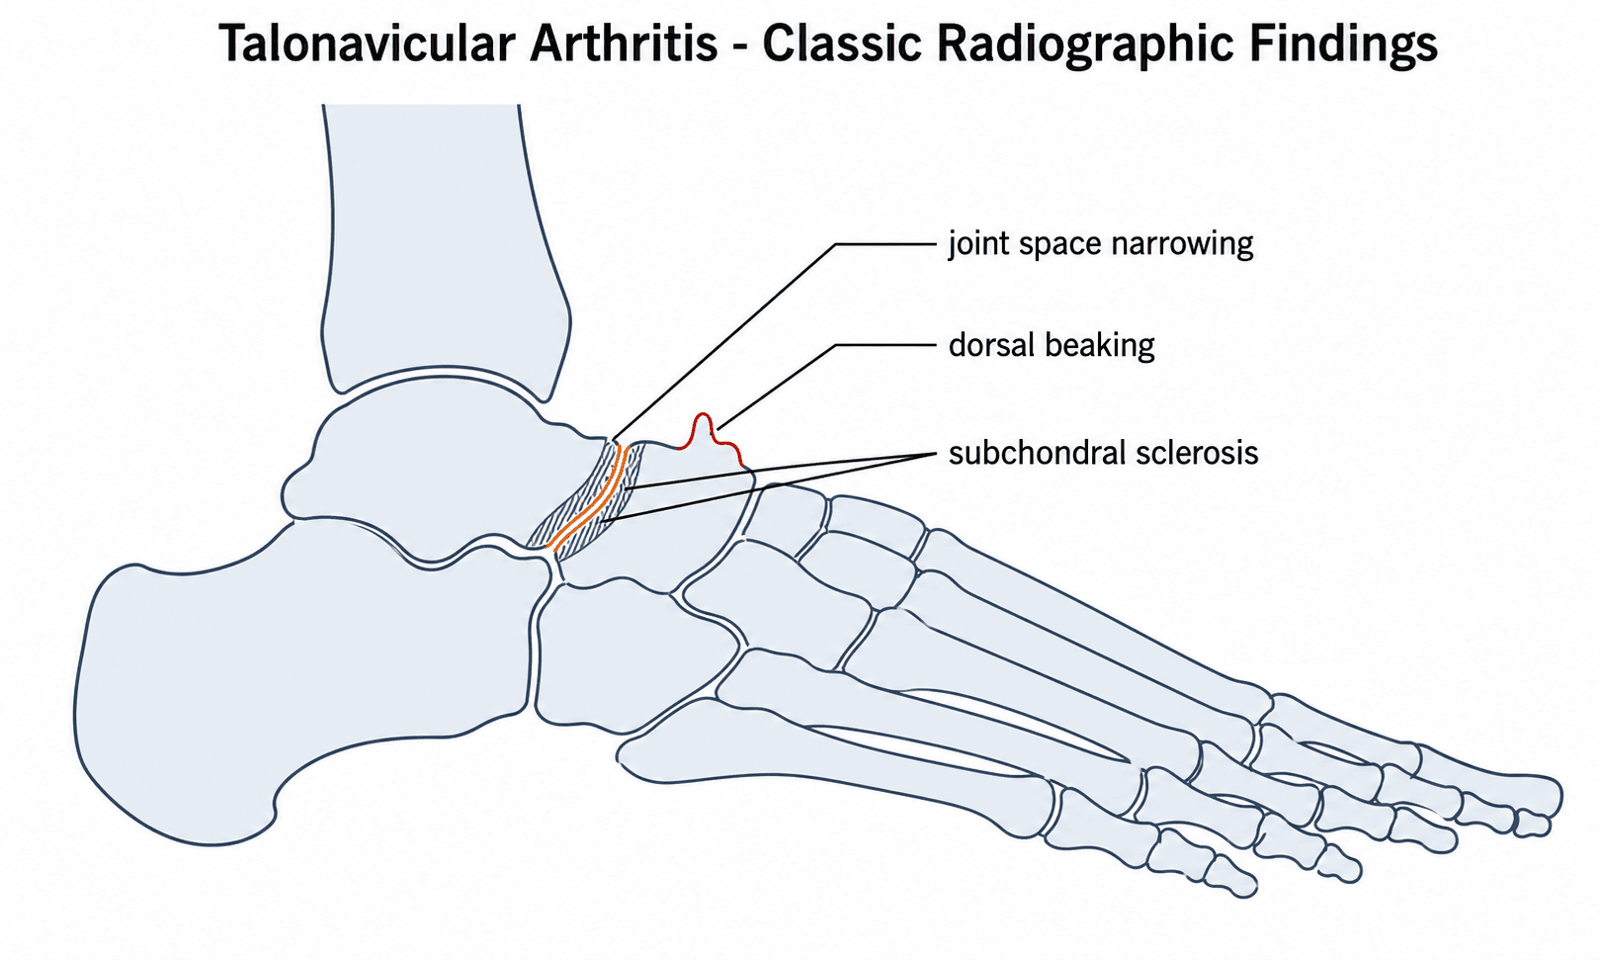
Weight-bearing radiographs come first. Standing AP, lateral and oblique views of the foot show the joint space, osteophytes and dorsal beaking, the alignment (how much of the talar head the navicular covers, and forefoot abduction), and the state of the subtalar and calcaneocuboid joints.
- Description
- Reduction in TN joint space under 2mm
- Clinical Implication
- Primary sign of arthritis - correlates with symptoms
- Description
- Osteophyte formation on dorsal navicular
- Clinical Implication
- Pathognomonic for chronic TN arthritis
- Description
- Increased density at articular surfaces
- Clinical Implication
- Chronic abnormal loading pattern
- Description
- Lateral subluxation, under 60% coverage
- Clinical Implication
- Indicates flatfoot deformity and PTTD
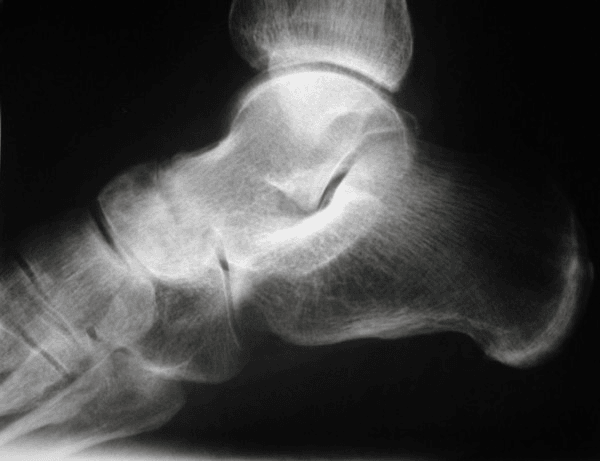
CT is for surgical planning and for judging how severe the deformity is. It shows bone stock quality and the size of subchondral cysts, informs preparation for fusion, and its 3D reconstructions help in understanding complex deformity.
MRI is selective, used before surgery when soft-tissue pathology is suspected. It assesses the integrity of the posterior tibial tendon and spring ligament and the articular cartilage, showing cartilage loss, bone marrow oedema and tendon pathology.
Management Algorithm
The decision rests on the distribution of the arthritis, the severity of the deformity, the patient's age and activity level, and the state of the adjacent joints. Conservative measures come first; arthrodesis, isolated or extended according to the adjacent joints, follows when they fail.
Who. Mild to moderate symptoms, early arthritis (Grade 1-2), and the patient who prefers it or whose medical comorbidities weigh against surgery. The trial lasts a minimum of 6 months before surgery is considered.
The programme.
- Activity modification (initial) - reduce high-impact activities such as running, jumping and prolonged standing, and lose weight if applicable, to decrease stress on the joint in daily life
- Footwear - supportive shoes with a rigid rocker-bottom sole and stiff midsole
- Orthoses (weeks 0-6) - custom orthoses with medial arch support and forefoot posting, or off-the-shelf rigid support with an Arizona brace or UCBL orthosis, to support the arch, reduce talonavicular motion and offload the joint
- Pharmacological (ongoing) - NSAIDs first-line for pain and inflammation; image-guided corticosteroid injection into the joint, which is both diagnostic and therapeutic, to a maximum of 2-3 injections a year
- Physiotherapy (weeks 6-12) - strengthen the posterior tibial tendon and intrinsic foot muscles, stretch the gastrocnemius-soleus complex to reduce forefoot load, and retrain gait to reduce talonavicular stress
Approximately 40-50% of patients with mild to moderate TN arthritis achieve satisfactory symptom control with comprehensive conservative management. Predictors of success include flexible deformity, mild radiographic changes, and absence of significant PTTD.
Surgical Technique: Isolated TN Arthrodesis
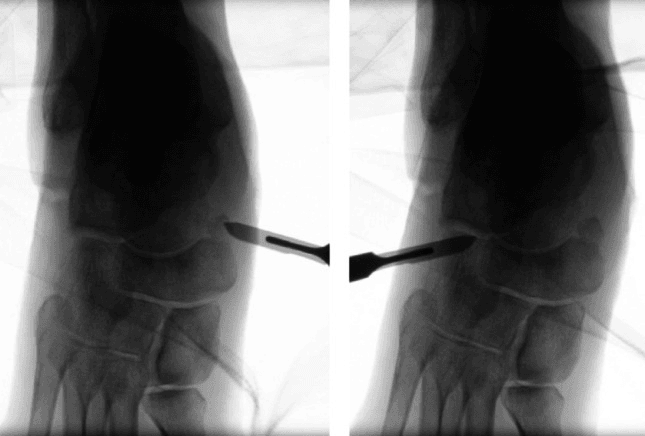
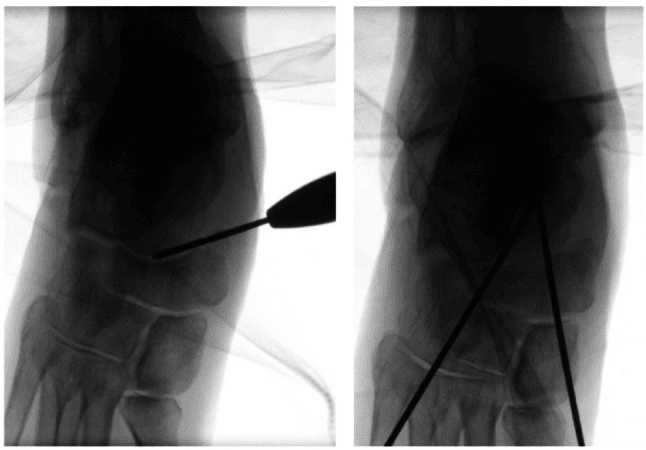
Set-up. Supine with a bump under the ipsilateral hip and a thigh tourniquet, the C-arm positioned for AP, lateral and oblique views of the foot.
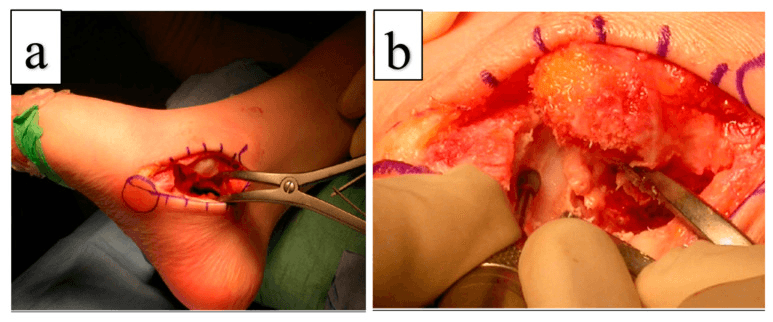
The dorsomedial approach.
- Incision - dorsomedial, curvilinear along the course of the joint and centred over it, starting 2cm proximal to the navicular tuberosity and extending 6-8cm distally
- Superficial dissection - identify the extensor hallucis longus (EHL) tendon medially and develop the interval lateral to it
- Deep dissection - incise the capsule dorsally and reflect it to expose the talar head and navicular articular surfaces completely
- Superficial peroneal nerve - dorsolateral to the incision, with branches lateral in the superficial dissection; identify and protect
- Dorsalis pedis artery - deep to the extensor tendons; avoid excessive lateral retraction
- Deep peroneal nerve - adjacent to the dorsalis pedis; preserve the vascular supply
Complications
- Incidence
- 10-15% isolated TN, 15-20% double arthrodesis
- Risk Factors
- Smoking, diabetes, osteoporosis, poor bone contact
- Management
- Revision fusion with bone graft and improved fixation
- Incidence
- 20-30% at 10 years post-fusion
- Risk Factors
- Increased motion demand, malalignment
- Management
- Activity modification, orthoses, possible future fusion
- Incidence
- 5-10% superficial infection, under 2% deep
- Risk Factors
- Diabetes, smoking, poor soft tissue handling
- Management
- Antibiotics for superficial, debridement for deep
- Incidence
- 2-5% temporary, under 1% permanent
- Risk Factors
- Superficial peroneal nerve at risk
- Management
- Usually resolves; neurolysis if persistent
- Incidence
- 5-10% malalignment
- Risk Factors
- Poor intraoperative alignment, inadequate fixation
- Management
- May require corrective osteotomy or revision
Nonunion is the most common major complication. The prevention strategies:
- Complete cartilage removal to bleeding bone
- Maximise the bone contact surface area
- Rigid fixation with crossed screws or a plate
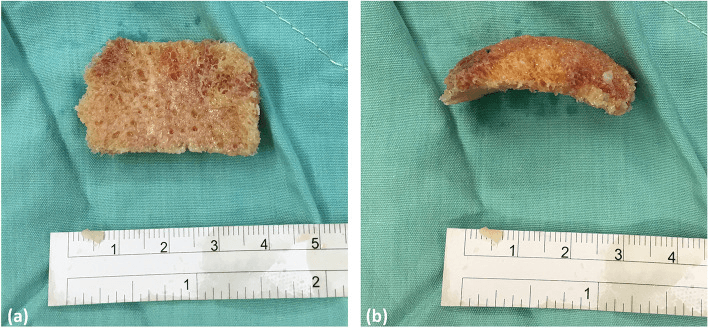
- Bone graft for defects
- Non-weight-bearing for 6-8 weeks after surgery
- Smoking cessation, which is mandatory
- Optimised diabetes control
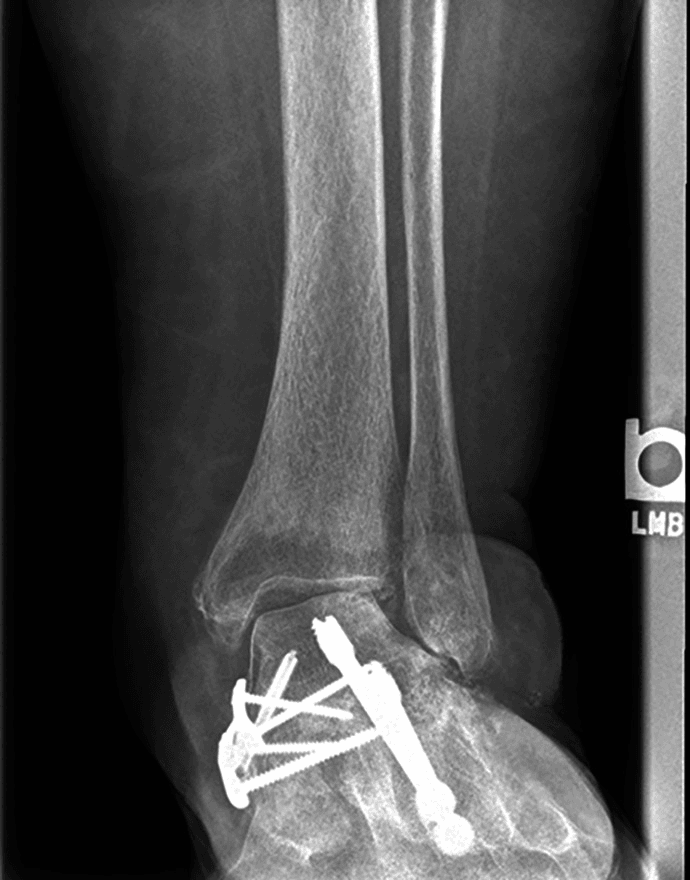
Malalignment reaches the ankle. Residual hindfoot malalignment after a talonavicular-subtalar fusion can show up as ankle valgus, which is why the ankle and the axis of correction are assessed before fixation.
Postoperative Care and Rehabilitation
After isolated fusion the foot is protected and kept off the ground until the radiographs show bridging, then loaded progressively.
Rehabilitation Timeline - Isolated TN Fusion
- Below-knee cast or CAM boot
- Non-weight-bearing with crutches
- Strict elevation for 48-72 hours to minimise swelling
- Wound check and suture removal at 2 weeks
- Continue the cast or boot, non-weight-bearing
- Radiographs at 6 weeks to assess fusion progress
- Consider DVT prophylaxis if risk factors are present
- Partial, then full, weight-bearing in the boot once radiographs show fusion (bridging trabeculae)
- Range-of-motion exercises for the adjacent joints
- Radiographs at 12 weeks to confirm fusion
- Wean from the boot to a supportive shoe with an orthosis
- Gradual return to normal activities, aiming for full weight-bearing and pain-free walking
- Final clinical and radiographic assessment at 6 months
Outcomes and Prognosis
- Isolated TN Fusion
- 85-90%
- Triple Arthrodesis
- 90-95%
- Notes
- Higher with plate fixation
- Isolated TN Fusion
- 80-85%
- Triple Arthrodesis
- 75-85%
- Notes
- Pain relief primary driver
- Isolated TN Fusion
- 70-80% return to pre-injury level
- Triple Arthrodesis
- 60-70%
- Notes
- Younger, healthier patients do better
- Isolated TN Fusion
- 20-30% at 10 years
- Triple Arthrodesis
- 30-40% at 10 years
- Notes
- Increased with malalignment
Who does well. The patient with a successful fusion free of complications, restored alignment and isolated talonavicular disease, who does not smoke, has well-controlled diabetes and holds moderate activity expectations. The outcome is worse with a nonunion that needs revision, malalignment or malunion, pre-existing adjacent-joint arthritis, smoking or uncontrolled diabetes, and high-impact demands.
Guidelines, Registries & Global Practice
- Midfoot OA is common but under-recognised; symptomatic midfoot OA affects roughly 1 in 8 adults over 50 in population imaging studies
- Isolated TN involvement is uncommon (~10-15%); the TN joint is most often affected as part of a triple-complex or planovalgus pattern
- Leading drivers globally: post-traumatic (Lisfranc / navicular injury), inflammatory (RA), and stage III progressive flatfoot
- Müller-Weiss disease clusters in middle-aged women and in regions with historic childhood under-nutrition
- Nonunion risk: 10-15%, higher in smokers and diabetics
- Adjacent joint arthritis: 20-30% at 10 years
- Nerve injury: 2-5% superficial peroneal nerve
- Infection: 5-10% superficial, under 2% deep
- Prolonged recovery: 3-6 months to fusion, 6-12 months full recovery
- Position Relevant to TN Arthritis
- Stage-based management; joint-sparing reconstruction before fusion where flexible
- Practical Implication
- Reserve TN fusion for rigid/arthritic stage III disease
- Position Relevant to TN Arthritis
- Trial of structured non-operative care and orthoses before arthrodesis
- Practical Implication
- Document conservative trial; podiatry-led pathway emphasised
- Position Relevant to TN Arthritis
- Rigid fixation, complete cartilage debridement to bleeding bone, dual-implant compression
- Practical Implication
- Technique standard underpinning high union rates
- Position Relevant to TN Arthritis
- Favour limited (joint-sparing) fusion to preserve hindfoot motion when feasible
- Practical Implication
- Isolated/double fusion over triple when CC and STJ are healthy
- Position Relevant to TN Arthritis
- No dedicated TN implant tracking — no registry-validated TN arthroplasty exists
- Practical Implication
- TN arthroplasty remains investigational; fusion is the registry-supported standard
- Weight-bearing CT and MRI for staging and PTT/spring-ligament assessment
- Cannulated compression screws, locking dorsal plates, headless compression implants
- Adjuncts: bone stimulators, biologics for high-risk fusions
- Reliance on weight-bearing plain radiographs alone; clinical staging of PTTD
- Standard cancellous screws and staples; local autograft (calcaneus) over iliac crest
- Extended cast immobilisation where boots/early ROM rehab unavailable
Key documentation requirements:
- Document comprehensive conservative trial (minimum 6 months) before surgery
- Assessment of adjacent joint status and reasoning for procedure selection
- Discussion of smoking cessation and diabetes optimization
- Detailed informed consent including nonunion and adjacent joint degeneration risks
- Post-operative non-compliance with weight-bearing restrictions can lead to failure - document instructions clearly
Controversies and Areas of Uncertainty
- Arguments For
- Modified double spares CC joint and lateral column
- Arguments Against
- Higher TN nonunion after modified double (44% vs 0% in Burrus) - but that is 9 versus 7 patients, and zero events in 7 cannot exclude a triple nonunion rate as high as 43%; Moore's 70 patients point the other way, finding CC nonunions common and asymptomatic
- Current Position
- Triple still favoured for rigid deformity; double in selected mobile lateral columns
- Arguments For
- CC fusion theoretically improves correction and stability
- Arguments Against
- Symptomatic CC nonunion is rare; sparing it shortens surgery
- Current Position
- Increasing support for sparing CC when not arthritic (Moore et al)
- Arguments For
- Preserves midfoot motion in young, high-demand patients
- Arguments Against
- No registry data, unknown implant survival, technically demanding
- Current Position
- Investigational only — fusion remains the standard of care
- Arguments For
- Plates/dual implants give rigid compression in poor bone
- Arguments Against
- Crossed screws are lower-profile with less dissection
- Current Position
- Dual-implant (screw + staple/plate) favoured over single screw
- Arguments For
- Isolated TN/tension-band preserves motion (Fornaciari et al)
- Arguments Against
- Perinavicular OA may demand TN-cuneiform extension
- Current Position
- MRI-guided extent decision; isolate when peri-navicular joints spared
Related pages: Adult Flatfoot Deformity and Rigid Flatfoot are the deformity context for most of the operations on this page, and the reason a talonavicular fusion is so often part of a larger correction rather than an isolated procedure; Posterior Tibial Tendon Dysfunction is the commonest route into this joint's failure - and note the Astion finding carded above, that talonavicular fusion cuts posterior tibial excursion to 25 percent, which is why a tendon reconstruction adds nothing once the joint is fused; Subtalar Arthritis for the neighbouring joint whose involvement converts an isolated fusion into a double, and for the diagnostic block that separates the two; Midfoot Arthritis for the naviculocuneiform and tarsometatarsal joints that inherit load and degenerate afterwards, as Saltzman documented at 44 years; Muller-Weiss Disease for the avascular navicular pattern the Fornaciari tension-band card addresses, which is a varus rather than valgus hindfoot and follows different rules; Tarsal Coalition for the ball-and-socket ankle this page names as a contraindication, and for why the 'spared' subtalar joint may not be mobile at all; Rheumatoid Foot and Ankle for the inflammatory population that supplies both the Popelka and Chiodo series and in which early fusion is preventive rather than salvage; Spring Ligament Insufficiency for the static restraint whose failure accompanies talonavicular subluxation; Navicular Fractures for the post-traumatic route to the same endpoint; and Ankle Arthritis for the joint that absorbs the motion this operation removes, and which every ankle in the Saltzman series had degenerated by the second review.
MCQ Practice Points
Q: What percentage of total hindfoot inversion and eversion motion occurs at the talonavicular joint? A: 50% - The TN joint contributes approximately 50% of hindfoot inversion/eversion through its role in the oblique axis. Loss of TN motion shifts demands to subtalar and ankle joints.
Q: What is the most common cause of talonavicular arthritis? A: Post-traumatic arthritis - Midfoot fractures and dislocations are the leading cause. Adult-acquired flatfoot (PTTD Stage 3) is the second most common etiology.
Q: What clinical sign is pathognomonic for chronic talonavicular arthritis on radiographs? A: Dorsal beaking of the navicular - Dorsal osteophyte formation on the navicular is characteristic of chronic TN arthritis and indicates longstanding degenerative changes.
Q: What is the fusion rate for isolated talonavicular arthrodesis? A: 85-90% - Isolated TN fusion has high success rates. Nonunion occurs in 10-15% and is more common in smokers, diabetics, and cases with inadequate fixation.
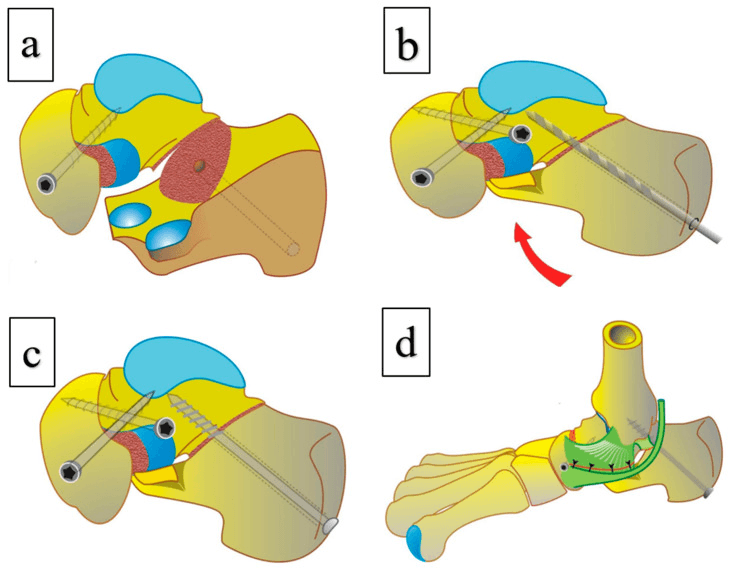
Q: What is the standard fixation for isolated TN arthrodesis? A: Two crossed 3.5mm or 4.0mm cannulated screws - One screw from dorsal navicular to plantar talus, second from plantar navicular to dorsal talus. Crossed configuration provides rotational stability.
Q: What is the incidence of adjacent joint arthritis following isolated TN fusion at 10-year follow-up? A: 20-30% - Adjacent joint degeneration (subtalar, calcaneocuboid) occurs due to increased motion demands. Risk increased with malalignment and high activity levels.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 55-year-old woman presents with progressive medial midfoot pain over 2 years. She has difficulty walking more than 500 meters and notes that her arch has collapsed. On examination, she has tenderness over the TN joint, a flatfoot deformity, and can perform a single heel rise with difficulty. Weight-bearing radiographs show moderate TN joint space narrowing with dorsal beaking but preserved subtalar joint. How would you manage this patient?”
“You have decided to proceed with isolated talonavicular arthrodesis in a 60-year-old diabetic patient with failed conservative management. Walk me through your surgical technique and key technical considerations.”
“At 6-month follow-up, your patient who underwent TN arthrodesis continues to have pain at the fusion site. Radiographs show a lucent gap at the TN joint with no bridging trabeculae. How do you manage this nonunion?”
Evidence Base and Key Trials
Isolated TN Arthrodesis in Rheumatoid Arthritis with PTTD
- Prospective series of 26 patients (20 women, 6 men), mean age 43.6 years
- Mean AOFAS hindfoot score improved from 48.2 to 88.6 at mean 4.5-year follow-up
- Only one nonunion and two superficial wound infections across the cohort
- Fusion achieved with screws, memory staples, or a combination
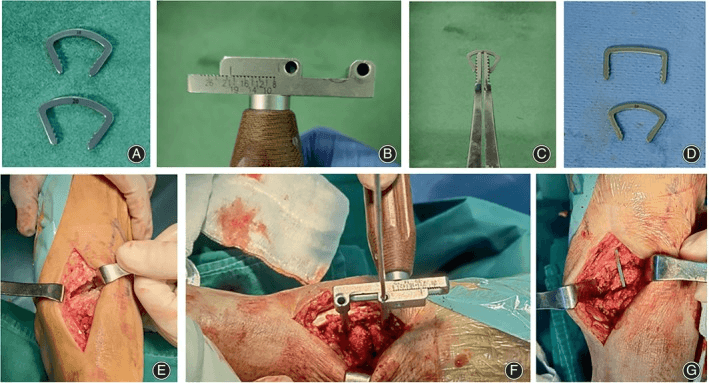
Screw-and-Staple Technique for Isolated TN Arthrodesis
- Single-surgeon series of 20 feet with inflammatory talonavicular arthritis
- Solid arthrodesis in 19 of 20 feet (95%) at an average of 11 weeks
- Combined screw plus staple fixation with indirect joint distraction
- Complications: one nonunion, one DVT, one superficial wound infection