Rare Long Bone Deficiency | Jones Classification | Knee Functionality Key | Synostosis vs Amputation
- Jones classification: Type IA-IV, a radiographic grading of how much tibia is present; knee functionality then decides treatment
- Key decision: knee functionality - non-functional knee (Type IA) = amputation, functional knee (IB/II) = synostosis + Syme
- Type IB vs IA differentiation: USS/MRI essential - IB has proximal cartilage (preserve knee), IA has no tibia (amputation)
- Proximal tibiofibular synostosis: Creates stable knee joint when proximal tibia present (IB/II)
- Treatment timing: Amputation at 6 months - 1 year, synostosis when sufficient ossification
- “Key decision is knee functionality - non-functional (Type IA) = amputation, functional (IB/II) = synostosis + Syme
- “Type IB vs IA: Must differentiate with USS/MRI - IB has cartilage (preserve), IA has nothing (amputate)
- “Proximal tibiofibular synostosis preserves knee function when proximal tibia present
- “Jones Type IA and II are most common - know these well
Overview and Epidemiology
Tibial hemimelia is a rare congenital deficiency in which part or all of the tibia is absent. It is much rarer than fibular hemimelia, one of the most challenging conditions in paediatric orthopaedics, and its treatment is decided primarily by whether the knee functions.
How rare. The incidence usually quoted is 1 in 1,000,000 live births, against 1 in 40,000 for fibular hemimelia. That figure is repeated through the literature without an identifiable population study behind it, so treat it as an order of magnitude rather than a measurement.
Who. Boys are affected slightly more often than girls (1.5:1), the right and left sides equally, and about 30% of cases are bilateral.
Cause. Tibial hemimelia results from failure of normal tibial development during embryogenesis. The exact cause is unknown but may involve:
- Vascular insult during development
- Genetic factors (rare familial cases)
- Teratogenic exposure
- Failure of mesenchymal condensation
The condition is a spectrum, from complete absence of the tibia (Jones type IA) to partial presence (types IB-IV).
Pathophysiology and Mechanisms
Why the tibia matters. The tibia normally carries roughly 85-90% of axial load. It stabilises the knee, where it articulates proximally with the femur via the medial tibial plateau and cruciates, and the ankle, where it articulates distally with the talus. Losing it produces a predictable set of problems, and where they fall depends on which part of the tibia is missing.
- Joint affected
- Knee
- Functional consequence
- Knee instability, fixed flexion contracture, no extensor pull if quadriceps/patella absent
- Joint affected
- Ankle
- Functional consequence
- Ankle instability, the fibula migrates proximally, severe varus foot
- Joint affected
- Knee + ankle
- Functional consequence
- Non-weight-bearing limb, marked shortening, the fibula lies lateral and proximally displaced
The decisive structures. Whether a stable knee can be salvaged depends on the proximal tibial anlage (bony or cartilaginous), the patella and an active quadriceps mechanism. The fibula is almost always present and frequently becomes the load-bearing strut after reconstruction.
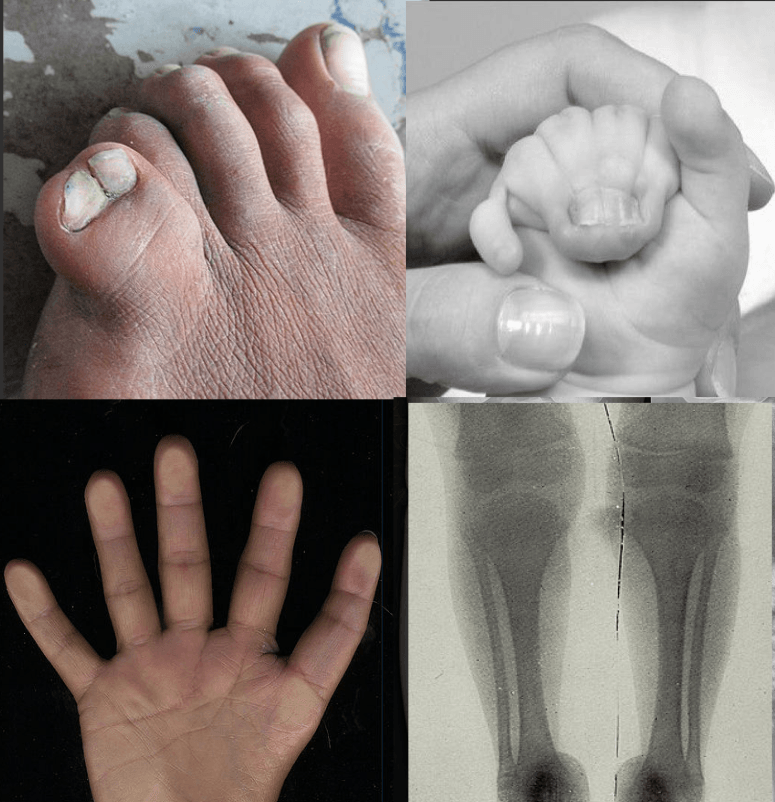
Rarely isolated. Expect a foot deformity, usually equinovarus, and a marked limb-length discrepancy. Look for ipsilateral hand and upper-limb anomalies and a bifid or duplicated femur, and remember the recognised autosomal-dominant familial form; the syndromes are set out below.
Classification Systems
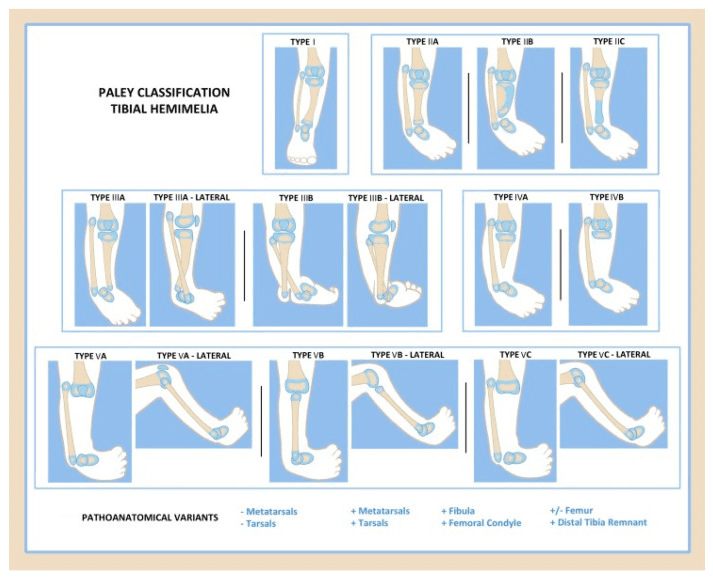
Choosing a system. None is universally adopted, so always state which one you are quoting. Jones remains the exam standard but is purely radiographic; Kalamchi is treatment-oriented; Weber adds the cartilaginous anlage and a whole-limb score; Paley is reconstruction-focused.
Jones (1978) graded the deficiency by how much tibia is present. The classification itself is radiographic; knee functionality is assessed alongside it, and together they decide treatment.
- Tibial Status
- Absent tibia
- Knee Function
- Non-functional
- Treatment
- Amputation
- Tibial Status
- Proximal cartilage only
- Knee Function
- Functional (preserve)
- Treatment
- Synostosis + Syme
- Tibial Status
- Ossified proximal tibia
- Knee Function
- Functional (preserve)
- Treatment
- Synostosis + Syme
- Tibial Status
- Ossified distal only
- Knee Function
- Variable
- Treatment
- Syme or Chopart
- Tibial Status
- Short tibia, diastasis
- Knee Function
- Variable
- Treatment
- Syme amputation
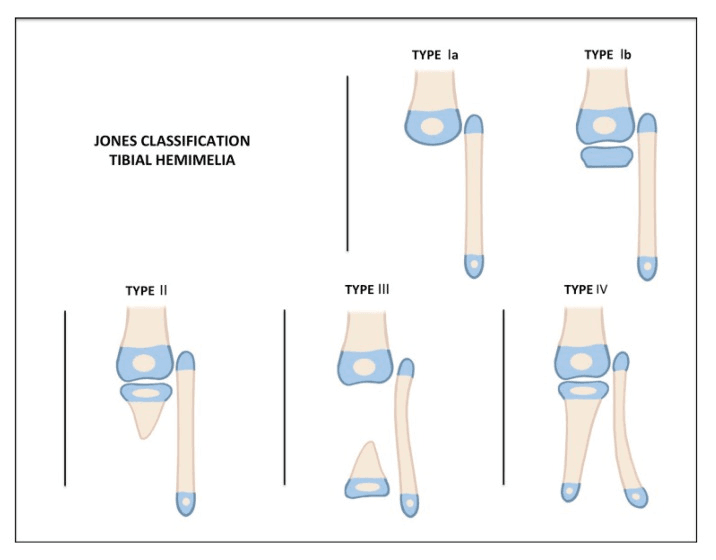
Type IA is the most severe form: complete absence of the tibia and a non-functional knee. Type IB has a proximal tibia present only as cartilage, not ossified on radiographs, and must be told apart from IA with ultrasound or MRI. Type II is the same pattern with the proximal tibia ossified.
Type III, an ossified distal tibia with the proximal tibia absent, is the least common; assume that proximal ossification may eventually occur. Type IV is a short tibia with distal tibiofibular diastasis (separation).
Types IA and II are the most common, although in Fernandez-Palazzi's 22 limbs type II (3) was outnumbered by types Ib and IV (4 each), with type Ia leading at 9.
Clinical Assessment
History. A shortened lower limb is noted at birth, sometimes with a foot deformity. Ask about:
- Family history (rare, but may be present)
- Difficulty with weight-bearing or walking
- Previous treatment, in an established case
Inspection and palpation. The limb is short and foot deformity is common. The tibia may be absent or hypoplastic and may not be palpable, while the fibula is usually present. Check whether both legs are involved, and look at the other limbs for associated anomalies; associations in other systems are rare.
The knee. This is the critical part of the examination, because knee functionality decides treatment. Assess quadriceps function, stability and passive motion, and look for contractures.
Ankle and foot. The ankle may have limited motion or be unstable. Assess the structure and deformities of the foot, and whether it could be preserved.
Leg length.
- True: ASIS to medial malleolus
- Apparent: umbilicus to medial malleolus
Investigations
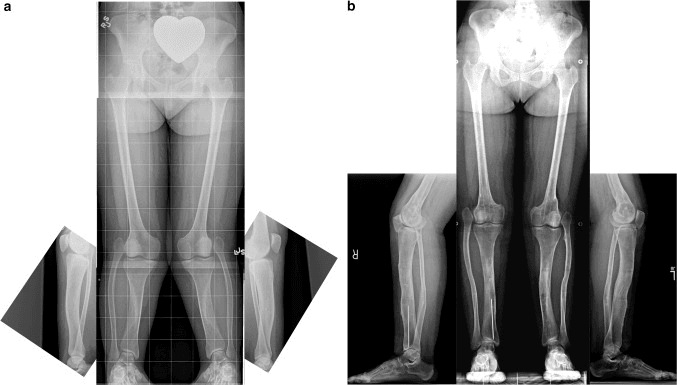
Radiographs. Plain films show what has ossified:
- AP and lateral lower limb: whether the tibia is present, the proximal and distal tibia where present, the fibula, the knee and ankle joints, and the limb-length discrepancy
- Full-length standing radiographs: accurate LLD measurement and alignment, with the knee and ankle
- Foot radiographs: foot structure and deformities
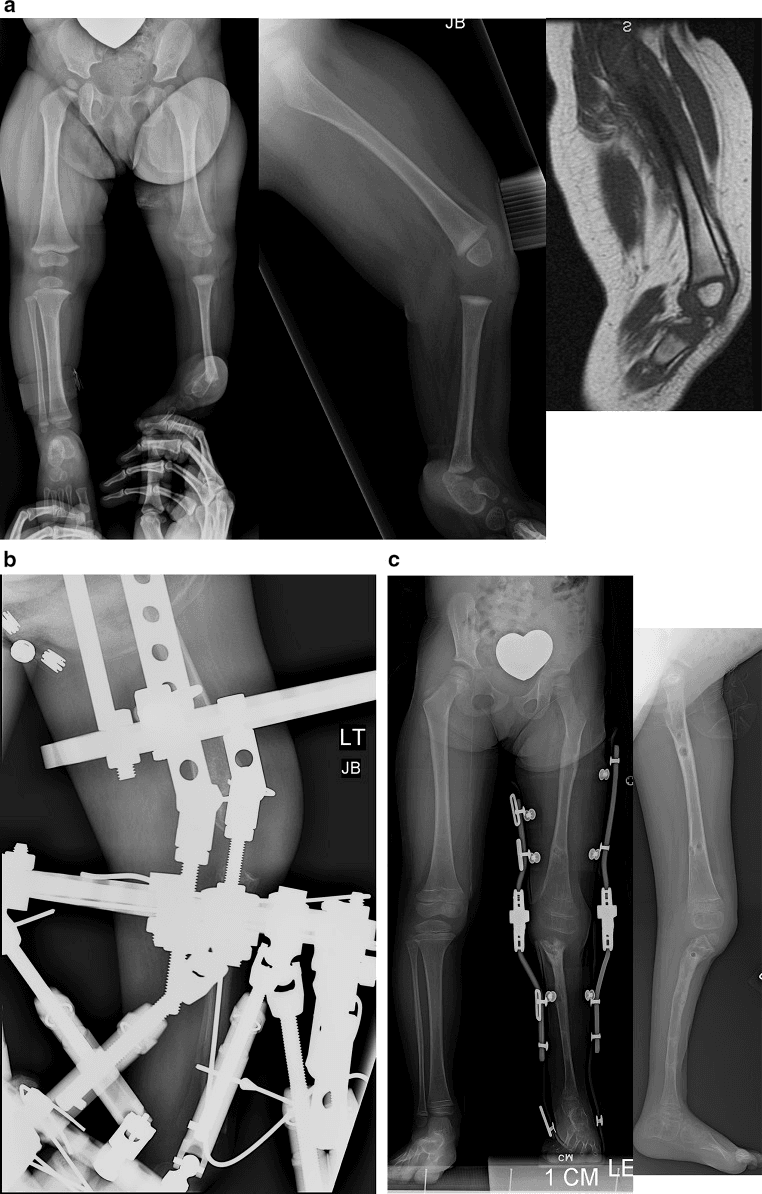
Ultrasound and MRI. Cartilage is not visible on radiographs, so a film that shows no tibia cannot separate type IA from IB, and ultrasound is essential. Proximal tibial cartilage means type IB and a knee to preserve; no cartilage means type IA and amputation. MRI assesses the proximal tibia and its cartilage in detail when ultrasound is inconclusive.
Ultrasound and MRI are decisive, yet access to them varies worldwide. Mislabelling a salvageable knee as type IA and amputating is the central pitfall.
Differential Diagnosis
The short, varus, externally deformed leg of tibial hemimelia overlaps clinically with several other congenital long-bone deficiencies.
- Key bone affected
- Tibia deficient, fibula intact
- Foot/deformity
- Equinovarus, foot supinated
- Distinguishing feature
- Varus foot, prominent fibular head laterally, extensor mechanism may be absent
- Key bone affected
- Fibula deficient, tibia present
- Foot/deformity
- Equinovalgus, lateral rays absent
- Distinguishing feature
- Valgus foot, anteromedial tibial bow, ~25x commoner than tibial
- Key bone affected
- Proximal femur
- Foot/deformity
- Foot at level of opposite knee
- Distinguishing feature
- Bulky thigh held in flexion/abduction/ER, hip instability
- Key bone affected
- Tibia present but dysplastic
- Foot/deformity
- Anterolateral tibial bow
- Distinguishing feature
- Anterolateral (not posteromedial) bow, NF1 association, fracture/nonunion
- Key bone affected
- Tibia absent + bifid femur
- Foot/deformity
- Hand ectrodactyly
- Distinguishing feature
- Distal femoral bifurcation with ipsilateral complete tibial hemimelia
Associated Syndromes: Gollop-Wolfgang Complex and Familial Forms
The syndromic associations cluster at the severe, proximally deficient end of the spectrum. Recognising them changes both the counselling and the reconstructive plan.
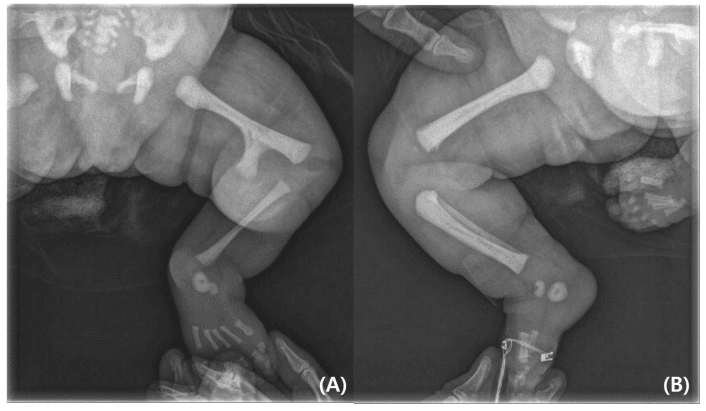
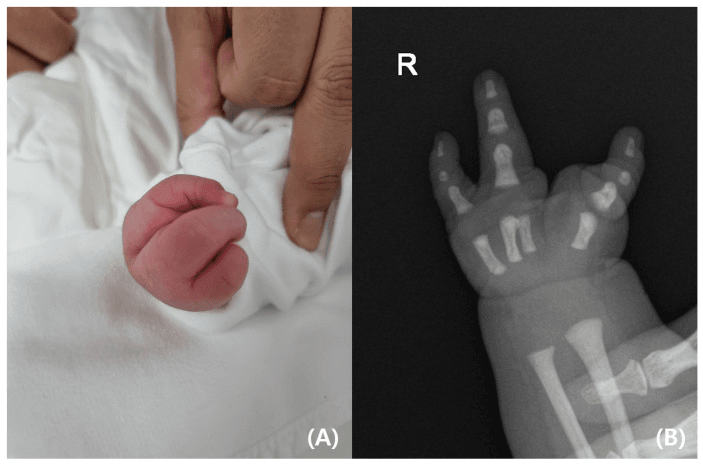
Gollop-Wolfgang complex. The triad is distal femoral bifurcation (a forked, duplicated distal femur), ipsilateral complete tibial hemimelia (aplasia) and hand ectrodactyly (split hand, or "lobster claw"). The femur-tibia overlap is sometimes labelled the tibial agenesis-ectrodactyly syndrome.
What it means for treatment. The bifurcated femur carries an accessory bony spike that typically must be resected to bring the limb into line before any reconstruction or prosthetic fitting. The complex signals that the proximal tibia is usually absent and the knee usually non-salvageable, so management gravitates toward knee disarticulation or complex staged reconstruction rather than a simple synostosis.
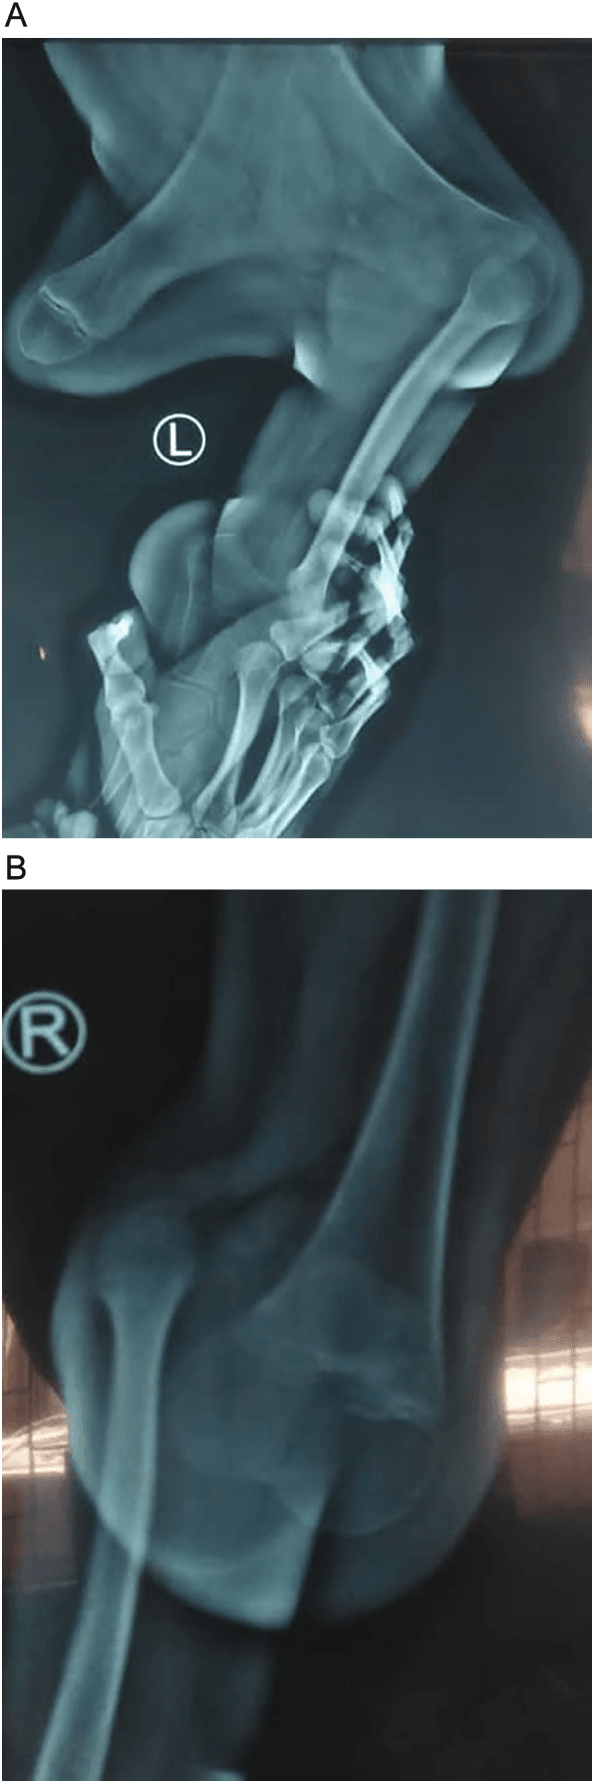
Familial tibial hemimelia. Pedigrees with affected siblings and vertical transmission are documented, and Fernandez-Palazzi recorded familial cases. An autosomal-dominant pattern with variable expressivity and incomplete penetrance is recognised, and familial cases are more often bilateral and syndromic. A careful family history, and clinical-genetics referral where available, is therefore part of the workup.
Other associations. Survey for preaxial polydactyly and triphalangeal thumb, other limb-reduction defects and occasional visceral anomalies. A deliberate head-to-toe anomaly survey is mandatory before committing to any irreversible surgical decision.
Management Algorithm
Treatment is based on knee functionality, not just on whether a tibia is present.
Goals of treatment, whatever the classification:
- A stable, extensor-competent knee, if salvageable
- A plantigrade, weight-bearing foot or a good end-bearing stump
- Leg lengths equalised by maturity
- Acceptable alignment and an efficient, comfortable gait
The decision rests on four factors:
- Knee function: a non-functional knee (type IA) means amputation; a functional knee (IB/II) means synostosis and Syme
- Tibial presence, assessed with radiographs, ultrasound and MRI
- Type IB versus IA, which only ultrasound or MRI can settle
- Family preference, after counselling about both options
Type IA: amputation. When the tibia is completely absent, the knee non-functional and ultrasound or MRI confirms no proximal tibial cartilage, the treatment is knee disarticulation or above-knee amputation, followed by prosthetic fitting.
Types IB and II: synostosis, then Syme. When the proximal tibia is present, as cartilage in IB (confirmed with ultrasound or MRI) or ossified in II, and the knee functions, a proximal tibiofibular synostosis creates a bony bridge between the proximal tibia and fibula. It provides a stable knee and the fibula becomes the weight-bearing bone. A Syme amputation follows distally once the synostosis has healed, preserving the knee and allowing prosthetic fitting.
Types III and IV. Type III is treated by Syme or Chopart amputation and type IV by Syme amputation.
Timing. Amputation at 6 months to 1 year; synostosis when there is sufficient ossification, usually at 1-2 years. Early treatment allows prosthetic fitting and better developmental outcomes.
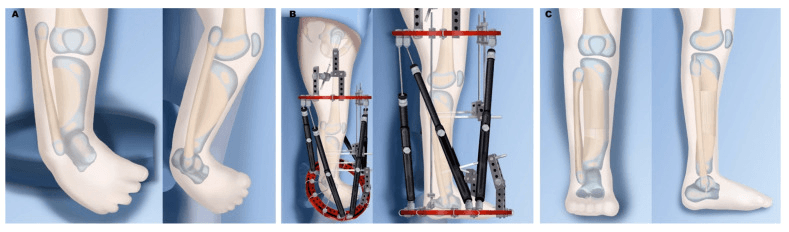
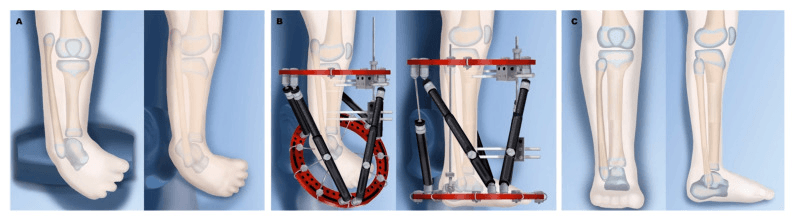
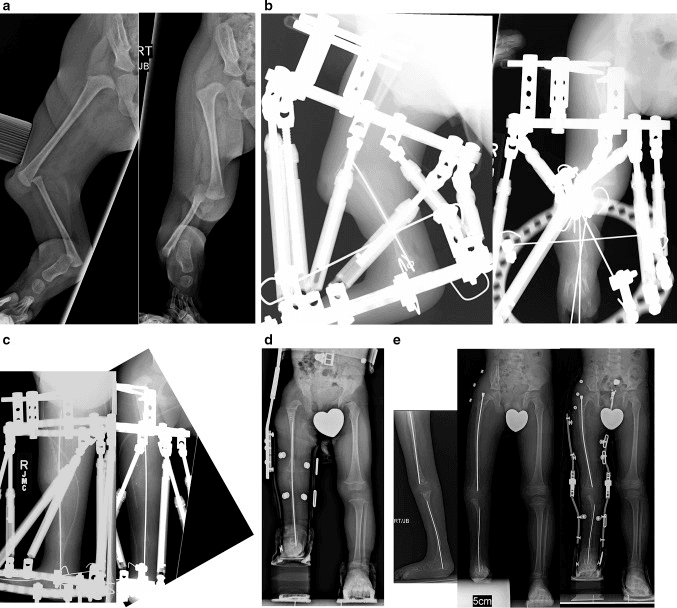
Reconstruction. Paley's approach favours joint-preserving reconstruction when a knee joint or proximal tibia, patella and quadriceps mechanism are present. Where it stands against amputation is set out under Controversies.
Surgical Techniques
For types IB and II, where the proximal tibia is present and the knee functions.
- Approach: lateral, to the proximal tibia and fibula
- Preparation: expose the proximal tibia and fibula, decorticate the contact surfaces and create bony contact
- Synostosis: create the bony bridge between tibia and fibula, with bone graft if needed, and internal fixation (screws or plate)
- Position: ensure proper alignment
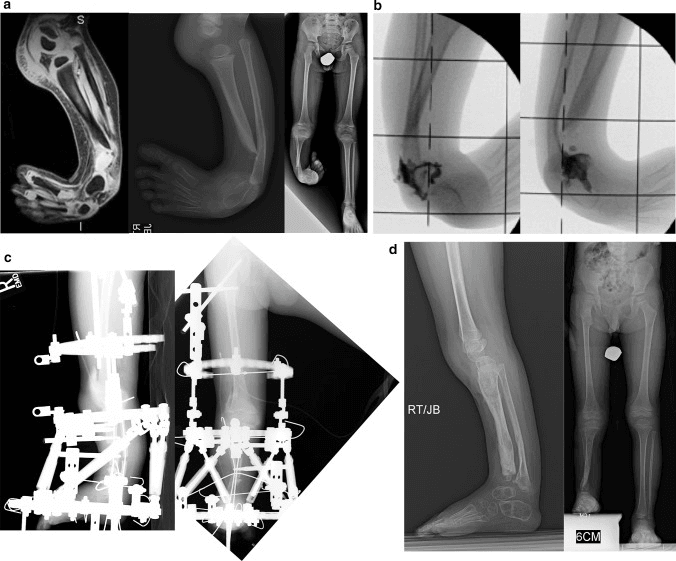
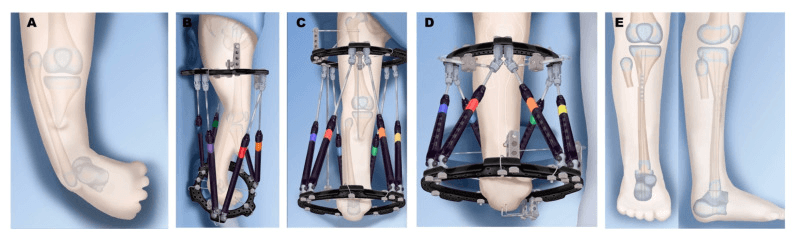
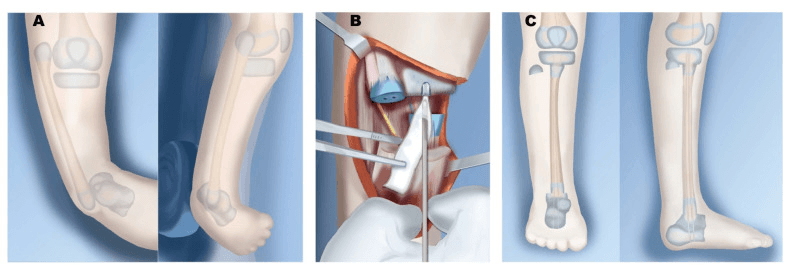
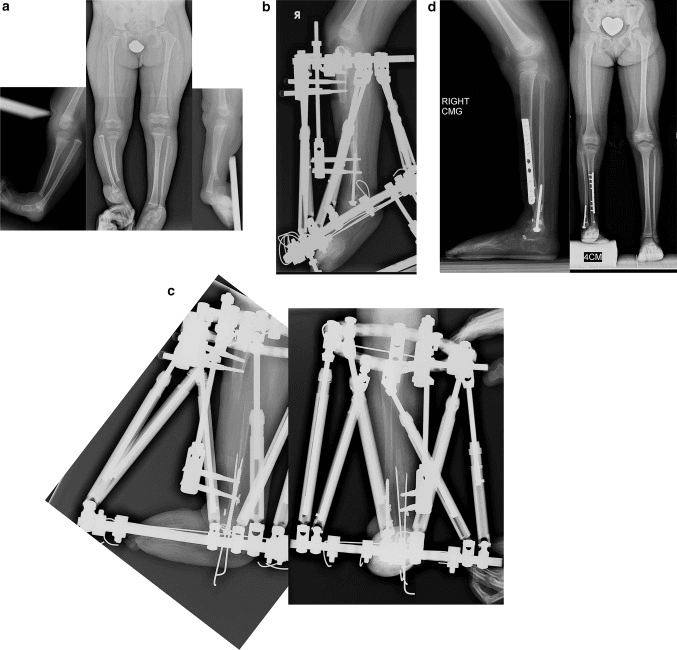
Staged reconstruction. The sequences below show the Paley reconstructive alternative to amputation, done in stages with external fixation.
Fibular Centralisation (The Brown Procedure)
Concept. Brown (1965) transposed the fibula medially and centralised it beneath the femoral condyles, so that it articulates with the distal femur as a weight-bearing strut: "fibula pro tibia", the fibula in place of the tibia. The proximal fibula is aligned under the intercondylar notch and stabilised, the soft tissues (including the hamstrings and knee flexors) are balanced, and the foot is managed separately, usually by Syme amputation or ankle reconstruction.
Why it disappoints in complete absence. True Jones type IA generally means an absent or deficient extensor mechanism, quadriceps and patella. A knee with no active extension develops persistent or recurrent flexion contracture and posterior instability or subluxation of the centralised fibula, and a large proportion of these limbs ultimately need knee disarticulation anyway. That is why the historic Brown procedure for complete absence gave poor knee stability.
Who might suit it. The rare good candidate has active knee extension, a stable proximal fibula and minimal fixed flexion. Such a limb, by definition, tends to have a proximal tibial anlage (Jones IB/II) and is usually better served by tibiofibular synostosis. For genuine complete absence with no extensor mechanism, most surgeons now favour early knee disarticulation.
Its modern place is narrow. It has largely been superseded by anlage-preserving synostosis (IB/II), and by Paley-type staged reconstruction (patelloplasty, distraction of contractures, lengthening) where a proximal tibia, patella and quadriceps exist. In a viva, state this nuance explicitly rather than offering centralisation as a routine option for the absent tibia.
Complications
After synostosis. Early problems are wound healing and, rarely, infection or neurovascular injury. Later, the synostosis may fail to unite and need revision, and there may be malalignment, hardware problems, or knee instability if the synostosis fails.
After amputation. Wound-healing problems occur in 5-10% and infection is rare. After a Syme, the heel pad may migrate if it is not properly fixed; heel-pad migration and bony overgrowth may each need revision. Prosthetic fitting problems are rare.
Prevention. Careful patient selection, meticulous surgical technique, proper imaging (ultrasound or MRI to separate IB from IA) and realistic expectations.
Postoperative Care
After synostosis. Pain management, wound care and a cast for 6-8 weeks, monitoring for union. Once united, protected weight-bearing and physiotherapy prepare the child for the Syme amputation, after which come prosthetic fitting, gait training and return to activities.
After amputation (type IA). Pain management, wound care and a cast for 2-3 weeks. Once healed, prosthetic fitting (6-8 weeks), gait training and return to activities.
Long term. The prosthesis needs adjusting as the child grows, with regular follow-up and monitoring for complications.
Outcomes and Prognosis
Type IA. Amputation gives good function with a prosthesis from a single operation, with minimal restrictions, and early treatment allows development.
Types IB and II. Synostosis and Syme preserve the knee and give good prosthetic function, at the price of a two-stage procedure. The result is better than a through-knee amputation when the knee is genuinely functional, but no study has compared the two in comparable limbs: in the largest series the amputated limbs were the worst ones, so the apparent advantage of reconstruction is confounded by indication.
Types III and IV. Outcomes are variable and depend on the specific anatomy.
Overall. Both groups function well, prosthetic function is good and most children function independently; psychosocial support is important. Success depends on appropriate patient selection, proper imaging to separate IB from IA, meticulous technique and early treatment.
Guidelines, Registries & Global Practice
Global epidemiology
- Incidence approximately 1 per 1,000,000 live births - one of the rarest long-bone deficiencies, roughly 25-30x less common than fibular hemimelia.
- Slight male predominance; bilateral in around 30%; right and left affected equally.
- Rarely isolated - associated limb (hand ectrodactyly, bifid femur/Gollop-Wolfgang), and occasional syndromic or autosomal-dominant familial forms; a deliberate anomaly survey is mandatory.
Practice positions across regions (no single society publishes a dedicated tibial hemimelia guideline given rarity; positions are derived from major paediatric limb-deficiency literature):
- Position on first-line treatment
- Early amputation - knee disarticulation for type 1a, Syme for distal types
- Emphasis
- Reliable single-stage prosthetic rehabilitation
- Position on first-line treatment
- Stage with US/MRI first; preserve the cartilaginous anlage where present
- Emphasis
- Pathoanatomy-driven, anlage-preserving
- Position on first-line treatment
- Joint-preserving reconstruction when proximal tibia, patella and quadriceps present
- Emphasis
- Brown centralization, patelloplasty, Ilizarov lengthening
- Position on first-line treatment
- Early amputation and locally fabricated prosthesis
- Emphasis
- Cost, durability, single definitive procedure
Registry note: congenital limb-deficiency surveillance networks (e.g. EUROCAT in Europe, ICBDSR internationally) capture birth-prevalence data, but no arthroplasty-style implant registry exists for this reconstructive paediatric condition - outcome evidence rests on single-centre case series (level IV), not registry or randomised data.
High- vs limited-resource practice variation
- High-resource: MRI/ultrasound staging, multidisciplinary teams (paediatric orthopaedics, radiology, prosthetics, physiotherapy, psychology, genetics), and the option of multi-stage reconstruction with growth-friendly lengthening.
- Limited-resource: imaging access may be confined to plain radiographs, biasing toward early amputation; prosthetic durability, follow-up logistics and cost favour a single definitive procedure.
Counselling and governance (universal): informed consent for an irreversible decision (amputation vs reconstruction), documented knee/quadriceps assessment, US/MRI confirmation of the anlage before committing, balanced discussion of both pathways with realistic outcome expectations, and structured follow-up to skeletal maturity for limb-length management and prosthetic adjustment.
Related pages: Congenital Lower Limb Deficiency Overview is the parent page and places tibial hemimelia among the longitudinal deficiencies; Fibular Hemimelia is the far commoner counterpart and the essential contrast — fibular hemimelia spares the knee and threatens the foot and ankle, tibial hemimelia threatens the knee itself, which is why the presence of a quadriceps mechanism and a proximal anlage dominates every decision on this page; Proximal Femoral Focal Deficiency frequently coexists and must be assessed before any plan is made, because the femoral segment determines whether the reconstructed limb can ever be length-matched; Congenital Knee Dislocation and Clubfoot are the associated deformities most often present at birth in the same limb; Polydactyly matters specifically here because preaxial polydactyly with tibial deficiency is the Gollop-Wolfgang phenotype discussed above and should trigger a family history and a genetics referral; Limb Lengthening Principles, Distraction Osteogenesis and Ilizarov External Fixation carry the reconstruction machinery this page prescribes — and the healing index and complication burden that make a multi-stage reconstruction a decade-long commitment rather than an operation; Guided Growth for Angular Deformity Correction for the residual angular problems that follow; and Prosthetic Limb Components is the page to read before counselling a family, because the honest comparison is not reconstruction against nothing but reconstruction against a well-fitted prosthesis, and no study on this page has made that comparison in comparable limbs.
Controversies and Areas of Uncertainty
Amputation versus reconstruction. The historic default, early amputation (knee disarticulation for type 1a, Syme for the distal types), is reliable and single-stage and gives excellent prosthetic function. Modern reconstruction (fibular centralisation, patelloplasty, lengthening) can preserve a biological knee and foot, and Shahcheraghi reported better quality-of-life scores in reconstructed limbs, at the cost of multiple operations and higher complication rates. That comparison is the confounded one described under Outcomes; there is no level 1 evidence, and the decision is individualised.
MCQ Practice Points
Q: What is the key difference between Jones Type IA and Type IB tibial hemimelia? A: Type IA has complete absence of tibia (no cartilage or bone) with non-functional knee, requiring amputation. Type IB has proximal tibial cartilage present (not visible on X-ray, requires USS/MRI) with functional knee, allowing synostosis + Syme amputation. The differentiation is critical and requires imaging beyond X-ray.
Q: What is the most important factor in determining treatment for tibial hemimelia? A: Knee functionality - non-functional knee (Type IA) = amputation, functional knee (Type IB/II) = proximal tibiofibular synostosis + Syme amputation. The presence of proximal tibia (even as cartilage) allows knee preservation, while complete absence requires amputation.
Q: Why is USS or MRI essential for Type IB tibial hemimelia? A: Proximal tibial cartilage is not visible on X-ray - Type IB has cartilage present that allows knee preservation, but this cannot be seen on radiographs. USS/MRI is essential to differentiate Type IB (cartilage present, preserve knee) from Type IA (no tibia, amputation). Clinical exam and X-ray alone are insufficient.
Q: What is the purpose of proximal tibiofibular synostosis in tibial hemimelia? A: Creates stable knee joint when proximal tibia present (Type IB/II) - the synostosis fuses the proximal tibia to the fibula, allowing the fibula to become the weight-bearing bone and preserving knee function. This is followed by Syme amputation distally to create an end weight-bearing stump.
Q: What is the recommended timing for amputation in Type IA tibial hemimelia? A: 6 months to 1 year of age - early amputation allows prosthetic fitting and normal development. For Type IB/II synostosis, the procedure is performed at 1-2 years when sufficient ossification is present. Early treatment improves outcomes.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 3-month-old infant presents with tibial hemimelia. On examination, the tibia appears absent on X-ray, but there is some knee function. How would you assess and manage this child?”
“A 2-year-old child with confirmed Type IB tibial hemimelia (proximal tibial cartilage present, functional knee) is ready for synostosis. Describe the procedure and postoperative management.”
“A 6-month-old infant with Type IA tibial hemimelia (confirmed absent tibia, non-functional knee) is ready for treatment. The parents are asking about treatment options. How would you counsel them and what procedure would you recommend?”
Key Facts
- Incidence: 1 in 1,000,000 (very rare, much rarer than fibular hemimelia)
- Jones classification: Type IA-IV based on radiographic tibial presence; knee function decides treatment
- Key decision: Knee functionality - non-functional (IA) = amputation, functional (IB/II) = synostosis
- Type IA and II are most common
Jones Classification
- Type IA: Absent tibia, non-functional knee = Amputation
- Type IB: Proximal cartilage only (differentiate with USS/MRI) = Synostosis + Syme
- Type II: Ossified proximal tibia = Synostosis + Syme (like IB)
- Type III: Ossified distal only (rare) = Syme or Chopart
- Type IV: Short tibia, distal diastasis = Syme amputation
Treatment Decision
- Type IA: Knee disarticulation or above-knee amputation (6m-1y)
- Type IB/II: Proximal tibiofibular synostosis (1-2y) + Syme amputation
- Key: Knee functionality determines treatment
- USS/MRI essential for IB vs IA differentiation (cartilage not visible on X-ray)
Surgical Pearls
- Synostosis: Decorticate surfaces, create bony bridge, internal fixation
- Preserves knee function when proximal tibia present
- Fibula becomes weight-bearing bone after synostosis
- Syme amputation performed distally after synostosis heals
Complications
- Synostosis: Nonunion (may need revision), malalignment, knee instability
- Amputation: Wound healing (5-10%), heel pad migration (Syme)
- Prevention: Careful patient selection, proper imaging, meticulous technique
- Realistic expectations essential
Evidence Base
Jones Classification of Tibial Aplasia/Dysplasia
- Original radiographic classification of congenital tibial deficiency with intact fibula
- Type 1a: tibia not visualised, hypoplastic distal femoral epiphysis; Type 1b: tibia not seen but proximal anlage present
- Type 2: proximal tibia ossified, distal tibia absent; Type 3: distal tibia present, proximal absent (rare); Type 4: distal tibiofibular diastasis
- Quadriceps/knee function and proximal tibial presence drive whether the knee can be salvaged
Kalamchi Classification of Congenital Tibial Deficiency
- Late results of 24 legs in 21 children with a proposed treatment-oriented classification
- Type I: total tibial absence; Type II: distal absence; Type III: distal deficiency with tibiofibular diastasis
- Early radiographic appearance, quadriceps function and severity of knee flexion contracture guided operation selection
- Classification correlated with both treatment recommendation and final functional result
Weber Classification and Score: Role of the Cartilaginous Anlage
- Seven-type classification with a five-class score evaluated on 95 affected limbs
- Explicitly incorporates the cartilaginous tibial anlage, under-recognised in earlier systems
- Requires sonography and MRI for precise pre-operative pathoanatomy beyond plain radiographs
- Type VII (61%) and type III (15%) were the most frequent patterns in the series
Paley Classification and Reconstructive Options
- New classification linking pathoanatomy to reconstruction rather than defaulting to amputation
- Describes Brown fibular centralization, Weber patelloplasty and staged distraction techniques
- Improved understanding of genetics, aetiology and pathoanatomy underpins joint-preserving surgery
- Presence of a knee joint, patella and quadriceps mechanism favours reconstruction
Functional Outcomes of Reconstruction with Foot Preservation
- 36 patients (48 tibial-deficient limbs), mean follow-up 9 years - largest single-surgeon series
- Primary amputation in 8 patients (10 limbs); limb preservation in 38 legs (28 patients)
- Tibiofibular synostosis, ankle centralization and Ilizarov lengthening were the commonest procedures
- Reconstructed group PedsQL 68, higher than the amputation group; nonunion of synostosis (2) and knee stiffness (6) were the main complications
Epidemiology and Type Distribution
- 22 limbs in 18 patients from Caracas, 1970-1987; the paper QUOTES the conventional incidence of ~1 per million live births rather than measuring it
- Frequently associated with other anomalies of the same limb or elsewhere; familial cases recorded
- Jones type distribution: 9 type Ia, 4 type Ib, 3 type II, 2 type III, 4 type IV
- Earlier amputation gave faster rehabilitation; the child accepts it as a congenital amputation
Deformity Reconstruction Surgery for Tibial Hemimelia
- Comprehensive contemporary review of pathology, classification and surgical options
- Type-specific reconstruction: staged distraction of knee/ankle contractures, Weber patelloplasty, fibular centralization, arthrodesis
- Amputation remains simpler and reliable, but reconstruction increasingly delivers good function
- Factors favouring reconstruction: present knee joint/proximal tibia and an intact patella with quadriceps mechanism