Toddler's Fracture | Cozen's Phenomenon | Tibial Spine
- Toddler's fracture: spiral tibia in 9 months to 3 years, limping child, X-ray often normal initially
- Cozen's phenomenon: progressive valgus after proximal tibial metaphyseal fracture, largely self-corrects
- Tibial spine fracture = paediatric ACL injury - treat based on displacement
- Floating knee in children: ipsilateral femur and tibia fractures - high energy
- Intact fibula may cause valgus deformity in tibial shaft fractures
- “Negative X-ray does not rule out toddler's fracture - treat clinically if suspected
- “Cozen's valgus peaks at 12-18 months then largely corrects - observe, but do not promise symmetry
- “Tibial spine Type III = surgical (ORIF or arthroscopic reduction)
- “Age over 10 years: consider flexible IM nails for tibial shaft fractures
Overview and Epidemiology
The tibia is the second most common paediatric long-bone fracture, accounting for about 15% of all paediatric fractures. Incidence peaks in toddlers and in adolescents. Boys are affected more than girls, about 2:1, and left and right equally.
Mechanism. Each pattern has its own:
- Toddler's fracture - a low-energy twist or fall
- Proximal metaphyseal fracture - direct impact
- Tibial spine fracture - hyperextension, classically off a bicycle
- Shaft fracture - a direct blow or torsion
- Floating knee - high energy (for example a motor vehicle accident)
Anatomy and Biomechanics
The physes. The proximal tibial physis contributes 57% of tibial length and the distal physis 43%, so injuries to the proximal physis have greater potential for growth disturbance.
Where they lie. The proximal physis lies 1-2 cm distal to the joint line and is protected by the tibial tubercle apophysis. The distal physis closes asymmetrically: central, then medial, then lateral.
The tubercle apophysis is a secondary ossification centre, vulnerable during adolescence (Osgood-Schlatter).
Blood supply. The nutrient artery enters the posterior cortex at the junction of the proximal and middle thirds and supplies the inner two-thirds of the cortex. Periosteal vessels supply the outer third, and they are more robust in children, so healing is better.
The popliteal trifurcation. The proximal tibia is a vulnerable area at the trifurcation: watch for vascular injury with displaced proximal fractures.
Soft tissues. The anteromedial tibia is subcutaneous, with minimal soft-tissue cover, which brings a risk of open fractures and wound complications. The leg has four compartments, and children can develop compartment syndrome.
The periosteum is thick in children; it helps maintain reduction and contributes to rapid healing.
Classification Systems
Toddler's fracture. CAST, the Childhood Accidental Spiral Tibial fracture: a non-displaced spiral or oblique fracture in a child of walking age, 9 months to 3 years, after a low-energy twist or fall. The distal tibial shaft is the most common site, and the fracture is often not visible on the initial radiograph.
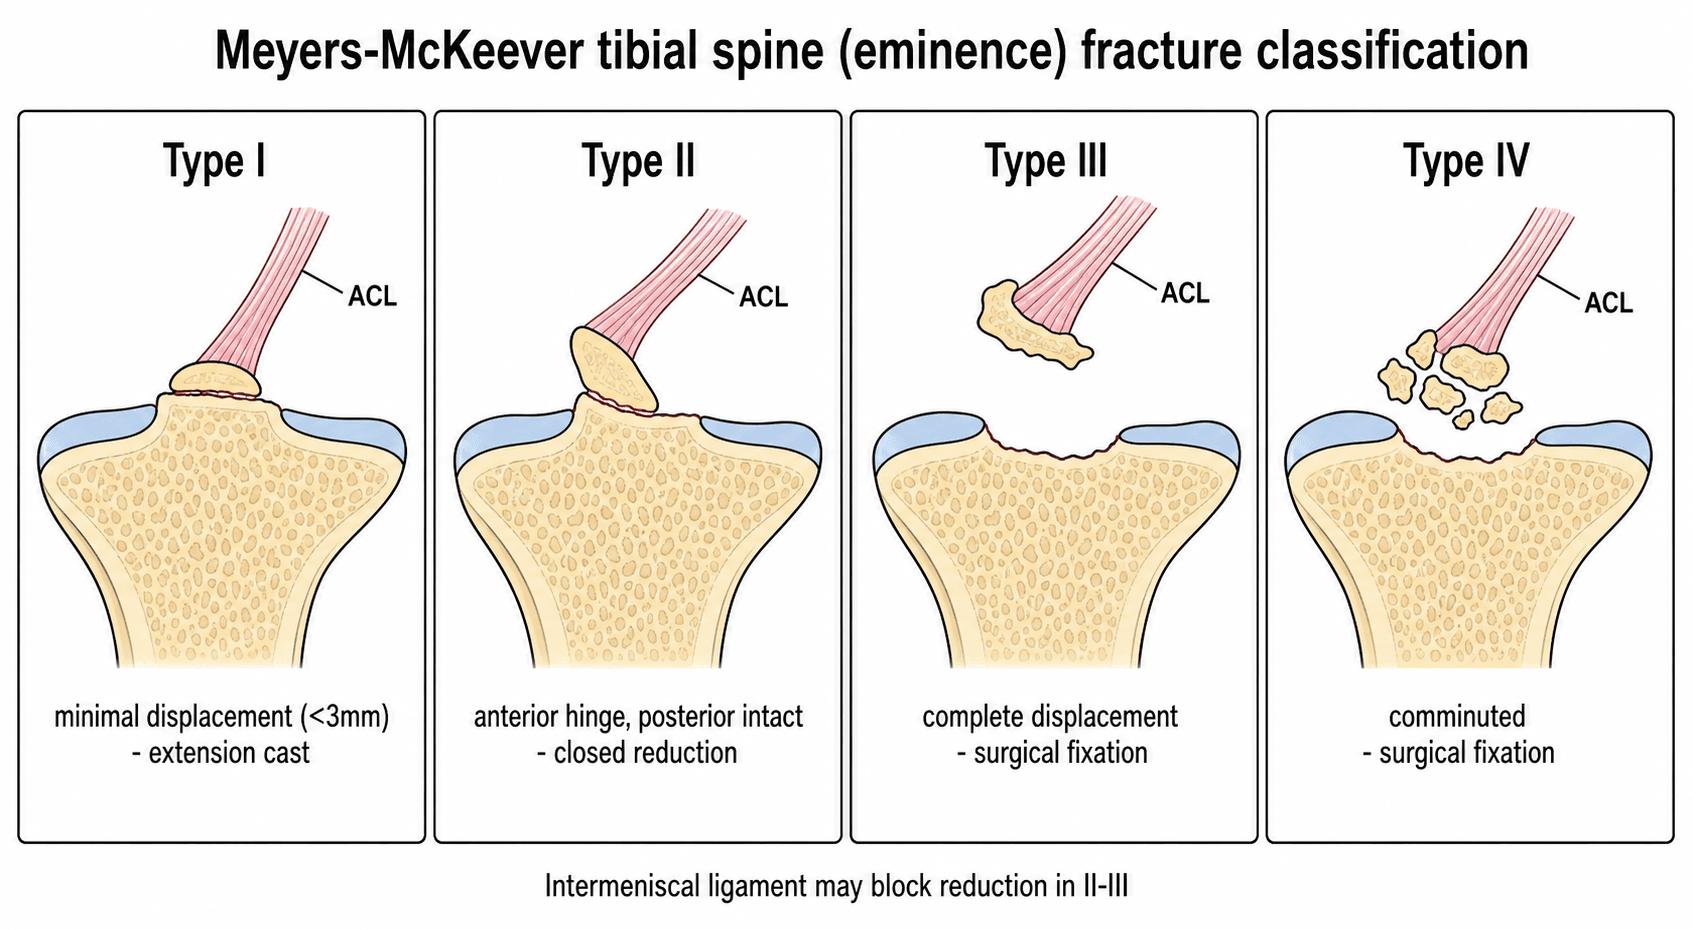
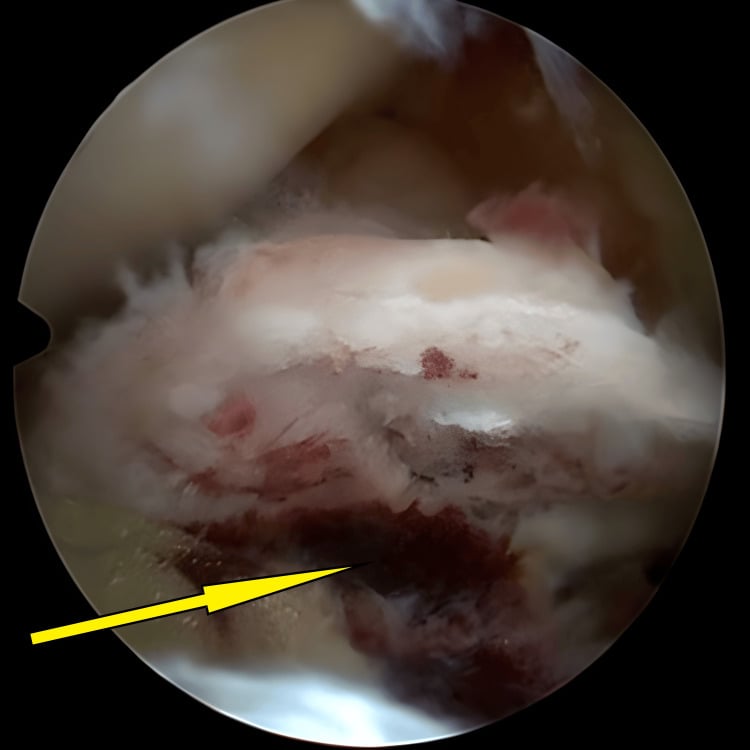
Tibial spine fractures, the paediatric ACL equivalent, are classified by Meyers and McKeever. The intermeniscal (transverse) ligament can interpose and block reduction in Types II and III.
- Description
- Minimal displacement
- Displacement
- Less than 3mm
- Description
- Anterior elevation
- Displacement
- Posterior hinge intact
- Description
- Complete displacement
- Displacement
- No contact
- Description
- Comminuted fragment
- Displacement
- Multiple fragments
Tibial shaft fractures are described by pattern (spiral, oblique, transverse, comminuted), by location (proximal, middle or distal third) and by stability. An isolated tibial fracture with an intact fibula is stable; a fracture of both bones, or one with significant displacement, is unstable. The intact fibula has its own cost: it may cause valgus malunion.
Clinical Assessment
The toddler. The child limps or will not walk, refuses to bear weight, and has point tenderness over the tibia after a minor fall or twist. Swelling is often absent at first and the radiographs may be normal, so the diagnosis is clinical.
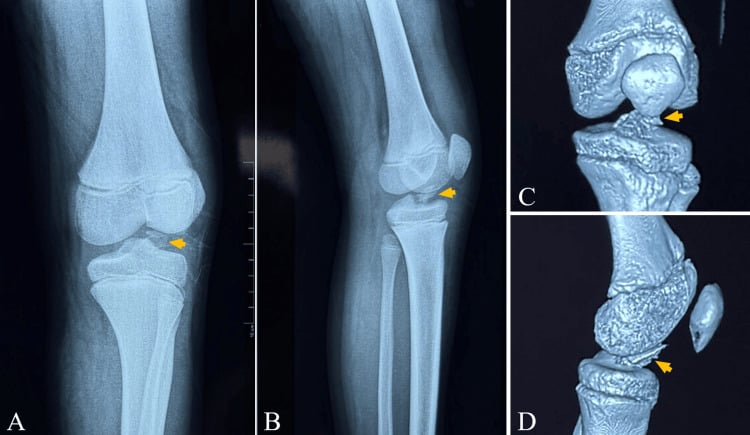
The tibial spine. Acute knee pain after hyperextension, often a bicycle handlebar injury, with a knee effusion (haemarthrosis) and an inability to extend the knee fully. Lachman is positive if tested.
The floating knee. A high-energy injury. Assess the ipsilateral hip, knee and ankle, and screen for head, chest and abdominal trauma. A neurovascular examination is essential.
Be vigilant for compartment syndrome, especially in the floating knee, in both-bone fractures and after high-energy mechanisms: pain out of proportion, pain on passive stretch, tense compartments.
Investigations
Radiographs. AP and lateral views of the tibia and fibula, including the knee and ankle joints. For a suspected tibial spine fracture, AP and lateral views of the knee.
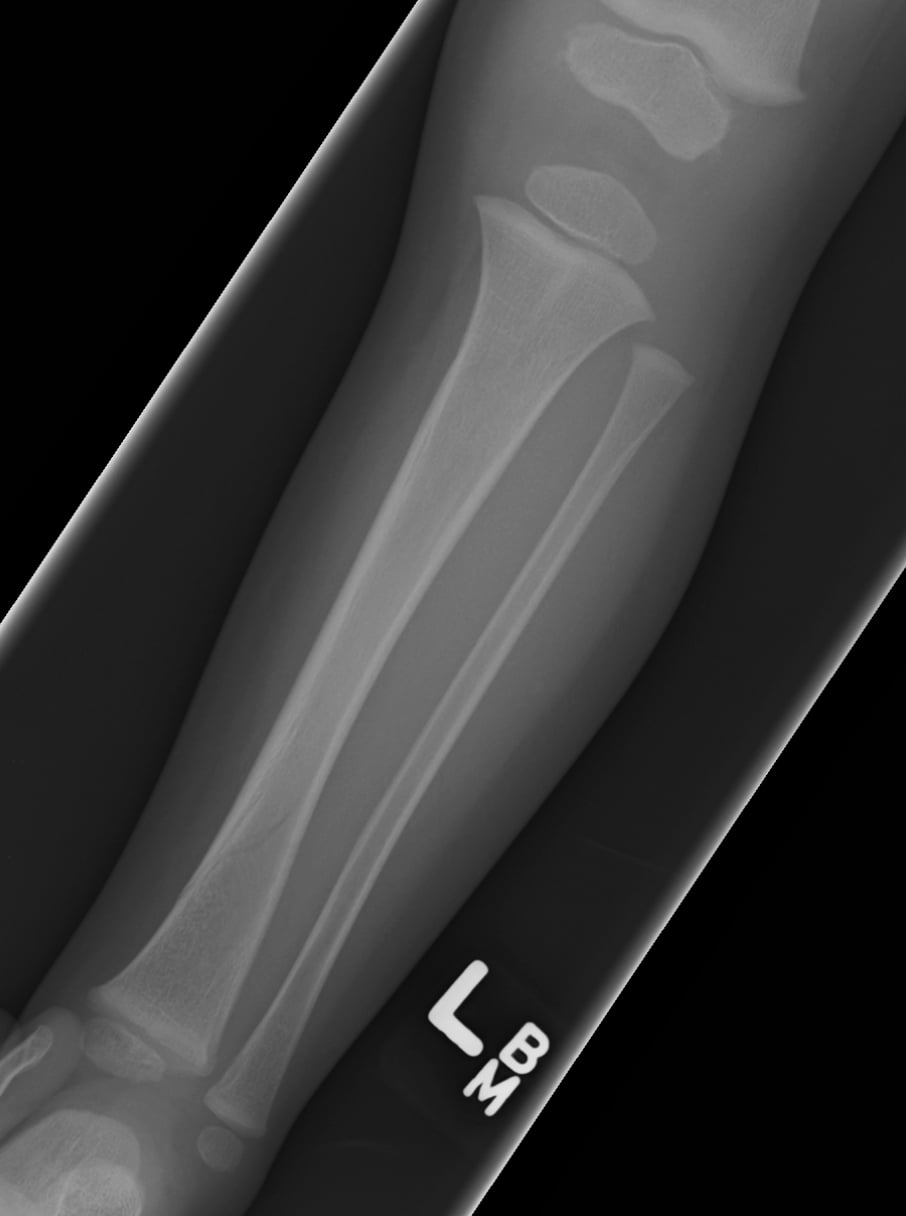
The occult toddler's fracture. The first film may be negative. Look for subtle periosteal reaction at 10-14 days, and if clinical suspicion is high, a bone scan or MRI can confirm the fracture. A bone scan is rarely needed.
MRI is used for the occult toddler's fracture, for assessing a tibial spine fracture and for associated soft-tissue injury. CT is for surgical planning of a tibial spine fracture and for complex intra-articular fractures.
Differential Diagnosis
The limping or non-weight-bearing child. A toddler refusing to weight-bear with a normal radiograph has a broad differential. The job is to separate a benign occult fracture from infection, malignancy and non-accidental injury before reassuring the family.
- Typical age
- 9 months - 3 years
- Key discriminator
- Point tibial tenderness, low-energy twist, periosteal reaction at 10-14 days
- Pitfall to avoid
- Calling it 'normal' on day 1 film
- Typical age
- Infants and young children
- Key discriminator
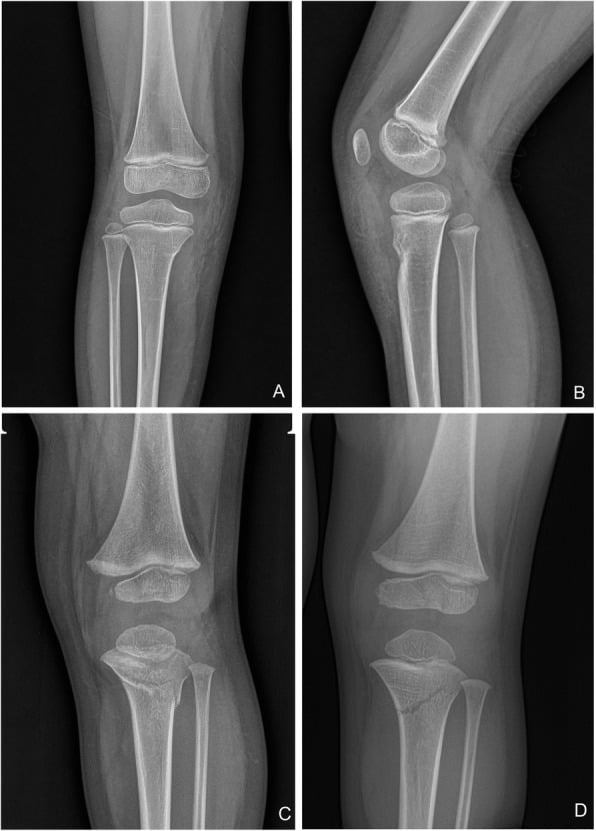
- Hyperextension mechanism at the knee with focal PROXIMAL tibial tenderness - the second occult toddler-type pattern, described by Swischuk
- Pitfall to avoid
- Searching only the distal tibia. A toddler's fracture is not always distal, and this one is missed by looking in the usual place
- Typical age
- Any
- Key discriminator
- Fever, raised CRP/ESR, warmth, refusal to move joint
- Pitfall to avoid
- Casting an infected limb
- Typical age
- Pre-ambulatory or inconsistent history
- Key discriminator
- Mechanism-injury mismatch, other injuries on survey
- Pitfall to avoid
- Failing to safeguard a young child
- Typical age
- 3-8 years
- Key discriminator
- Hip-referred pain, recent viral illness, settles quickly
- Pitfall to avoid
- Missing a tibial source of pain
- Typical age
- Any
- Key discriminator
- Pain before injury, lytic lesion, trivial trauma
- Pitfall to avoid
- Treating fracture without imaging the lesion
- Typical age
- 3-10 years
- Key discriminator
- Cozen's appears 8-19 months after a healed metaphyseal fracture
- Pitfall to avoid
- Blaming initial treatment for late valgus
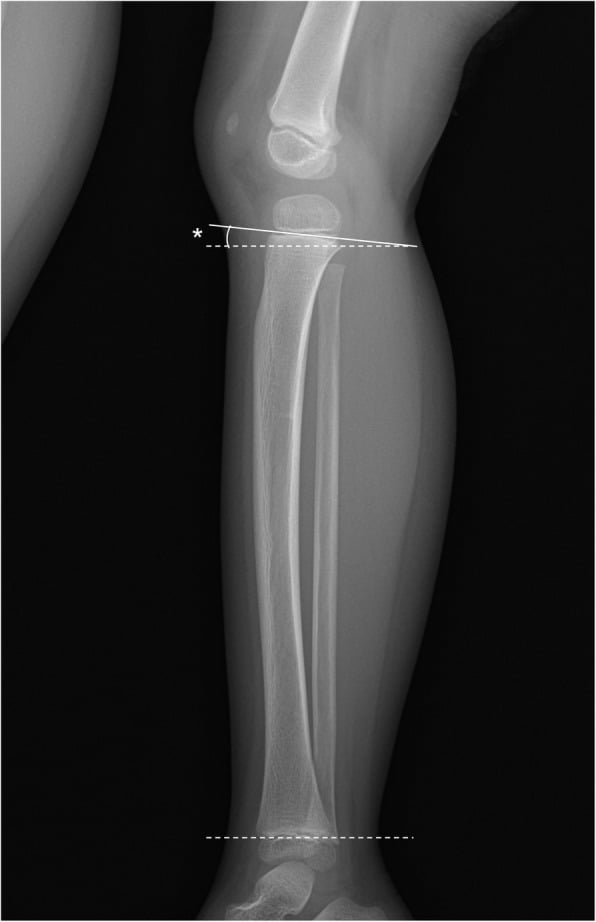
Non-Accidental Injury and the Paediatric Tibial Fracture
A tibial fracture may be the first presentation of non-accidental (inflicted) injury, and recognising the red flags before reassuring or discharging a family is a non-negotiable safeguarding duty. The single most important discriminator is whether the child is developmentally able to have caused the injury.
- Why it is concerning
- A spiral or long-bone tibial fracture needs force a pre-walking baby cannot generate; a toddler's fracture by definition needs a walking child
- Action
- Treat as suspected NAI until explained; escalate to safeguarding
- Why it is concerning
- Mechanism-injury mismatch and inconsistent accounts are classic
- Action
- Document verbatim histories; involve the child-protection team
- Why it is concerning
- Metaphyseal corner and bucket-handle fractures are highly specific for inflicted injury
- Action
- Skeletal survey to find them and other occult fractures
- Why it is concerning
- Healing fractures at varied stages, bruising in a non-mobile baby, torn frenulum or burns
- Action
- Full skeletal survey and multidisciplinary safeguarding assessment
- Why it is concerning
- Late presentation without adequate explanation
- Action
- Consider in the safeguarding picture rather than in isolation
In any young child (generally under 2 years) with a tibial fracture that does not fit the history or who is not yet walking, obtain a skeletal survey (per AAP/NICE guidance) and make a child-protection referral before discharge. Casting the fracture without addressing the safeguarding concern is a serious and recurring error - the orthopaedic injury and the safeguarding pathway must run in parallel. The patterns that should raise concern, and the investigation sequence, are set out in non-accidental injury.
Management
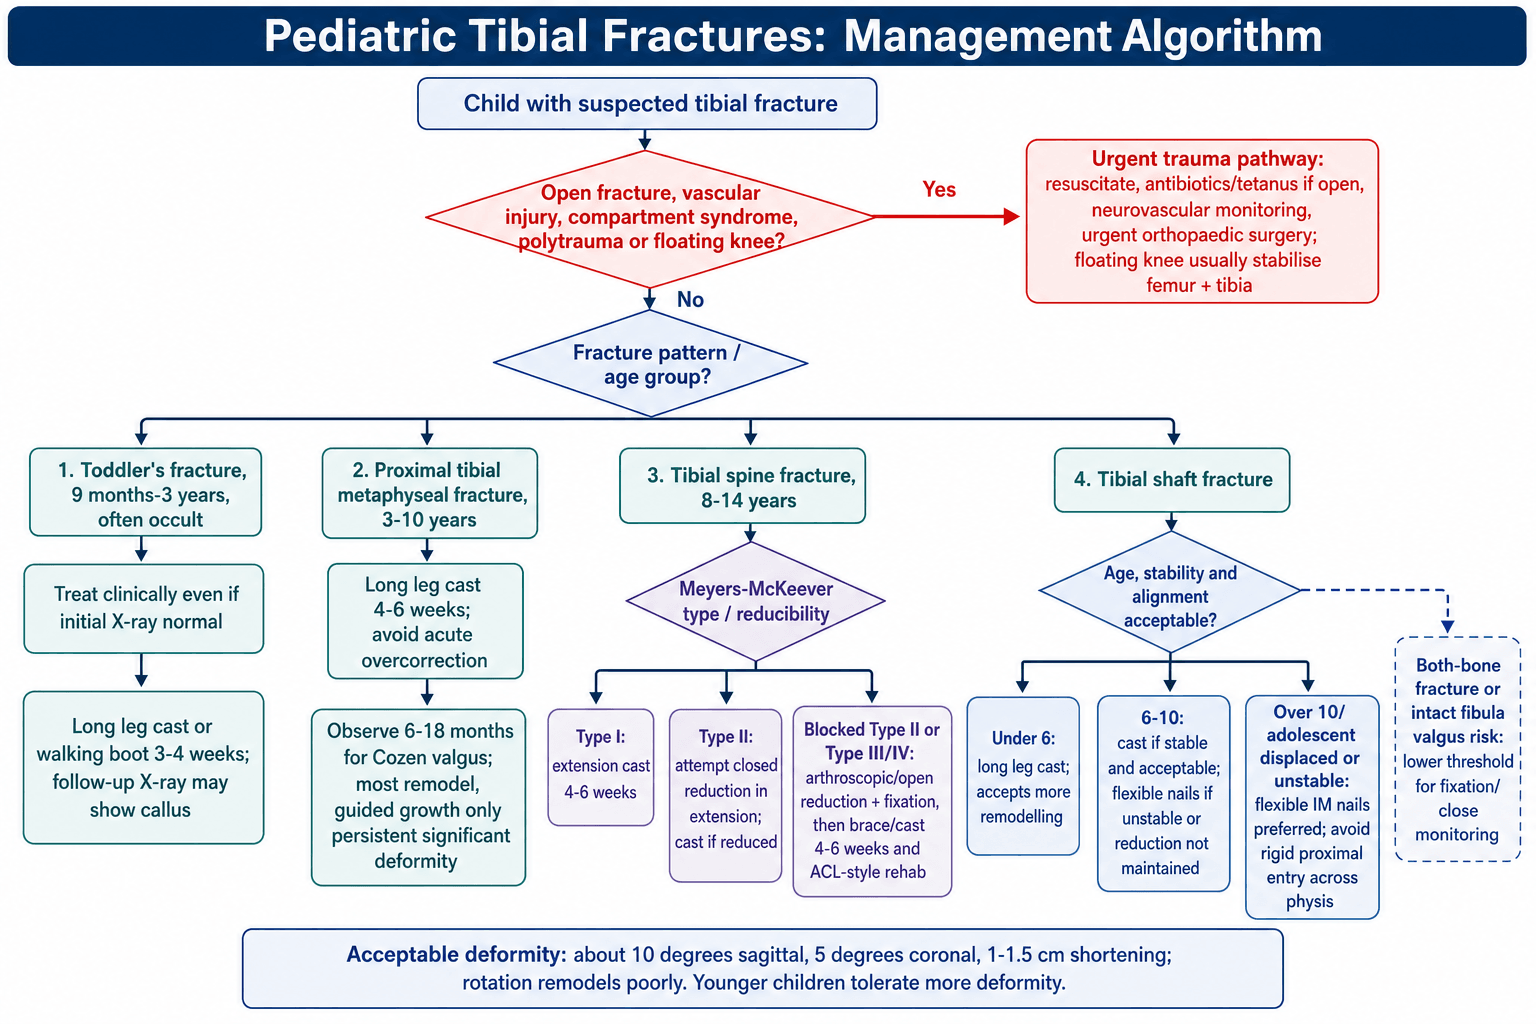
Age sets the strategy. The treatment principles by age:
- Under 6 years - a cast for most fractures; remodelling potential is high
- 6-10 years - a cast if the fracture is stable; operative treatment if it is unstable or acceptable alignment is not achieved (for an unstable shaft fracture, consider flexible nails)
- Over 10 years - remodelling potential is lower, and flexible IM nails are considered for shaft fractures
- Age
- 9 months - 3 years
- Key Feature
- Spiral tibia, often occult
- Treatment
- Cast 3-4 weeks
- Age
- 3-10 years
- Key Feature
- Risk of Cozen's valgus
- Treatment
- Cast, observe for valgus
- Age
- 8-14 years
- Key Feature
- ACL equivalent
- Treatment
- Type III = surgical
- Age
- All ages
- Key Feature
- High remodelling
- Treatment
- Cast or flexible nails
- Age
- Any age
- Key Feature
- High energy
- Treatment
- Surgical stabilisation
Treat the clinical diagnosis. A long leg cast or walking boot for 3-4 weeks, even if the radiograph is negative. The fracture is non-displaced and needs no reduction. Healing is rapid at this age, and a follow-up radiograph at 2 weeks shows callus.
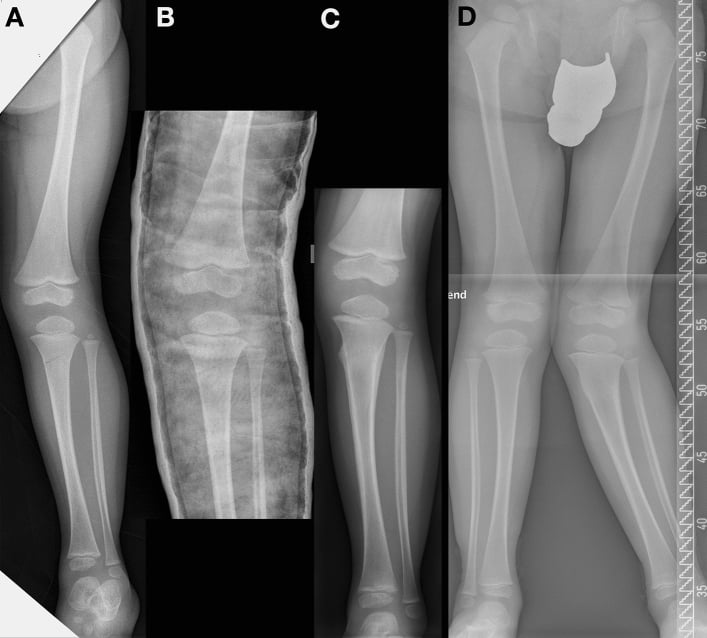
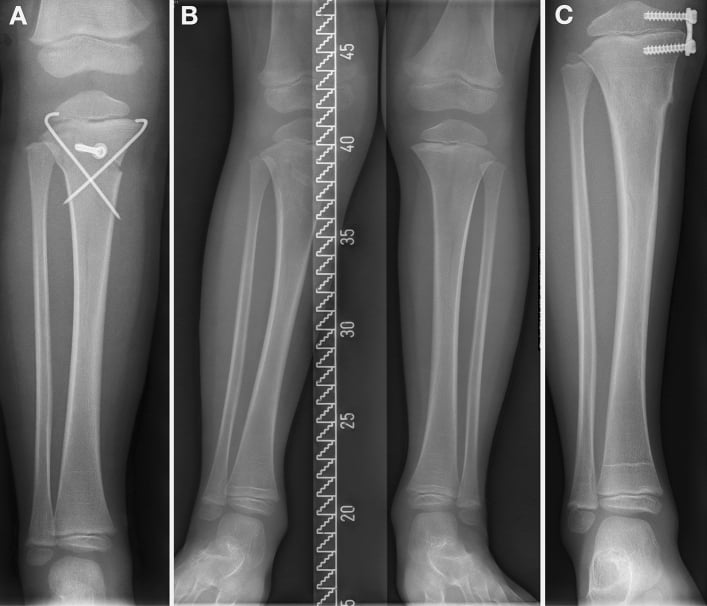
Principles of Remodelling in the Paediatric Tibia
The acceptable-deformity thresholds are not arbitrary: they follow the predictable rules of physeal remodelling. Knowing why a deformity will or will not correct is what lets you justify closed treatment versus reduction in the viva.
- Remodels well
- Young child with years of growth ahead
- Remodels poorly / not at all
- Adolescent near skeletal maturity
- Remodels well
- Deformity close to an active physis
- Remodels poorly / not at all
- Deformity at the mid-diaphysis, far from the physis
- Remodels well
- Angulation in the plane of joint motion (sagittal at the knee and ankle)
- Remodels poorly / not at all
- Coronal-plane (varus/valgus) angulation and, above all, ROTATION, which does not remodel
The tibia is less forgiving than the femur. Overall it remodels less reliably, so coronal angulation is corrected less readily and rotation not at all. This is why the accepted limits tighten with age and are plane-dependent, and why a rotational malalignment must be corrected at the time of treatment rather than left to remodel.
- Angulation - up to 10 degrees in the sagittal plane, 5 degrees in the coronal plane
- Shortening - up to 1-1.5 cm, which will remodel with growth
- Rotation - minimal accepted; it does NOT remodel at any age
Younger children tolerate more deformity because their remodelling potential is greater.
Surgical Technique Considerations
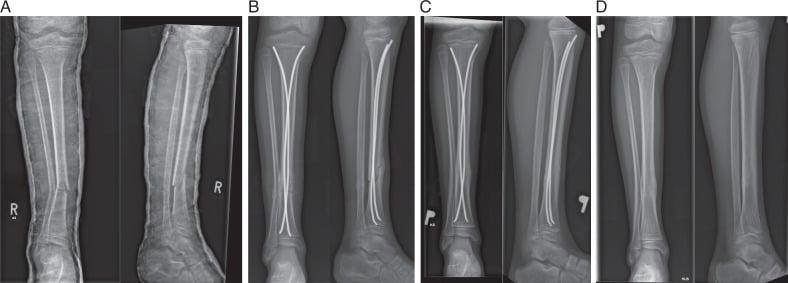
Flexible IM nailing (TENS/ESIN) is indicated for:
- Age over 6-10 years
- Unstable shaft fractures
- Polytrauma
Technique. Entry points are medial and lateral in the distal metaphysis, avoiding the physis. Avoid proximal entry, which risks damage to the tibial tubercle physis. Nail size is 40% of the medullary canal at the isthmus. Pre-contour the nails for apex anterior angulation.
Complications
- Fracture Type
- Proximal metaphyseal
- Management
- Observe - largely corrects by maturity; guided growth if it persists
- Fracture Type
- Shaft fractures
- Management
- Remodelling or corrective osteotomy if needed
- Fracture Type
- Tibial spine
- Management
- Proper reduction and fixation, ACL rehab
- Fracture Type
- Floating knee, high energy
- Management
- Urgent fasciotomy
- Fracture Type
- Physeal injuries
- Management
- Bar resection or corrective procedures
- Fracture Type
- Rare in children
- Management
- Operative intervention if occurs
Postoperative Care
Post-Treatment Protocol
Cast immobilisation. Non-weight bearing. Monitor for compartment syndrome in high-energy injuries.
X-ray at 2-3 weeks to confirm alignment. Toddler's fracture usually healed. Weight bearing as tolerated in cast.
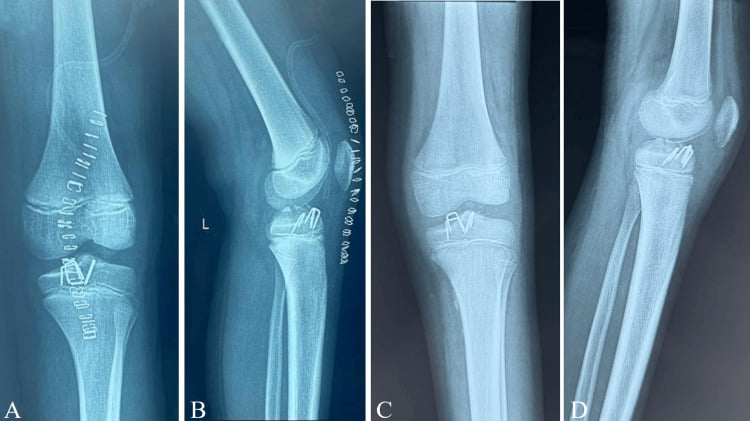
Remove cast when clinically and radiographically healed. Begin weight bearing. Tibial spine: begin ROM.
Follow proximal metaphyseal fractures for Cozen's valgus. Document and reassure. Tibial spine: assess for ACL laxity.
Outcomes and Prognosis
Toddler's fracture. Excellent: complete healing in 3-4 weeks, with no long-term sequelae.
Proximal metaphyseal fracture. Good, despite Cozen's phenomenon. Expect the small residual valgus excess and mild overgrowth described under Management rather than a return to symmetry. See genu valgum and varum for how a residual coronal deformity is then assessed and, if needed, corrected.
Tibial spine fracture. Good outcomes with proper treatment. Residual ACL laxity is possible but usually not symptomatic.
Shaft fractures. Excellent, with high union rates and good remodelling potential in younger children.
Guidelines, Registries & Global Practice
- Tibia/fibula fractures are among the commonest paediatric long-bone injuries worldwide
- Bimodal pattern: toddlers (low-energy twisting) and adolescents (sport, road traffic)
- Male predominance roughly 2:1 across most published cohorts
- Mechanism shifts by setting: trampolines, scooters and cycling in high-income regions; falls and road traffic dominate elsewhere
- Age-based remodelling logic is shared across all major training systems
- Toddler's fracture is a clinical diagnosis treated on suspicion regardless of resources
- Displaced tibial spine and floating-knee injuries are operative everywhere when expertise allows
- Non-accidental injury must be considered in any young, pre-ambulatory child with a tibial fracture
- Toddler's & shaft
- Cast for low-energy; flexible nails for unstable adolescents
- Tibial spine
- Arthroscopic suture fixation favoured for displaced
- NAI screening
- Skeletal survey under 2 years per AAP
- Toddler's & shaft
- Closed treatment first; ESIN for length-unstable
- Tibial spine
- Refer to paediatric ortho/sports knee service
- NAI screening
- Follow BOAST safeguarding standard
- Toddler's & shaft
- ESIN entry distal to tubercle apophysis
- Tibial spine
- ORIF/ARIF avoiding physis
- NAI screening
- Document mechanism vs injury concordance
- Toddler's & shaft
- Stable angulation thresholds by age
- Tibial spine
- Suture over screw to avoid removal
- NAI screening
- National safeguarding pathways
- No dedicated paediatric tibial-fracture implant registry exists; evidence is cohort/series level
- Trauma registries (e.g. national paediatric trauma networks) inform floating-knee and polytrauma outcomes
- Flynn criteria remain the common outcome language for flexible-nail series
- High-resource: routine arthroscopy, intra-operative imaging, MRI for occult injury, guided-growth implants
- Limited-resource: closed reduction and casting prioritised; open reduction when arthroscopy unavailable
- Telemedicine and serial radiographs substitute for advanced imaging where access is constrained
- Outcomes for closed-treatable patterns remain excellent regardless of setting
Special Considerations
The floating knee. Ipsilateral femur and tibia fractures from high-energy trauma, such as a motor vehicle accident or a fall from height. Associated injuries include knee ligament injuries in 40-80%, vascular injuries and other trauma, and the complication rate is higher.
Managing it. Both levels usually need surgical stabilisation: the femur typically with flexible nails, the tibia with a cast or nails depending on the pattern. It carries the highest risk of compartment syndrome, and a leg-length discrepancy is possible.
Pathological fractures. The fracture follows minimal trauma, and there may have been prior symptoms. Causes include simple bone cyst, fibrous dysplasia and osteogenesis imperfecta. Treat the fracture first, then address the underlying pathology, with curettage and bone grafting for cysts if needed.
Controversies and Areas of Uncertainty
Cozen's: predict or just watch? Age, sex and initial angulation do not reliably predict who develops late valgus, and the angle usually improves substantially, but it does not reliably resolve (see Natural history under Management). Routine prophylactic intervention is still not justified; the genuine debate is how long to observe before offering guided growth.
Tibial spine: suture, screw or anchor? Comparative data favour suture-based fixation for function and lower implant-removal rates, although in the meta-analysis under Surgical Technique the outcomes that measure the repair itself showed no difference. No high-quality randomised trial defines the optimal construct, and open versus arthroscopic reduction also remains debated.
The operative threshold in adolescents. The angulation and shortening a growing tibia will remodel is age-dependent and imprecise. Heavier, older adolescents behave more like adults, which narrows the case for purely closed treatment.
Imaging the occult toddler's fracture. MRI, bone scan and ultrasound can confirm occult fractures, but most authorities treat clinically without advanced imaging. The controversy is cost and radiation against diagnostic certainty.
MCQ Practice Points
Q: A 2-year-old refuses to walk after a fall. X-ray is normal. What is the management? A: Treat as toddler's fracture with cast 3-4 weeks. Clinical diagnosis is sufficient. X-ray may be negative initially.
Q: What is the management of progressive valgus 12 months after proximal tibial metaphyseal fracture? A: Observation and reassurance. The angle largely corrects by skeletal maturity, so do not operate early - osteotomy in particular has been abandoned because the valgus recurs. If deformity genuinely persists near maturity, guided growth is the intervention of choice.
Q: Which Meyers-McKeever type requires surgical treatment? A: Type III and IV. Type I and II are typically non-operative. Type III is completely displaced and requires fixation.
Q: What is the main complication risk in floating knee injury? A: Compartment syndrome. Floating knee is high energy with highest compartment syndrome risk. Also screen for other injuries.
Q: How much angulation is acceptable in pediatric tibial shaft fractures? A: 10 degrees sagittal, 5 degrees coronal. Younger children tolerate more. Rotation does not remodel.
Q: What is the risk of tibial shaft fracture with intact fibula? A: Valgus deformity. Intact fibula acts as tether, preventing shortening but may cause progressive valgus.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 2-year-old child is brought to ED by his mother. He has been refusing to bear weight on his left leg since yesterday after a fall from a low chair. On examination, there is no obvious swelling but tenderness over the distal tibia. X-rays appear normal. How would you manage this?”
“You are seeing an 8-year-old boy in clinic 12 months after he sustained a proximal tibial metaphyseal fracture that was treated in a cast. The fracture has healed but the parents are worried because his leg has become progressively bowed outwards. Examination confirms a 12 degree valgus deformity. How would you manage this?”
“A 12-year-old girl fell off her bicycle and presents with a swollen, painful right knee. She cannot fully extend her knee. X-ray shows a tibial spine fracture that appears displaced by about 8mm with complete loss of contact. How would you manage this?”
“A 10-year-old is brought in after being struck by a car. He has ipsilateral closed femoral shaft and tibial shaft fractures. Six hours after admission the nursing staff report escalating pain and increasing analgesia requirement despite the leg being splinted. How do you proceed?”
Toddler's Fracture
- Age 9 months to 3 years
- Spiral tibia, often occult on X-ray
- Clinical diagnosis - treat if suspected
- Cast 3-4 weeks, excellent prognosis
Cozen's Phenomenon
- Progressive valgus after proximal tibial metaphyseal fracture
- Develops 6-18 months post-injury
- Self-corrects by skeletal maturity
- DO NOT operate early
Tibial Spine
- Pediatric ACL equivalent
- Meyers-McKeever I-IV
- Type I-II: non-operative (cast)
- Type III-IV: surgical fixation
Floating Knee
- Ipsilateral femur and tibia fractures
- High energy - look for other injuries
- Highest compartment syndrome risk
- Usually requires surgical stabilization
Acceptable Deformity
- 10 degrees sagittal plane
- 5 degrees coronal plane
- 1-1.5 cm shortening
- Rotation: minimal (doesn't remodel)
Evidence Base and Key Studies
Each card below is anchored to a verified PubMed record (PMID and DOI shown). Use the level of evidence and sample size to judge how heavily to lean on a given statement in a viva.
Cozen's Phenomenon: Natural History and Resolution
- Retrospective series of 33 children (6 months to 14 years), mean follow-up 8.8 years
- 15 of 33 (almost half) developed late valgus between 8 and 19 months (mean onset 12.5 months)
- 24 of 33 (roughly three-quarters) developed tibial elongation; neither finding correlated with age at injury
- Maximum valgus subsequently corrected to near the initial post-treatment angle by final follow-up
- But compared with the UNINJURED limb the valgus difference, having peaked and then fallen, still left an excess over the initial measurement - correction was to the injured limb's own baseline, not to symmetry
Guided Growth for Persistent Cozen's Deformity
- Largest reported series (19 patients, 24 Cozen's phenomena) treated with medial proximal tibial guided growth
- Corrective osteotomy abandoned because of frequent recurrent valgus
- Mechanical axis and medial proximal tibial angle corrected in all but one patient
- Five recurrences after implant removal; managed by repeat or retained metaphyseal screw