Rocker Bottom Foot | Irreducible Dorsal Dislocation
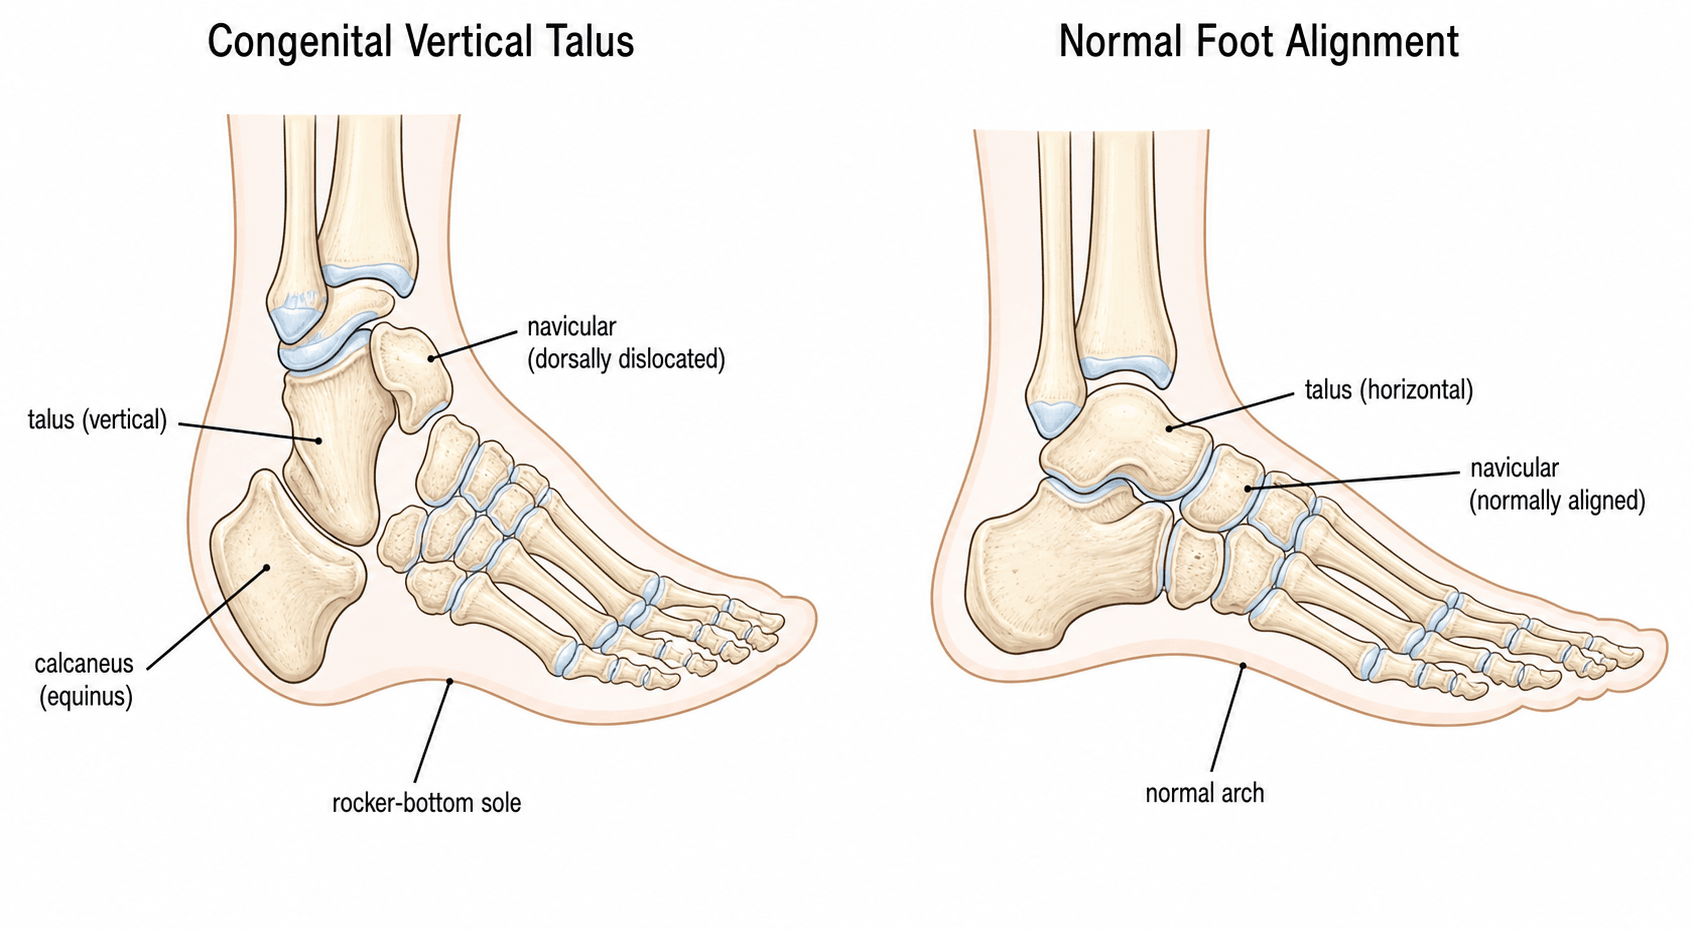
- Definition: Irreducible DORSAL dislocation of the navicular on the talus. The talus is 'vertical'.
- Deformity: Rigid Rocker Bottom Foot (Convex plantar surface). Heel in valgus and equinus.
- Key differentiation: CVT is rigid; calcaneovalgus is flexible. Congenital oblique talus (COT) is a less severe, more flexible talonavicular dislocation but need not fully reduce on forced plantarflexion.
- Diagnosis: Forced plantarflexion and dorsiflexion lateral radiographs quantify talonavicular alignment and hindfoot equinus; interpret the whole morphology rather than one binary sign.
- Management: Reverse-Ponseti serial casting followed by limited talonavicular stabilisation and Achilles tenotomy as needed is the contemporary first-line strategy.
- “CVT is a DISLOCATION of the Talonavicular joint.
- “50% of cases are associated with syndromes (Arthrogryposis, Neural Tube Defects) - Check the spine!
- “On forced plantarflexion view, the axis of the talus passes BELOW the first metatarsal (does not align).
- “Traditional treatment was extensive release (PMR). Modern treatment is Dobbs method (Reverse Ponseti).
Overview & Epidemiology
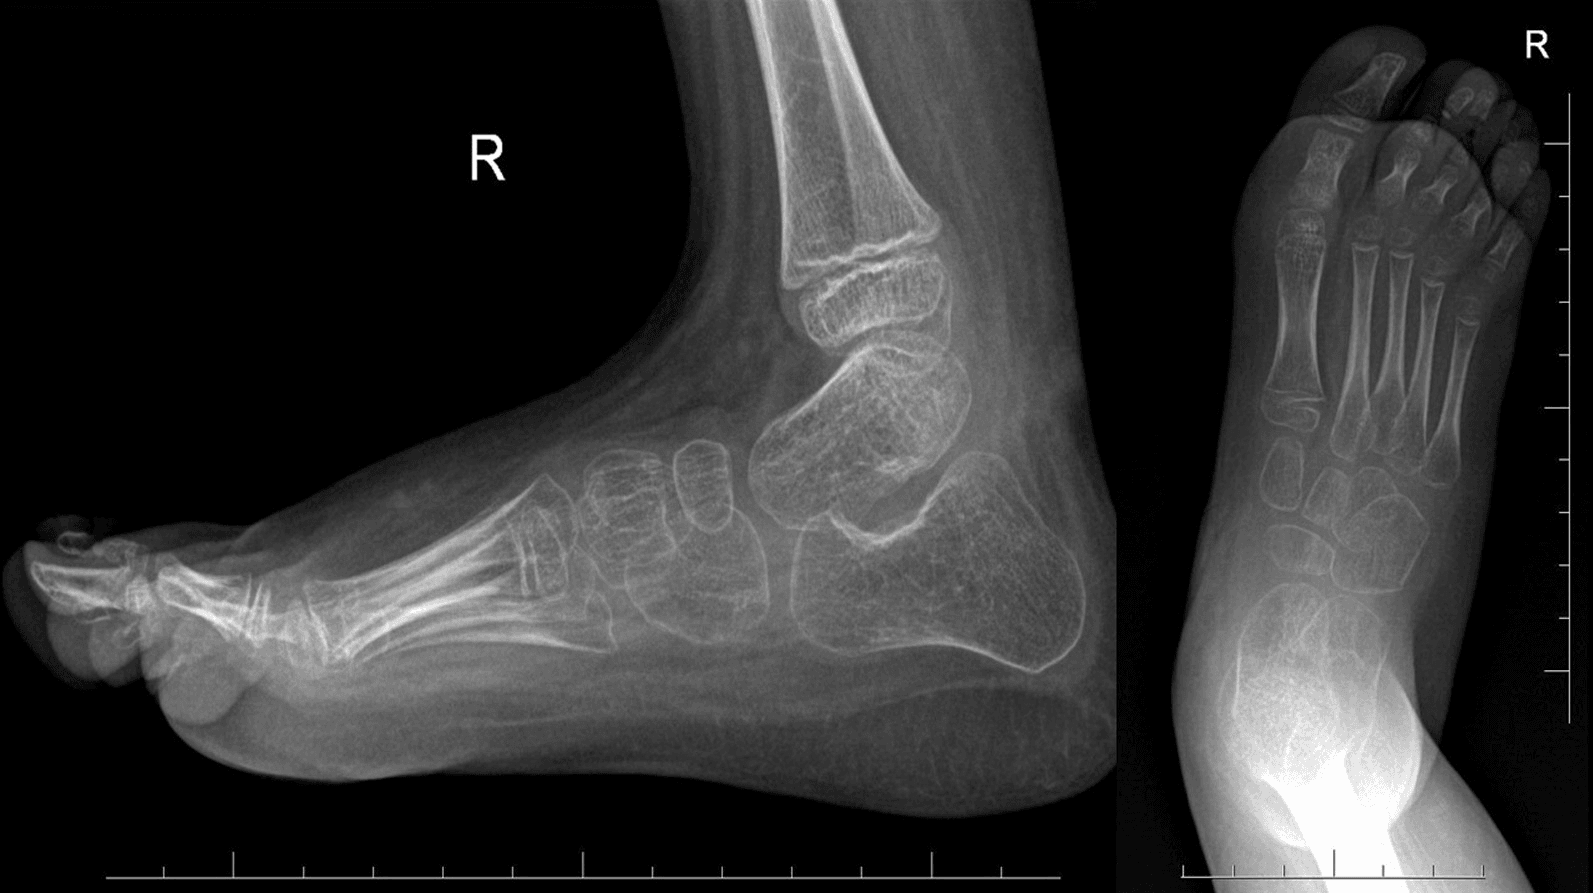
Congenital vertical talus (CVT), also called congenital convex pes valgus, is a rigid, irreducible dorsal dislocation of the navicular on the head of the talus. The talus is locked in a near-vertical, plantarflexed position, and the result is the characteristic rocker-bottom foot.
Who. CVT is rare, at approximately 1 in 10,000 live births, with no strong sex predilection. It is bilateral in roughly half of cases.
Associations. Around 50% are non-idiopathic (teratologic), occurring with neuromuscular or genetic disorders:
- Arthrogryposis
- Myelomeningocele or spina bifida
- Trisomy 13 or 18
- Other chromosomal and single-gene syndromes
An autosomal-dominant familial form linked to a HOXD10 mutation has also been described.
Pathophysiology & Pathoanatomy
The four deformities. The rocker-bottom foot combines four deformities:
- Hindfoot equinus - the calcaneus is fixed in plantarflexion, held by a contracted tendo-Achilles and posterior capsule
- Hindfoot valgus - increased talocalcaneal divergence
- Midfoot dorsiflexion with dorsal dislocation - the navicular sits dorsal to the talar neck, held there by the contracted tibialis anterior, extensor digitorum longus, extensor hallucis longus, peroneus tertius and dorsal talonavicular capsule. The peroneals and tibialis anterior are displaced and act as deforming dorsiflexors
- Forefoot abduction and dorsiflexion
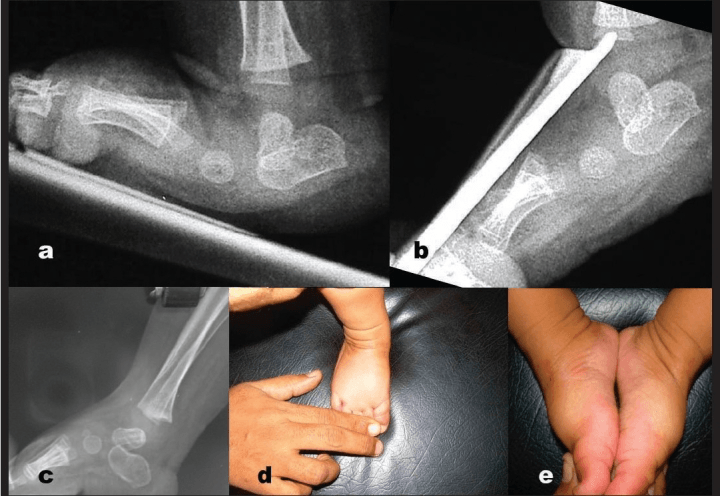
The disguise. The hindfoot equinus is masked by the dorsiflexed midfoot. The sole becomes convex, the rocker bottom, with the prominent talar head palpable medially in the sole. The deformity is rigid and irreducible, and that is the cardinal feature separating CVT from its flexible mimics.
Classification Systems
The clinically useful classification is the split between idiopathic and teratologic feet, and it is the split that guides prognosis and counselling:
- Idiopathic (~50%) - an isolated deformity with no associated syndrome, including the familial autosomal-dominant form. Better prognosis.
- Teratologic or syndromic (~50%) - accompanying the neuromuscular, chromosomal and genetic conditions listed above. More rigid and more resistant, with higher recurrence.
Clinical Assessment
Look. The sole is convex, the rocker bottom. The heel is up, in equinus and valgus, and the forefoot is abducted and dorsiflexed, with deep creases on the dorsolateral aspect of the foot.
Feel. The head of the talus is palpable in the medial sole, prominent because it points down. The deformity is stiff: you cannot plantarflex the forefoot or dorsiflex the heel.
Examine the whole baby. A missed syndrome is the pitfall. Look at the spine, including for a sacral dimple (spina bifida); the hips, for DDH; general tone, for arthrogryposis; and look for dysmorphism.
Differential diagnosis.
- Calcaneovalgus foot - very common and flexible; it dorsiflexes easily and is usually a packaging defect. The heel is down in calcaneus, not up in equinus, and it resolves with stretching.
- Congenital oblique talus (COT) - the mimic. Generally less severe and more flexible than CVT, with greater improvement on forced plantarflexion, but under current objective definitions residual talonavicular dislocation may persist, so complete normalisation is not required for the diagnosis.
- Posteromedial bowing - the apex is in the tibial shaft.
- Congenital Vertical Talus
- RIGID
- Oblique Talus
- FLEXIBLE
- Calcaneovalgus
- FLEXIBLE
- Congenital Vertical Talus
- Persistent severe dislocation; talus axis below 1st MT
- Oblique Talus
- Improves but may remain partly dislocated
- Calcaneovalgus
- Normal or near-normal alignment
- Congenital Vertical Talus
- Equinus + Valgus
- Oblique Talus
- Valgus
- Calcaneovalgus
- Calcaneus (Dorsiflexed) + Valgus
- Congenital Vertical Talus
- Reverse-Ponseti pathway
- Oblique Talus
- Individualised observation, casting or reconstruction
- Calcaneovalgus
- Observation and stretching
Investigations
The films. Radiographs are taken as simulated weight-bearing or forced views, and it is the forced views that make the diagnosis; a static film does not. The navicular is not ossified until age 3, so its position is inferred from the first metatarsal, which stands in as its surrogate.
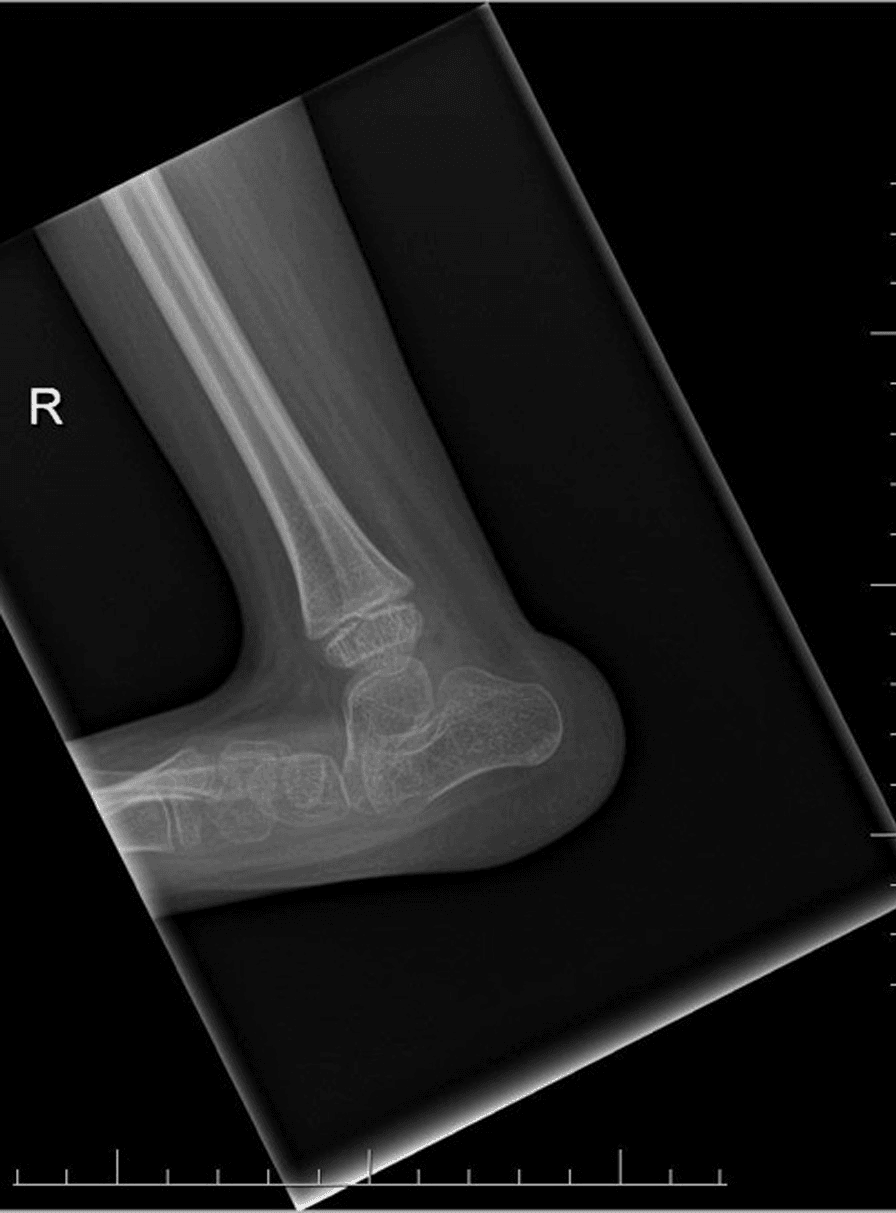
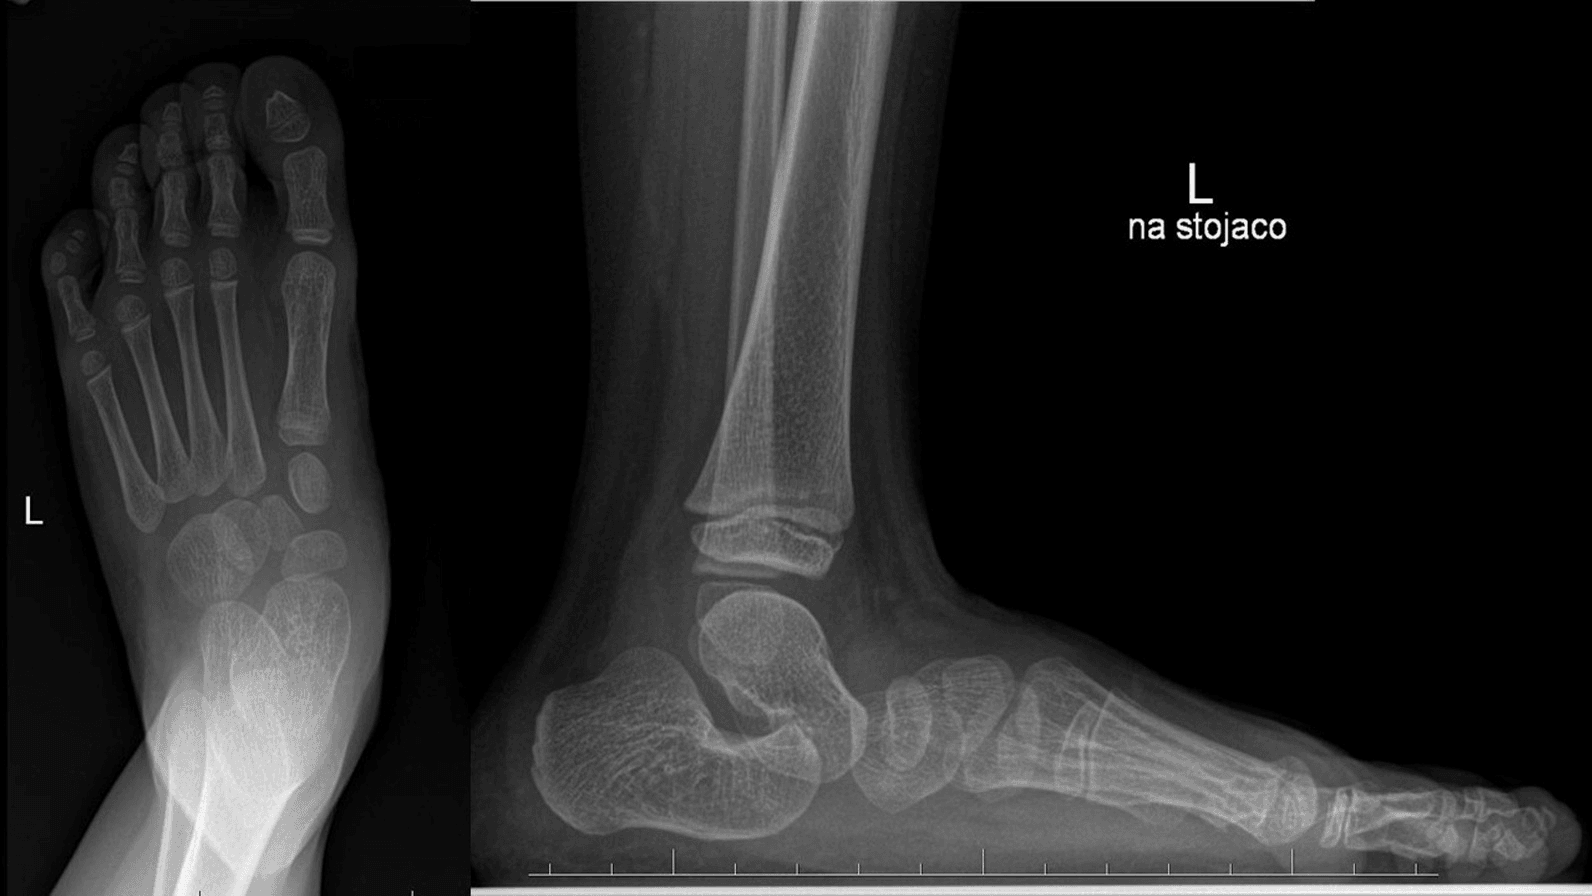
- Forced maximal plantarflexion lateral - the key view. It tests the degree of correction of the talonavicular relationship. Normally the axis of the talus lines up with the first metatarsal. In CVT it passes below the first metatarsal, and the navicular and forefoot stay dorsally dislocated and cannot be reduced onto the talar head.
- Forced maximal dorsiflexion lateral. It demonstrates the fixed hindfoot equinus: the calcaneus fails to dorsiflex and stays plantarflexed, confirming the rigid equinus that the rocker-bottom midfoot hides clinically.
- AP view. For the talocalcaneal angle, increased by the valgus.
Separating CVT from COT. On the plantarflexion view CVT keeps its marked dorsal dislocation. COT improves more and is less severe, but may retain residual dislocation. A foot that completely normalises is better classified within the flexible flatfoot with short tendo-Achilles spectrum than as COT.
The angles.
- Talar axis-first metatarsal base angle (TAMBA) - the lateral angle between the long axis of the talus and the first metatarsal. It is normally close to zero, the two axes roughly colinear (the lateral talo-first-metatarsal, or Meary, relationship). In CVT the talus is plantarflexed and the angle is grossly positive, plantar-apex; treatment series report it improving from about 60 degrees toward 15 degrees with correction.
- Calcaneal axis-first metatarsal base angle (CAMBA) - the calcaneus-to-forefoot relationship, complementing TAMBA.
- Talocalcaneal (Kite) angle - increased on both AP and lateral, reflecting the hindfoot valgus and divergence. Series quote roughly 70 degrees correcting to about 31 degrees.
The general definition of Meary's angle is covered in the dedicated Meary angle topic.
Measure the talar axis-first metatarsal base angle and compare neutral with forced plantarflexion, rather than applying a binary "reduces or does not reduce" rule.
Management Algorithm
The Dobbs method. Reverse-Ponseti serial casting, followed by limited talonavicular stabilisation and Achilles tenotomy as needed, is the contemporary first-line strategy. It has replaced the traditional extensive release (PMR).
Casting, the reverse of clubfoot. The foot is plantarflexed and inverted to bring the navicular back onto the talus, the opposite of Ponseti casting for clubfoot. It is never dorsiflexed: that worsens the deformity by breaking the midfoot. Casts are changed weekly, usually 5-8 in all.
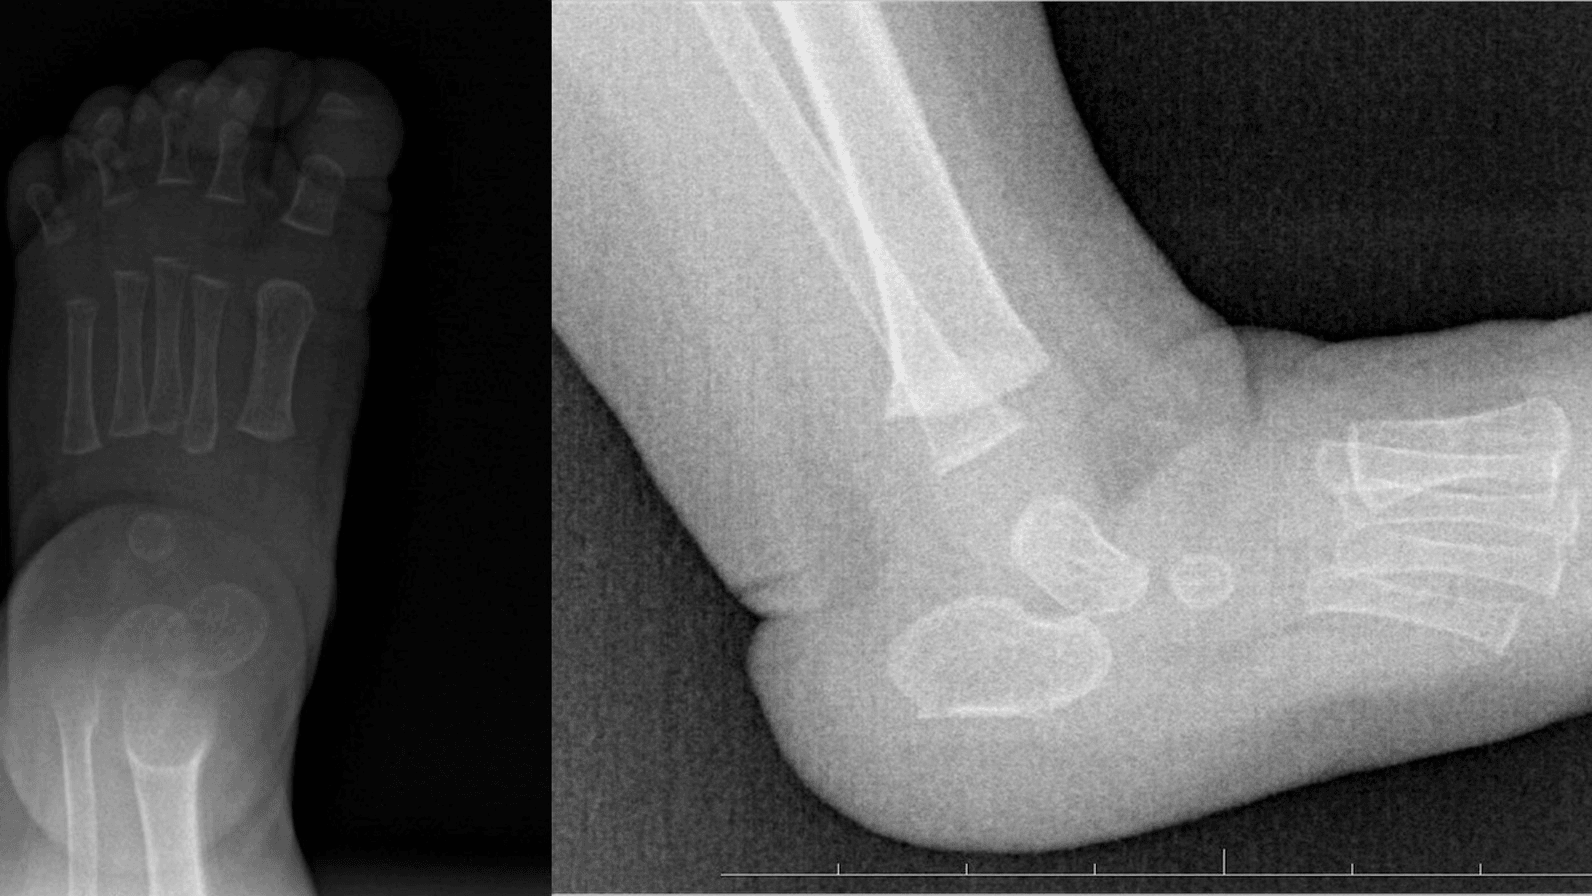
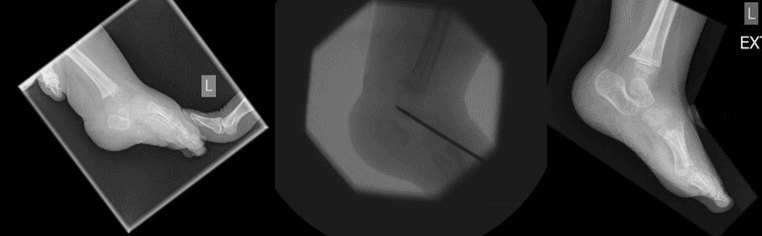
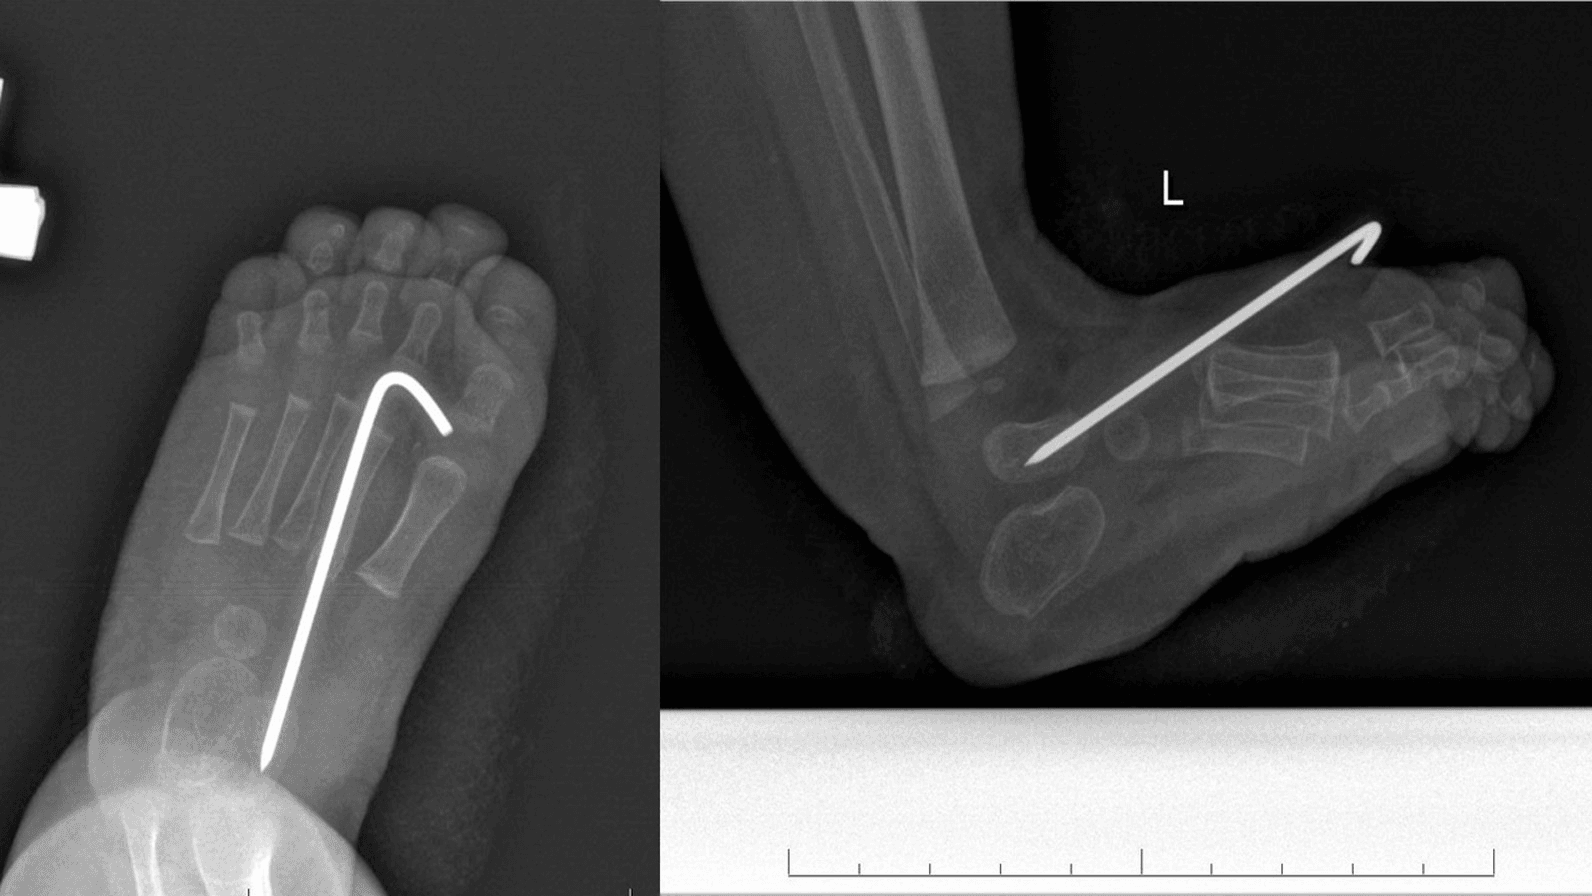
Stabilisation. Once the navicular is reduced, and the reduction confirmed on X-ray, a K-wire is passed across the talonavicular joint, percutaneously or through a mini-open approach. An Achilles tenotomy then corrects the fixed equinus, which remains after casting. A period in plaster and long-term bracing follow.
Open release. A one-stage extensive soft-tissue release is reserved for failure of the Dobbs method or late presentation, and is rarely needed now that the Dobbs method succeeds:
- Posterior release - capsulotomies and Achilles lengthening
- Dorsal release - talonavicular capsule, EHL and EDL lengthening
- Reduction of the talonavicular joint
- Pin fixation
Its problems are stiffness, AVN risk and wound complications.
Surgical Technique
The cast. Counter-pressure goes on the medial talar head, pushing it up, and the hand moulds the forefoot into plantarflexion and inversion. The aim is to stretch the tight dorsal structures (EHL, EDL and the TC ligament) and reduce the navicular.
The operation.
- Mini-open approach - a small incision over the talonavicular joint
- Pinning - visualise the reduction of the navicular on the talus and drive a 1.6mm K-wire from the dorsal navicular into the talus
- Percutaneous Achilles tenotomy - corrects the heel equinus
- Cast - a long-leg cast in neutral
Complications
- Risk Factor
- Neuromuscular cause, Poor bracing
- Management
- Repeat casting / Open surgery
- Risk Factor
- Extensive open release
- Management
- Fusion (salvage)
- Risk Factor
- Open surgery
- Management
- Observation
- Risk Factor
- Insufficient casting
- Management
- Revision
- Risk Factor
- Pin migration/removal
- Management
- Revision
Postoperative Care & Bracing
- Long-leg cast for about 6-8 weeks after the Dobbs procedure
- The talonavicular K-wire is typically removed at 5-6 weeks
- Weight-bearing permitted once the cast is off and the foot is plantigrade; mobilisation encouraged
- Ankle-foot orthosis or solid-ankle shoe, worn long term to maintain correction; many surgeons use a foot-abduction-style brace part-time for 1-2 years, mirroring the Ponseti maintenance phase
- Recurrence is the dominant late problem - 10 of 21 feet in the Wright cohort, in both idiopathic and teratologic feet - so follow until skeletal maturity
- Early recurrence is managed with repeat casting; established relapse may need revision surgery or, in the neglected or recurrent ambulatory foot, naviculectomy
- Counsel families at the outset that recurrence is the expected problem, not a failure of their care
Outcomes
Treated. The Dobbs method has a high success rate, with greater than 90% initial correction, and less stiffness than open surgery.
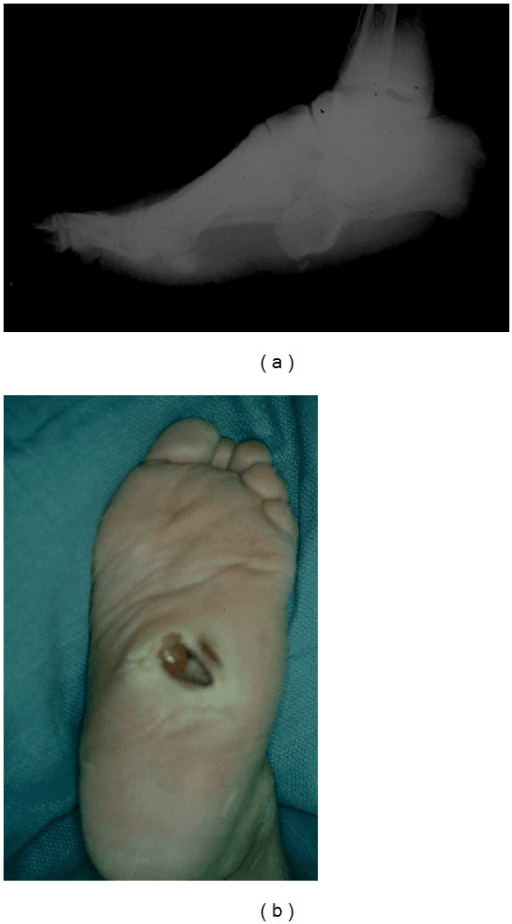
Untreated. The result is severe disability, painful calluses on the sole under the talar head, and difficulty wearing shoes.
The Teratologic (Syndromic) Foot: Why It Is Different
About half of CVT is teratologic, and the teratologic foot is the one that relapses. The principle of treatment is the same; the threshold differs.
Why it behaves worse. Teratologic CVT accompanies a persisting driver: the fixed contractures of arthrogryposis, the ongoing muscle imbalance and sensory loss of myelomeningocele or spina bifida, or a chromosomal syndrome such as trisomy 13 or 18. Because the underlying cause keeps acting, these feet are more rigid at presentation and recur far more often than idiopathic feet; independent cohorts report recurrence well above the original idiopathic series.
Casting still comes first. Reverse-Ponseti casting achieves initial correction even in syndromic and older feet. Expect more casts, and have a lower threshold to add a limited dorsal or talonavicular capsulotomy at the index operation, rather than tenotomy and pinning alone, to reduce relapse.
Bracing is not optional. In teratologic feet maintenance bracing is near-mandatory, and surveillance must continue to skeletal maturity because relapse is the rule, not the exception.
Protect the insensate foot. In myelomeningocele, watch the skin: pressure sores under the cast and plantar ulceration over the prominent talar head are real hazards.
Salvage is needed more often. For repeated failures or neglected syndromic feet, a tailored limited release or naviculectomy, and at maturity triple arthrodesis, is reached for sooner than in idiopathic disease.
Treat the child, not just the foot. Screen for and co-manage the spine, the hips and the underlying condition; the syndromes themselves are covered in the arthrogryposis and related topics.
Guidelines, Registries & Global Practice
Global epidemiology:
- Rare congenital deformity, ~1 in 10,000 live births; bilateral in roughly half.
- Around 50% are teratologic, associated with arthrogryposis, myelomeningocele, trisomies (13/18) and other syndromes — proportions vary with referral pattern and access to prenatal screening.
Practice consensus (no single national guideline governs CVT):
- Prevailing position
- Reverse-Ponseti (Dobbs) serial casting then percutaneous Achilles tenotomy and talonavicular pinning — now standard across North America, UK/Europe, Australasia and increasingly worldwide
- Prevailing position
- Reserved for casting failure, neglected or rigid teratologic feet; superseded as primary treatment due to stiffness and AVN
- Prevailing position
- Naviculectomy / tailored release for complex ambulatory feet; triple arthrodesis at maturity for painful uncorrectable feet
- Prevailing position
- Examine spine (sacral dimple/myelomeningocele), hips and neuromuscular tone in every case; arrange genetics/family history in isolated familial CVT (HOXD10)
High- vs limited-resource variation:
- Where neonatal screening and paediatric orthopaedic services exist, most feet present and are cast in infancy with minimally invasive surgery.
- In limited-resource or remote settings, late/neglected presentation is more common, shifting the balance toward salvage procedures (naviculectomy, talectomy, later triple arthrodesis). Reverse-Ponseti casting is attractive globally because it is low-cost and avoids major open surgery.
- No dedicated implant registry exists for CVT (unlike arthroplasty); evidence rests on single-centre series, so practice is guided by consensus rather than registry data.
Controversies & Areas of Uncertainty
In the original Dobbs series every recurrence occurred in feet without talonavicular pinning, so most surgeons now pin routinely. The optimal pin construct, duration and whether to pin in very young infants remain debated.
Pure reverse-Ponseti relies on tenotomy plus pinning, but several groups add a limited dorsal/talonavicular capsulotomy at the index procedure to cut recurrence (Wright 2014). The line between "minimally invasive" and "selective release" is blurred and not standardised.
Independent cohorts report recurrence in up to ~40-50% of feet — well above the original series — particularly in teratologic feet. Reported success depends heavily on case mix and definition of recurrence.
For older ambulatory children, neglected feet, or repeated failures there is no consensus: options span late reverse-Ponseti, talectomy, naviculectomy (resection arthroplasty) and, at maturity, triple arthrodesis. Evidence is limited to small series.
MCQ Practice Points
Q: What represents the radiographic hallmark of CVT? A: Irreducible dorsal dislocation of the navicular on the talus, demonstrated on a forced plantarflexion lateral X-ray (talar axis passes below 1st metatarsal).
Q: What percentage of CVT cases are associated with other anomalies? A: Approximately 50% (Neural tube defects, Arthrogryposis, Genetic syndromes).
Q: How do you clinically differentiate CVT from Calcaneovalgus foot? A: CVT is RIGID and the heel is in equinus. Calcaneovalgus is FLEXIBLE and the heel is in calcaneus (dorsiflexed).
Q: In the Dobbs method for CVT, how is the foot manipulated? A: Plantarflexion and Inversion (to reduce the navicular). Dorsiflexion is AVOIDED as it causes a midfoot break.
Q: What happens to Kite's Angle (Talocalcaneal Angle) in CVT? A: It is increased (greater than 35-40 degrees), indicating severe hindfoot valgus.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“What is your diagnosis and differential?”
“Explain the casting and surgery.”
“How do you assess and manage recurrent / neglected CVT?”
Key Features
- Rocker Bottom Foot
- Rigid Deformity
- Talar Head in Sole
- 50% Syndromic
X-ray Sign
- Forced Plantarflexion View
- Irreducible TN joint
- Talus axis below 1st MT
- Kite's Angle greater than 40 (Valgus)
- Fixed Equinus on DF View
Management
- Dobbs Method (Gold Std)
- Cast: PF + Inversion
- Sx: Pin + Tenotomy
- Open Release (Historic)
Differential
- Calcaneovalgus (Flexible)
- Congenital oblique talus (less severe, more flexible)
- Clubfoot (Wait.. opposite)
- Review Spine/Hips
Complications
- Recurrence (Common)
- AVN (Open Surgery)
- Stiff Foot
- Navicular Subluxation
Evidence Base
Dobbs method (landmark)
- 11 patients (19 idiopathic CVT feet); reverse-Ponseti serial casting then percutaneous Achilles tenotomy and talonavicular pinning.
- Initial correction achieved in all 19 feet with a mean of 5 casts; no extensive releases needed.
- At minimum 2 years: mean ankle dorsiflexion 25 degrees, plantarflexion 33 degrees; all radiographic angles normalised.
- Dorsal navicular re-subluxation recurred in 3 patients, NONE of whom had undergone talonavicular pin fixation.
Minimally invasive vs extensive release (long-term comparison)
- 27 patients (42 feet) reviewed at mean 7 years (range 5-11.3): 24 feet minimally invasive vs 18 feet extensive soft-tissue release.
- Final ankle range of motion 42.4 degrees (minimally invasive) versus 12.7 degrees (extensive release), p less than 0.0001.
- PODCI pain and global function scores superior in the minimally invasive group; greater correction of hindfoot valgus.
- Benefit persisted in the isolated/idiopathic subgroup.
Reverse Ponseti: idiopathic vs teratologic & recurrence
- Prospective cohort of 13 children (21 feet); 12 idiopathic and 9 teratologic feet treated with reverse-Ponseti casting then percutaneous reduction/fixation.
- Initial correction achieved in ALL children with significant radiographic improvement.
- Recurrence occurred in 10 feet — higher than the original Dobbs series, in both idiopathic and teratologic groups.
- Authors suggest adding limited capsulotomy at the index operation may reduce recurrence; rates still lower than after open release.
Dobbs method in idiopathic AND syndromic / older children
- 15 feet in 10 patients aged 1 month to 9 years (idiopathic and syndromic) treated with the Dobbs method.
- Mean talocalcaneal angle improved 70.5 to 31 degrees; talar-axis-metatarsal-base angle 60 to 15 degrees (both p less than 0.001).
- All feet plantigrade and flexible with good radiographic correction at mean 2-year follow-up.