Indolent Periprosthetic Infection | Low-Virulence Organism | Diagnostic Challenge
- C. acnes is the most common organism in shoulder PJI, overtaking Staphylococcus species
- Normal CRP, ESR, and WCC do NOT exclude C. acnes PJI
- Culture all tissue samples for a minimum of 14-21 days in anaerobic conditions
- Male patients predominate (hair follicles of upper trunk and shoulder)
- Sonication of explanted components increases culture yield
- “Think C. acnes in any painful shoulder arthroplasty with normal inflammatory markers
- “Prolonged anaerobic culture (14-21 days) is mandatory, not optional
- “Male sex + shoulder arthroplasty + unexplained pain = culture for C. acnes
- “Sonication of explanted prosthesis significantly improves detection
Overview and Epidemiology
Cutibacterium acnes (formerly Propionibacterium acnes) is the most common causative organism in shoulder periprosthetic joint infection, responsible for approximately 30-60% of all shoulder PJIs and overtaking Staphylococcus aureus and the coagulase-negative staphylococci. Its indolent, low-virulence nature means it frequently presents with normal inflammatory markers and no systemic features, which makes it a diagnostic trap. Examiners test it because it illustrates the principle that normal bloods do not exclude infection.
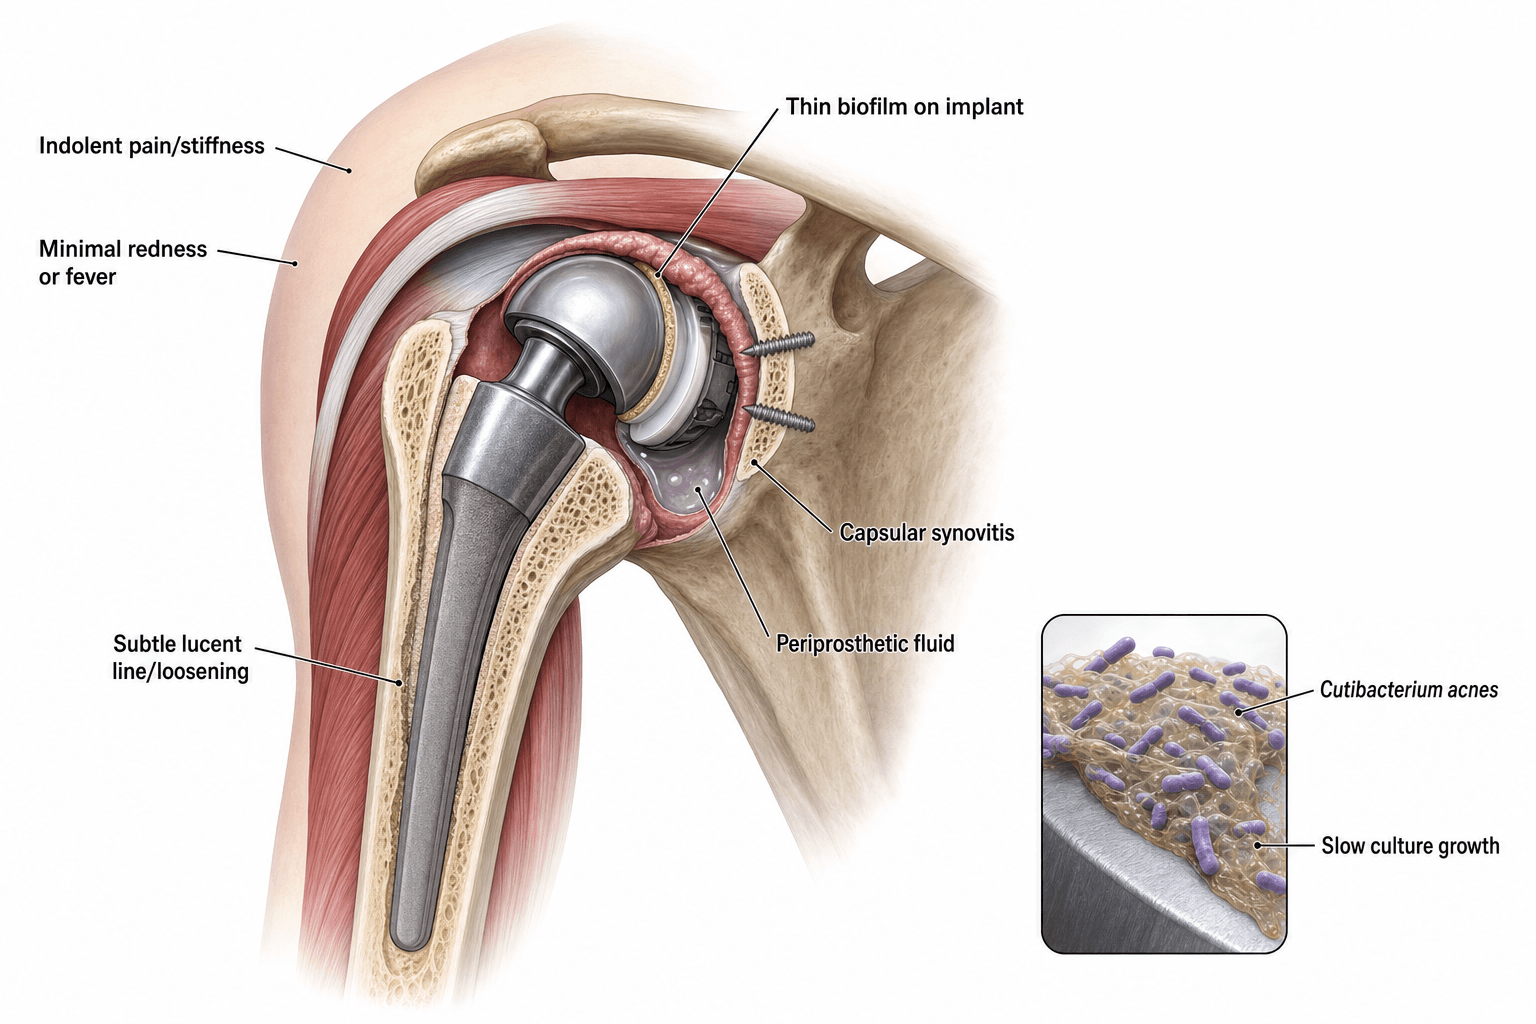
The organism. A Gram-positive anaerobic bacillus and a skin commensal of the deep hair follicles and sebaceous glands of the upper trunk. It is slow-growing, requiring 14-21 days of anaerobic culture; it forms biofilm on implant surfaces; and its virulence is low, with minimal local inflammation and typically no systemic response.
Who gets it. Males are affected significantly more than females, likely because of the greater pilosebaceous density of the upper trunk, shoulder and proximal arm. The other risk factors are prior shoulder surgery, haematoma and prolonged operative time. Recognition has increased as improved culture techniques and longer incubation have revealed the true prevalence.
Pathophysiology
Inoculation. The shoulder region has the highest density of pilosebaceous units harbouring C. acnes on the human body, and the organism resides deep within them, where standard chlorhexidine or povidone-iodine skin preparation does not fully eradicate it. It can therefore be inoculated into the surgical field despite standard skin preparation: intra-operative contamination rates of 15-30% have been reported from tissue cultures taken during primary shoulder arthroplasty.
Biofilm. Once in contact with an implant surface, metal or polyethylene, C. acnes forms a biofilm, a structured extracellular polymeric matrix that protects the bacteria from both the host immune response and antibiotic penetration. Within it the organism exists in a metabolically quiescent state that is resistant to cell-wall active antibiotics, and the minimum biofilm eradication concentration (MBEC) can be 100-1000 times the planktonic minimum inhibitory concentration (MIC). This is why antibiotics alone rarely cure established implant-related infection, and why surgical intervention with component removal or exchange is usually required for eradication.
- C. acnes PJI
- Indolent, low-grade, months to years
- Staphylococcal PJI
- Acute, often fulminant, days to weeks
- C. acnes PJI
- Often normal
- Staphylococcal PJI
- Usually elevated
- C. acnes PJI
- Absent (no fever, no wound breakdown)
- Staphylococcal PJI
- Fever, wound erythema, drainage common
- C. acnes PJI
- 14-21 days anaerobic incubation
- Staphylococcal PJI
- Grows within 48-72 hours on standard media
- C. acnes PJI
- Prominent, thin biofilm on implant
- Staphylococcal PJI
- Thick biofilm (S. aureus) or slime layer (CoNS)
- C. acnes PJI
- Strong male predominance
- Staphylococcal PJI
- No sex predilection
Prevention. The reservoir is the dermis rather than the surface, so contamination is the problem to attack before it becomes an infection, and the examinable point is what actually reduces it:
- Topical benzoyl peroxide, applied for several days pre-operatively, is the single most effective measure: it penetrates the follicle and significantly lowers the C. acnes skin and dermal burden
- Standard chlorhexidine/alcohol skin prep is necessary but insufficient: even after a textbook prep, dermal punch-biopsy cultures remain positive in a substantial proportion of patients
- Hydrogen peroxide applied to the skin and dermis after the incision has been shown to reduce C. acnes culture positivity from the wound
- Standard prophylactic cefazolin covers C. acnes, which is penicillin- and cephalosporin-sensitive; some units add clindamycin or vancomycin in high-risk cases, though the evidence for the addition is limited
- Male sex cannot be modified, so the modifiable levers are the skin and dermal antiseptic protocol, meticulous technique, and minimising operative time and haematoma
The trap is assuming that a normal-looking surgical prep has sterilised the field. The dermal reservoir means the field is never truly sterile for C. acnes, which is why these adjuncts and a low threshold for intra-operative culture both matter.
Classification and Types
Classification by Timing (Adapted from Tsukayama)
- Timing
- Within 3 months of index surgery
- Presentation
- Acute wound inflammation, pain, possible drainage
- Treatment Approach
- DAIR + targeted antibiotics (if stable implant)
- Timing
- Greater than 3 months, indolent course
- Presentation
- Gradually worsening pain, loosening, normal CRP
- Treatment Approach
- One-stage or two-stage revision + antibiotics
- Timing
- Sudden onset in previously well-functioning arthroplasty
- Presentation
- Acute pain, systemic features possible
- Treatment Approach
- DAIR if less than 3 weeks of symptoms + stable implant
- Timing
- Found during revision for presumed aseptic loosening
- Presentation
- No pre-operative suspicion of infection
- Treatment Approach
- Targeted antibiotics +/- staged revision based on findings
The "unexpected positive" category is particularly relevant to C. acnes, because the organism is frequently identified only after prolonged incubation of tissue samples sent during revision for presumed aseptic failure.
Clinical Assessment
History. Pain is the most common presenting symptom: persistent or worsening pain after shoulder arthroplasty, with progressive loss of range of motion, presenting months to years after the index surgery. There is typically nothing to suggest infection, with no erythema, warmth or drainage from the wound and no fever, rigors or malaise. Delayed diagnosis is common, with an average delay of months to years from symptom onset.
Examination. The wound is well healed with no erythema or sinus. There may be mild tenderness around the implant, though palpation is often unremarkable; range of motion is decreased, often with pain at the end ranges; component loosening may cause subtle instability; and the neurovascular examination is usually intact, with no specific deficit.
The trap. C. acnes shoulder PJI is virtually indistinguishable from aseptic loosening on clinical and basic radiographic assessment. Both present with gradual-onset pain, stiffness and possible radiographic lucency, and the distinction depends entirely on microbiological culture with prolonged anaerobic incubation. Tissue therefore goes for prolonged culture at every revision shoulder arthroplasty, regardless of pre-operative suspicion.
When to suspect it. Always suspect C. acnes in:
- Any male patient with a painful shoulder arthroplasty and normal inflammatory markers
- Any revision shoulder arthroplasty, even if the pre-operative work-up is negative for infection
- Any "aseptic loosening" that progresses more rapidly than expected
- Persistent pain after arthroscopic or open shoulder surgery with implants in situ
- CRP/ESR
- Normal in many cases
- Key Discriminator
- Indolent pain, male, normal bloods, loosening
- Definitive Test
- Prolonged tissue culture (14-21 d) + sonication
- CRP/ESR
- Normal
- Key Discriminator
- Mechanical pain, lucency on X-ray, no infection
- Definitive Test
- Negative culture (must culture to exclude C. acnes)
- CRP/ESR
- Elevated
- Key Discriminator
- Acute presentation, wound changes, systemic features
- Definitive Test
- Standard culture (48-72 h), blood cultures
- CRP/ESR
- Normal
- Key Discriminator
- Weakness, inability to elevate arm, instability
- Definitive Test
- Ultrasound or MRI (gadolinium)
- CRP/ESR
- Normal or mildly elevated
- Key Discriminator
- Painless effusion, pseudotumour, metal-on-metal bearing
- Definitive Test
- Metal ion levels, MRI, histology
- CRP/ESR
- Normal
- Key Discriminator
- Episodes of dislocation or subluxation
- Definitive Test
- Stress radiographs, CT for component version
Investigations
Serum markers. CRP and ESR are frequently normal or only mildly elevated, and the FBC is frequently normal too, so do not be reassured by normal values: they are useful if positive and meaningless if negative. Interleukin-6 may be more sensitive than CRP for low-grade PJI but is not universally available. Procalcitonin is not sensitive for low-virulence infection and is not recommended for C. acnes screening.
Radiographs. AP, axillary lateral and scapular-Y views of the shoulder. Look for radiolucent lines at the bone-cement or bone-implant interface, component migration or subsidence and osteolysis; periosteal reaction is rare in C. acnes. The findings are often subtle and nonspecific, with only mild radiolucent lines or component loosening and no overt sign of infection, and radiographic loosening in C. acnes PJI is indistinguishable from aseptic loosening on X-ray alone. This indolent picture is a hallmark of the organism and contributes to the delay in diagnosis.
Joint aspiration. Ultrasound- or fluoroscopy-guided aspiration is preferable, because a dry tap is common without imaging guidance. Send the fluid for cell count and differential, Gram stain, and aerobic and anaerobic culture with a specific request for 14-21 day incubation. The synovial white cell count thresholds for the shoulder are lower than those for the hip and knee, as set out in the MSIS adaptation above.
Synovial biomarkers. Alpha-defensin performance varies with the assay format. The laboratory ELISA, in 105 painful shoulder arthroplasties in which 63% of the infections were C. acnes, gave a sensitivity of 75% (95% CI 53-90) and specificity of 96% (90-99); the lateral-flow point-of-care version, in a separate prospective cohort, gave sensitivity 60% and specificity 83%, and its authors concluded it "does not appear to be useful in predicting shoulder PJI". So a positive laboratory alpha-defensin is worth a lot, and a negative one does not exclude C. acnes: a quarter of infections were missed even by the better-performing assay. Leukocyte esterase is weaker still in this joint, with sensitivity 50% (95% CI 21-79) and specificity 87%, and is often unreadable because shoulder aspirates are scanty or blood-stained; it is useful to rule in and useless to rule out. Both tests are less sensitive in the shoulder than the hip and knee figures they are famous for.
Advanced imaging. CT assesses component position, version, bone stock and the pattern of osteolysis for revision planning. MRI with gadolinium may show a periprosthetic fluid collection, synovitis or abscess in low-grade PJI, and metal artefact reduction sequences are essential. Nuclear medicine (PET-CT, labelled leukocyte scan) has limited evidence specific to C. acnes shoulder PJI and may be used in equivocal cases.
Tissue culture. The single most important investigation is tissue culture with prolonged anaerobic incubation, because bloods, imaging and even aspiration may all be negative. At revision surgery, send a minimum of 5 tissue samples from different periprosthetic sites, and request sonication of any explanted components: it disrupts the biofilm and significantly increases culture yield compared with periprosthetic tissue culture alone.
- Specimen
- 5 or more tissue samples from different sites
- Duration
- 14-21 days anaerobic
- Sensitivity for C. acnes
- Moderate — dependent on sampling and technique
- Specimen
- Removed prosthesis placed in sterile container
- Duration
- 14-21 days anaerobic after sonication
- Sensitivity for C. acnes
- High — disrupts biofilm, increases yield significantly
- Specimen
- Synovial fluid aspirate
- Duration
- 14-21 days anaerobic
- Sensitivity for C. acnes
- Lower — dry taps common, biofilm not sampled
- Specimen
- Any specimen
- Duration
- 5 days (routine)
- Sensitivity for C. acnes
- POOR — misses the majority of C. acnes
Management Algorithm
Chronic C. acnes PJI (Greater than 3 Months or Indolent)
The goal is to eradicate the infection with component exchange and targeted antibiotic therapy. Culture confirmation comes first: never treat empirically without a tissue or aspirate culture.
Planning. Aspiration with prolonged culture and CT for bone stock, then consent that covers the one-stage and two-stage options, the functional outcomes and the antibiotic duration. Template for both scenarios, because bone loss may dictate the approach intra-operatively.
Surgery. Through a deltopectoral approach extending the prior incision:
- Send tissue samples for prolonged anaerobic culture and all explanted components for sonication, as set out under Investigations
- Thorough irrigation and debridement of all infected tissue
- Decide between one-stage exchange at the same operation and two-stage exchange with spacer placement and delayed reimplantation
One stage or two. One-stage exchange is increasingly favoured for C. acnes PJI when the organism is known pre-operatively, bone stock is adequate, the patient is not immunocompromised and thorough debridement can be achieved. Two-stage exchange remains the gold standard for extensive bone loss, an unclear organism, multi-organism infection or significant soft tissue compromise. Current evidence suggests similar eradication rates for C. acnes with both approaches when appropriate antibiotic therapy is used.
After surgery. IV pathogen-directed therapy for 4-6 weeks based on culture sensitivities; C. acnes is usually sensitive to penicillin G, cephalosporins, clindamycin and vancomycin, and often resistant to metronidazole. In a two-stage revision the antibiotic spacer stays in situ while inflammatory markers are monitored, though they may remain normal, and reimplantation follows at 6-12 weeks: re-aspirate the joint with culture beforehand to confirm eradication, and send multiple tissue samples again at the reimplantation surgery. Some protocols use prolonged oral suppressive antibiotics after reimplantation.
Antibiotic Management
Susceptibility. C. acnes is an anaerobe but is resistant to metronidazole, a classic exam trap; the agents it is usually susceptible to are set out in the table. Rifampicin is used as a combination agent for its biofilm-penetrating properties and never as monotherapy, because resistance develops rapidly.
- Route
- IV
- Duration
- 4-6 weeks
- Notes
- First-line if susceptible; check MIC
- Route
- IV
- Duration
- 4-6 weeks
- Notes
- Alternative if penicillin-susceptible but penicillin not tolerated
- Route
- IV
- Duration
- 4-6 weeks
- Notes
- For penicillin-allergic patients or resistant strains
- Route
- IV then oral
- Duration
- 4-6 weeks total
- Notes
- Good bone penetration; step-down to oral; check inducible resistance
- Route
- Oral
- Duration
- Added to primary agent
- Notes
- Biofilm penetration; ALWAYS use in combination (never monotherapy)
- Route
- Any
- Duration
- N/A
- Notes
- NOT effective against C. acnes — do not use
Complications
- Incidence / Risk
- 5-20 percent after revision
- Risk Factors
- Inadequate debridement, retained biofilm, immunocompromise
- Management
- Repeat revision with aggressive debridement + antibiotics
- Incidence / Risk
- Common presentation of PJI
- Risk Factors
- Biofilm-mediated osteolysis, chronic inflammation
- Management
- Revision arthroplasty with component exchange
- Incidence / Risk
- Variable, may be extensive
- Risk Factors
- Chronic infection, osteolysis, multiple revisions
- Management
- Bone grafting, allograft, or reverse shoulder arthroplasty
- Incidence / Risk
- Common after revision surgery
- Risk Factors
- Multiple operations, capsular scarring, prolonged immobilisation
- Management
- Structured physiotherapy, manipulation under anaesthesia if needed
- Incidence / Risk
- Dependent on agent and duration
- Risk Factors
- Prolonged IV access, rifampicin hepatotoxicity, C. difficile
- Management
- Monitor LFTs, renal function, therapeutic drug levels
Recurrence. The recurrence rate after revision is generally lower than for more virulent organisms, but recurrence may present late and with the same indolent pattern, so long-term clinical and microbiological surveillance is essential. Any recurrence of pain after revision should prompt repeat investigation with aspiration and prolonged culture.
Outcomes and Prognosis
- Eradication Rate
- 85-95 percent (C. acnes specific)
- Functional Outcome
- Good — single surgery, faster recovery
- Key Consideration
- Organism identified, adequate bone stock, thorough debridement
- Eradication Rate
- 85-95 percent
- Functional Outcome
- Good — but requires two surgeries
- Key Consideration
- Extensive bone loss, uncertain organism, immunocompromise
- Eradication Rate
- 60-80 percent
- Functional Outcome
- Good if successful — retains original components
- Key Consideration
- Only for acute infection (under 3 months) with stable implants
- Eradication Rate
- Variable, not curative
- Functional Outcome
- Palliative — suppresses but does not eradicate
- Key Consideration
- Unfit for surgery, minimal symptoms, patient preference
Prognosis. The favourable factors are the organism itself, with its low virulence, one-stage or two-stage revision with appropriate antibiotics, adequate bone stock, a single organism and an immunocompetent patient. The poor ones are multi-organism infection, extensive bone loss requiring allograft, multiple prior revisions, an immunocompromised patient, and inadequate culture that leaves the organism unidentified. Properly managed with surgical revision and targeted antibiotics, C. acnes PJI has better outcomes than Staphylococcus aureus or fungal PJI.
Guidelines, Registries & Global Practice
- C. acnes is the most common organism in shoulder PJI worldwide, with prevalence estimates of 30-60 percent across North American, European, and Australasian series
- Male predominance is consistent across all geographic populations studied
- Intra-operative contamination rates of 15-30 percent during primary shoulder arthroplasty are reported in studies from multiple continents
- Recognition increasing globally as culture techniques (prolonged incubation, sonication) become standard
- Europe: Strong trend toward one-stage exchange for C. acnes PJI, supported by multicentre data from France, Germany, and Scandinavia
- North America: Two-stage exchange remains more commonly performed, though one-stage is gaining acceptance
- Australasia: Individualised approach based on organism, bone stock, and surgeon preference
- Universal principle: Prolonged anaerobic culture (14-21 days) and multiple tissue samples are mandatory regardless of region
- Culture Recommendation
- 14-21 day anaerobic culture; sonication recommended
- Surgical Approach
- Two-stage preferred; one-stage in selected cases
- Antibiotic Duration
- 4-6 weeks IV followed by oral suppression
- Culture Recommendation
- Prolonged culture mandatory for all revision shoulder cases
- Surgical Approach
- One-stage increasingly supported for C. acnes
- Antibiotic Duration
- Minimum 6 weeks pathogen-directed therapy
- Culture Recommendation
- Minimum 14 days anaerobic culture; sonication of explants
- Surgical Approach
- One-stage acceptable for known C. acnes with adequate bone stock
- Antibiotic Duration
- 4-6 weeks IV/oral; rifampicin combination recommended
- Culture Recommendation
- Prolonged culture + sonication standard of care
- Surgical Approach
- One- or two-stage based on individual case factors
- Antibiotic Duration
- 4-6 weeks targeted therapy + clinical monitoring
National joint registries (NJR UK, AOANJRR Australia, AJRR US) capture revision for infection but generally do not distinguish C. acnes from other organisms at the organism-specific level. The evidence base for C. acnes shoulder PJI is predominantly from specialist shoulder unit case series rather than registry data. This means clinical judgement and protocol-driven culture techniques remain more important than population-level data for individual patient management.
In every revision shoulder arthroplasty, regardless of pre-operative suspicion:
- Send a minimum of 5 tissue samples from different periprosthetic sites
- Request 14-21 day anaerobic culture (not standard 5-day)
- Sonicate any explanted components
- Do not dismiss C. acnes growth as contamination without clinical correlation
- Normal CRP and ESR do not exclude C. acnes PJI
These principles apply globally and are not resource-dependent — the culture duration request costs nothing additional.
Controversies & Areas of Uncertainty
Current evidence suggests comparable eradication rates for one-stage and two-stage revision in C. acnes PJI. One-stage avoids a second surgery and may offer faster functional recovery. Two-stage remains traditional for cases with extensive bone loss, uncertain microbiology, or soft tissue compromise. No high-quality RCT exists to definitively guide the choice.
Debate continues about whether a single positive C. acnes culture (of 5 or more samples) represents true infection or contamination. Most authorities now treat it as significant in the appropriate clinical context (male, shoulder, indolent pain), but the threshold for intervention varies between centres.
The debate is genuine, but it is less evidence-free than it sounds - the culture report already contains two discriminators. The first is how fast it grew: true infections turned positive significantly sooner than contaminants (5.5 versus 6.8 days). The second is how many samples grew it: more positive specimens correlated with a shorter time to positivity, and the two travel together. So an organism appearing on day 4 in four of five samples is a very different proposition from one appearing on day 9 in one of five - and neither is well described as "a positive culture". Set against that, know your denominator: in patients with no infection at all, 17% of open shoulder cases and 10.4% of arthroscopic ones still grew something.
Optimal antibiotic duration is not established by RCT evidence. Protocols range from 4 weeks to greater than 12 weeks of combined IV and oral therapy. Some centres use prolonged oral suppression for 6-12 months in high-risk patients. The role of rifampicin combination therapy for C. acnes biofilm is extrapolated from Staphylococcus data.
The MSIS criteria were developed for hip and knee PJI and have poor sensitivity for shoulder infections. Proposed shoulder-specific thresholds (lower synovial WCC, lower neutrophil percentage) have not been universally validated. An international consensus on shoulder-specific PJI diagnostic criteria is still evolving.
MCQ Practice Points
Q: What is the mandatory minimum culture duration for suspected C. acnes shoulder PJI? A: 14-21 days under anaerobic conditions. This is the single most frequently tested fact about this organism - and it is worth knowing WHY the answer is a range rather than a number. Mean time to positivity is about 6.5 days (range 3-10), which is precisely why a routine 5-day plate is discarded before the average true infection has declared itself. The hold is then extended well past that mean as insurance against the slow grower. Crucially, the extra time is not bought at the price of contamination: holding beyond 14 days did not increase the false-positive rate, so there is no diagnostic trade-off to weigh - only laboratory workload.
Q: Can C. acnes PJI be excluded with normal CRP and ESR? A: No. CRP and ESR are frequently normal in C. acnes shoulder PJI. The diagnosis should be suspected clinically (male patient, shoulder arthroplasty, indolent pain) and confirmed by prolonged tissue culture. Normal bloods cannot exclude this infection.
Q: What is the antibiotic of choice for C. acnes PJI? A: Penicillin G (IV) or ceftriaxone/cefazolin if the organism is susceptible. Vancomycin for penicillin-allergic patients. Clindamycin is an alternative with good bone penetration for step-down therapy. Rifampicin is added as a combination agent for biofilm penetration. Metronidazole is NOT effective against C. acnes despite it being an anaerobe — this is a classic trap.
Q: When is DAIR appropriate for C. acnes shoulder PJI? A: Only in acute infection (within 3 months of index surgery or acute haematogenous with less than 3 weeks of symptoms) with stable, well-fixed components. For chronic C. acnes PJI, revision with component exchange (one-stage or two-stage) is required because biofilm on retained implants cannot be eradicated by antibiotics alone.
Q: What is the role of sonication in C. acnes PJI? A: Sonication disrupts the biofilm on explanted prosthetic components, releasing bacteria into the surrounding fluid for culture. It significantly increases the detection rate of C. acnes compared with periprosthetic tissue culture alone. It should be requested whenever components are removed during revision shoulder surgery.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 62-year-old man presents with gradually worsening pain in his right shoulder arthroplasty performed 3 years ago. He has no fever, no wound issues, and examination shows a well-healed scar with reduced range of motion. CRP is 4 mg/L, ESR is 12 mm/hr. X-rays show a radiolucent line around the glenoid component. How would you investigate and manage this?”
“You are performing a revision shoulder arthroplasty for presumed aseptic loosening in a 58-year-old man. You send 6 tissue samples as routine. At 10 days post-operatively, the microbiology lab phones to say 3 of 6 tissue samples have grown Cutibacterium acnes on anaerobic culture. The patient is making good post-operative progress. How do you manage this?”
Microbiology Essentials
- Gram-positive anaerobic bacillus (formerly Propionibacterium acnes)
- Slow-growing: requires 14-21 day anaerobic culture
- Biofilm-forming: adheres to implants, resistant to antibiotics and host immunity
- Skin commensal in deep hair follicles and sebaceous glands of upper trunk
- Resistant to metronidazole — do NOT use as anti-anaerobic cover
Diagnosis
- CRP and ESR are frequently NORMAL — cannot exclude PJI
- Male sex + shoulder arthroplasty + indolent pain = suspect C. acnes
- Prolonged anaerobic culture (14-21 days) of minimum 5 tissue samples is mandatory
- Sonication of explanted components increases sensitivity significantly
- Shoulder-specific synovial WCC thresholds (greater than 1000-2000) are lower than hip/knee
Treatment Algorithm
- Acute (under 3 months) = DAIR + 4-6 weeks targeted antibiotics
- Chronic = one-stage or two-stage revision + 4-6 weeks antibiotics
- Unexpected positive = antibiotics alone if 1 sample, full PJI protocol if 2 or more
- Antibiotics: penicillin G / ceftriaxone / vancomycin / clindamycin + rifampicin combination
- Metronidazole is INEFFECTIVE against C. acnes — classic exam trap
One-Stage vs Two-Stage
- One-stage: known organism, adequate bone stock, thorough debridement achievable
- Two-stage: extensive bone loss, uncertain organism, immunocompromised patient
- Eradication rates similar (85-95 percent) for C. acnes with both approaches
- One-stage gaining favour in European centres for C. acnes specifically
- C. acnes has better outcomes than S. aureus or fungal PJI
Exam Traps
- Normal CRP/ESR does NOT exclude C. acnes shoulder PJI
- Standard 5-day culture will miss C. acnes — must request 14-21 day anaerobic
- Metronidazole does NOT work against C. acnes despite anaerobe classification
- A single positive C. acnes culture may be significant — do not dismiss as contaminant
- C. acnes is the most common shoulder PJI organism, not Staphylococcus
Evidence Base and Key Trials
Propionibacterium acnes: an agent of prosthetic joint infection and colonization
- Retrospective series demonstrating that C. acnes is the most common organism isolated in shoulder PJI
- Normal CRP and ESR in a significant proportion of confirmed C. acnes PJI cases
- Prolonged anaerobic culture (14-21 days) was essential for organism identification
- Male sex was the predominant risk factor
Microbiologic diagnosis of prosthetic shoulder infection by use of implant sonication
- Sonication of removed prosthetic components significantly increased culture yield for P. acnes compared with periprosthetic tissue culture alone
- Biofilm disruption by sonication enabled detection of organisms not isolated from tissue samples
- Recommended as an adjunct to tissue culture in all revision shoulder arthroplasties
One-stage revision for infected shoulder arthroplasty: prospective, observational study of 37 patients
- One-stage exchange with thorough debridement and targeted antibiotics achieved eradication rates comparable to two-stage exchange for shoulder PJI including C. acnes
- Functional outcomes were favourable with a single surgical intervention
- Appropriate for patients with known organism, adequate bone stock, and no severe soft tissue compromise
Propionibacterium acnes: an underestimated pathogen in implant-associated infections
- Comprehensive review of P. acnes pathogenesis, from skin commensal to implant pathogen
- Intra-operative contamination rates during arthroplasty are significant
- Biofilm formation is central to pathogenesis and antibiotic resistance
- Recommended minimum 14-day anaerobic culture for all revision cases
How is infection diagnostic criteria for shoulder periprosthetic joint infection reported in literature: systematic review
- Standard MSIS criteria have poor sensitivity for shoulder PJI, particularly for low-virulence organisms like C. acnes
- Diagnostic criteria for shoulder PJI are inconsistently reported and applied across studies
- Prolonged culture duration and sonication are essential adjuncts for shoulder PJI diagnosis
- Clinical context (male sex, indolent presentation, shoulder arthroplasty) should weigh heavily in diagnosis
Alpha-Defensin and Leukocyte Esterase in the Shoulder - The Actual Numbers
- 105 patients aspirated for painful total shoulder arthroplasty; 24 had PJI, and C. acnes accounted for 15 of them (63%)
- Synovial alpha-defensin ELISA: sensitivity 75% (95% CI 53-90), specificity 96% (90-99), NPV 93%, PPV 86%, accuracy 91%
- Leukocyte esterase: sensitivity only 50% (95% CI 21-79), specificity 87%, accuracy 76%
- Authors' conclusion: both tests were LESS sensitive in the shoulder than previously reported for knee or hip arthroplasty
- They attribute part of the difficulty to the small volume and poor quality of shoulder aspirate
How Often Do Cultures Lie, and Does the Long Hold Make It Worse?
- 95 prospectively enrolled patients having shoulder surgery WITHOUT infection, followed 6 months to confirm none developed; cultures held 28 days
- False-positive culture rate 17.0% after open surgery and 10.4% after arthroscopy
- C. acnes was isolated in 6.4% of the open group and in NONE of the arthroscopic group
- All positive bacterial cultures were reported within 7 days of collection (one mould grew at 26 days)
- Holding cultures beyond 14 days did NOT increase the false-positive rate
Time to Positivity Itself Discriminates Infection from Contaminant
- 34 patients with C. acnes-positive shoulder cultures, before and after introducing a regulated anaerobic incubation chamber
- Mean time to positive culture 6.5 days (range 3-10), falling to 4.9 days (range 2.75-10) with the chamber (p=0.002)
- True infections turned positive significantly FASTER than contaminants - 5.5 versus 6.8 days (p=0.003)
- A greater number of positive specimens correlated with a shorter time to positivity