Quadratus Femoris Space Narrowing | Posterior Hip Pain | MRI QF Oedema
- Ischiofemoral space (IFS) measured on axial MRI between lateral ischial cortex and medial lesser trochanter cortex
- Normal IFS is greater than 25 mm; values less than 15 mm support the diagnosis of impingement when the clinical picture fits
- Quadratus femoris space (QFS) measured between the hamstring tendons and the iliopsoas tendon or lesser trochanter
- MRI shows QF muscle oedema (T2/STIR hyperintensity) as the hallmark finding
- Conservative management is first-line and most patients improve without surgery; the frequently quoted 80 percent figure is conventional rather than evidenced, since the treatment literature is entirely case series and reports
- “Posterior hip/buttock pain reproduced by long-stride walking or extension-adduction-external rotation
- “Differential: piriformis syndrome, hamstring origin tendinopathy, lumbar radiculopathy, FAI
- “Measure IFS and QFS on axial MRI at the level of the quadratus femoris
- “Endoscopic lesser trochanter osteoplasty is the most commonly described operation - but do NOT call it a gold standard: the 2020 systematic review found only case series and case reports, no comparative studies, and a mean follow-up of 8.4 months
Overview and Epidemiology
Ischiofemoral impingement (IFI) is an increasingly recognised but still under-diagnosed cause of posterior hip and deep buttock pain. The space between the ischial tuberosity and the lesser trochanter narrows, and the quadratus femoris muscle, and in some cases the sciatic nerve, is compressed within it. Johnson first described the condition in 1977, but it gained widespread attention only in the MRI era.
Who. Women outnumber men by approximately 3:1. Patients are typically aged 30 to 70, with a peak at 40 to 60, and approximately 25 percent of cases are bilateral. Impingement after total hip arthroplasty accounts for a significant proportion of secondary IFI.
Why it matters. The pain limits walking distance and sitting tolerance, and long-stride walking, stairs and running become difficult. Left undiagnosed it becomes chronic pain, much as FAI did before it was recognised, and a high index of suspicion is needed because the symptoms overlap with piriformis syndrome, hamstring origin tendinopathy and lumbar radiculopathy. It can also be iatrogenic, provoked by the position of the components after a hip replacement.
Pathophysiology
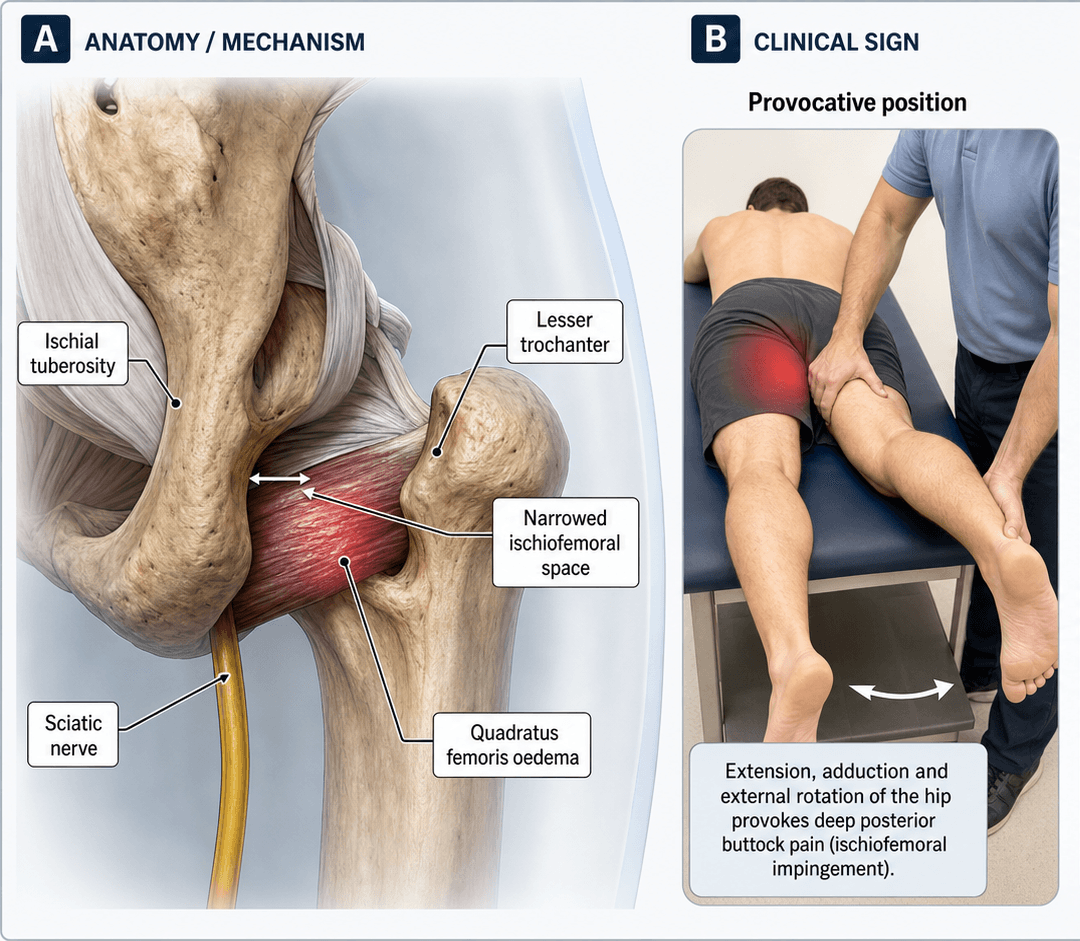
The muscle and its interval. Quadratus femoris runs from the lateral border of the ischial tuberosity to the quadrate tubercle of the proximal femur, acts as an external rotator and adductor of the hip, and normally glides freely in the ischiofemoral space as the hip moves. The sciatic nerve passes immediately posterior to it, which is why a narrowed space can compress the nerve as well as the muscle, and why some patients report radiating, sciatica-like leg pain rather than pure mechanical buttock pain.
The two spaces. The ischiofemoral space (IFS) is the narrowest distance between the lateral cortex of the ischial tuberosity, at the level of the quadratus femoris origin, and the medial cortex of the lesser trochanter. The quadratus femoris space (QFS) is the narrowest distance between the superolateral surface of the hamstring tendons and the posteromedial surface of the iliopsoas tendon or lesser trochanter. The muscle occupies this interval.
What narrowing does. Whether the cause is developmental bony morphology, post-surgical change or a pathological process, a narrowed space traps the muscle against the ischium and lesser trochanter during terminal extension and adduction of the hip. The interval is dynamic, narrowing in extension and adduction, so a measurement on a static scan is a snapshot of one position. Repetitive microtrauma produces muscle oedema and inflammation, and eventually fatty infiltration or tearing.
Why women. A wider pelvis increases the interischial distance and alters the ischiofemoral angle, and a greater average femoral anteversion positions the lesser trochanter closer to the ischium in extension. Women also have less quadratus femoris bulk, so there is less soft-tissue cushion in the interval, and hormonal and gait factors, a wider stance and coxalgic gait patterns, may exacerbate the narrowing.
Classification and Types
Two classifications are in use: by cause, which determines what the treatment must address, and by MRI severity, which guides how aggressive it needs to be.
- Mechanism
- Developmental bony morphology: prominent LT, narrow IFS
- Clinical Context
- Female patient, insidious onset, no prior surgery
- Treatment Implication
- Conservative first; endoscopic osteoplasty if refractory
- Mechanism
- Medialised cup, increased offset, leg-lengthening
- Clinical Context
- Posterior hip pain after total hip arthroplasty
- Treatment Implication
- Consider component revision vs endoscopic decompression
- Mechanism
- Exostosis, malunion of lesser trochanter or ischial fracture
- Clinical Context
- History of proximal femur or pelvis fracture
- Treatment Implication
- Address bony deformity; osteoplasty or excision of exostosis
- Mechanism
- Valgus intertrochanteric osteotomy repositions LT medially
- Clinical Context
- Prior proximal femoral osteotomy (often paediatric)
- Treatment Implication
- Corrective osteotomy vs endoscopic decompression
- Mechanism
- Coxa valga, DDH, femoral retroversion altering IFS
- Clinical Context
- Young patient with hip dysplasia or abnormal morphology
- Treatment Implication
- Address underlying deformity; consider realignment surgery
Primary IFI is the most common form encountered in the exam setting. Secondary causes, particularly post-THA, are increasingly recognised in clinical practice.
Clinical Assessment
History. The pain is posterior, in the hip or deep in the buttock, and rarely radiates below the knee. Long-stride walking, running, prolonged sitting and extension with adduction aggravate it; rest, short strides and hip flexion relieve it. Ask specifically about prior THA, osteotomy or fracture fixation, and in a woman about an insidious onset, since female sex is strongly associated.
Examination. Inspection is usually normal, though the gait may be antalgic or Trendelenburg. Tenderness lies deep in the buttock, distal to the gluteal fold, and is difficult to localise. Terminal extension with adduction hurts; flexion is typically comfortable.
The provocation tests. No single test is pathognomonic, and the diagnosis needs clinical suspicion plus MRI confirmation.
- Long-stride walking test: standing, the patient takes a long stride with the affected leg trailing, which extends and adducts the hip and narrows the ischiofemoral space; reproduction of the characteristic deep posterior hip or buttock pain is positive
- Extension-adduction-external rotation (the IFI test): the supine alternative, passive extension of the hip with adduction and external rotation
- FAIR test (flexion, adduction, internal rotation): often positive because it compresses the quadratus femoris, but more classically associated with piriformis syndrome and deep gluteal syndrome
- Key Discriminating Features
- Pain with extension-adduction, long-stride walking; QF tenderness
- Imaging
- MRI: narrowed IFS, QF oedema
- Critical Test
- Long-stride walking test; measure IFS/QFS on axial MRI
- Key Discriminating Features
- Pain with FAIR manoeuvre; may have sciatic distribution
- Imaging
- MRI: piriformis hypertrophy or anomaly; no QF oedema
- Critical Test
- FAIR test with sciatic nerve latency on EMG
- Key Discriminating Features
- Proximal hamstring pain, worse with sit-to-stand and sprinting
- Imaging
- MRI: hamstring tendon oedema/tear at ischial origin
- Critical Test
- Palpation over ischial tuberosity; resisted knee flexion
- Key Discriminating Features
- Radiculopathic pain below knee, neurological signs
- Imaging
- MRI lumbar spine: disc protrusion, stenosis
- Critical Test
- SLR, neurological exam, EMG/NCS
- Key Discriminating Features
- Groin pain (not buttock), flexion-adduction-internal rotation
- Imaging
- MRI: cam/pincer morphology, labral tear
- Critical Test
- FADIR test positive; FABER may be positive
- Key Discriminating Features
- Sacroiliac region pain, positive FABER and Gaenslen
- Imaging
- MRI/CT SI joints; diagnostic injection
- Critical Test
- SI joint provocation tests; diagnostic block
Deep gluteal syndrome. A common exam framing error treats IFI and deep gluteal syndrome as parallel diagnoses. Deep gluteal syndrome (DGS) is the umbrella term for non-discogenic, extrapelvic entrapment or irritation of the sciatic nerve in the subgluteal space, and IFI is one of its recognised causes, alongside piriformis syndrome, obturator internus/gemelli pathology, proximal hamstring origin pathology, fibrovascular adhesive bands and vascular lesions such as gluteal vein varicosities. Asked for the differential of posterior hip or buttock pain, frame it as DGS causes with IFI inside that family, then separate them by the discriminating manoeuvre (long-stride or extension-adduction for IFI, FAIR for piriformis) and by the MRI finding (quadratus femoris oedema in a narrowed IFS). This is also why a structured deep-gluteal-space MRI and, in selected refractory cases, sciatic nerve assessment are part of the workup.
After a hip replacement. Posterior hip pain after THA is a common exam scenario. Infection, loosening and instability head the differential, but a medialised acetabular cup, excessive femoral offset or leg-lengthening can narrow the ischiofemoral space, and IFI is increasingly recognised. When plain films and the infection workup are negative, consider MRI to measure the IFS; if implant position is the primary driver, management may require component revision.
Investigations
Radiographs first. An AP pelvis, a lateral hip (cross-table or frog) and a Dunn view. Look for a prominent lesser trochanter, coxa valga, evidence of prior osteotomy, exostoses and, after THA, component position (a medialised cup, leg-lengthening). Radiographs cannot measure the IFS directly, which needs cross-sectional imaging, and normal films do not exclude IFI.
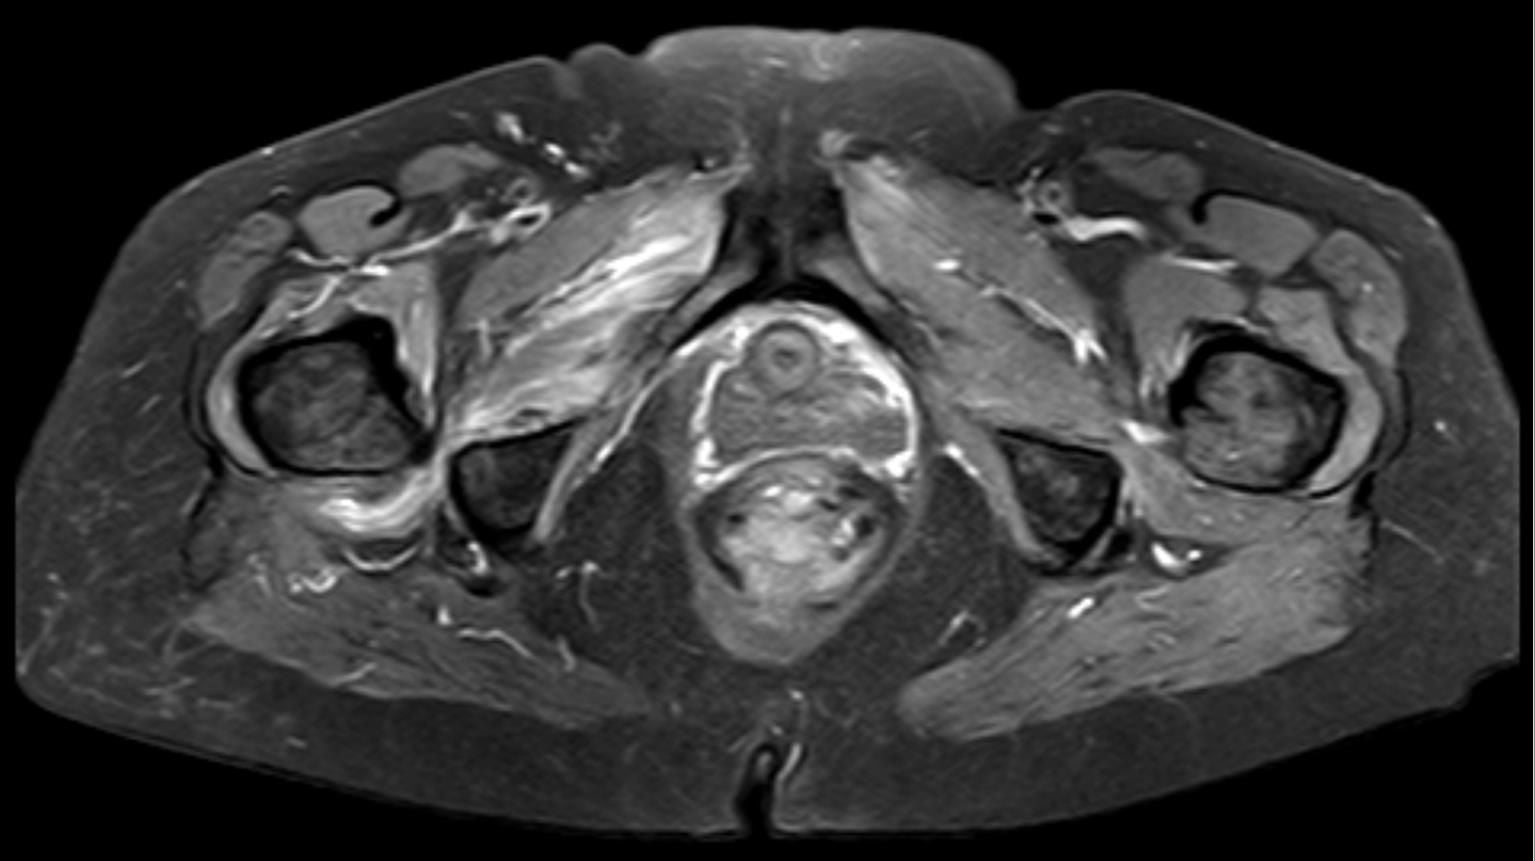
MRI is the gold standard. Axial T1 and T2 fat-saturated or STIR sequences through the hip at the level of the quadratus femoris are essential, because the IFS and QFS are measured on them. Quadratus femoris oedema, T2/STIR hyperintensity in the muscle belly, is the hallmark finding; look also for fatty infiltration, partial tears, hamstring tendon pathology and sciatic nerve signal change.
- Normal Value
- Greater than 25 mm (approximate)
- Impingement Threshold
- Less than 15 mm
- Normal Value
- Greater than 15 mm (approximate)
- Impingement Threshold
- Less than 10 mm
- Normal Value
- Isointense to skeletal muscle
- Impingement Threshold
- Hyperintense (oedema pattern)
Read the numbers with the patient in mind. A measurement below threshold suggests IFI, but only with clinical correlation: asymptomatic narrowing of the IFS has been reported in up to 10 to 15 percent of routine hip MRI studies. The diagnosis is clinical plus radiological, oedema and a narrowed space matching posterior hip pain reproduced by extension-adduction. Treat the patient, not the MRI.
CT. For detailed bony anatomy when planning osteoplasty, with 3D reconstruction for surgical planning. It measures the bony IFS precisely, defines the lesser trochanter morphology and the ischial configuration, and maps the extent of resection needed for endoscopic or open decompression.
Image-guided injection. Corticosteroid and local anaesthetic into the quadratus femoris belly or the ischiofemoral space, under ultrasound or CT guidance, is both a test and a treatment. Pain relief of greater than 50 percent supports IFI as the pain generator, and the relief can last weeks to months, long enough to make rehabilitation possible.
Management Algorithm
First line for every patient. The aim is to reduce compression and inflammation of the quadratus femoris, restore normal gait mechanics and avoid surgery.
Weeks 0 to 4. Activity modification: avoid long-stride walking, running and prolonged hip extension, and use shorter strides. Oral NSAIDs are used for symptomatic relief. Physiotherapy addresses pelvic tilt correction, gait retraining to a shorter stride, and hip abductor and core strengthening, and the patient is taught the mechanism of impingement and why activity modification matters.
Weeks 4 to 8, if no improvement. Arrange the image-guided injection described under Investigations: it settles the inflammation and makes engagement with physiotherapy possible while supporting the diagnosis. Physiotherapy continues, progressing the strengthening and gait retraining.
Months 2 to 6. Assess progress by pain scores, functional improvement and walking distance. A second injection may be considered at 3 months for a partial response, and physiotherapy advances to lumbopelvic stability, eccentric loading and dynamic movement control. For a patient still refractory at 6 months, consider surgical referral for endoscopic decompression.
How well it works. Most patients with primary IFI improve with conservative management. The figure usually quoted is around 80 percent, but it is conventional rather than measured: the entire published treatment literature is case series and case reports with a mean follow-up of 8.4 months, and none of it reports a controlled conservative success rate. The keys are gait modification (shorter strides reduce hip extension and so narrow the IFS less), hip abductor strengthening to improve pelvic stability, and targeted injection to break the inflammatory cycle. Do not rush to surgery in primary IFI: the 80 percent is unproven, and the surgical evidence is weaker still.
Botulinum toxin. Image-guided botulinum toxin (BoNT-A) injection into the quadratus femoris is a non-operative option distinct from corticosteroid. Its mechanism is different: it chemically relaxes (partially denervates) the muscle, which reduces its bulk and resting tone in the ischiofemoral interval and so the dynamic compression that drives symptoms. Like a local anaesthetic block, meaningful relief supports the quadratus femoris as the true pain generator; the effect lasts several months and can bridge the period while gait retraining and abductor strengthening take effect, or temporise in a poor surgical candidate or a patient who wishes to avoid bony decompression. The effect is temporary and may need repeating, transient weakness of the quadratus femoris and external rotators can occur, and accurate ultrasound or CT guidance is essential given the sciatic nerve's immediate posterior relationship to the muscle. In a refractory primary-IFI patient who responded to a diagnostic injection but wants to avoid or delay osteoplasty, it is a legitimate intermediate step between corticosteroid injection and endoscopic decompression.
Complications
What the evidence says, and does not. The 2020 systematic review reported no complications or adverse effects across its 17 included studies, a reassuring signal drawn from small uncontrolled series that are unlikely to capture rare harms. The figures in the table are those reported in case series.
- Incidence
- Reported in case series, rare overall
- Risk Factors
- Endoscopic surgery, proximity of nerve to QF
- Management
- Intra-operative nerve monitoring; identify and protect nerve throughout
- Incidence
- 5 to 10 percent post-operatively
- Risk Factors
- Bony resection, inadequate haemostasis
- Management
- Prophylactic NSAIDs; excision if symptomatic and mature
- Incidence
- Not well quantified; under-recognised
- Risk Factors
- Limited endoscopic visualisation, inadequate resection
- Management
- Intra-operative assessment of IFS widening; post-operative CT if symptoms persist
- Incidence
- Variable; reported in small series
- Risk Factors
- Incomplete resection, ongoing impingement from ischial side
- Management
- Repeat MRI, consider revision surgery or ischioplasty
- Incidence
- If chronic fatty atrophy present pre-operatively
- Risk Factors
- Long duration of symptoms prior to surgery
- Management
- Rehabilitation may be prolonged; muscle may not fully recover
Nerve identification and protection is the single most important surgical consideration. Document a neurological examination (dorsiflexion, plantarflexion, sensation in the foot) pre-operatively and monitor it post-operatively; any new neurological deficit requires urgent evaluation.
Outcomes and Prognosis
- Expected Outcome
- Most improve significantly
- Time to Improvement
- 6 to 12 weeks with physiotherapy and injection
- Long-term Prognosis
- Good if activity modification maintained; recurrence possible
- Expected Outcome
- Good to excellent outcomes in case series
- Time to Improvement
- 3 to 4 months for full recovery
- Long-term Prognosis
- Favourable when decompression adequate and nerve uninjured
- Expected Outcome
- Variable; depends on revision complexity
- Time to Improvement
- 3 to 6 months for full recovery
- Long-term Prognosis
- Good if implant position corrected; risk of recurrent instability
- Expected Outcome
- Functional improvement likely; full muscle recovery uncertain
- Time to Improvement
- 6 months or more for rehabilitation
- Long-term Prognosis
- Residual weakness possible; pain relief generally achievable
Prognosis. The best outcomes follow a short duration of symptoms, primary IFI, a quadratus femoris preserved on MRI without fatty atrophy, a good response to injection and compliance with rehabilitation. The outlook is poorer with long-standing symptoms and fatty atrophy of the muscle, post-THA IFI with severe component malposition, failed prior surgery, and coexisting lumbar or intra-articular pathology.
Guidelines, Registries & Global Practice
- IFI is reported worldwide with female predominance across all ethnicities
- Post-THA IFI is increasingly recognised as implant design and positioning evolve
- Underdiagnosis is global: many patients are labelled with piriformis syndrome or non-specific buttock pain before the correct diagnosis
- No registry data specifically for IFI; most evidence comes from case series and institutional reviews
- High-resource: MRI-first approach with axial IFS/QFS measurement; image-guided injection widely available; endoscopic surgery in specialist centres
- Limited-resource: Diagnosis based on clinical pattern and response to injection; CT may substitute for MRI if unavailable; open decompression more common
- Universal principle: Diagnosis requires clinical suspicion PLUS imaging correlation; conservative management is first-line regardless of setting
- Surgery: Concentrated in tertiary hip arthroscopy centres; outcomes vary with surgeon experience
- Diagnosis Emphasis
- Clinical suspicion + MRI IFS/QFS measurement + QF oedema; injection for diagnostic confirmation
- Acute Treatment
- Activity modification, gait retraining, hip abductor strengthening, image-guided injection
- Surgery / Decompression
- Endoscopic lesser trochanter osteoplasty for refractory cases; nerve protection mandatory
- Diagnosis Emphasis
- MRI with axial sequences; rule out lumbar spine, intra-articular, and piriformis pathology first
- Acute Treatment
- Conservative care for minimum 3 to 6 months before considering surgery
- Surgery / Decompression
- Endoscopic preferred over open; component revision for post-THA IFI if implant malpositioned
- Diagnosis Emphasis
- Posterior hip pain algorithm; IFI considered after lumbar and SIJ excluded
- Acute Treatment
- Physiotherapy-led rehabilitation; image-guided injection for diagnostic and therapeutic purposes
- Surgery / Decompression
- Specialist hip arthroscopy centres; MDT discussion for post-THA cases
- Diagnosis Emphasis
- Cross-sectional imaging (MRI/CT) to define bony anatomy and soft-tissue involvement
- Acute Treatment
- Standard non-operative protocol; injection under imaging guidance
- Surgery / Decompression
- Endoscopic or open osteoplasty with attention to sciatic nerve anatomy
There is no dedicated joint registry or outcome database for ischiofemoral impingement. The evidence base consists entirely of retrospective case series (level 4 evidence) and expert opinion. No randomised controlled trials have been published comparing surgical to non-surgical management or endoscopic to open decompression. Treatment recommendations are therefore principle-based: diagnose with clinical plus MRI correlation, treat conservatively first, and reserve surgery for refractory cases with careful sciatic nerve protection.
Record in every suspected IFI presentation:
- Clinical examination findings including long-stride walking test result
- MRI measurements: IFS and QFS values in millimetres on axial sequences
- Presence or absence of QF muscle oedema on T2/STIR
- Response (or lack thereof) to image-guided injection
- Duration of conservative management before considering surgical referral
IFI is an evolving diagnosis. Documenting objective MRI measurements and clinical response to injection strengthens the diagnostic pathway and protects against missed or delayed diagnosis.
Controversies & Areas of Uncertainty
The IFS less than 15 mm and QFS less than 10 mm cut-offs are derived from case-control studies, not population-based normative data. Dynamic narrowing occurs with hip extension, meaning static MRI may underestimate or overestimate the clinical significance of measured narrowing. Some authors argue for a spectrum rather than binary thresholds.
Up to 10 to 15 percent of asymptomatic individuals have IFS measurements below the diagnostic threshold on MRI. This raises the question of whether narrowing alone is sufficient for diagnosis or whether QF oedema and clinical correlation should be mandatory requirements. Most authorities now require all three: clinical symptoms, MRI narrowing, and QF signal change.
Lesser trochanter osteoplasty is the most commonly described surgical approach, but some authors advocate ischial-sided decompression (ischioplasty) or combined procedures. There are no comparative studies. The choice is currently based on which side contributes more to the narrowing and surgeon preference.
Post-THA IFI is recognised but its true incidence is unknown. Some argue it is under-diagnosed as a cause of unexplained post-arthroplasty buttock pain, while others caution against over-attributing pain to IFI when component issues (loosening, infection, instability) have not been fully excluded. A systematic approach to post-THA pain evaluation should include IFI in the differential.
MCQ Practice Points
Q: What muscle is primarily compressed in ischiofemoral impingement? A: The quadratus femoris muscle, which runs from the lateral border of the ischial tuberosity to the quadrate tubercle of the proximal femur. It is trapped in the narrowed space between the ischium and the lesser trochanter, producing its characteristic oedema pattern on MRI.
Q: What are the MRI diagnostic criteria for ischiofemoral impingement? A: Ischiofemoral space (IFS) less than 15 mm measured on axial MRI between the lateral ischial cortex and the medial lesser trochanter cortex, quadratus femoris space (QFS) less than 10 mm, and quadratus femoris muscle oedema on T2/STIR sequences. Clinical correlation is essential as asymptomatic narrowing exists.
Q: How do you distinguish ischiofemoral impingement from piriformis syndrome clinically? A: Both cause deep buttock pain. IFI is worsened by extension-adduction (long-stride walking) and shows QF oedema on MRI. Piriformis syndrome is worsened by flexion-adduction-internal rotation (FAIR test), may have sciatic nerve symptoms, and shows piriformis hypertrophy or anomaly on MRI. The key discriminator is the MRI finding: QF oedema points to IFI, piriformis abnormality points to piriformis syndrome.
Q: What is the management algorithm for primary ischiofemoral impingement? A: Step 1: Activity modification (shorter strides) + NSAIDs + physiotherapy (gait retraining, hip abductor strengthening). Step 2 (if no improvement at 4 to 6 weeks): Image-guided corticosteroid injection into the QF. Step 3 (if refractory at 3 to 6 months): Endoscopic lesser trochanter osteoplasty. Most patients improve with conservative management alone - and note that the surgical step rests on case series with a mean follow-up under 9 months, so the threshold for operating should be high.
Q: What is the most important structure at risk during endoscopic decompression for IFI? A: The sciatic nerve, which courses immediately posterior to the quadratus femoris muscle. It must be identified and protected throughout the procedure. Pre-operative neurological examination should be documented, and any new post-operative deficit (particularly foot drop from common peroneal nerve involvement) requires urgent evaluation.
Q: What surgical factors predispose to post-THA ischiofemoral impingement? A: Acetabular cup medialisation (narrows the IFS by moving the centre of rotation medially), excessive femoral offset (positions the lesser trochanter closer to the ischium), and leg-lengthening (alters the ischiofemoral relationship). Component revision should be considered if malposition is the primary driver rather than osteoplasty alone.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 42-year-old woman presents with a 6-month history of deep left buttock pain, worse with long-stride walking and relieved by rest and shorter strides. She has no prior hip surgery. Examination reveals tenderness in the deep buttock, pain reproduced by passive extension-adduction of the hip, and no neurological deficit. Lumbar spine examination is unremarkable. Her GP has ordered a lumbar MRI which was normal. What is your diagnosis and how would you investigate?”
“A 68-year-old woman presents with deep right buttock pain 14 months after an uncomplicated right total hip arthroplasty. The hip is stable, wound healed, and infection markers are normal. Radiographs show a well-fixed cementless prosthesis with the acetabular cup appearing slightly medialized compared to the contralateral native hip. She describes pain with walking that is relieved by shorter strides. Examination shows a positive long-stride walking test reproducing her buttock pain and no neurological deficit. How would you manage this?”
Key Anatomy
- IFS = narrowest distance between lateral ischial cortex and medial lesser trochanter cortex
- QFS = narrowest distance between hamstring tendons and iliopsoas/LT soft-tissue borders
- Quadratus femoris occupies the ischiofemoral interval; compressed when space narrows
- Sciatic nerve lies immediately posterior to QF (key surgical landmark)
Diagnosis
- Clinical: posterior hip or deep buttock pain worsened by long-stride walking and extension-adduction
- MRI: IFS less than 15 mm, QFS less than 10 mm on axial sequences at QF level
- MRI hallmark: QF muscle oedema (T2/STIR hyperintensity); may see fatty infiltration in chronic cases
- Image-guided injection into QF is both diagnostic (pain relief confirms source) and therapeutic
Differential Diagnosis
- Piriformis syndrome: FAIR test positive, piriformis anomaly on MRI, no QF oedema
- Hamstring origin tendinopathy: ischial tuberosity tenderness, tendon tear on MRI
- Lumbar radiculopathy: radicular pain below knee, neurological signs, abnormal lumbar MRI
- Post-THA IFI: consider component medialisation, increased offset, leg-lengthening
Treatment Algorithm
- Conservative first: activity modification (shorter strides), NSAIDs, physiotherapy (gait retraining)
- Injection (4 to 6 weeks): image-guided corticosteroid into QF for diagnostic and therapeutic value
- Endoscopic osteoplasty (3 to 6 months refractory): lesser trochanter resection with nerve protection
- Post-THA: consider component revision if implant malposition is the primary driver
Surgical Pearls
- Endoscopic lesser trochanter osteoplasty is the preferred approach for primary IFI
- Sciatic nerve identification and protection is mandatory (runs directly posterior to QF)
- Preserve iliopsoas tendon attachment during osteoplasty to maintain hip flexion power
- Heterotopic ossification prophylaxis should be considered post-operatively
Exam Traps
- Do NOT diagnose IFI on MRI alone (asymptomatic narrowing exists in 10 to 15 percent)
- Do NOT confuse with piriformis syndrome (different anatomy, different MRI findings)
- Do NOT rush to surgery without 3 to 6 months of conservative management (most respond)
- Do NOT forget to check sciatic nerve function pre- and post-operatively
Evidence Base and Key Trials
Ischiofemoral impingement: evaluation with new MRI parameters and assessment of their reliability
- Proposed standardised MRI measurement of the ischiofemoral space (IFS) and quadratus femoris space (QFS) on axial sequences
- Demonstrated excellent inter- and intra-observer reliability for IFS and QFS measurements
- Patients with IFI had significantly narrowed IFS (mean approximately 13 mm) compared to controls (mean approximately 26 mm)
- QF muscle oedema on T2/STIR sequences was the most consistent soft-tissue finding
Diagnosis and 2-year outcomes of endoscopic treatment for ischiofemoral impingement
- Endoscopic lesser trochanter osteoplasty performed safely with good clinical outcomes at 2-year follow-up
- Surgical technique described in detail including patient positioning, portal placement, and nerve protection
- Outcome measures (modified Harris Hip Score, pain scores) showed significant improvement post-operatively
- No sciatic nerve injuries reported in the series with meticulous nerve identification technique
Ischiofemoral impingement syndrome: a meta-analysis
- Pooled 217 IFI hip MRIs against 140 asymptomatic control hips - a purely RADIOLOGICAL meta-analysis. It reports no treatment data of any kind
- Ischiofemoral space: 14.91 +/- 4.8 mm in IFI versus 26.01 +/- 7.98 mm in controls. Quadratus femoris space: 9.57 +/- 3.7 mm versus 15.97 +/- 6.07 mm (both p less than 0.0001)
- IFS cutoff of 15 mm or less: sensitivity 76.9%, specificity 81.0%, overall accuracy 78.3%. QFS cutoff of 10 mm or less: sensitivity 78.7%, specificity 74.1%, overall accuracy 77.1%
- READ THE STANDARD DEVIATIONS, NOT JUST THE MEANS. An IFI mean of 14.91 with an SD of 4.8 means a large minority of genuinely affected hips measure ABOVE the 15 mm threshold, and the control spread reaches down toward it. The thresholds are useful and roughly four-in-five accurate - they are not a rule-in or rule-out test
- The authors' own conclusion is conditional: IFI 'can be accurately diagnosed with MRI IN CONJUNCTION WITH CLINICAL FINDINGS'
Treatment strategies for ischiofemoral impingement: a systematic review
- 17 papers met inclusion. NO comparative studies were found - every single included study was a case series or case report
- Treatment split: non-surgical (injection, prolotherapy) in 8 studies (47%), endoscopic surgery in 5 (29%), open surgery in 4 (24%). Mean age 41 years
- MEAN FOLLOW-UP WAS 8.4 MONTHS (range 2 weeks to 2.3 years) - too short to describe any surgical option as durable
- No complications or adverse effects were reported across the whole review - a reassuring signal, but one drawn from small uncontrolled series that are unlikely to capture rare harms
- The authors state plainly that there are NO comparative studies to assess the superiority of one technique over another, and call for randomised trials
Extra-articular hip impingement: a systematic review examining operative treatment of psoas, subspine, ischiofemoral, and greater trochanteric/pelvic impingement
- Systematic review covering all extra-articular hip impingement including IFI, confirming the increasing recognition of these conditions
- Endoscopic decompression for IFI shows promising short-term outcomes with low complication rates
- Post-THA IFI is an important iatrogenic subset requiring component position assessment
- Emphasised that accurate diagnosis requires clinical suspicion plus MRI correlation, not imaging alone