Granulomatous Disease - Joints, Muscle, Bone
- Sarcoidosis is a multisystem non-caseating granulomatous disease; its MSK forms are an acute or chronic arthropathy, a granulomatous myopathy, osseous sarcoidosis and the indirect skeletal effects.
- Löfgren syndrome (typically bilateral ankle arthritis or periarthritis, erythema nodosum, bilateral hilar lymphadenopathy) is usually self-limiting with a good prognosis; chronic arthritis is less common and uncommonly deforming or destructive.
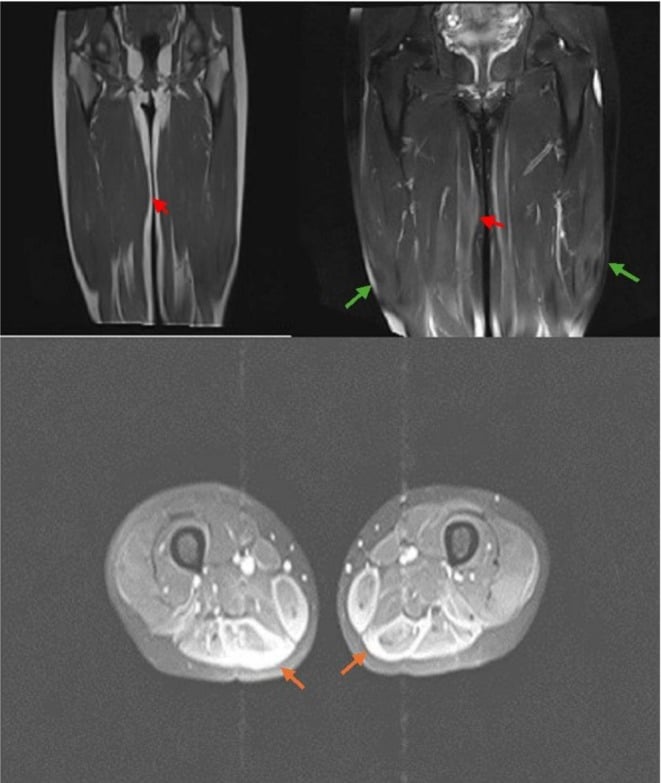
- Granulomatous myopathy is common pathologically but most often clinically silent; MRI should be considered for unexplained musculoskeletal complaints in sarcoidosis.
- Osseous sarcoidosis classically gives lace-like lytic or cystic phalangeal lesions of the hands and feet, frequently asymptomatic; the differential of a lytic phalangeal lesion must be considered.
- Granuloma macrophages produce calcitriol, causing hypercalcaemia and hypercalciuria; patients are at increased risk of osteoporosis and fracture, so use vitamin D cautiously.
- Treat the systemic disease: Löfgren symptomatically (NSAIDs, sometimes colchicine or a short steroid course); chronic arthritis, myopathy and significant systemic disease with corticosteroids and steroid-sparing agents (methotrexate; anti-TNF if refractory).
- Löfgren's good prognosis does not extend to sarcoidosis as a whole: of 640 patients, 42.6% remitted spontaneously and 10.4% on treatment, but 28.1% became chronic (8.5% with moderate-to-severe organ damage).
- Age over 40, pulmonary involvement on chest radiograph, splenic involvement and needing treatment predicted a chronic course; Löfgren syndrome and mediastinal lymphadenopathy predicted a good one (Löfgren adjusted OR 0.15 for chronicity).
- Löfgren can recur after complete remission, described up to more than 17 years later, usually again as Löfgren syndrome and usually with a good outcome; arrange long-term follow-up, recognising the evidence is a 17-patient series that gives no recurrence rate.
- “Sarcoid = non-caseating granulomatous multisystem disease. ACUTE arthropathy = LOFGREN syndrome (ankle periarthritis + erythema nodosum + bilateral hilar lymphadenopathy) - self-limiting, GOOD prognosis.
- “Osseous sarcoid = LACE-LIKE lytic/cystic phalangeal lesions (hands/feet, often asymptomatic). Granulomatous myopathy is usually clinically SILENT - MRI is sensitive.
- “Indirect effects: macrophage calcitriol → HYPERCALCAEMIA/hypercalciuria (stones), osteoporosis, fracture risk (be cautious with vitamin D). Treat the systemic disease (steroids +/- methotrexate/anti-TNF).
- “OUTCOMES (n = 640, mean 112 months): 42.6% spontaneous remission + 10.4% on treatment, but 28.1% CHRONIC (8.5% severe organ damage); 43.4% needed steroids. Chronic predicted by age over 40, pulmonary involvement, splenic involvement, needing treatment; Lofgren protective (adjusted OR 0.15).
The Musculoskeletal Manifestations
Sarcoidosis is a multisystem non-caseating granulomatous disease, and its musculoskeletal manifestations vary widely in how they present and how they respond to treatment. The forms to know are an acute or chronic arthropathy, a granulomatous myopathy, osseous sarcoidosis, and the indirect effects of the disease on the skeleton.
Acute arthropathy: Löfgren syndrome. The classic acute form is a sarcoid arthritis or periarthritis of the ankles, occurring as part of Löfgren syndrome. It is usually self-limiting with a good prognosis, and the triad is a high-yield exam association:
- Ankle arthritis or periarthritis, typically bilateral
- Erythema nodosum
- Bilateral hilar lymphadenopathy
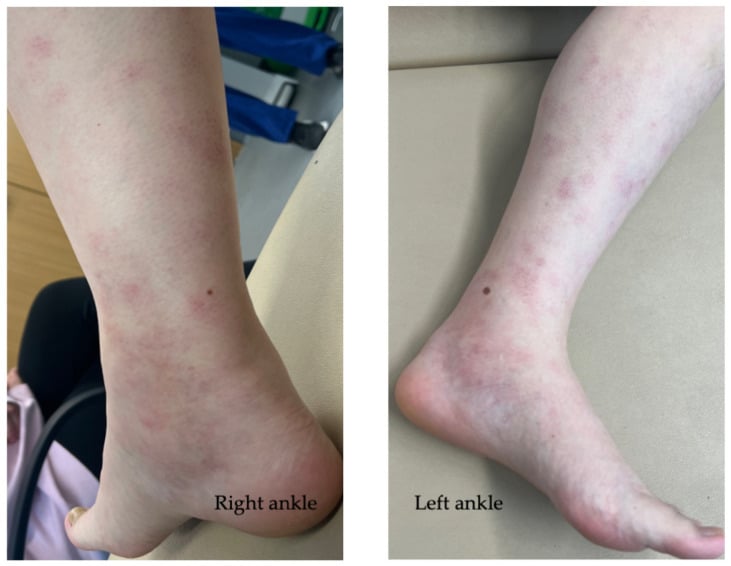
Chronic arthritis. A chronic arthritis is less common. It is a granulomatous synovitis that can be oligo- or polyarticular and is occasionally deforming or destructive, as in dactylitis with bone involvement, and the chronic articular disease can be subtle.
Granulomatous myopathy. Muscle involvement is common pathologically but most often clinically silent. It may also present acutely, as a chronic proximal myopathy mimicking polymyositis, or as a nodular form. MRI shows the lesions, which are frequently missed clinically, and muscular sarcoidosis can appear on MRI as a focal intramuscular mass with a dark-star sign.
Osseous sarcoidosis. Bone involvement classically produces lace-like (reticular) lytic or cystic lesions in the phalanges of the hands and feet, often beneath cutaneous lesions and frequently asymptomatic. The axial skeleton and large bones can also be affected.
Indirect skeletal effects. Activated macrophages in the granulomas produce calcitriol (1,25-dihydroxyvitamin D), causing hypercalcaemia and hypercalciuria, with nephrolithiasis or nephrocalcinosis. Patients are also at increased risk of osteoporosis and fracture.
How Sarcoidosis Is Diagnosed
A diagnosis of exclusion. There is no single diagnostic test. Sarcoidosis requires:
- A compatible clinical and radiological picture
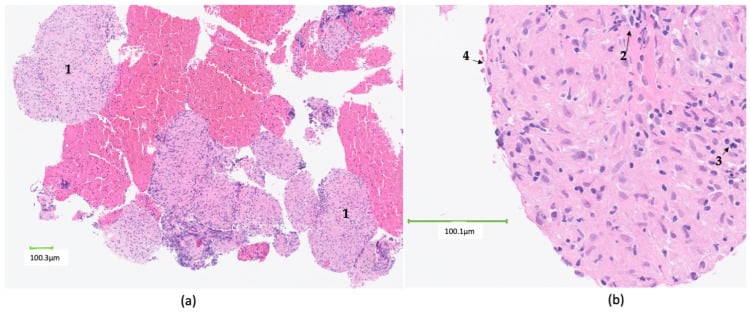
- Non-caseating epithelioid granulomas on biopsy
- Exclusion of other granulomatous causes: above all mycobacterial (TB) and fungal infection, with negative stains and cultures, and also berylliosis, granulomatous drug reactions and lymphoma
The histology. The granulomas contain epithelioid histiocytes and multinucleate giant cells, sometimes with asteroid and Schaumann bodies, which are non-specific.
When biopsy can be omitted. Löfgren syndrome is characteristic enough that it is often diagnosed clinically without biopsy, the main exception to the biopsy rule.
Serum ACE and supporting tests. Serum angiotensin-converting enzyme (ACE), produced by the epithelioid cells of the granuloma, is often raised but is neither specific nor sensitive, and is better for monitoring activity than for diagnosis. The other supporting findings are hypercalcaemia or hypercalciuria, lymphopenia, raised inflammatory markers, and the chest finding of bilateral hilar lymphadenopathy.
Osseous Sarcoidosis: The Jüngling Pattern and Its Differential
The eponym. The lace-like phalangeal pattern is osteitis multiplex cystoides of Jüngling (Perthes-Jüngling). It often underlies lupus pernio of the skin and dactylitis.
The radiographic patterns. The lace-like form is the classic appearance, but it is not the only one:
- Lace-like or reticular trabecular resorption in the middle and distal phalanges, often with an intact cortex
- Cystic, "punched-out" lucencies
- Permeative or destructive change, with or without acro-osteolysis and pathological fracture
- Rarely, sclerotic lesions in the axial skeleton, which can mimic metastases
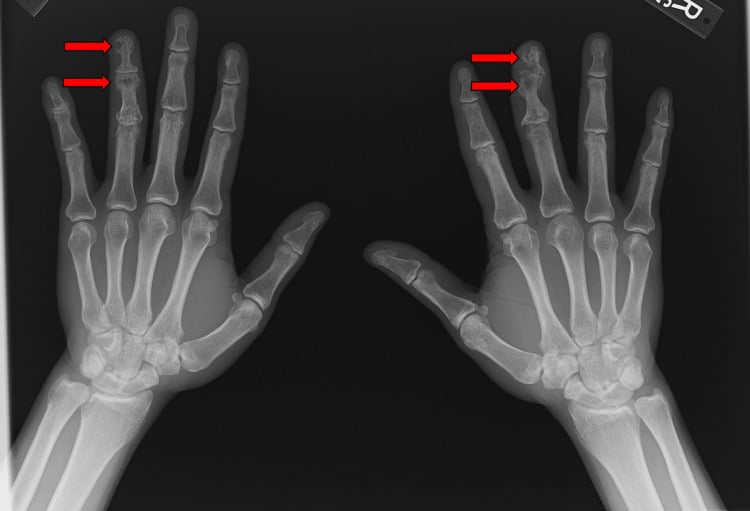
The differential of a lytic phalangeal lesion. The appearance is characteristic, but a lytic phalangeal lesion has its own differential, and each candidate should be weighed against the systemic sarcoid picture:
- Enchondroma, the commonest: chondroid and expansile
- Infection: tuberculous dactylitis ("spina ventosa")
- Gout tophus
- Glomus tumour
- Epidermoid inclusion cyst
- Brown tumour of hyperparathyroidism
- Metastasis
Imaging, Differential & Management
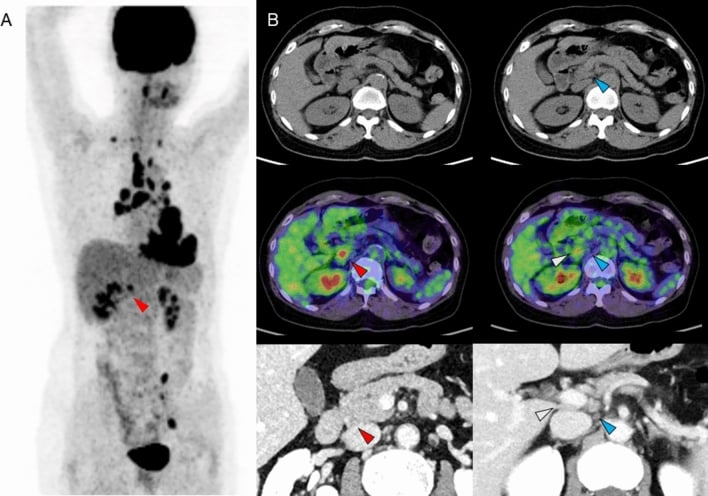
Imaging. Radiographs show the lace-like phalangeal lesions. MRI is sensitive for the often-silent articular and muscular lesions, and MRI and PET detect marrow lesions that radiographs miss. That sensitivity is expert recommendation from narrative reviews: no sensitivity or specificity figure for MRI in musculoskeletal sarcoidosis has been published.
The wider differential. Beyond the lytic phalangeal lesion, the differential of chronic sarcoid arthritis includes rheumatoid arthritis and spondyloarthropathy, and that of the myopathy includes polymyositis. Correlate with the systemic picture, and biopsy where needed.
Management follows the systemic disease. Musculoskeletal sarcoidosis is generally treated as part of the systemic disease, with the rheumatology or respiratory team.
Acute Löfgren arthropathy. Treatment is symptomatic, with NSAIDs and sometimes colchicine or a short steroid course, and the arthropathy usually resolves.
Chronic disease. Chronic arthritis, myopathy and significant systemic disease are treated with corticosteroids and steroid-sparing agents: methotrexate, and anti-TNF biologics in refractory disease.
Bone health. Treat hypercalcaemia, use vitamin D supplementation cautiously, and address osteoporosis and fracture risk.
Löfgren arthropathy has a good prognosis and should generally be managed symptomatically rather than committed to prolonged immunosuppression. Much of the rest of MSK sarcoid is occult, so MRI should be used to evaluate unexplained osteoarticular complaints when standard radiographs are negative.
What Actually Happens: Outcomes in 640 Patients Over 40 Years
"Sarcoidosis often resolves spontaneously" is true but incomplete, and the incomplete version is the one that gets candidates into trouble. A 640-patient cohort was followed at a single Spanish tertiary centre from 1976 to 2015, with follow-up in 587 patients over a mean of 112 months:
- 42.6% had spontaneous remission and a further 10.4% remitted under treatment, so a little over half resolve
- 28.1% evolved to chronic sarcoidosis, 19.6% with mild disease but 8.5% with moderate-to-severe organ damage, and another 18.9% still had active disease when the study closed
- 43.4% required corticosteroids and 7.7% needed steroid-sparing agents
"Usually self-limiting" describes Löfgren syndrome, not sarcoidosis as a whole.
What predicts a chronic course. On multivariate analysis, age over 40 at diagnosis, pulmonary involvement on chest radiograph, splenic involvement and needing treatment were associated with chronic disease.
What predicts a good one. Löfgren syndrome and mediastinal lymphadenopathy were indicators of a good outcome. The optimism about Löfgren is therefore well founded, and it is Löfgren specifically, not acute presentation in general, that carries the favourable prognosis. A separate Portuguese study comparing 110 chronic with 129 resolved patients put a number on it: Löfgren syndrome had an adjusted odds ratio of 0.15 for progressing to chronicity, against 2.68 for extrapulmonary involvement and 1.06 per year of age.
Löfgren syndrome genuinely carries a good prognosis, but it can recur years after complete remission. In a series of 17 patients with 24 recurrences collected over 28 years, the disease-free interval between resolution and the first recurrence ranged from 10 months to more than 17 years, and most recurrences again presented as Löfgren syndrome. Outcomes remained good, with 14 of the 17 in complete remission at last review and only one becoming chronic, but the authors recommend long-term follow-up even in patients whose disease is inactive. All but one of the 17 patients were women. With only 17 patients this describes a rare phenomenon, not a recurrence rate, and it cannot tell you how often relapse occurs.
Mnemonics & Memory Aids
GRAIN
Hook:GRAIN: Granulomatous, lofgRen arthropathy, Asymptomatic bone/silent myopathy, Indirect hypercalcaemia/osteoporosis, Need systemic treatment.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A patient has bilateral ankle swelling, painful red shin nodules and bilateral hilar lymphadenopathy on chest radiograph. What is this, and what is the prognosis?”
Arthropathy
- Acute = Lofgren syndrome (ankle periarthritis + erythema nodosum + bilateral hilar lymphadenopathy)
- Lofgren is usually self-limiting with a good prognosis (adjusted OR 0.15 for chronicity)
- But it can recur after complete remission, up to more than 17 years later - follow up long term
- Chronic arthritis less common; occasionally deforming/destructive
Outcomes (n = 640, mean 112 months)
- 42.6% spontaneous remission + 10.4% remission on treatment - just over half resolve
- 28.1% evolve to chronic sarcoidosis; 8.5% with moderate-to-severe organ damage
- 18.9% still active at study closure; 43.4% required corticosteroids
- Chronic predicted by: age over 40, pulmonary involvement on CXR, splenic involvement, needing treatment
- Good outcome predicted by: Lofgren syndrome and mediastinal lymphadenopathy
- Cohort was 95.8% Caucasian at one tertiary centre - do not transfer the proportions unchanged
Muscle & bone
- Granulomatous myopathy - usually clinically silent (MRI sensitive)
- Osseous: lace-like lytic/cystic phalangeal lesions (hands/feet, often asymptomatic)
- Axial/large-bone lesions also occur
Indirect effects
- Calcitriol from granulomas → hypercalcaemia + hypercalciuria (stones)
- Osteoporosis and increased fracture risk
- Be cautious with vitamin D supplementation
Management
- Acute Lofgren: symptomatic (NSAIDs +/- colchicine/short steroid course)
- Chronic/systemic: corticosteroids + methotrexate (anti-TNF if refractory)
- MRI for unexplained osteoarticular complaints; treat as part of systemic disease
Evidence & Key Studies
Multidisciplinary approach and long-term follow-up in 640 consecutive patients with sarcoidosis: a 40-year cohort at a tertiary centre in Barcelona
- 640 consecutive patients diagnosed 1976-2015 on a prospective protocol; 68.4% female, mean age 43.3 (SD 13.8), 95.8% Caucasian. Follow-up achieved in 587 (91.7%) over a mean of 112.4 months (SD 98.3, range 6.4-475) - genuinely long-term, which most sarcoidosis series are not.
- OUTCOMES: spontaneous remission in 250 (42.6%), remission under treatment in 61 (10.4%), still active at study closure in 111 (18.9%), and evolution to CHRONIC sarcoidosis in 165 (28.1%) - of whom 115 (19.6%) had mild disease and 50 (8.5%) moderate-to-severe organ damage. Corticosteroids were needed by 43.4% and steroid-sparing agents by 7.7%.
- Predictors of chronic disease on multivariate analysis: age over 40 at diagnosis, pulmonary involvement on chest radiograph, splenic involvement, and the need for treatment. LOFGREN SYNDROME and mediastinal lymphadenopathy were indicators of GOOD outcome.
- Erythema nodosum was the commonest extrapulmonary manifestation at 39.8%, with specific cutaneous lesions in 20.8%; 91.2% had intrathoracic involvement on chest radiograph at diagnosis and most had normal pulmonary function.
- Limitations: single tertiary referral centre and 95.8% Caucasian, so the proportions do not transfer to populations where sarcoidosis is more severe - notably African-ancestry patients, in whom the disease is well recognised to run a worse course. Referral bias inflates severe phenotypes; the 'still active' group is censored by the study end rather than truly resolved.
Pulmonary sarcoidosis: prognostic factors at diagnosis in patients from the north of Portugal
- Compared 110 patients with a chronic course against 129 whose disease resolved, seeking prognostic factors identifiable at diagnosis.
- In the final logistic regression, LOFGREN SYNDROME was strongly protective against chronicity with an adjusted odds ratio of 0.15, while EXTRAPULMONARY INVOLVEMENT carried an adjusted odds ratio of 2.68 and each year of age 1.06.
- Chronic disease was also positively associated with lung function impairment, radiologic stage II, a lower lymphocyte CD4/CD8 ratio and extrapulmonary disease. Asthenia, like Lofgren syndrome, was protective.
- Limitations: retrospective, single region, and the groups were defined by outcome rather than followed from a common starting point - so these are associations available at diagnosis, not a validated prediction rule. No confidence intervals are given in the abstract for the odds ratios.
Recurrent sarcoidosis: a study of 17 patients with 24 episodes of recurrence
- A SMALL DESCRIPTIVE SERIES, not a frequency study: 17 patients with 24 recurrences identified over 28 years at one hospital. It shows that late recurrence happens; it cannot say how often.
- Recurrence was defined strictly - reappearance after complete resolution of clinical, radiographic and other activity markers, maintained at least 3 years without therapy. The disease-free interval before first recurrence ranged from 10 months to more than 17 years.
- All but one of the 17 patients were women. All but one presented as Lofgren syndrome at onset, and 17 of the recurrences were again Lofgren syndrome.
- Outcome remained good: at last review 14 were in complete remission, 2 had recent activity and only 1 developed chronic sarcoidosis - supporting the teaching that acute sarcoid arthropathy does well even when it relapses, but justifying long-term follow-up rather than discharge.
Musculoskeletal manifestations of sarcoidosis
- A NARRATIVE REVIEW, not a study - it summarises the field and supplies no cohort, denominator or outcome data of its own.
- Sarcoidosis can involve the joints (acute arthritis - mostly self-resolving - and, less commonly, chronic arthritis that may deform/destroy the joint), the muscles (categorised by clinical presentation), and the bones (with around half of patients with bone lesions remaining asymptomatic).
- Indirect skeletal effects include osteoporosis, increased fracture risk, hypercalcaemia and hypercalciuria, contributed to by elevated calcitriol.
- Sarcoidosis can also be associated with small-, medium- and large-vessel vasculitis, and distinguishing sarcoid vasculitis from coexisting pure vasculitis can be difficult.
Radiologic manifestations of musculoskeletal sarcoidosis
- A NARRATIVE REVIEW of imaging findings - its recommendations reflect expert synthesis rather than a measured diagnostic yield, and no sensitivity or specificity figure for MRI in musculoskeletal sarcoidosis is supplied.
- Articular manifestations of sarcoidosis are difficult to distinguish from other inflammatory and degenerative arthropathies, and muscular lesions are generally clinically silent and therefore often missed.
- MRI shows these manifestations to be very common in active sarcoidosis and should be included in screening when musculoskeletal sarcoidosis is suspected.
- MRI should be considered for evaluating patients with sarcoidosis who have unexplained osteoarticular complaints if standard radiographs are negative.
The outcome proportions (42.6% spontaneous remission, 10.4% remission on treatment, 18.9% active, 28.1% chronic with 8.5% moderate-to-severe organ damage), the 43.4% corticosteroid requirement, the erythema nodosum frequency of 39.8%, and the predictors of chronic versus good outcome come from Mana's 640-patient Barcelona cohort (DOI). The adjusted odds ratios - 0.15 for Lofgren syndrome, 2.68 for extrapulmonary involvement, 1.06 per year of age - come from Silva (DOI), 110 chronic versus 129 resolved patients. The late-recurrence observations come from Mana's 17-patient series (PMID 14620164), which reports no recurrence rate. The MSK spectrum and indirect skeletal effects come from the El Hasbani review (DOI) and the imaging role from Brandao Guimaraes (DOI) - both NARRATIVE REVIEWS rather than studies. The Lofgren triad, the Jungling osseous pattern, the calcitriol mechanism of hypercalcaemia, and the biopsy/exclusion approach to diagnosis are standard, well-established teaching.
What is not established: no diagnostic accuracy figure (sensitivity or specificity) has been published for MRI in musculoskeletal sarcoidosis, so "MRI is sensitive" is expert recommendation rather than measured performance; there is no validated prognostic score, no agreed surveillance interval after remission, and no trial defining when to treat sarcoid arthropathy. The prevalence of MSK involvement is quoted variably and no reliable single figure exists. Both outcome cohorts are European and predominantly Caucasian, and sarcoidosis is recognised to run a more severe course in patients of African ancestry, so these proportions should not be applied universally.