Great Toe | Lesser Toes | Usually Conservative
- Phalangeal fractures foot = most common foot fractures - great toe (hallux) most important, lesser toes usually conservative
- Great toe requires better alignment - the hallux carries load at push-off, so displacement greater than 2mm or an intra-articular step-off is the conventional trigger to fix it
- Lesser toes usually conservative - Buddy taping and early weight bearing usually sufficient, ORIF rarely needed
- Intra-articular fractures - a step-off greater than 2mm is the conventional trigger to fix the hallux; the cut-off is pragmatic, not trial-derived
- Usually conservative treatment - Most heal with buddy taping and protected weight bearing
- “Great toe most important - requires better alignment
- “Lesser toes usually conservative - buddy taping
- “Intra-articular displacement requires ORIF
- “Usually conservative treatment
Overview and Epidemiology
Phalangeal fractures are the most common fractures of the foot. They involve the proximal, middle or distal phalanx of the great toe (hallux) or of a lesser toe (2nd-5th), and most are treated conservatively with a good outcome. The great toe is the exception: it needs better alignment, and its displaced fractures are the ones fixed.
Who and how often. Toe fractures are a frequent emergency-department and fracture-clinic presentation at all ages, with a median patient age around 40-45 years and no strong sex predominance. In a 339-patient cohort the first toe (38%) and fifth toe (30%) were the most commonly fractured.
Mechanism. Crush is the most common, whether from stubbing the toe or dropping an object on it, and stubbing or crush together account for about 76% of cases; barefoot or open-footwear injuries predominate. Direct trauma to the toe and axial loading during push-off are the other mechanisms. Over 95% of these fractures are displaced less than 2mm and are amenable to conservative care.
Associated injuries. Look for a nailbed laceration, which makes a distal phalanx fracture effectively open, an open crush wound, and an injury to the adjacent metatarsal.
Anatomy and Pathophysiology
The hallux. The proximal phalanx is the largest and articulates with the first metatarsal. The distal phalanx is smaller, and tuft fractures of it are common. Between them lies the interphalangeal (IP) joint.
The lesser toes. Each has a proximal phalanx articulating with its metatarsal, a middle phalanx and a distal phalanx, and tuft fractures of the distal phalanx are common here too. The fifth toe may have only two: one survey of 102 cadaveric feet found a biphalangeal little toe in 26%, a normal variant that the differential diagnosis below returns to.
Deforming forces. The flexor and extensor tendons act on the great toe. In the lesser toes the forces are similar but less significant, and the intrinsic muscles contribute minimal deforming force.
Why the hallux is held to a stricter standard. It is critical for push-off and gait, and its IP joint is the most important joint. Malunion there is taken to cause arthritis, a claim examined under Outcomes. The lesser toes tolerate displacement: their function is less critical, the adjacent toes compensate, and most heal with conservative treatment.
Classification Systems
Toe fractures are described by location, pattern and articular involvement. Location comes first because hallux versus lesser toe decides the management: the hallux (proximal phalanx, distal phalanx, IP joint) is treated conservatively or by ORIF, and the lesser toes (proximal, middle and distal phalanx) usually conservatively.
- Type
- Transverse, a simple fracture
- Treatment
- Conservative or ORIF
- Type
- Oblique or spiral, an unstable pattern
- Treatment
- ORIF if displaced
- Type
- Comminuted, multiple fragments
- Treatment
- ORIF if displaced
- Type
- Extra-articular
- Treatment
- Conservative if aligned
- Type
- Intra-articular
- Treatment
- ORIF if step-off greater than 2mm
Clinical Assessment
History. The patient reports pain, swelling localised to the toe and pain on weight bearing after a crush, a stub or direct trauma. Most toe fractures are diagnosed clinically and confirmed on radiographs.
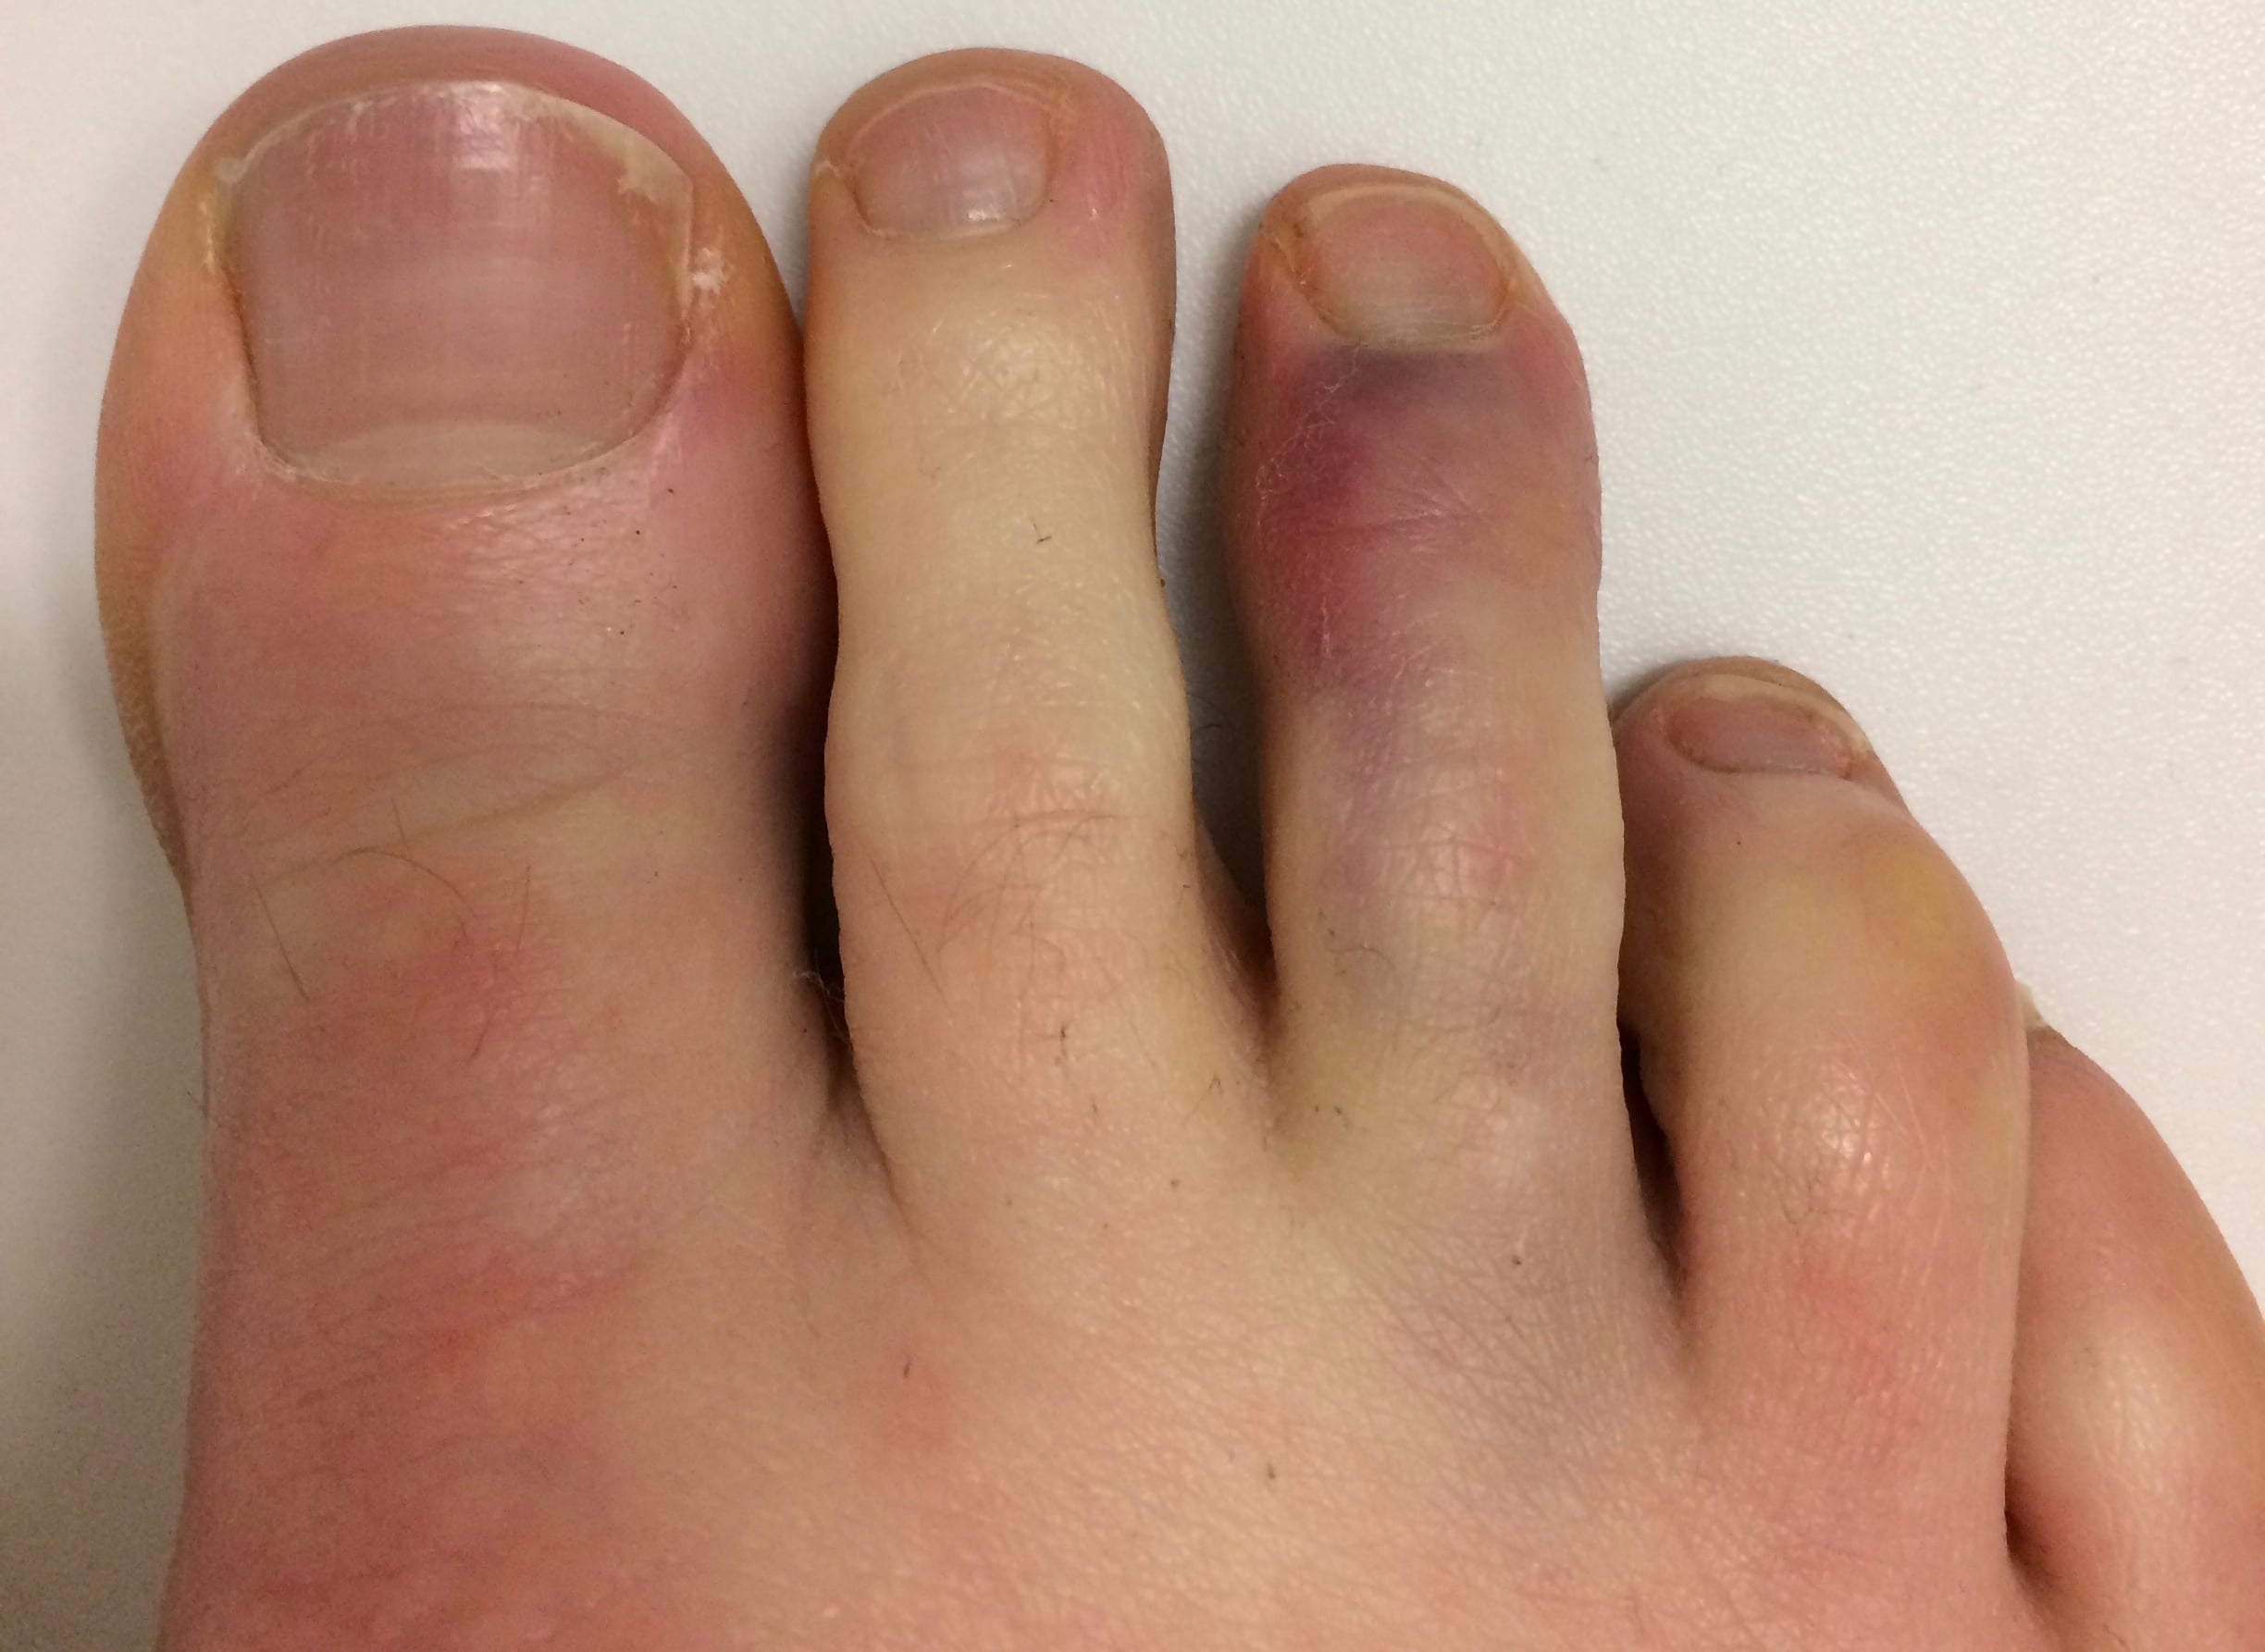
Examination. Inspect for swelling, ecchymosis (which may be delayed) and deformity in angulation or rotation. Tenderness is over the fracture site, with crepitus if the fracture is unstable and a palpable deformity if it is displaced. Toe movement is limited and painful, weight bearing hurts, and in the great toe test the range and stability of the IP joint.
Alignment. Check every toe for angulation and rotation. The great toe requires better alignment, while the lesser toes usually tolerate displacement; the next section sets out what needs reducing.
Always lift the nail / inspect the nailbed on a distal phalanx fracture. A subungual haematoma over a fracture signals an open injury.
Differential diagnosis. The mimics below each carry their own pitfall.
- Distinguishing features
- Acute stub/crush, focal bony tenderness, cortical break on film
- Key investigation
- AP/oblique radiograph
- Pitfall
- Miss nailbed = miss open fracture
- Distinguishing features
- Diffuse tenderness, no cortical break, no point bony pain
- Key investigation
- Radiograph normal
- Pitfall
- Over-imaging; treat symptomatically
- Distinguishing features
- Two phalanges in little toe (26% of feet in one cadaveric survey), no acute pain
- Key investigation
- Compare contralateral foot
- Pitfall
- Variant misread as fracture
- Distinguishing features
- Atraumatic overuse pain in athlete, plantar base tenderness
- Key investigation
- Oblique radiograph, MRI if early
- Pitfall
- Normal AP film falsely reassures
- Distinguishing features
- Hot, red, exquisitely tender joint, no trauma, raised urate
- Key investigation
- Joint aspirate, serum urate
- Pitfall
- Mistaking flare for fracture
- Distinguishing features
- Plantar hallux pain on push-off, not on the phalanx
- Key investigation
- Sesamoid/axial view, MRI
- Pitfall
- Bipartite sesamoid mimics fracture
Malrotation vs Angulation: What Actually Needs Reducing
Rotation is the villain. Lesser toes tolerate considerable sagittal and coronal angulation. Malrotation makes the toe scissor or override its neighbour, producing painful footwear conflict, callosities and pressure sores, so in the lesser toes rotation is the key operative indication and the angle is not.
Detecting it. Compare the plane of the nail with the adjacent uninjured toes, since a rotated toe's nail faces the wrong way. Look for scissoring or overlap on weight bearing, and check that the toe points straight on standing. Clinical assessment beats the radiograph for rotation.
The hallux is stricter. The great toe tolerates far less. Articular incongruity of the IP or MTP joint, malrotation, or displacement over about 2mm justify reduction or fixation, because the hallux drives push-off and a malunion there is symptomatic.
The practical rule. Reduce for malrotation, scissoring, an intra-articular step-off (especially in the hallux) or an open injury. Accept modest isolated angulation in a lesser toe that sits straight and fits a shoe.
Investigations
Radiographs are usually sufficient for diagnosis.
- AP - fracture pattern, displacement and alignment
- Lateral - angulation, and the IP joint of the great toe
- Oblique - may show the fracture better; less commonly needed
CT is rarely needed for a simple fracture. It shows the fracture pattern, articular step-off and displacement, and is recommended when:
- Intra-articular involvement is unclear
- Surgery is being planned
- The fracture pattern is complex
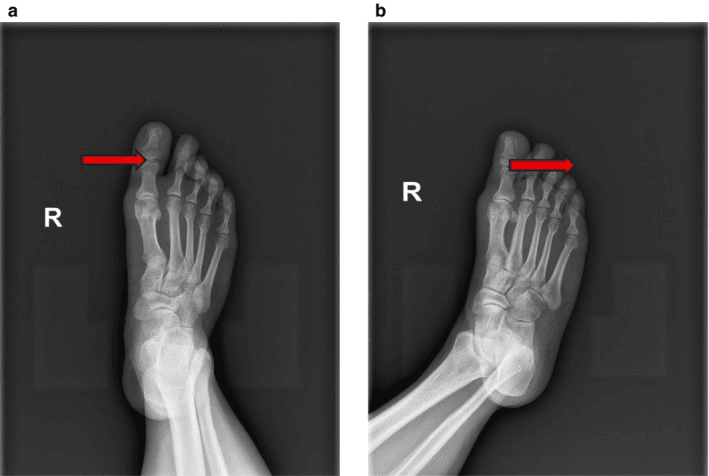
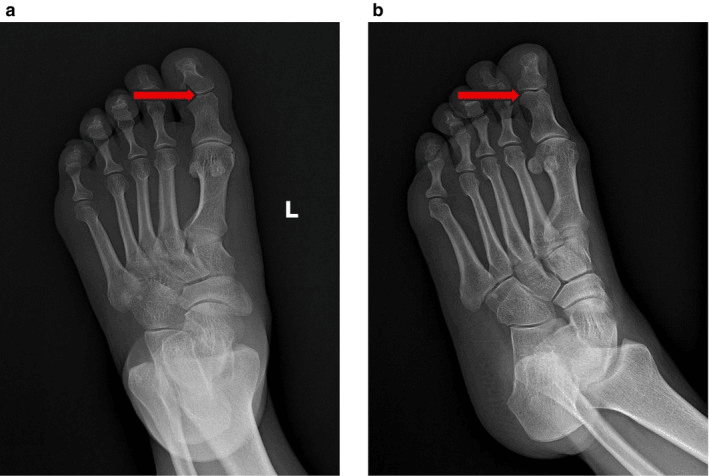
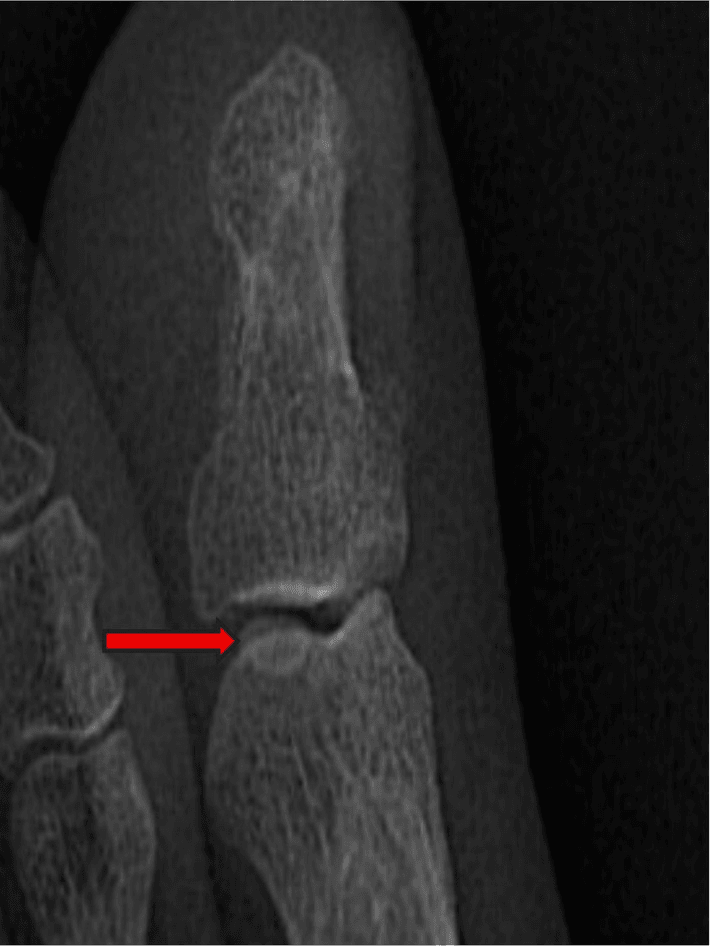
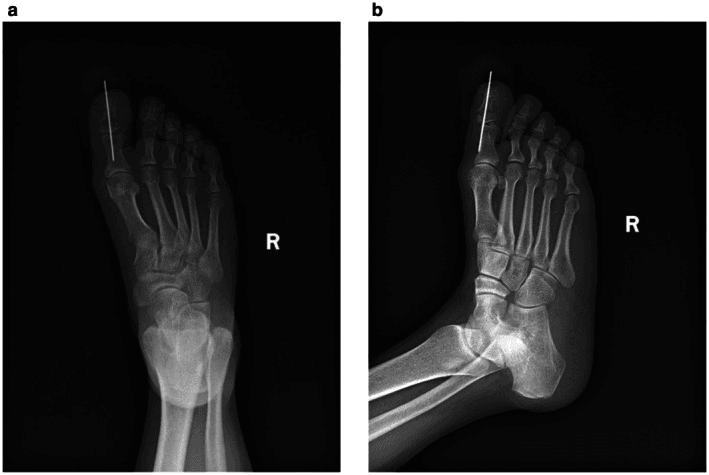
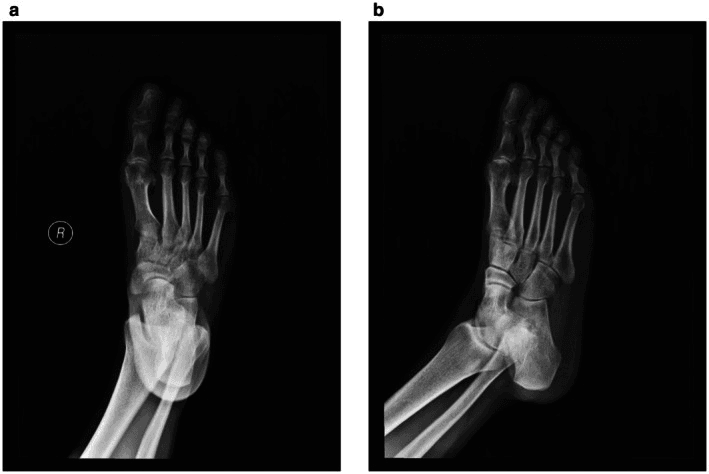
The interphalangeal sesamoid. A rounded ossicle near the hallux IP joint may be a normal interphalangeal sesamoid or a fracture fragment, and a radiograph of the contralateral foot clarifies which. Interposed in a distal phalanx fracture, the sesamoid is an uncommon mechanical block to reduction. The case below follows one such fracture through to union.
Management Algorithm
Most fractures are treated without surgery. Non-operative treatment suits the non-displaced or minimally displaced fracture, the lesser toes, and the great toe if it is non-displaced. The protocol is buddy taping to the adjacent toe with protected weight bearing for 3-4 weeks.
Follow-up. Serial radiographs monitor healing. Stable, undisplaced fractures, however, need no routine fracture-clinic review, and many units discharge them from the emergency department with self-care advice (Eves and Oddy, below).
- Displacement
- Less than 2mm, extra-articular
- Treatment
- Conservative (buddy taping)
- Outcome
- 85-90% good results
- Displacement
- Greater than 2mm or intra-articular
- Treatment
- ORIF
- Outcome
- 80-85% good results
- Displacement
- Displaced, but sits straight without malrotation
- Treatment
- Conservative (buddy taping)
- Outcome
- 85-90% good results
Surgical indications. Surgery is rare, and when it is indicated it is done within 1-2 weeks.
- Absolute - great toe displacement greater than 2mm; intra-articular step-off greater than 2mm; open fractures
- Relative - failed conservative treatment; severe displacement in a lesser toe
How firm is 2mm? The threshold is pragmatic, not trial-derived. No randomised data define the cut-off, and in the largest series cited here articular involvement did not predict a worse outcome, although almost every fracture in it was undisplaced. Displaced intra-articular hallux fractures are nonetheless usually fixed, by screw or K-wire, when the step-off exceeds about 2mm, the great toe IP joint being the one that matters. In the lesser toes ORIF is rarely needed, only for severe displacement or open fractures.
Surgical Technique
ORIF of the great toe is for the displaced or intra-articular fracture above and for an unstable fracture pattern.
- Exposure - medial or dorsal approach, exposing the fracture and protecting the neurovascular structures
- Reduction - anatomic, restoring IP joint congruity if the fracture is intra-articular
- Fixation - screws (1.5-2.0mm) or K-wires (1.0-1.5mm)
- Verification - reduction and hardware position confirmed fluoroscopically
What fixation offers. It restores alignment and allows early motion. It is also intended to prevent post-traumatic arthritis, but that is a mechanical rationale rather than a demonstrated outcome: no study on this page measured arthritis after either treatment.
K-wire fixation. An alternative to screws for the unstable fracture, and a means of temporary fixation. After closed or open reduction, percutaneous K-wires (1.0-1.5mm) hold the fracture and are removed at 3-4 weeks. The technique is minimally invasive and leaves less hardware.
How to Reduce and Buddy-Tape a Toe Fracture
Anaesthetise first. For a displaced or painful reduction use a digital (ring) block, or a hallux block, at the base of the toe. A bloodless, pain-free field lets you feel the reduction.
The reduction manoeuvre. Apply longitudinal traction, then re-create and reverse the deformity. For a dorsally angulated proximal phalanx, a pencil or a finger placed in the web space acts as a fulcrum to lever the fragment down. Confirm rotation and length clinically, then re-image.
Buddy taping done properly. Strap the injured toe to the adjacent, longer, more stable toe with a gauze or felt spacer between them to prevent skin maceration and pressure sores. Add a rigid-soled or post-operative shoe that offloads toe-off, and encourage early protected weight bearing.
Pitfalls.
- Taping skin-to-skin, which macerates
- Buddy taping across an open or nailbed wound
- Forgetting to re-check neurovascular status and rotation after taping
Complications
- Incidence
- 5-10%
- Risk Factors
- Displacement, inadequate reduction
- Prevention/Management
- Anatomic reduction, ORIF if needed; corrective osteotomy if symptomatic
- Incidence
- 10-15% (conventional figure, unsourced)
- Risk Factors
- Intra-articular malunion, step-off
- Prevention/Management
- Anatomic reduction, ORIF if step-off greater than 2mm; IP joint fusion if severe
- Incidence
- 10-15%
- Risk Factors
- Prolonged immobilisation
- Prevention/Management
- Early motion, buddy taping
- Incidence
- 2-5%
- Risk Factors
- Displacement, inadequate fixation
- Prevention/Management
- Rigid fixation
Postoperative Care
Immediately after surgery the toe is buddy taped or splinted, weight bearing is protected and toe movement starts early. Physiotherapy is not usually needed.
Rehabilitation Protocol
Buddy taping or splint, protected weight bearing, toe range-of-motion exercises.
K-wires removed if used; progressive weight bearing.
Full weight bearing.
Return to sport.
Outcomes and Prognosis
- Success (union, pain relief)
- 85-90%
- Return to pre-injury level
- 80-85%
- Success (union, pain relief)
- 80-85%
- Return to pre-injury level
- 75-80%
- Success (union, pain relief)
- 85-90%
- Return to pre-injury level
- 85-90%; complications rare
Arthritis is the number to handle carefully. A post-traumatic IP arthritis rate of around 10-15% is widely repeated for the great toe after intra-articular injury with proper treatment, but it is not established by any study cited on this page, and no series here measured radiographic or symptomatic arthritis at all. Quote it as conventional teaching, not as a figure you can give a patient. The risk factors are intra-articular malunion and displacement.
The comparison that does not hold. A higher figure of 20-30% without treatment is often set beside it. Neither number is sourced here, so the apparent halving of arthritis risk by operating is an untested comparison between two unsourced estimates; do not present it to a patient as a benefit of surgery.
Guidelines, Registries & Global Practice
Global epidemiology. Toe phalangeal fractures are among the most common foot fractures worldwide. The first and fifth toes account for roughly two-thirds of cases, and about three-quarters arise from stubbing or crush in barefoot/open-footwear settings - a pattern reproduced across high- and low-resource populations. Over 95% are minimally displaced.
- Default stance
- Conservative: buddy taping + rigid-sole shoe
- Surgical threshold
- Displaced intra-articular hallux, open, gross deformity
- Follow-up
- Selective; ED advice for stable injuries
- Default stance
- Conservative; reduce ED-to-clinic burden
- Surgical threshold
- As above; few need theatre (about 3%)
- Follow-up
- Virtual / discharge for stable undisplaced (evidence-led)
- Default stance
- Non-operative for most; anatomic care of hallux IPJ
- Surgical threshold
- Intra-articular step-off, unstable/rotated
- Follow-up
- Radiographic check if reduced/fixed
- Default stance
- Conservative default; function over radiographic perfection
- Surgical threshold
- Hallux articular incongruity, open, malrotation
- Follow-up
- Symptom-driven
- No dedicated arthroplasty/implant registry tracks toe phalangeal fractures (no implants survived long-term)
- Evidence is observational: large cohorts confirm excellent conservative outcomes (median AOFAS 100)
- Convergent global guidance: conservative care is the default everywhere
- Well-resourced: ready radiographs, ED nailbed repair, selective CT, percutaneous K-wiring when indicated
- Limited-resource: clinical diagnosis and buddy taping suffice for most; reserve scarce imaging/theatre for open, intra-articular hallux, or grossly deformed injuries
- Outcomes are comparable because the great majority need only protection and time
Phalangeal fractures of the foot are a common viva topic. Know that the great toe matters most because it loads at push-off, that displaced intra-articular hallux fractures are conventionally fixed at a step-off over 2mm, and that lesser toes are managed with buddy taping and early weight-bearing. The marks are in the qualifications: the 2mm threshold is pragmatic, not trial-derived; "prevents arthritis" is mechanical reasoning rather than a measured outcome; malrotation matters more than angulation; a nail-bed laceration over a distal phalanx fracture is an open fracture, and in a child an open physeal one; and a biphalangeal fifth toe is a normal variant in roughly a quarter of feet, not a fracture.
Related pages: Metatarsal Fractures and Fifth Metatarsal Stress Fractures for the neighbouring forefoot injuries with genuinely different rules - the base of the fifth metatarsal is where a stubbing mechanism often actually breaks; Turf Toe for the hyperextension injury to the same first MTP joint that produces pain without a fracture line; Sesamoid Disorders for the bones under the hallux that fracture, are bipartite in about a tenth of people, and are the other great mimic on a hallux radiograph; Hallux Rigidus for the arthritis this page's fixation is meant to prevent, and for what it actually costs the patient when it develops; Hallux Valgus for the deformity that changes toe loading and footwear tolerance afterwards; Physeal Injuries and the Salter-Harris Classification for the growth plate injured in the paediatric Seymour-equivalent fracture carded here; Stress Fractures Overview for the bone-stress spectrum behind the second proximal phalanx case series; Lisfranc Injuries for the midfoot injury that must not be missed in a "stubbed foot"; and Foot Anatomy and Biomechanics for why the hallux is the toe that matters at push-off.
Controversies and Areas of Uncertainty
Evidence (Eves & Oddy, 2016) shows only about 3% of toe phalangeal fractures need surgery and none developed symptomatic malunion at 2 years. Many units now discharge stable, undisplaced fractures directly from ED with self-care advice rather than routine fracture-clinic review.
The "greater than 2mm displacement or intra-articular step-off" threshold for the hallux is pragmatic, not trial-derived. No randomised data define the exact cut-off; decisions weigh articular involvement, instability, rotation and patient demand.
Lesser toes tolerate considerable angulation; significant malrotation or scissoring is the more important indication to reduce, because it causes footwear problems and skin pressure - angulation in the sagittal/coronal plane is often accepted.
A displaced distal phalanx fracture with nailbed disruption is functionally an open fracture, but routine prophylactic antibiotic duration and the need for formal theatre washout (vs ED nailbed repair) remain debated, especially in children with Seymour-type injuries.
MCQ Practice Points
Q: Why does the great toe require better alignment than lesser toes? A: Great toe is critical for push-off and gait - Displacement greater than 2mm or intra-articular step-off requires ORIF. IP joint most critical. Success rate 80-85% with ORIF.
Q: How are lesser toe fractures treated? A: Usually conservative with buddy taping - Lesser toes tolerate displacement better than great toe. Buddy taping and protected weight bearing usually sufficient. ORIF rarely needed. Success rate 85-90% with conservative treatment.
Q: When is ORIF required for phalangeal fractures of the foot? A: Great toe displacement greater than 2mm or intra-articular step-off greater than 2mm - Prevents malunion and arthritis. Lesser toes rarely need ORIF - only for severe displacement or open fractures.
Q: What is the treatment for phalangeal fractures of the foot? A: Usually conservative with buddy taping - Most heal with buddy taping and protected weight bearing. ORIF for great toe displacement (greater than 2mm) or intra-articular step-off. Success rate 85-90% with conservative, 80-85% with ORIF.
Q: What are the complications of phalangeal fractures of the foot? A: Malunion (5-10%), arthritis (10-15% if intra-articular malunion), stiffness (10-15%) - Prevent with anatomic reduction and ORIF if needed. Early motion prevents stiffness. Success rate 85-90% with proper treatment.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 30-year-old patient presents with great toe pain after stubbing injury. X-rays show displaced proximal phalanx fracture of great toe with 3mm displacement and 5 degrees angulation.”
“A 25-year-old patient presents with 3rd toe pain after crush injury. X-rays show displaced middle phalanx fracture with 4mm displacement and 10 degrees angulation.”
“A 9-year-old child stubbed the great toe on a bedpost. There is a subungual haematoma, blood at the nail fold and the nail is partly lifted. Radiographs show a displaced Salter-Harris II fracture of the distal phalanx physis.”
Key Concepts
- Most common foot fractures
- Great toe (hallux) most important - requires better alignment
- Lesser toes (2nd-5th) usually conservative
- Usually conservative treatment (85-90% good results)
Classification
- Great toe: Proximal or distal phalanx, IP joint - conservative or ORIF
- Lesser toes: Proximal, middle, or distal phalanx - usually conservative
- Intra-articular: Joint involvement - ORIF if step-off greater than 2mm
- Key Factor: Hallux vs lesser toe determines management
Treatment
- Great toe non-displaced: Conservative (buddy taping, 85-90% good results)
- Great toe displaced: ORIF if greater than 2mm (80-85% good results)
- Lesser toes: Conservative (buddy taping, 85-90% good results)
- Intra-articular: ORIF if step-off greater than 2mm (80-85% good results)
Surgical Technique
- Medial or dorsal approach: Protect neurovascular structures
- Reduction: Anatomic reduction, restore IP joint congruity if intra-articular
- Fixation: Screws (1.5-2.0mm) or K-wires (1.0-1.5mm)
- Verify reduction fluoroscopically
Complications
- Malunion: 5-10% (prevent with anatomic reduction, ORIF if needed)
- Arthritis: 10-15% if intra-articular malunion (prevent with ORIF if step-off)
- Stiffness: 10-15% (prevent with early motion, buddy taping)
- Nonunion: 2-5% (prevent with rigid fixation)
Evidence Base
Demographics and functional outcome of toe fractures
- First (38%) and fifth (30%) toes most commonly fractured
- 75.6% from stubbing or crush; over 95% displaced under 2 mm
- All treated conservatively; median AOFAS 100 at 27 months
- Outcome independent of toe, phalanx, or articular involvement
Do Broken Toes Need Follow-Up in the Fracture Clinic?
- Only 2 of 65 patients (about 3%) required surgery
- No symptomatic malunion at 2 years
- Stable undisplaced fractures need no fracture-clinic follow-up
- Supports community/GP management of most toe fractures