Degenerative Process | Conservative First | 90% Resolve at 1 Year | Surgery Only After 6-12 Months
- PLANTAR FASCIITIS IS A DEGENERATIVE PROCESS, not an inflammatory one - the terms plantar fasciosis or plantar heel pain are preferred
- 90% RESOLVE WITH CONSERVATIVE MANAGEMENT within 12 months, so surgery is rarely needed
- RISK FACTORS: obesity, pes planus, limited ankle dorsiflexion, and prolonged standing
- DIAGNOSIS IS CLINICAL: tenderness at the medial calcaneal tubercle with pain on the first steps
- A CONSERVATIVE TRIAL OF 6-12 MONTHS is mandatory before considering surgery
- STEROID INJECTION gives short-term relief but carries a risk of fascial rupture - use it sparingly
- SURGICAL RELEASE: partial (medial 50%) versus complete - never release more than 50%, to avoid lateral column overload
- “Plantar fascia is windlass mechanism - passive toe extension tightens fascia and raises arch
- “Heel spur present in 50% but is incidental finding, not cause of pain
- “Fascia rupture causes sudden relief of pain but lateral column pain and arch collapse
- “Nerve entrapment (Baxter nerve) is important differential - burning pain, night pain
Overview and Epidemiology
Plantar fasciitis, also termed plantar fasciosis or plantar heel pain syndrome, is the most common cause of inferior heel pain in adults, accounting for approximately 1 million patient visits a year in the United States. The name is entrenched in clinical practice, but plantar fasciosis or plantar heel pain more accurately reflects the pathology, and in the exam it is worth saying so: despite the suffix, histology shows degeneration rather than inflammation (see Pathophysiology).
Who gets it. About 10% of the population are affected at some point in their lifetime. The peak age is 40-60 years, though it can occur at any age, and there is a 2:1 female predominance. It is bilateral in 30% of cases, and more common in runners (prevalence up to 22%) and dancers.
Natural history. The condition is self-limiting: 80-90% resolve with conservative treatment within 12 months (a figure also quoted as 12-18 months), and even without treatment many cases improve over 1-2 years. Approximately 25% have recurrent symptoms, and 10% develop chronic, refractory symptoms requiring advanced interventions.
That prognosis is the foundation of every treatment algorithm. Surgery is reserved for the small minority who fail comprehensive non-operative management.
Risk Factors and Prevention
- Modifiable
- Tight gastrocnemius, poor footwear, training errors, abnormal gait
- Non-Modifiable
- Pes planus, pes cavus, leg length discrepancy, age 40-60
- Modifiable
- Obesity (BMI over 30), weight management
- Non-Modifiable
- Female gender, genetic predisposition to flat feet
- Modifiable
- Occupational standing, running volume, surface hardness
- Non-Modifiable
- None
- Modifiable
- Diabetes control, inflammatory arthritis management
- Non-Modifiable
- Seronegative spondyloarthropathy, diabetes mellitus
The contributory factors. Most add load or strain at the fascial origin:
- Obesity - increased BMI directly increases load on the fascia, and a BMI over 30 increases risk 5-fold
- Tight gastrocnemius-soleus complex - limited ankle dorsiflexion increases plantar fascia strain, by up to 15%
- Foot mechanics - both pes planus (overpronation) and pes cavus (poor shock absorption) increase stress, as do supination and other gait abnormalities
- Footwear - worn-out shoes, lack of arch support, high heels, flip-flops
- Training errors - a sudden increase in running distance or intensity (over 10% a week) in runners or athletes
- Occupation - prolonged standing or walking on hard surfaces (over 8 hours daily), as in teachers, nurses and factory workers
Prevention pulls the same levers: weight management to keep a healthy BMI, a daily gastrocnemius and plantar fascia stretching programme, appropriate footwear, gradual progression of activity with cross-training to vary the repetitive stress, and early attention to tight calf muscles and biomechanical problems. The specifics, the 10% rule and when to replace running shoes, are under Management.
Pathophysiology
Plantar Fascia Anatomy
The fascia. Dense fibrous connective tissue arises from the medial calcaneal tubercle, on the medial process of the calcaneal tuberosity, and divides distally into five bands that insert onto the proximal phalanges and flexor tendon sheaths. It is arranged in three bands, medial, central and lateral; the central band is the thickest and strongest, and the one most commonly affected in plantar fasciitis.
Normal fascia is 2-4mm thick. It is relatively avascular, which contributes to slow healing.
What it does. Through the windlass mechanism, passive toe extension during push-off tightens the fascia and raises the medial longitudinal arch. The fascia also gives static support to the longitudinal arch, working in concert with the spring ligament and the posterior tibial tendon, and absorbs impact at heel strike, up to 2-3 times body weight.
The Pathology
Degeneration, not inflammation. Histological studies of chronic plantar fasciitis show four changes:
- Myxoid degeneration - disorganisation of collagen fibres
- Collagen necrosis - breakdown of the normal fascial architecture
- Angiofibroblastic hyperplasia - proliferation of fibroblasts and small blood vessels
- Absence of inflammatory cells - minimal or no lymphocytes, macrophages or neutrophils
The pattern resembles other tendinopathies, Achilles tendinosis and lateral epicondylosis among them. It explains why anti-inflammatory treatments, NSAIDs and steroid injections included, have limited long-term benefit.
Mechanical overload. The most accepted theory is repetitive microtrauma at the fascial origin. Excessive or repetitive loading exceeds the fascia's capacity for repair, and microtears develop at the origin from the medial calcaneal tubercle. Instead of inflammation and repair, degeneration occurs, and ongoing stress prevents healing, so the degenerative process perpetuates itself. The contributory factors are set out under Risk Factors.
The heel spur. Calcaneal spurs are present in 50% of patients with plantar fasciitis, and in 15-25% of asymptomatic individuals. The spur develops from traction at the origin of flexor digitorum brevis, not the plantar fascia, and it is an incidental finding, not the cause of pain.
Classification
Classification by Severity
- Description
- Early/acute
- Symptoms
- Morning pain resolving within 10-15 minutes
- Impact on Activity
- Minimal activity modification
- Description
- Subacute
- Symptoms
- Persistent pain affecting daily activities
- Impact on Activity
- Modified exercise programme
- Description
- Chronic
- Symptoms
- Constant pain with rest pain
- Impact on Activity
- Unable to perform usual activities
- Description
- Treatment-resistant
- Symptoms
- Failed 6+ months conservative care
- Impact on Activity
- Consider procedural intervention
Clinical Presentation and Diagnosis
History
The story. The classic complaint is severe pain with the first steps in the morning or after prolonged sitting, present in 95% of cases, felt in the inferior heel at the medial calcaneal tubercle. Onset is usually gradual, over weeks to months, not acute.
The pattern through the day. Pain improves with initial activity as the fascia "warms up", then worsens with prolonged activity. It decreases with rest and recurs with weight-bearing. Walking barefoot on hard surfaces, climbing stairs, prolonged standing or walking, running or jumping, and first steps after rest aggravate it; rest, sitting with the feet elevated, supportive footwear and activity modification relieve it.
Night pain is typically absent, and if present, consider other diagnoses.
These red flags require further investigation:
- Severe night pain (possible infection, tumour, inflammatory arthritis)
- Fever, systemic symptoms (septic arthritis, osteomyelitis)
- History of trauma (calcaneal fracture)
- Progressive neurological symptoms (tarsal tunnel, nerve compression)
- Lack of response to conservative treatment (reconsider diagnosis)
Physical Examination
Look. The gait may be antalgic, with a shortened stance phase on the affected side. Assess alignment for pes planus, pes cavus or a neutral arch; chronic cases may show calf atrophy. Swelling is typically absent, and if present, consider an alternative diagnosis.
Feel. The key finding is exquisite point tenderness at the medial calcaneal tubercle, 95% sensitive, typically 4cm or less from the insertion point. Plantar fasciitis causes focal tenderness, and diffuse pain suggests an alternative diagnosis; absence of lateral heel tenderness helps distinguish it from other conditions.
Move. Assess ankle dorsiflexion with the knee extended (gastrocnemius) and flexed (soleus): less than 10 degrees with the knee extended is a significant risk factor. Hallux dorsiflexion is normal but may reproduce the pain, which is the windlass test.
The special tests:
- Technique
- Passively dorsiflex hallux
- Positive Finding
- Reproduction of heel pain
- Clinical Significance
- Confirms plantar fascia as pain source
- Technique
- Tap over tarsal tunnel or Baxter nerve
- Positive Finding
- Radiating burning pain
- Clinical Significance
- Suggests nerve entrapment
- Technique
- Dorsiflex ankle and evert foot
- Positive Finding
- Pain medial heel
- Clinical Significance
- Suggests posterior tibial tendon pathology
- Technique
- Deep palpation between abductor hallucis and quadratus plantae
- Positive Finding
- Burning pain, radiation
- Clinical Significance
- Baxter nerve entrapment
With the patient standing or sitting, passively dorsiflex the hallux (great toe) while palpating the plantar fascia. This tightens the fascia through the windlass mechanism and stresses its origin. Pain at the medial calcaneal origin is a positive test. Sensitivity is low: in the only accuracy study the weight-bearing test was positive in 7 of 22 patients with plantar fasciitis (31.8%) and the non-weight-bearing test in 3 of 22 (13.6%), but in none of 53 comparison subjects (De Garceau 2003). A positive test supports the diagnosis; a negative one excludes nothing, so perform it weight-bearing.
Investigations and Imaging
Diagnosis is clinical. Plantar fasciitis is primarily a clinical diagnosis, based on the history and examination. Imaging is reserved for atypical presentations, failed conservative treatment, or suspicion of an alternative diagnosis.
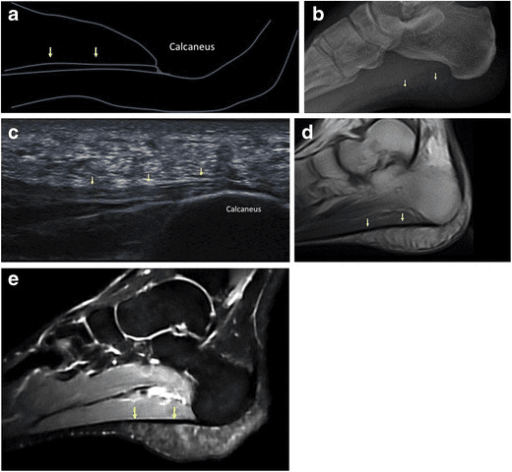
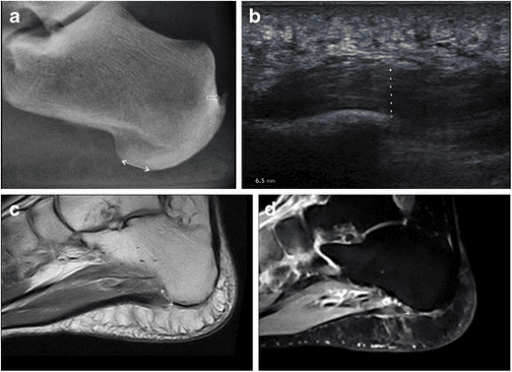
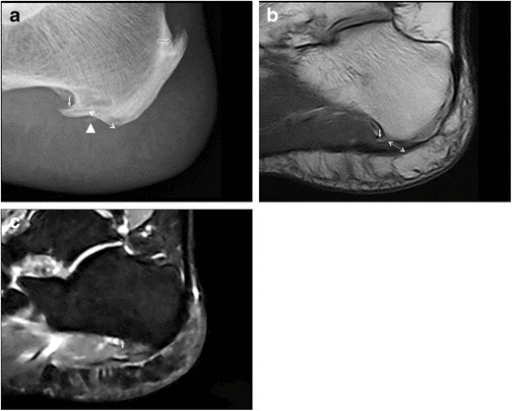
Plain radiographs are indicated for an atypical presentation, a history of trauma, failed conservative treatment over 3 months, or to rule out fracture, tumour or other bony pathology. The lateral view is best for assessing the heel spur and soft-tissue thickness; weight-bearing films are preferred for foot alignment and arch height, and bilateral comparison may help in assessing arch differences.
A spur may be seen, but its presence or absence neither confirms nor excludes the diagnosis (see Pathophysiology). Films may also reveal a stress fracture, tumour or arthritic change.
Ultrasound is non-invasive, involves no radiation, is less expensive than MRI, and is readily available in clinic. It allows dynamic assessment with the foot in different positions and real-time guidance for injection therapy. In plantar fasciitis it shows:
- Fascial thickening, often 5-7mm
- Hypoechoic appearance - loss of the normal fibrillar pattern, indicating degeneration
- Perifascial oedema - fluid around the fascia
- Increased vascularity on power Doppler - suggests an active process, though less common given the degenerative nature
Plantar fascia thickness over 4mm on ultrasound has sensitivity of 80-95% and specificity of 80-85% for plantar fasciitis. Measurement should be taken at the fascial origin from the medial calcaneal tubercle in sagittal plane.
Ultrasound also shows the alternatives:
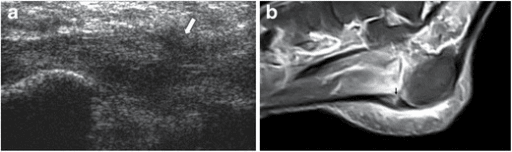
- Fascia rupture - discontinuity of the fascia, often with haematoma
- Heel pad atrophy - thinning of the normal 2cm heel fat pad
- Nerve compression - a hypoechoic mass or swelling along the nerve course
- Plantar fibroma - a hypoechoic nodule within the plantar fascia, more distal
MRI is indicated for an atypical presentation with concern for an alternative diagnosis, failed conservative treatment over 6 months, preoperative planning in the rare surgical candidate, suspected stress fracture, tumour or infection, and evaluation of nerve entrapment. In plantar fasciitis it shows:
- Fascial thickening, often 5-8mm
- Increased T2 signal - oedema and degeneration within the fascia
- Perifascial oedema - high signal around the fascia on fluid-sensitive sequences
- Calcaneal bone marrow oedema at the fascial attachment, in severe cases
- Fascial discontinuity - partial or complete rupture, a complication
MRI also identifies the alternatives:
- Baxter nerve entrapment - oedema or mass between abductor hallucis and quadratus plantae
- Tarsal tunnel syndrome - nerve enlargement or a mass in the tarsal tunnel
- Calcaneal stress fracture - bone marrow oedema in the calcaneal body
- Tumour - a mass lesion with characteristic signal patterns
- Infection - bone marrow oedema with cortical destruction and soft-tissue involvement
Management
Treatment Philosophy
The goal is to address biomechanical factors, reduce load on the fascia and allow the degenerative process to resolve. A structured, stepwise approach is recommended, with patience and realistic expectations; each phase below carries the cumulative proportion expected to have improved by its end.
Initial treatment, with 20% significantly improved by 6 weeks:
- Activity modification (reduce standing, running) and no barefoot walking
- Ice massage, 15 minutes, 3-4 times daily
- NSAIDs, a 2-week course for pain relief, not long-term
- Stretching exercises (calf and plantar fascia)
- Supportive footwear with cushioned heels
Escalate conservative treatment, for a further 30-40% improved by 3 months (60% in total):
- Formal physiotherapy referral
- Night splints
- Custom orthoses or prefabricated arch supports
- Low-dye taping
- Continue the stretching programme
- Consider extracorporeal shockwave therapy (ESWT)
Advanced conservative therapies, for a further 20-25% by 6 months (80-85% in total):
- ESWT, if not already tried
- Corticosteroid injection, used sparingly
- Platelet-rich plasma (PRP) injection (emerging evidence)
- Intensive physiotherapy with iontophoresis
- Assess footwear and biomechanics
- Weight loss if BMI over 30
Final conservative measures, for a further 5-10% by 12 months (90% in total):
- Repeat injection therapy if only a single prior injection
- Trial of different orthoses or footwear
- Walking boot for 4-6 weeks (rarely needed)
- Imaging to rule out alternative diagnoses
- Reassess compliance with stretching and physiotherapy
Surgery is considered only when the strict criteria under Surgical Management are met.
Specific Conservative Interventions
Stretching is first-line and essential, with high-quality evidence supporting it as the cornerstone of treatment. Two stretches are taught:
- Gastrocnemius-soleus - stand facing a wall, affected leg behind, knee straight, and lean forward until the stretch is felt in the calf. Hold 30 seconds, repeat 3 times, 3 times daily (morning, midday, evening), then repeat with the knee bent to isolate soleus.
- Plantar fascia-specific - seated, cross the affected foot over the opposite knee and pull the toes back toward the shin while massaging the arch. Hold 10 seconds, repeat 10 times, before the first steps in the morning and before standing after prolonged sitting.
A landmark RCT by DiGiovanni et al. demonstrated that plantar fascia-specific stretching was superior to standard Achilles stretching for pain relief and functional improvement at 8 weeks. This has become the foundation of conservative treatment protocols.
Heel cups, insoles and taping. Silicone heel cups reduce impact forces on the heel, gel inserts provide cushioning, and low-dye taping supports the arch and reduces fascia strain. Prefabricated arch supports and cushioned insoles are readily available and inexpensive, with moderate evidence for short-term benefit (3-6 months).
Custom orthoses. Semi-rigid orthoses provide arch support and control pronation, and are indicated for significant pes planus or cavus or failed prefabricated orthoses. They are more expensive but may be worth a trial in refractory cases, although evidence that custom is superior to prefabricated is limited.
Footwear. Avoid high heels, flip-flops, worn-out shoes and flat, unsupportive shoes. Prefer well-cushioned athletic shoes with arch support and a heel counter, and replace running shoes every 400-500 miles.
Night splints maintain the ankle in neutral or slight dorsiflexion overnight, preventing the fascia from contracting and reducing first-step pain in the morning. Posterior leaf-spring (L-shaped) splints, more comfortable, lower-profile sock-type splints, and adjustable splints that allow a gradual increase in the stretch are all used. They are worn nightly for 1-3 months.
Compliance is the key challenge: 50% discontinue because of discomfort. The evidence for effectiveness when tolerated is moderate.
Extracorporeal shockwave therapy (ESWT). The protocol is as follows:
- Energy level 0.1-0.2 mJ/mm² (low to medium energy)
- 2000-4000 shocks per session
- Typically 3 sessions, 1-2 weeks apart
- Usually performed without anaesthesia (mild discomfort)
The placebo-controlled trials disagree, and you should know both sides. Two large earlier trials were negative: in 272 patients with heel pain recalcitrant for at least 6 months, focused ESWT under local anaesthesia (3 sessions of 4000 impulses at 0.08 mJ/mm²) succeeded in 34% at 12 weeks against 30% with sham, with no difference in pain or walking up to a year (Haake 2003); and in 166 patients with ultrasound-confirmed plantar fasciitis, ultrasound-guided ESWT improved pain, function and quality of life no more than placebo at 6 and 12 weeks (Buchbinder 2002). The later Gollwitzer trial below was positive with a higher focused dose given without anaesthesia. Success rates of 60-80% are quoted from uncontrolled series in refractory cases, higher than the 50-65% of that trial. If ESWT is offered, it is after 3-6 months of failed conservative care, with the conflicting evidence explained. It is contraindicated with infection at the treatment site, malignancy, pregnancy, coagulopathy or anticoagulation, and open growth plates in children.
Gollwitzer RCT: Focused ESWT for chronic plantar fasciitis
- Multicentre, double-blind, placebo-controlled FDA trial of 250 subjects with recalcitrant plantar fasciitis
- Three sessions of 2000 focused impulses (0.25 mJ/mm²) reduced the composite VAS heel-pain score by 69.2% versus 34.5% with placebo (p=0.0027)
- Roles and Maudsley score also significantly favoured ESWT (p=0.0006); success rates 50-65%
- Only temporary pain and swelling were observed as device-related adverse events
Haake RCT: ESWT versus placebo for chronic plantar fasciitis
- Randomised, blinded multicentre trial (nine hospitals and one clinic in Germany) of 272 patients recalcitrant to at least 6 months of conservative care
- Focused electromagnetic ESWT, 3 sessions of 4000 impulses at 0.08 mJ/mm² under local anaesthesia, versus identical sham
- Roles and Maudsley success at 12 weeks 34% with ESWT versus 30% with placebo (95% CI for the difference -8.0% to 15.1%)
- No difference in pain ratings or walking ability up to a year
Buchbinder RCT: Ultrasound-guided ESWT versus placebo
- Double-blind, placebo-controlled trial of 166 patients with ultrasound-confirmed plantar fasciitis (fascia at least 4mm, hypoechoic)
- ESWT weekly for 3 weeks to a total dose of at least 1000 mJ/mm², versus placebo at 6.0 mJ/mm²
- Both groups improved similarly in pain, Maryland Foot Score, walking and SF-36 at 6 and 12 weeks; no outcome differed between groups
Focused versus Radial Shockwave, and How Energy Is Classified
ESWT is not a single modality, and the distinction is examinable because the level-I evidence above applies to one specific type.
Focused ESWT is a true shockwave. An electrohydraulic, electromagnetic or piezoelectric source generates it and geometrically converges it, so that peak energy is delivered at a chosen focal depth in the deep tissue. It reaches a higher energy flux density and is the modality used in the Gollwitzer trial. Higher-energy focused protocols can be uncomfortable and some centres add local anaesthesia, although the Gollwitzer trial notably demonstrated efficacy without it, and there is a theoretical concern that anaesthesia may blunt the analgesic effect.
Radial pressure-wave therapy (rESWT) uses a pneumatically driven projectile to produce a radially dispersing pressure wave whose energy is maximal at the skin surface and falls off with depth. It is lower energy, delivered without anaesthesia, cheaper and more widely available, but its evidence base is more mixed than that for focused ESWT.
Dose is described as energy flux density (EFD, mJ/mm²), conventionally banded into low (roughly below 0.1), medium (roughly 0.1 to 0.3) and high (roughly above 0.3) energy. The low-to-medium figures of the protocol above sit in the radial/low-energy range, whereas the recalcitrant-disease RCT evidence used a higher focused dose.
How it works. Acoustic energy is converted into a biological signal (mechanotransduction) that produces controlled microtrauma and a healing response in degenerative tissue. Angiogenic and growth factors, including VEGF and endothelial nitric oxide synthase, are upregulated to drive neovascularisation of the degenerate fascia, and analgesia comes from hyperstimulation of nociceptors and modulation of substance P. That fits the degenerative (fasciosis) model of the disease rather than the inflammatory one.
When asked about shockwave therapy, separate focused from radial: the strongest (level-I) evidence for recalcitrant plantar fasciitis is for focused, higher-energy ESWT (Gollwitzer 2015, 0.25 mJ/mm²). Do not quote the focused-ESWT trial results as if they apply to a radial device, and know that two earlier placebo-controlled trials of focused ESWT found no benefit over sham (Haake 2003; Buchbinder 2002).
Activity modification. Take regular sitting breaks if the occupation requires prolonged standing, replace running with swimming, cycling or the elliptical trainer, and always wear supportive footwear, even at home. Return to activity gradually by the 10% rule, increasing by no more than 10% a week, cross-train to vary the repetitive stress, and prefer grass or synthetic tracks to hard surfaces.
Surgical Management
Indications for Surgery
Strict criteria must be met before surgical intervention is considered:
- Failed comprehensive conservative treatment for a minimum of 6-12 months
- All non-operative measures attempted: stretching, physiotherapy, orthoses, night splints, ESWT and at least one injection
- No alternative diagnosis on imaging (MRI if needed)
- Significant functional impairment, with pain limiting activities of daily living
- A motivated, compliant patient who understands the postoperative rehabilitation and has realistic expectations: surgery is not guaranteed success
Relative contraindications are:
- Active infection
- Peripheral neuropathy (diabetic neuropathy increases the risk of complications)
- Venous insufficiency or PAD (poor healing)
- Inflammatory arthropathy (may have a systemic component)
- Workers' compensation or litigation (poorer outcomes)
- Non-compliance with prior treatment
Only 10% of plantar fasciitis patients are surgical candidates after appropriate conservative management. Surgery should be considered a last resort for chronic, refractory cases only.
Surgical Options
Open Plantar Fascia Release
When to choose it. Open release suits the surgeon who prefers it or lacks endoscopic equipment, the patient who needs Baxter nerve decompression, and any concern about atypical anatomy or pathology.
Technique. The operation runs in six steps.
- Position supine with a bump under the ipsilateral hip and a thigh tourniquet; prepare and drape the foot and ankle.
- Make a 3-4cm medial longitudinal incision centred over the medial calcaneal tubercle, starting just distal to the tubercle and extending distally along the medial arch. Avoid the plantar surface, to prevent a painful scar.
- Incise skin and subcutaneous tissue, identify abductor hallucis along the medial border, and retract it plantarly to expose the fascial origin: thick, glistening white fascia inserting onto the medial tubercle.
- Release the medial 50% of the fascia width only, transecting it sharply 1-2cm from its calcaneal origin. Preserving the lateral 50% is essential to prevent lateral column overload and arch collapse; palpate with a finger to confirm an adequate release with the lateral half intact.
- If entrapment is suspected, decompress the Baxter nerve. Identify the first branch of the lateral plantar nerve deep between abductor hallucis and quadratus plantae, release the fascia compressing it, and decompress it distally to the medial calcaneal tuberosity.
- Irrigate, close the subcutaneous layer with absorbable suture and the skin with non-absorbable suture or staples, and apply a soft dressing and a posterior splint in neutral.
The heel spur is not routinely excised: it is an incidental finding and removal is not necessary for symptom relief. A large, prominent spur may be removed with a rongeur.
Surgical Outcomes
Success. After plantar fascia release, 70-90% of patients report good to excellent outcomes and 80-85% achieve significant pain reduction; most return to normal activities by 3-6 months. Endoscopic and open release give similar outcomes in experienced hands, and endoscopic release may give a faster return.
Open versus endoscopic. Open plantar fasciotomy succeeds in 75-90%, with 80-85% patient satisfaction, complications in 10-15% (nerve injury, lateral column overload) and return to full activity at 3-6 months. Endoscopic fasciotomy succeeds in 80-90%, with faster recovery, 4-8 weeks to regular footwear, and a lower complication rate of 5-10%.
Success is predicted by:
- Appropriate patient selection (failed all conservative measures)
- Correct diagnosis (no alternative pathology)
- Partial (not complete) fascia release
- Compliance with postoperative rehabilitation
- Non-workers' compensation cases
Failure is predicted by:
- An incomplete conservative trial
- Workers' compensation or litigation
- Secondary gain issues
- Peripheral neuropathy or systemic disease
- Complete fascia release, which causes new problems
How much to release. The rule is to release no more than the medial 50%. The Monteagudo review below describes the most accepted operation as open release of approximately the medial third, plus release of the first branch of the lateral plantar nerve, which sits within that limit.
Molund RCT: Proximal medial gastrocnemius recession plus stretching versus stretching
- 40 patients with plantar heel pain for more than 1 year randomised to home stretching alone or recession plus stretching
- AOFAS rose from 59.5 to 88.0 after recession versus 52.5 to 65.5 with stretching alone; AOFAS, VAS pain and SF-36 significantly better with surgery at 12 months
- Ankle dorsiflexion increased from 6 to 10.5 degrees; forefoot plantar pressure rose after recession
- 6-year follow-up (Riiser 2024, PMID 37902240): 33 of 40 reviewed, 7 crossovers to surgery; per-protocol AOFAS 88.9 vs 78.6 and VAS 2.5 vs 5.5 favoured recession
Monteagudo: Plantar fasciopathy — current concepts review
- Plantar fasciopathy affects roughly one in ten people in their lifetime, and around 90% resolve within 12 months with conservative care
- Eccentric calf stretching combined with fascia-specific stretching is the non-operative treatment of choice for chronic disease
- Medial open release of approximately the medial third of the fascia plus release of the first branch of the lateral plantar nerve is the most accepted surgical option
- Isolated proximal medial gastrocnemius release achieves excellent results for refractory cases without the complications of plantar fasciotomy
Complications
Conservative Treatment Complications
Injection and shockwave. The risks of steroid injection are listed under Management (Injections), and rupture is described below. ESWT causes pain during treatment, usually mild and tolerable, and bruising that resolves in 1-2 weeks; nerve injury and skin burns are very rare.
Night splints. Besides poor compliance (see Management), they cause skin irritation from friction at points of contact and calf cramping from the prolonged dorsiflexion stretch.
Surgical Complications
Intraoperative complications:
- Nerve injury - the Baxter nerve (first branch of the lateral plantar nerve), causing lateral heel numbness or burning pain
- Incomplete release - under-release fails to relieve symptoms
- Excessive release - over-release, more than 50%, causes lateral column overload
- Vascular injury - rare; the medial plantar artery is at risk
Early postoperative complications, under 6 weeks:
- Wound infection - 1-2% incidence
- Haematoma - usually resolves spontaneously
- Wound dehiscence - more common in diabetics, smokers, or with excessive early activity
- Deep vein thrombosis - rare; consider prophylaxis in high-risk patients
Late postoperative complications, over 6 weeks:
- Lateral column pain and overload (10-15%) - see the alert below
- Arch collapse - loss of the medial longitudinal arch from complete release
- Continued heel pain (10-30%) - from incomplete release, scar tissue or an incorrect diagnosis
- Calcaneal stress fracture - rare; from altered biomechanics after release
- Tarsal tunnel syndrome - from scarring around the posterior tibial nerve
- Neuromas - entrapment of small sensory nerves in scar tissue
- Painful scar - especially if the incision is placed on the plantar surface
Lateral column overload syndrome is the most serious complication of plantar fascia release. It results from releasing more than 50% of the fascia width, causing loss of arch support, lateral foot pain, cuboid stress fractures, and peroneal tendinitis. This complication can be more disabling than the original plantar fasciitis. Prevention is essential - never release more than 50% of fascia.
Plantar Fascia Rupture (Non-Surgical)
Causes. Corticosteroid injection is the most common cause. Rupture also follows acute trauma to chronically degenerated fascia, and can occur spontaneously in severe plantar fasciitis.
Presentation. A sudden "pop" or tearing sensation in the arch brings immediate relief of the heel pain, which is the diagnostic clue. The arch collapses acutely and the foot flattens, bruising and swelling develop along the medial arch over 24-48 hours, and new lateral column pain follows from the altered biomechanics, with worse function.
Diagnosis is clinical: the pop, sudden relief of plantar heel pain and new arch collapse. Ultrasound shows discontinuity of the fascia and haematoma; MRI shows fascial disruption with surrounding oedema.
Treatment. Most ruptures are treated non-operatively:
- Walking boot for 4-6 weeks
- Custom orthoses to support the collapsed arch
- No high-impact activities for 3-6 months
- Physiotherapy to strengthen the intrinsic foot muscles and peroneal tendons
- Surgical repair rarely needed; consider it for a complete rupture with severe symptoms
Prognosis is variable. Some patients do well while others develop chronic lateral column pain, the arch may not fully recover, and return to sport is often delayed 6-12 months.
Postoperative Rehabilitation
Immediate Postoperative Period (0-2 Weeks)
After open release, the patient is non-weight-bearing or toe-touch weight-bearing in a posterior splint or boot, which is kept for 2-4 weeks. Keep the foot elevated above heart level to reduce swelling and apply ice for 15-20 minutes every 2-3 hours. The dressing stays clean and dry until the sutures come out at 10-14 days, with oral analgesics as needed.
After endoscopic release, the small incisions allow earlier mobilisation. Many protocols allow immediate protected weight-bearing as tolerated in a surgical shoe or boot, and the sutures come out at 7-10 days.
Rehabilitation Phase (2-6 Weeks)
Weight-bearing increases gradually to full weight-bearing in the boot over weeks 2-4, and the boot gives way to a supportive athletic shoe over weeks 4-6. Gentle ankle range of motion (dorsiflexion, plantarflexion, circumduction) begins at 2 weeks, avoiding forced dorsiflexion to protect the healing fascia.
Formal physiotherapy starts at 2-4 weeks, to restore range of motion, begin gentle strengthening and normalise gait. The open-release protocol places formal strengthening physiotherapy at 4-6 weeks.
Strengthening Phase (6-12 Weeks)
Strengthening progresses through four groups:
- Intrinsic foot muscles - towel curls, marble pickups
- Calf - heel raises, bilateral progressing to unilateral
- Peroneals - resistance-band eversion exercises
- Balance - single-leg stance, wobble board
Low-impact activities, walking, swimming and cycling, return at 6-8 weeks, progressing by the 10% rule.
Return to Sport Phase (3-6 Months)
Interval running begins at 3 months if walking is pain-free; jumping and cutting are delayed until 4-6 months, again progressing by the 10% rule. Return to activity after endoscopic release is quoted at 6-12 weeks, and return to sport after open release at 3-6 months, both depending on activity level.
Full recovery. Return to full, unrestricted activity takes 4-6 months after open release and 3-4 months after endoscopic release. Gastrocnemius and plantar fascia stretching continues indefinitely, with supportive shoes with arch support, and continued use of arch supports may be needed.
Outcomes
Conservative Outcomes
With a structured conservative protocol, 70% are improved at 6 months, and 85-90% are satisfied with conservative management alone at 12 months. The Management timeline puts the cumulative figure at 6 months higher, at 80-85%, so quote improvement at 6 months as a range of 70-85% rather than a single number.
Treatment-Specific Outcomes
- Success Rate
- 70-80%
- Time to Effect
- 6-8 weeks
- Duration of Benefit
- Long-term if maintained
- Success Rate
- 60-70%
- Time to Effect
- 4-8 weeks
- Duration of Benefit
- Variable
- Success Rate
- 70-85%
- Time to Effect
- 1-2 weeks
- Duration of Benefit
- 3-6 months
- Success Rate
- 60-75%
- Time to Effect
- 6-12 weeks
- Duration of Benefit
- 12+ months
- Success Rate
- 70-80%
- Time to Effect
- 8-12 weeks
- Duration of Benefit
- 12+ months
- Success Rate
- 75-90%
- Time to Effect
- 6-12 weeks
- Duration of Benefit
- Long-term
- Success Rate
- 80-90%
- Time to Effect
- 3-6 months
- Duration of Benefit
- Long-term
Read the corticosteroid row against the Cochrane review under Management, which found no clinically meaningful effect on heel pain beyond 1 month.
Prognostic Factors
The outlook is favourable with a duration of less than 6 months, a BMI less than 30, no systemic inflammatory disease and good compliance with stretching.
It is unfavourable with bilateral symptoms, workers' compensation claims, obesity (BMI greater than 35), inflammatory arthropathy and previous failed surgery.
Guidelines, Registries & Global Practice
Global Epidemiology
Plantar fasciopathy is one of the most common causes of inferior heel pain worldwide, affecting approximately one in ten people during their lifetime, with around 90% resolving within 12 months of conservative care (Monteagudo, EFORT Open Rev 2018, DOI). Peak incidence is in the 40-60 year age group. The dominant, modifiable risk factors are consistent across populations: a matched case-control study found reduced ankle dorsiflexion the strongest factor (odds ratio 23.3 for ≤0° versus over 10°), with obesity (BMI over 30: OR 5.6) and prolonged occupational weight-bearing (OR 3.6) also independently associated (Riddle, JBJS Am 2003, DOI).
Major Guidelines — Side by Side
- Diagnosis & imaging
- Clinical; imaging reserved for atypical or refractory cases
- First-line
- Stretching (fascia-specific + calf), orthoses, activity modification
- Adjuncts / second-line
- Night splints, ESWT, short-term corticosteroid (limit number due to rupture risk)
- Surgery threshold
- After failure of comprehensive conservative care (≥6 months)
- Diagnosis & imaging
- Clinical diagnosis; imaging only if diagnosis in doubt
- First-line
- Reassurance (self-limiting), footwear advice, stretching, weight loss
- Adjuncts / second-line
- Orthoses, physiotherapy; ESWT considered for persistent pain
- Surgery threshold
- Refer to specialist only after sustained failure of conservative care
- Diagnosis & imaging
- Clinical; ultrasound (fascia over 4mm) supports uncertain cases
- First-line
- Eccentric calf + fascia-specific stretching (treatment of choice)
- Adjuncts / second-line
- ESWT for chronic disease; injections used cautiously
- Surgery threshold
- Medial open release of medial third + Baxter nerve release; gastrocnemius recession for selected refractory cases
There is broad international agreement on three points: the diagnosis is clinical, conservative care is first-line for at least 6-12 months, and surgery is a last resort for a small refractory minority. The main areas of genuine variation are the role and energy protocol of ESWT (more entrenched in European and US specialist practice), enthusiasm for PRP versus corticosteroid, and whether isolated gastrocnemius recession is offered as a fascia-sparing alternative to fasciotomy.
Evidence Base for Key Recommendations
- Strength
- Level I RCT
- Source
- DiGiovanni 2006, DOI
- Strength
- Level I RCT
- Source
- Gollwitzer 2015, DOI
- Strength
- Level I RCT
- Strength
- Level I RCT
- Strength
- Level I Cochrane
- Source
- David 2017, DOI
- Strength
- Level I Cochrane
- Source
- Hawke 2008, DOI
- Strength
- Expert consensus
- Source
- Monteagudo 2018, DOI
Registry & Surveillance Note
Plantar fasciopathy is a soft-tissue, predominantly non-operative condition, so it is not tracked by the arthroplasty/implant registries (NJR, AJRR, AOANJRR). Population-level burden is instead captured through primary-care and insurance datasets; in the USA it accounts for roughly one million patient visits annually, underscoring its public-health importance despite its benign natural history.
Global Practice Variation
In high-resource settings, refractory patients can readily access podiatry, formal physiotherapy, ESWT and image-guided injections before surgery is contemplated. In limited-resource settings, management relies more heavily on low-cost, high-value interventions — patient education, calf and fascia stretching, weight management, footwear modification and prefabricated insoles — which address the same modifiable risk factors and resolve the large majority of cases without specialist referral. Work-relatedness (prolonged standing on hard surfaces) is recognised across jurisdictions, with return-to-work and workplace-modification programmes a common feature of occupational management.
MCQ Practice Points
Q: What is the windlass mechanism and how does it relate to plantar fasciitis?
A: Passive toe dorsiflexion tightens the plantar fascia, raising the medial longitudinal arch and converting the foot to a rigid lever for push-off. This mechanism creates repetitive tension at the calcaneal origin, predisposing to degeneration. Dorsiflexion of the great toe reproduces pain (windlass test).
Q: What percentage of plantar fasciitis cases resolve with conservative management and what is the recommended duration before considering surgery?
A: 90% resolve with conservative management within 12 months. A minimum of 6-12 months of conservative treatment is mandatory before considering surgical intervention. Conservative measures include stretching, orthoses, night splints, and activity modification.
Q: What is the clinical significance of a calcaneal heel spur in a patient with plantar heel pain?
A: Heel spurs are an incidental finding present in 50% of asymptomatic individuals. They are NOT the cause of pain and do not correlate with symptom severity. The spur originates from the flexor digitorum brevis, not the plantar fascia. Spur excision is NOT routinely performed with plantar fascia release.
Q: In plantar fascia release surgery, what percentage of the fascia should be released and why?
A: Release the medial 50% ONLY. Complete release causes lateral column overload with lateral foot pain and arch collapse. The windlass mechanism is eliminated, causing push-off weakness. Partial release preserves some mechanical function while decompressing the medial insertion.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 48-year-old female school teacher presents with 3 months of left heel pain. She describes severe pain with the first steps in the morning that improves after walking for 10 minutes but returns after prolonged standing at work. She is otherwise healthy with BMI of 32. Examination reveals exquisite tenderness at the medial calcaneal tubercle. Ankle dorsiflexion is 5 degrees with knee extended. How would you manage this patient?”
“A 52-year-old recreational runner presents with 18 months of right heel pain despite comprehensive conservative treatment including PT, custom orthoses, night splints, two cortisone injections, and ESWT. Pain significantly limits his running and daily activities. MRI shows plantar fascia thickening to 7mm with no other pathology. He is motivated and understands recovery time. Would you offer surgery, and if so, what procedure?”
“A 45-year-old male presents with 6 months of medial heel pain that is worse at night and described as burning. Pain radiates to the lateral heel. He has undergone 3 months of PT and stretching without improvement. Examination reveals tenderness at the medial heel but also a positive Tinel sign deep between the abductor hallucis and quadratus plantae. How does this change your management?”
Key Definitions
- Plantar fasciitis: a degenerative condition of the plantar fascia origin causing inferior heel pain - plantar fasciosis or plantar heel pain are the preferred terms
- Windlass mechanism: passive toe extension tightens the fascia and raises the arch - the basis for the windlass test
- Baxter's nerve: the first branch of the lateral plantar nerve, running between abductor hallucis and quadratus plantae - it can mimic plantar fasciitis
- Partial release: surgical release of the medial 50% of the fascia only - complete release causes lateral column overload
Epidemiology Numbers
- 10% lifetime incidence in the population
- 40-60 years is the peak age of onset
- 90% resolve with conservative management within 12 months
- 4 mm is the normal plantar fascia thickness on ultrasound (over 4 mm in plantar fasciitis)
- 50% have a heel spur, but it is an incidental finding rather than the cause of pain
- 70-90% success rate with surgical release in properly selected patients
Risk Factors
- Prolonged standing or walking occupations
- Limited ankle dorsiflexion (less than 10 degrees)
- Age 40-60 years
- No arch support (pes planus or cavus)
- Training errors in runners
- Adiposity (BMI over 30)
- First-step pain (the classic symptom)
Clinical Diagnosis
- First-step pain: severe pain with the first steps in the morning or after sitting (95% sensitive)
- Point tenderness: at the medial calcaneal tubercle - the most specific finding
- Windlass test: passive hallux dorsiflexion reproduces the pain, confirming the fascia as the source
- Limited dorsiflexion: less than 10 degrees with the knee extended is a risk factor
- Red flags: night pain, burning pain or radiation suggest an alternative diagnosis such as nerve entrapment
Conservative Treatment Stages
- 0-6 weeks (acute): stretching (fascia-specific and gastrocnemius), ice, NSAIDs, activity modification, supportive footwear
- 6 weeks to 3 months (subacute): add physiotherapy, night splints and orthoses; consider ESWT
- 3-6 months (chronic): ESWT (2000-4000 shocks); consider steroid injection, maximum of 2 because of rupture risk
- 6-12 months (refractory): repeat injection or trial PRP, and rule out alternative diagnoses with MRI
- Over 12 months: consider surgery only if ALL conservative measures have failed
Injection Therapies
- Steroid: short-term relief lasting about a month but no long-term benefit; rupture uncommon but real (about 10% in one series, 2 in 699 in trials); maximum 2 injections; use a medial approach to spare the fat pad
- PRP: slower onset but better long-term outcomes than steroid at 3-6 months, with a lower rupture risk; 2-3 mL under ultrasound guidance
- Technique: a medial approach under ultrasound guidance lets you visualise the fascia and avoid injecting the fat pad
Surgical Indications (Strict)
- Failed 6-12 months of comprehensive conservative treatment
- All measures tried: stretching, physiotherapy, orthoses, night splints, ESWT, and at least one injection
- Imaging confirmation: MRI to rule out an alternative diagnosis if needed
- Significant impairment: pain limiting activities of daily living and quality of life
- Motivated patient: understands the recovery time and holds realistic expectations
Surgical Technique Principles
- Partial release only: release the medial 50% of the fascia - NEVER a complete release
- Complete release causes lateral column overload, arch collapse, and pain worse than the original problem
- Open approach: a 3-4 cm medial incision lets you visualise and release the medial half, and allows Baxter's nerve decompression
- Endoscopic: medial and lateral 1 cm portals give faster recovery but cannot address the nerve
- Heel spur: do NOT routinely excise it - an incidental finding that does not require removal
- Baxter's nerve: decompress if there is burning pain, night pain, or a positive Tinel sign suggesting entrapment
Surgical Outcomes
- Success: 70-90% good to excellent outcomes in properly selected patients
- Recovery: return to running at 3-4 months after endoscopic release, or 4-6 months after open release
- Continued pain: 10-30% have residual symptoms despite surgery
- Complications: lateral column overload (10-15% if over-released), nerve injury, infection, and continued pain
Differential Diagnosis
- Baxter's nerve entrapment: burning pain, night pain, radiation to the lateral heel, and a Tinel sign deep between abductor hallucis and quadratus plantae
- Tarsal tunnel: posterior tibial nerve compression, with a Tinel sign posterior to the medial malleolus and radiation into the plantar foot
- Calcaneal stress fracture: pain on medial-lateral squeeze, with a history of increased activity
- Fat pad atrophy: diffuse heel pain, a history of steroid injections, and no focal tenderness
- Inflammatory arthritis: bilateral symptoms, morning stiffness over 30 minutes, and systemic features
Exam Viva Pearls
- Plantar fasciosis, not fasciitis: histology shows degeneration (myxoid change, collagen necrosis) rather than inflammation
- The heel spur is incidental: present in 50% of plantar fasciitis but also in 15-25% of asymptomatic people, so it is not the cause
- Fascial rupture presentation: a sudden pop, immediate relief of the heel pain, arch collapse, bruising, and new lateral column pain
- The 50% rule: never release more than 50% of the fascia width, to prevent lateral column overload
- Baxter's nerve anatomy: the first branch of the lateral plantar nerve, between abductor hallucis and quadratus plantae - an important differential
- Conservative treatment is key: 90% resolve without surgery, so set realistic expectations of a 6-12 month timeline
Evidence Base and Guidelines
Cochrane Review: Custom-made foot orthoses for foot pain
- Eleven RCTs (1332 participants), of which five evaluated custom orthoses for plantar fasciitis
- Only 'silver level' evidence for custom orthoses in plantar fasciitis — it is unclear whether they outperform sham or prefabricated devices
- Custom orthoses were a safe intervention across all studies
- Supports custom orthoses as an adjunct rather than a stand-alone cure for plantar heel pain
DiGiovanni RCT (2-year follow-up): Plantar fascia-specific stretching
- Two-year follow-up of an RCT in which the tissue-specific plantar fascia-stretching protocol was favoured over Achilles stretching at 8 weeks
- All patients adopted the fascia-specific stretch after 8 weeks; by 2 years there was no significant between-group difference, confirming durable benefit
- 92% of patients reported satisfaction and 94% reported a decrease in pain at 2 years
- Establishes tissue-specific plantar fascia stretching as the key, inexpensive component of conservative treatment
Riddle: Risk factors for plantar fasciitis — matched case-control study
- Matched case-control study (50 cases, 100 controls) identifying independent risk factors for plantar fasciitis
- Reduced ankle dorsiflexion was the strongest factor — ≤0° gave an odds ratio of 23.3 (95% CI 4.3-124.4) versus over 10° of dorsiflexion
- BMI over 30 kg/m² conferred an odds ratio of 5.6 (95% CI 1.9-16.6)
- Spending most of the workday weight-bearing gave an odds ratio of 3.6 (95% CI 1.3-10.1)
Lemont: Plantar fasciitis is a degenerative fasciosis without inflammation
- Histological review of 50 heel-spur surgery specimens for chronic plantar fasciitis
- Findings showed myxoid degeneration, fascial fragmentation and bone-marrow vascular ectasia — not inflammation
- Supports the term 'plantar fasciosis': a degenerative process rather than a true fasciitis
- Authors warn serial corticosteroid injection into degenerative fascia should be re-evaluated given the risk of rupture
Bazaz & Ferkel: Results of endoscopic plantar fascia release
- Case series of 20 patients (23 feet) undergoing endoscopic plantar fascia release with mean 47-month follow-up
- AOFAS hindfoot score improved from 66 to 88 and Maryland Foot Score from 62 to 83 (both p<0.05)
- Patients with symptoms longer than 2 years before surgery and workers'-compensation patients had inferior results
- Obesity had no negative effect on outcome; supports careful patient selection for endoscopic release
References
-
Hawke F, Burns J, Radford JA, du Toit V. Custom-made foot orthoses for the treatment of foot pain. Cochrane Database Syst Rev. 2008;(3):CD006801.
-
DiGiovanni BF, Nawoczenski DA, Malay DP, et al. Plantar fascia-specific stretching exercise improves outcomes in patients with chronic plantar fasciitis. A prospective clinical trial with two-year follow-up. J Bone Joint Surg Am. 2006;88(8):1775-1781.
-
Tong KB, Furia J. Economic burden of plantar fasciitis treatment in the United States. Am J Orthop. 2010;39(5):227-231.
-
Riddle DL, Pulisic M, Pidcoe P, Johnson RE. Risk factors for plantar fasciitis: a matched case-control study. J Bone Joint Surg Am. 2003;85(5):872-877.
-
Lemont H, Ammirati KM, Usen N. Plantar fasciitis: a degenerative process (fasciosis) without inflammation. J Am Podiatr Med Assoc. 2003;93(3):234-237.
-
McMillan AM, Landorf KB, Barrett JT, Menz HB, Bird AR. Diagnostic imaging for chronic plantar heel pain: a systematic review and meta-analysis. J Foot Ankle Res. 2009;2:32.
-
Gollwitzer H, Saxena A, DiDomenico LA, et al. Clinically relevant effectiveness of focused extracorporeal shock wave therapy in the treatment of chronic plantar fasciitis: a randomized, controlled multicenter study. J Bone Joint Surg Am. 2015;97(9):701-708.
-
Bazaz R, Ferkel RD. Results of endoscopic plantar fascia release. Foot Ankle Int. 2007;28(5):549-556.
-
David JA, Sankarapandian V, Christopher PR, Chatterjee A, Macaden AS. Injected corticosteroids for treating plantar heel pain in adults. Cochrane Database Syst Rev. 2017;(6):CD009348.
-
Monto RR. Platelet-rich plasma efficacy versus corticosteroid injection treatment for chronic severe plantar fasciitis. Foot Ankle Int. 2014;35(4):313-318.
-
Neufeld SK, Cerrato R. Plantar fasciitis: evaluation and treatment. J Am Acad Orthop Surg. 2008;16(6):338-346.
-
Monteagudo M, de Albornoz PM, Gutierrez B, Tabuenca J, Alvarez I. Plantar fasciopathy: A current concepts review. EFORT Open Rev. 2018;3(8):485-493.
-
Davies MS, Weiss GA, Saxby TS. Plantar fasciitis: how successful is surgical intervention? Foot Ankle Int. 1999;20(12):803-807.
-
Gollwitzer H, Saxena A, DiDomenico LA, et al. Clinically relevant effectiveness of focused extracorporeal shock wave therapy in the treatment of chronic plantar fasciitis: a randomized, controlled multicenter study. J Bone Joint Surg Am. 2015;97(9):701-708.
-
League AC. Current concepts review: plantar fasciitis. Foot Ankle Int. 2008;29(3):358-366.
-
Cole C, Seto C, Gazewood J. Plantar fasciitis: evidence-based review of diagnosis and therapy. Am Fam Physician. 2005;72(11):2237-2242.
-
Thomas JL, Christensen JC, Kravitz SR, et al. The diagnosis and treatment of heel pain: a clinical practice guideline-revision 2010. J Foot Ankle Surg. 2010;49(3 Suppl):S1-19.
-
Goff JD, Crawford R. Diagnosis and treatment of plantar fasciitis. Am Fam Physician. 2011;84(6):676-682.
-
Buchbinder R. Clinical practice. Plantar fasciitis. N Engl J Med. 2004;350(21):2159-2166.
-
Cornwall MW, McPoil TG. Plantar fasciitis: etiology and treatment. J Orthop Sports Phys Ther. 1999;29(12):756-760.
-
Haake M, Buch M, Schoellner C, et al. Extracorporeal shock wave therapy for plantar fasciitis: randomised controlled multicentre trial. BMJ. 2003;327(7406):75.
-
Buchbinder R, Ptasznik R, Gordon J, Buchanan J, Prabaharan V, Forbes A. Ultrasound-guided extracorporeal shock wave therapy for plantar fasciitis: a randomized controlled trial. JAMA. 2002;288(11):1364-1372.
-
De Garceau D, Dean D, Requejo SM, Thordarson DB. The association between diagnosis of plantar fasciitis and Windlass test results. Foot Ankle Int. 2003;24(3):251-255.
-
Molund M, Husebye EE, Hellesnes J, Nilsen F, Hvaal K. Proximal medial gastrocnemius recession and stretching versus stretching as treatment of chronic plantar heel pain. Foot Ankle Int. 2018;39(12):1423-1431.
-
Riiser MO, Husebye EE, Hellesnes J, Molund M. Outcomes after proximal medial gastrocnemius recession and stretching vs stretching as treatment of chronic plantar fasciitis at 6-year follow-up. Foot Ankle Int. 2024;45(1):1-9.
-
Acevedo JI, Beskin JL. Complications of plantar fascia rupture associated with corticosteroid injection. Foot Ankle Int. 1998;19(2):91-97.