Dial Test | Arcuate Sign | Combined PCL | Reconstruction
- PLC = primary restraint to EXTERNAL ROTATION and VARUS
- Dial test at 30 degrees only = isolated PLC. At 30 AND 90 degrees = combined PCL
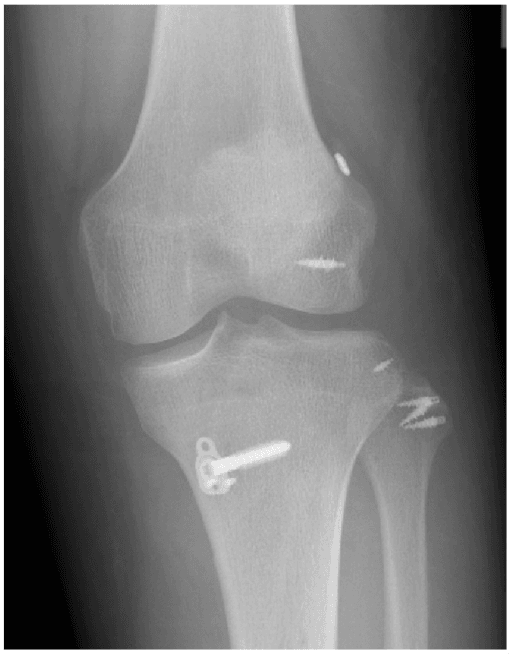
- Arcuate sign on X-ray = avulsion of PLC attachment to fibula
- Missing PLC injury = ACL/PCL graft failure
- Reconstruct rather than repair for best outcomes
- “Varus thrust gait = chronic PLC deficiency
- “Common peroneal nerve at risk (20%+ injuries)
- “LaPrade anatomic reconstruction = gold standard
- “Address varus alignment with osteotomy before/with PLC
Overview and Epidemiology
Posterolateral corner (PLC) injuries make up about 16% of knee ligament injuries, and 60-70% occur with a cruciate injury. They are frequently missed at first presentation, and a missed PLC leads to cruciate graft failure, so every injured structure must be addressed. Keep a high index of suspicion in any PCL or ACL injury.
Who and how. The injury is usually the product of high-energy trauma. Motor vehicle collisions are a common cause, and in sport it is seen in football, soccer and skiing. The mechanisms:
- Varus force - a direct blow to the medial knee
- Hyperextension with a varus component
- External rotation on a planted foot
- Knee dislocation - the multiligament pattern
- Contact sports - a direct lateral blow
Anatomy and Function
The structures. LaPrade's anatomic description centres on three primary static stabilisers. The fibular collateral ligament (FCL) runs from the lateral femoral epicondyle to the lateral fibular head. The popliteus tendon, the tendon of a muscle-tendon unit, has its femoral origin on the lateral femoral condyle and inserts on the tibia, and the popliteofibular ligament connects the popliteus to the fibular styloid. Tendon and ligament together form the popliteus complex.
The capsule. The posterolateral capsule, with the arcuate ligament, forms the arcuate complex, a further static stabiliser.
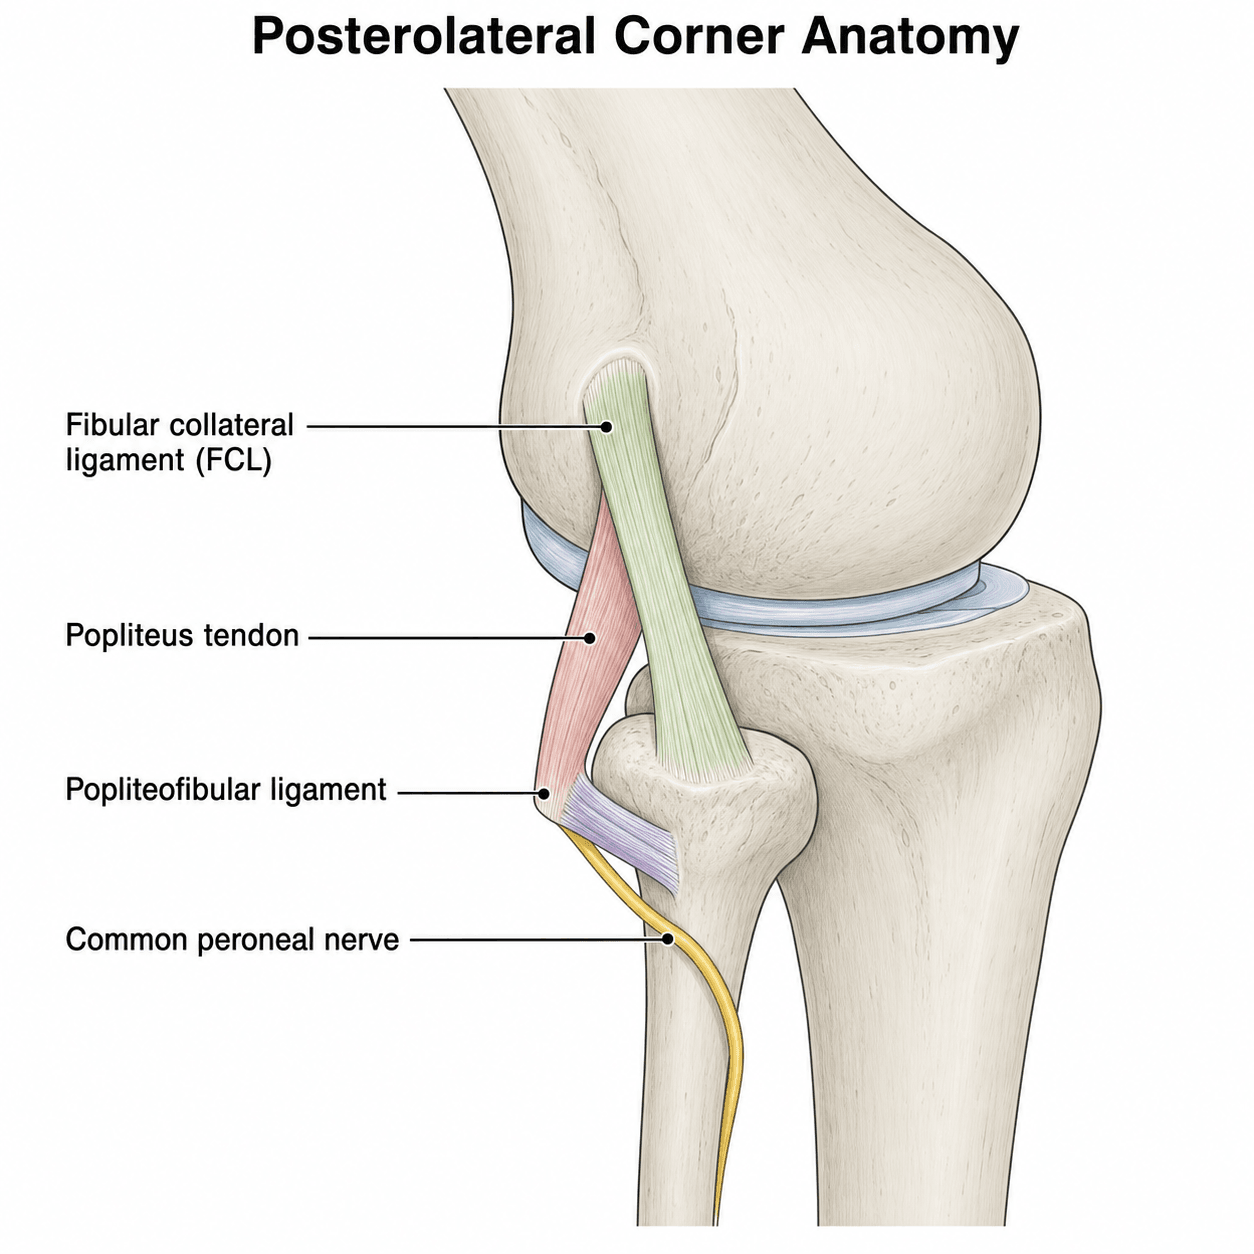
FAPPLC Structures
Hook:FAP structures form the PLC!
What the corner resists. The PLC is the primary restraint to varus and to external rotation. The FCL is the primary varus restraint and the popliteus complex the primary external-rotation restraint. Secondarily the corner resists posterior translation at full extension and hyperextension (recurvatum). It tightens in extension, and as a secondary backup to the ACL it helps control anterior translation.
The PLC and the PCL. The two work together: the PCL resists posterior translation and the PLC resists rotation. Loss of one stresses the other.
The common peroneal nerve. It wraps around the fibular neck and is very vulnerable, injured in 20%+ of PLC injuries. Injury shows as foot drop with numbness over the lateral leg and the dorsum of the foot.
Test ankle dorsiflexion and toe extension and document sensation before any operation. The record has medicolegal importance, and nerve injury affects rehabilitation and prognosis.
Classification Systems
Grade. The grade is set by dial-test asymmetry compared with the contralateral side.
- External Rotation
- Less than 5 degree increase
- Varus
- Minimal
- Implication
- Sprain, intact structures
- External Rotation
- 5-10 degree increase
- Varus
- Moderate
- Implication
- Partial tear
- External Rotation
- Greater than 10 degree increase
- Varus
- Significant
- Implication
- Complete rupture, surgery indicated
Injury pattern. The corner is torn alone or with other ligaments:
- Isolated PLC - rare (under 30%), and still usually needs reconstruction
- Combined PCL/PLC - the most common pattern (50%+)
- Combined ACL/PLC - also common
- Multiligament (knee dislocation) - check for vascular injury and examine every ligament
By structure. An FCL injury gives primary varus laxity at 30 degrees; a popliteus injury gives external-rotation laxity on the dial test. Usually both are involved. Avulsions may be femoral or fibular, and the arcuate sign marks a fibular one. MRI determines which structures are injured.
Fanelli classification. Fanelli grades the injury by external rotation plus the degree of varus laxity, and so maps it onto the structures torn.
- Findings
- Increased external rotation ONLY (no varus laxity)
- Structures involved
- Popliteofibular ligament and popliteus tendon
- Findings
- Increased external rotation plus MILD varus laxity (about 5 mm)
- Structures involved
- Popliteofibular ligament, popliteus, and an attenuated FCL
- Findings
- Increased external rotation plus GROSS varus laxity (about 10 mm)
- Structures involved
- FCL, popliteofibular ligament and popliteus all disrupted, with lateral capsular avulsion (often with cruciate injury)
The progression from A to C tracks increasing FCL involvement. A pure rotational Type A injury spares the FCL, whereas the varus laxity of Types B and C signals attenuation and then complete rupture of the primary varus restraint. The appearance of varus laxity is the clue that raises the injury from A to B or C and makes reconstruction, rather than rehabilitation, the answer.
The Multiligament Knee: Schenck Classification and Vascular Assessment
PLC injuries are frequently part of a knee dislocation, and the dislocated knee needs both the Schenck (KD) classification and a vascular assessment.
- Ligament pattern
- One cruciate intact (single cruciate plus a collateral)
- Ligament pattern
- Both cruciates torn, collaterals intact
- Ligament pattern
- Both cruciates plus ONE collateral - subdivided KD-IIIM (medial) or KD-IIIL (lateral/PLC)
- Ligament pattern
- Both cruciates plus BOTH collaterals
- Ligament pattern
- Dislocation with a periarticular fracture (fracture-dislocation)
A PLC injury with both cruciates is a KD-IIIL. The suffix C denotes an associated arterial injury and N a nerve injury.
The popliteal artery. Tethered proximally at the adductor hiatus and distally at the soleal arch, it is at high risk in any dislocation, and its assessment is the limb-threatening priority. Examine the pulses and measure the ankle-brachial index (ABI):
- ABI 0.9 or above - serial vascular observation is acceptable
- ABI under 0.9 - CT angiography to exclude an intimal or occlusive injury
- Hard signs (absent pulses, expanding haematoma, bruit, active bleeding) - straight to the operating theatre and vascular surgery; do not delay for imaging
Normal pulses on arrival do not close the question. Occult intimal injury can declare late, so serial examination is essential even with initially normal pulses.
Clinical Assessment
History. The patient describes a varus blow, hyperextension or a motor vehicle accident, with lateral and posterolateral knee pain and varus instability or giving way. Ask about foot drop and numbness. A varus thrust gait belongs to the chronic injury.
Examination. The PLC examination:
- Dial test at 30 and 90 degrees - the key test
- Varus stress at 0 and 30 degrees
- External rotation recurvatum test - supine, lift the great toe; positive when the tibia drops into hyperextension and external rotation
- Reverse pivot shift - a PLC-specific test, positive as a clunk on extension
- Common peroneal nerve - motor and sensory
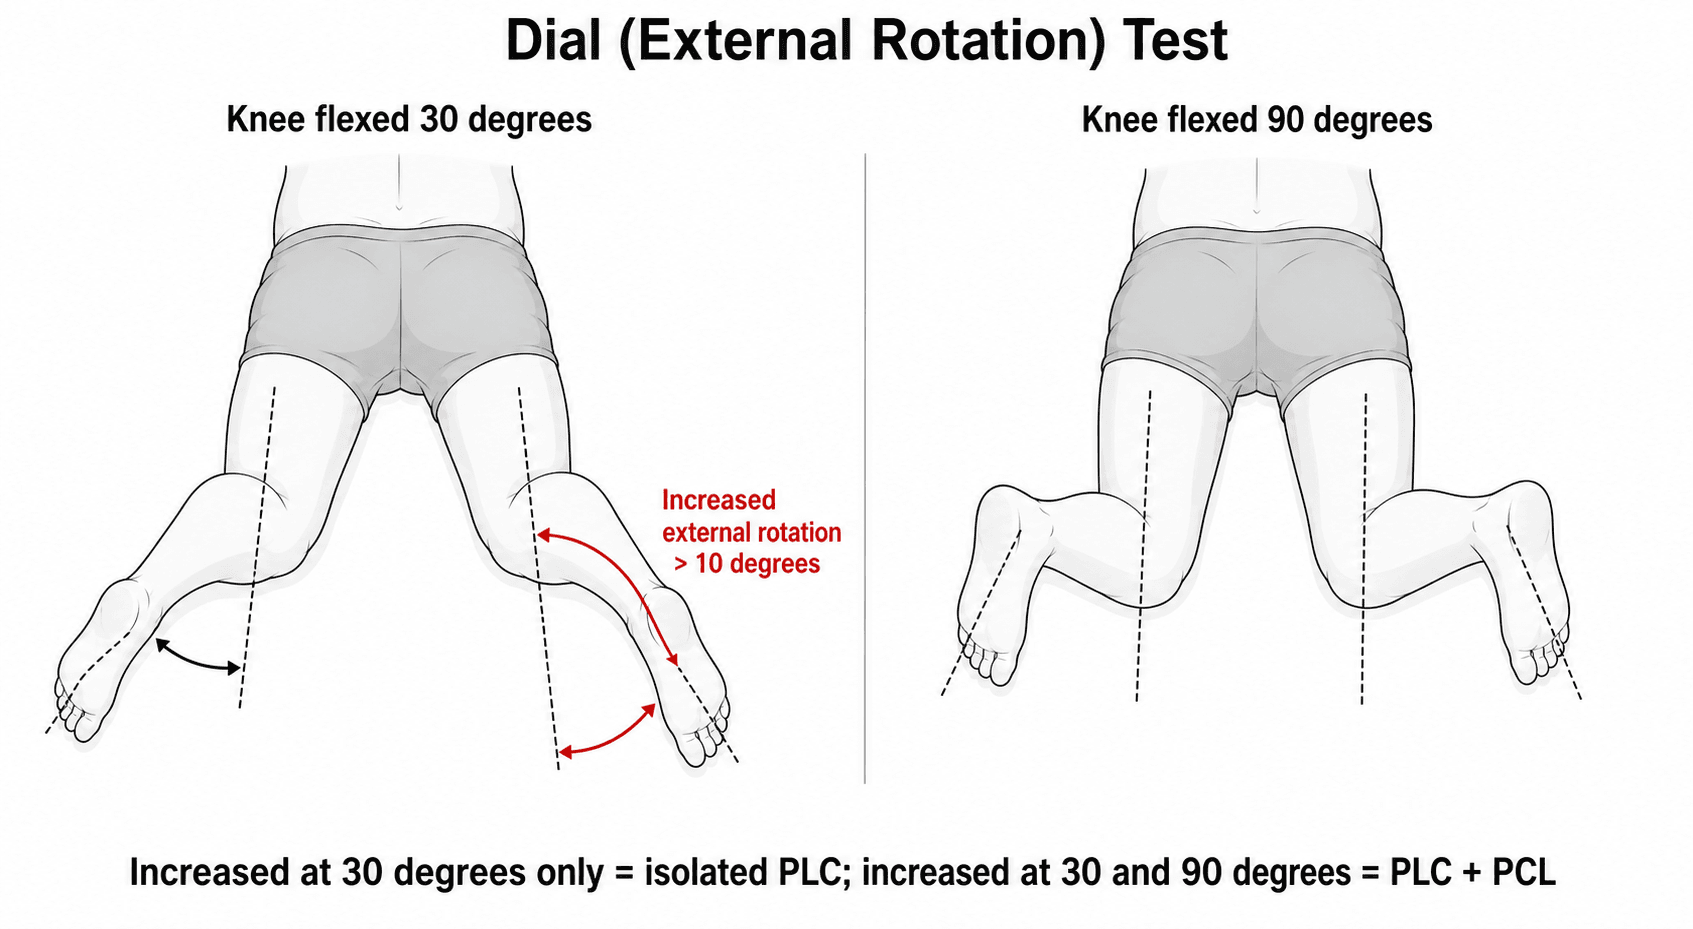
The dial test. With the patient prone and the knees flexed to 30 degrees, then 90, externally rotate both feet simultaneously and compare the thigh-foot angle side to side. An asymmetry of more than 10 degrees is positive. Positive at 30 degrees only is an isolated PLC injury; positive at 30 and 90 degrees is a combined PCL and PLC injury, because at 90 degrees an intact PCL prevents the extra external rotation. The distinction is critical for surgical planning.
Varus thrust gait. A lateral thrust during stance phase indicates chronic PLC deficiency with significant laxity.
- Key discriminator
- Dial positive at 30 only; varus laxity
- Best test
- Dial at 30 and 90; varus stress
- Pitfall
- Easily missed when subtle
- Key discriminator
- Dial positive at 30 AND 90; posterior sag
- Best test
- Posterior drawer + dial
- Pitfall
- Operating on PCL alone
- Key discriminator
- Posterior sag; dial symmetric
- Best test
- Posterior drawer
- Pitfall
- Mislabelling as PLC
- Key discriminator
- Varus laxity at 30 without rotational laxity
- Best test
- Varus stress at 30
- Pitfall
- Underestimating popliteus involvement
- Key discriminator
- Gross instability, possible vascular injury
- Best test
- ABI, CT angiography
- Pitfall
- Missing limb-threatening ischaemia
- Key discriminator
- Foot drop without major laxity
- Best test
- Motor/sensory exam, NCS
- Pitfall
- Attributing all weakness to pain
Investigations
The arcuate sign is an avulsion fracture of the fibular head or styloid on the plain radiograph. It is pathognomonic for PLC injury, indicates avulsion of the FCL and/or biceps femoris, and should make you suspect a multiligament injury.
Plain radiographs. Scrutinise the fibular head and Gerdy tubercle for an avulsion that signals a PLC injury. Beyond the arcuate sign, look for a Segond fracture of the lateral tibial plateau, a widened lateral joint space on varus stress, and osteophytes in the chronic knee. Assess the alignment for varus malalignment.
Stress radiography. Varus stress views quantify lateral joint opening, and are only meaningful compared with the contralateral side. They are useful in chronic cases, for monitoring, and in research.
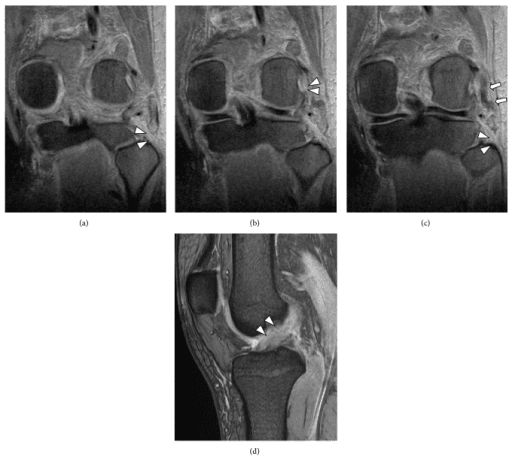
MRI. MRI is good for the PLC, but the structures can be subtle. Each is read on the images that show it best:
- FCL - coronal images
- Popliteus - sagittal and coronal
- Popliteofibular ligament - often difficult to see
- Arcuate complex - the posterolateral capsule
MRI also shows the associated injuries: peroneal nerve oedema, bone bruising and cruciate tears.
Management Algorithm
The pathway. Grade and chronicity set the course once the acute knee has been assessed.
Treatment Pathway
Document neurovascular status. MRI for the full injury pattern. Assess alignment.
Limited evidence. Bracing and rehabilitation, monitoring for progressive laxity.
Anatomic reconstruction preferred, addressing all injured structures. Early surgery (within 3 weeks) if combined.
Assess for varus thrust. May need HTO before or with PLC reconstruction.
Repair or reconstruct. Repair has a high failure rate for isolated PLC injuries, and overall reconstruction is the more durable, with repair failing in around 37% against 9%. Reconstruction gives more reliable outcomes, addresses chronic attenuation and restores the anatomy. The exception is an acute avulsion with good bone, where the fragment can be fixed.
Combined injuries. Both cruciate combinations need the cruciate and the corner reconstructed. With a PCL tear this may be a single or staged operation, and acute surgery is preferred. Early surgery prevents PLC contracture and improves outcomes.
Surgical Technique
LaPrade anatomic reconstruction. The gold standard. It reconstructs the FCL (allograft), the popliteus tendon and the popliteofibular ligament, restoring both varus and rotational stability, with superior outcomes to isolated repairs. The graft is an Achilles allograft with a bone block, or split semitendinosus. The steps:
- Separate femoral tunnels at the FCL and popliteus origins
- A fibular tunnel at the FCL insertion
- Reconstruct the FCL from femur to fibula
- Reconstruct the popliteus and popliteofibular ligament, the graft crossing from the fibula to the tibial sulcus
The principles are anatomic tunnel placement, appropriate tensioning, and addressing every structure.
Alignment. Varus malalignment increases stress on the PLC, and without alignment correction a PLC reconstruction will fail. When significant varus is present, an opening-wedge HTO of the proximal tibia corrects it to neutral or slight valgus. It may be staged before the PLC reconstruction or performed with it.
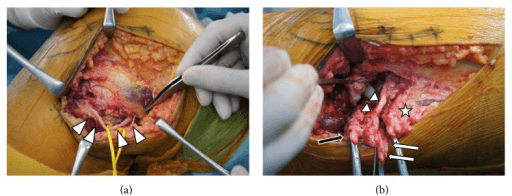
The common peroneal nerve is at risk during PLC reconstruction. Dissect meticulously, and identify and protect the nerve throughout. In chronic cases it may be scarred or displaced.
Complications
- Cause
- Traction, direct
- Prevention
- Identify and protect
- Management
- Observation, EMG, may recover
- Cause
- Technical error, missed structure
- Prevention
- Anatomic reconstruction
- Management
- Revision
- Cause
- Scarring, immobilisation
- Prevention
- Early ROM
- Management
- Physiotherapy, MUA
- Cause
- Missed varus alignment
- Prevention
- Correct alignment
- Management
- HTO then revision
Complete lesions have poor recovery and carry a poor prognosis regardless of approach. Incomplete lesions may recover over 6-12 months. Consider nerve exploration or grafting if there is no recovery at 3-6 months.
Postoperative Care
PLC Reconstruction Rehabilitation
Brace locked in extension. Non-weight bearing. Avoid external rotation.
Progressive flexion. Partial weight bearing. Quad strengthening.
Full ROM. Weight bearing progression. Closed chain exercises.
Sport-specific preparation. Pool running. Proprioception.
Functional testing. Full sport when strength and stability restored.
Avoid external rotation stress early, since it stresses the PLC reconstruction, and avoid varus stress. Progress more slowly when other reconstructions were done at the same time.
Outcomes and Prognosis
What predicts the result. Outcomes are good with anatomic reconstruction, early surgery, every structure addressed and alignment corrected. They are poor after isolated repair, delayed surgery, missed varus alignment or incomplete reconstruction, and with a peroneal nerve injury.
The long term. Addressed appropriately, the knee is stable, function is preserved, and the return to activity is good. Untreated or undertreated, it goes on to progressive varus deformity, lateral compartment osteoarthritis and cruciate graft failure.
Guidelines, Registries & Global Practice
- PLC injury accounts for roughly 16% of knee ligament injuries
- Up to 60-70% occur with a cruciate injury (rarely truly isolated)
- Common peroneal nerve involvement in 15-25% of cases
- Typical patient is young and male (mean age mid-20s to early 30s in published series)
- High-energy mechanisms predominate: road traffic trauma, contact sport, knee dislocation
- No single dedicated international society guideline exists; practice is driven by expert consensus and series
- ESSKA / European consensus: reconstruct rather than repair grade III injuries; address all structures anatomically
- AANA / AOSSM (North America): anatomic reconstruction is the reference standard for chronic and most acute grade III injuries
- AO / multiligament-knee principles: ankle-brachial index in suspected dislocation, early surgery, reconstruct the PLC/FCL
- Broad agreement that missed varus malalignment must be corrected before or with reconstruction
- European consensus (ESSKA)
- Anatomic reconstruction
- North American (AOSSM/AANA)
- Anatomic reconstruction
- Multiligament / AO principles
- Reconstruct PLC/FCL, not repair alone
- European consensus (ESSKA)
- Selective (good bony avulsion)
- North American (AOSSM/AANA)
- Selective; reconstruction favoured
- Multiligament / AO principles
- Repair carries higher failure
- European consensus (ESSKA)
- Early (within ~3 weeks)
- North American (AOSSM/AANA)
- Early for combined injuries
- Multiligament / AO principles
- Early after vascular clearance
- European consensus (ESSKA)
- Correct (staged or combined)
- North American (AOSSM/AANA)
- Correct before/with reconstruction
- Multiligament / AO principles
- Realign to protect the graft
- National knee-ligament registries (e.g. Scandinavian and UK datasets) capture mainly ACL; isolated PLC is under-represented, so high-quality outcome data come from specialist series
- Allograft is widely used in North America; many European and resource-limited settings rely on autograft (hamstring, peroneus longus, quadriceps) due to allograft cost and availability
- MRI and stress radiography availability shape how confidently PLC is diagnosed pre-operatively
- High-resource: anatomic multi-tunnel reconstruction, intra-operative fluoroscopy, allograft, structured bracing and physiotherapy
- Limited-resource: autograft, fibular-based (Larson-type) or hybrid techniques, greater reliance on clinical examination and plain films
- Universal priorities everywhere: document the peroneal nerve, exclude vascular injury in dislocations, and never miss the PLC alongside a cruciate tear
PLC injuries are high-yield viva topics. Know the dial test interpretation, arcuate sign significance, and why reconstruction is preferred. Be prepared to discuss combined injuries and the importance of addressing alignment.
Controversies and Areas of Uncertainty
Anatomic or fibular-based reconstruction. The LaPrade anatomic two-graft technique reconstructs the FCL, popliteus and popliteofibular ligament; fibular-based (Larson) techniques are simpler and reconstruct the FCL and popliteofibular ligament only. Anatomic methods better restore rotation biomechanically, but high-level comparative clinical data are limited, and many surgeons obtain good results with a hybrid approach.
Acute repair or reconstruction. Reconstruction is more durable overall, yet a good acute bony avulsion with healthy tissue can be primarily fixed. The threshold for choosing repair over reconstruction in the acute setting remains debated.
Staged or single-stage alignment. With genu varus some advocate osteotomy first, and a proportion then avoid ligament surgery; others perform combined realignment and reconstruction. Optimal sequencing, especially in multiligament knees, is unresolved.
Graft choice and nerve outcomes. Allograft versus autograft, the optimal tensioning angle, and whether early peroneal nerve exploration changes outcomes are all without consensus.
MCQ Practice Points
Q: Dial test positive at 30 degrees only vs 30 and 90 degrees? A: 30 degrees only = isolated PLC. 30 and 90 degrees = combined PCL + PLC. At 90 degrees, intact PCL prevents external rotation.
Q: What are the primary functions of the PLC? A: Varus restraint (FCL primary) and external rotation restraint (popliteus primary). Also resists hyperextension.
Q: What is the arcuate sign? A: Avulsion fracture of fibular head on X-ray. Pathognomonic for PLC injury. Indicates avulsion of FCL/biceps attachment.
Q: Why is reconstruction preferred over repair for PLC? A: Repair has 37% failure rate vs 9% for reconstruction. Reconstruction anatomically restores all structures.
Q: What nerve is at risk with PLC injuries? A: Common peroneal nerve - 20%+ injury rate. Check ankle dorsiflexion and lateral leg sensation. Document preoperatively.
Q: Why is varus alignment important in PLC injuries? A: Varus increases load on PLC. Must correct with HTO before or with reconstruction, or reconstruction will fail.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 25-year-old motorcyclist presents after an MVC. He has a swollen knee. Posterior drawer shows Grade III laxity. Dial test shows 20 degrees increased external rotation at both 30 and 90 degrees compared to the opposite side. He has ankle dorsiflexion weakness. What is your assessment and management?”
“A 35-year-old presents with lateral knee instability for 2 years after a rugby injury. He walks with a noticeable varus thrust. Dial test shows 15 degrees increased external rotation at 30 degrees, symmetric at 90 degrees. X-rays show varus alignment (mechanical axis 5 degrees varus). What is your approach?”
“A 22-year-old presents after a knee hyperextension injury during soccer. X-ray shows a small avulsion fracture of the fibular head. He has tenderness posterolaterally. Dial test is positive at 30 degrees only. What is your management?”
PLC Structures (FAP)
- FCL: Primary varus restraint
- Arcuate complex: Posterolateral capsule
- Popliteus complex: External rotation restraint
- Popliteofibular ligament connects them
Dial Test Critical
- Test at 30 AND 90 degrees
- Positive at 30 only = isolated PLC
- Positive at 30 AND 90 = combined PCL + PLC
- Greater than 10 degree asymmetry = positive
Key Findings
- Arcuate sign: Fibular head avulsion = PLC
- Varus thrust gait: Chronic PLC deficiency
- Peroneal nerve injury: 20%+ cases
- Combined injuries most common
Treatment Principles
- Reconstruction superior to repair (37% vs 9% failure)
- LaPrade anatomic technique gold standard
- Early surgery (within 3 weeks) preferred
- Address varus alignment or reconstruction fails
Exam Pearls
- Commonly missed injury - high suspicion
- Always check with PCL and ACL injuries
- Document peroneal nerve status
- Early surgery prevents contracture
Evidence Base and Key Studies
Quantitative Posterolateral Attachment Anatomy
- Cadaveric study (10 fresh-frozen knees) mapping the FCL, popliteus tendon, popliteofibular ligament and lateral gastrocnemius attachments
- FCL femoral attachment averaged 1.4 mm proximal and 3.1 mm posterior to the lateral epicondyle; fibular attachment 8.2 mm posterior to the anterior fibular head
- Popliteus femoral attachment lies in the proximal-anterior fifth of the popliteal sulcus, always anterior to the FCL (mean separation 18.5 mm)
- Popliteofibular ligament had constant anterior and posterior divisions at the fibular styloid
Anatomic PLC Reconstruction (Biomechanical Validation)
- In-vitro biomechanical study in 10 cadavers describing a 2-graft technique reconstructing the FCL, popliteus tendon and popliteofibular ligament
- Restored varus stability versus the sectioned (grade III) state at 0, 30, 60 and 90 degrees of flexion
- Restored external rotation control, with no significant difference from the intact knee at any flexion angle
- Became the reference anatomic reconstruction technique