'Toulouse-Lautrec Disease' | Cathepsin K Deficiency | Dense Fragile Bones
- Cathepsin K deficiency - CTSK gene mutation causing defective osteoclast bone resorption (collagen degradation impaired)
- Dense but fragile bones - osteosclerosis paradoxically associated with increased fracture risk and delayed healing
- Acroosteolysis - pathognomonic resorption of distal phalanges (terminal tufts) distinguishes from osteopetrosis
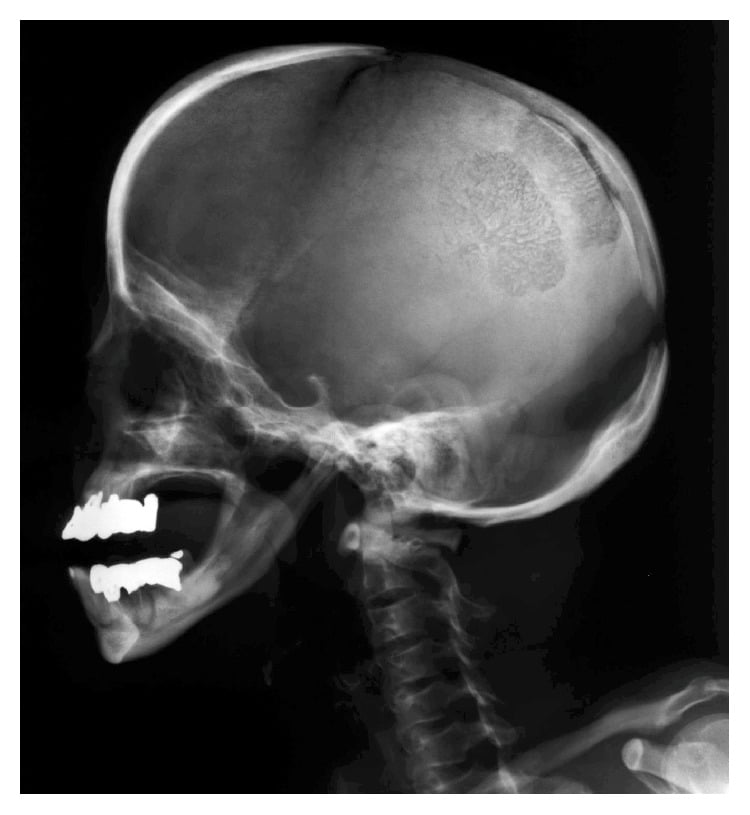
- Open fontanelles - persistent wide-open fontanelles and sutures throughout life (cranial sutures fail to close)
- Toulouse-Lautrec - famous French artist Henri de Toulouse-Lautrec is believed to have had this condition
- “Distinguish from osteopetrosis: pyknodysostosis has acroosteolysis (osteopetrosis does not)
- “Bisphosphonates are contraindicated - bone resorption is already deficient; further inhibition worsens pathology
- “Mandibular osteomyelitis is a characteristic complication due to dental extraction and poor bone vascularity
- “Know the clinical triad: short stature, osteosclerosis, acroosteolysis
Overview and Epidemiology
Pyknodysostosis (Greek pyknos, dense; dys, defective; ostosis, bone condition) is a rare autosomal recessive sclerosing bone dysplasia, first described by Maroteaux and Lamy in 1962. Its molecular basis, cathepsin K deficiency, was identified in 1996. The bones are dense on imaging, yet they fracture easily and heal slowly.
How rare. The incidence is approximately 1 per 1.7 million births, and fewer than 200 cases have been reported worldwide. Males and females are affected equally. Consanguinity is common, and prevalence is higher in populations where it is.
Natural history. The condition is present at birth and recognised in childhood. Bone density stays stable, but the fracture risk is ongoing, and the short stature is progressive. Intelligence is normal and a normal lifespan is expected.
Toulouse-Lautrec. The condition drew historical interest when it was retrospectively diagnosed in the French Post-Impressionist Henri de Toulouse-Lautrec (1864-1901), known for his vivid depictions of Parisian nightlife. His parents were first cousins, he was approximately 150cm tall, and he fractured both femurs during adolescence from minor trauma. His short stature, frequent fractures, facial features and short limbs are consistent with the diagnosis, though it remains retrospective speculation.
Pathophysiology and Genetics
The gene. Pyknodysostosis is caused by loss-of-function mutations in CTSK on chromosome 1q21, and various mutations have been described. CTSK encodes cathepsin K, a lysosomal cysteine protease that is highly expressed in osteoclasts and is essential for osteoclast-mediated bone resorption. It is the primary enzyme that degrades type I collagen in the bone matrix.
What the osteoclast can and cannot do. Without functional cathepsin K, osteoclasts can still demineralise bone but cannot degrade the organic collagen matrix, so undigested bone material accumulates in the resorption lacunae. Bone turnover is severely impaired. The result is bone that is dense but structurally abnormal.
Dense yet fragile. Because the abnormal bone lacks proper remodelling, microdamage accumulates and the bone is paradoxically brittle. The same impaired turnover is why fractures heal slowly.
Histology. Microscopy of affected bone shows:
- Normal or increased osteoclast numbers
- Demineralised bone matrix accumulating in resorption lacunae
- Disorganised bone architecture
- Increased bone mass of abnormal quality
- None of the fibrous tissue seen in fibrous dysplasia
How osteopetrosis differs. Both conditions cause osteosclerosis, but by different mechanisms. In pyknodysostosis the osteoclasts are present and partially functional: demineralisation is intact and only matrix degradation is blocked. Osteopetrosis arises from several genes (TCIRG1, CLCN7 and others, a chloride channel rather than a protease among them) and produces complete osteoclast dysfunction or absence, so demineralisation and matrix degradation both fail, and obliteration of the medullary cavity may cause bone marrow failure.
Clinical Features
The cardinal features. The presentation is a distinctive combination:
- Short stature, with adult height typically less than 150cm
- Craniofacial abnormalities: open fontanelles and an obtuse mandibular angle
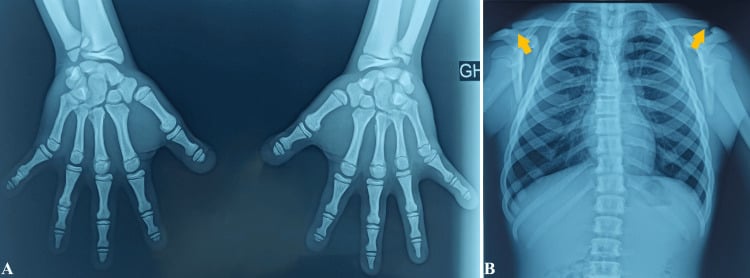
- Acroosteolysis, resorption of the terminal phalanges
- Recurrent fractures despite radiographically dense bones
- Dental abnormalities: delayed eruption and crowding
Stature. The short stature is proportionate, with a short trunk and short limbs, and adult height is typically 130-150cm. Development and intelligence are normal.
Head and face. The anterior fontanelle is widely open and palpable as a soft spot, and the fontanelles persist throughout life. The cranial sutures stay open. Look for:
- Frontal bossing and a prominent forehead
- A beaked nose
- Micrognathia, with a small chin
- An obtuse mandibular angle with relative prognathism
- A high-arched palate
- Blue sclerae, which may be present but are not pathognomonic
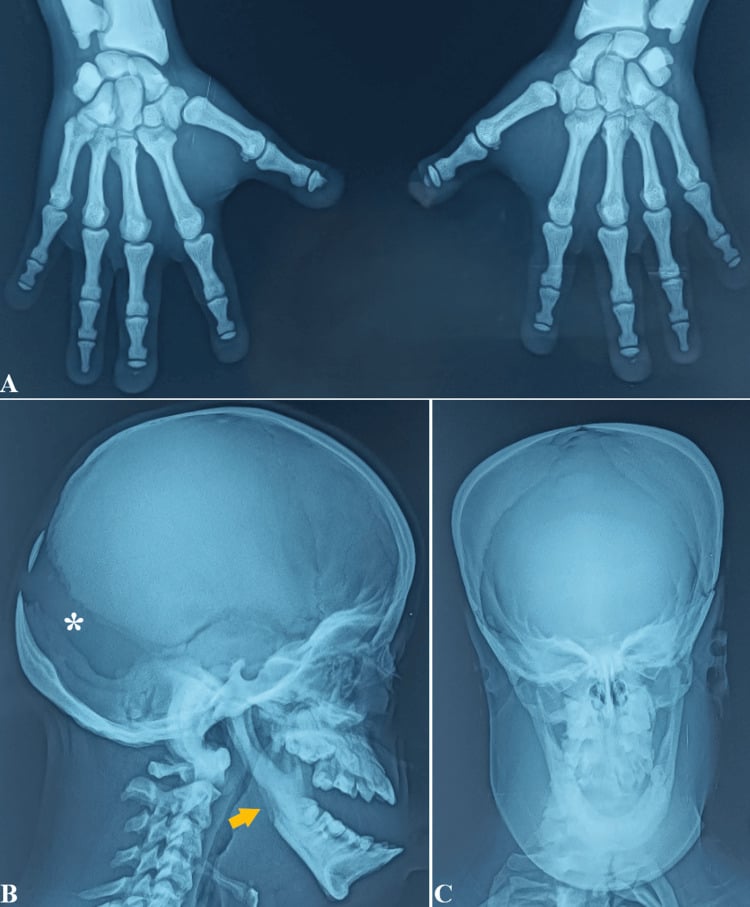
Hands. The fingers are short and stubby (brachydactyly with acroosteolysis), and the resorbed terminal phalanges make the fingertips spatulate or drumstick-like. Nails may be dystrophic or grooved, and the skin over the dorsum of the hands is wrinkled.
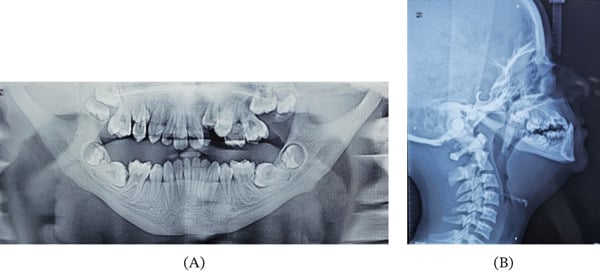
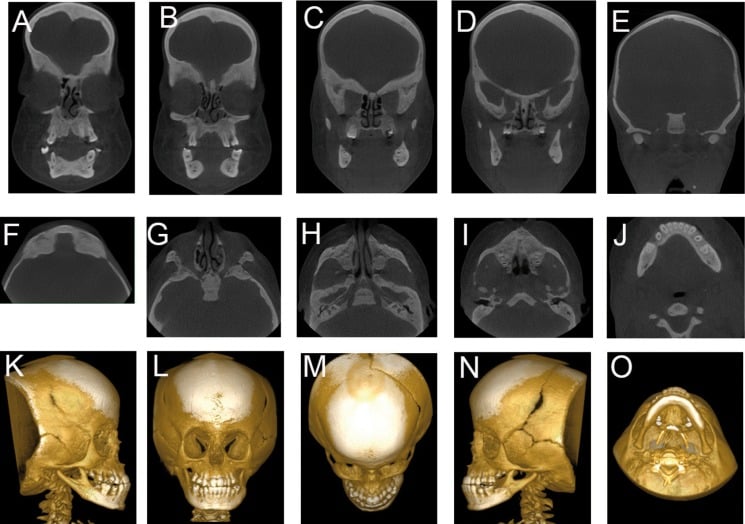
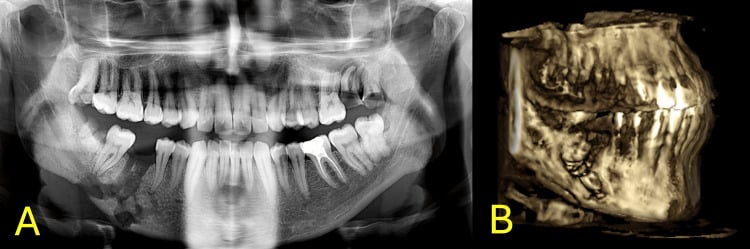
Teeth and jaw on the films. In the patient shown below, the panoramic and lateral cephalometric radiographs showed dental crowding and impaction, an obtuse mandibular angle, elongated processes and a skeletal Class III relationship.
Trunk and limbs. The clavicles are hypoplastic and may be dysplastic. Some patients have kyphoscoliosis or joint laxity. Muscle mass is generally normal, but gait may be affected by limb deformity.
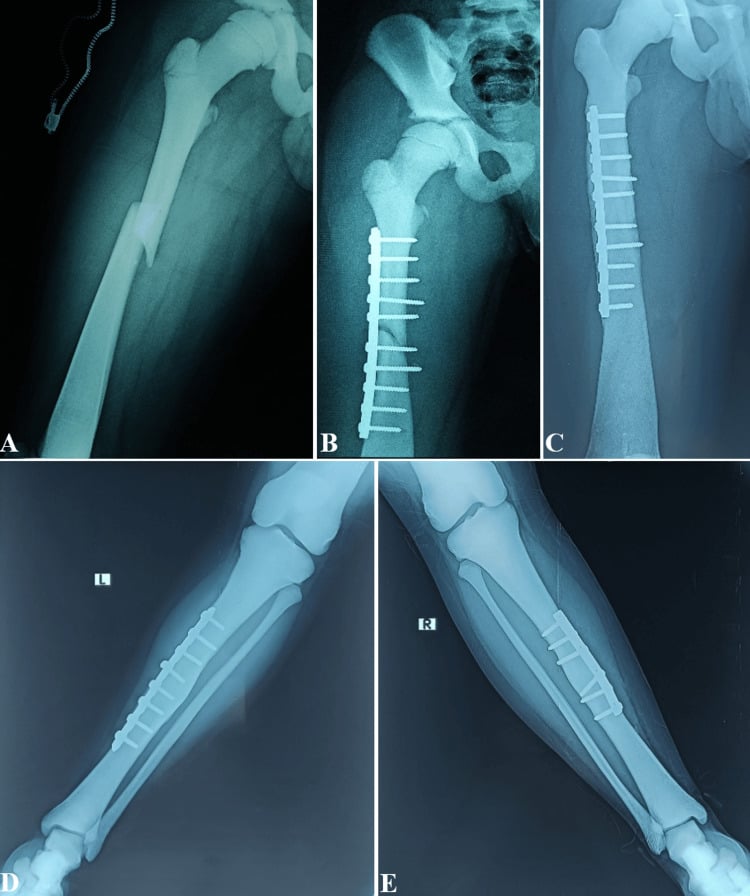
Fractures. Fractures are a major source of morbidity. They occur most often in the lower limbs, the femur and tibia, after minimal trauma. Delayed union is characteristic, the same bone may fracture several times, and deformity from repeated fractures is common.
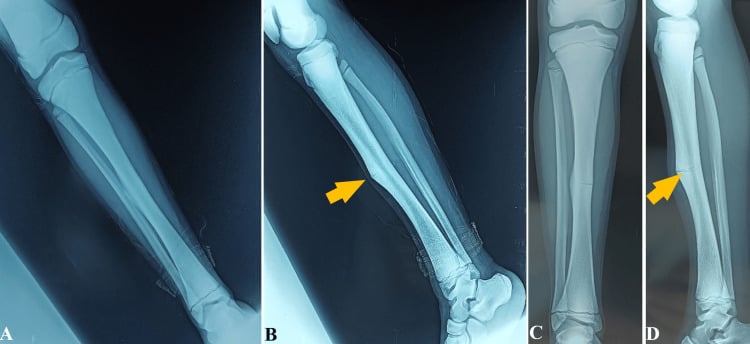
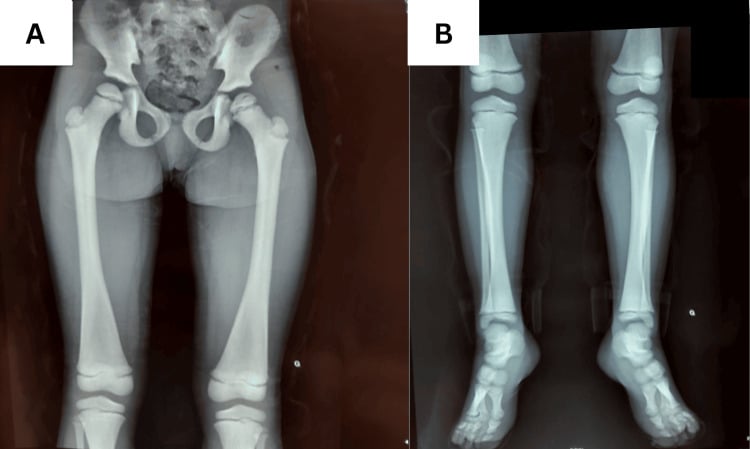
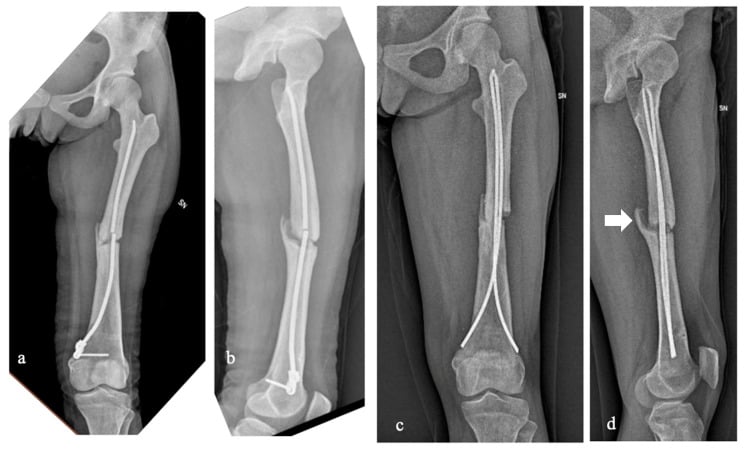
The fracture series. In one series of films, a femoral fracture was treated with plate fixation, maintained at six years, and followed by new tibial fractures. In another, the dense lower-limb bones held a mid-shaft tibial fissure and, later, a nondisplaced fracture through a limb with bulky callus from previous injuries. Serial films are essential, because pain may precede displacement.
Investigations and Radiographic Features
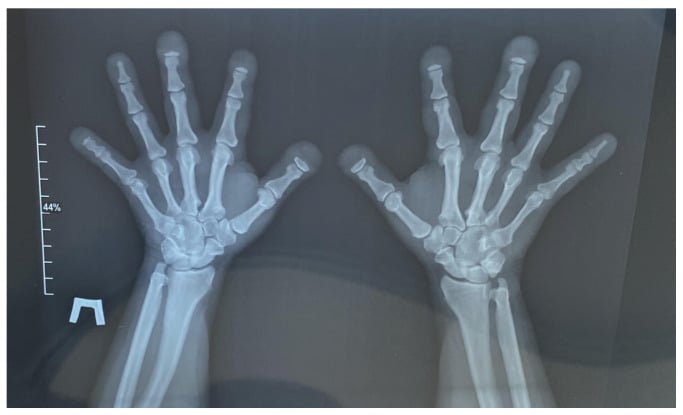
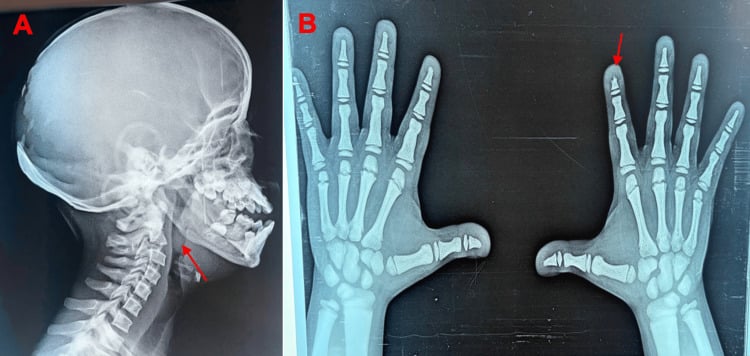
The radiographic hallmarks. Three features define the films: diffuse osteosclerosis, a uniform increase in density throughout the skeleton; acroosteolysis, resorption of the terminal phalangeal tufts; and open fontanelles and sutures.
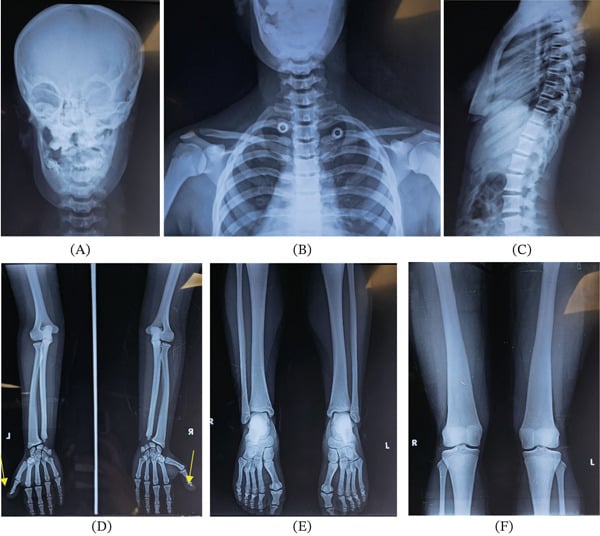
Skull. The fontanelles and sutures are widely open, with Wormian bones, and stay open into adult life. The mandible is hypoplastic with an obtuse angle, the paranasal sinuses and mastoids are absent or hypoplastic, and the calvarium is thickened and dense. Open sutures in a densely sclerotic skull are peculiar to this condition, and that is the pairing to remember.
Spine. The vertebrae are diffusely sclerotic, but without the sandwich (rugger-jersey) vertebra of osteopetrosis: the sclerosis is uniform rather than banded at the endplates. Spondylolysis or spondylolisthesis, hypoplastic posterior elements and cervical anomalies may occur.
Long bones. The sclerosis is generalised, with increased medullary density and thickened cortices, but metaphyseal modelling is relatively preserved, so there is no Erlenmeyer flask deformity. Look for healed fractures, often malunited: transverse fractures of the femur or tibia after trivial injury are how many of these patients present.
Hands. Resorption of the distal phalangeal tufts is progressive, so the ungual tufts look eroded or absent, and the metacarpals and phalanges are short. This is the single finding that separates pyknodysostosis from every other sclerosing dysplasia. Its mechanism is unclear, but may relate to altered mechanical stress or vascular compromise in the acral regions.
Osteosclerosis with acroosteolysis is virtually diagnostic. A dense skeleton with dissolving fingertips is the diagnosis.
- Pyknodysostosis
- Diffuse osteosclerosis
- Osteopetrosis
- Diffuse osteosclerosis
- Pyknodysostosis
- PRESENT (pathognomonic)
- Osteopetrosis
- ABSENT
- Pyknodysostosis
- Persistently open
- Osteopetrosis
- Normal closure
- Pyknodysostosis
- Relatively preserved
- Osteopetrosis
- Erlenmeyer flask deformity
- Pyknodysostosis
- Uniform sclerosis
- Osteopetrosis
- Sandwich or rugger-jersey spine
- Pyknodysostosis
- Absent
- Osteopetrosis
- May be present
CT. CT delineates the skull base better, assesses the absent paranasal sinuses, shows how a fracture is healing and helps surgical planning when it is required.
MRI. MRI is generally not required for the diagnosis. Marrow signal may be abnormal, and it is used to look for cord compression where there are spinal abnormalities and to evaluate fracture complications.
Confirming the diagnosis. When diffuse osteosclerosis and short stature turn up incidentally, check the hands for acroosteolysis to separate the condition from osteopetrosis, then arrange genetic testing, family counselling and surveillance.
Differential Diagnosis
Osteopetrosis. The key differential, because it also produces diffuse osteosclerosis. Pyknodysostosis is distinguished by:
- Acroosteolysis (absent in osteopetrosis)
- Open fontanelles (absent in osteopetrosis)
- Absent paranasal sinuses (may be present in osteopetrosis)
- No bone marrow failure (occurs in severe osteopetrosis)
- Gene/Mechanism
- CTSK (cathepsin K)
- Key Features
- Short stature, open fontanelles, fractures
- Distinguishing Point
- Acroosteolysis present
- Gene/Mechanism
- TCIRG1, CLCN7, others
- Key Features
- Dense bones, Erlenmeyer flask, bone marrow failure (severe)
- Distinguishing Point
- NO acroosteolysis, may have anaemia
- Gene/Mechanism
- MAP2K1 somatic
- Key Features
- Dripping candle wax appearance
- Distinguishing Point
- Unilateral, sclerotomal distribution
- Gene/Mechanism
- LEMD3
- Key Features
- Multiple round sclerotic foci
- Distinguishing Point
- Spotted bones, asymptomatic
Management
The principles. There is no disease-modifying treatment, so management is supportive: fracture prevention, fracture treatment, dental care to prevent mandibular osteomyelitis, and genetic counselling for affected families.
Bone resorption is already impaired, and further inhibition of osteoclast function would worsen the underlying pathology. The contraindication, which extends to denosumab, is mechanistic rather than trial-proven: no study shows harm, only the strong rationale that suppressing resorption is illogical when resorption is already deficient. Examiners expect you to argue from mechanism.
Preventing fractures. Avoid high-impact activities, put fall-prevention strategies in place, and consider assistive devices as needed. Physical therapy maintains strength and balance, and the patient and family should understand the risk. General bone health still matters:
- Adequate calcium and vitamin D
- Weight management to avoid obesity
- No smoking
- Regular monitoring of growth and development
Treating the acute fracture. Standard reduction and immobilisation apply, adapted to the bone. Expect delayed healing and immobilise for longer than usual. Fixation may be used, but the bone is brittle; avoid multiple drill holes, which act as stress risers in sclerotic bone.
Expected healing. Delayed union is the rule rather than the exception, and union may take 2-3 times longer than normal. Follow healing with serial radiographs, be patient, and avoid early hardware removal.
Choosing the fixation. Pooled data suggest that intramedullary fixation has the lowest refracture rate and external fixation the highest, but the numbers are tiny and selection-biased. Sclerotic bone makes nail insertion technically hard, so plates remain widely used despite their higher refracture signal. Plates and screws may be challenging too, and locking constructs may give better purchase. External fixation is an option for complex fractures, and bone-cement augmentation may be considered in selected cases. No construct is proven superior.
Drilling sclerotic bone. The bone is difficult to drill and tap, and dull bits generate heat. Expect slow progress through dense bone; pre-drilling may help. The technique:
- Use sharp, new drill bits
- Use low-speed, high-torque settings
- Irrigate to prevent thermal necrosis
- Drill pilot holes before larger instruments
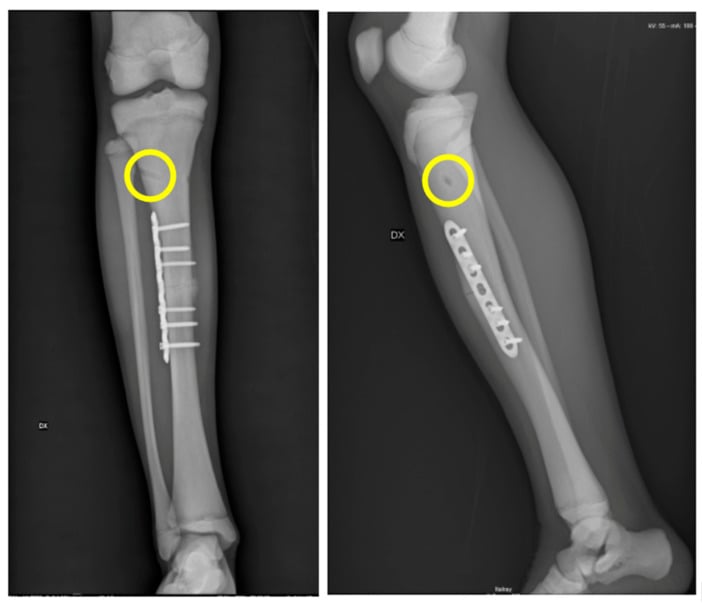
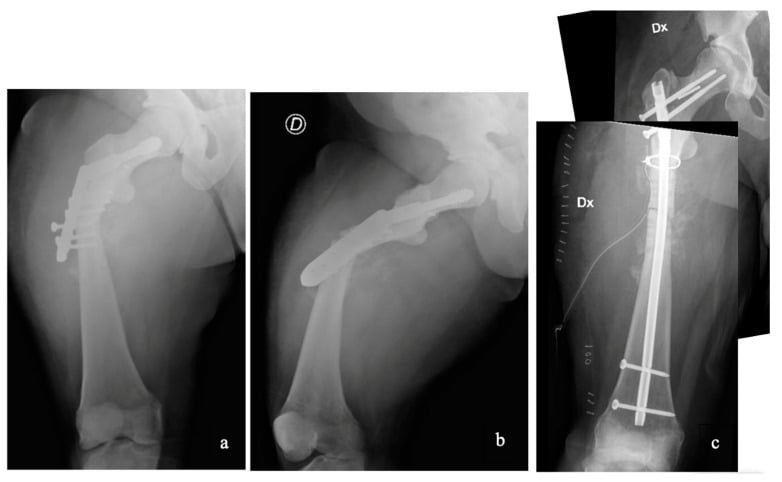
What the canal does to the plan. In the tibial case shown, a displaced shaft fracture could not accept elastic nails through the dense, narrow canal, so treatment was converted to open reduction and plate fixation; backup implants are mandatory. In the femoral case, a subtrochanteric refracture was complicated by a second fracture during canal preparation, and cerclage stabilisation allowed long-nail fixation. Dense, brittle bone carries a real risk of iatrogenic fracture.
Delayed union and nonunion. This is the most common complication, with nonunion in roughly a quarter to a third of operated cases. Continue immobilisation and consider bone grafting; bone stimulators may be considered, and hardware failure calls for revision fixation.
Malunion. Common, because of repeated fractures; genu and ankle valgus are reported. Mild deformity is accepted if the limb functions; major deformity may need correction, although corrective osteotomy is challenging in sclerotic bone.
Refracture. The same bone may fracture repeatedly, and pooled data put the overall refracture rate at about 25%. Consider prophylactic fixation in selected cases, and long-term protection may be needed.
Hardware. Insertion is difficult in sclerotic bone, drill holes become stress risers, and implants may need prolonged retention.
A nonunion that kept failing. In the case below, a femoral shaft nonunion refractured through the pseudoarthrosis with nail breakage, and revision elastic nailing still produced a hypertrophic nonunion at one year. The sequence supports prolonged surveillance and early revision planning.
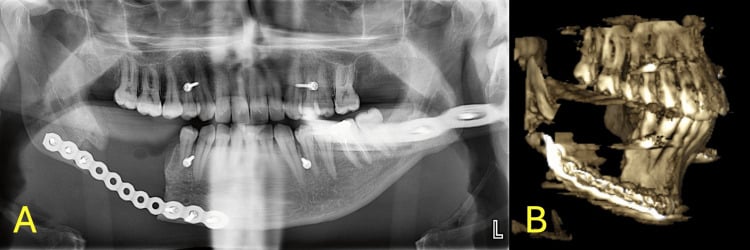
Mandibular osteomyelitis. Osteomyelitis or osteonecrosis of the mandible is a characteristic and serious complication, often after a dental extraction or a mandibular fracture. The sclerotic, poorly vascularised mandible is susceptible to infection, which shows itself with pain and chronic drainage. The risk factors are:
- Dental extraction (highest risk)
- Dental caries and periodontal disease
- Poor oral hygiene
- Local trauma
Prevention. Prevention through careful dental care is paramount. Keep the patient under regular dental surveillance and treat caries aggressively. Avoid extraction if possible, preferring root canal treatment; if a tooth must come out, give prophylactic antibiotics and keep trauma to a minimum.
Treatment. Early involvement of oral and maxillofacial surgery is essential when the infection is suspected, as part of a multidisciplinary approach. Antibiotic therapy is prolonged, weeks to months, and surgical debridement is often required. Hyperbaric oxygen may be beneficial, and reconstruction may be needed for extensive disease. In the case shown, destructive mandibular osteomyelitis with a pathological fracture was treated by excision of the infected sclerotic bone and segmental stabilisation with a reconstruction plate.
Complications and Prognosis
The fracture complications and jaw infection are covered under management. The others are:
- Dental disease: caries and retained deciduous teeth, on top of the crowding and delayed eruption
- Obstructive sleep apnoea, from the craniofacial morphology and midface hypoplasia
- Serous otitis media, reported, which may need ventilation tubes
Prognosis. Life expectancy is normal and intelligence unaffected. Morbidity comes from the fracture burden, the slow healing and the jaw. With careful fracture management and preventive dental care most patients achieve good long-term function, though short stature persists and repeated orthopaedic intervention is common.
Guidelines, Registries & Global Practice
Global Epidemiology
Pyknodysostosis is an ultra-rare autosomal recessive sclerosing bone dysplasia with an estimated incidence of approximately 1 per 1.7 million live births and fewer than a few hundred reported cases worldwide. Prevalence is higher in populations and regions with frequent consanguineous union (parts of the Middle East, North Africa and South Asia), where homozygosity for pathogenic CTSK variants is more likely. There is no published disease-specific registry; evidence derives from case reports, small institutional series and the pooled systematic review by Taka et al. (2022). Because most surgeons will see at most one case in a career, recognition and referral to a skeletal-dysplasia centre matter more than any single-country pathway.
Why No Society "Guideline" Exists — and What Governs Practice
No orthopaedic society (AAOS, BOA, EFORT, SICOT) or genetics body publishes a condition-specific guideline for pyknodysostosis given its rarity. Practice is therefore extrapolated from generic principles applied to a uniquely sclerotic, brittle bone:
- Governing principle
- Load-sharing/intramedullary constructs preferred where feasible; expect technically hard drilling and delayed union
- Source of guidance
- AO Foundation fracture-management principles; pooled review (Taka 2022)
- Governing principle
- Bisphosphonates and denosumab NOT indicated — resorption is already deficient
- Source of guidance
- Pathophysiology; consensus across reviews
- Governing principle
- Caries prevention and avoidance of extraction to reduce jaw osteomyelitis/osteonecrosis
- Source of guidance
- Oral/maxillofacial literature (Moroni 2024)
- Governing principle
- CTSK molecular confirmation; multidisciplinary skeletal-dysplasia assessment
- Source of guidance
- Clinical genetics standards
- Governing principle
- Recombinant growth hormone has been used in selected children with variable response
- Source of guidance
- Case series (Rovira Martí 2016)
Registry and Evidence Notes
- Implant/arthroplasty registries (NJR, AJRR, AOANJRR, SHAR, Norwegian, NZJR) do not capture pyknodysostosis separately; there are no registry-level implant-survival data for this condition.
- Best available synthesis: the Cureus systematic review (40 patients) shows intramedullary fixation had the lowest refracture rate and external fixation the highest — the closest thing to evidence-based fixation guidance.
High- vs Limited-Resource Practice Variation
- Well-resourced settings: CTSK sequencing, multidisciplinary skeletal-dysplasia and OMFS clinics, growth-hormone access, and image-guided fixation with specialist instruments for sclerotic bone.
- Limited-resource settings: diagnosis is clinical/radiographic (osteosclerosis + acroosteolysis + open fontanelles); fixation relies on available implants, and consanguinity-related caseloads may be relatively higher. Prevention of jaw osteomyelitis through basic dental hygiene is high-value and low-cost everywhere.
Genetic Counselling (Universal)
- Autosomal recessive: unaffected carrier parents face a 25% recurrence risk per pregnancy.
- Offer carrier testing to relatives and discuss consanguinity where relevant.
- Prenatal or preimplantation genetic testing is feasible once the family's CTSK variant(s) are known.
Controversies and Areas of Uncertainty
With so few reported cases and no randomised data, almost all management is extrapolated. Examiners reward a candidate who states the principle, then frankly acknowledges the uncertainty.
Growth hormone. Recombinant growth hormone has been used for short stature with a variable, inconsistent response. Some children show GH/IGF-1 axis abnormalities, but a predictable height benefit is unproven and it is not standard of care.
Disease-modifying treatment. There is no disease-modifying drug for pyknodysostosis, and gene and enzyme-replacement approaches remain experimental.
The Difficult Airway and Anaesthetic Concerns
These patients need repeated general anaesthetics for their frequent fractures, so the airway matters to the orthopaedic surgeon.
A predictably difficult airway. Micrognathia or retrognathia, the obtuse mandibular angle, a high-arched or grooved palate, midface hypoplasia and a short, stiff neck combine to make laryngoscopy and intubation difficult. Plan for it with videolaryngoscopy or an awake or fibreoptic approach; the generic difficult-airway drill is in the general-anaesthesia topic.
Fragile bone during airway manipulation. The brittle, sclerotic mandible, and the cervical spine, can fracture during forceful laryngoscopy or positioning, and teeth are easily damaged. Handle gently.
Obstructive sleep apnoea. Their obstructive sleep apnoea makes these patients sensitive to sedatives and opioids, and they need careful postoperative respiratory monitoring.
Cathepsin K as a Drug Target: the Experiment of Nature
The experiment of nature. By showing that losing cathepsin K blocks bone resorption, pyknodysostosis and its knockout-mouse model validated cathepsin K as a drug target for diseases of excess resorption: osteoporosis, bone metastasis and myeloma.
A different kind of antiresorptive. A cathepsin K inhibitor blocks the osteoclast's collagenase without killing the cell, so it reduces resorption while relatively preserving bone formation, because the osteoclast still signals to osteoblasts. That uncoupling is its advantage over bisphosphonates and denosumab, which suppress both.
Why it did not reach the clinic. The lead inhibitor, odanacatib, was developed for osteoporosis and reduced fractures in trials, but it was withdrawn in 2016 over cardiovascular safety, after an increased stroke signal, with atypical femoral fractures and skin changes from off-target effects as well. For pyknodysostosis itself, the mirror image with too little cathepsin K, there is still no cure.
Viva Practice Scenarios
Practise clinical reasoning and management decisions out loud
“A 6-year-old boy presents with a femoral shaft fracture after a minor fall. Radiographs show diffusely sclerotic bones throughout. His parents mention he has a 'soft spot' on his head that never closed. What is your differential diagnosis and how would you investigate?”
“You are asked about the difference between pyknodysostosis and osteopetrosis. Both cause dense bones and fractures. How do you distinguish them clinically and radiographically?”
“A teenager with known pyknodysostosis develops pain and swelling of the jaw after a dental extraction. What complication do you suspect and how would you manage it?”
Definition and Key Facts
Molecular Pathogenesis
Clinical Features
Radiographic Features
Distinguishing from Osteopetrosis
Management
Complications
Exam Pearls
Evidence Base
Molecular Basis of Pyknodysostosis
- Identified CTSK (cathepsin K) gene mutations as cause of pyknodysostosis
- Cathepsin K is essential for osteoclast-mediated bone matrix degradation
- Loss-of-function mutations lead to impaired bone resorption
- Confirmed autosomal recessive inheritance pattern
- Established molecular basis for therapeutic targeting
Pycnodysostosis: Role and Regulation of Cathepsin K in Osteoclast Function
- Comprehensive review of cathepsin K biology and the pycnodysostosis phenotype
- Cathepsin K-deficient osteoclasts demineralise bone but cannot degrade the type I collagen matrix
- Acroosteolysis of distal phalanges, short stature and skull deformities are core features
- Cathepsin K inhibitors proposed for diseases of excess resorption (osteoporosis, bone metastasis, myeloma)
- Understanding cathepsin K regulation is the basis for future targeted therapy
Cathepsin K and Bone Remodeling
- Cathepsin K knockout mice recapitulate human pyknodysostosis
- Osteoclasts present but unable to degrade collagen matrix
- Undigested collagen accumulates in resorption lacunae
- Model useful for therapeutic development
- Confirms essential role in bone resorption
Orthopaedic Treatment of Pycnodysostosis: A Systematic Review
- 29 case reports/series pooled (40 patients); 86% had prior fractures and 48% sustained low-energy or spontaneous fractures
- Femur (60%) and tibia (40%) were the commonest fracture sites; 63% of patients had consanguineous parents
- 84% were managed surgically: plate fixation 48%, intramedullary fixation 21%, Ilizarov external fixation 14%
- Overall refracture rate 25%, lowest with intramedullary fixation (0/6) and highest with external fixation (3/4)
- Sclerotic, brittle bone makes any fixation technically demanding; long-term follow-up is essential
Orthopaedic Disorders of Pycnodysostosis: A Report of Five Clinical Cases
- Five patients; all had typical craniofacial features, terminal phalangeal dysplasia and increased bone density
- Four with short stature were treated with growth hormone; most sustained fractures
- Intramedullary nailing is difficult because of skeletal sclerosis; alternative fixation should be considered
- Nonunion occurred in two of five patients and is common in this population
- Newly described associations included serous otitis media and nonunion in pycnodysostosis
Pathological Mandibular Fracture Complicated by Osteonecrosis in Pycnodysostosis
- Confirmed homozygous CTSK pathogenic variant c.746T-to-A (p.Ile249Asn) on direct sequencing
- Spontaneous pathological mandibular fracture with osteonecrosis at age 52, treated with load-bearing osteosynthesis
- Jaw osteomyelitis/osteonecrosis risk is increased, especially after tooth extraction or mandibular fracture
- Dental abnormalities (delayed eruption, hypodontia, malocclusion, increased caries) are frequent and warrant surveillance
- Recommends considering pycnodysostosis in osteosclerosis even without brachydactyly or short stature