Robotic-Assisted & Computer-Navigated Arthroplasty
Overview
What it is. Technology-assisted arthroplasty uses computer navigation or a surgical robot to plan and execute bone preparation and component positioning more precisely than manual jigs allow. The shared premise is that tighter control of alignment, component position and soft-tissue balance should improve durability and function, a premise only partly borne out by the clinical evidence.
Navigation and robotics. The two technologies sit on a spectrum of surgeon control. Computer navigation is a measuring and feedback tool: optical or electromagnetic trackers report limb and instrument position in real time, but the surgeon still makes every cut by hand. Robotics adds a physical execution element, from a fully autonomous milling arm (active systems) to a haptically constrained, surgeon-guided tool (semi-active systems) that simply stops the surgeon cutting outside the plan.
Enabling tools. Robotic and navigated arthroplasty are best understood as enabling tools rather than treatments in their own right. Their value depends entirely on the target they are asked to hit, which is why they are inseparable from the modern debate over alignment philosophy. These are the targets the technology executes:
- Mechanical alignment (MA), the traditional gold standard, restores a neutral hip-knee-ankle (HKA) mechanical axis of 0° (within ±3°), with the femoral and tibial cuts perpendicular to their mechanical axes. It is durable and reproducible, but it ignores the patient's native joint-line obliquity and often needs soft-tissue releases to balance.
- Kinematic alignment (KA) restores the patient's pre-arthritic native alignment and joint-line obliquity by resurfacing the worn condyles, matching resection to cartilage and bone loss. It aims to recreate native kinematics with fewer releases, but can place components in outlier positions in some knees.
- Restricted kinematic alignment (rKA) keeps KA within safe boundaries, for example each component and the overall HKA within about ±5° of neutral, to avoid extremes.
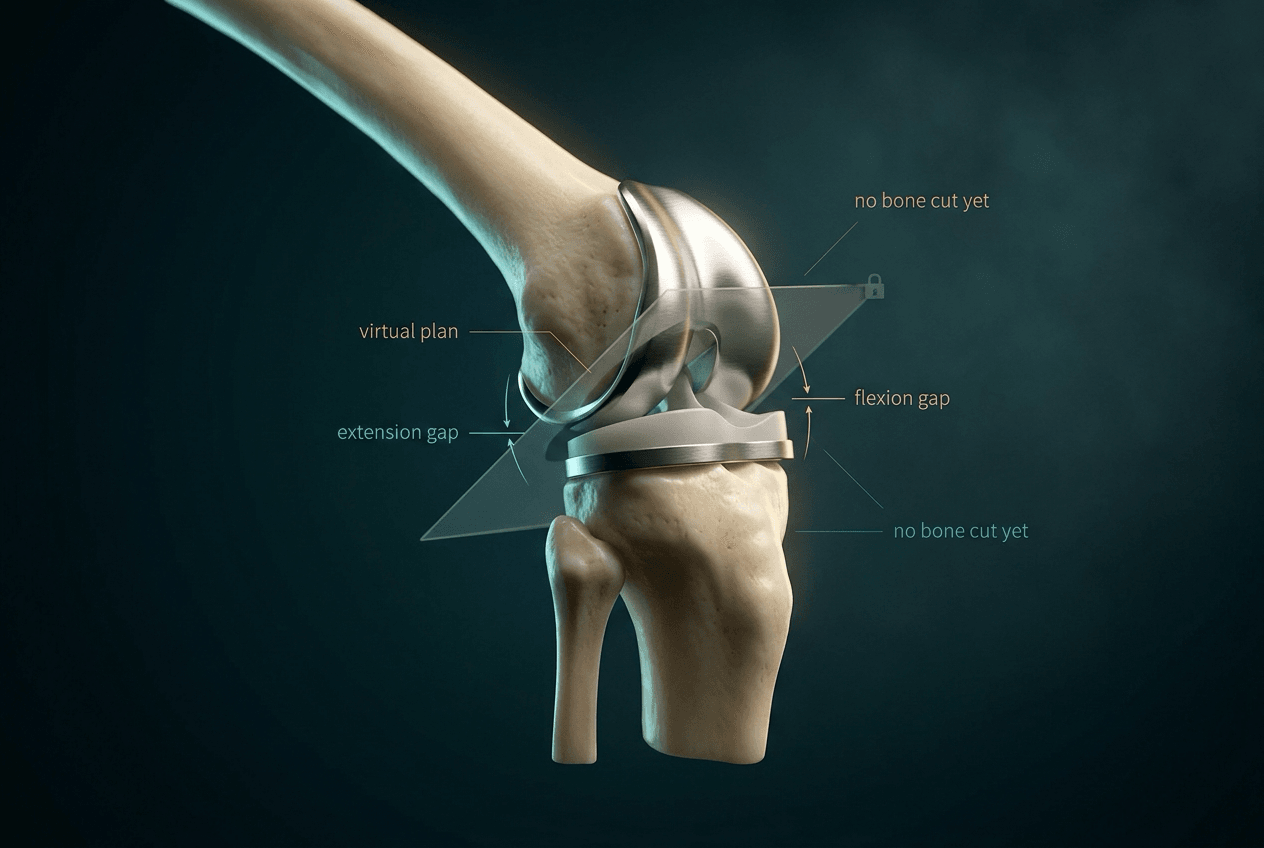
- Functional alignment (FA) is the robotics-era hybrid: plan component position virtually, then adjust it within defined limits to balance the soft-tissue gaps through range before any bone is cut. In the Young Insall Award RCT it needed far fewer releases (16% vs 65%) with a comparable 2-year Forgotten Joint Score.
- CPAK (Coronal Plane Alignment of the Knee) classifies knees by arithmetic HKA (limb alignment) and joint-line obliquity into phenotypes, Types I–IX, to individualise the target. The Young RCT found the FA benefit concentrated in CPAK Type I knees, which are constitutional varus rather than neutral.
Principles: system taxonomy
Classify any system twice: by how much the robot does (active, semi-active or passive), and by whether it needs a pre-operative image.
Active systems. The robot performs the bone resection itself while the surgeon supervises. The prototype was ROBODOC, for femoral canal preparation in THA. Concerns over soft-tissue injury, cost and inflexibility have made active systems largely historical.
Semi-active systems. The surgeon holds and moves the cutting tool, but the robot constrains it to a pre-defined three-dimensional boundary, the haptic envelope, preventing cuts outside the plan. This is the dominant contemporary architecture, for example Mako.
Passive navigation. The computer plans and continuously displays alignment and resection data but imposes no physical constraint. The surgeon executes all cuts conventionally.
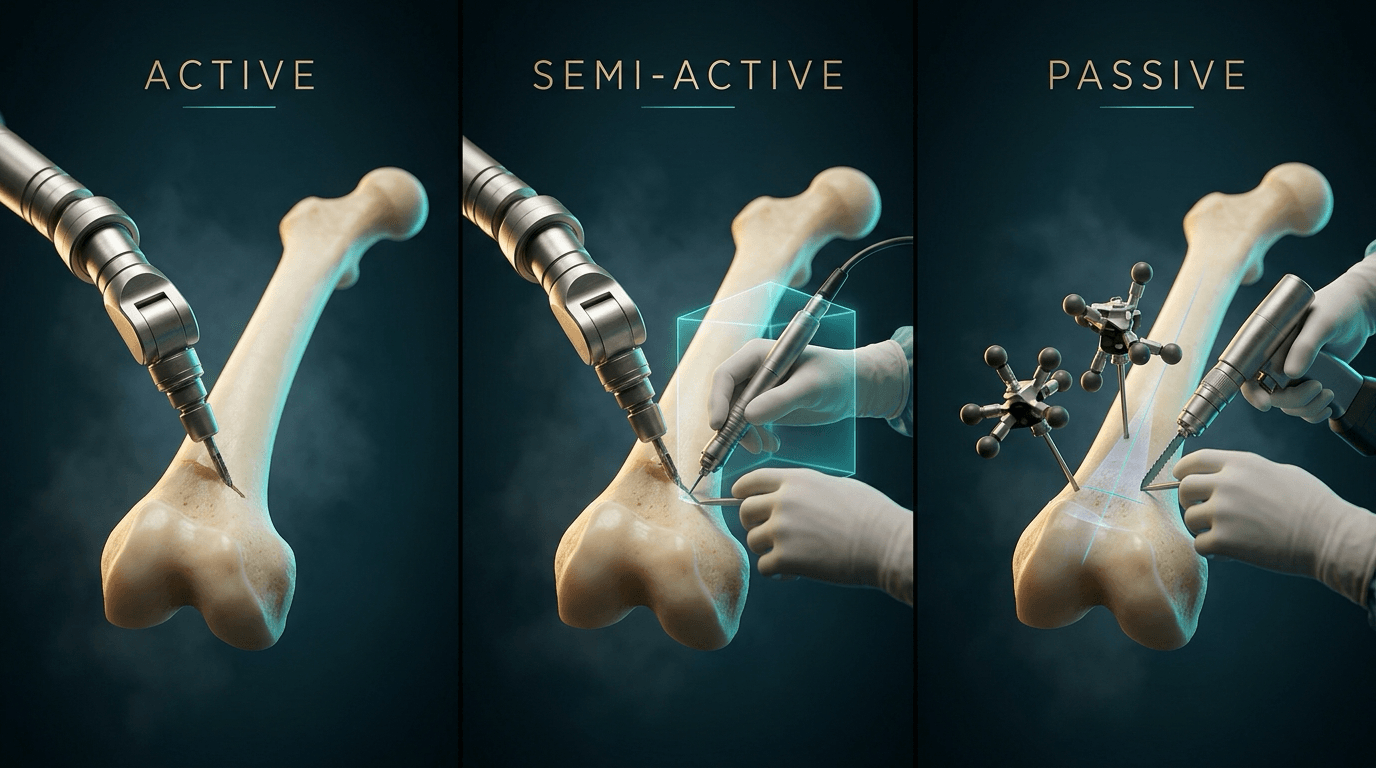
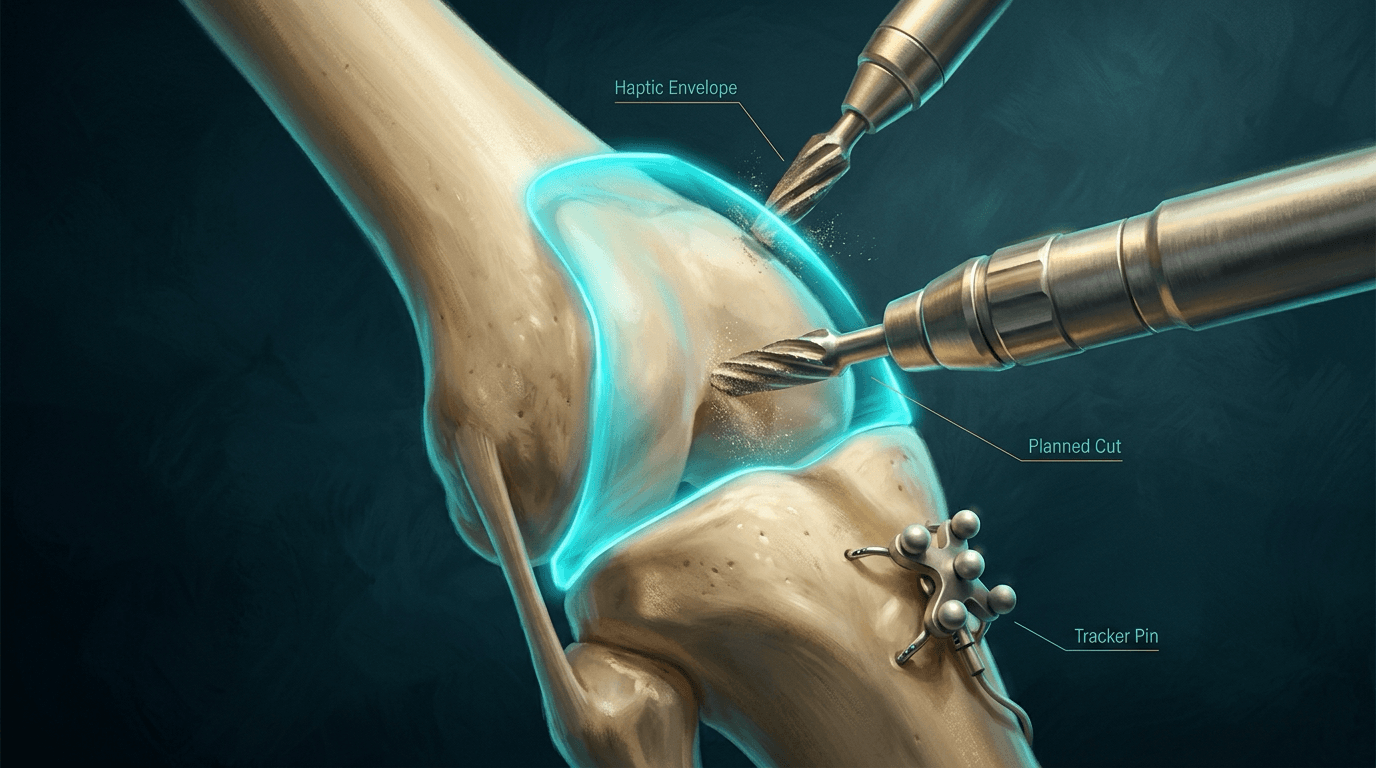
Image-based systems. A pre-operative CT (occasionally MRI) builds a patient-specific 3D model on which the procedure is planned, and to which the patient is registered intra-operatively. The gain is detailed pre-planning; the price is extra cost, logistics and a radiation dose from the planning CT.
Imageless systems. The anatomical model is generated intra-operatively by registering bony landmarks and kinematic axes, such as the hip centre found by circumducting the limb. There is no pre-operative scan and no radiation, but accuracy depends on the quality of intra-operative registration.
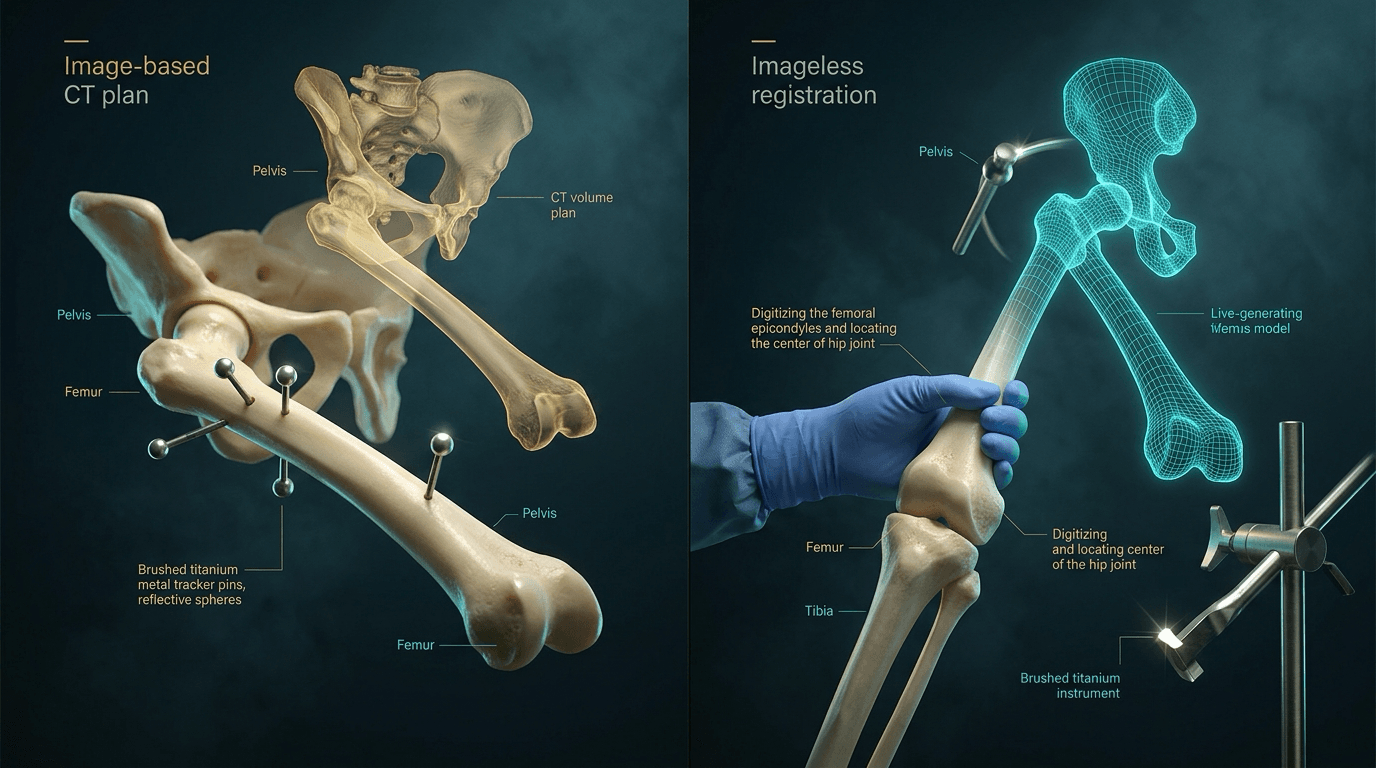
Tracking and registration. Optical tracking is the most common method: infrared cameras follow reflective marker arrays mounted on bone-anchored pins, and it requires line of sight. Electromagnetic tracking avoids the line-of-sight problem but is susceptible to metallic interference. Registration maps the patient's real anatomy onto the planning model, and registration error is a key source of system inaccuracy that is operator-dependent.
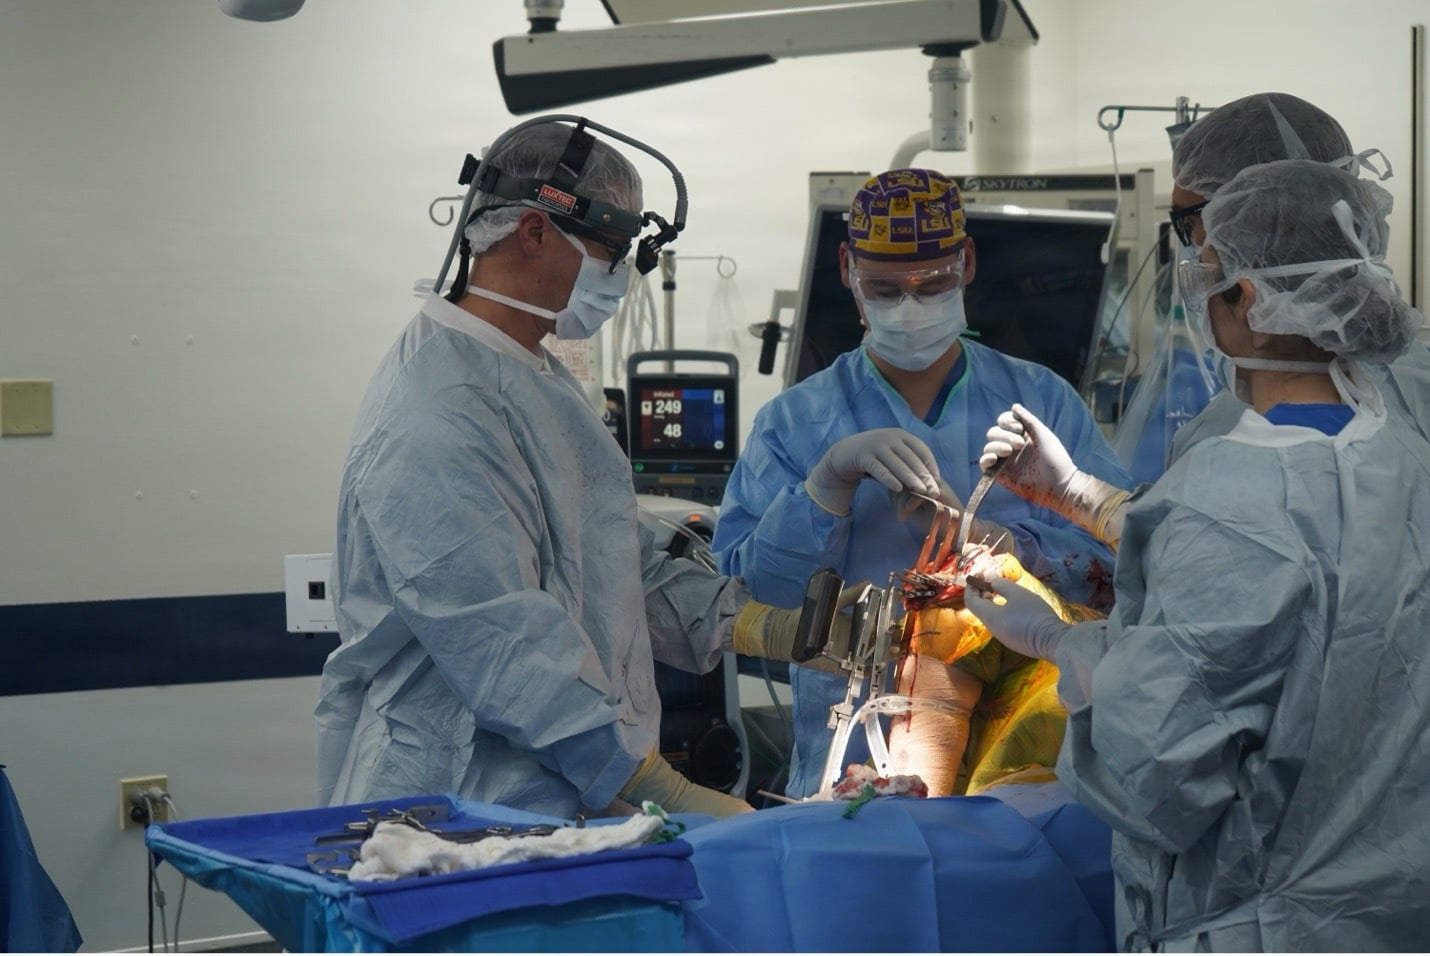
A robotic TKA, step by step. "Walk me through a robotic knee" is a common viva, and the answer is the sequence that distinguishes it from a manual case.
- Plan. An image-based system builds a patient-specific 3D model with implant size and position from the pre-operative CT; an imageless system plans intra-operatively.
- Pin and register. Insert bone-anchored tracker arrays in the femur and tibia, and register the anatomy to the model by capturing bony landmarks and surface points.
- Capture alignment and gaps. Record the limb (HKA) alignment and assess the flexion and extension gaps and laxity through range under varus and valgus stress.
- Balance the plan before cutting. Adjust component position, size and rotation on screen to optimise alignment and balance the gaps. This step is unique to robotics: the plan is balanced to the soft tissues before any bone is cut, which is how functional alignment is delivered and releases are minimised.
- Execute within the boundary. Make the resections with the tool constrained to the haptic boundary; the semi-active arm stops cutting outside the plan.
- Trial and refine. Reassess the gaps with trial components, fine-tune the plan if needed, then implant.
What separates this from manual instrumentation or plain navigation is quantified, dynamic gap-balancing, with the ability to adjust the plan before resecting bone.
Clinical relevance: accuracy versus outcome
The literature answers two separate questions. Does the technology hit the target more precisely? Consistently, yes. Does hitting it more precisely make the patient better? At high levels of evidence, so far, no.
The accuracy question. Meta-analysis of randomised trials shows robotic TKA achieves significantly better post-operative anatomical and mechanical alignment than conventional jig-based TKA, with fewer radiographic outliers. The benefit is most pronounced in knees with severe pre-operative deformity. In robotic THA the great majority of acetabular cups are placed within the intended safe zone for inclination and anteversion: 99% in a large prospective series.
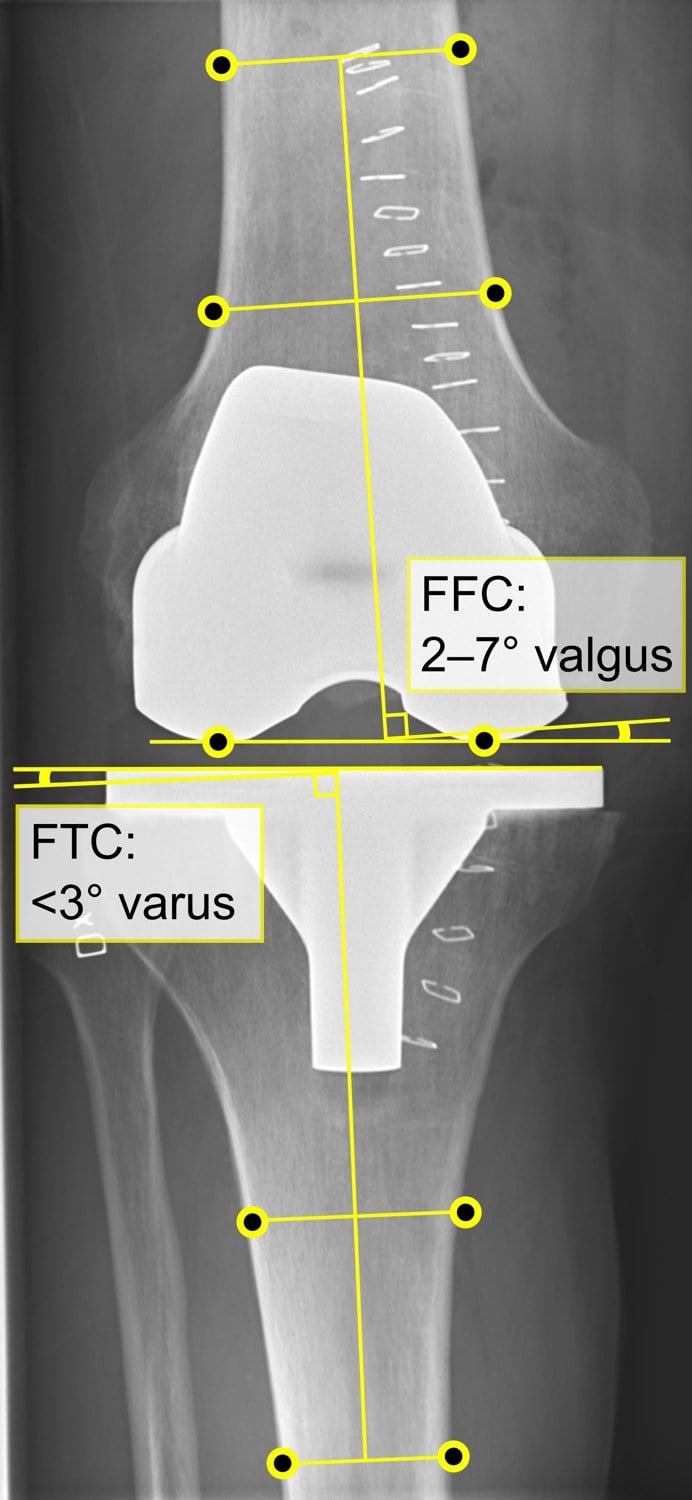
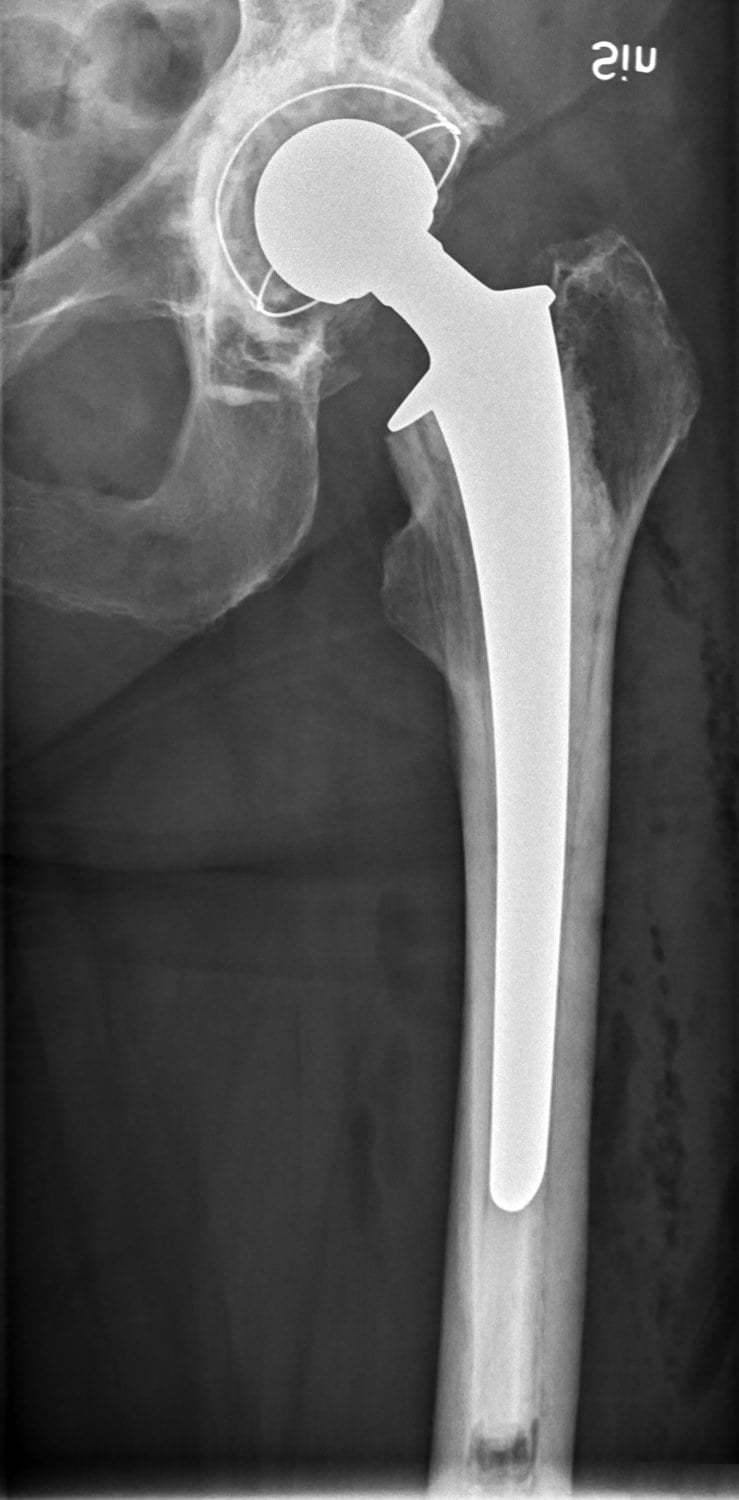
The outcome question. The strongest evidence, a long-term randomised controlled trial with over a decade of follow-up, found no difference between robotic-assisted and conventional TKA in Knee Society scores, WOMAC, range of motion, aseptic loosening, overall survivorship or complications. Better radiographs have not translated into better-feeling knees or longer-lasting implants in high-level trials.
Where a benefit might come from. Functional benefit from navigation appears only in studies where the system also controlled soft-tissue balancing, not alignment alone. Quantified soft-tissue balancing is therefore the likely mechanism behind any functional benefit.
Advantages and Limitations
Advantages. Beyond alignment precision, the potential advantages are these:
- Real-time gap and laxity data allow component position to be fine-tuned to the soft-tissue envelope
- Planning component position to the native envelope can reduce the need for ligament releases
- Functional and kinematic alignment depend on the precise, reproducible bone cuts that robotics provides
- Intra-operative data may flatten the variability between surgeons
Limitations. The decisive limitation is that precision has not translated into better function or survivorship at high levels of evidence. The practical costs follow, alongside the planning-CT radiation and registration error already described:
- Cost: substantial capital outlay, disposables and maintenance
- Operative time: randomised data consistently show longer operative duration, particularly during the learning curve
- Learning curve: registration, planning and workflow require dedicated training
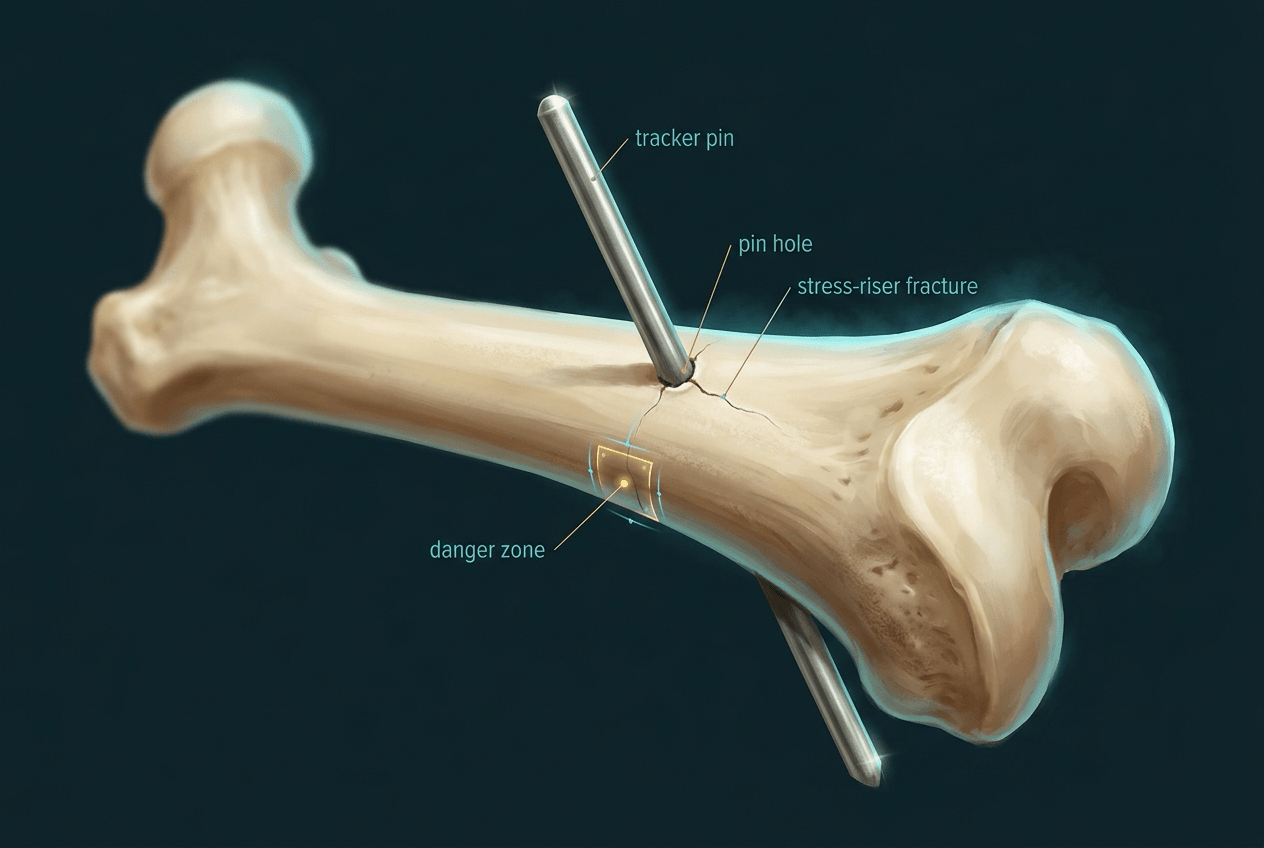
Technology-specific complications. Beyond the usual risks of arthroplasty, tracker-pin fixation introduces distinct hazards that randomised trials have specifically monitored. They are uncommon, but they are the complications an examiner expects you to name as "specific to the technology":
- Pin-tract infection
- Pin-site (stress-riser) fracture through a tracker-pin hole
- Peroneal nerve palsy from a badly placed tibial pin, and other neurovascular injury related to pin placement
- Patellar and extensor complications, historically reported with some systems
Cost, Adoption and the Value Question
Value. Adoption has been rapid and commercially driven, but the value proposition remains contested. The capital cost of a robotic platform, per-case disposables and added theatre time must be justified against outcomes that, at present, are equivalent to conventional surgery in the highest-quality trials.
The argument. Proponents argue the benefit will emerge with longer follow-up, newer systems, and the pairing of robotics with alignment philosophies that robotics uniquely enables. Sceptics note that decades of navigation data improved radiographs without improving patient-perceived outcomes, and caution against assuming robotics will be different.
A defensible exam stance: robotic and navigated arthroplasty are accurate, safe, and enabling technologies whose precision is established but whose clinical superiority is not yet proven. They are reasonable for surgeons who value reproducibility and wish to execute individualised alignment, but they are not a prerequisite for an excellent arthroplasty, and current evidence does not mandate their use.
Guidelines, Registries & Global Practice
Global Adoption and Evidence Picture
Technology-assisted arthroplasty has been adopted rapidly and worldwide, led commercially by semi-active haptic robotic platforms for knee and hip replacement. The consistent message across international randomised trials and meta-analyses is the same regardless of healthcare system: alignment accuracy improves; patient-perceived outcomes and survivorship, at current follow-up, do not differ from conventional surgery.
Side-by-Side Evidence Synthesis
- What the evidence shows
- Improved; fewer outliers, biggest effect in deformity
- Best supporting evidence
- RCT meta-analysis (Alrajeb 2024); RCT (Tian 2023)
- What the evidence shows
- Most cups within safe zone
- Best supporting evidence
- Prospective cohort (Elmallah 2015)
- What the evidence shows
- No difference vs manual
- Best supporting evidence
- Level I RCT, 13-year follow-up (Kim 2020)
- What the evidence shows
- Soft-tissue balancing, not alignment alone
- Best supporting evidence
- Meta-analysis (van der List 2016)
- What the evidence shows
- Robotics is the execution platform
- Best supporting evidence
- Insall Award RCT (Young 2025)
Registry and Practice Variation
National joint registries increasingly capture computer- and robot-assisted cases, and long-term registry survivorship data are maturing; at present they have not demonstrated a clear survivorship advantage that would compel adoption. Practice varies by resource setting: well-resourced centres may run image-based robotic programmes paired with individualised alignment, while many high-volume centres worldwide continue to achieve excellent results with manual instrumentation. The honest global summary is that robotics is an accurate and safe option, not an evidence-mandated standard of care.
Viva practice
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“Your hospital is considering purchasing a surgical robot for knee arthroplasty. As the arthroplasty lead, what is your evidence-based view?”
“A patient develops a distal femoral fracture two weeks after an uncomplicated robotic TKA. What is the likely mechanism and how could it have been avoided?”
Exam cheat sheet
Evidence
Landmark Level I RCT: No Long-Term Benefit
- Prospective randomised trial of 1406 patients (robotic-assisted vs conventional TKA) with a mean 13-year follow-up
- No difference in Knee Society scores, WOMAC, UCLA activity, or range of motion between groups
- Kaplan-Meier survivorship was 98% in both groups at 15 years (endpoint aseptic loosening or revision)
- No between-group difference in complications; authors could not recommend widespread use given added time and expense
Navigation/Robotics: Alignment vs Function
- Systematic review and meta-analysis of computer navigation and robotics in uni- and total knee arthroplasty
- Navigation reliably improves mechanical-axis accuracy and component positioning
- No functional benefit when navigation controlled alignment and component position alone (p = 0.63)
- A significant functional benefit emerged only when the system additionally controlled soft-tissue balancing (mean difference 4.84, p = 0.003)