Musculoskeletal Manifestations
- Sjogren syndrome is a chronic autoimmune exocrinopathy: lymphocytic infiltration of the lacrimal and salivary glands causes sicca (keratoconjunctivitis sicca and xerostomia). It is primary alone, and secondary with RA, SLE or systemic sclerosis.
- Arthralgia is very frequent, and the arthritis is usually non-erosive in an RA-like distribution - but the spectrum extends to erosive arthritis resembling RA.
- Articular involvement in 115 of 133 (86%) in one cohort, already present at diagnosis in 68%; hands and wrists commonest, then knees, shoulders and ankles.
- Serology: anti-Ro (SSA), anti-La (SSB), ANA, rheumatoid factor and a polyclonal raised IgG.
- Increased risk of B-cell (MALT) lymphoma, the most serious complication: persistent salivary-gland swelling, lymphadenopathy or new systemic features warrant investigation.
- Hydroxychloroquine failed its placebo-controlled trial (JOQUER: 17.9% versus 17.2%, P = 0.98); no drug has been shown to relieve the symptom burden of primary Sjogren syndrome.
- “Sjogren = autoimmune exocrinopathy (sicca: dry eyes + mouth) + anti-Ro (SSA)/anti-La (SSB). PRIMARY (alone) vs SECONDARY (with RA/SLE/other CTD).
- “MSK: arthralgia is VERY common; arthritis is usually NON-EROSIVE (RA-like distribution but not destructive). Myalgia/inflammatory myopathy can occur.
- “Key complication = increased B-cell (MALT) LYMPHOMA risk - be alert to persistent gland swelling/lymphadenopathy.
- “HYDROXYCHLOROQUINE FAILED ITS RCT (JOQUER, n = 120): 17.9% vs 17.2% responders, OR 1.01, P = 0.98, with no efficacy even in anti-SSA-positive, high-IgG or systemically involved patients. Adherence was verified by blood levels.
- “Articular involvement in 115 of 133 (86%), present at diagnosis in 68%; hands/wrists then knees, shoulders, ankles. Usually non-erosive - but the spectrum extends to EROSIVE arthritis resembling RA.
What It Is and Its Musculoskeletal Footprint
The disease. Sjogren syndrome is a chronic autoimmune exocrinopathy. Lymphocytic infiltration of the lacrimal and salivary glands produces sicca, keratoconjunctivitis sicca (dry, gritty eyes) and xerostomia (dry mouth), and there is systemic extraglandular involvement as well. It is primary when it occurs alone and secondary when it accompanies another connective-tissue disease such as rheumatoid arthritis, SLE or systemic sclerosis.
The joints. Musculoskeletal involvement is among the most common extraglandular features. Arthralgia is very frequent, and there is often an inflammatory arthritis in a symmetric small-joint, RA-like distribution that, unlike rheumatoid arthritis, usually does not erode the joints. Recognising this helps distinguish it from RA at presentation.
The muscles. Myalgia is common, and an inflammatory myopathy can occur, in overlap with the inflammatory myopathies. Fibromyalgia-type widespread pain and fatigue frequently coexist and add to the musculoskeletal symptom burden.
The serology. Anti-Ro (SSA) and anti-La (SSB) antibodies, a positive ANA and rheumatoid factor, and a polyclonal raised IgG are characteristic. The antibodies, especially anti-Ro, are important beyond diagnosis, for example in neonatal lupus and congenital heart block in pregnancy.
Why the surgeon needs to know. For the orthopaedic surgeon the disease is mostly a systemic context to recognise behind joint symptoms, managed with the rheumatology team. The table sets out how it differs from rheumatoid arthritis.
- Sjogren syndrome
- Usually NON-erosive
- Rheumatoid arthritis
- Erosive, destructive
- Sjogren syndrome
- Symmetric small-joint (RA-like)
- Rheumatoid arthritis
- Symmetric small-joint
- Sjogren syndrome
- Anti-Ro (SSA)/anti-La (SSB)
- Rheumatoid arthritis
- Anti-CCP / rheumatoid factor
- Sjogren syndrome
- Prominent (dry eyes/mouth)
- Rheumatoid arthritis
- Can be secondary Sjogren
- Sjogren syndrome
- B-cell (MALT) lymphoma
- Rheumatoid arthritis
- Erosive joint destruction
A seropositive, non-erosive symmetric arthritis with dry eyes and mouth should be recognised as Sjogren syndrome, primary or secondary, rather than simply managed as rheumatoid disease. The prominent sicca points to the diagnosis.
How Common Is the Joint Involvement, and Is It Really Never Erosive?
"Very common" and "usually non-erosive" are both defensible, but each needs qualifying.
The denominator. In a cohort of 133 patients with primary Sjogren syndrome, 115 (86%) had articular involvement, so joint disease is the rule. 91 patients (68% of the whole cohort) already had articular manifestations when Sjogren was diagnosed, and the remainder developed them during the disease course; those whose joints declared later had been diagnosed younger and reported more dryness. The cohort was assembled around articular manifestations, which will inflate the 86% relative to unselected Sjogren patients.
Which joints. Hands and wrists were most frequently involved, followed by knees, shoulders and ankles. The pattern is often described as symmetric small-joint and RA-like, but the distribution is not confined to the small joints.
The qualification to "non-erosive". Articular manifestations span a spectrum from arthralgia through to erosive arthritis resembling rheumatoid arthritis. Most cases are mild and self-limiting, but some patients develop a chronic polyarthritis requiring DMARDs. Sjogren arthritis is usually non-erosive, and taught as an absolute that will mislead: an erosive course does not exclude the diagnosis or automatically reclassify the patient as rheumatoid.
Imaging. In that cohort MRI detected more abnormalities than ultrasound, and both were used to quantify the extent of involvement and guide treatment. This was a retrospective descriptive study with no reference standard, so it reports relative detection, not diagnostic accuracy.
Diagnosis: Objective Tests and the 2016 Classification Criteria
Classification uses validated criteria that incorporate serology and gland involvement. The sicca is confirmed objectively, and the gland is examined histologically:
- Schirmer test - filter paper in the lower fornix; abnormal at 5 mm or less of wetting in 5 minutes
- Ocular staining score - lissamine green or fluorescein; abnormal at 5 or more
- Unstimulated whole salivary flow - abnormal at 0.1 mL/min or less
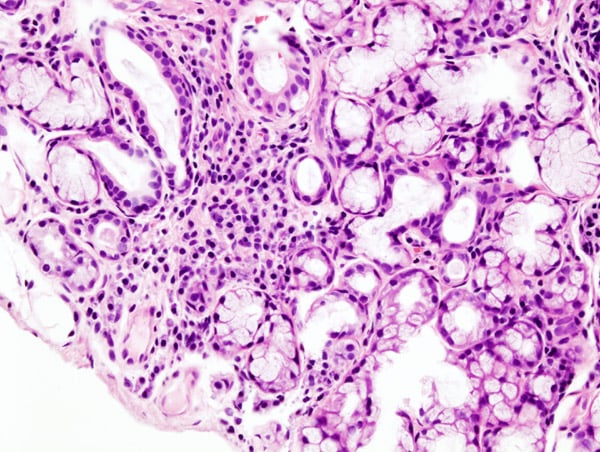
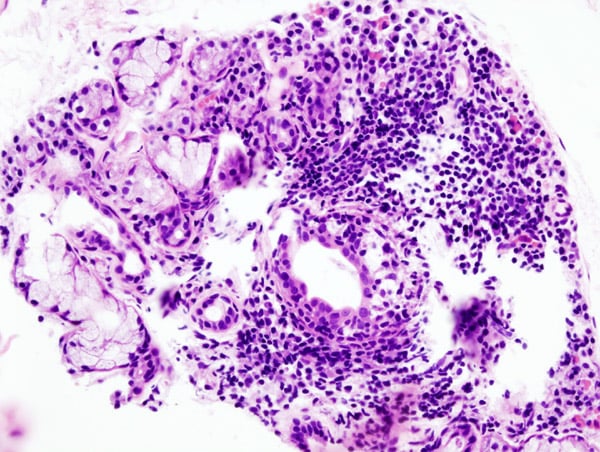
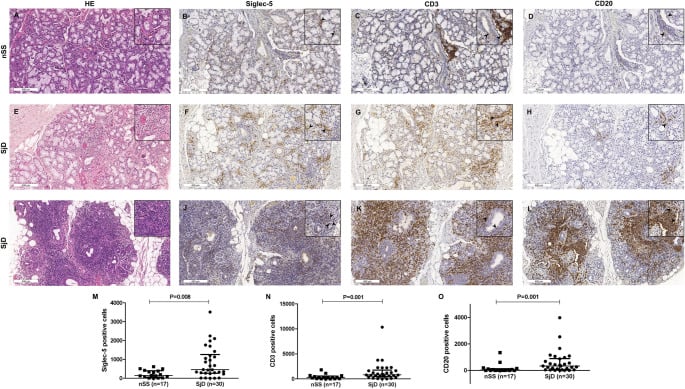
- Labial (minor) salivary-gland biopsy - the histological hallmark is focal lymphocytic sialadenitis with a focus score of at least 1 (one or more foci of 50 or more lymphocytes per 4 mm squared)
The 2016 ACR/EULAR classification criteria. In a patient with sicca symptoms and no exclusions, the items are weighted, and a total of at least 4 points classifies Sjogren syndrome:
- Focus score of at least 1 - 3 points
- Anti-Ro/SSA positive - 3 points
- Ocular staining score, Schirmer test and unstimulated salivary flow - 1 point each
Anti-La/SSB is not weighted in the 2016 criteria. Only anti-Ro/SSA counts.
The Lymphoma Risk: Why It Happens and Who Is at Risk
The size of the risk. Sjogren syndrome carries the highest lymphoma risk of the autoimmune connective-tissue diseases, roughly a 5% lifetime risk, about 15-20 times that of the general population. It is the most serious complication, and a recurring exam point.
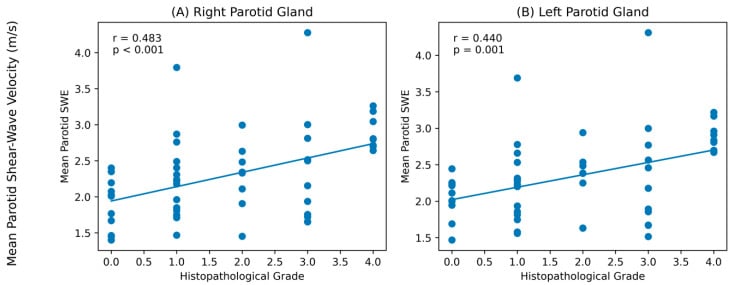
Why it happens. Chronic B-cell hyperactivation and antigen drive within the lymphocyte-infiltrated glands lead to clonal B-cell expansion. The result is most often an extranodal marginal-zone (MALT) B-cell lymphoma arising in the parotid or salivary gland itself.
Who is at risk. Persistent salivary-gland swelling, lymphadenopathy or new systemic features should be investigated, not dismissed. The high-risk patient is flagged by the following, which should prompt investigation (imaging, gland biopsy):
- Persistent parotid or salivary-gland enlargement
- Lymphadenopathy or splenomegaly
- Palpable purpura or cutaneous vasculitis
- Low C4 (hypocomplementaemia)
- Cryoglobulinaemia
- A serum monoclonal band
- Lymphopenia or low CD4
New or persistent gland swelling in Sjogren syndrome is lymphoma until proven otherwise.
Management
The sicca. Treatment is symptomatic: artificial tears and saliva, eye and mouth care, and secretagogues.
The inflammatory musculoskeletal disease. NSAIDs, with DMARDs or immunosuppression for significant systemic involvement. Prescribing decisions sit with rheumatology. Hydroxychloroquine is the most-prescribed drug, but it failed a placebo-controlled trial, including in anti-SSA-positive and systemically involved patients, and should be prescribed, if at all, knowing that.
The orthopaedic role. Recognise Sjogren syndrome as the systemic disease behind a seropositive, usually non-erosive arthritis. Coordinate joint care with rheumatology, with attention to the dry eyes and mouth and to perioperative immunosuppression.
Hydroxychloroquine: The Most-Prescribed Drug, and the Trial That Found It Did Not Work
Hydroxychloroquine is the most frequently prescribed immunosuppressant in primary Sjogren syndrome, and it is routinely offered for the arthralgia. The best evidence does not support that practice, and a candidate who quotes it as effective without the caveat is quoting habit rather than evidence.
The trial. JOQUER randomised 120 patients with primary Sjogren syndrome across 15 French university hospitals to hydroxychloroquine 400 mg daily or placebo, double-blind, for 24 weeks. The primary endpoint, a 30% or greater reduction in two of three analogue scales for dryness, pain and fatigue, was met by 17.9% (10 of 56) on hydroxychloroquine and 17.2% (11 of 64) on placebo (odds ratio 1.01, 95% CI 0.37-2.78, P = 0.98). The pain score moved from 5.09 to 4.59 on drug and from 4.92 to 5.08 on placebo: no meaningful separation.
Why it cannot be explained away. All but one patient in the treatment arm had detectable blood levels of the drug, so the null result is not a compliance failure. The subgroups you would most expect to respond did not: there was no efficacy with anti-SSA antibodies, high IgG or systemic involvement, precisely the seropositive, systemically active patients in whom it is usually justified.
What it does not show. The trial measured dryness, pain and fatigue over 24 weeks. It did not test hydroxychloroquine against articular inflammation as a specific endpoint, nor over a longer horizon, and the authors call for studies of longer-term outcomes. Serious adverse events were few and comparable between arms, so the drug is not dangerous, simply unproven for symptoms; the honest statement is that no drug has been shown to relieve the symptom burden of primary Sjogren syndrome.
Mnemonics & Memory Aids
DRYNESS
Hook:DRYNESS: Dry eyes/mouth, Ro/La antibodies, Yet usually non-erosive, Non-erosive arthritis (but erosive occurs), Either primary/secondary, Swelling → Suspect lymphoma, Symptomatic+Systemic Rx.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A patient with dry eyes and dry mouth has a symmetric small-joint arthralgia. How do you approach this, and how does it differ from rheumatoid arthritis?”
What it is
- Autoimmune exocrinopathy: sicca (dry eyes/mouth) from lymphocytic gland infiltration
- Primary (alone) or secondary (with RA/SLE/other CTD)
- Serology: anti-Ro (SSA)/anti-La (SSB), ANA, RF, raised IgG
Musculoskeletal
- Articular involvement in 115 of 133 (86%); present at Sjogren diagnosis in 68%
- Hands and wrists commonest, then knees, shoulders, ankles
- Usually NON-EROSIVE - but the spectrum runs to EROSIVE arthritis resembling RA
- Myalgia common; inflammatory myopathy (overlap) can occur
- Distinguish from RA: usually non-erosive, anti-Ro/La (not anti-CCP)
Key risk
- Increased B-cell (MALT) lymphoma risk
- Investigate persistent salivary-gland swelling/lymphadenopathy
- Most serious complication
Management
- Sicca: artificial tears/saliva, secretagogues (symptomatic)
- Inflammatory MSK: NSAIDs; DMARDs/immunosuppression for significant systemic disease
- Hydroxychloroquine failed JOQUER (n = 120): 17.9% vs 17.2% responders, OR 1.01, P = 0.98
- No efficacy even in anti-SSA-positive, high-IgG or systemically involved patients (adherence verified)
- No drug has been shown in an RCT to relieve the symptom burden of primary Sjogren
- Coordinate joint care + perioperative considerations with rheumatology
Evidence & Key Studies
Effects of hydroxychloroquine on symptomatic improvement in primary Sjogren syndrome: the JOQUER randomised clinical trial
- Double-blind, placebo-controlled, multicentre randomised trial: 120 patients with primary Sjogren syndrome from 15 French university hospitals, randomised 1:1 to hydroxychloroquine 400 mg daily or placebo to week 24, then all received hydroxychloroquine to week 48.
- NEGATIVE PRIMARY ENDPOINT: a 30% or greater reduction in 2 of 3 analogue scales (dryness, pain, fatigue) at 24 weeks was achieved by 17.9% (10/56) on hydroxychloroquine versus 17.2% (11/64) on placebo - odds ratio 1.01, 95% CI 0.37-2.78, P = 0.98.
- Individual scores confirm the null: pain moved 5.09 to 4.59 on drug versus 4.92 to 5.08 on placebo; dryness and fatigue likewise showed no separation.
- NOT A COMPLIANCE PROBLEM: all but one patient in the hydroxychloroquine arm had detectable blood levels of the drug.
- Hydroxychloroquine had NO efficacy in the subgroups where it is most often justified - patients with anti-SSA autoantibodies, high IgG, or systemic involvement.
- Limitations and scope: the endpoint was dryness, pain and fatigue over 24 weeks, not articular inflammation specifically, and the authors call for evaluation of longer-term outcomes. Serious adverse events were few and comparable between arms (2 vs 3 in the first 24 weeks), so this is evidence of inefficacy for symptoms, not of harm.
Characterisation of articular manifestations in primary Sjogren's syndrome: clinical and imaging features
- 133 patients with primary Sjogren syndrome, of whom 115 (86%) had articular involvement - giving a denominator to the claim that joint involvement is 'very common'.
- 91 patients (68% of the cohort) had articular manifestations already at the time of Sjogren diagnosis, the remainder developing them during the disease course. Those developing them later had been diagnosed at a younger age and reported higher dryness scores.
- Hands and wrists were the most frequently involved sites, followed by knees, shoulders and ankles - so involvement is not restricted to the small joints.
- IMPORTANT QUALIFICATION: articular manifestations span a spectrum from arthralgia to EROSIVE ARTHRITIS RESEMBLING RHEUMATOID ARTHRITIS. Most are mild and self-limiting, but some patients develop chronic polyarthritis requiring DMARDs - so 'non-erosive' is a generalisation, not an absolute rule.
- MRI detected more abnormalities than ultrasound, and imaging was used to quantify extent and guide treatment.
- Limitations: retrospective, single-country, and a referral cohort assembled around articular manifestations, which will inflate the 86% figure relative to unselected Sjogren patients. No reference standard was used, so the MRI-versus-ultrasound comparison describes relative detection, not diagnostic accuracy. Percentages in the source are internally inconsistent in places, so the counts are quoted here in preference to derived proportions.
Rheumatic-disease arthritis of the temporomandibular joint - rehabilitative pain relief
- SCOPE CAVEAT: this review concerns the TEMPOROMANDIBULAR JOINT in rheumatic disease generally, not the peripheral joint involvement of Sjogren syndrome. Sjogren appears only as one of the rheumatic diseases encompassed. It should not be read as evidence about Sjogren arthritis of the hands, wrists or knees.
- Conservative rehabilitative approaches (for example intra-articular corticosteroid injection and low-level laser therapy) may relieve pain in rheumatic-disease-related temporomandibular arthritis, though the authors note the evidence quality is limited.
- It offers general support for a symptomatic, conservative-first approach, but supplies no Sjogren-specific prevalence, outcome or treatment-effect figure.
The hydroxychloroquine trial figures - the 17.9% versus 17.2% response, the odds ratio of 1.01 (95% CI 0.37-2.78, P = 0.98), the verified blood levels and the absence of efficacy in anti-SSA-positive, high-IgG and systemically involved patients - come from the JOQUER randomised trial (DOI), 120 patients across 15 French hospitals. The articular prevalence (115 of 133, 86%), the 68% present at diagnosis, the joint distribution and the arthralgia-to-erosive spectrum come from Carubbi (PMID 33025895), a retrospective Italian cohort assembled around articular manifestations. The temporomandibular rehabilitation review (DOI) concerns rheumatic disease of the TMJ generally and supplies no Sjogren-specific figure. The exocrinopathy and sicca, the anti-Ro/anti-La serology, the 2016 ACR/EULAR criteria and their weightings, the focus-score histology, and the B-cell (MALT) lymphoma risk with its predictors are standard, well-established teaching.
What is not established: no drug has been shown in a randomised trial to relieve the symptom burden of primary Sjogren syndrome, and there is no trial evidence supporting any specific agent for its articular disease in particular. No validated prognostic score predicts which patients progress to erosive arthritis, and no agreed surveillance interval exists for the lymphoma risk - the predictors listed are recognised risk markers that should prompt investigation, not a validated scoring system.