ICM and EBJIS Definitions | DAIR vs Exchange | Organism-Specific Treatment
- Diagnosis uses a definition, not one test: major criteria or a weighted 2018 ICM score; EBJIS separates unlikely, likely and confirmed infection
- DAIR is a time-sensitive strategy, not a three-week law: symptom duration, implant stability, biofilm, organism, host and modular exchange matter
- One-stage and two-stage exchange are both established for chronic hip PJI in selected settings
- Spacer retention can be definitive in selected patients; cement toxicity and mechanical risk require monitoring rather than an absolute ban
- Obtain cultures before antibiotics when safe; never delay treatment of sepsis to create an antibiotic holiday
- “2018 ICM: one major criterion or preoperative score 6 or more indicates infection; scores 2-5 require intraoperative evidence
- “Alpha-defensin, leukocyte esterase and synovial counts add evidence but no test is universally best
- “DAIR outcome varies widely by timing, organism, host, components and surgical execution
- “Biofilm maturity is continuous and organism-dependent, not a binary three-week switch
- “S. aureus, resistant, polymicrobial and fungal infections require specialist antimicrobial and reconstructive planning
Overview and Epidemiology
Periprosthetic joint infection (PJI) is one of the most devastating complications of total hip arthroplasty. Despite advances in prevention it remains a leading cause of early revision, and its impact on patient outcomes is profound.
Incidence. Infection follows 1-2% of primary THAs and 3-5% of revisions. The incidence is increasing despite improved prevention, likely because the patients are higher-risk, and treating PJI costs 3-4 times as much as the primary arthroplasty.
Patient factors. These should trigger an optimisation protocol before surgery; the targets are set out under Prevention Strategies.
- Modifiable: obesity, diabetes, smoking, malnutrition, immunosuppression (steroids, biologics) and active infection elsewhere
- Non-modifiable: rheumatoid arthritis, prior surgery at the same site, male sex and advanced age
Surgical factors. The operating room environment and surgical technique have a major impact on infection risk. Risk rises with prolonged operative time (over 120 minutes), wound complications (haematoma, dehiscence), blood transfusion, revision surgery, bilateral simultaneous procedures and allogenic bone grafting. The protective measures are covered under Prevention Strategies.
Pathophysiology and Microbiology
Routes of infection. Direct inoculation, through intraoperative contamination or a postoperative wound complication, is the most common route for early PJI and accounts for the majority of early infections. Haematogenous spread is the route linked to late PJI, from dental procedures, urinary tract infections, skin and soft-tissue infections or gastrointestinal sources such as endoscopy and diverticulitis. Contiguous spread from adjacent osteomyelitis or a pre-existing septic hip is rare.
Biofilm. Biofilm formation is the key pathophysiology of PJI. Bacteria adhere to the implant surface and produce an extracellular matrix that protects them from the immune system and from antibiotics, raising the MIC 1000-fold. Antibiotics cannot penetrate established biofilm, which is why implant removal is usually necessary for chronic PJI.
The biofilm develops in stages:
- Adhesion (hours). Bacteria adhere to the implant, mediated by surface proteins and a conditioning layer; this is the critical window for prevention.
- Proliferation (days). Bacteria multiply, form microcolonies and begin producing extracellular matrix.
- Maturation (1-3 weeks). A mature biofilm with complex architecture and a protective matrix drastically reduces antibiotic penetration.
- Dispersion (ongoing). Bacteria shed from the biofilm can seed new locations, with chronic inflammation and bone resorption.
Biofilm develops progressively and differs by organism, surface and antimicrobial exposure. Shorter symptom duration favours DAIR, but no universal three- or four-week point converts retention from effective to impossible. Use the whole clinical and surgical context.
The organisms. Organism virulence affects both the presentation and the success of treatment.
- Staphylococcus aureus - 30% of PJI, the most virulent
- Coagulase-negative staphylococci - 30%, low virulence
- Streptococcus species - 10%
- Enterococcus - 5-10%
- Gram-negative rods - 10%
- Polymicrobial - 10-20%
- Culture-negative - 7-10%, with the worst prognosis
- Virulence
- High
- Biofilm
- Strong
- Treatment Challenge
- Aggressive, often needs implant removal
- Virulence
- High
- Biofilm
- Very strong
- Treatment Challenge
- Not a one-stage candidate, prolonged antibiotics
- Virulence
- Low
- Biofilm
- Very strong
- Treatment Challenge
- Indolent presentation, strong biofilm producer
- Virulence
- Moderate
- Biofilm
- Weak
- Treatment Challenge
- Better success with DAIR if caught early
- Virulence
- Low-Moderate
- Biofilm
- Moderate
- Treatment Challenge
- Often resistant, difficult to treat
- Virulence
- Variable
- Biofilm
- Variable
- Treatment Challenge
- Often resistant, polymicrobial common
- Virulence
- Low
- Biofilm
- Moderate
- Treatment Challenge
- Requires antifungals, often two-stage or resection
Classification Systems
Tsukayama's temporal classification divides infection by when it declares itself, and it directly guides the choice of treatment.
- Timing
- Under 3 months
- Presentation
- Acute wound inflammation
- Typical Organisms
- S. aureus, Gram-negatives
- Timing
- 3-24 months
- Presentation
- Indolent, pain, loosening
- Typical Organisms
- CoNS, P. acnes
- Timing
- Over 24 months
- Presentation
- Acute symptoms, well-fixed implant
- Typical Organisms
- S. aureus, Streptococcus
- Timing
- During revision
- Presentation
- Unexpected positive cultures
- Typical Organisms
- Variable
Early infections (Type I), and acute haematogenous infections (Type III) with under 3 weeks of symptoms, may be suitable for DAIR. Delayed or chronic infection (Type II) almost always requires exchange, one-stage or two-stage. The three-week and three-month boundaries are historical heuristics rather than biological laws (see Management Algorithm), and Type IV is discussed under Unexpected Positive Intraoperative Cultures.
McPherson staging grades the host and the limb. Host grade affects antibiotic duration and how aggressive treatment should be.
- Features
- Healthy, no comorbidities, good nutrition, no immunosuppression
- Prognosis
- Best
- Features
- Diabetes, obesity, smoking, local wound issues
- Prognosis
- Intermediate
- Features
- Significant immunosuppression, active malignancy, ESRD, multiple failed surgeries
- Prognosis
- Poor; consider salvage
Extremity grade affects the surgical approach and the need for plastic surgery involvement.
- Features
- Good soft-tissue coverage, no scarring or fibrosis, good vascularity
- Features
- Previous surgery and scarring, radiation history, venous stasis
- Features
- Major soft-tissue loss, vascular insufficiency, multiple prior surgeries; may need flap coverage
Clinical Presentation and Assessment
The presentation depends on when the infection declares itself.
Early, under 3 months. Fever, wound drainage and erythema: clear signs of infection, with systemic symptoms.
Subacute, 3-24 months. Pain, stiffness and mechanical symptoms. The presentation is subtle and may mimic aseptic loosening, so any painful THA, especially one that was never pain-free after surgery or became painful after a pain-free interval, should be worked up for infection.
Late haematogenous, over 24 months. Acute pain in a previously well-functioning THA, with an identifiable source of infection elsewhere.
History. Establish:
- The timing of symptoms relative to surgery
- Previous function of the THA: was it ever pain-free?
- Postoperative wound complications
- Recent infections or procedures (dental, UTI)
- Risk factors: diabetes, immunosuppression, prior surgery
- Prior antibiotic use, which affects culture yield
Examination. Look for wound erythema, warmth and swelling, a sinus tract or wound drainage, and previous surgical scars. Pain with movement, even passive, and a reduced range from contracture due to chronic inflammation are findings, and systemic signs (fever, and sepsis in severe cases) may be present.
A sinus tract communicating with the prosthesis is pathognomonic for infection (MSIS major criterion). Even without other signs, this mandates treatment for PJI.
- Key Features
- Rest pain, never pain-free, sinus/drainage, raised ESR/CRP
- Discriminating Test
- Aspiration (cell count, alpha-defensin, culture); MSIS score 6 or more
- Key Features
- Start-up/activity pain, progressive radiolucent lines, normal CRP
- Discriminating Test
- Normal aspiration cell count and markers; radiographic migration
- Key Features
- Groin pain, effusion, metal-on-metal or large-head MoP bearing
- Discriminating Test
- Serum cobalt/chromium, MARS-MRI showing pseudotumour; bland aspirate
- Key Features
- Mechanical giving-way, positional pain, dislocation history
- Discriminating Test
- Radiographs/dynamic exam; markers normal
- Key Features
- Acute pain after trauma, deformity, inability to weight-bear
- Discriminating Test
- Radiographs (Vancouver classification); markers normal
- Key Features
- Pain not reproduced by hip movement, neuro/vascular signs
- Discriminating Test
- Spinal/vascular workup; normal hip aspiration and markers
Before attributing a painful THA to a mechanical cause, exclude PJI with serum ESR/CRP and, if elevated or suspicion is high, off-antibiotic aspiration. Missing low-grade infection before a revision converts a one-stage mechanical revision into a failed, contaminated reconstruction.
Diagnostic Investigations
The 2018 MSIS/ICM definition. One major criterion is enough for definite PJI:
- Two positive cultures of the same organism from separate samples
- A sinus tract communicating with the prosthesis
Without a major criterion, the minor criteria are weighted and scored, not counted; do not revert to "four minor criteria". A preoperative score of 6 or more indicates infection, 2-5 is inconclusive and needs the intraoperative criteria added, and 0-1 means not infected.
- Threshold
- Points
- Threshold
- CRP over 10 mg/L (or D-dimer over 860 ng/mL)
- Points
- 2
- Threshold
- Over 30 mm/hr
- Points
- 1
- Threshold
- Over 3000 cells/µL
- Points
- 3
- Threshold
- Over 70%
- Points
- 2
- Threshold
- Qualitative positive
- Points
- 3
- Threshold
- ++ or +++
- Points
- 3
- Threshold
- Over 6.9 mg/L
- Points
- 1
- Threshold
- Points
- Threshold
- One organism
- Points
- 2
- Threshold
- Over 10 PMN/HPF (5 HPF)
- Points
- 3
- Threshold
- Present
- Points
- 3
Serum markers. ESR and CRP are the first-line blood tests. They are screening tests and not diagnostic alone: they can be raised by aseptic inflammation, with a sensitivity of 80-90% and specificity of 70-80%. Raised markers prompt further workup, but normal markers do not rule out PJI, especially with low-virulence organisms; their trend is more useful for monitoring the response to treatment. A full blood count with differential can be sent, though leukocytosis is less sensitive. D-dimer was newly incorporated into the 2018 definition, and its limitations are discussed with the evidence below.
Aspiration. Joint aspiration is critical for diagnosis. It is image-guided, by fluoroscopy or ultrasound, with a lateral approach preferred, and a minimum of 3 samples go for culture. The fluid is sent for:
- Cell count and differential
- Culture: aerobic, anaerobic, and fungal if indicated
- Alpha-defensin, with the highest accuracy (sensitivity 97%, specificity 97%), though no test is universally best
- Leukocyte esterase, a rapid point-of-care test
- Synovial CRP
Hold antibiotics for 2 weeks before aspiration if clinically safe. Starting antibiotics before cultures reduces diagnostic yield significantly and can lead to culture-negative PJI (worse outcomes).
Intraoperative sampling. This provides the definitive diagnosis and guides antibiotic selection. Take a minimum of 5 separate tissue samples, not swabs, from deep tissues in different locations, for aerobic, anaerobic and, if needed, fungal culture; extend incubation to 14 days if a slow-growing organism is suspected.
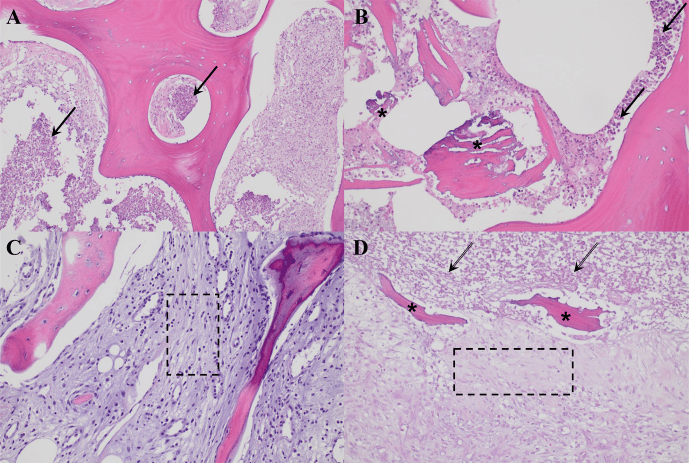
Frozen section. Over 10 PMN per HPF (5 fields at 400x) indicates infection, with a sensitivity of 80-85% and specificity of 95%. It is useful for intraoperative decisions and can guide conversion to two-stage when infection is unexpected.
Sonication. Culturing the sonicated removed components disrupts the biofilm and improves yield, particularly in culture-negative cases, but it is not universally available.
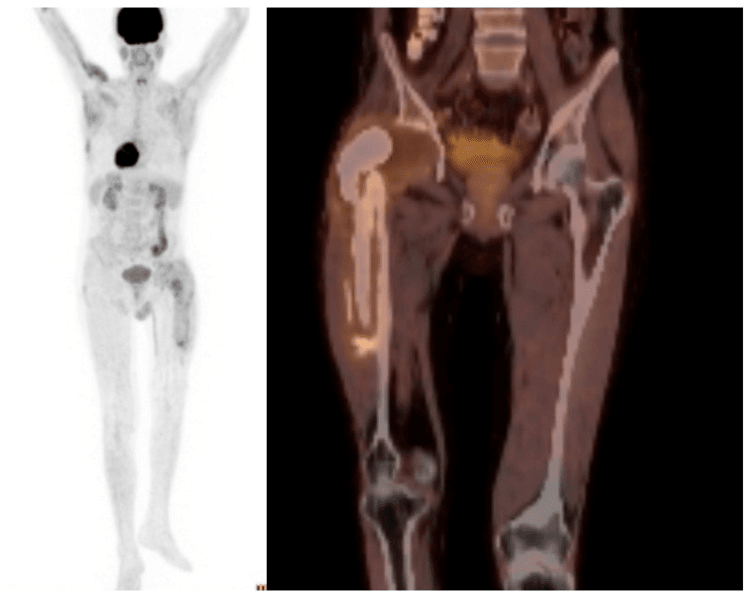
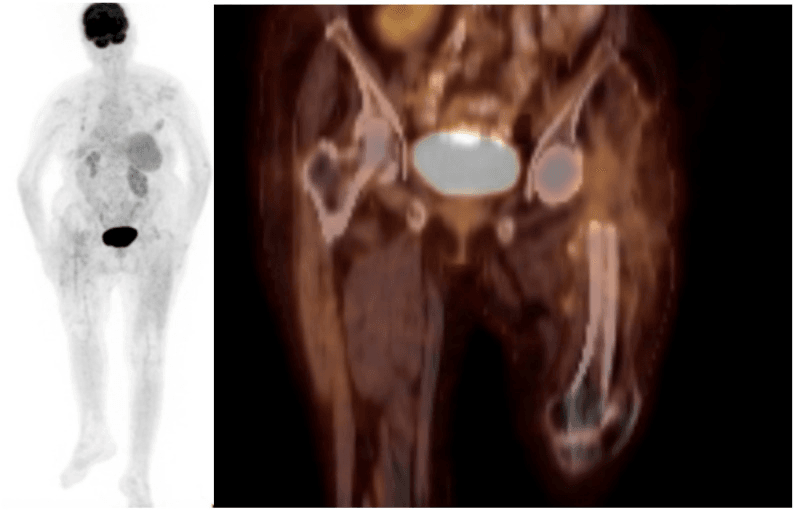
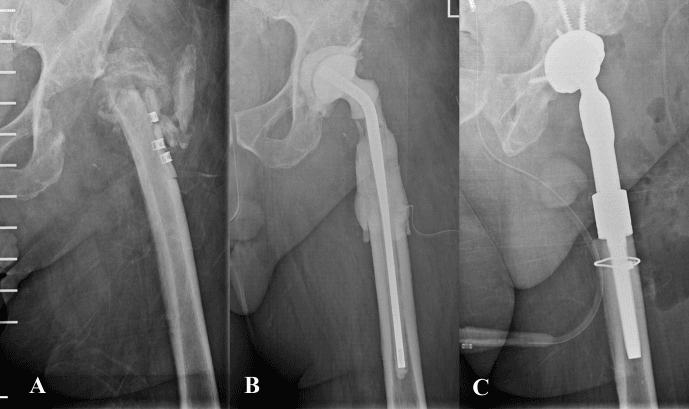
Imaging. Radiographs are the baseline for every painful THA, looking for loosening, osteolysis and cement fracture; PJI can cause rapid bone loss. Imaging cannot reliably distinguish PJI from aseptic loosening, since both cause bone resorption, implant loosening and radiolucency, so it guides surgical planning while laboratory diagnosis is essential.
- CT assesses bone loss and guides revision planning
- MRI is usually not helpful because of artefact, and rarely used
- Tc-99m bone scan is sensitive but not specific
- Labelled WBC scan is more specific for infection
- FDG-PET remains a research tool, with improving availability
The sequence.
- Clinical suspicion: serum ESR and CRP
- If raised, or suspicion is high: hip aspiration, off antibiotics if possible
- Aspirate for cell count, culture and alpha-defensin
- Apply the MSIS criteria
- If PJI is confirmed, plan treatment on timing and organism
- Intraoperative cultures confirm the diagnosis and guide antibiotic therapy
Management Algorithm
Stabilise first. Recognise sepsis, obtain blood and deep cultures promptly, and begin empiric therapy after sampling when clinically safe. In sepsis or rapidly progressive infection, collect cultures promptly and start treatment: diagnostic yield does not outrank resuscitation.
Phenotype the infection. Confirm it against the definition score, then define the organism and its susceptibility, the symptom duration, any sinus or abscess, component fixation, bone loss, the soft tissues and the host's reserve. These choose the strategy; the aim is the one that achieves source control at an acceptable burden to the patient.
- Favourable Features
- Short symptom duration, fixed components, exchangeable modular parts, achievable debridement
- Reasons to Choose Another Path
- Loose implant, chronic sinus/abscess, poor source control, difficult organism or repeated failure
- Favourable Features
- Organism and susceptibility defined, reconstructable bone/soft tissue, complete debridement feasible
- Reasons to Choose Another Path
- Uncertain microbiology, severe host/soft-tissue compromise or reconstruction needing interval management
- Favourable Features
- Need for interval local antibiotic delivery, uncertain control, complex organism or reconstruction
- Reasons to Choose Another Path
- Patient unlikely to tolerate two operations or prolonged spacer interval
- Favourable Features
- Reconstruction burden exceeds expected benefit or patient preference
- Reasons to Choose Another Path
- Progressive sepsis, mechanical spacer failure or unacceptable function
DAIR. Consider it when the components are well fixed, modular exchange and thorough debridement are feasible, and symptom duration, organism and host support retention. An unmanageable sinus or abscess weighs against it. Shorter symptoms favour success but there is no absolute cut-off, and patients should be counselled with centre- and organism-specific outcomes.
DAIRDAIR Decision Domains
Hook:DAIR is a multidomain decision, not simply under three weeks.
One-stage or two-stage exchange. Both can control chronic hip PJI. One-stage is a single definitive debridement and reimplantation, chosen when complete debridement and immediate reconstruction are feasible and the microbiological and local environment is acceptable. Two-stage separates them with an interval spacer, chosen when interval source control, local antibiotic delivery or staged reconstruction offers an advantage worth two operations. Choose between them on organism certainty, bone loss, soft tissue, host reserve, reconstructive complexity and local expertise.
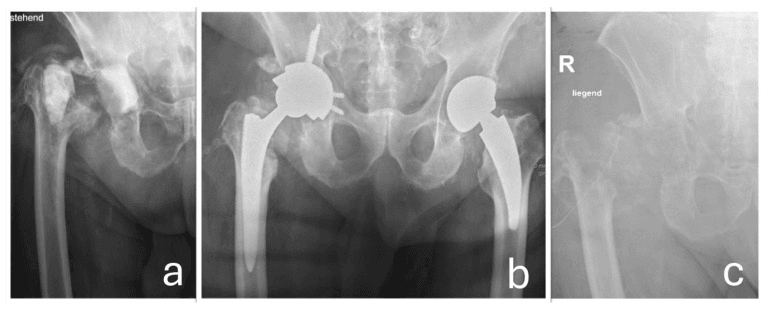
Salvage. A retained spacer, chronic suppression, resection arthroplasty or, rarely, amputation is selected when definitive reconstruction is unsafe, unwanted or unlikely to succeed.
Antimicrobials. The route, the biofilm-active combination and the duration follow the organism, the operation, any retained material, source control, renal and hepatic function and infectious-diseases input.
Reimplantation. No single ESR or CRP, aspiration, antibiotic holiday or elapsed week proves eradication. The decision rests on the clinical course, the wound, serial evidence, operative findings and shared judgement.
Do not prescribe DAIR, one-stage or two-stage exchange from “three weeks”, “three months” or “six-to-twelve weeks” alone. Those are historical heuristics, not biological laws.
Antibiotic Therapy
The choice of agent follows the organism and its sensitivities.
- First-Line IV
- Flucloxacillin or cefazolin
- Oral Suppression
- Cefalexin + rifampicin
- Duration
- IV 4-6 weeks, oral 3-6 months
- First-Line IV
- Vancomycin
- Oral Suppression
- Linezolid, cotrimoxazole, or doxycycline
- Duration
- IV 6 weeks minimum, oral 6-12 months
- First-Line IV
- Vancomycin (often resistant to beta-lactams)
- Oral Suppression
- Cefalexin (if sensitive) + rifampicin
- Duration
- IV 4-6 weeks, oral 3-6 months
- First-Line IV
- Penicillin or ceftriaxone
- Oral Suppression
- Amoxicillin
- Duration
- IV 2-4 weeks, oral 3 months
- First-Line IV
- Ampicillin + gentamicin (synergy)
- Oral Suppression
- Amoxicillin
- Duration
- IV 4-6 weeks, oral 3-6 months
- First-Line IV
- Fluoroquinolone (ciprofloxacin)
- Oral Suppression
- Ciprofloxacin + rifampicin
- Duration
- IV 4 weeks, oral 6 months minimum
- First-Line IV
- Broad-spectrum (vancomycin + pip-tazo)
- Oral Suppression
- Based on sensitivities
- Duration
- Extended duration, tailored to organisms
Rifampicin enhances biofilm penetration and should be used for Staph infections (MSSA, MRSA, CoNS) when implant is retained (DAIR) or after reimplantation. Never use rifampicin monotherapy - resistance develops rapidly. Always combine with another active agent.
Around a two-stage revision. After stage 1, give 4-6 weeks of IV antibiotics chosen on culture and sensitivities, then continue oral antibiotics until stage 2, or stop them 2-6 weeks beforehand for an antibiotic holiday. After reimplantation, give 2-4 weeks IV followed by oral suppression for 3-6 months at least; some advocate 12 months for S. aureus and MRSA. Infectious-diseases consultation is recommended.
Stewardship. This is a global principle:
- Reserve agents such as linezolid, daptomycin and newer cephalosporins for resistant Gram-positives (MRSA/VRE), according to local sensitivities
- Monitor drug levels for vancomycin and aminoglycosides
- Engage the antimicrobial stewardship and infectious-diseases teams in every case
Culture-negative PJI. It has worse outcomes. The causes are prior antibiotics, fastidious organisms and biofilm. Treat empirically with a broad-spectrum regimen (vancomycin plus pip-tazo or meropenem), and consider extended culture incubation, molecular diagnostics or fungal cultures.
Fungal (Candida) PJI
When to suspect it. Fungal PJI, usually Candida and occasionally Aspergillus, is uncommon, around 1% of PJI. Consider it in an immunocompromised or debilitated host, after prolonged broad-spectrum antibiotics, in culture-negative infection that fails to settle, or as part of a polymicrobial infection. It is typically indolent, and standard bacterial cultures may miss it, so request fungal cultures with extended incubation and consider sonication and molecular tests.
Why it is hard. Candida forms a biofilm on the implant just as bacteria do, so eradication almost always needs implant removal and DAIR rarely works. Antifungal penetration is limited and treatment is prolonged.
Treatment. Two-stage revision is the mainstay, with an antifungal-loaded spacer: amphotericin B is the agent usually added to cement, as azoles and echinocandins elute poorly. Systemic antifungal therapy starts with an echinocandin or a lipid amphotericin formulation and steps down to fluconazole for susceptible Candida, continued as a prolonged course guided by infectious diseases. Outcomes are worse than for bacterial PJI, and resection arthroplasty (Girdlestone) or long-term suppression is a realistic endpoint in the frail or multiply-failed patient.
Unexpected Positive Intraoperative Cultures
The single-culture problem. At a revision done for presumed aseptic failure, one unexpected positive culture is usually a contaminant and does not by itself indicate infection. Two or more cultures growing the same organism (Tsukayama Type IV) is the threshold for a true, previously unrecognised low-grade infection. This is why at least five separate deep tissue samples are taken, and why a single positive result is interpreted with caution.
What to do. A genuine Type IV infection is treated with an organism-directed antibiotic course, commonly around 6 weeks and guided by infectious diseases, with the newly implanted components retained; reported outcomes are relatively good because the biofilm burden is low. A single positive culture in a well-appearing patient is generally observed with vigilance rather than treated, unless it is a virulent organism such as S. aureus or other criteria are met.
Positive cultures at stage 2. Growth at reimplantation is more concerning, because it suggests persistent infection. A single contaminant may again be observed, but two or more concordant cultures mean the infection was not cleared: continue or restart targeted antibiotics, reconsider whether reimplantation was premature, and be prepared for repeat resection or long-term suppression.
Surgical Technique
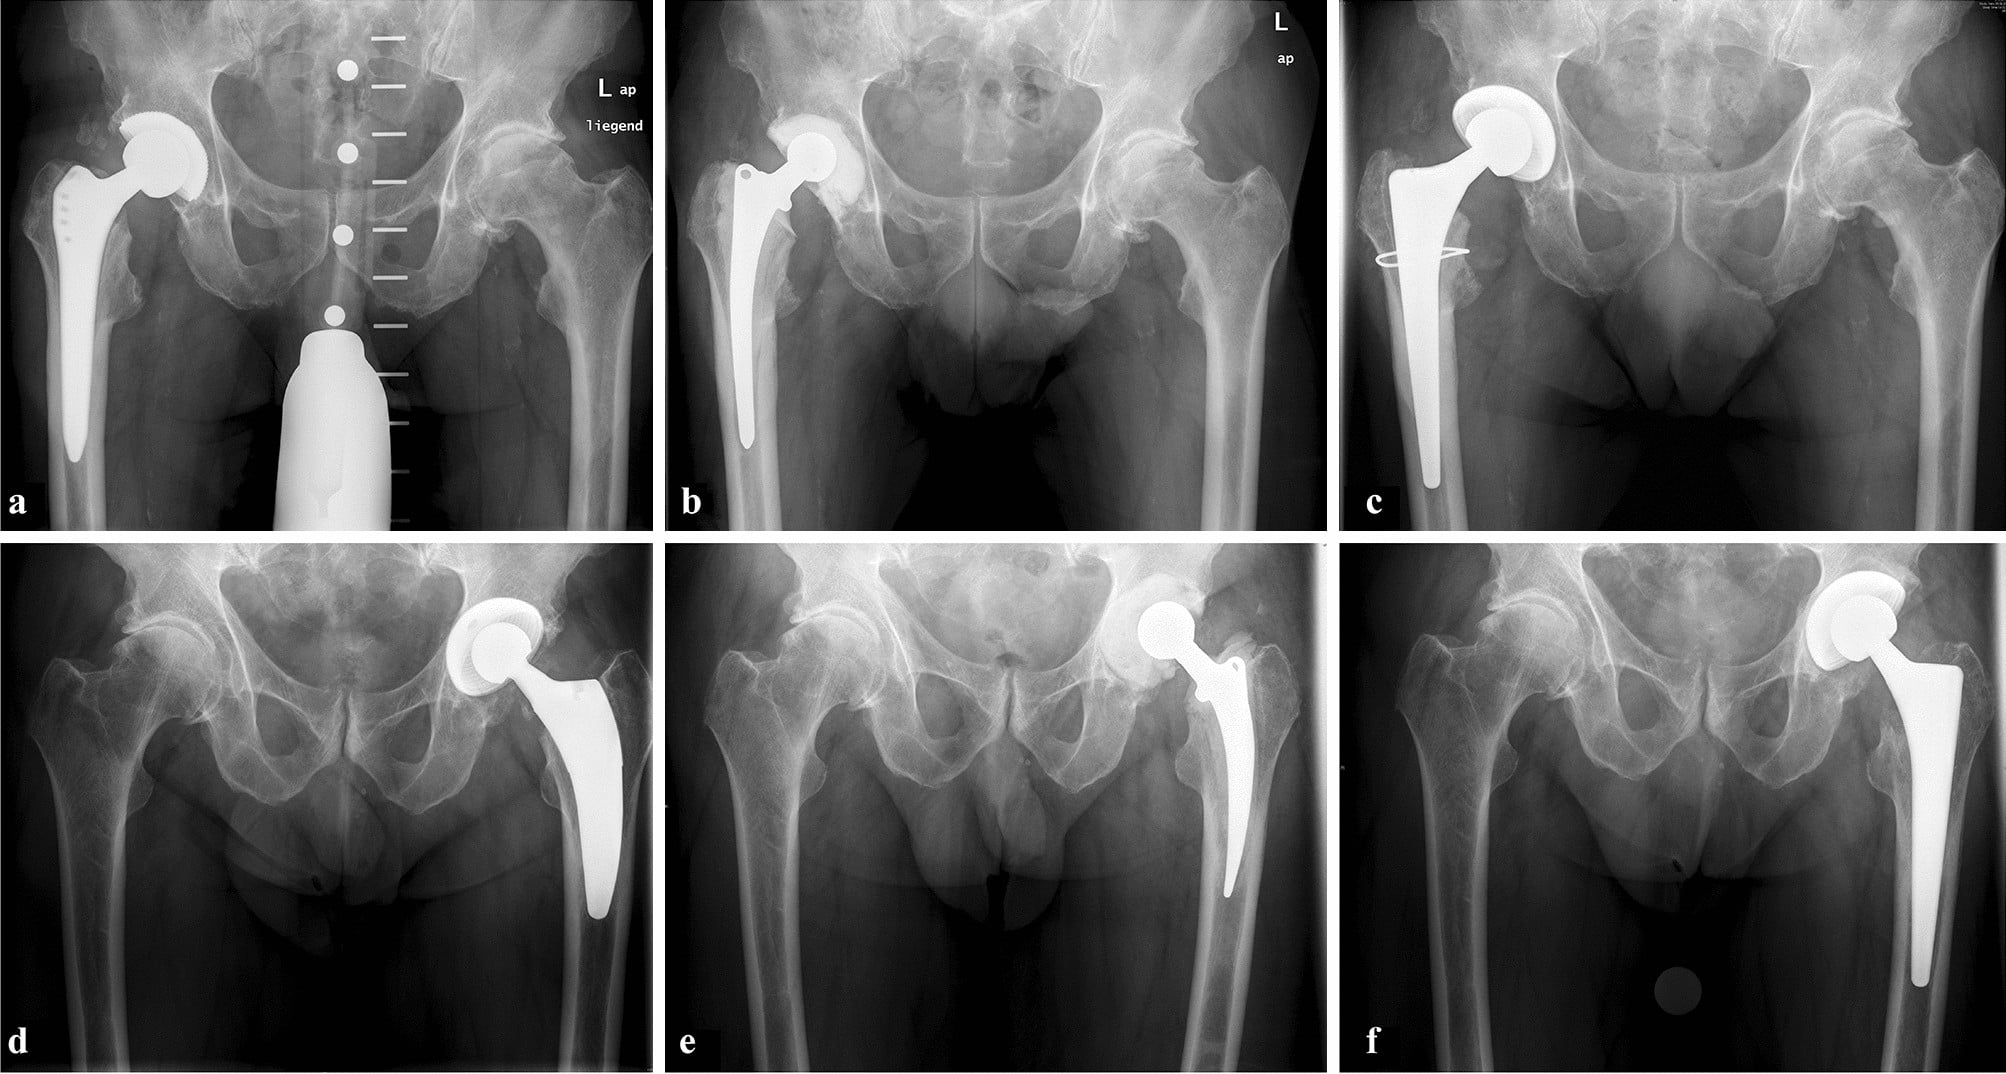
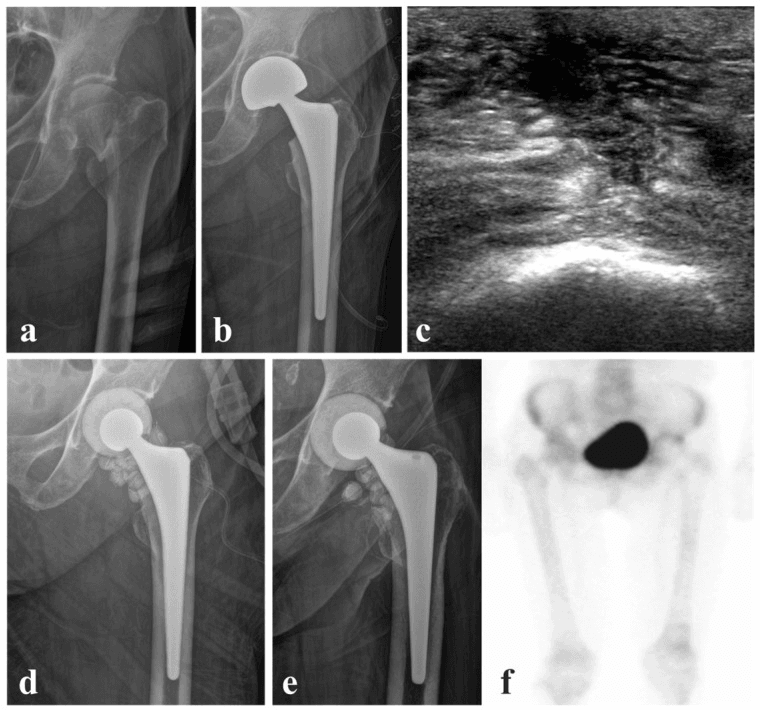
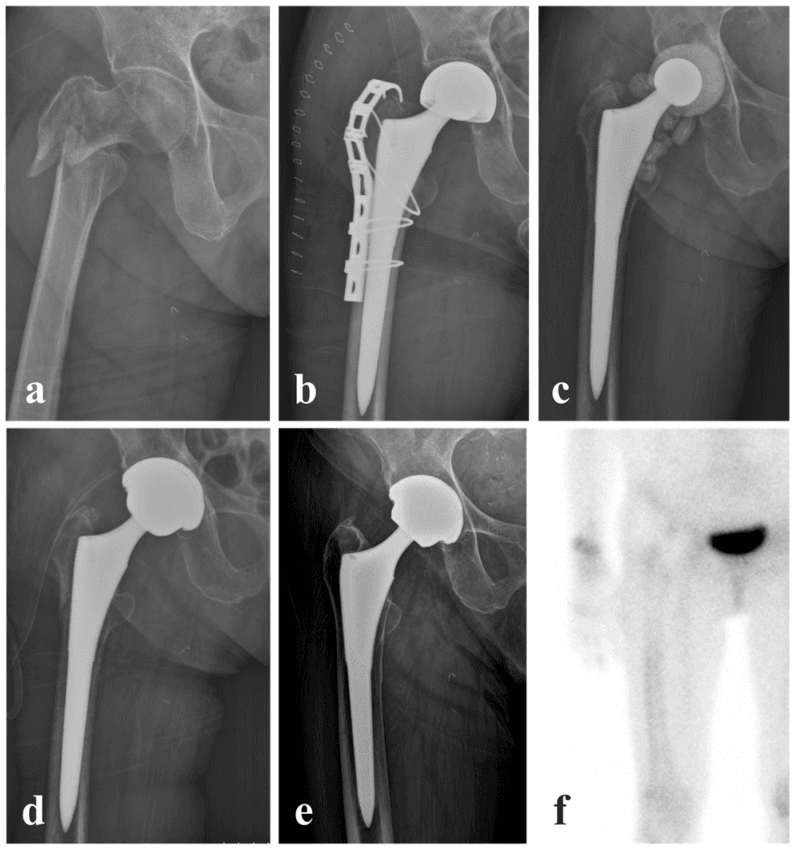
The steps of debridement, antibiotics and implant retention (DAIR):
- Approach through the previous surgical incision.
- Exposure: a full capsulotomy, and inspect the entire joint.
- Debridement: a complete synovectomy, removing all the synovium; debride necrotic tissue, inspect the component-bone interfaces and remove loose debris.
- Component assessment: test stability with a push-pull test and inspect for loosening and wear. If loose, convert to two-stage.
- Modular exchange: remove the femoral head and acetabular liner and fit new ones, never reusing them, then check for neck-liner impingement.
- Irrigation: copious, a minimum of 6 litres of normal saline without additives, with pulsatile lavage for the deeper areas.
- Cultures: a minimum of 5 tissue samples from different locations.
- Closure in layers over a drain.
Always exchange ALL modular components during DAIR (head and liner). Biofilm forms on these surfaces. Reusing modular components dramatically increases DAIR failure rate.
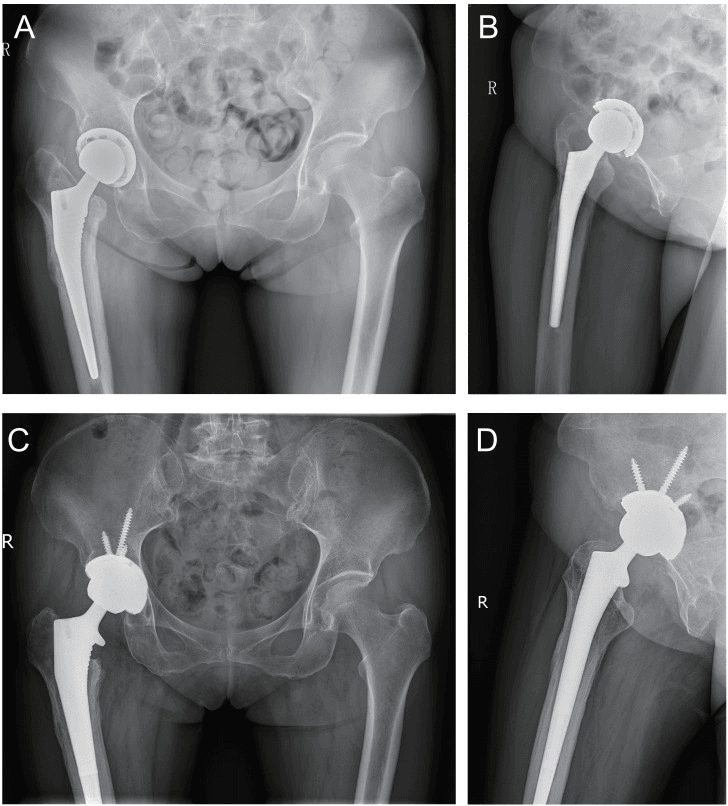
Complications
- Incidence
- 10-20% (two-stage), 20-40% (DAIR)
- Prevention/Management
- Adequate debridement, appropriate antibiotics, good host optimisation
- Incidence
- Common in chronic PJI
- Prevention/Management
- Staged reconstruction, impaction grafting, revision components
- Incidence
- 10-15% (fracture, dislocation)
- Prevention/Management
- Articulating spacer preferred, patient education on weight-bearing
- Incidence
- 5-15% (renal, hepatic, GI)
- Prevention/Management
- Drug level monitoring, renal function checks, ID consultation
- Incidence
- 20-30% even after successful treatment
- Prevention/Management
- Set realistic expectations, consider salvage if infection cleared
- Incidence
- 1-2% (higher in elderly, comorbid)
- Prevention/Management
- Early recognition, aggressive treatment, optimise comorbidities
Recurrent infection is the most devastating complication. Resistant organisms, an immunocompromised host and inadequate debridement all raise the risk. It is managed by a repeat two-stage, with salvage by resection arthroplasty considered.
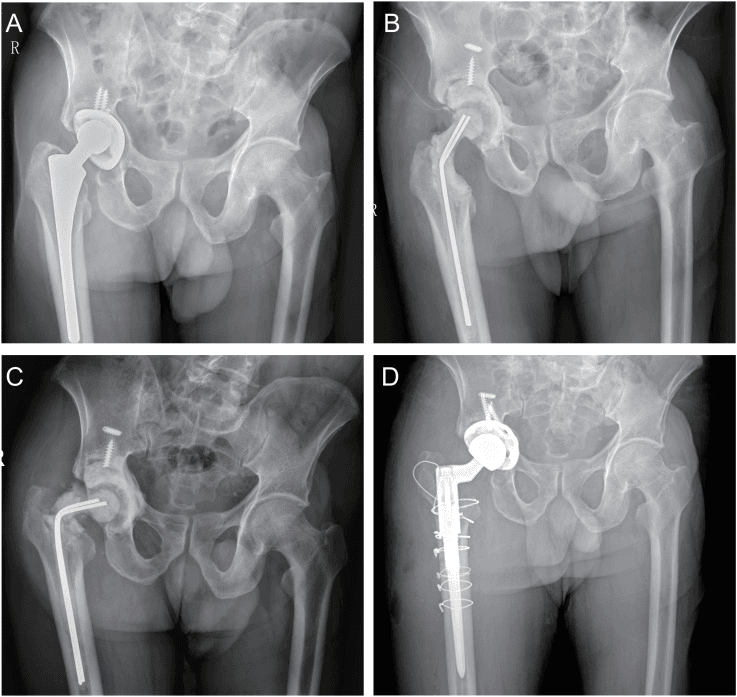
Antibiotic toxicity. Each class carries its own risk:
- Vancomycin - nephrotoxicity; monitor trough levels and creatinine
- Aminoglycosides - oto- and nephrotoxicity; avoid in renal impairment
- Rifampicin - hepatotoxicity and drug interactions; monitor LFTs
- Fluoroquinolones - tendon rupture; avoid in the elderly if possible
Postoperative Care and Rehabilitation
After DAIR. Recovery follows a standard THA, with the antibiotic course layered on top.
- Standard THA precautions
- Early mobilisation (POD 1-2)
- IV antibiotics
- Monitor wound closely
- Continue IV antibiotics (home IV via PICC if stable)
- Transition to oral antibiotics at 4-6 weeks
- Progressive weight-bearing
- Outpatient physiotherapy
- Oral suppressive antibiotics
- Continue mobilisation and strengthening
- Monitor inflammatory markers monthly
- Continue oral antibiotics (per ID)
- Monitor for recurrence
- Gradual return to activities
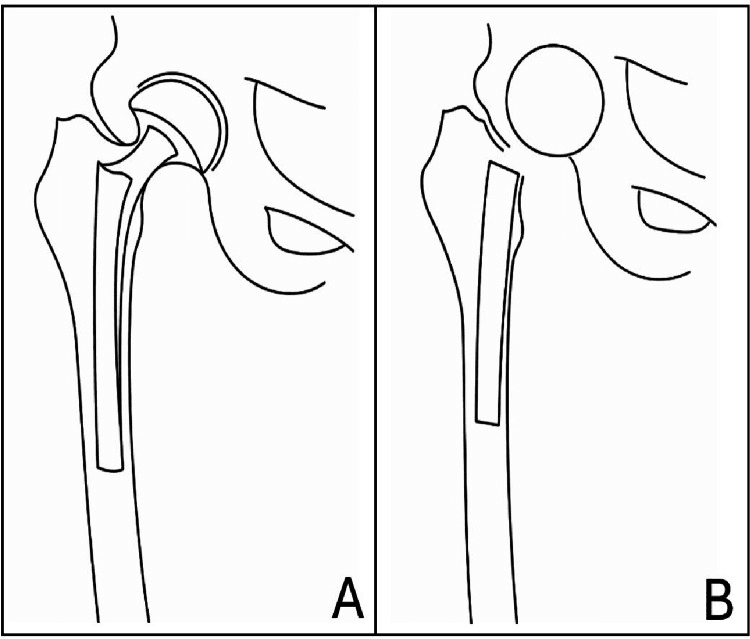
After stage 1. Weight-bearing is protected, partial with a walker or crutches, though an articulating spacer allows mobilisation. IV antibiotics start in hospital and continue at home through a PICC line. Manage expectations: this is a phase of significant disability, and the spacer is intended to be temporary, retention as definitive treatment being reserved for selected patients (see Outcomes and Prognosis).
Between the stages. Continue antibiotics per protocol, monitor the inflammatory markers and aspirate the hip off antibiotics before stage 2. Optimise the medical comorbidities and nutrition (albumin, vitamin D).
After stage 2. Standard THA precautions, early mobilisation on day 1-2, and weight-bearing as tolerated if fixation is stable; antibiotics follow the protocol under Antibiotic Therapy.
Long-term surveillance. Check the inflammatory markers at 3, 6 and 12 months, then review clinically and radiographically every year. Any new pain or symptoms should prompt a search for recurrence, and patients should be educated about dental prophylaxis.
Outcomes and Prognosis
- Success Rate
- 30-60%
- Functional Outcome
- Good if successful
- Complications
- High reinfection
- Success Rate
- 80-85%
- Functional Outcome
- Good
- Complications
- Moderate reinfection
- Success Rate
- 90-95% (sensitive)
- Functional Outcome
- Good to fair
- Complications
- Lowest reinfection
- Success Rate
- 95% infection control
- Functional Outcome
- Poor function
- Complications
- Pain, instability
Favourable factors. Sensitive organisms, Streptococcus best of all; a healthy host without immunosuppression; early diagnosis and treatment; a good soft-tissue envelope; and adequate bone stock.
Unfavourable factors. MRSA, resistant Gram-negatives and fungi; an immunosuppressed host (steroids, biologics); multiple prior surgeries; extensive bone loss; polymicrobial infection; and culture-negative PJI.
Even with successful infection eradication, functional outcomes after two-stage revision are inferior to primary THA. Patients have longer recovery, more pain, worse ROM, and lower satisfaction scores. Setting realistic expectations is critical.
The long view. PJI survivors have increased mortality compared with matched controls, and their quality of life is significantly affected. The economic burden, from lost work and caregiver needs, is substantial, and depression and anxiety are common.
When the spacer stays. In selected patients, spacer retention can be definitive treatment.
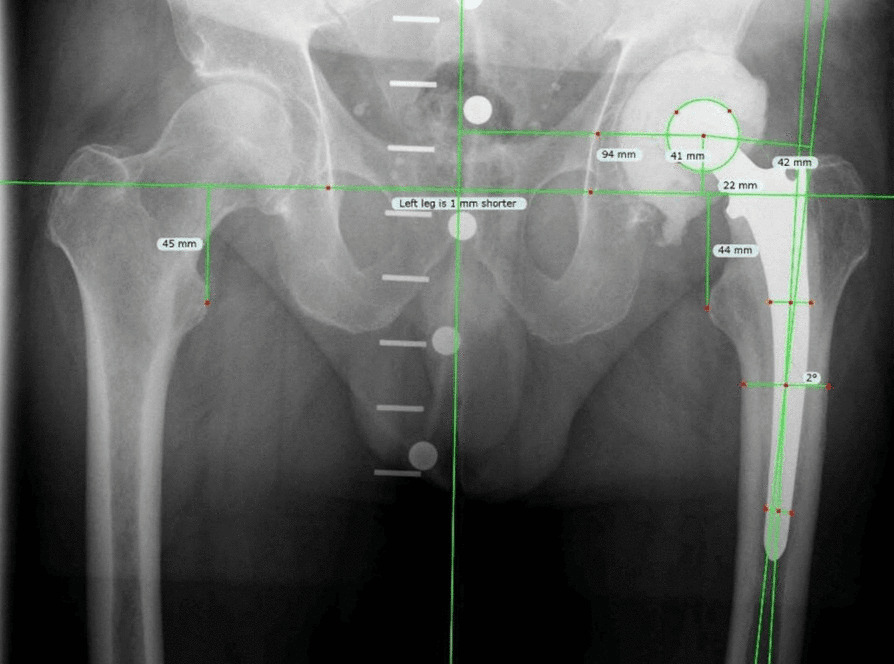
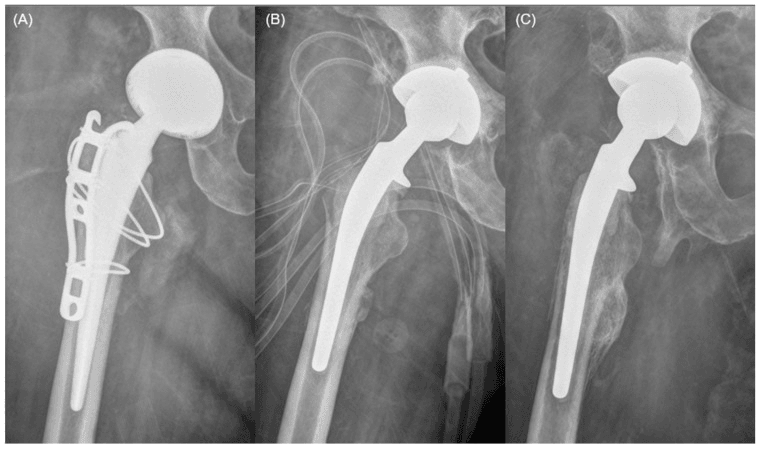
Prevention Strategies
Optimisation before surgery. Medical optimisation reduces infection risk by 50% or more in high-risk patients. The targets:
- HbA1c under 7% in diabetics
- BMI under 35, considering weight loss if over 40
- Albumin over 3.5 g/dL
- Smoking cessation for 4 weeks or more before surgery
- Optimised rheumatoid or inflammatory disease, minimising steroids
Screening and treatment. Screen for and treat MRSA colonisation (nasal mupirocin), clear remote infections (dental, skin, UTI), and optimise immunosuppression, holding biologics perioperatively per protocol.
System-level prevention. Globally, prevention also works at the level of whole systems:
- National surgical site infection surveillance programmes (e.g. NHSN in the US, the UK SSI surveillance service, ECDC HAI-Net) benchmark and drive down rates
- Standardised perioperative antibiotic prophylaxis protocols and the WHO Surgical Safety Checklist
- Preoperative optimisation pathways (glycaemic control, MRSA decolonisation, nutrition, smoking cessation) in high-volume arthroplasty centres
Guidelines, Registries & Global Practice
Global epidemiology:
- Primary THA PJI incidence ~1-2%; revision THA 3-5%
- Infection is consistently among the top 3 indications for THA revision worldwide, alongside aseptic loosening and dislocation/instability
- Absolute case numbers are rising as arthroplasty volume and patient age/comorbidity increase, even where the percentage rate is stable
Registry evidence (cumulative revision for infection):
- Region
- England, Wales, NI
- Notable finding
- Infection a leading early-revision cause; rising as a proportion of revisions over time
- Region
- United States
- Notable finding
- Infection among top reported revision indications, especially within 2 years of index surgery
- Region
- Australia/New Zealand
- Notable finding
- Primary THA revision for infection ~1% at 10 years; higher after revision surgery
- Region
- Sweden
- Notable finding
- Long-term data underpin prophylaxis and bearing-related infection-risk analyses
- Region
- Norway / New Zealand
- Notable finding
- Confirm antibiotic-loaded cement and prophylaxis associations with lower infection-related revision
Side-by-side guideline comparison:
- Diagnosis
- Scoring-based definition (score 6 or more)
- DAIR
- Acute infection, stable implant, susceptible organism
- Exchange strategy
- Two-stage default; one-stage in selected cases
- Diagnosis
- Clinical + culture + histology
- DAIR
- DAIR acceptable for early/acute with stable implant
- Exchange strategy
- Staged or one-stage exchange; rifampin for staphylococci
- Diagnosis
- MDT-led, off-antibiotics aspiration
- DAIR
- DAIR for acute, well-fixed implant
- Exchange strategy
- Increasing single-stage use (INFORM RCT support)
- Diagnosis
- Tiered "confirmed/likely/unlikely" definition
- DAIR
- Early acute, susceptible organism
- Exchange strategy
- Two-stage or one-stage by host/organism
Resource-setting variation:
- High-resource: dedicated bone-infection MDTs (orthopaedics, ID, microbiology, plastics), sonication, molecular/next-generation sequencing, articulating spacers, and single-stage exchange programmes
- Limited-resource: reliance on serum markers and aspiration without alpha-defensin or sonication; two-stage and resection arthroplasty (Girdlestone) more frequently used where revision implants, prolonged IV antibiotics, or spacer fabrication are constrained
Be prepared to discuss MSIS/ICM 2018 diagnostic criteria (major and minor with scoring). Know the treatment algorithm: DAIR for acute with strict criteria; staged or one-stage exchange for chronic. Cite the INFORM RCT showing single-stage non-inferiority for the hip. Understand organism-specific management (especially S. aureus vs Streptococcus) and rifampicin use for staphylococci with retained or reimplanted components.
Related pages: Periprosthetic Joint Infection is the parent topic covering principles common to all joints, and TKA Complications: Infection is the knee counterpart - the diagnostic thresholds differ between hip and knee, which is why the 2018 definition's synovial cut-offs must be applied to the right joint; Biofilm Formation is the reason tissue culture misses a third of cases, why sonication works, why rifampin is added, and why a chronically infected implant must come out - every treatment decision on this page descends from it; Orthopaedic Antibiotic Therapy and Antibiotic Pharmacology and Resistance for the agents, durations and the rifampin combination rule the IDSA card anchors; Local Antibiotic Delivery for cement spacers, beads and the elution kinetics that determine whether an interval spacer is therapeutic or merely a placeholder; Perioperative Antibiotics and Surgical Site Infection Prevention for the prophylaxis that prevents most of this; Revision THA for the reconstruction at reimplantation, including the bone loss a resection arthroplasty leaves behind; THA Aseptic Loosening is the differential that must be excluded in every painful replacement, because an infected loose stem and an aseptically loose stem are radiographically identical; Synovial Fluid and Synovium for the aspirate that carries five of the eight scored minor criteria; and Osteomyelitis Pathophysiology for bone infection without an implant, and for the sequestrum-and-involucrum logic that explains why dead bone and dead space must be addressed as well as the organism.
Controversies and Areas of Uncertainty
The evidence base in PJI is evolving, and several management questions remain genuinely contested.
One stage or two. Two-stage is the traditional "gold standard", and the success rates quoted above favour it. But the INFORM RCT (BMJ 2022) and the Kunutsor meta-analysis show comparable re-infection with faster recovery, fewer intraoperative events and lower cost for single-stage in selected hips. The meta-analysis pooled cohorts in which the surgeon chose the operation, and the debate is shifting from "which is better" to "which patient for which strategy".
Antibiotic duration. The OVIVA trial (NEJM 2019) showed oral therapy was non-inferior to IV for bone and joint infection in the first 6 weeks, challenging routine prolonged IV courses. Total duration, 6 weeks against 12 weeks against lifelong suppression, remains unsettled and is being tested in ongoing trials.
DAIR criteria and timing. The "3-week biofilm window" is a useful heuristic, not a hard rule. Reported success varies widely with the organism, the host and the quality of debridement, and whether a single thorough DAIR or a planned repeat debridement is better is debated.
Diagnostic thresholds. Alpha-defensin, synovial CRP, leukocyte esterase, D-dimer and next-generation sequencing each add value but lack universal cut-offs. Culture-negative PJI and the significance of low-virulence organisms such as Cutibacterium remain difficult areas.
Spacer type and dosing. Articulating against static spacers, and high-dose antibiotic loading of cement, are supported mainly by cohort data; the systemic toxicity ceiling and the ideal elution profile are not standardised.
Suppression or eradication. In frail or multiply-revised patients, long-term suppressive antibiotics with implant retention may be preferable to repeated major surgery, but their durability and the risk of resistance are uncertain.
MCQ Practice Points
Q: What are the two major criteria for PJI diagnosis in MSIS 2018? A: (1) Sinus tract communicating with the prosthesis, OR (2) Two positive cultures of the same organism from separate samples. Either ONE major criterion is sufficient for definite PJI diagnosis.
Q: Which minor criteria are worth 3 points each in the MSIS 2018 scoring system? A: (1) Alpha-defensin (qualitative positive), (2) Leukocyte esterase (++ or +++), (3) Histology (over 10 PMN/HPF in 5 high-power fields). Score of 6 or more equals definite PJI.
Q: What are the strict criteria that must ALL be met for DAIR to be appropriate? A: (1) Acute infection (under 3 weeks symptoms OR under 3 months from surgery), (2) Stable/well-fixed implant, (3) Known organism with sensitivities, (4) No sinus tract, (5) Reasonable host (not severely immunocompromised).
Q: What are the success rates for two-stage revision based on organism? A: Sensitive organisms (Strep, MSSA): 90-95%. S. aureus: 85-90%. Resistant organisms (MRSA, resistant GNR): 70-80%. Fungi: under 70%. Two-stage has highest success of all treatments.
Q: Why does DAIR only work in acute infections (under 3 weeks)? A: Biofilm maturation takes 3-4 weeks. Mature biofilm protects bacteria from antibiotics (increases MIC by 1000-fold) and immune system. Before biofilm matures, antibiotics can penetrate. After maturation, implant removal is required for eradication.
Q: When should rifampicin be used in PJI treatment? A: For Staphylococcus species (S. aureus, MRSA, CoNS) when implant is retained (DAIR or after reimplantation). Rifampicin enhances biofilm penetration. Never use as monotherapy - always combine with another active agent to prevent resistance.
Q: What are the main causes of culture-negative PJI and how is it managed? A: Causes: (1) Prior antibiotics (most common), (2) Fastidious organisms (slow-growing), (3) Biofilm (organisms in biofilm less culturable). Manage with: extended culture incubation (14 days), molecular diagnostics, sonication of removed implants, empiric broad-spectrum antibiotics (vancomycin + broad Gram-negative coverage).
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 68-year-old man is 10 days post-primary THA. He develops increasing hip pain, fevers to 38.5°C, and the wound has serous drainage. ESR 65, CRP 120. What is your assessment and management?”
“A 72-year-old woman had a primary THA 18 months ago. She has had persistent pain since surgery, never pain-free. X-rays show subtle periosteal reaction and focal osteolysis. ESR 45, CRP 35. Hip aspiration grows coagulase-negative Staphylococcus (CoNS) from 2 of 3 samples. How do you manage this?”
“A 65-year-old man had a well-functioning THA 5 years ago (pain-free until now). He presents with 1 week of acute severe hip pain and fever following a dental extraction 2 weeks ago. ESR 75, CRP 95. X-rays show well-fixed components with no loosening. Hip aspiration grows Streptococcus viridans. What is your management?”
MSIS 2018 MAJOR CRITERIA (ONE = DEFINITE PJI)
- 1. Sinus tract communicating with prosthesis
- 2. Two positive cultures of same organism (separate samples)
- Either ONE major criterion alone = definite PJI diagnosis
- No further workup required if major criterion present
MSIS/ICM 2018 MINOR CRITERIA (SCORE 6+ = DEFINITE PJI)
- Elevated serum CRP or D-dimer = 2 points
- Elevated serum ESR (over 30 mm/hr) = 1 point
- Elevated synovial WBC (over 3000) = 3 points
- Elevated synovial PMN% (over 70%) = 2 points
- Positive alpha-defensin = 3 points
- Positive LE (++ or +++) = 3 points
- Elevated synovial CRP (over 6.9 mg/L) = 1 point
- Single positive culture (intraoperative) = 2 points
- Positive histology (over 10 PMN/HPF, 5 fields) = 3 points
DAIR STRICT CRITERIA (ALL MUST BE MET)
- Acute: under 3 weeks symptoms OR under 3 months from surgery
- Stable/well-fixed implant (no loosening)
- Known organism with sensitivities
- No sinus tract present
- Healthy host (not severely immunocompromised)
TWO-STAGE REVISION (GOLD STANDARD)
- Stage 1: Complete removal, debridement, antibiotic spacer
- IV antibiotics 4-6 weeks, oral until stage 2
- Antibiotic holiday 2-6 weeks before stage 2
- Aspirate off antibiotics before stage 2
- Stage 2: Reimplant when infection cleared (normal markers, negative aspirate)
- Success: 90-95% sensitive organisms, 85% MSSA, 70-75% resistant
ORGANISM-SPECIFIC TREATMENT
- MSSA: Flucloxacillin IV → cefalexin + rifampicin PO
- MRSA: Vancomycin IV → linezolid/cotrimoxazole PO (longer duration)
- Streptococcus: Penicillin/ceftriaxone (best DAIR success 70-80%)
- Enterococcus: Ampicillin + gentamicin (synergy)
- Gram-negatives: Ciprofloxacin + rifampicin
- Culture-negative: Vancomycin + pip-tazo (broad empiric)
KEY PEARLS AND TRAPS
- Biofilm matures in 3-4 weeks → why DAIR only works early
- Rifampicin for Staph with retained implants (never monotherapy)
- DAIR success 30-60% overall (organism-dependent)
- Culture before antibiotics (2 weeks off if possible)
- Never use spacer as permanent implant (cement toxicity)
- Alpha-defensin best single test (sens 97%, spec 97%)
- Chronic PJI can mimic aseptic loosening - always rule out infection
Evidence Base
Parvizi et al. The 2018 Definition of Periprosthetic Hip and Knee Infection
- Multi-institutional development and external validation of an updated scoring-based PJI definition (n=1504 development cohort, 422 validation). Major criteria: two positive cultures of the same organism OR a sinus tract. Preoperative minor criteria weighted: serum CRP and D-dimer 2 points each, ESR 1; synovial WBC 3, alpha-defensin 3, leukocyte esterase 3, PMN% 2, synovial CRP 1. Score 6 or more equals infected. New criteria sensitivity 97.7% versus MSIS 79.3% and ICM 86.9%, specificity 99.5%.
Kunutsor et al. Re-infection after one- vs two-stage revision of infected hip prosthesis
- Meta-analysis of 38 one-stage studies (2,536 patients) and 60 two-stage studies (3,288 patients) for infected THA. Pooled re-infection rate 8.2% (95% CI 6.0-10.8) after one-stage versus 7.9% (95% CI 6.2-9.7) after two-stage, with no significant difference and rates similar across subgroups. No randomised trials existed at the time.
Blom et al. Single- vs two-stage revision for hip PJI (INFORM RCT)
- Pragmatic RCT of 140 adults with hip PJI (65 single-stage, 75 two-stage) across the UK and Sweden. No difference in WOMAC pain/function at 18 months (mean difference 0.13, 95% CI -8.2 to 8.5), but single-stage was better at 3 months and had fewer intraoperative events (8% vs 27%). Markers of possible ongoing infection at 18 months: 14% vs 11% (NS). Single-stage was cost-effective.
Trampuz et al. Sonication of removed hip and knee prostheses
- Prospective study of 331 explanted hip/knee prostheses (79 infected). Culture of sonicate fluid (which dislodges biofilm bacteria) was more sensitive than periprosthetic-tissue culture: 78.5% vs 60.8% overall (p less than 0.001), and 75.0% vs 45.0% in patients given antibiotics within 14 days before surgery. Specificity ~99% for both.
Osmon et al. IDSA Clinical Practice Guidelines for PJI
- Infectious Diseases Society of America guidelines covering DAIR, resection with staged reimplantation, one-stage exchange, and amputation. Recommend 2-6 weeks of pathogen-directed IV (or highly bioavailable oral) therapy, addition of rifampin for staphylococcal infection when the implant is retained or reimplanted, and routine infectious-diseases involvement.
Lora-Tamayo et al. S. aureus PJI managed with DAIR (REIPI multicentre cohort)
- Largest cohort of Staphylococcus aureus PJI treated with DAIR: 345 episodes (81 MRSA). Overall success 55%; failure 45%, often early. No overall prognostic difference between MSSA and MRSA. Rifampin-based combinations had an independent protective effect. Predictors of failure: polymicrobial, inflammatory and bacteraemic infection, need for more than one debridement, immunosuppression, and not exchanging modular components.