Post-Arthroplasty Femoral Fracture | Vancouver Classification | Revision Arthroplasty
- Stem stability is a diagnosis integrating serial films, implant design, interfaces and safe direct testing—not one lucency sign
- B1 usually supports fracture-specific fixation; B2/B3 usually support revision/reconstruction, with selected host/implant exceptions
- Map fracture morphology, bone stock, infection, acetabular/other implant status and whole-femur mechanics
- Obtain imaging that covers the actual fracture and planned construct; full-length views are not technically possible or necessary in every patient
- Screen infection when history, osteolysis/loosening, wound, inflammatory markers or operative findings raise concern
- “Do not reduce treatment to B1 ORIF versus B2 revision
- “A selected B2 around specific cemented stem mechanics may be fixed without exchange
- “A Type C fracture still interacts with the stem tip and other implants
- “Prepare fixation and revision options when stability remains uncertain
Periprosthetic Fractures Around Total Hip Arthroplasty
Overview and Epidemiology
Periprosthetic femoral fracture is now among the top 3-4 reasons for THA revision across the major joint registries (NJR, AJRR, AOANJRR, Swedish/Nordic). Incidence is rising globally with ageing populations, the dominance of uncemented stems and the growing cumulative pool of primary THAs.
Intraoperative fracture. The technical risks are revision surgery (4-7% risk), uncemented press-fit stem insertion, undersized canal preparation and excessive impaction force. The patient risks are rheumatoid arthritis, severe osteoporosis and anterior femoral cortical defects.
Postoperative fracture. On the implant side, the risks are aseptic loosening with osteolysis, stress shielding with cortical thinning, and a retained cement mantle. On the patient side, they are age over 70, female sex (2.5 times the risk) and frequent falls.
Epidemiology of Periprosthetic Fracture (Primary THA)
- Intraoperative fracture in 1.7% overall; 14x more common with uncemented stems (3.0% vs 0.23% cemented)
- 20-year cumulative postoperative fracture probability 3.5% (7.7% uncemented vs 2.1% cemented)
- Within 30 days, postop fracture risk after an uncemented stem was 10x higher than cemented
- Intraoperative fractures most common in women and patients over 65; most occurred during femoral component placement (60%) and involved the calcar (69%)
- Vancouver AG was the most common postoperative type (32%); 67% followed a fall
Anatomy and Biomechanics
Stress shielding. Rigid metallic stems transfer load distally, bypassing the proximal femur. The proximal femur adapts by resorbing bone (Wolff's law), and the resulting cortical thinning and osteopenia significantly increase the risk of fracture from minor trauma.
Bone quality. Wear debris induces cytokine-mediated bone loss, which is osteolysis. A cortex less than 4mm thick increases fracture risk exponentially, and osteopenia is common in the THA population.
Danger zones. Three sites, each with its own cause:
- Anterior cortex at the apex of the femoral bow, a common perforation site
- Proximal lateral cortex, at risk from aggressive broaching
- Calcar, with varus stem malposition
Prevention. Choose the stem, its fixation and the insertion technique from femoral morphology and patient risk. Prophylactic cerclage is selective, not routine for every fragile femur.
Classification Systems
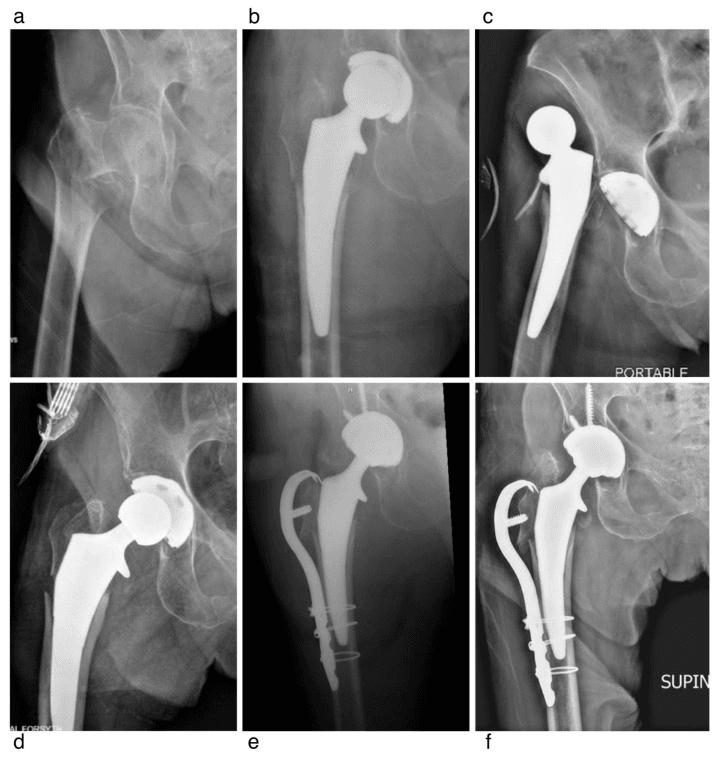
Femoral: Vancouver. A descriptive framework based on location, stem status and bone stock. It does not encode host, infection, implant design or fracture morphology, so each type gives a usual direction that those factors can change.
- Location
- Greater/lesser trochanter
- Stem and Bone
- Assess stem relevance and bone
- Usual Direction
- Observe or fix according to displacement/function
- What Can Change It
- Displacement, abductor function, osteolysis and stem relevance
- Location
- Around stem
- Stem and Bone
- Truly stable stem, usable bone
- Usual Direction
- Fracture-specific fixation
- What Can Change It
- Morphology, bone, infection and fixation corridors
- Location
- Around stem
- Stem and Bone
- Loose stem, usable bone
- Usual Direction
- Usually revision plus fracture reconstruction; selected fixation exceptions
- What Can Change It
- Host risk, cemented-stem mechanics and reducibility
- Location
- Around stem
- Stem and Bone
- Loose stem, deficient bone
- Usual Direction
- Revision plus reconstruction or replacement
- What Can Change It
- Remaining distal bone, abductors, infection and goals
- Location
- Distal to stem
- Stem and Bone
- Assess stem and interprosthetic mechanics separately
- Usual Direction
- Fracture-specific fixation with overlap/stress-riser planning
- What Can Change It
- Stem stability, overlap, interprosthetic segment and alignment
Vancouver Classification Reliability
- Interobserver agreement substantial: kappa 0.69 (consultants), 0.61 (trainees)
- Intraobserver kappa 0.74-0.90 (substantial to almost perfect)
- Validity in 37 type B cases: 81% agreement on B1/B2/B3 subgroup, kappa 0.68
- Authors emphasise intraoperative assessment of implant stability when radiographs are equivocal
Acetabular: modified Petersen. Acetabular fractures are described by timing and cup stability.
- Description
- Intraoperative
- Cup Status
- Stable
- Management
- Screws/Plate + Cup
- Description
- Postoperative
- Cup Status
- Stable
- Management
- Conservative (if min displaced)
- Description
- Postoperative
- Cup Status
- Unstable
- Management
- Revision (Cage/Triflange)
Vertical shear fracture separating anterior and posterior columns. Requires complex reconstruction with cup-cage constructs or custom triflange implants.
Clinical Assessment
History. Establish the mechanism, a low-energy fall or higher-energy trauma. Prodromal thigh or groin pain suggests loosening. Record pre-injury function, from independent to bedbound, and comorbidities such as osteoporosis, rheumatoid arthritis and steroid use.
Examination. Look for shortening, rotation and swelling, and feel for tenderness and crepitus. A sciatic and femoral nerve check is mandatory, and systemic signs of infection or sepsis are sought.
Any of these requires immediate orthopaedic review.
- Open fracture - rare but critical
- Neurovascular compromise - sciatic nerve palsy
- Compartment syndrome - pain out of proportion; keep a high index of suspicion
- Septic loosening - a red, hot, swollen joint with a fracture; is this an infected arthroplasty?
- Acetabular involvement - do not miss pelvic discontinuity
- Skin - a compromised soft-tissue envelope
Investigations
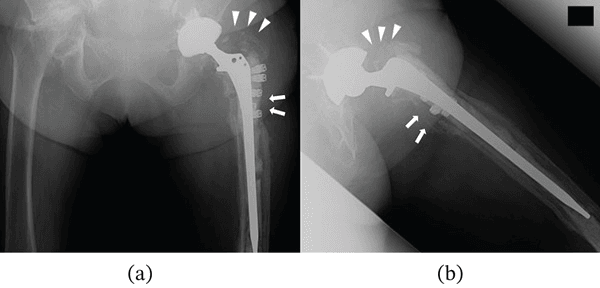
Radiographs. Obtain an AP pelvis and orthogonal femoral views that include the entire fracture, the implant and the planned fixation or revision zone. Add full-length imaging for distal extension, other implants, deformity or long construct planning. The rule is coverage of the complete injury and every implant or stress riser relevant to the construct, not a mandatory full-length film.
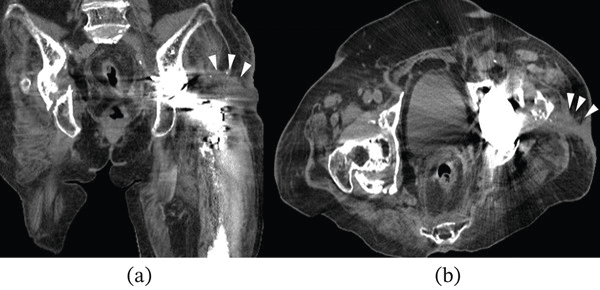
CT. Metal-artefact-reduction CT is used selectively, for occult extension, comminution, bone stock or osteolysis, acetabular or pelvic involvement, or complex revision planning.
Infection work-up. Infection can present with fracture, loosening or osteolysis. ESR/CRP, aspiration and intraoperative cultures and histology are selected from the symptoms, the wound, osteolysis or loosening, prior infection and operative findings, rather than treated as mandatory clearance tests. Normal markers do not exclude infection, and abnormal markers are nonspecific after trauma.
Reading the Stem for Loosening: Gruen Zones and Radiographic Criteria
Distinguishing a stable B1 from a loose B2 is the single most important decision in this topic. The signs are read against a standard map, the Gruen zones, using defined loosening criteria.
Gruen zones. The femoral component is divided into seven zones on the AP film, numbered 1-7 from the lateral shoulder at the greater trochanter, down the lateral cortex to the stem tip and back up the medial cortex, with matching zones on the lateral view. They give a reproducible language for where a lucency, osteolysis or debonding sits.
Cemented stems: the Harris criteria. A progressive or circumferential lucency is the key signal. Read subsidence against the design, because a polished taper-slip stem may subside within an intact cement mantle by design (see Controversies).
- Definite - stem migration or subsidence, or a fractured cement mantle
- Probable - a continuous radiolucent line at the cement-bone interface around the entire stem
- Possible - a lucent line over 50 to 100% of the interface
Uncemented stems. Loosening is suggested by subsidence or migration on serial films, a continuous reactive line around a porous surface, and a distal pedestal with no proximal bone ongrowth. Spot-welds (endosteal bone bridging to the porous coating) and absence of migration indicate a stable, osseointegrated stem.
When the films stay equivocal. Compare against serial and immediate-postoperative films whenever possible. If the radiographs remain equivocal, test the stem directly at operation before committing: a loose stem fixed as a B1 fails. The selected B2 fixations described under Surgical Technique are a deliberate choice around specific cemented-stem mechanics, not this error.
IMPLANTAssessing Stem Stability (B1 vs B2/B3)
Hook:Check the IMPLANT before you plan your fixation strategy.
Differential Diagnosis
The painful THA with a possible fracture must be distinguished from other causes of acute or progressive hip/thigh pain. The two errors that fail candidates are missing infection (septic loosening masquerading as fracture) and missing occult loosening in an apparently intact femur.
- Key Features
- Trauma/fall, deformity, inability to weight-bear
- Discriminator
- Visible fracture line on full-length femur films
- Action
- Classify (Vancouver) + assess stem stability
- Key Features
- Prodromal start-up thigh pain, gradual onset
- Discriminator
- Radiolucent lines, subsidence, pedestal; no cortical break
- Action
- Workup for revision; exclude infection
- Key Features
- Rest pain, wound/effusion or unexplained osteolysis/loosening
- Discriminator
- Markers plus aspiration/tissue sampling when indicated
- Action
- Plan source control and reconstruction through infection pathway
- Key Features
- Groin pain, cup migration
- Discriminator
- AP pelvis and metal-reduction CT
- Action
- Assess cup stability, columns and reconstructive options
- Key Features
- Activity-related pain, osteoporosis/medications
- Discriminator
- Cortical reaction or occult MRI/CT finding
- Action
- Protect/treat bone and monitor or fix by stability
- Key Features
- Lateral tenderness and weakness
- Discriminator
- Soft-tissue examination/imaging
- Action
- Diagnosis-specific non-operative or repair pathway
Management Algorithm
The decision. Stem stability materially changes the reconstruction, but host, infection, stem design, reducibility, fracture morphology and surgical burden can modify the operation. Do not reduce treatment to B1 ORIF versus B2 revision.
- 1Map
Fracture, stem/cup, bone, infection and whole-femur mechanics
Working phenotype
- 2Assess
Host physiology, function, consent and reconstructive burden
Feasible goals
- 3Prepare
Fixation and revision contingencies when stability uncertain
No unplanned compromise
- 4Treat
Restore stable implant/fracture and alignment with least appropriate morbidity
Individual construct
Non-operative or limited goals. Observation or protected mobilisation may suit selected stable trochanteric or minimally displaced patterns, very frail or nonambulatory patients, or palliative goals. Loading, imaging and escalation depend on displacement, pain, function and construct, not a fixed 5 mm or 6-12 week rule.
Intraoperative Periprosthetic Fracture: Recognition and Management
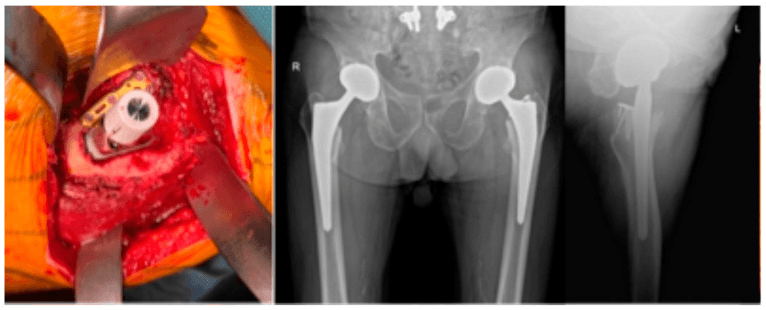
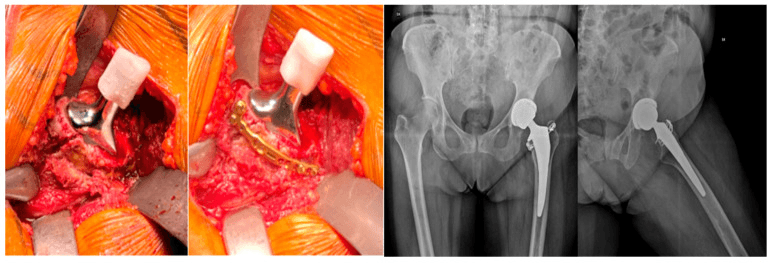
Intraoperative fracture is defined by location, propagation, component stability and bone, not by one cable recipe. Do not assume every calcar crack needs one cable or every split needs a stem two cortical diameters longer.
The sequence. Stop, define the full pattern and component stability, then stabilise the demonstrated deficit:
- Stop the manoeuvre that caused concern, expose and inspect as needed, and image the relevant extent of femur and implant.
- Determine whether the component remains stable and whether seating or removal will propagate the fracture.
- A limited stable calcar or trochanteric crack may be treated with cerclage, screw or plate fixation, but pattern and stem stability can require a different stem, longer fixation or fracture reconstruction.
- Diaphyseal or distal propagation may require a plate, a revision stem or both; bypass and overlap are individualised.
- Re-test implant and fracture stability before closure, and set loading from the actual construct.
Surgical Technique
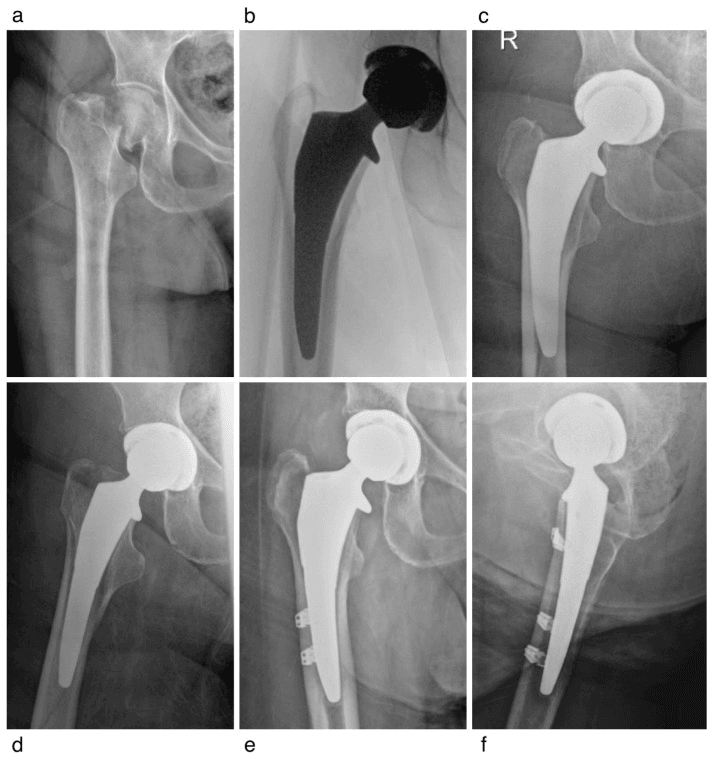
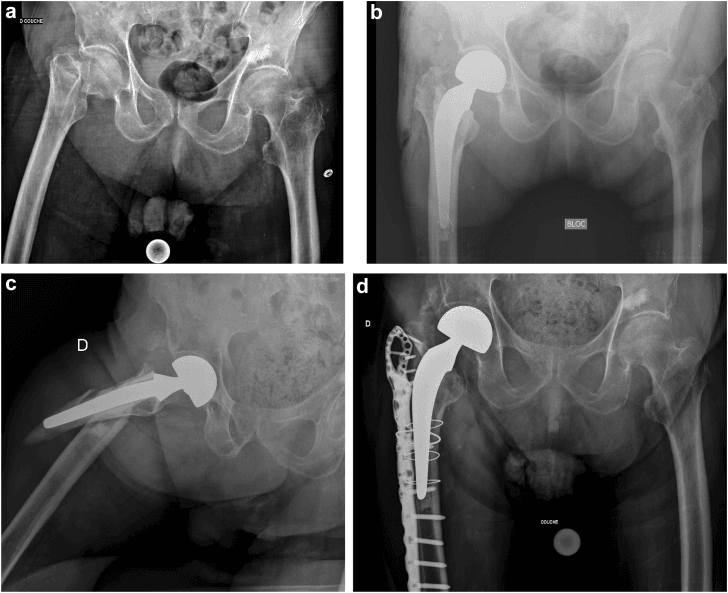
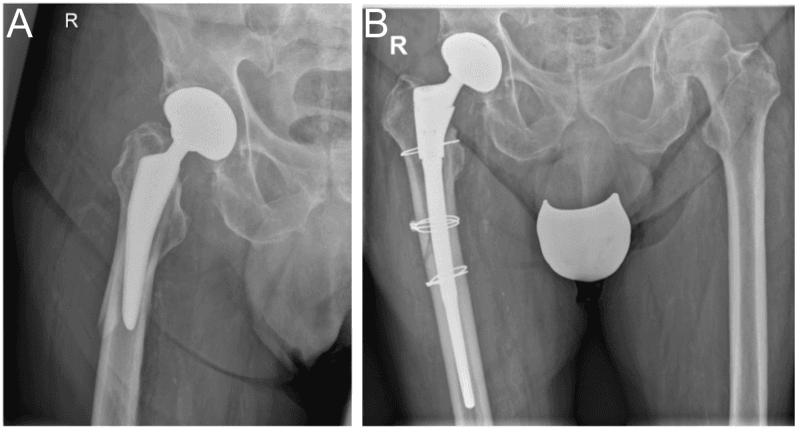
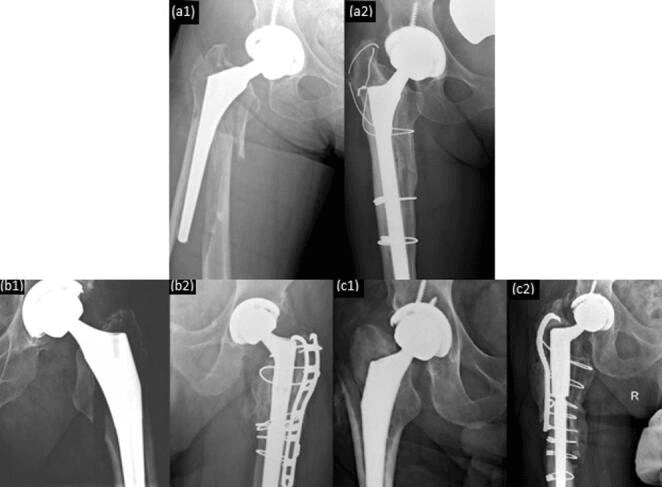
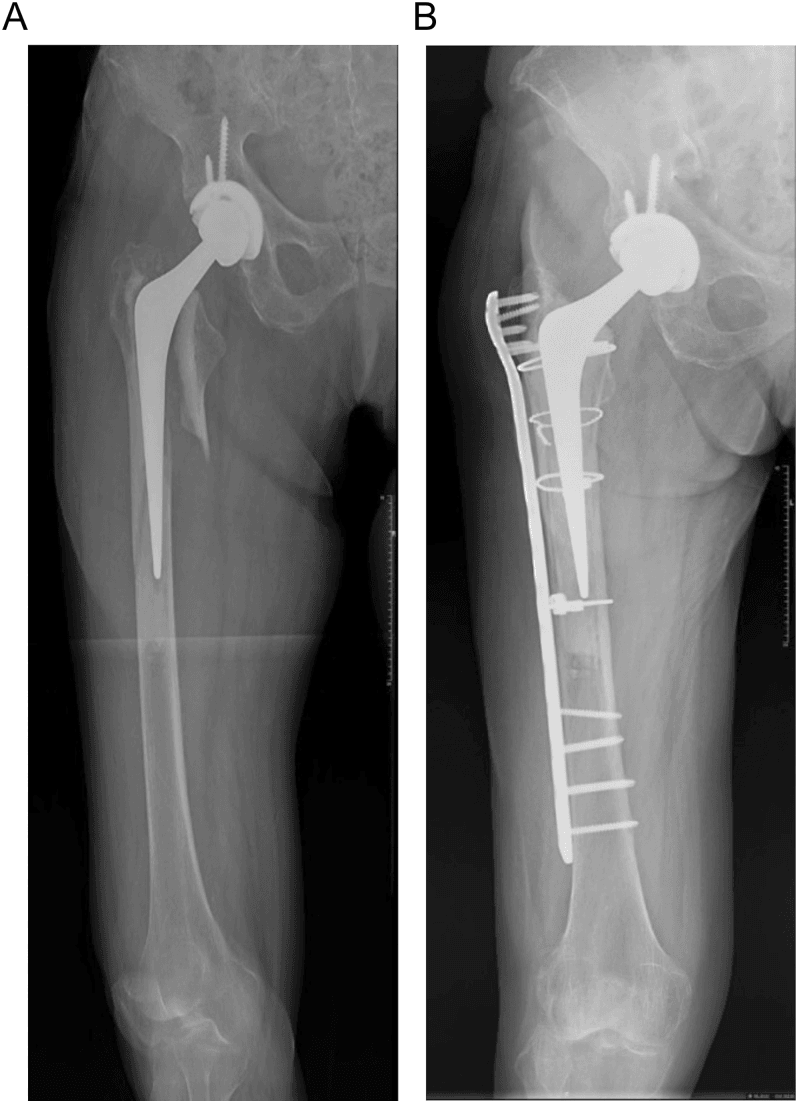
Retaining the stem. Confirm that retaining the stem is defensible after implant-specific serial-film and safe direct assessment. Choose exposure and reduction from morphology and biology, and preserve vascular attachments where possible.
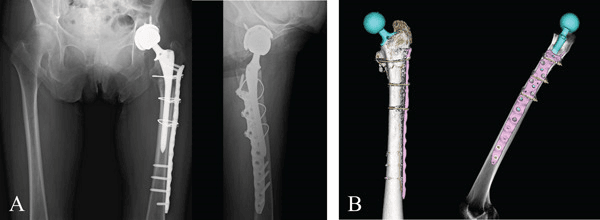
The construct. Each element is selected from the available corridors and load:
- Plate length and working length
- Locking or conventional bicortical screws
- Stem-compatible attachment plates and unicortical fixation
- Cerclage
- Orthogonal fixation and/or strut
Stress risers and alignment. Span vulnerable stem tips and adjacent implants enough to avoid a new stress concentration; no fixed two-cortical-diameter distance fits every femur. Restore length, alignment and rotation, and test the construct through the planned loading strategy.
Complications
Early. Infection, dislocation, VTE, bleeding, wound problems and nerve injury depend on host, exposure, revision burden and implants. Dual mobility or constrained bearings and cerclage are selective risk-management tools, not automatic.
Late. Nonunion or malunion, loosening, stem subsidence, refracture or stress concentration, and hardware failure should be analysed by biology, alignment, implant stability and construct, not assigned one Vancouver percentage.
Outcomes & the 'Loose Stem' Signal (National Registry)
- A loose stem was present at the time of fracture in 66% (after primary THA) and 51% (after revision)
- 88% of fractures were Vancouver type B, but radiographic preoperative subgrouping was difficult
- High failure rate: 66-month survival (reoperation as endpoint) only 74.8% (plus or minus 5.0%)
- Implant design was associated with fracture risk
Postoperative Care
Aftercare follows host and construct.
Loading. Mobilise early, with weight-bearing prescribed from stem fixation, fracture and plate stability, bone quality, soft-tissue repair and patient ability. Some constructs permit weight-bearing as tolerated and others require temporary protection.
Precautions and prophylaxis. Use hip precautions only for the surgical approach, component instability and individual dislocation risk. Select VTE prophylaxis from fracture and arthroplasty guidance, bleeding risk, renal function and local protocol rather than a universal 35 days.
Surveillance. Monitor the wound, infection, alignment, union and callus, stem subsidence or loosening, hardware and joint stability at decision-relevant intervals.
Bone health. Treat falls, nutrition, osteoporosis and its secondary causes, and rehabilitation globally. Vitamin D, calcium and drug choice and timing follow measured deficiency, renal function and bone-health guidance, not fixed targets or waiting for radiographic union.
Outcomes and Prognosis
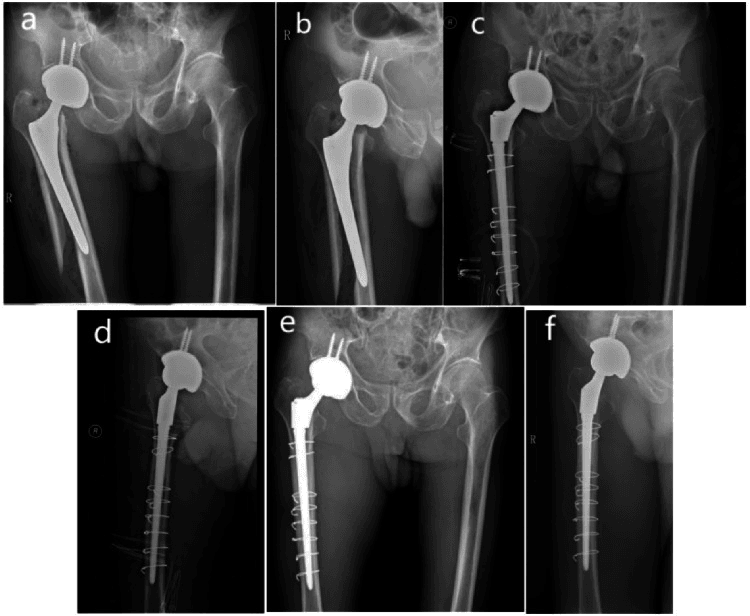
Outcome depends on frailty and comorbidity, pre-fracture mobility, infection, morphology, implant stability, bone stock, reconstructive burden, union and complications. Vancouver subtype alone does not provide a reliable union, revision or functional-return percentage.
- Favourable Features
- Stable reconstruction and viable bone
- Adverse Features
- Missed loosening, instability, malalignment or infection
- Favourable Features
- Independent baseline and early safe mobilisation
- Adverse Features
- Frailty, cognitive/medical burden and abductor loss
- Favourable Features
- Union with stable stem/component
- Adverse Features
- Nonunion, subsidence, recurrent fracture or dislocation
- Favourable Features
- Goal-directed rehabilitation and support
- Adverse Features
- Prolonged restrictions and deconditioning
Counselling. Counsel from the patient's baseline and the chosen operation. Many need aids or do not regain prior mobility, but no universal six-to-twelve-month endpoint applies.
Guidelines, Registries & Global Practice
Registries consistently identify rising fracture burden and higher risk with some uncemented stems in older/frail femora, but treatment evidence remains observational and implant-era dependent. No global guideline supplies a complete B1/B2/B3 operation table.
- Principle
- Map implant stability/design, fracture, bone, host and infection
- Resource adaptation
- Plain serial films and operative preparedness remain central
- Principle
- Fracture-specific fixation with safe corridors and stress-riser planning
- Resource adaptation
- Conventional plates/cerclage can work when advanced attachments unavailable
- Principle
- Obtain durable fixation/reconstruction with acceptable burden
- Resource adaptation
- Transfer when revision inventory/expertise cannot deliver the plan
- Principle
- Orthogeriatric, falls and secondary-fracture prevention
- Resource adaptation
- Use globally available nutrition, mobilisation and bone-health pathways
Related pages: THA Aseptic Loosening, THA Wear and Osteolysis, Revision THA, Femoral Impaction Bone Grafting, and Periprosthetic Hip Fracture.
Controversies & Areas of Uncertainty
Revision remains usual for a genuinely loose stem, but selected ORIF is reported in frail/high-risk hosts and specific cemented polished-taper/composite situations with reducible fractures. Selection is implant- and morphology-specific, not simply “unfit.”
Modular fluted tapered, monoblock, cemented/impaction and replacement options depend on intact distal bone, canal geometry, bone restoration goals and host. No stem family is universally preferred.
Plate, nail or combined fixation follows component geometry, bone, overlap and axis; an unprotected stress riser is avoidable but overlap length is not standardized.
A polished taper-slip stem may subside within an intact cement mantle by design. Determine whether interfaces/cement mantle and fracture can be restored before labelling the component loose or choosing revision.
State the usual direction, then the patient/implant/morphology evidence that could change it. Do not hide uncertainty behind a two-diameter rule.
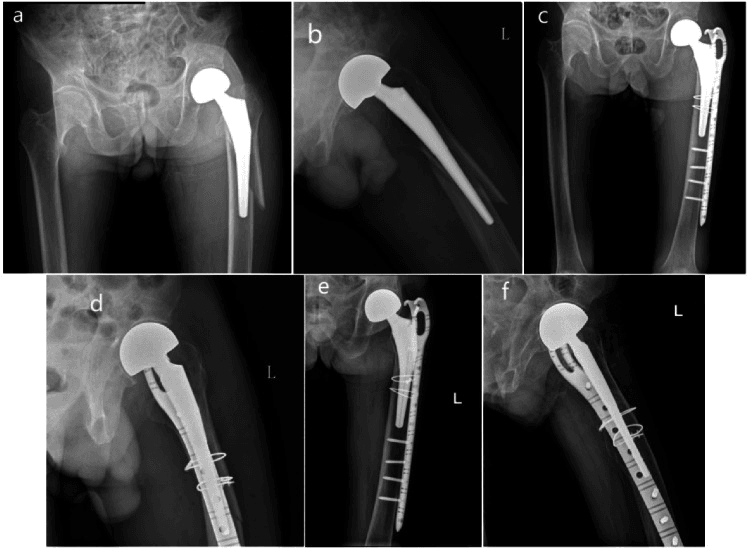
MCQ Practice Points
Q: What makes fixation fail? A: Retaining a truly unstable implant, inadequate fracture mechanics/biology, infection or malalignment can fail. “Loose stem” is important but not the only predictor, and selected B2 fixation can succeed in defined settings.
Q: What minimum bypass is required? A: No universal distance. Span the fracture, stem tip and adjacent implants enough for load transfer and fixation while avoiding a new stress concentration; use morphology, plate working length and available bone.
Q: How are fixation elements selected? A: Use bicortical screws where safe; locking attachments, unicortical screws or cerclage where the stem blocks a corridor; orthogonal fixation/strut for specific deficits. Cables are not mandatory proximally.
Q: When is infection work-up required? A: When symptoms, wound, osteolysis/loosening pattern, prior infection, markers or operative findings raise suspicion. Use aspiration and multiple tissues selectively; inflammatory markers alone neither prove nor exclude infection.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“An older patient has a Vancouver-B-pattern fracture around a longstanding THA. How do you decide whether to retain the stem?”
“A stable stem is retained. Describe construct planning.”
“A frail patient has a loose stem, major bone loss and abductor compromise. How do you choose reconstruction?”
Describe
- Location and morphology
- Stem/cup fixation and design
- Bone stock and infection
- Host physiology and baseline function
Vancouver Direction
- A: trochanteric, assess abductors/stem relevance
- B1: stable stem, usually fracture-specific fixation
- B2: loose/usable bone, usually revision with selected ORIF exceptions
- B3: loose/deficient bone, revision plus reconstruction/replacement
- C: distal, plan overlap/interprosthetic mechanics
Construct
- Restore length alignment and rotation
- Use every safe screw/attachment/cerclage corridor
- Span stress risers without a fixed distance
- Augment only a defined mechanical or biological deficit
Safety
- Prepare fixation and revision contingencies
- Target infection work-up
- Set loading from actual stability
- Address frailty falls and bone health
Evidence Base
Demographics & Implant Factors (Swedish Register)
- 1049 fractures (1979-2000); a majority of late fractures occurred around a loose stem
- Implant-related factors were significantly associated with fracture occurrence
- Treatment results were poor with low long-term survivorship and high complication rates
- Established the periprosthetic fracture burden as a rising, costly complication
Epidemiology in Revision THA
- Intraoperative fracture incidence 12% in revision THA (3x higher than primary)
- Intraoperative fractures 3x more common with uncemented stems (19% vs 6% cemented)
- 20-year probability of postoperative fracture 11%; risk similar for cemented and uncemented
- Most common postoperative type was Vancouver B1 (31%)
Mortality After Periprosthetic Femoral Fracture
- Postoperative fracture after primary THA: modestly increased death risk (HR 1.19), confined to patients with comorbid orthopaedic conditions
- Intraoperative fracture in primary THA: no excess mortality (HR 1.03)
- In revision THA, neither intra- nor post-operative fracture carried excess mortality
- 1112 intraoperative and 704 postoperative fractures analysed across 30,782 THAs
Patient-Specific Risk Calculator
- 16,696 primary THAs; 5-year patient-specific risk ranged 0.5-25% by comorbid profile
- Non-modifiable: female (HR 1.6), older age, osteoporosis (HR 1.7), non-OA indication (fracture HR 2.2)
- Modifiable: uncemented fixation (HR 2.5), collarless stem (HR 1.3), non-anterior approach (lateral HR 2.9)
- Demonstrates surgeon decisions (fixation, implant, approach) materially shift risk