Pneumatic cuff for a bloodless field | Set pressure from limb occlusion pressure | Mind the safe inflation time | Watch for nerve injury and post-tourniquet syndrome
- Purpose: a pneumatic tourniquet creates a bloodless field that improves visibility and can speed the operation. The blood-loss claim is narrower than the slogan: in the trial on this page, full-time use lowered measured intraoperative loss (about 172 versus 226 mL) but made no significant difference to total, hidden or postoperative loss, and none to transfusion rates. It buys the field, not the haemoglobin, and the blood is largely deferred rather than saved. It also does not make the operation sterile
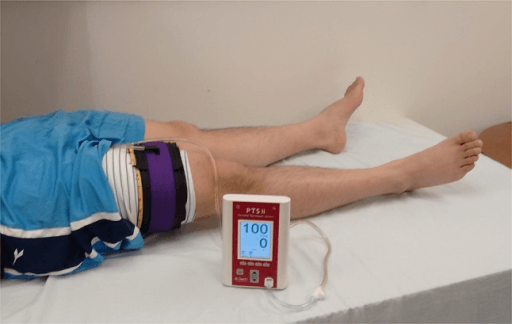
- Set the pressure to the limb, not the textbook: limb occlusion pressure (LOP) plus a safety margin gives the lowest effective pressure - lower pressure means less soft-tissue and nerve injury
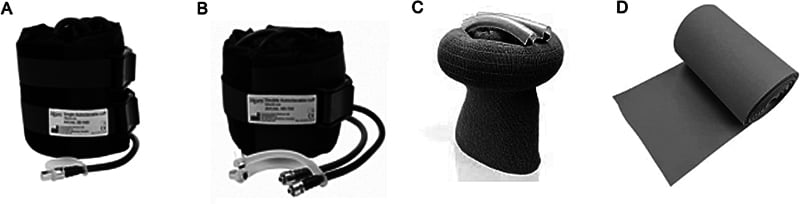
- Apply correctly: widest cuff that fits, padding underneath, over the proximal limb, exsanguinate first (elevate then Esmarch/limb roll), then inflate - and protect the skin from prep fluid pooling under the cuff
- Time matters: keep inflation as short as possible; many units plan deflation by about 2 hours and a reperfusion break before re-inflating - the longer the time, the higher the complication risk
- The headline harms: nerve injury (commonest serious problem), post-tourniquet syndrome (swollen, stiff, weak limb), skin injury, and the systemic ischaemia-reperfusion response on deflation
- “Use the WIDEST cuff that fits - a wider cuff occludes arterial flow at a LOWER pressure, reducing nerve and muscle injury
- “Document inflation pressure and total tourniquet time in the operation note every time
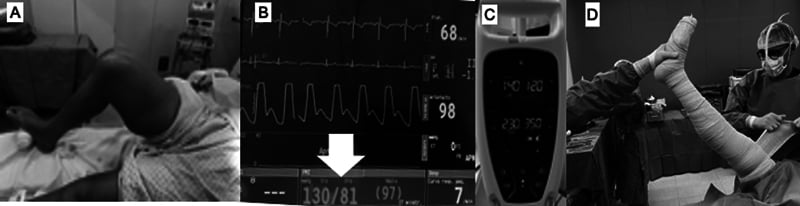
- “Warn the anaesthetist before deflation - reperfusion causes a transient fall in blood pressure and a rise in end-tidal CO2 and serum potassium
- “Avoid or think very carefully before using a tourniquet in severe peripheral arterial disease, sickle cell disease, or a limb with infection or tumour
Overview
What it is. The pneumatic tourniquet is one of the most common pieces of equipment in orthopaedic theatres: an inflatable cuff placed around the proximal limb and pumped above arterial pressure to stop blood flow, giving the surgeon a clean, bloodless field. It is used routinely for knee replacement, foot and ankle work, hand surgery and many trauma cases.
The trade. The benefit is better visibility and usually a faster operation with less blood in the wound. The cost is that the limb beyond the cuff is ischaemic for the duration, and the tissue under the cuff is squeezed hard. Almost every problem with tourniquets comes back to the two things the examiner will test, how much pressure and how long: get those right and apply the cuff properly and the device is very safe; get them wrong and you can injure nerves, muscle and skin.
Why it turns up in the viva. It links anatomy, physiology and safe practice in one device, so it is a favourite of basic-science and operative vivas alike. In knee replacement, whether to use it, for how long and at what pressure is an active debate you should be able to argue. In hand, foot and trauma surgery, cuff choice, exsanguination and time-keeping are everyday skills, and the reperfusion changes on deflation are a classic anaesthesia and physiology teaching point.
How to set a safe pressure, how to apply the cuff, when to avoid it and what can go wrong is the practical core examiners probe. It all reduces to one idea: the lowest effective pressure, the widest cuff, for the shortest time.
Principles: How a Tourniquet Works
The device. A pneumatic tourniquet is an inflatable cuff connected to a console that pumps it to a set pressure and holds it there. When cuff pressure rises above the pressure in the limb's arteries, arterial inflow stops; the cuff also compresses the veins, so blood cannot drain in or out, and the limb beyond the cuff becomes pale and bloodless.
Occlude at the lowest safe pressure. You need only enough pressure to stop arterial flow in that particular limb, and two factors decide how much that is:
- The patient's arterial pressure. A hypertensive patient needs more, which is why cuff pressure is linked to systolic blood pressure or to a measured occlusion pressure.
- The cuff and the limb. A wider cuff transmits pressure more efficiently and occludes flow at a lower set pressure. A large, conical or muscular limb needs more pressure than a thin one.
Limb occlusion pressure (LOP) is the minimum cuff pressure that stops arterial flow in that specific limb at that moment, detected by loss of a distal pulse or of a Doppler or plethysmography signal. Setting the cuff to LOP plus a safety margin gives a personalised pressure lower than the old fixed numbers, and lower pressure is safer for nerves and muscle.
- How it is set
- Measure LOP for that limb, then add a margin (often 40 to 100mmHg depending on the LOP)
- Comment
- Preferred modern method - lowest effective pressure, personalised
- How it is set
- Systolic BP plus about 100mmHg (upper limb) or 150mmHg (lower limb)
- Comment
- Common, simple rule of thumb - reasonable when LOP is not measured
- How it is set
- About 250mmHg arm, 300mmHg leg for everyone
- Comment
- Outdated - often higher than the limb actually needs
If asked for a number, lead with the principle: "I set the lowest effective pressure using limb occlusion pressure plus a safety margin, and I use the widest cuff that fits." Then you can quote the systolic-plus-margin rule as a practical fallback. Leading with a single fixed number for all patients is the dated answer.
Applying the Tourniquet Safely
A safe tourniquet is as much about technique as about the machine. Four steps make a reliable viva structure:
- Choose and position the cuff. Use the widest cuff that fits and place it on the proximal limb, the upper arm or proximal thigh, where muscle bulk cushions the nerves. A contoured cuff fits a conical thigh better than a straight one.
- Protect the skin. Apply padding or a limb-protection sleeve under the cuff, with no wrinkles, and keep skin-prep fluid from pooling beneath it.
- Exsanguinate, then inflate. Elevate the limb for a few minutes, then apply an Esmarch bandage or limb roller from distal to proximal; where squeezing must be avoided, for example with suspected infection or tumour, elevate only. Then inflate to the set pressure and start the clock.
- Record and monitor. Document the inflation pressure and start time, watch the total tourniquet time and keep the team aware of it, and warn the anaesthetist before deflation. Deflate and let the limb reperfuse before closing if needed.
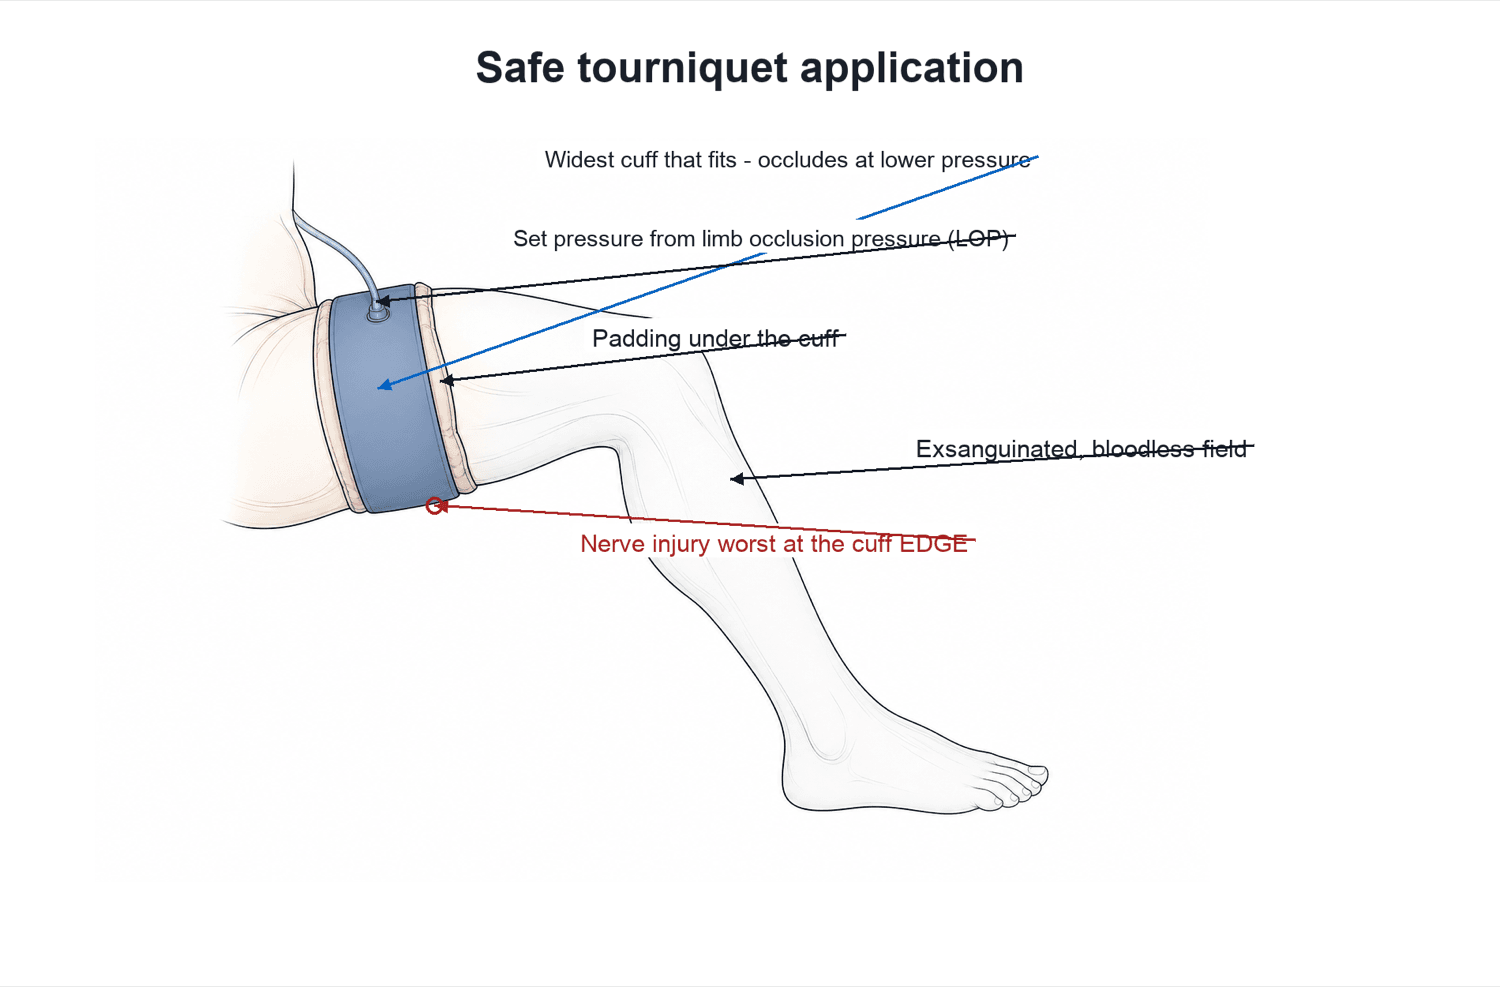
Alcoholic skin-prep fluid that runs under the cuff and is then trapped against the skin under pressure for the whole case is a classic cause of chemical burns and pressure blisters. Prevent it: pad the cuff, prevent pooling, and consider a waterproof seal at the cuff edge.
Inflation Time and the Ischaemic Limb
How long is safe. While the cuff is up, the limb beyond it has no blood supply. Tissue tolerates this for a while, because muscle and nerve can survive a period of ischaemia, but the margin shrinks with time. There is no single universally agreed maximum, but a widely used practical approach is to keep inflation as short as possible and to plan a deflation by about 2 hours. If more time is needed, the cuff is let down for a reperfusion break (commonly around 10 to 15 minutes) before re-inflating.
During inflation. The limb becomes ischaemic, acidotic and cold, and anaerobic metabolites (lactate, potassium, carbon dioxide) build up. Nerve and muscle function progressively fail, which underlies the temporary "tourniquet palsy" seen after long inflations.
At deflation. The pooled metabolites wash into the central circulation, causing a transient fall in blood pressure, a rise in end-tidal CO2, and rises in serum potassium and lactate. Blood also surges into the dilated limb, so central volume and pressure drop briefly. This is usually well tolerated in a fit patient but can be significant after a long inflation or in a frail or cardiac patient, which is exactly why you warn the anaesthetist first.
"Tourniquet time" is the total time the cuff is inflated, and it belongs in the operation note. The reperfusion changes on deflation are a favourite physiology link: tie them to the metabolites that built up in the ischaemic limb.
Contraindications and Cautions
There are few absolute contraindications, but several situations where you should think hard, choose elevation-only exsanguination, or avoid the tourniquet altogether:
- Severe peripheral arterial disease. A tourniquet can damage diseased, calcified vessels and worsen distal ischaemia. A previous vascular bypass graft in the limb is a strong reason to avoid the cuff.
- Sickle cell disease or trait. The stagnant, hypoxic, acidotic limb beyond the cuff promotes sickling. Many avoid tourniquets here; if one is used, careful exsanguination, oxygenation and minimal time are advised.
- Limb infection. Exsanguinating an infected limb risks pushing organisms into the circulation; elevation-only exsanguination is preferred if a tourniquet is needed at all.
- Limb tumour. There is a theoretical risk of squeezing tumour cells into the circulation during exsanguination, so avoid the Esmarch and use gentle elevation, or avoid the tourniquet.
Other cautions include significant venous thromboembolism risk, severe crush or vascular injury in the same limb, and very poor skin condition under the cuff.
Easy to miss. Two more are worth naming explicitly, because they are easy to miss on a ward round and awkward to explain afterwards:
- Dialysis access in that arm. An arteriovenous fistula or graft must not have a cuff inflated over or above it, because thrombosis of the access can cost the patient their dialysis route. Check both arms before you position, and mark the limb.
- Known or suspected deep vein thrombosis in the limb. Exsanguination mechanically empties the deep veins and can dislodge established clot; if a tourniquet is unavoidable, exsanguinate by elevation alone and never with an Esmarch.
VASTThink Twice (Contraindications)
Hook:A VAST list of red flags - Vascular disease, Abnormal red cells, Sepsis, Tumour - means think twice about a tourniquet.
Tourniquet for Intravenous Regional Anaesthesia (Bier Block)
Beyond the bloodless field, the tourniquet is the safety device in a Bier block (intravenous regional anaesthesia, IVRA), a technique for short distal-limb procedures, typically under about an hour: hand or forearm surgery and fracture manipulation, for example.
Technique. Step by step:
- Insert a cannula distally in the operative limb.
- Exsanguinate: elevate, then apply an Esmarch.
- Inflate a double-cuff tourniquet, proximal cuff first.
- Inject dilute local anaesthetic into the distal vein, so that it fills the venous system and anaesthetises the limb.
- When the proximal cuff becomes painful, inflate the distal cuff over the now-anaesthetised skin and release the proximal one.
The drug. Prilocaine is preferred for its low cardiotoxicity. Bupivacaine is contraindicated, being too cardiotoxic for this technique.
The danger is the cuff. The tourniquet is the only thing keeping the local anaesthetic in the limb. Premature deflation or cuff failure releases a bolus of local anaesthetic into the systemic circulation, causing local anaesthetic systemic toxicity (LAST): seizures and cardiovascular collapse.
Keep the cuff inflated for a minimum time (commonly around 20 to 30 minutes) even if the procedure finishes sooner, so the local anaesthetic becomes tissue-bound, and then deflate slowly or in cycles while watching for toxicity. Respect the maximum safe dose, and have lipid emulsion and resuscitation available.
The Emergency Haemorrhage-Control Tourniquet
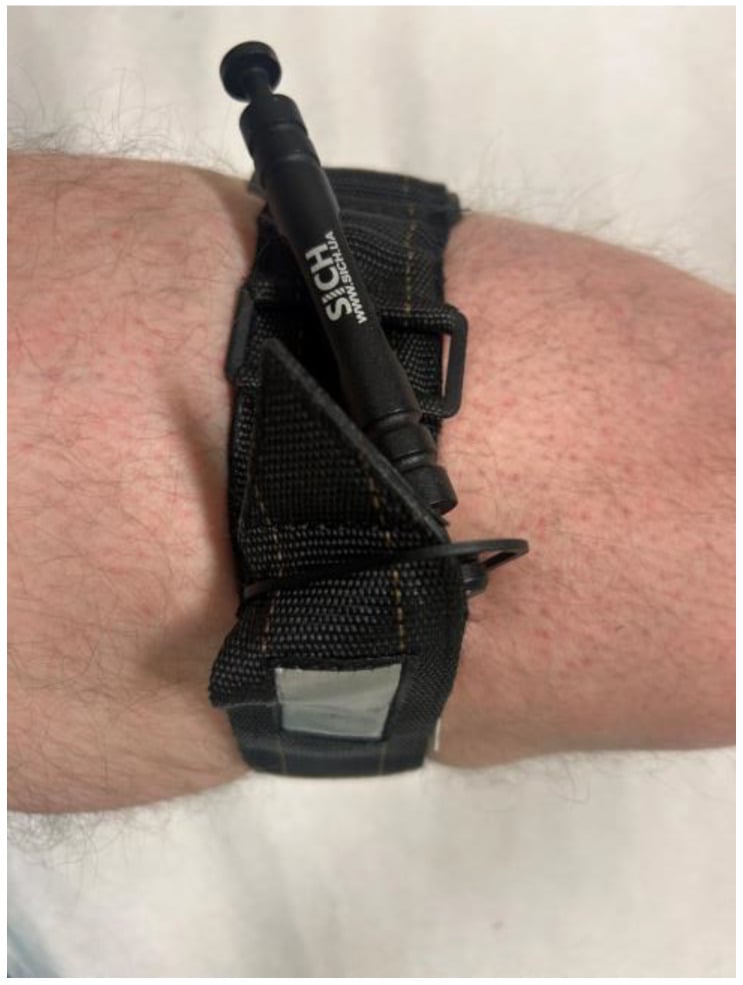
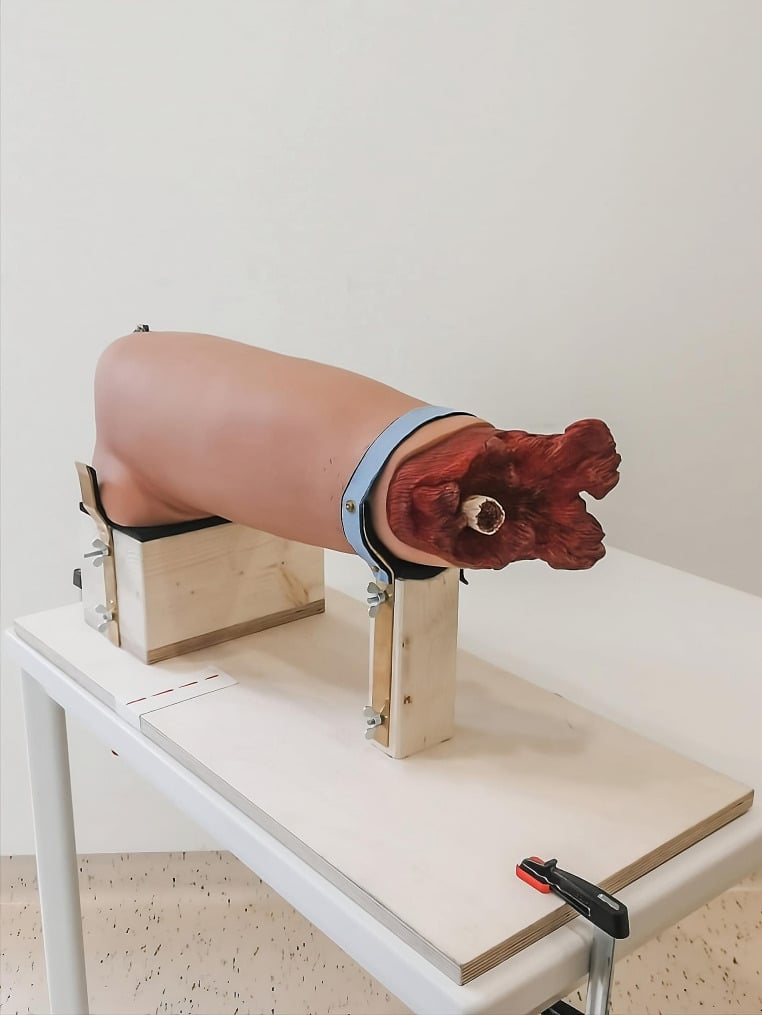
Distinct from the theatre pneumatic cuff is the pre-hospital / trauma haemorrhage-control tourniquet, used for life-threatening external limb bleeding. This is the catastrophic haemorrhage ("C") that is addressed before the airway in the trauma primary survey.
Device and application. A windlass tourniquet (for example a Combat Application Tourniquet, CAT) or a pneumatic or improvised one is applied proximal to the wound and tightened until external bleeding stops and the distal pulse is abolished. If one does not control the bleeding, apply a second tourniquet side by side.
Principles. Apply it early for exsanguinating limb haemorrhage, record the time of application, mark it clearly and hand it over explicitly. Do not periodically release it in the field, because this rebleeds and disrupts the clot. The limb tolerates ischaemia for up to about 2 hours, after which the same reperfusion and metabolic load applies on release.
Conversion. In hospital, once the patient is resuscitated and bleeding is controlled, the tourniquet is converted to definitive haemostasis by direct repair or a haemostatic dressing.
Modern military and civilian evidence shows that, used correctly, an emergency tourniquet is life-saving with an acceptable complication rate. The old fear that "a tourniquet costs the limb" should not delay control of catastrophic limb haemorrhage.

Complications
Nerve injury. This is the commonest serious complication and the one examiners chase. The crucial concept is that it is mainly mechanical, not ischaemic: the nerve is crushed under the cuff, so injury is worst at the edge of the cuff. Risk climbs with high pressure, long inflation time, a narrow cuff and a thin limb.
Which nerves, and the outlook. The vulnerable nerves are the radial nerve in the arm and the sciatic and common peroneal nerves in the lower limb. Most injuries are a neurapraxia that recovers over weeks to months, but severe or prolonged compression can cause lasting deficit. Prevention is the same theme throughout: lowest effective pressure, widest cuff, shortest time.
If a patient wakes with a wrist drop after upper-limb surgery under tourniquet, think tourniquet-related radial nerve neurapraxia from cuff compression. Document the deficit, reassure that most recover, and follow up - but always exclude a surgical cause for the nerve injury too.
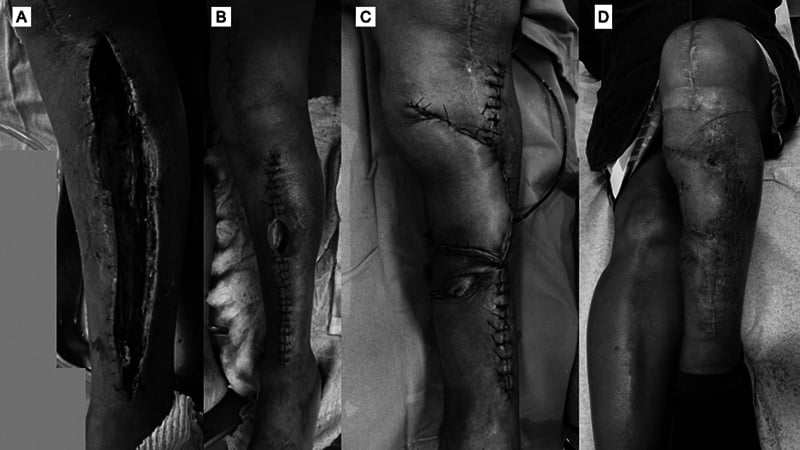
Post-tourniquet syndrome. After deflation the limb can become swollen, stiff, pale, weak and numb without an actual nerve transection. It reflects reperfusion oedema and ischaemic soft-tissue injury and is more likely after long or high-pressure inflations. It is usually self-limiting over days to weeks and is managed supportively, with elevation and time.
Other harms. Five more complete the list.
- Skin injury: chemical burns and blisters from prep fluid pooling under the cuff, or from pressure on the skin
- Reperfusion and metabolic effects at deflation, described above
- Venous thromboembolism: venous stasis distal to the cuff can promote deep vein thrombosis, and there is a higher DVT signal with tourniquet use in knee replacement
- Muscle injury: crush plus ischaemia, worse with high pressure and long time; rhabdomyolysis is rare, after very prolonged or high-pressure inflation
- Equipment failure: a wrong pressure or a leak, so check the system before use
Guidelines, Registries and Global Practice
- Lowest effective pressure is the consistent message across modern guidance (for example AORN perioperative recommendations and AAOS/specialty education): set cuff pressure from limb occlusion pressure plus a margin and use the widest cuff that fits, rather than a fixed high pressure for everyone.
- Documentation of cuff pressure and total tourniquet time in the operative record is standard safe-surgery practice worldwide.

- Knee replacement practice varies globally: some surgeons use a tourniquet for the whole case, some only for cementation, and some omit it entirely. The trend, supported by meta-analyses, is toward shorter and lower-pressure use because of the early pain, slower recovery, and higher deep vein thrombosis signal seen with full-length high-pressure inflation.
- Special populations (sickle cell disease, severe peripheral arterial disease, previous vascular bypass, limb infection or tumour) are handled cautiously everywhere, with elevation-only exsanguination or avoidance of the tourniquet depending on the situation.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are about to perform a foot operation under tourniquet on a 55-year-old man. The examiner asks how you choose the cuff and pressure and how you apply it safely.”
“A 60-year-old woman has had a 90-minute forearm operation under an upper-arm tourniquet. In recovery she cannot extend her wrist or fingers. How do you approach this?”
Purpose and Principle
- Pneumatic cuff above arterial pressure - bloodless field
- Set the LOWEST effective pressure for that limb
- Wider cuff occludes flow at a lower pressure
- Does not stop hidden (postoperative) blood loss
Setting Pressure
- Best: limb occlusion pressure (LOP) plus a safety margin
- Rule of thumb: systolic + about 100mmHg arm, 150mmHg leg
- Avoid quoting one fixed number for everyone
- Document pressure and start time every case
Safe Application
- Widest cuff on the proximal limb, padded
- Protect skin from prep-fluid pooling (chemical burn)
- Exsanguinate: elevate then Esmarch (or elevation only if infection/tumour)
- Keep time short; plan deflation by about 2 hours, reperfuse before re-inflating
Red Flags / Harms
- Nerve injury - mechanical, at the cuff edge, commonest serious harm
- Post-tourniquet syndrome - swollen, stiff, weak limb
- Warn anaesthetist before deflation (BP down, CO2, potassium, lactate up)
- Think twice: severe PAD, sickle cell, limb infection, limb tumour
Evidence: Tourniquet in Knee Replacement
Total knee arthroplasty is where tourniquet use has been studied most, because surgeons disagree about whether the bloodless field is worth the soft-tissue cost.
Tourniquet Worsens Early Pain and Function in Knee Replacement (Meta-Analysis)
- Systematic review and meta-analysis of 18 studies, 1279 total knee arthroplasties (646 with tourniquet, 633 without)
- Significantly LOWER early pain without a tourniquet, both in the first 5 days and at 1 to 3 months
- Range of motion at 2 to 3 days was significantly better without a tourniquet
- Deep vein thrombosis occurred significantly more often WITH a tourniquet; no difference in Knee Society Score, pulmonary embolism, or surgical site infection
Personalised (Limb Occlusion) Pressure Beats Uniform Pressure (Meta-Analysis of RCTs)
- Meta-analysis of 13 randomised controlled trials, 1204 total knee arthroplasties
- Personalised pressure (based on systolic BP and limb occlusion pressure) gave the same bloodless field as a uniform high pressure
- Personalised pressure produced LESS postoperative pain, less thigh swelling (circumference at 1 day, 2-3 days and discharge) and less thigh bruising (ecchymosis)
- The pain benefit is not uniform across timepoints, which bounds the claim: pain on ACTIVITY was lower at 1 day, 2-3 days and at discharge, but pain AT REST showed no difference by discharge (p = 1.0) even though it differed at 1 and 2-3 days
- Personalised pressure gave a higher early function score and better early knee range of motion
Limited Tourniquet Time Is Safe in Knee Replacement (RCT)
- Randomised controlled trial of 62 patients having primary unilateral total knee arthroplasty
- Compared a tourniquet used only during cementation versus full-time inflation throughout
- No significant difference in total or hidden blood loss, or in transfusion and perioperative complication rates
- Full-time use gave a significantly clearer surgical field and lower measured intraoperative blood loss (171.7 plus or minus 19.7 mL versus 226.3 plus or minus 50.3 mL, p = 0.001), but limited use was safe