Adductor-Related Groin Pain
- Adductor strain is the commonest cause of acute groin pain in athletes, and the adductor longus is the usual muscle, at its musculotendinous junction or proximal enthesis on the pubis.
- The mechanism is a forceful eccentric contraction during cutting, change of direction or kicking, the muscle loaded while it lengthens.
- Acute medial groin pain, tenderness at the adductor origin, and pain on resisted adduction and the squeeze test.
- The Doha agreement calls it adductor-related groin pain, one entity beside iliopsoas-, inguinal- and pubic-related and hip causes, and more than one may coexist.
- Ultrasound and MRI confirm and grade; in an adolescent, consider an apophyseal avulsion rather than a strain.
- Management is conservative, the reinjury rate is high, and progressive eccentric strengthening with a criteria-based return is what prevents it; surgery is for complete tear or avulsion or refractory cases.
- “Adductor strain = commonest acute groin injury; adductor longus the usual muscle (musculotendinous junction/enthesis); eccentric contraction during cutting/kicking.
- “Acute medial groin pain; pain on resisted adduction and the squeeze test; graded I-III; Doha 'adductor-related groin pain'. Exclude apophyseal avulsion in adolescents, osteitis pubis, sports hernia, hip pathology.
- “Conservative with a high reinjury rate - progressive eccentric strengthening (Copenhagen adduction), criteria-based return; surgery only for complete tear/avulsion or refractory cases.
Overview, Mechanism and Epidemiology
Adductor (groin) strain is the commonest cause of acute groin pain in athletes. The muscle most often injured is the adductor longus, usually at its musculotendinous junction or its proximal enthesis on the pubis.
Mechanism. A forceful eccentric contraction of the adductors, the muscle loaded while it lengthens, during cutting, change of direction, kicking, or reaching or lunging for a ball. Large eccentric contractions are known to cause or exacerbate the strain, for example in run-to-cut manoeuvres, and that is the basis for eccentric-focused prevention and rehabilitation.
Burden. Groin injuries account for a reported 4-19% of all time-loss injuries in male football, and adductor-related groin pain is the commonest subtype. The problem concentrates in the change-of-direction and kicking sports - football (soccer), ice hockey, Australian rules and handball - and in in-season play, when exposure to sprinting, cutting and kicking is highest.
The dominant modifiable risk factor is adductor weakness. A low adductor strength, and particularly a low adductor-to-abductor strength ratio, is the most consistently reported predictor of subsequent groin injury. That is why the ratio is both the screening measure and the rehabilitation target.
The strongest non-modifiable predictor is previous injury. A prior groin injury markedly raises the risk of a further one, and incomplete rehabilitation is the mechanism. Other contributors are repeatedly cited:
- Pre-season deconditioning
- Reduced hip range of motion
- Higher exposure and match load
- Core and lumbopelvic control deficits, which increase the demand on the adductors during single-leg loading
Prevention works. Adductor-strengthening programmes built around the Copenhagen adduction exercise reduce groin-injury rates at squad level, and are most effective when maintained through the season rather than performed only pre-season. Screening with hand-held dynamometry identifies the athletes to target.
Directional compression shorts can reduce adductor loading during cutting. The supporting study measured muscle activity in healthy volunteers and reported no injury outcome, so it is a plausible way to reduce adductor demand, not an injury-prevention result.
Adductor Compartment Anatomy: Why the Adductor Longus
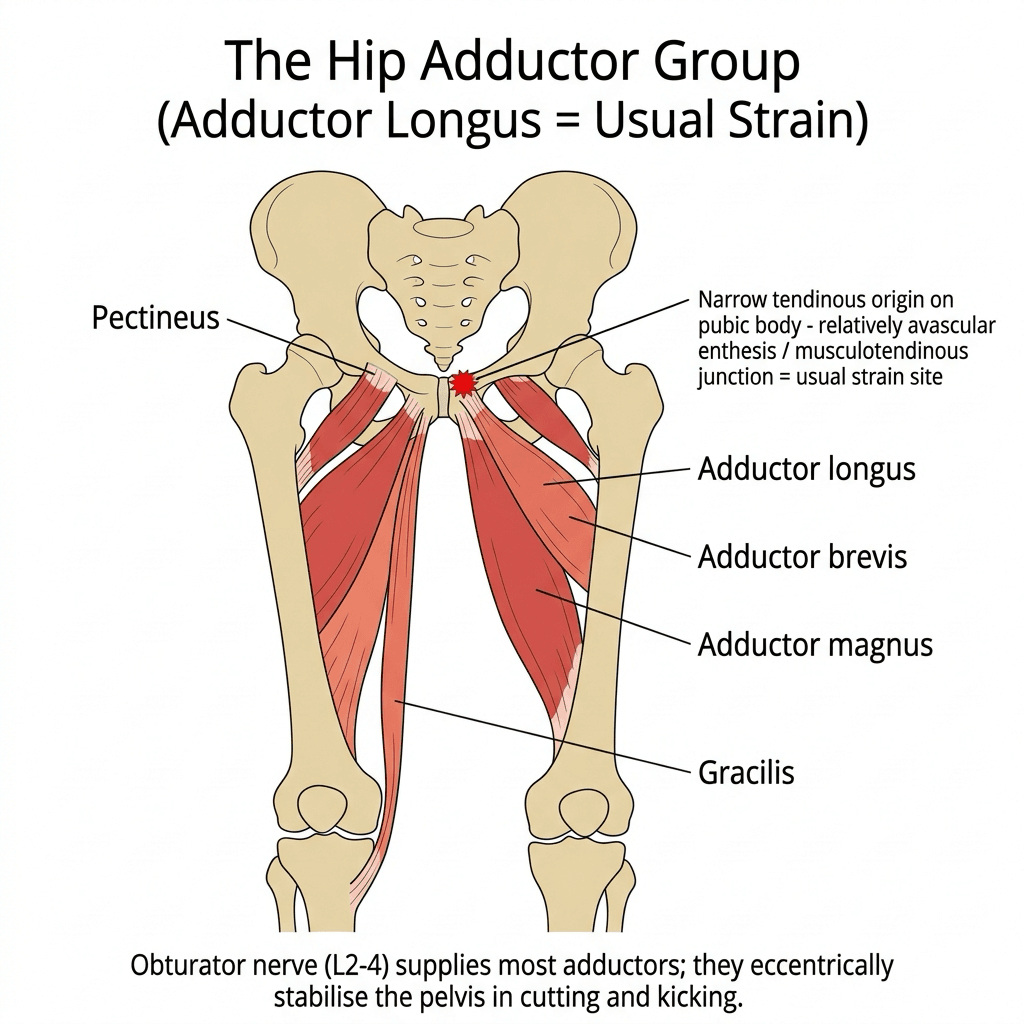
The group. The hip adductors are the adductor longus, adductor brevis, adductor magnus, gracilis and pectineus. They arise from the pubis and ischium and insert along the linea aspera, the gracilis onto the pes anserinus and the adductor magnus also to the adductor tubercle. They adduct the hip and contribute to flexion and rotation, and in sport they eccentrically control the limb and stabilise the pelvis during cutting and kicking, which is why the adductor-to-abductor balance matters in rehabilitation.
Why the adductor longus. Its proximal origin is a narrow, largely tendinous attachment to the body of the pubis, and relatively poorly vascularised. The musculotendinous junction and the pubic enthesis are therefore the weak points that fail under eccentric load, and the adductor longus is the most commonly strained adductor.
Innervation. Mostly the obturator nerve (L2-4), which supplies the adductor longus, adductor brevis, gracilis and the adductor part of the magnus. The hamstring portion of the adductor magnus is supplied by the tibial division of the sciatic nerve, and the pectineus by the femoral nerve. The nerve itself is developed in our Obturator Nerve Anatomy topic.
Classification and Grading
Two axes. The Doha agreement names the entity, adductor-related groin pain being one of its defined clinical entities (the table lists the others). It encourages a systematic approach and accepts that more than one entity may coexist. Severity and site are graded separately: at the bedside by the traditional I-III scale, and by BAMIC (an MRI grade) or the Munich consensus.
- How it grades
- I minor (pain, no weakness); II partial tear (pain plus weakness); III complete tear or avulsion
- What it adds
- Simple, bedside, still the commonest exam answer
- How it grades
- MRI grade 0-4, with a suffix for the site: a myofascial, b musculotendinous, c intratendinous
- What it adds
- The suffix matters - intratendinous (c) injuries take longer and reinjure more
- How it grades
- Separates functional (no structural lesion) from structural muscle injury, then subgrades
- What it adds
- Recognises that a painful muscle without a tear is a different problem
- How it grades
- Classifies the clinical entity: adductor-related, iliopsoas-related, inguinal-related, pubic-related, plus hip causes
- What it adds
- Frames the differential; entities frequently coexist
Clinical Presentation and Examination
History. Sudden medial groin pain during a cut, stretch, lunge or kick, often with a tearing or popping sensation, which the athlete can usually localise to the proximal medial thigh. A more insidious onset over weeks points instead to chronic adductor-related groin pain rather than an acute strain.
Inspection. Swelling and bruising track distally down the medial thigh in higher-grade injuries. Ecchymosis appearing a day or two later suggests a more substantial tear.
Palpation. Tenderness lies along the adductor longus, at the pubic enthesis, the musculotendinous junction or through the muscle belly. The site of maximal tenderness predicts the site of injury on imaging, so document it.
Provocation. Pain on active and resisted adduction and on the squeeze test, and a passive abduction stretch reproduces it. Weakness on resisted testing, rather than pain alone, suggests a higher grade. Bent-knee fall-out records range.
The squeeze test. Resisted isometric adduction against the examiner's fist, a ball, or a sphygmomanometer or dynamometer between the knees; pain or weakness reproduces adductor-related groin pain. It is classically tested in three positions, and the bent-knee position is often the most provocative:
- Legs straight, hips at 0 degrees
- Hips flexed to about 45 degrees
- Bent knees, hips at 90 degrees
Objective strength. Hand-held dynamometry quantifies adductor and abductor strength. The adductor-to-abductor ratio it measures is the risk factor above and a return-to-play criterion, which is why eccentric strengthening that rebuilds the ratio is central.
Examine the neighbours. Test hip range of motion and impingement, and examine the pubic symphysis, the inguinal canal and the abdominal wall. The Doha entities coexist, and localising the pain is what confirms the adductor-related entity; the full framework is in our Athletic Groin Pain topic.
Differential diagnosis. The conditions to exclude:
- Apophyseal avulsion in the adolescent
- Osteitis pubis
- Iliopsoas-related groin pain
- Sports hernia or inguinal disruption
- Hip-joint pathology, such as femoroacetabular impingement or a labral tear
In the skeletally immature athlete the apophysis is the weak link, so what looks like an adductor 'strain' after a forceful kick or sprint may actually be an apophyseal avulsion (e.g. of the pubic or ischial apophysis), which a plain radiograph will show. Do not assume a muscle strain in an adolescent without considering and, if needed, imaging for an avulsion.
Investigations and Their Interpretation
Most acute adductor strains need no imaging. The diagnosis is clinical; when imaging is used, ultrasound and MRI confirm and grade. Image when:
- The grade will change management
- A complete tear or avulsion is suspected
- The athlete is elite and a timeline is needed
- The presentation is atypical or failing to progress
MRI is the reference standard. It shows the site (enthesis, musculotendinous junction or muscle belly), the extent of the tear, any retraction, and the tendon involvement that drives prognosis. Oedema on fluid-sensitive sequences maps the injury, and the report should say which structure, how much of its cross-section, and whether the tendon itself is involved.
Ultrasound is quick, cheap and dynamic, and suits confirming a strain, following healing and guiding injection. It is operator-dependent, and less reliable at the pubic enthesis and for intratendinous injury.
Plain radiographs answer the bony questions: the adolescent apophyseal avulsion that mimics a strain, and the pubic changes of osteitis pubis in the chronic presentation.
A normal scan. A normal MRI in a painful groin does not end the assessment. It pushes you towards the other Doha entities, the hip joint, or a functional (non-structural) injury.
Imaging findings in the groin are common in asymptomatic athletes - pubic marrow oedema and minor adductor signal change are frequently seen in players with no symptoms. Always correlate the scan with the site of maximal tenderness and the provocation tests, or you will treat an incidental finding and miss the real source.
Management & Return to Play
Management is predominantly conservative. The reinjury rate is high, so the quality of rehabilitation, more than the passage of time, decides whether the recovery lasts.
Acute phase. Relative rest, ice and analgesia, protecting the muscle from re-loading.
Progressive eccentric strengthening. The core of rehabilitation. It restores adductor strength and the adductor-to-abductor ratio, with Copenhagen-adduction-type exercises, and reconditions the athlete for the specific demands of their sport, including cutting and change of direction.
How long. A validated reconditioning programme can return professional players to team training in about two weeks for lower-grade injuries. That series had no control group and was drawn from elite professionals, so quote it as what that programme achieved rather than as a general timeline.
Criteria-based return. Return is by criteria, not by date. The athlete returns when:
- Pain-free
- Strength is restored and the adductor-to-abductor ratio normalised
- Sport-specific function is restored
Surgery is uncommon. Complete tears and proximal avulsions are themselves uncommon, and many are managed non-operatively with good functional results, even in athletes. Repair is considered for the high-demand athlete or where retraction is substantial; the evidence does not mandate repair, so be able to argue both sides. Adductor tenotomy is occasionally considered for refractory adductor-related groin pain, after a genuine, supervised, failed rehabilitation programme.
Complications, the Chronic Case and Outcomes
Reinjury is the defining complication. It is common, and it is usually the consequence of returning before strength and function are restored.
Progression to chronic adductor-related groin pain. A strain that is inadequately rehabilitated can settle into a persistent enthesopathy at the pubic attachment, with pain on loading that limits the athlete for months. This is the group in whom tenotomy is occasionally considered.
The groin that does not settle. Before blaming the rehabilitation, ask two questions, because both change the timeline and the counselling. First, is there a second Doha entity? The entities overlap, so a persisting groin is often an unrecognised pubic-related, iliopsoas-related, inguinal-related or hip diagnosis rather than a failed adductor rehabilitation. Second, is the injury intratendinous on MRI?
Prognosis by severity. Low-grade injuries recover in weeks with a structured programme. Higher grades, and particularly intratendinous (BAMIC c) injuries, take substantially longer and carry a higher reinjury risk. An intratendinous injury does so even compared with the same numerical grade sitting at the musculotendinous junction.
Mnemonics & Memory Aids
ADDUCT
Hook:ADDUCT: Adductor longus, Direction-change mechanism, Doha entity, Use squeeze test, Consider avulsion in teens, Treat eccentrically (high reinjury).
SQUEEZE
Hook:SQUEEZE - the test that names the injury, and the checklist that manages it.
Three positions of the squeeze test
Hook:0 - 45 - 90: test all three, because a negative squeeze in one position does not exclude the diagnosis.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A soccer player develops acute medial groin pain after a cutting movement. What is the likely diagnosis and how do you assess it?”
“How would you rehabilitate an adductor strain and reduce reinjury?”
What & mechanism
- Commonest acute groin injury; adductor longus usually (musculotendinous junction/enthesis)
- Eccentric contraction during cutting/kicking/change of direction
- Sports: soccer/football, ice hockey, AFL
Assessment
- Acute medial groin pain; adductor tenderness
- Pain on resisted adduction and the squeeze test; grade I-III
- Doha 'adductor-related groin pain'; ultrasound/MRI confirm and grade
Differential
- Adolescent apophyseal avulsion (image it), osteitis pubis
- Iliopsoas, sports hernia/inguinal disruption
- Hip-joint pathology (FAI/labral tear); entities may coexist
Management
- Acute: relative rest, ice, analgesia
- Progressive eccentric strengthening (Copenhagen adduction); restore adductor:abductor ratio
- Criteria-based return (high reinjury rate); surgery only for complete tear/avulsion or refractory
Evidence & Key Studies
Validated rehab and reconditioning programme after adductor longus injury in professional soccer
- High rates of adductor injuries and reinjuries in soccer indicate that prevention and reconditioning programmes are needed to prepare athletes for the specific demands of the sport.
- An expert-validated rehabilitation and reconditioning programme, based on strengthening the injured muscle and retraining conditional capacities, aimed to reduce reinjury risk.
- Return to team training occurred at 13.08 days (SD 1.42); expert agreement on the programme's content was high, with Aiken V values of 0.77 to 0.94 across drills.
Hip adductor activation during run-to-cut manoeuvres (mechanism and load reduction)
- Athletes in sports such as hockey and soccer are at high risk of groin/adductor strains, and large eccentric contractions are known to cause or exacerbate strain injuries.
- Run-to-cut manoeuvres load the adductor longus, consistent with the eccentric/cutting mechanism of injury.
- In 29 healthy individuals performing unanticipated 45-degree run-to-cut manoeuvres, average stance-leg adductor activity on surface EMG was significantly lower wearing directional compression shorts than non-directional ones, throughout stance (all p less than 0.042).
Doha agreement: the standard terminology and definitions for groin pain in athletes
- Twenty-four international experts from 14 countries reached unanimous agreement on a standard taxonomy after systematic reviews and a Delphi process.
- Groin pain in athletes is classified under three major headings: defined clinical entities (adductor-related, iliopsoas-related, inguinal-related and pubic-related), hip-related groin pain, and other causes.
- The classification is built on history and physical examination rather than imaging, which is what makes it usable at the bedside and in research.
Adductor Strengthening Programme: players adopt it readily but do not maintain it
- Groin injuries represent 4-19% of all time-loss injuries in male football, and the Adductor Strengthening Programme is the first groin-specific prevention programme shown to reduce the risk of groin problems.
- Of 501 players surveyed from the trial cohort, 96% believed preventive measures were needed and 91% believed a strengthening programme would reduce risk; 73% completed it in under five minutes.
- Despite that, only 46% reported performing the programme as recommended and just 31% planned to continue it the following season.
The high adductor injury/reinjury rate in soccer and the value of a validated, strengthening- based rehabilitation/reconditioning programme (with return to training in about two weeks for lower-grade injuries) come from the cited Jimenez-Rubio study; the eccentric/cutting mechanism (large eccentric contractions causing/exacerbating strain, adductor longus loading during run-to-cut, and adductor-load reduction with directional compression) from the cited Chaudhari study. The adductor longus as the usual site, the squeeze test and grading, the Doha adductor-related groin-pain framework, and the differential (including adolescent apophyseal avulsion) are standard, well-established teaching. (See also our Osteitis Pubis and Pelvic Apophyseal Avulsion Fractures topics.)