Anterolateral Complex of the Knee
- The ANTEROLATERAL LIGAMENT (ALL) and the wider anterolateral complex - which includes the iliotibial band and its deep Kaplan fibre attachments to the distal femur - act as SECONDARY restraints to INTERNAL ROTATION of the tibia, controlling the anterolateral rotatory instability that is clinically detected as the PIVOT SHIFT; they work alongside the ACL, which is the primary restraint to anterior translation.
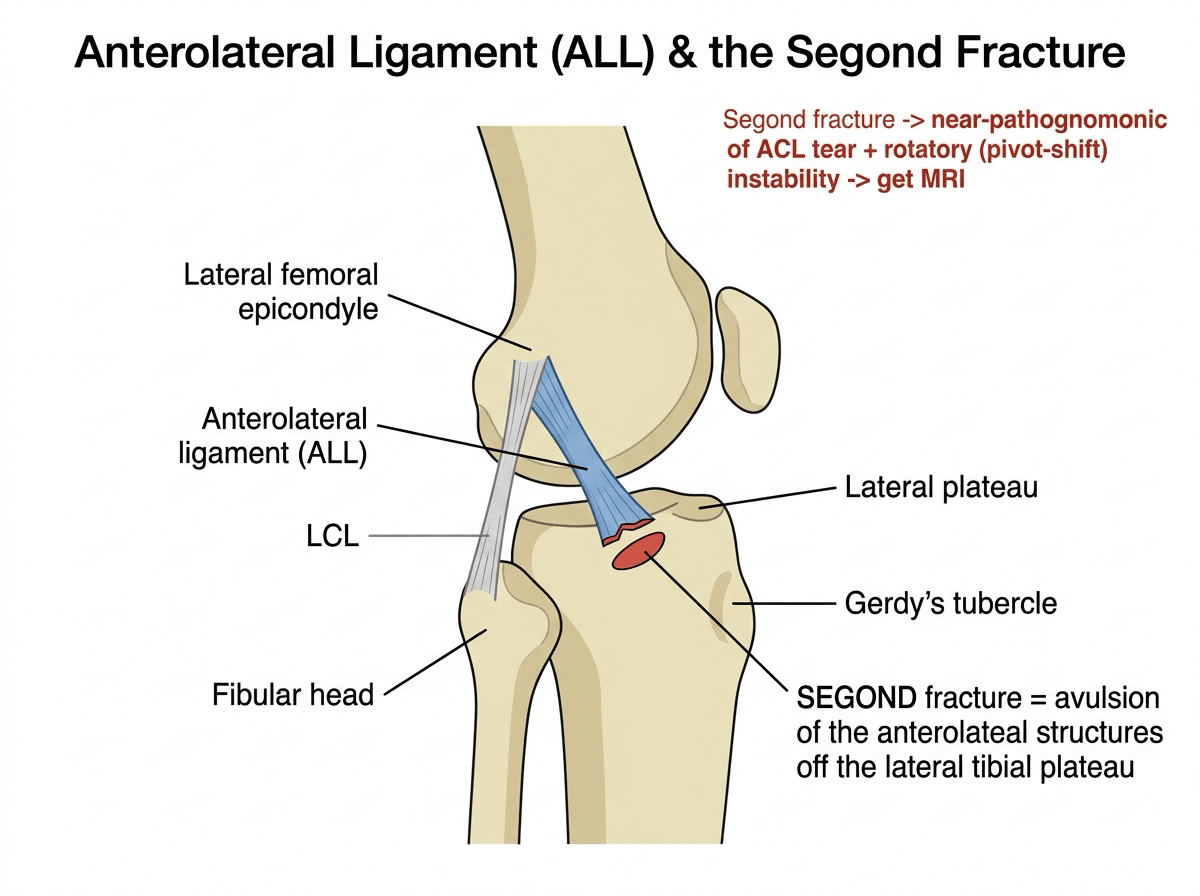
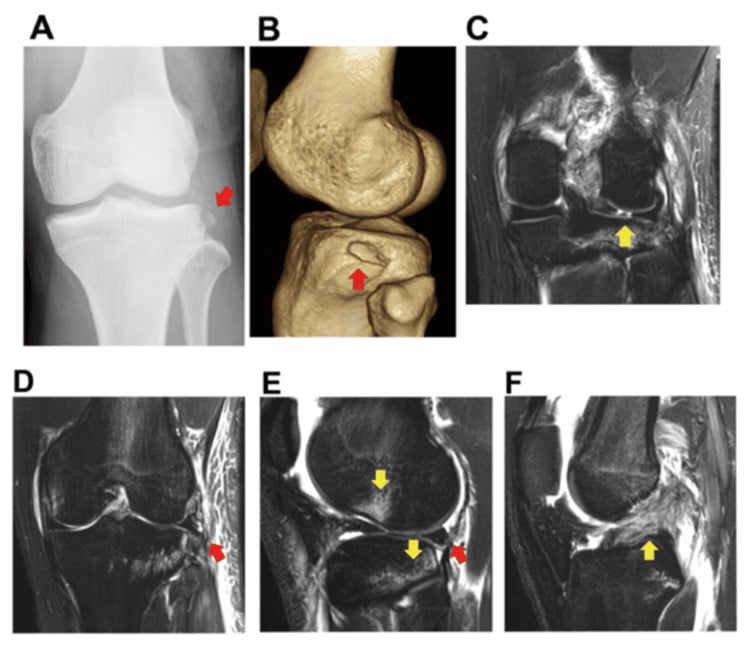
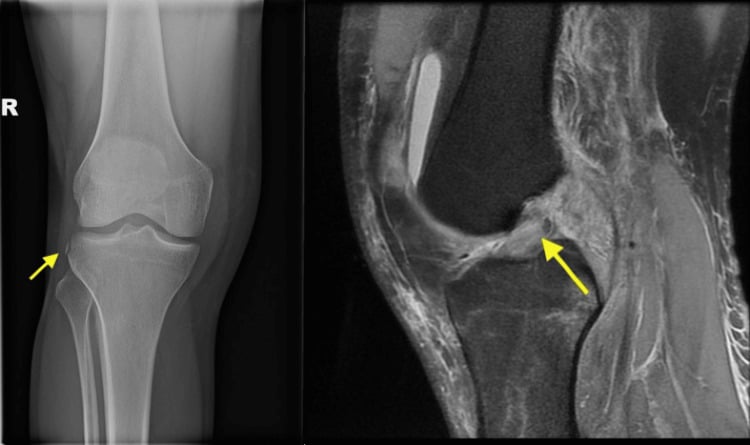
- The SEGOND FRACTURE is the radiographic signature of anterolateral injury: a small elliptical bony AVULSION off the LATERAL margin of the proximal tibial plateau (a lateral capsular/anterolateral structure avulsion), and it is near-pathognomonic of an ACL tear - so a Segond fracture on a knee radiograph should prompt MRI and careful assessment of rotatory stability.
- After ACL reconstruction, residual ANTEROLATERAL ROTATORY INSTABILITY (a persistent pivot shift) and graft failure are problems particularly in HIGH-RISK patients, which is the rationale for adding an EXTRA-ARTICULAR procedure - either a LATERAL EXTRA-ARTICULAR TENODESIS (LET) or an ANTEROLATERAL LIGAMENT RECONSTRUCTION - to the intra-articular ACL graft to better control the pivot shift.
- The INDICATIONS for adding LET/ALL reconstruction to ACLR are high-risk features: young age (under about 25), generalised LIGAMENTOUS LAXITY/hyperlaxity, a high-grade (grade 2 or greater) PIVOT SHIFT, REVISION ACL reconstruction or previous graft failure, elite athletes in CUTTING/PIVOTING sports, and an increased posterior TIBIAL SLOPE.
- The EVIDENCE is strong: in the STABILITY randomised controlled trial, adding LET to a hamstring-autograft ACL reconstruction reduced clinical failure from about 40% to 25% and graft rupture from about 11% to 4% at 2 years, with similar return-to-sport rates; meta-analyses confirm reduced graft failure and reduced postoperative anterolateral rotatory instability with the addition of an extra-articular procedure.
- TECHNIQUE (LET, modified Lemaire): a strip of the iliotibial band is harvested (left attached distally at Gerdy's tubercle), passed DEEP to the lateral collateral ligament, and fixed to the distal femur approximately proximal-and-posterior to the lateral epicondyle with the knee around 60 degrees of flexion in neutral rotation; the iliotibial band is then repaired - the downsides are reported to be minimal, though long-term osteoarthritis is being monitored.
- “Anterolateral complex (ALL + IT band/Kaplan fibres) = secondary restraint to internal rotation, and it is what controls the PIVOT SHIFT (works with the ACL).
- “SEGOND fracture = lateral tibial plateau avulsion = near-pathognomonic of ACL/anterolateral injury, so obtain MRI and assess rotatory stability.
- “Add LET (modified Lemaire) or ALL reconstruction to ACLR in HIGH-RISK patients (young, hyperlax, high-grade pivot, revision, pivoting athletes, steep slope). STABILITY trial: clinical failure 40% to 25%, graft rupture 11% to 4%.
Overview and Epidemiology
The problem it answers. Isolated intra-articular ACL reconstruction leaves a subset of knees with a residual pivot shift and a graft-rupture rate that is unacceptable in young pivoting athletes. The anterolateral complex is the structure that explains why, and augmenting it is the response.
Who fails. Failure concentrates in the following patients.
- The young, particularly under 25
- Those with generalised ligamentous laxity or hyperextension
- Revision reconstructions
- Soft-tissue (hamstring) grafts
- A high posterior tibial slope
- Athletes returning to cutting and pivoting sport
Not a new idea. Extra-articular tenodesis was widely performed in the 1970s-80s, then largely abandoned when arthroscopic intra-articular reconstruction matured. It has returned as a selective adjunct on the back of Level I evidence, a useful historical arc for a viva.
The Segond fracture is the visible epidemiological marker. It is uncommon, but when present it is near-pathognomonic of ACL rupture and signals anterolateral injury.
Anatomy: the ALL and the 'Is It a Ligament?' Debate
The anterolateral complex is the anterolateral ligament (ALL) together with the iliotibial band and its deep Kaplan fibres. What it restrains, and how its loss shows up clinically, is taken up under Pathophysiology.
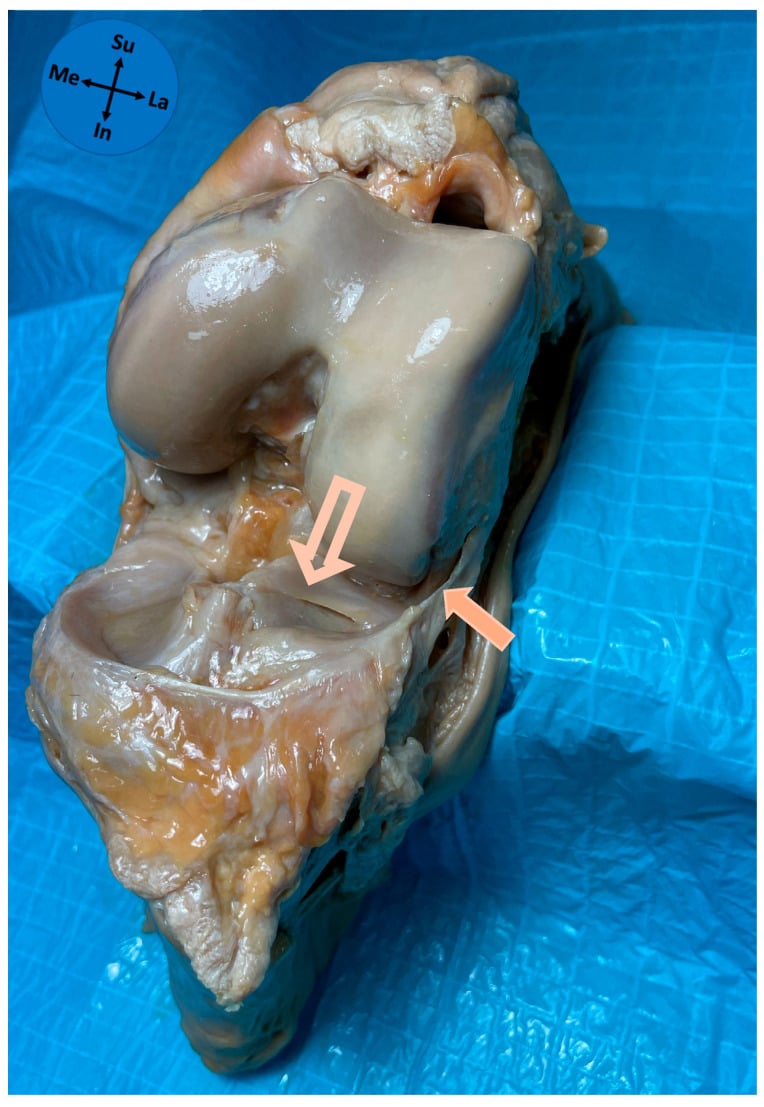
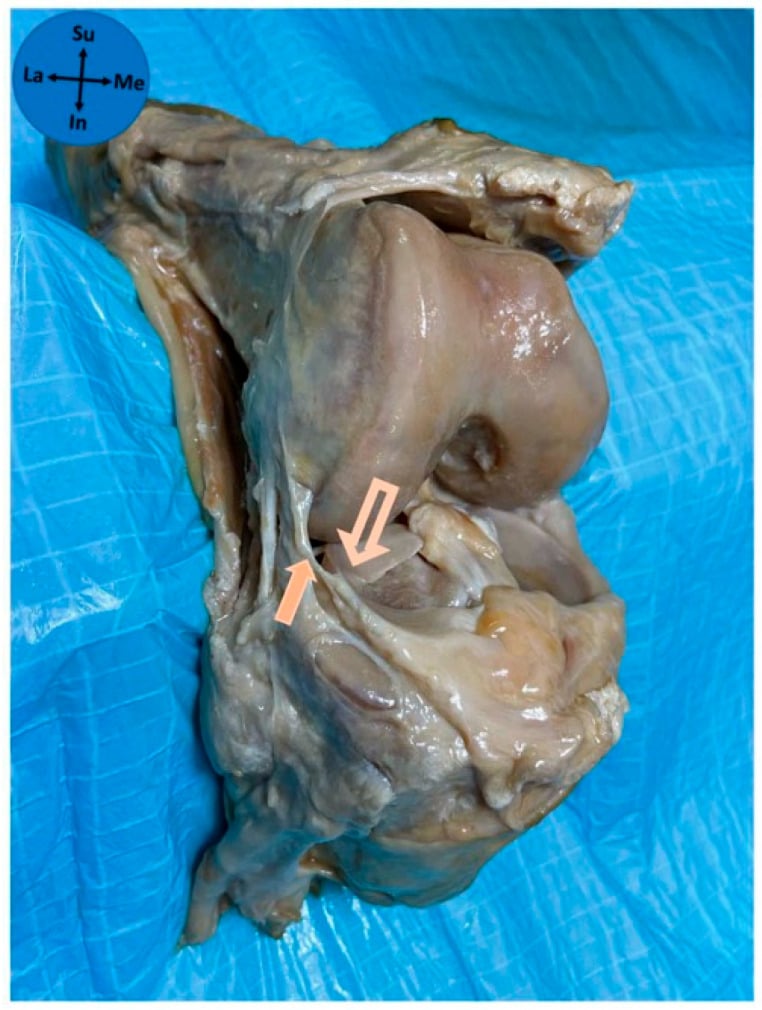
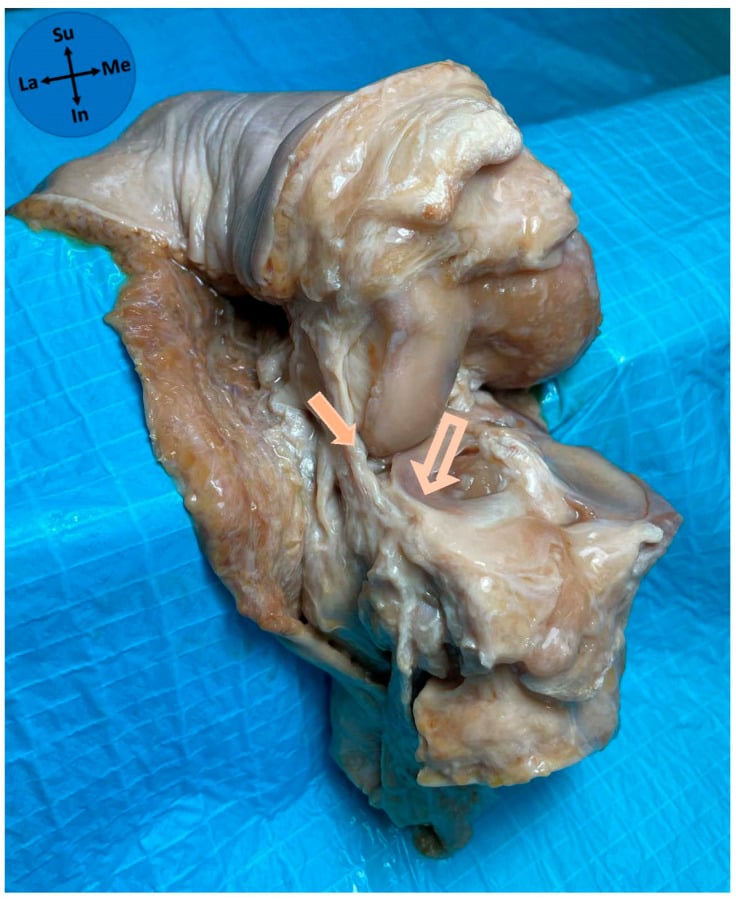
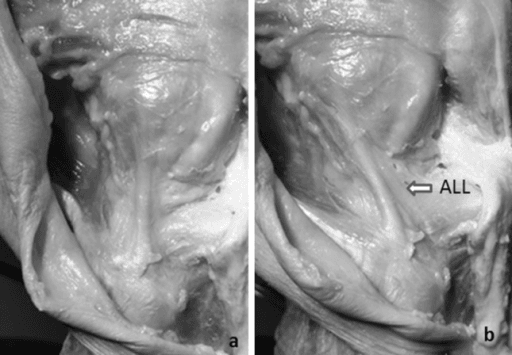
The course of the ALL. It arises from the lateral femoral epicondyle region, near the IT-band/Kaplan-fibre attachment, and runs anterodistally, with an attachment to the periphery of the lateral meniscus in many descriptions. It inserts on the anterolateral proximal tibia roughly midway between Gerdy's tubercle and the fibular head, about 5 to 10 mm below the joint line.
The femoral origin is not described consistently. The account above places it just proximal-and-posterior to the LCL origin. Claes, in the cadaveric study carded under Evidence, placed it at the prominence of the lateral femoral epicondyle, slightly anterior to the LCL origin.
The Segond site. The tibial insertion is precisely the Segond avulsion site, so the Segond fragment is the bony avulsion of this insertion. The fracture itself is covered in our Segond Fractures topic, and its radiographic significance under Investigations below.
The Kaplan fibres are the deep IT-band attachments to the distal lateral (supracondylar) femur. They are a key anterolateral rotatory restraint that complements the ALL, and the anatomical reason an IT-band-based LET (modified Lemaire) works.
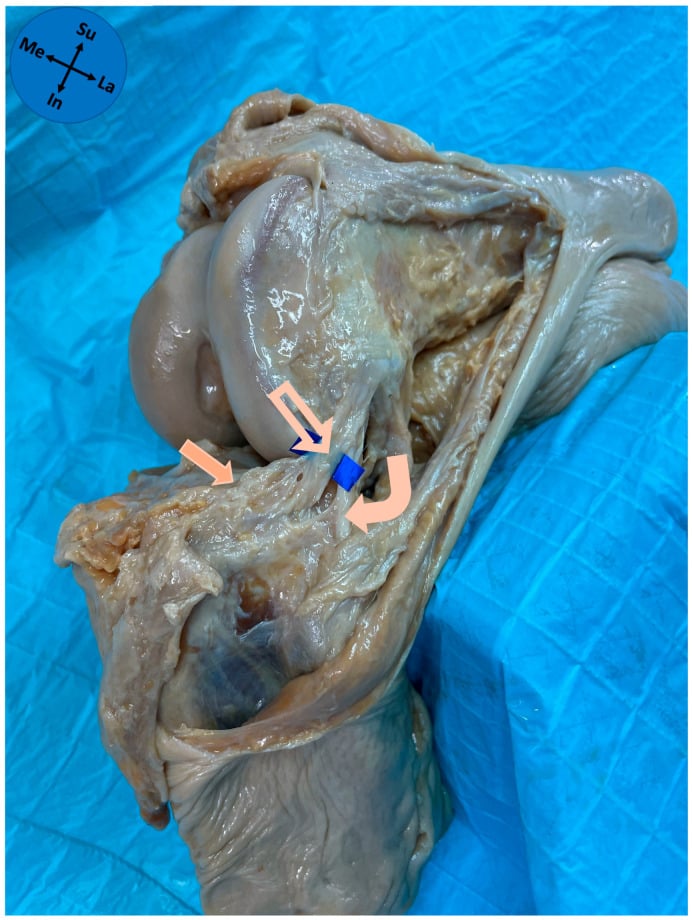
Is it a ligament? Whether the ALL is a discrete, consistent ligament or merely a thickening of the anterolateral capsule is still debated, because it is variably identified in cadaver and imaging studies. That is why the term "anterolateral complex" is often preferred, and why surgeons may choose an IT-band tenodesis over an "anatomic ALL reconstruction".
Even the meniscal attachment varies. Dissections show full-thickness, bipolar and inferior patterns of ALL attachment to the lateral meniscus. In the full-thickness pattern the ligament fibres merge through the meniscal height rather than remaining a purely capsular band; in the bipolar pattern, superior and inferior fibre bundles contact the lateral meniscus. That variability helps explain the inconsistent descriptions across dissections and MRI studies, and supports the safer clinical term.
Pathophysiology
The mechanism is the ACL mechanism. The anterolateral structures are injured in the same event as the ACL tear, a valgus, internally rotated, decelerating pivot. They are loaded in internal rotation, so they fail alongside the ACL rather than in isolation.
What is lost. The ACL is the primary restraint to anterior translation; the anterolateral complex is a secondary restraint to internal rotation. Sectioning studies show the ALL and Kaplan fibres contribute little to translation but meaningfully to internal rotation control, especially at higher flexion angles.
Why that produces a pivot shift. With the ACL gone, the lateral plateau subluxes anteriorly in extension. If the anterolateral restraints are also incompetent, nothing limits that rotation, so the reduction as the knee flexes becomes the palpable clunk rather than a smooth glide.
Why an intra-articular graft may not fix it. A central graft resists translation well but has a short lever arm for rotation. An extra-articular tenodesis sits far lateral, giving a long lever arm, which is the biomechanical reason it controls rotation so effectively, and also why over-tensioning it over-constrains.
Clinical Presentation
History. The ACL history is a pivoting or decelerating injury, a pop, immediate haemarthrosis and giving way. What points specifically to anterolateral involvement is rotational giving way: instability on turning, cutting or pivoting rather than on straight-line activity, often with a poor response to rehabilitation alone.
Examination. Lachman and anterior drawer confirm ACL deficiency. The pivot shift grades the rotatory component and is the number that drives the decision; compare with the contralateral knee and grade both.
Look for the risk phenotype, because it changes the operation.
- Generalised laxity (Beighton score)
- Knee hyperextension/recurvatum
- A history of contralateral ACL injury
The chronic ACL-deficient knee. Symptomatic rotatory instability despite rehabilitation is itself an indication to consider an anterolateral procedure at reconstruction.
The Pivot-Shift Test: Performing and Grading It
The pivot shift is the clinical correlate of anterolateral rotatory instability and the metric that selects a knee for an extra-articular augment, so it has to be elicited and graded properly. The wider knee-ligament examination is covered in our ACL Injuries topic.
Performing it. With the knee in extension, apply a valgus force and internal rotation with a gentle axial load, then slowly flex the knee. In a positive test the lateral tibial plateau, held subluxed anterolaterally in extension by the deficient ACL, reduces with a palpable or visible clunk at around 20 to 30 degrees of flexion, as the iliotibial band converts from an extensor to a flexor and pulls the plateau back. The Jerk test is the same phenomenon elicited from flexion into extension.
Grading it. The IKDC grading runs as follows.
- Grade 0: none, symmetrical with the other side
- Grade 1: a smooth glide
- Grade 2: a clunk
- Grade 3: gross subluxation with transient locking/impingement
Examine under anaesthesia where possible. Guarding abolishes a subtle shift in the awake patient, which is why examination under anaesthesia remains the most reliable assessment of the pivot shift. A high-grade shift (grade 2 or greater) is the feature that selects a knee for an added extra-articular procedure; how that sits with the 2025 consensus is set out under Management.
Investigations
Plain radiographs. Look specifically for the Segond fracture on the AP view, a small elliptical avulsion off the lateral tibial plateau margin. Its presence means ACL rupture until proven otherwise, and it should prompt MRI and assessment of rotatory stability.
Posterior tibial slope. Measure it on a true lateral, because a slope above roughly 12 degrees is one of the recognised risk factors for graft failure.
MRI. It confirms the ACL tear and shows the associated injuries: the bone bruise pattern, meniscal tears, a ramp lesion and posterolateral corner injury. Report the anterolateral complex rather than claiming a discrete ALL tear.
The ALL is inconsistently visualised on MRI, and it is variably identified even in cadaveric dissection, so MRI cannot reliably confirm or exclude an "ALL tear": a normal-looking ALL does not exclude anterolateral injury. That uncertainty is precisely why the anatomical debate persists. Do not let imaging overrule the examination. The decision to add an extra-articular procedure is driven by the pivot-shift grade and the patient's risk profile, not by an MRI report.
Quantified pivot shift. Accelerometer or image-analysis methods exist largely as a research tool. They are worth naming as an attempt to make a subjective grade objective, but they are not routine practice.
Management
Non-operative management is for the ACL injury as a whole, not for the anterolateral complex in isolation. A genuinely isolated anterolateral injury is rare and does not require reconstruction on its own.
Why augment. After ACL reconstruction, residual anterolateral rotatory instability (a persistent pivot shift) and graft failure are problems particularly in high-risk patients. Adding an extra-articular procedure, either a lateral extra-articular tenodesis (LET) or an ALL reconstruction, to the intra-articular graft is meant to control the pivot shift better.
The key modern lesson in ACL surgery is that, in high-risk knees, controlling the anterolateral rotatory instability is as important as restoring anterior translation. In these patients an isolated intra-articular ACL graft, especially a soft-tissue graft, is more likely to fail. Avoid an isolated soft-tissue graft here and add an extra-articular procedure, LET or ALL reconstruction. A Segond fracture is a useful flag that the anterolateral complex is involved.
The indications. Those cited alongside the STABILITY data are the high-risk features: young age (under about 25), generalised ligamentous laxity, a high-grade (grade 2 or greater) pivot shift, revision ACLR or previous graft failure, elite cutting/pivoting athletes, and increased posterior tibial slope.
The 2025 international consensus. It reached strong agreement (at or above 90%) that a lateral extra-articular procedure should be added at primary ACL reconstruction for:
- A grade 3 pivot shift
- Knee hyperextension
- Revision ACL reconstruction
- Return to pivoting sport
- Active patients 25 or under receiving a non-hamstring graft
- A grade 3 Lachman
- Multiple relative risk factors coexisting
It reached consensus (75-89.9%) for skeletally immature patients, chronic symptomatic ACL deficiency, posterior tibial slope above 12 degrees, and a history of contralateral ACL injury.
Reconciling the two lists. The indications above take a grade 2 or greater pivot shift; the consensus reached strong agreement for a grade 3 pivot shift, and for multiple relative risk factors coexisting. The consensus is framed around risk factors precisely because the benefit is concentrated in high-risk knees, so do not apply the augment indiscriminately.
If asked "who gets a LET?", answer with the risk profile, not a single number, and say explicitly that coexisting risk factors strengthen the indication.
The choice of augment. An iliotibial-band-based LET (modified Lemaire) and an anatomic ALL reconstruction are both used, and comparative evidence has not established clear superiority. The pragmatic argument for LET is that it uses local tissue and does not depend on the ALL being a discrete structure.
The modified Lemaire LET, step by step:
- Harvest a strip of iliotibial band, left attached distally at Gerdy's tubercle.
- Pass it deep to the LCL.
- Fix it to the distal femur approximately proximal-and-posterior to the lateral epicondyle, with the knee at around 60 degrees of flexion in neutral rotation.
- Repair the iliotibial band.
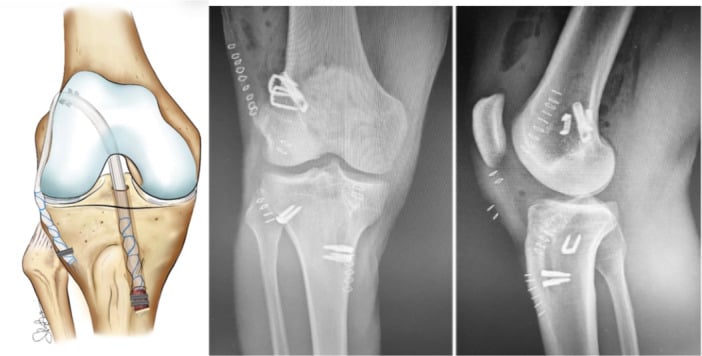
The evidence. In the STABILITY randomised trial, adding LET to a hamstring-autograft ACL reconstruction reduced clinical failure from about 40% to 25% and graft rupture from about 11% to 4% at 2 years, with similar return-to-sport rates. Meta-analyses confirm reduced graft failure and reduced postoperative anterolateral rotatory instability with an added extra-articular procedure. The downsides of LET appear minimal, but long-term osteoarthritis should be monitored (see Complications).
Complications
Over-constraint of the lateral compartment. This is the theoretical concern: fixing the tenodesis too tight, or in internal rotation, restricts rotation and could raise lateral compartment contact pressure. Fix in neutral rotation at the angle given above, and avoid over-tensioning.
Lateral compartment osteoarthritis. This is the long-term worry that follows from over-constraint, and the main reason the augment is reserved for high-risk knees. Longer follow-up is still needed.
Adverse events were not increased in trial data. The STABILITY randomised trial reported no increase in adverse events with LET augmentation, a reassuring and frequently examined finding.
Local problems include lateral knee pain and irritation over the fixation, IT-band donor-site morbidity or Gerdy's tubercle discomfort, haematoma, and hardware prominence requiring removal.
Neurovascular risk. The dissection passes near the lateral inferior geniculate vessels, and distally the common peroneal nerve must be respected. Passing the graft deep to the LCL is a technical step with its own risk.
Stiffness and loss of terminal extension are the risk if the construct is over-tensioned or rehabilitation is delayed.
Mnemonics & Memory Aids
PIVOT
Hook:PIVOT: Pivot shift target, Internal rotation restraint, Very high-risk indications, Outcomes improved (STABILITY), Tenodesis/ALLR (Segond flag).
Pivot shift grades: 0-1-2-3
Hook:Glide, Clunk, Gross - and it is the CLUNK (grade 2) where the operation changes.
RISKY knee - who gets a LET
Hook:RISKY: the coexistence of these factors strengthens the indication more than any single one.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“What is the anterolateral complex of the knee, and what is a Segond fracture?”
“When would you add a lateral extra-articular tenodesis to an ACL reconstruction, and what does the evidence show?”
Anatomy & function
- Anterolateral complex = ALL + IT band/Kaplan fibres
- Secondary restraint to internal rotation, and what controls the pivot shift
- Works with the ACL (primary restraint to anterior translation)
Segond fracture
- Small avulsion off the lateral tibial plateau margin
- Near-pathognomonic of an ACL tear / anterolateral injury
- Prompt MRI and assessment of rotatory stability
Indications to augment ACLR
- Young (under ~25), generalised ligamentous laxity
- High-grade (grade 2+) pivot shift; revision/graft failure
- Elite cutting/pivoting athletes; increased posterior tibial slope
LET & evidence
- Modified Lemaire: IT-band strip deep to LCL, fixed proximal-posterior to lateral epicondyle (~60 deg, neutral rotation)
- ALL reconstruction is an alternative extra-articular augment
- STABILITY RCT: clinical failure 40% to 25%, graft rupture 11% to 4%; monitor long-term OA
Evidence & Key Studies
Anatomy of the anterolateral ligament of the knee
- In 41 cadaveric knees the anterolateral ligament (Segond's 1879 'pearly, resistant fibrous band') was found as a well-defined ligamentous structure, clearly distinguishable from the anterolateral capsule, in 97% of specimens
- Origin at the prominence of the lateral femoral epicondyle (slightly anterior to the LCL origin); oblique course with firm lateral-meniscus attachments; insertion on the anterolateral tibia midway between Gerdy's tubercle and the fibular head - the Segond avulsion site
- By virtue of its structure and location, the ALL is hypothesised to control internal tibial rotation and thereby the pivot-shift phenomenon
The anterolateral ligament (ALL) and its role in rotational extra-articular stability of the knee joint: a review of anatomy and surgical concepts
- Reviews the long history of the ALL under its various names (mid-third lateral capsular ligament, capsulo-osseous layer of the iliotibial band) before its 2013 rediscovery by Claes
- The structure acts as a limiter of internal rotation and lateral meniscal extrusion, and contributes to the pivot-shift phenomenon
- Anatomic variance underlies why the term 'anterolateral complex' is often preferred and why concomitant anterolateral stabilization with ACL reconstruction may prevent residual instability
Lateral extra-articular tenodesis as an adjunct to ACL reconstruction (indications, technique, STABILITY data)
- LET supplements internal rotational stability and reduces the pivot shift; indications include age under 25, increased posterior tibial slope, ligamentous laxity, elite cutting/pivoting athletes, grade 2 or greater pivot shift, and prior ACL graft failure.
- In the STABILITY randomised controlled trial, adding LET to hamstring-autograft ACLR reduced 2-year clinical failure from 40% to 25% and graft rupture from 11% to 4%, with a similar return-to-sport rate.
- A meta-analysis of ACLR versus ACLR plus LET reported reduced graft failure and reduced postoperative anterolateral rotatory instability.
Editorial Commentary: graft choice and lateral extra-articular tenodesis in ACL reconstruction
- Outcomes of ACL reconstruction were historically disappointing in high-risk populations (generalised ligament laxity, pivoting athletes) with low return-to-sport rates, incomplete restoration of rotatory stability and relatively high osteoarthritis rates.
- A renewed focus on extra-articular procedures (anterolateral ligament reconstruction and lateral extra-articular tenodesis) and avoiding isolated soft-tissue grafts in high-risk patients has significantly improved outcomes.
- Indications for extra-articular procedures have expanded with apparently minimal downsides, though long-term osteoarthritis should be monitored.
The anterolateral-complex anatomy, its discrete-ligament status and the Segond-site insertion come from the Claes 2013 cadaveric description; the internal-rotation/pivot-shift function and the "is it a discrete ligament" debate come from the Roessler 2016 review. The role of LET (supplementing internal rotational stability/reducing pivot shift), its indications, the STABILITY-trial outcomes (clinical failure 40% to 25%, graft rupture 11% to 4%) and the supporting meta-analysis come from the cited McGovern article; the improvement in high-risk ACLR outcomes with extra-articular procedures (ALL reconstruction/LET), the avoidance of isolated soft-tissue grafts in high-risk patients and the need to monitor long-term osteoarthritis from the cited van der List commentary. The pivot-shift mechanism is standard, well-established teaching. (See also our ACL Reconstruction and Pivot Shift / Knee Examination topics.)