Balance Thrombosis Risk | Balance Bleeding Risk | Evidence-Based Protocols
- Warfarin: stop 5 days preop, bridge if high thrombosis risk (mechanical valve, recent VTE)
- DOACs: stop 24h if CrCl greater than 50, 48h if CrCl less than 50
- Neuraxial anaesthesia: 12h after LMWH prophylactic, 24h after therapeutic
- Restart anticoagulation 24-72h postop depending on bleeding risk
- Use current guideline tables for evidence-based cessation/restart protocols
- “Bridging with LMWH/UFH only for HIGH thrombosis risk patients (mechanical valve, recent VTE less than 3mo)
- “Most patients do NOT need bridging - BRIDGE trial showed bridging increases bleeding without preventing thrombosis
- “DOACs easier than warfarin - predictable offset, no bridging needed
- “Neuraxial timing critical - spinal haematoma is catastrophic complication
Overview and Clinical Significance
Who is anticoagulated. Atrial fibrillation is the most common indication met in orthopaedic practice. The others are mechanical heart valves, treatment or prophylaxis of venous thromboembolism, and stroke prevention. Patients with coronary stents are on antiplatelet agents, which are a separate problem and have their own section below.
Why it matters. Anticoagulation that continues through surgery brings bleeding; anticoagulation stopped for too long brings thrombosis, and the balance between the two is patient-specific. Major surgery needs the INR normalised, and neuraxial anaesthesia is contraindicated while the patient is coagulopathic.
The BRIDGE trial (2015) changed practice. Bridging AF patients with LMWH increased bleeding (3.2% vs 1.3%) without reducing thrombosis. Most patients do not need bridging: bridge only at high thrombosis risk (mechanical mitral valve, recent VTE under 3 months).
Pathophysiology and Risk Stratification
Assess thrombosis risk first. The bridging decision follows from it: only high-risk patients need a bridge, and most orthopaedic patients are at low-to-moderate thrombosis risk and do not.
- Clinical Features
- Mechanical MITRAL valve, VTE less than 3mo, stroke less than 3mo, AF CHA2DS2-VASc 5 or more, prior stroke or VTE while on therapeutic anticoagulation, severe thrombophilia
- Annual Risk
- Greater than 10%
- Periop Management
- BRIDGE with LMWH or UFH
- Clinical Features
- Mechanical AORTIC valve, VTE 3-12mo ago, AF CHA2DS2-VASc 3-4, active cancer
- Annual Risk
- 5-10%
- Periop Management
- Consider bridging, individualise
- Clinical Features
- AF CHA2DS2-VASc 0-2, VTE greater than 12mo, bioprosthetic valve, low-risk thrombophilia
- Annual Risk
- Less than 5%
- Periop Management
- NO bridging - stop AC, restart postop
AF Thrombosis Risk (CHA2DS2-VASc Score)
The score adds one point for each of the following, and two for age 75 or over and for prior stroke, TIA or thromboembolism:
- Congestive heart failure (1 point)
- Hypertension (1)
- Age 75 or over (2)
- Diabetes (1)
- Stroke, TIA or thromboembolism (2)
- Vascular disease (1)
- Age 65-74 (1)
- Female sex (1)
- Risk
- Low
- Bridging Decision
- NO bridging
- Risk
- Moderate
- Bridging Decision
- Consider bridging if additional risks
- Risk
- High
- Bridging Decision
- Bridge with LMWH
Classification
By mechanism. The classes, their examples, how they act and how long they last:
- Examples
- Warfarin
- Mechanism
- Inhibits factors II, VII, IX, X
- Half-life
- 36-42 hours
- Examples
- Dabigatran
- Mechanism
- Direct factor IIa inhibition
- Half-life
- 12-17 hours
- Examples
- Rivaroxaban, Apixaban
- Mechanism
- Direct factor Xa inhibition
- Half-life
- 8-15 hours
- Examples
- Enoxaparin, UFH
- Mechanism
- AT-III mediated
- Half-life
- 4-7 hours (LMWH)
- Examples
- Aspirin, Clopidogrel
- Mechanism
- Platelet inhibition
- Half-life
- Variable
The DOACs as a class. Their shorter half-life allows faster cessation, and renal clearance varies between the agents. There is no reliable reversal agent for all of them.
By procedure. Procedures can also be classified by their bleeding risk, with a hold duration attached to each tier:
- Examples
- Carpal tunnel, trigger finger
- Anticoagulation Strategy
- Continue or hold 24 hours
- Examples
- Knee arthroscopy, hardware removal
- Anticoagulation Strategy
- Hold DOACs 24-48 hours
- Examples
- Hip/knee TJA, spinal without fusion
- Anticoagulation Strategy
- Hold 48-72 hours, consider bridging
- Examples
- Spinal fusion, pelvic surgery, revision TJA
- Anticoagulation Strategy
- Hold 5+ days, bridging if high risk
Read the hold column against the agent: the 24-48 hour holds are DOAC intervals and the 5-plus days is warfarin's. The restart intervals elsewhere on this page use the three-tier grading in Clinical Assessment and Bleeding Risk.
Clinical Assessment and Bleeding Risk
Grade the procedure. Bleeding risk is graded by the operation, and the grade sets how far anticoagulation is interrupted and when it restarts.
- Orthopaedic Procedures
- Arthroscopy, carpal tunnel, trigger finger, K-wire removal
- Management
- Minimal interruption, restart 6-12h
- Orthopaedic Procedures
- THA, TKA, ORIF, shoulder arthroplasty, fracture fixation
- Management
- Stop AC preop, restart 24-48h postop
- Orthopaedic Procedures
- Spine surgery, revision THA/TKA, pelvic ORIF, tumour resection
- Management
- Extended cessation, restart 48-72h postop
What else affects the grade. At the bottom of the scale, minimal-risk procedures such as carpal tunnel or trigger finger release can often proceed with anticoagulation continued or held for 24 hours. A planned neuraxial anaesthetic raises the risk category. The other factors that bear on it are a compartment at risk (the spine, the pelvis), revision surgery with adhesions, and concurrent antiplatelet therapy.
Neuraxial anaesthesia is high bleeding risk. A spinal or epidural is treated as a high-bleeding-risk procedure because the consequence of a spinal haematoma, paralysis, is catastrophic. That grading is what sets the timing of cessation and restart around a block.
Investigations and Monitoring
Before surgery. The tests follow the drug:
- INR on warfarin
- Creatinine and eGFR on a DOAC, because renal function determines the cessation timing
- Platelet count on heparin, with HIT screening if indicated
- Coagulation studies (PT, APTT) if there is a bleeding concern
- Blood group and crossmatch for major procedures
Use current institutional protocols alongside ASRA, ACCP/CHEST, ESC/EHRA, NICE and other national guidance for cessation, restart and neuraxial-timing decisions. In smaller or remote centres, specific DOAC reversal agents (idarucizumab, andexanet alfa) and prothrombin complex concentrate may not be held on site - factor this into emergency planning.
Differential of Unexpected Perioperative Bleeding / Coagulopathy
When a patient bleeds more than expected or has an abnormal coagulation screen, distinguish residual anticoagulant from other causes before attributing it to the agent alone.
- Discriminating Feature
- Recent VKA, INR raised
- Typical Screen
- INR/PT prolonged, APTT normal-to-raised
- Action
- Vitamin K +/- PCC; recheck INR
- Discriminating Feature
- Recent dose, reduced CrCl, dabigatran
- Typical Screen
- Variable; raised APTT (dabigatran) or anti-Xa
- Action
- Time/renal clearance; specific reversal if life-threatening
- Discriminating Feature
- Recent dose, raised anti-Xa
- Typical Screen
- APTT prolonged (UFH); anti-Xa raised
- Action
- Protamine (full for UFH, partial for LMWH)
- Discriminating Feature
- Stigmata of chronic liver disease, low albumin
- Typical Screen
- INR raised, low platelets
- Action
- Vitamin K, FFP/PCC, treat cause
- Discriminating Feature
- Massive transfusion, sepsis, trauma
- Typical Screen
- Low fibrinogen, low platelets, raised D-dimer
- Action
- Treat cause; targeted blood products, fibrinogen
- Discriminating Feature
- Lifelong/familial bleeding history
- Typical Screen
- Prolonged APTT, abnormal factor/vWF assays
- Action
- Haematology; factor concentrate/desmopressin
Management Algorithm
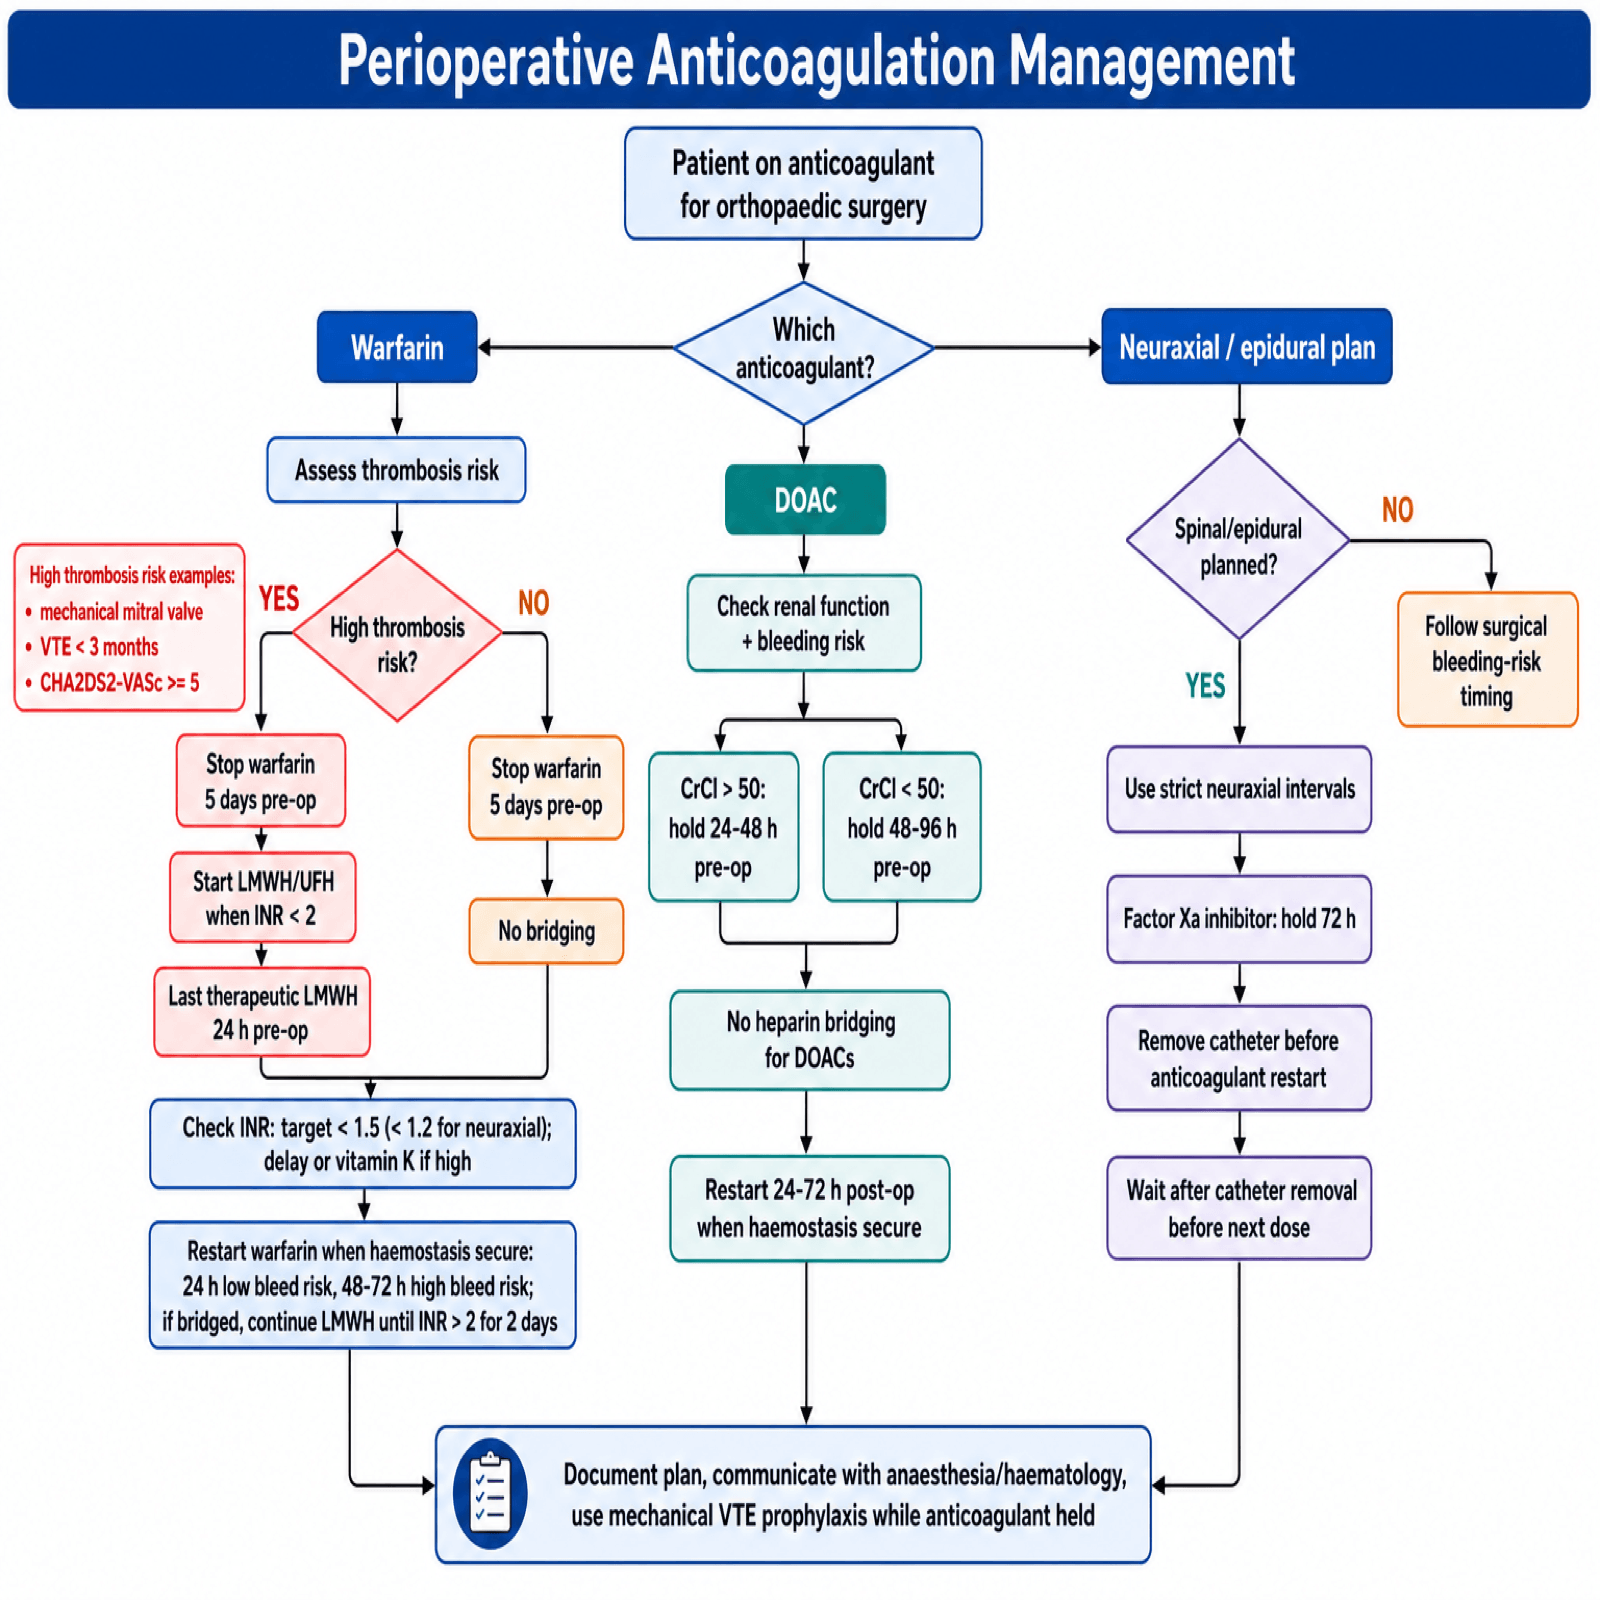
The shape of the decision. Warfarin takes days to wear off and may need a bridge while it does; a DOAC is stopped by a pharmacokinetic rule and is never bridged. The thrombosis risk decides the bridge, the bleeding risk decides the restart.
Warfarin Perioperative Management
Warfarin Perioperative Protocol
Stop warfarin 5 days before surgery. The INR normalises to less than 1.5 by the day of surgery in most patients; check it the day before to confirm.
At high thrombosis risk, start therapeutic LMWH or a UFH infusion once the INR falls below 2, usually day 3 after the last warfarin dose. The doses and the last-dose timing are in the Bridging Protocol tab.
Confirm the INR is less than 1.5, and ideally less than 1.2 if a neuraxial block is planned. If it is over 1.5, delay, or give vitamin K 1-2mg orally.
Restart once haemostasis is secure: 24h after low-bleeding-risk surgery, 48-72h after high-bleeding-risk surgery.
- Stop Before Surgery
- 5 days preop
- Restart After Surgery
- 24-72h postop
- Bridge?
- NO - do not bridge
- Stop Before Surgery
- 5 days preop + LMWH bridge
- Restart After Surgery
- LMWH 24h postop, warfarin overlap
- Bridge?
- YES - mechanical valve, recent VTE
- Stop Before Surgery
- 24-48h preop
- Restart After Surgery
- 24-72h postop
- Bridge?
- NO - never bridge DOACs
- Stop Before Surgery
- 48-96h preop (longer)
- Restart After Surgery
- 24-72h postop
- Bridge?
- NO - never bridge DOACs
- Stop Before Surgery
- 12h before neuraxial
- Restart After Surgery
- Restart 6-12h postop
- Bridge?
- N/A - this IS prophylaxis
Direct Oral Anticoagulant (DOAC) Management
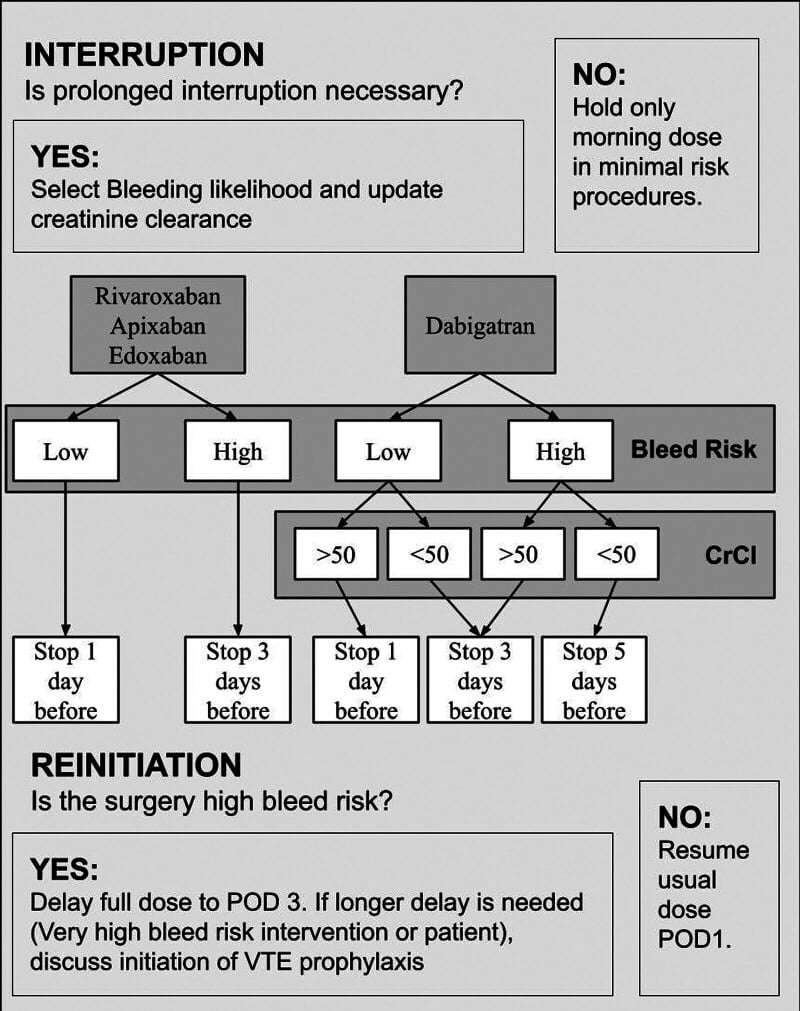
Why DOACs are simpler. Predictable pharmacokinetics, no INR monitoring, rapid offset and no bridging. The one variable that changes the plan is renal function.
Before surgery. Calculate the creatinine clearance (Cockcroft-Gault) rather than assume it; older patients have a lower CrCl. With CrCl over 50, stop the drug 24h before low-bleeding-risk surgery and 48h before high-bleeding-risk surgery. Below 50 the interval lengthens, as in the table, and dabigatran needs the longest.
- CrCl greater than 50
- 24-48h preop
- CrCl 30-50
- 48h preop
- CrCl less than 30
- 48-72h preop
- CrCl greater than 50
- 24-48h preop
- CrCl 30-50
- 48h preop
- CrCl less than 30
- 48-72h preop
- CrCl greater than 50
- 24-48h preop
- CrCl 30-50
- 72h preop
- CrCl less than 30
- 96h preop (4 days)
- CrCl greater than 50
- 24-48h preop
- CrCl 30-50
- 48h preop
- CrCl less than 30
- 48-72h preop
If CrCl is under 50, stop dabigatran 72-96h (3-4 days) before surgery. Check renal function in every patient on dabigatran; apixaban and rivaroxaban are less renal-dependent.
Renal handling of each agent. Dabigatran is 80% renally excreted and is contraindicated when CrCl is under 30; rivaroxaban is 33% and apixaban 27% renally eliminated. Warfarin has minimal renal elimination and needs no dose adjustment, though the INR is monitored closely. LMWH is renally cleared: avoid it when CrCl is under 30, or use UFH.
After surgery. Restart at the full therapeutic dose, with no loading, once haemostasis is secure, at the interval set by the procedure's bleeding-risk category.
Antiplatelet Agents and Coronary Stents
Antiplatelet management is a distinct, high-yield problem from anticoagulant management, and getting the coronary-stent patient wrong can be fatal.
Perioperative Antiplatelet Cessation
- Stop before surgery
- Usually CONTINUE
- Before neuraxial (ASRA)
- Not a contraindication alone
- Note
- Modest bleeding increase; stop only for very-high-risk (intracranial/some spine) or per cardiology
- Stop before surgery
- 5-7 days
- Before neuraxial (ASRA)
- 5-7 days
- Note
- Irreversible P2Y12 inhibitor
- Stop before surgery
- 3-5 days
- Before neuraxial (ASRA)
- 5-7 days
- Note
- Reversible but potent
- Stop before surgery
- 7 days
- Before neuraxial (ASRA)
- 7-10 days
- Note
- Most potent; longest interval
Coronary Stents and Dual Antiplatelet Therapy (DAPT)
A patient with a recent coronary stent on DAPT (aspirin plus a P2Y12 inhibitor) is at risk of catastrophic, often fatal stent thrombosis if the antiplatelets are stopped too early. Elective surgery is deferred through the mandatory DAPT period:
- Bare-metal stent (BMS) - at least 6 weeks (ideally longer)
- Drug-eluting stent (DES) - ideally 6 months; a newer-generation DES a minimum of about 3 months (absolute minimum about 1 month) only for time-sensitive surgery, after cardiology discussion
If surgery cannot wait, continue aspirin throughout wherever possible and stop only the P2Y12 inhibitor, with a clear cardiology-agreed plan to restart it as soon as haemostasis allows. Never interrupt both agents in the high-risk window without multidisciplinary (cardiology) input.
Heparin-Induced Thrombocytopenia (HIT)
HIT is a critical complication of the very heparins used to bridge and to prophylax, and it is prothrombotic, not a bleeding problem.
Mechanism. Immune IgG antibodies against the platelet factor 4 (PF4)-heparin complex activate platelets, causing thrombosis and a falling platelet count.
Timing. The platelet count falls, typically by over 50% from baseline, at days 5-10 after heparin exposure, or within hours if there has been recent prior exposure. It is more common with UFH than with LMWH.
The paradox. Despite the thrombocytopenia the danger is arterial and venous thrombosis, not bleeding: limb ischaemia, DVT and PE, stroke.
Diagnosis. Estimate the probability with the 4Ts score (Thrombocytopenia magnitude, Timing, Thrombosis, oTher causes excluded), then confirm with a PF4 ELISA and a functional assay (serotonin-release assay).
Management. Stop all heparin, including LMWH, line flushes and heparin-bonded catheters, and start a non-heparin anticoagulant (argatroban, danaparoid, fondaparinux, or a DOAC). Do not transfuse platelets, and do not start warfarin until the platelet count recovers: warfarin in acute HIT risks venous limb gangrene.
Neuraxial Anaesthesia and Anticoagulation
Why the intervals exist. The complication these rules prevent is spinal epidural haematoma, which causes irreversible paralysis; its recognition and the decompression window are under Complications. The intervals below are the ASRA 4th edition (2018) figures.
- BEFORE Neuraxial (Wait Time)
- 12 hours
- AFTER Neuraxial / Catheter (Restart)
- 4h after needle/catheter (catheter OK)
- BEFORE Neuraxial (Wait Time)
- 24 hours
- AFTER Neuraxial / Catheter (Restart)
- 24h after block; no indwelling catheter
- BEFORE Neuraxial (Wait Time)
- 4-6 hours (or normal APTT)
- AFTER Neuraxial / Catheter (Restart)
- 1 hour
- BEFORE Neuraxial (Wait Time)
- INR less than or equal to 1.4
- AFTER Neuraxial / Catheter (Restart)
- Restart once catheter removed
- BEFORE Neuraxial (Wait Time)
- 72 hours
- AFTER Neuraxial / Catheter (Restart)
- 6 hours after catheter removal
- BEFORE Neuraxial (Wait Time)
- 72-120 hours (renal dependent)
- AFTER Neuraxial / Catheter (Restart)
- 6 hours after catheter removal
The DOAC interval that makes surgery safe (PAUSE: 1-2 days) is shorter than the interval ASRA requires for a neuraxial block (72h for factor Xa inhibitors). When a spinal or epidural is planned, the ASRA neuraxial interval governs - this is a classic exam discriminator.
The indwelling catheter. With an epidural catheter in place, anticoagulation is held until after the catheter is out. Wait 12h after a prophylactic LMWH dose and 24h after a therapeutic dose before removing it, then 4h after removal before the next LMWH dose.
Surgical Technique
Pre-operative Assessment
Confirm the anticoagulation status. Document the date and time of the last dose, check the INR on warfarin or drug levels on a DOAC if they are available, review renal function for DOAC clearance, and confirm the bridging plan if there is one.
Before the day. Check that:
- Anticoagulation held per protocol
- Bridging LMWH stopped at the planned interval
- Platelet function normal if on aspirin or clopidogrel
- Group and screen current
- Plan discussed with anaesthesia if a neuraxial block is intended
On the day. Confirm the patient is fasted and the anticoagulant held, recheck the INR in warfarin patients, and make sure the consent covers the bleeding risks.
Complications and Special Situations
Emergency Surgery on Anticoagulation
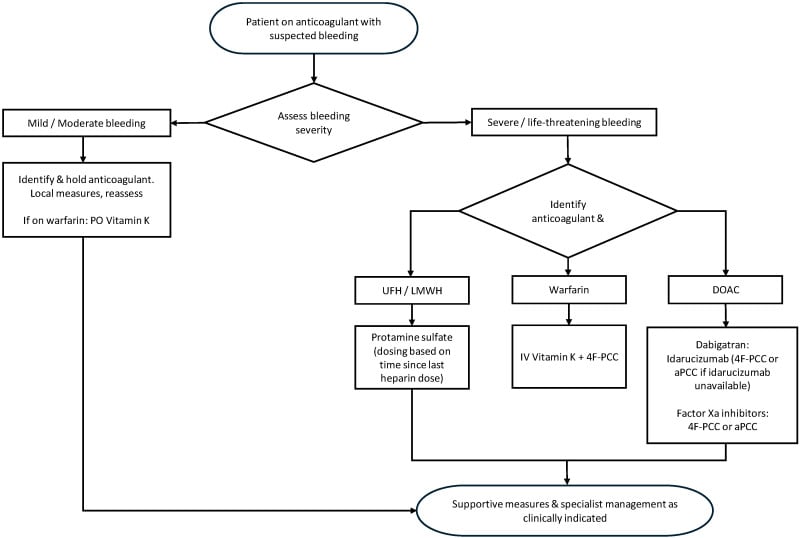
The patient needs urgent surgery and is anticoagulated. Reversal is specific to the agent:
Emergency Reversal Protocol
Vitamin K 5-10mg IV (onset 6-12h) plus prothrombin complex concentrate (PCC) 25-50 units/kg for immediate reversal. Check the INR 30 minutes after PCC.
Consider idarucizumab for dabigatran or andexanet alfa for a factor Xa inhibitor; both are expensive and of limited availability. Surgery may be delayed 12-24h if possible.
Protamine sulfate reverses heparin, 1mg per 100 units of UFH, and only partially reverses LMWH. Wait 4-6h if possible.
The balance. The bleeding risk of operating is weighed against the thrombosis risk of reversing, and the case is discussed with haematology.
The Anticoagulated Hip Fracture - a Time Target, Not an Emergency Reversal
The commonest version of this problem in orthopaedics is not a bleeding emergency but a clock. Hip fracture surgery is targeted within 36 to 48 hours because delay increases mortality, and an anticoagulant is one of the commonest avoidable reasons that target is missed: the patient is admitted, the drug is noted, and everyone waits for it to wear off.
Waiting is the error. The approach differs from true emergency reversal above:
- Warfarin - reverse early and deliberately with vitamin K so the INR falls in time to operate within the target, rather than watching the INR drift down over days. Reserve PCC for a genuine emergency or when the operation cannot wait for vitamin K to work. Restart warfarin once haemostasis is secure.
- DOACs - stop, and time surgery to the drug, the last dose and the renal function, typically 24 to 48 hours. Specific reversal (idarucizumab, andexanet alfa) is for the case that truly cannot wait, not for routine scheduling.
- Aspirin and clopidogrel - generally do not stop, and do not delay for them. Manage bleeding with tranexamic acid and, rarely, platelet transfusion.
- Do not bridge with LMWH when surgery is early and anticoagulation will be restarted promptly: bridging adds bleeding risk without closing a meaningful thrombotic gap.
Involve haematology and anaesthesia early for the complex case, and confirm both the renal function and the indication for anticoagulation, since a mechanical valve or recent VTE changes the calculus entirely.
Postoperative Care
Anticoagulation Restart Timing
The decision. The interval is set by the procedure's bleeding-risk category; within it, the restart is judged on the adequacy of haemostasis (drain output, the wound), the thrombotic risk against the bleeding risk, the timing of neuraxial catheter removal, and haematology input for the complex case. In the very highest-risk settings, intracranial surgery among them, the restart is delayed and individualised. Warfarin takes days to take effect once it is restarted.
Outcomes
Bleeding Outcomes
- Major Bleeding Risk
- 3-5%
- Major Bleeding Risk
- 1-2%
- Major Bleeding Risk
- 1-2%
- Major Bleeding Risk
- 5-10%
Major bleeding is defined by any of:
- Hb drop of 20 g/L or more
- Transfusion of 2 units or more
- Bleeding at a critical site
- Reoperation for bleeding
- Fatal bleeding
Who bleeds. Inadequate drug cessation, renal impairment with DOAC accumulation, concurrent antiplatelet therapy, and complex or revision surgery.
Guidelines, Registries & Global Practice
Atrial fibrillation affects an estimated 50+ million people worldwide and prevalence rises sharply with age; roughly 1 in 6 patients presenting for elective surgery is on long-term anticoagulant or antiplatelet therapy. With ageing arthroplasty and fragility-fracture populations, the orthopaedic surgeon manages perioperative anticoagulation almost daily, and DOACs have now overtaken warfarin as the most prescribed oral anticoagulant in most high-income health systems.
- Region
- North America / Global
- Key Position
- No bridging for most AF; selective bridging only for highest thrombotic risk; standardised DOAC interruption
- Evidence Level
- Guideline (GRADE)
- Region
- North America / Global
- Key Position
- Defines neuraxial intervals: 72h for factor Xa inhibitors, 12h/24h for prophylactic/therapeutic LMWH
- Evidence Level
- Guideline
- Region
- Europe
- Key Position
- DOAC interruption by bleeding risk and renal function; bridging discouraged in AF
- Evidence Level
- Guideline
- Region
- UK
- Key Position
- DOAC-led stroke prevention in AF; perioperative VTE prophylaxis for major orthopaedic surgery
- Evidence Level
- Guideline
- Region
- Australia / NZ
- Key Position
- PK-based DOAC interruption tables; ANZCA neuraxial timing aligned with ASRA
- Evidence Level
- Guideline
- Type
- RCT, n=1884
- Practice Point
- Forgoing bridging non-inferior for ATE, halves major bleeding in AF
- Type
- Prospective cohort, n=3007
- Practice Point
- Standardised 1-2 day DOAC interruption without bridging is safe
- Type
- RCT, n=1471
- Practice Point
- No benefit of postoperative LMWH bridging, including mechanical valves
- Type
- Registry
- Practice Point
- Track VTE, reoperation for haematoma and bleeding-related revision after TJA
Despite concordant guidelines, real-world bridging rates vary widely between centres and countries (historically 10-40% of warfarin patients), reflecting clinician risk perception rather than evidence. The consistent message across AAOS-aligned practice, NICE, ESC/EHRA, ACCP and eTG is: bridge rarely, interrupt DOACs by a simple PK rule, and let renal function and the neuraxial plan drive timing.
MCQ Practice Points
Q: How many days before elective surgery should warfarin be stopped? A: 5 days. Warfarin half-life is 36-42 hours. Stopping 5 days preop allows INR to normalize to less than 1.5 in most patients.
Q: Which patients require bridging anticoagulation with LMWH when stopping warfarin? A: HIGH thrombosis risk only: Mechanical MITRAL valve, recent VTE (less than 3 months), or AF with CHA2DS2-VASc greater than or equal to 5. BRIDGE trial showed bridging increases bleeding without preventing thrombosis in most patients.
Q: What is the main advantage of DOACs over warfarin for perioperative management? A: Predictable offset and NO bridging needed. DOACs can be stopped 24-48h preop and restarted postop without bridging, unlike warfarin which may need LMWH bridging in high-risk patients.
Q: How long after prophylactic LMWH is it safe to perform spinal anesthesia? A: 12 hours. Therapeutic LMWH requires 24 hours. This prevents spinal epidural hematoma, which causes irreversible paralysis.
Q: Why does dabigatran require longer preoperative cessation than other DOACs? A: 80% renal excretion. If CrCl less than 50, dabigatran must be stopped 72-96h preop (3-4 days) vs 48h for apixaban/rivaroxaban.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 72-year-old woman is scheduled for elective total hip arthroplasty in 10 days. She takes warfarin for atrial fibrillation (CHA2DS2-VASc score 3). Her INR today is 2.5. How would you manage her anticoagulation perioperatively?”
“A 68-year-old man on apixaban 5mg BD for AF is scheduled for TKA with spinal anesthesia. His CrCl is 55 ml/min. When would you stop the apixaban, when is it safe to perform the spinal, and when would you restart?”
Warfarin Protocol
- Stop 5 days preop, check INR day before surgery (target less than 1.5)
- Bridge only if HIGH risk: mechanical mitral, VTE less than 3mo, AF CHA2DS2-VASc greater than or equal to 5
- Last LMWH bridge dose 24h before surgery
- Restart 24-72h postop (bleeding risk dependent)
DOAC Protocol
- Calculate CrCl first - determines cessation timing
- Stop 24-48h if CrCl greater than 50, 48-96h if CrCl less than 50
- Dabigatran longest (96h if CrCl less than 50)
- NO bridging ever - DOACs have rapid offset
Neuraxial Timing (ASRA 2018 - Spinal Haematoma Prevention)
- LMWH prophylactic: Wait 12h before neuraxial, restart 4h after
- LMWH therapeutic: Wait 24h before neuraxial; avoid indwelling catheter
- Factor Xa inhibitors (apixaban/rivaroxaban): Wait 72h before neuraxial
- Dabigatran: 72-120h before neuraxial (renal dependent); restart 6h after catheter out
Bridging Indications (HIGH Risk Only)
- Mechanical MITRAL valve (always bridge)
- Recent VTE less than 3 months
- AF with CHA2DS2-VASc greater than or equal to 5
- Prior stroke/VTE while on therapeutic anticoagulation
Bleeding Risk Stratification
- LOW: Minor procedures - restart 6-12h postop
- MODERATE: THA/TKA/fracture ORIF - restart 24-48h
- HIGH: Spine, revision THA/TKA - restart 48-72h
- Neuraxial anesthesia = HIGH bleeding risk
Evidence Base and Key Trials
BRIDGE Trial - Bridging Anticoagulation in AF
- Double-blind RCT of 1884 AF patients on warfarin interrupted for elective procedure; randomised to dalteparin bridging or placebo
- Arterial thromboembolism 0.4% (no-bridge) vs 0.3% (bridge) - no-bridging non-inferior (P=0.01 for non-inferiority)
- Major bleeding 1.3% (no-bridge) vs 3.2% (bridge); RR 0.41 (95% CI 0.20-0.78), P=0.005 for superiority
- Most procedures were low bleeding risk; minor bleeding also reduced by forgoing bridging
PAUSE Cohort - Standardised DOAC Interruption
- Prospective cohort of 3007 AF patients on apixaban, dabigatran or rivaroxaban undergoing elective surgery/procedure
- Standardised, pharmacokinetics-based interruption: omit 1 day pre-op (low bleeding risk) or 2 days (high bleeding risk); no heparin bridging or coagulation testing
- 30-day major bleeding 0.9-1.85% across DOAC cohorts; ~3% for high-bleeding-risk procedures
- 30-day arterial thromboembolism 0.16-0.6%; most patients had minimal residual DOAC level (less than 50 ng/mL) at surgery
ARISTOTLE - Apixaban vs Warfarin in AF
- Double-blind RCT of 18,201 AF patients with at least one stroke risk factor; apixaban 5mg BD vs dose-adjusted warfarin
- Stroke or systemic embolism 1.27% vs 1.60% per year (HR 0.79, 95% CI 0.66-0.95; superior)
- Major bleeding 2.13% vs 3.09% per year (HR 0.69, 95% CI 0.60-0.80)
- All-cause mortality 3.52% vs 3.94% per year (HR 0.89, 95% CI 0.80-0.99)
RE-LY - Dabigatran vs Warfarin in AF
- RCT of 18,113 AF patients; dabigatran 110mg and 150mg BD vs adjusted-dose warfarin
- Dabigatran 150mg reduced stroke/systemic embolism (1.11% vs 1.69% per year; RR 0.66)
- Dabigatran 110mg non-inferior for stroke with lower major bleeding (2.71% vs 3.36% per year)
- Both doses reduced haemorrhagic stroke; GI bleeding higher with 150mg
PERIOP-2 - Postoperative LMWH Bridging RCT
- Double-blind RCT of 1471 patients with AF or mechanical heart valves whose warfarin was interrupted for a procedure
- Randomised after the procedure to postoperative dalteparin bridging vs placebo
- Major thromboembolism 1.0% (dalteparin) vs 1.2% (placebo) - no significant difference (risk difference -0.3%)
- Major bleeding 1.3% (dalteparin) vs 2.0% (placebo) - no significant difference; results consistent for AF and mechanical-valve subgroups
ASRA Evidence-Based Guidelines (4th Edition) - Neuraxial Anaesthesia and Antithrombotics
- Defines safe intervals between antithrombotic dosing and neuraxial puncture/catheter removal to prevent spinal-epidural haematoma
- Prophylactic LMWH: 12h before neuraxial; therapeutic LMWH: 24h before; resume 4h after needle/catheter (prophylactic) or 24h (therapeutic)
- Apixaban/rivaroxaban: hold 72h before neuraxial; dabigatran: 72-120h depending on CrCl
- Warfarin should be stopped and INR normalised (=1.4-1.5) before neuraxial block