Congenital Short Metatarsal
- Congenitally short metatarsal, most often from premature physeal closure; the fourth is most commonly affected; more common in females, frequently bilateral, with recognised syndromic associations
- The affected head sits proximal to the metatarsal parabola, and the toe is short and typically rides dorsally
- Cosmetic and footwear complaints predominate; some develop transfer metatarsalgia under the adjacent heads
- Weight-bearing AP radiograph, judged against the contralateral foot, confirms the short ray and measures the deficit
- Asymptomatic: reassurance and shoe modification. Symptomatic or cosmetically distressing: surgical lengthening
- One-stage graft: limited gain, shortest fixation. Callotasis: greater gain with soft-tissue lengthening and lower neurovascular risk, but a prolonged time in the fixator; distraction after an osteotome osteotomy is most reliable
- “Brachymetatarsia = congenitally short metatarsal (premature physeal closure); fourth metatarsal most common; female predominance, often bilateral; syndromic associations (pseudohypoparathyroidism, Down, Turner, Apert).
- “Disrupts the metatarsal parabola → short, dorsally-riding toe; cosmetic/footwear concern + transfer metatarsalgia. Weight-bearing AP radiograph shows the short metatarsal proximal to the cascade.
- “Symptomatic → lengthening: one-stage interpositional bone graft (limited gain, faster) vs gradual distraction/callotasis (greater length + soft-tissue lengthening, lower neurovascular risk, longer in fixator). Watch stiffness/MTP subluxation, nonunion, malunion.
Definition and Cause
Brachymetatarsia is a congenitally short metatarsal, most often the result of premature closure of the metatarsal physis (growth plate). The fourth metatarsal is the one most commonly affected.
Who. The condition is more common in females and is frequently bilateral. It has recognised syndromic associations, among them pseudohypoparathyroidism and pseudo-pseudohypoparathyroidism, Down syndrome, Turner syndrome and Apert syndrome.
Presentation and Diagnosis
The disrupted parabola. The metatarsal heads normally form a smooth cascade of lengths, the metatarsal parabola. A short metatarsal breaks it: the affected head sits proximal to the parabola, and the corresponding toe is shortened and typically rides dorsally, sitting up out of the line of the other toes.
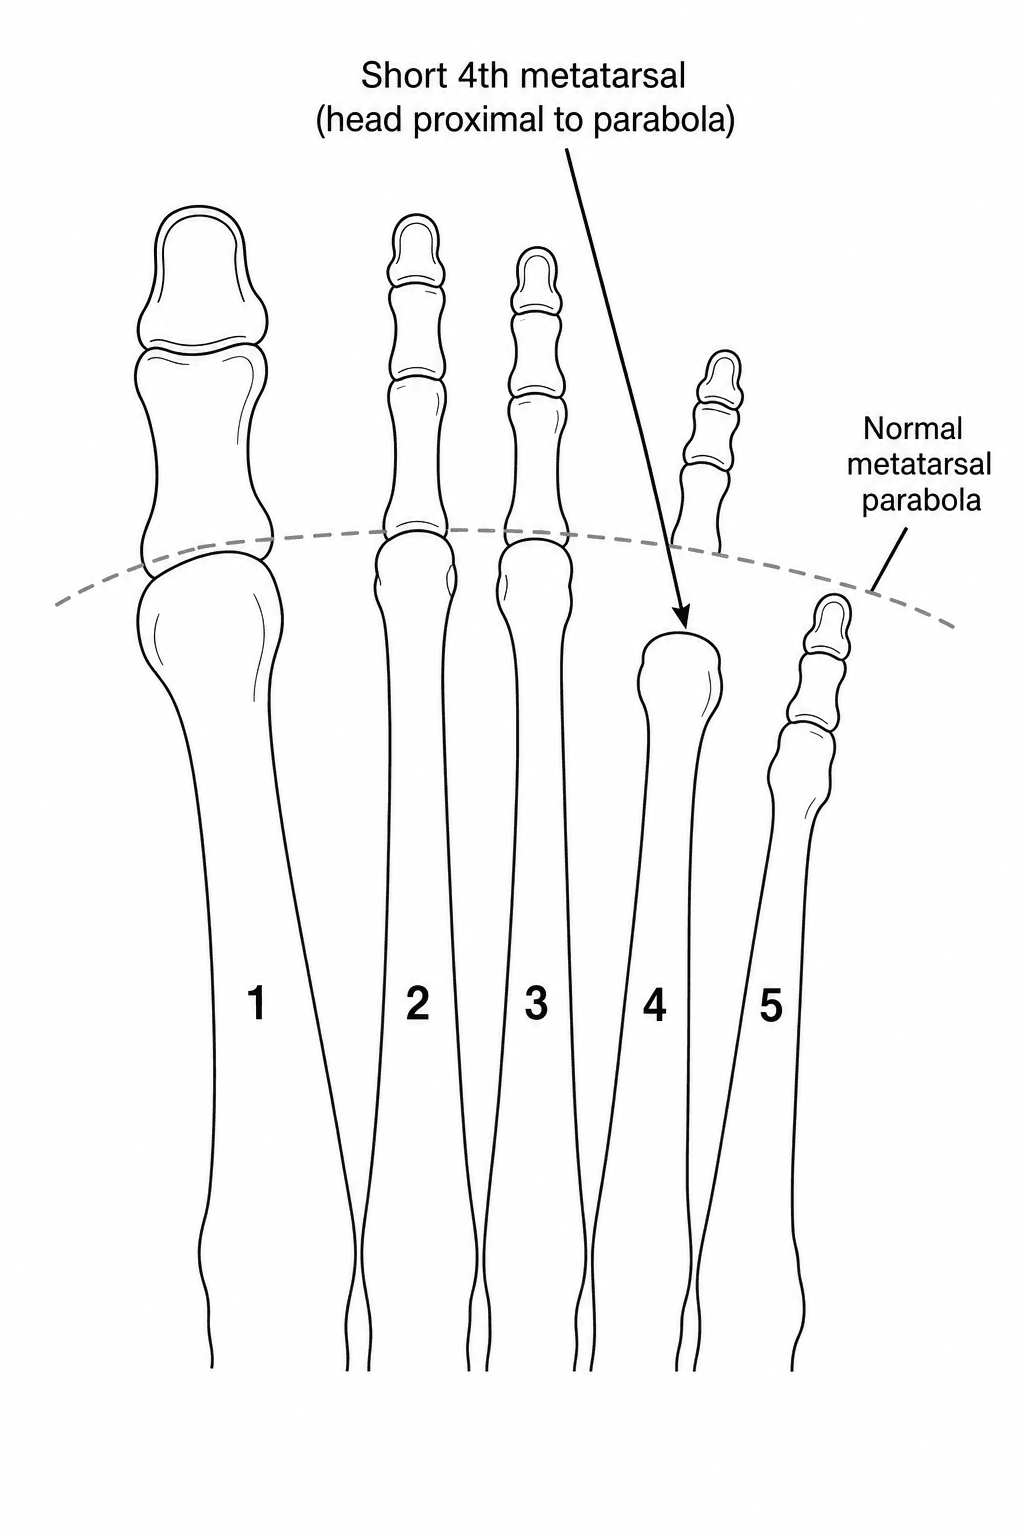
Symptoms. Most patients present with cosmetic concern and difficulty with footwear, and the dorsally displaced toe can rub in shoes. Some develop transfer metatarsalgia, pain under the adjacent metatarsal heads, because the short ray does not share the weight-bearing load.
Diagnosis. The diagnosis is clinical, with a weight-bearing AP radiograph of the foot showing the short metatarsal, its head proximal to the parabola and the cascade disrupted. The same film is used to measure the shortening and plan the lengthening, below.
Deciding Whether to Operate
The operation is elective, technically demanding and carries a real complication burden, so who is offered it matters as much as how it is done. The asymptomatic short metatarsal needs only reassurance and shoe modification; surgery is for symptoms or significant cosmetic distress, not for the radiograph alone.
The indication. It is usually a combination rather than appearance alone: difficulty with footwear, a transfer lesion or metatarsalgia under the adjacent heads, a dorsally riding or non-functional toe, and distress about the appearance of the foot. A purely cosmetic request deserves a frank discussion of the complication rate, the months in a fixator and the realistic aesthetic result.
Non-operative management. This is legitimate and often chosen, and many patients prefer it once the alternative is explained. The options are accommodative footwear with a wide toe box, metatarsal padding or a bar to offload the transfer lesion, and a toe prop or sleeve for a floating toe.
Timing. Lengthening is generally deferred until skeletal maturity. The causative physis has usually closed prematurely, and operating earlier risks further growth of the adjacent rays altering the parabola again.
Lengthening: One-Stage versus Gradual
Two strategies lengthen the ray: a one-stage lengthening with an interpositional bone graft, or gradual distraction osteogenesis (callotasis) through a mini-external fixator after a metatarsal osteotomy. The choice turns mainly on how much length is needed.
The soft tissues set the limit. The soft tissues and the neurovascular bundle limit how much length can be gained acutely. A one-stage graft stretches them all at once, which restricts the safe gain and risks neurovascular and soft-tissue compromise and MTP stiffness, so it suits cases needing only limited lengthening. When greater length is required, callotasis is preferred, because lengthening the bone slowly allows the soft tissues to lengthen with it.
- Length gain / soft tissue
- Limited gain; acute (no gradual soft-tissue lengthening)
- Trade-offs
- Shortest fixation time; risk of neurovascular/soft-tissue stretch; somewhat lower satisfaction
- Length gain / soft tissue
- Greater gain WITH concomitant soft-tissue lengthening
- Trade-offs
- Lower neurovascular risk; prolonged time in fixator; pin-site issues
- Length gain / soft tissue
- Osteotome (vs saw) osteotomy
- Trade-offs
- Osteotome-based distraction reported most reliable (fewer non-formations)
How much length. The target is to restore the affected head to the metatarsal parabola, judged on the weight-bearing AP against the adjacent metatarsals and the contralateral normal foot. That defines the required lengthening, which in brachymetatarsia is often substantial, commonly more than a centimetre.
The acute limit. What constrains one-stage grafting is acute stretch of the digital nerves and vessels. Acute gains beyond roughly 15% of the metatarsal length, a small absolute amount, risk neurovascular compromise and stiffness, so one-stage grafting suits small deficits only. Set this against the Lee series in the evidence below, where the one-stage group gained a mean of 13.9 mm (27.1%), from a fourth ray that was longer before surgery, and had the most dissatisfaction of the three groups.
Callotasis in the short metatarsal. The sequence is:
- A low-energy osteotome osteotomy
- A latency of about a week
- Distraction at roughly 0.5 to 1 mm per day, in divided increments
- Consolidation in the fixator until the regenerate corticates
The healing index, the time in the fixator per centimetre gained, is higher (slower) for first than for fourth brachymetatarsia, attributed to the larger osteotomy surface and to weight-bearing. The general principles of distraction osteogenesis are covered in the Distraction Osteogenesis and Limb Lengthening topics, and the parabola in the Metatarsalgia topic.
Protecting the MTP Joint and the Toe
The joint at risk. During lengthening the MTP joint is dragged distally, and the toe, already riding dorsally, is at real risk of dorsal subluxation or dislocation and stiffness. The joint is commonly protected with a temporary axial Kirschner wire across the MTP joint, and sometimes down the toe, through distraction and consolidation. It holds the reduction and resists subluxation, and is removed afterwards.
Soft-tissue adjuncts. A dorsal capsulotomy with extensor (sometimes flexor) lengthening or release may be needed if the ray will not come out as it lengthens, and any associated syndactyly, webbing or toe deformity is addressed. Gradual distraction itself reduces the need, by lengthening the soft tissues with the bone. Associated toe deformities are covered in the Lesser Toe Deformities topic.
After surgery. The patient follows a supervised distraction schedule with pin-site care, and starts early MTP range-of-motion physiotherapy to combat stiffness. Weight-bearing is modified during consolidation.
Complications to Consent For
Protect the MTP joint and lengthen within safe limits, and consent for the complications in the order they actually occur:
- MTP stiffness, the commonest
- Dorsal MTP subluxation
- Pin-site infection
- Premature consolidation or a poor or insufficient regenerate (failure of bone formation), requiring re-osteotomy or grafting
- Malunion or axial deviation of the lengthened ray
- Nonunion
- Neurovascular compromise if distraction is too rapid
- Floating toe
- An aesthetic result the patient does not consider worth it
Floating toe. This is the characteristic functional disappointment. The lengthened toe sits clear of the ground and takes no load, because tendon length and MTP mechanics have not kept pace with the bone. It is more likely after large gains and deserves a specific warning, because the foot may look better while the toe still does nothing.
Mnemonics & Memory Aids
SHORT
Hook:SHORT: Short 4th metatarsal, Heritable/syndromic, Out of parabola (dorsal toe), Radiograph, Treat by lengthening (one-stage vs callotasis).
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“What is brachymetatarsia and how does it present?”
“What are the surgical options to lengthen a short metatarsal, and how do you choose?”
What & cause
- Congenitally short metatarsal (premature physeal closure)
- Fourth metatarsal most common; female predominance; often bilateral
- Syndromic associations: pseudohypoparathyroidism, Down, Turner, Apert
Presentation
- Disrupted metatarsal parabola; short toe rides dorsally
- Cosmetic and footwear concern; transfer metatarsalgia in some
- Weight-bearing AP radiograph (short metatarsal proximal to the cascade)
Management
- Asymptomatic → reassurance / shoe modification
- Symptomatic/cosmetic → surgical lengthening
- One-stage interpositional graft (limited) vs gradual distraction/callotasis (greater length)
Technique & complications
- Gradual distraction: greater length + soft-tissue lengthening, lower neurovascular risk (longer in fixator)
- Distraction after osteotome (vs saw) osteotomy most reliable
- Complications: MTP stiffness/subluxation, nonunion/failure of bone formation, malunion, pin-site issues
Evidence & Key Studies
Lengthening of fourth brachymetatarsia by three different surgical techniques
- In 153 feet, the fourth metatarsal was lengthened by one-stage intercalary bone grafting, or by gradual distraction with a mini-external fixator after either a saw or an osteotome osteotomy.
- 153 feet in 106 patients - 100 female and six male - mean age 26.3 years (13 to 48), mean follow-up 22 months (7 to 55). Groups were 45 feet one-stage graft, 59 saw osteotomy and 49 pre-drilled osteotome.
- Mean lengthening: bone graft 13.9 mm (27.1%), saw 17.8 mm (29.9%), pre-drilled osteotome 16.8 mm (29.4%), p = 0.001 - so gradual distraction achieved more length than one-stage grafting.
- The one-stage bone-graft group had the shortest retention time but the most dissatisfaction (5 feet, 11.1%), while the saw group had failures of bone formation.
- Gradual lengthening by distraction osteogenesis after an osteotome osteotomy gave the most reliable results.
Metatarsal lengthening by callotasis in first brachymetatarsia
- One-stage lengthening with an autologous bone graft is preferred for metatarsals requiring limited lengthening, whereas gradual lengthening by callus distraction (callotasis) achieves a greater length gain with concomitant soft-tissue lengthening.
- In adults with first brachymetatarsia treated by callotasis, the average length gain was about 16 mm (around 44%).
- Bony consolidation took longer in first than in fourth brachymetatarsia - the average healing index was 3.8 months/cm - attributed to the larger osteotomised surface and to weight-bearing function.
The comparison of lengthening techniques for fourth brachymetatarsia (gradual distraction achieving greater length than one-stage grafting, the one-stage graft having the shortest fixation but more dissatisfaction, and distraction after an osteotome osteotomy being most reliable) comes from the cited Lee study; the principle that one-stage grafting suits limited lengthening while callotasis achieves greater gain with soft-tissue lengthening, and the slower consolidation of first brachymetatarsia, from the cited Hwang study. The fourth-metatarsal predominance, the premature-physeal-closure cause, the female/bilateral/syndromic associations, the disrupted metatarsal parabola, and the conservative-for-asymptomatic approach are standard, well-established teaching. (See also our Metatarsalgia and Distraction Osteogenesis topics.)