Endemic Zoonosis | Spondylodiscitis | Prolonged Antibiotic Therapy
- Endemic regions: Mediterranean, Middle East, Central Asia, Latin America
- Transmission: Unpasteurised dairy products, direct animal contact
- Lumbar spine most commonly affected (L4-L5 typical)
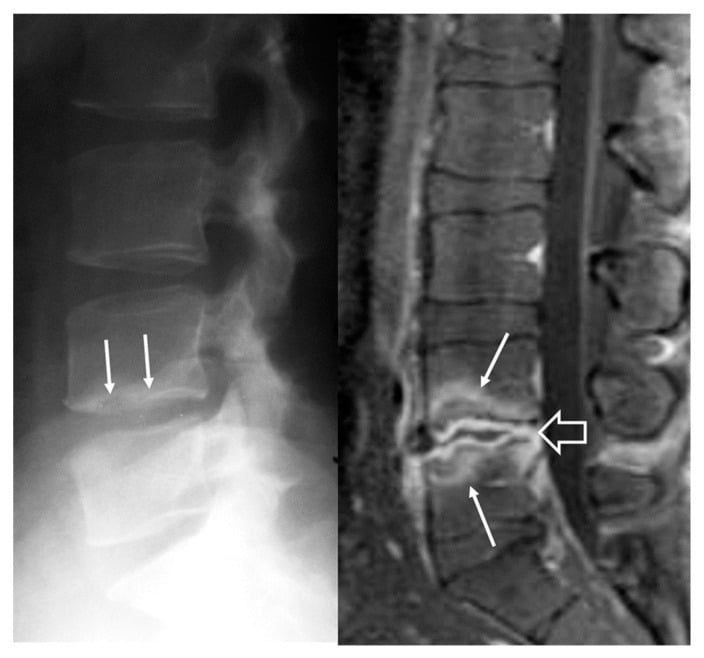
- Pedro Pons sign: Erosion of anterosuperior vertebral corner on X-ray
- Paraspinal abscess less common than tuberculosis (TB)
- Diagnosis: Serology (Rose Bengal, SAT) and blood cultures
- Treatment: Prolonged combination antibiotics for 3 to 6 months
- “Pedro Pons sign distinguishes early brucellosis from TB
- “Disc space preserved early - unlike pyogenic infection
- “B. melitensis is the most pathogenic species for humans
- “Surgery rarely needed except for neurological deficit or instability
Overview and Epidemiology
Spinal brucellosis is the most common form of osteoarticular brucellosis, a zoonotic infection caused by Brucella species. In endemic regions it is one of the most important causes of spondylodiscitis.
The organisms. Each species has its own animal host:
- B. melitensis (goats and sheep) - the most common and most virulent, responsible for more than 90% of spinal cases
- B. abortus (cattle) - milder disease, often from occupational exposure
- B. suis (pigs) - variable severity, and a less common cause of spinal disease
- B. canis (dogs) - a rare cause of human disease
Where it is found. The highest-risk regions are the Mediterranean basin (Spain, Italy, Greece), the Middle East, Central Asia and Latin America; the disease is also endemic in the Indian subcontinent and sub-Saharan Africa. There are about 500,000 new cases a year worldwide.
How often the skeleton is involved. Osteoarticular disease occurs in 6-12% of all brucellosis, and spondylitis is its most common manifestation, accounting for 50-60% of skeletal brucellosis. Spinal disease affects men twice as often as women, with a peak incidence at 40-60 years.
The history that makes the diagnosis. In non-endemic countries most cases are imported, so the travel, dietary and occupational history is essential. Ask specifically about unpasteurised dairy and animal contact.
Pathophysiology
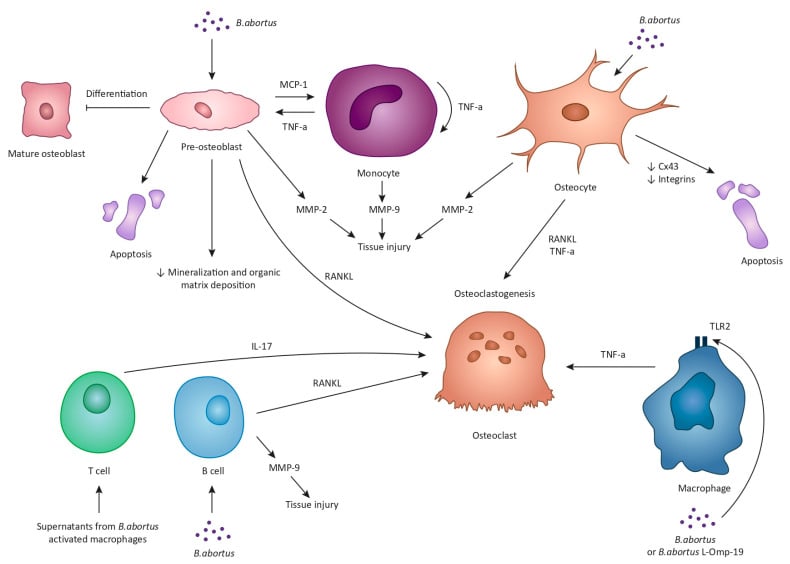
The organism. Brucella is a small, gram-negative coccobacillus: non-motile, non-spore forming, with no exotoxins or plasmids. It is a facultative intracellular organism that survives within macrophages, and it grows slowly.
Transmission. Ingestion is the most common route:
- Ingestion of unpasteurised milk, cheese or ice cream
- Direct contact with infected animals or their products through skin abrasions - farmers, vets and abattoir workers, raw meat handling, and a high risk when assisting at animal births
- Inhalation of aerosols in laboratories, abattoirs and on farms
- Vertical or sexual transmission, rarely
High-risk occupations: veterinarians, farmers, shepherds, abattoir workers and laboratory personnel. Always ask about occupation in patients from endemic areas presenting with back pain and fever.
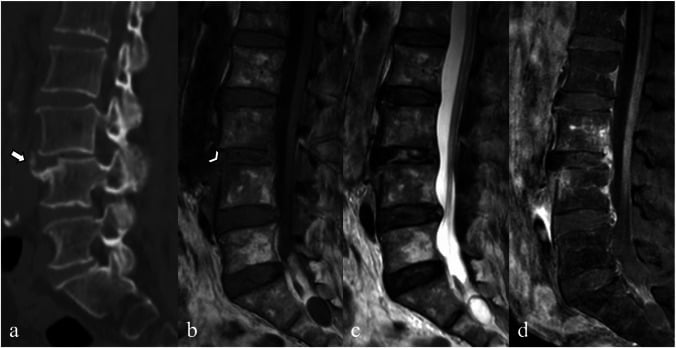
Seeding the vertebra. The organisms spread haematogenously from the primary infection, usually intestinal, and lodge in the vertebral metaphyseal vessels. These segmental, metaphyseal end-arteries arborise in the richly vascular anterosuperior endplate region, so seeded organisms lodge there first. That is why erosion of the anterosuperior corner, the Pedro Pons sign, is the earliest radiographic change, before the disc space narrows. The infection starts as osteomyelitis of the vertebral endplate and spreads to the adjacent disc and vertebra, producing spondylodiscitis.
Why it destroys less bone. The inflammation is granulomatous, with microabscess formation, and less destructive than pyogenic infection. The corner lesion therefore tends to repair with reactive sclerosis and osteophyte ("parrot-beak") formation rather than the collapse and gibbus of tuberculosis.
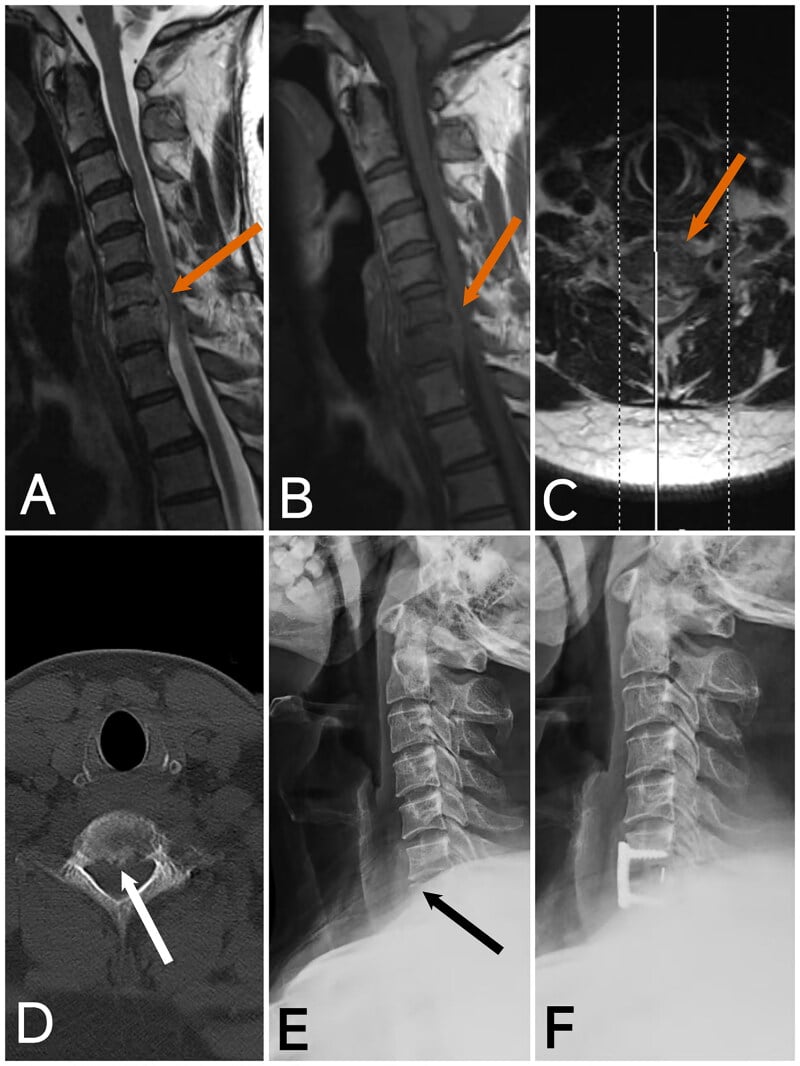
Where in the spine. The lumbar spine is involved in 70-80% of cases, L4-L5 most often (40-50%) and L3-L4 next. Cervical disease is rare (less than 5%), and 10-20% of patients have multifocal involvement.
The lumbar spine is most affected because of the rich blood supply and large vertebral body size at L4-L5, providing more area for bacterial seeding from the bloodstream.
Clinical Presentation
The systemic illness. The fever is undulant, classically rising and falling ("Malta fever"), with night sweats, malaise, fatigue, weight loss and anorexia. Hepatosplenomegaly is found in 30-50%. The presentation may be subacute or chronic.
The spine. Back pain is insidious in onset, progressive and worse at night. There is tenderness over the affected vertebrae, paravertebral muscle spasm, and reduced range of motion, particularly in extension.
Neurological involvement. Radiculopathy from root compression is the most common form. An epidural abscess can compress the cord, and cauda equina syndrome is rare but serious. The prognosis is better than that of tuberculous myelopathy.
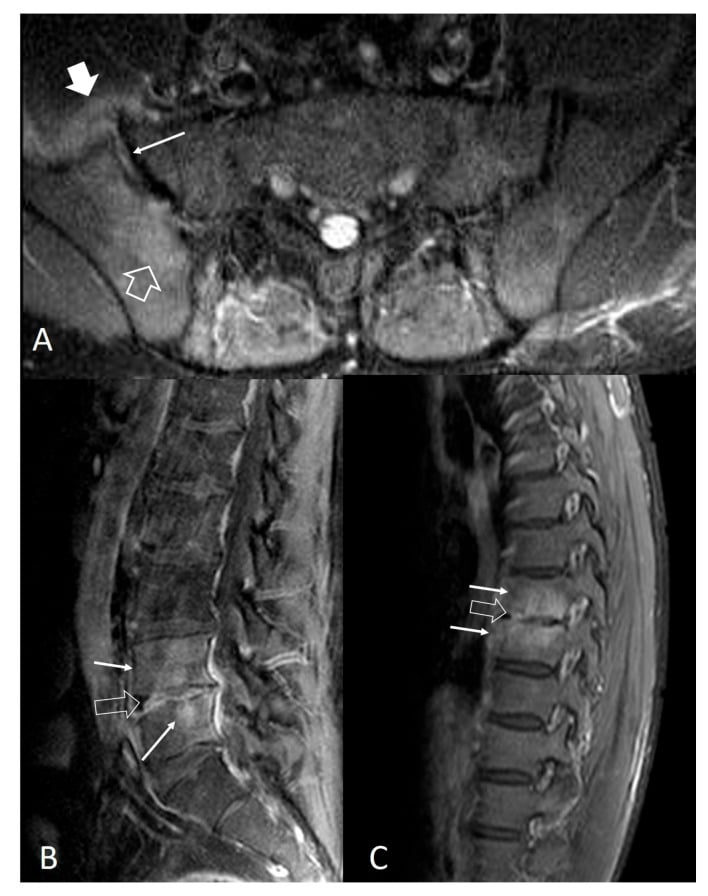
Sacroiliitis. Concurrent sacroiliitis occurs in 20-30% of spinal brucellosis and can cause buttock pain, a positive FABER test and sacroiliac joint tenderness. In an endemic region, spine plus sacroiliac involvement should raise the suspicion of brucellosis.
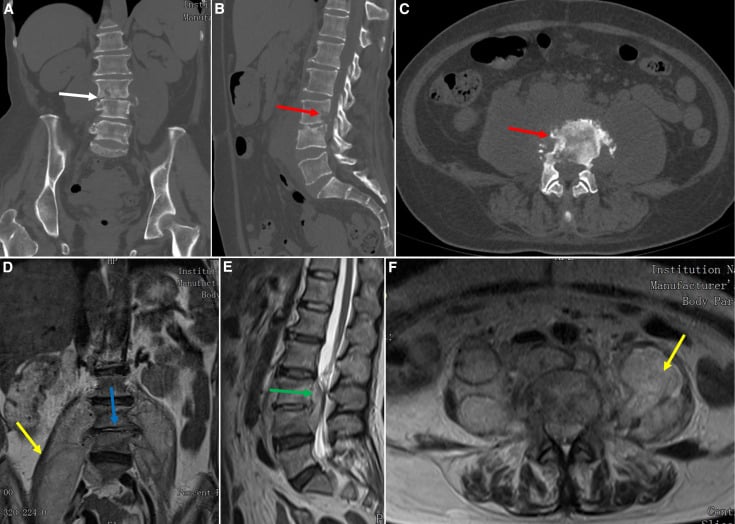
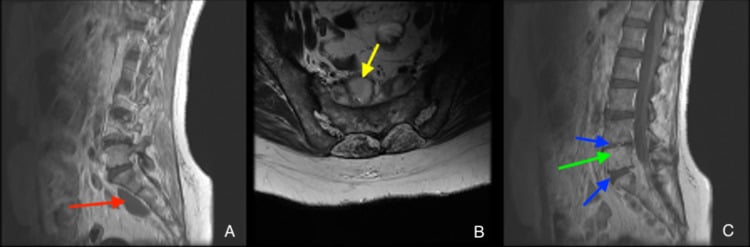
Against pyogenic infection and tuberculosis. Brucellar spondylitis is more indolent than pyogenic spondylodiscitis, and fever is less prominent. Against tuberculosis, the systemic symptoms are more prominent while destruction, kyphotic deformity and neurological involvement are less severe; paraspinal abscesses are less common and smaller, and the response to medical treatment is better.
- Brucellosis
- Mediterranean, Middle East, Latin America
- TB Spondylitis (Pott's Disease)
- Worldwide, especially developing countries
- Brucellosis
- Zoonosis (dairy, animal contact)
- TB Spondylitis (Pott's Disease)
- Respiratory (Mycobacterium tuberculosis)
- Brucellosis
- Lumbar most common (L4-L5)
- TB Spondylitis (Pott's Disease)
- Thoracolumbar junction (T10-L2)
- Brucellosis
- Pedro Pons sign (anterosuperior erosion)
- TB Spondylitis (Pott's Disease)
- Gibbus deformity, vertebra plana
- Brucellosis
- Less common (20-30%)
- TB Spondylitis (Pott's Disease)
- Common (50-75%), cold abscess
- Brucellosis
- Preserved early, involved late
- TB Spondylitis (Pott's Disease)
- Early disc destruction common
- Brucellosis
- Serology (SAT greater than 1:160), blood culture
- TB Spondylitis (Pott's Disease)
- Tissue biopsy, PCR, culture (slow)
- Brucellosis
- 3 to 6 months antibiotics
- TB Spondylitis (Pott's Disease)
- 9 to 12 months anti-TB therapy
- Brucellosis
- Rarely needed (10-15%)
- TB Spondylitis (Pott's Disease)
- More often needed (20-30%)
Investigations
Serology. Serology confirms the diagnosis in most cases. The Rose Bengal test screens; the standard agglutination test (SAT) gives the titre that makes the diagnosis.
- Method
- Rapid agglutination screening
- Interpretation
- Highly sensitive (greater than 95%), confirm positive with SAT
- Method
- Quantitative antibody titre
- Interpretation
- Greater than 1:160 diagnostic; greater than 1:320 highly suggestive
- Method
- Detects IgG (active infection)
- Interpretation
- Positive suggests active disease, useful for monitoring treatment
- Method
- Detects blocking antibodies
- Interpretation
- Useful for chronic brucellosis with negative SAT
- Method
- IgM and IgG antibodies
- Interpretation
- High sensitivity, useful for monitoring response
When the serology is falsely negative. The standard agglutination test can be negative in a patient who really has brucellosis:
- The prozone phenomenon. With very high antibody titres the SAT can be falsely negative at low dilutions, because antibody excess prevents the antigen-antibody lattice needed for visible agglutination. Testing further serial dilutions, well beyond 1:320, brings out agglutination at the higher dilutions.
- Blocking (incomplete) antibodies. In chronic or relapsing disease, non-agglutinating IgG and IgA can give a negative agglutination test; the Coombs (anti-human-globulin) test detects them.
- Very early acute infection, before antibodies rise.
- B. canis, a rough-lipopolysaccharide species not detected by the standard smooth-antigen test.
A negative result with strong suspicion therefore warrants further dilutions, a Coombs test, and culture or PCR.
Blood cultures. Positive in 50-70% of acute cases, but they need prolonged incubation, up to 4-6 weeks. Alert the laboratory to the clinical suspicion, because biosafety precautions are needed; modern BACTEC systems improve the yield.
Inflammatory markers and blood count. The CRP is raised, usually less than in pyogenic infection, and the ESR is raised, typically 50-100 mm/hr. The white count is low or normal, unlike pyogenic infection, with a mild normocytic anaemia, and liver enzymes are raised in 50%.
Management
The principle. Most patients respond well to antibiotics alone, and surgery is required in only 10-15%, unlike tuberculosis, where it is more commonly needed.
Combination, never monotherapy. Monotherapy relapses in 10-40% and fails 2.6 times as often as combination therapy, so a single drug is never acceptable, whatever the duration. Brucella survives in macrophages, so the drugs need intracellular penetration as well as good bone penetration.
The choice of regimen. Level I evidence prefers doxycycline plus an aminoglycoside. The all-oral doxycycline-rifampicin regimen is widely used for compliance, a pragmatic choice rather than a better one. Rifampicin substitutes for the aminoglycoside only when injectables are impractical, and the higher relapse rate is then accepted and counselled.
- Drugs
- Doxycycline 100mg BD + Streptomycin 1g IM OD (or gentamicin)
- Duration
- 2-3 weeks aminoglycoside, doxycycline for a minimum of 3 months, typically 6 months
- Notes
- Skalsky meta-analysis: doxycycline-rifampicin fails 2.8x more often (RR 2.80, 95% CI 1.81-4.36), driven by relapse. Gentamicin non-inferior to streptomycin
- Drugs
- Doxycycline + Rifampicin + aminoglycoside
- Duration
- 2-3 weeks aminoglycoside, then oral to 6+ months
- Notes
- Outperformed doxycycline-streptomycin in the meta-analysis (RR 2.50), though on only two trials. Reasonable for spondylitis with epidural or neurological involvement
- Drugs
- Doxycycline 100mg BD + Rifampicin 600-900mg OD
- Duration
- Minimum 6 weeks, 3-6 months for spondylitis
- Notes
- Chosen for compliance and where injectables are impractical - NOT because it works better. Accept and counsel the higher relapse rate
- Drugs
- Rifampicin + TMP-SMX
- Duration
- Throughout pregnancy
- Notes
- Avoid doxycycline and aminoglycosides
Duration. In the meta-analysis, treatment for six weeks or more beat shorter courses. Spondylitis needs 3-6 months, guided by clinical and radiological response.
Minimum 3 months, but most experts recommend 6 months for spondylodiscitis. Shorter courses have unacceptable relapse rates (up to 30%). Continue until clinical cure and normalisation of inflammatory markers.
Monitoring response. Successful treatment brings clinical improvement within 2-4 weeks.
- Clinical - the fever resolves in 1-2 weeks, and pain improves
- CRP and ESR - should fall by 2-4 weeks; check the CRP every 2-4 weeks
- Serology - the SAT may remain positive, but the 2-ME test should become negative
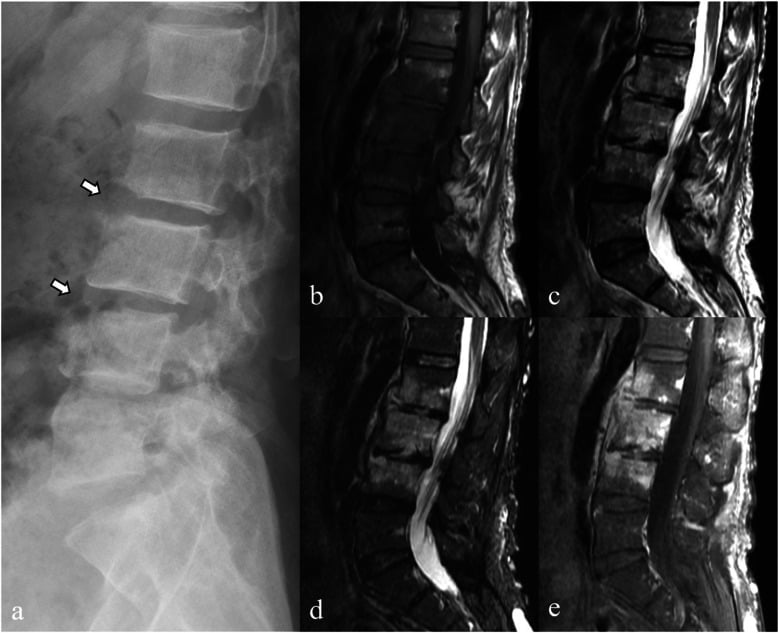
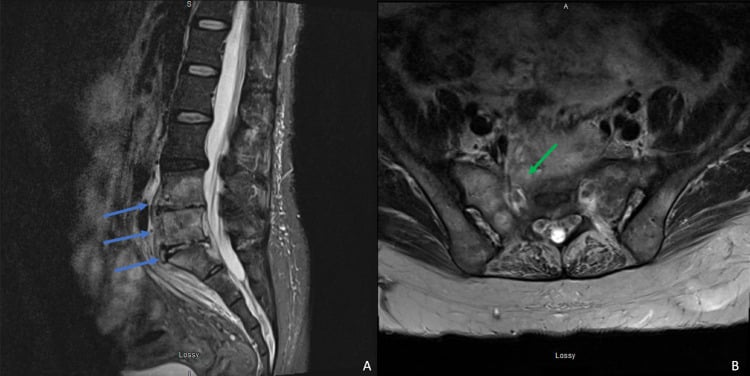
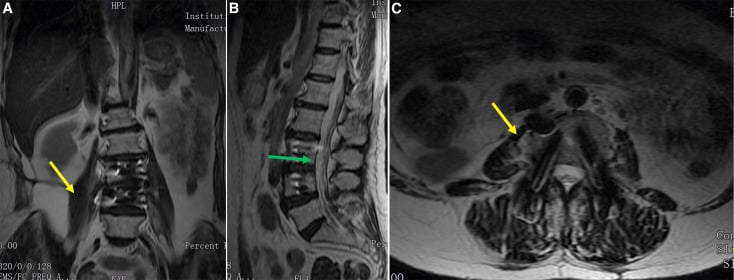
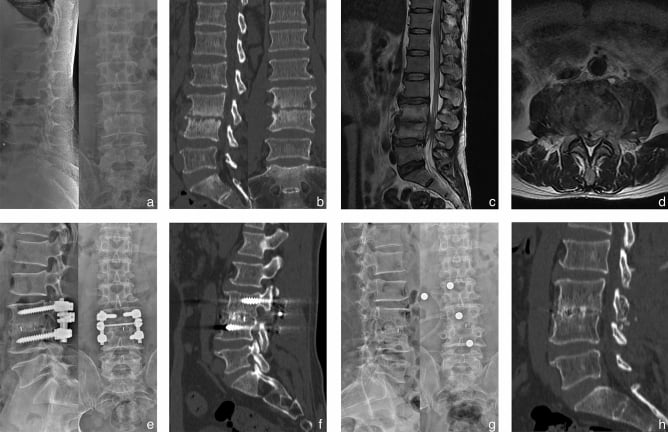
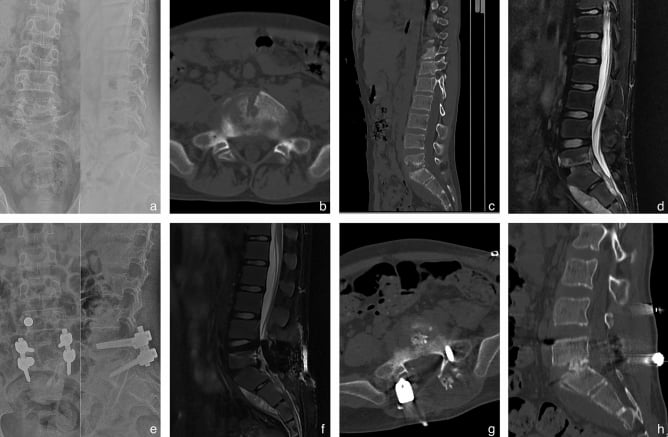
- MRI - at 3 months if the response is good, earlier if there is concern, and repeated at 3-6 months if the response is uncertain
When the initial disease was extensive, follow-up MRI provides an anatomical endpoint.
Complications
Outcome. With appropriate antibiotics the cure rate is 95%. Early diagnosis improves outcomes, and treatment delay is associated with a higher complication rate; neurological involvement worsens the prognosis, and compliance with the prolonged antibiotic course is crucial.
- Incidence
- 10-20%
- Management
- Urgent decompression if progressive
- Incidence
- 10-20%
- Management
- Surgery if not responding to antibiotics
- Incidence
- 20-30%
- Management
- Usually responds to antibiotics, drain if large
- Incidence
- 5-10% with adequate treatment (higher with monotherapy)
- Management
- Retreatment with prolonged course
- Incidence
- 20-30%
- Management
- Multidisciplinary pain management
- Incidence
- Rare (less than 5%)
- Management
- Surgical stabilisation
Guidelines, Registries & Global Practice
Global epidemiology:
Brucellosis is the commonest bacterial zoonosis worldwide, with the heaviest burden across the Mediterranean basin, Middle East, Central Asia, the Indian subcontinent, sub-Saharan Africa and Latin America. Incidence is highly heterogeneous: many high-income countries that have eradicated bovine brucellosis (much of Western Europe, North America, Japan, Australia and New Zealand) now see almost exclusively imported cases in travellers and migrants, whereas hyperendemic regions report population incidence orders of magnitude higher. There is no implant registry for spinal infection; the relevant "registries" are national notifiable-disease surveillance systems (e.g. national public-health agencies and WHO/FAO/OIE reporting), which capture confirmed human cases and inform regional risk.
Side-by-side guidance:
- Region
- Global
- Emphasis for spinal/focal disease
- Combination therapy (doxycycline + aminoglycoside or rifampicin); extended duration for osteoarticular/focal disease
- Region
- Europe/Mediterranean
- Emphasis for spinal/focal disease
- Doxycycline + aminoglycoside preferred for spondylitis; minimum 3 months, often longer with abscess
- Region
- US
- Emphasis for spinal/focal disease
- Doxycycline-based dual/triple therapy; ID referral and prolonged courses for complicated disease
- Region
- Non-endemic high-income
- Emphasis for spinal/focal disease
- Notifiable disease; alert laboratory for hazard-group containment; treat per international regimens
Diagnostic and biosafety considerations:
Brucella is a hazard-group/risk-group 3 organism; laboratories must be alerted to the clinical suspicion so that cultures are handled in appropriate containment and incubated for the extended period required. In non-endemic settings, local laboratories may have limited experience, and serology (Rose Bengal screening with confirmatory agglutination/ELISA) plus molecular testing through reference laboratories is the mainstay. A clear travel, dietary and occupational history is the single most important step that prompts the correct test.
High- vs limited-resource practice variation:
- High-resource settings: MRI is readily available for early diagnosis and monitoring; automated blood-culture systems and PCR improve and accelerate confirmation; infectious-diseases input guides prolonged therapy and surgery is reserved for neurological deficit, instability or abscess unresponsive to antibiotics.
- Limited-resource / hyperendemic settings: Diagnosis often rests on serology and plain radiographs (Pedro Pons sign), with MRI and PCR less accessible; the doxycycline + rifampicin oral regimen is favoured for outpatient feasibility and adherence despite a higher relapse risk than aminoglycoside-containing regimens; the major public-health lever is control of animal reservoirs and pasteurisation of dairy.
Related pages: Tuberculosis of the Spine (Pott's Disease) is the diagnosis this one is mistaken for and the comparison every examiner wants - the discriminators from the 219-case series carded above are a prolonged course, thoracic level, absent fever, spinal deformity, neurological deficit and large paravertebral or epidural masses favouring tuberculosis, against the single-level lumbar involvement, preserved disc height and preserved vertebral architecture of brucellosis. Pyogenic Discitis and Vertebral Osteomyelitis completes that triad and is suggested instead by diabetes, intravenous drug use, recent spinal surgery, preceding bacteraemia and a markedly raised white count. Spinal Epidural Abscess is the complication that turns a medically treated infection into a surgical one and the reason for the single operation in Solera's 35 patients, with Cauda Equina Syndrome the deficit to exclude on every review. Systematic Approach to Spine Imaging and Systematic Approach to Infection Imaging cover the MRI protocol on which all of this is judged. Fungal Spine Infections and Atypical Mycobacterial Infection are the rest of the granulomatous, culture-negative differential - a chronic spondylodiscitis with negative routine cultures is brucellar, tuberculous, mycobacterial or fungal until the laboratory is asked the right question. Orthopaedic Antibiotic Therapy and Antibiotic Pharmacology and Resistance carry the intracellular penetration that makes doxycycline and the aminoglycosides work against an organism living inside macrophages, and explain why monotherapy relapses. Osteomyelitis Pathophysiology with Biofilm Formation and Intervertebral Disc Biology explain why the disc is involved early here and late in tuberculosis, and Thoracolumbar Fractures covers the deformity and instability that follow untreated destruction.
Controversies and Areas of Uncertainty
Optimal regimen. Meta-analysis evidence (Skalsky, BMJ 2008) shows that doxycycline-rifampicin relapses more than aminoglycoside-containing regimens, yet the all-oral combination remains widely used for adherence in outpatient and limited-resource settings. The trade-off between efficacy and feasibility is unresolved for spinal disease specifically.
Treatment duration. No randomised evidence defines the ideal duration for brucellar spondylitis. Practice ranges from a minimum of 3 months to 6 months or longer, individualised to clinical response, abscess and inflammatory-marker normalisation rather than a fixed endpoint.
Role and timing of surgery. Thresholds for operating on an epidural or paravertebral abscess without progressive neurology are debated. Many collections resolve with antibiotics alone, but the size and response that should trigger drainage are not standardised.
Monitoring cure and defining relapse. Serological titres can persist after microbiological cure, so distinguishing true relapse from residual antibody or non-infective mechanical back pain is difficult. The relative value of MRI, inflammatory markers and antibody assays for follow-up is not firmly established.
Empirical therapy in dual-endemic regions. Where tuberculosis and brucellosis coexist, whether to await tissue or molecular confirmation or to start empirical therapy when both are plausible remains a clinical judgement, given the very different drug regimens and durations.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 55-year-old man presents with 6 weeks of progressive low back pain, night sweats, and weight loss. He returned from a trip to Turkey 3 months ago where he consumed unpasteurized cheese. Examination reveals lumbar tenderness at L4-5 with restricted range of motion. How would you approach this case?”
“A 45-year-old woman from rural Pakistan presents with 3 months of progressive thoracolumbar back pain. MRI shows spondylodiscitis at L1-L2 with a small paraspinal collection. How do you differentiate between TB spondylitis and brucellosis, and how does this affect your management?”
“A 50-year-old man with confirmed spinal brucellosis (L4-L5) has been on doxycycline and rifampicin for 4 weeks. He now presents with progressive bilateral lower limb weakness (power 3/5), urinary retention, and reduced perineal sensation. MRI shows enlarging epidural abscess with cord compression. What is your management?”
Epidemiology
- Endemic: Mediterranean, Middle East, Central Asia, Latin America
- Transmission: Unpasteurized dairy (most common), animal contact
- B. melitensis is most common and virulent species
- Spondylodiscitis in 6-12% of brucellosis cases
Clinical Features
- Lumbar spine most common (L4-L5)
- Insidious back pain with systemic symptoms
- Undulant fever, night sweats, weight loss
- Less destruction than TB, smaller abscesses
Diagnosis
- Rose Bengal: Screening (greater than 95% sensitive)
- SAT greater than 1:160: Diagnostic
- Blood cultures: Positive 50-70%, need prolonged incubation
- Pedro Pons sign: Anterosuperior vertebral corner erosion
Imaging
- X-ray: Pedro Pons sign early, disc narrowing late
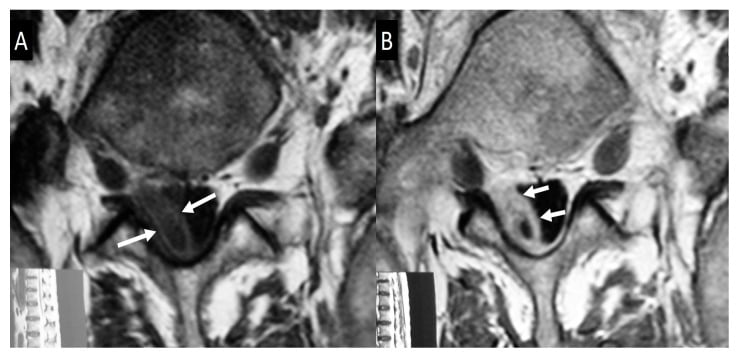
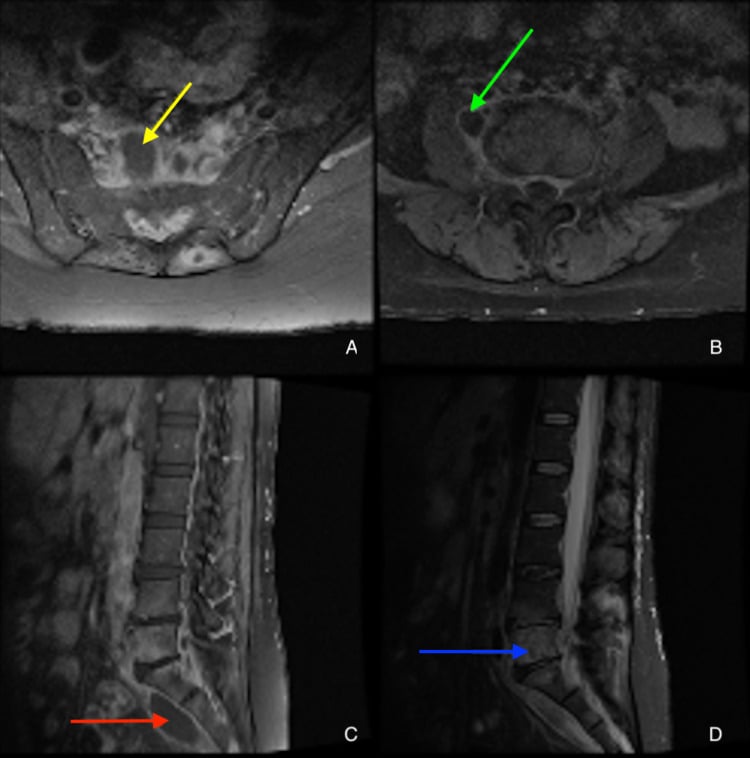
- MRI: T2 high signal, enhancement, epidural collection
- Less destruction and smaller abscesses than TB
- Disc preserved early (unlike pyogenic infection)
Treatment
- First-line: Doxycycline 100mg BD + Rifampicin 600-900mg OD
- Duration: 3-6 months (minimum 3 months)
- Alternative: Doxycycline + Streptomycin (more effective but injectable)
- Surgery rare (less than 10-15%): neurological deficit, large abscess, instability
Key Differences from TB
- Brucellosis: Lumbar spine, less destruction, smaller abscesses
- TB: Thoracolumbar, gibbus, large cold abscesses
- Brucellosis: Serology diagnosis; TB: Tissue diagnosis
- Brucellosis: 3-6 months treatment; TB: 9-12 months
Evidence Base
Brucellar Spondylitis: Course and Outcome
- Series of 35 patients with brucellar spondylitis (mean age 54 years)
- Back or neck pain in 100%, fever in 66%, constitutional symptoms in 57%
- Blood cultures positive for B. melitensis in 74%; median treatment 120 days (range 45-535)
- Therapeutic failure in 26% and relapse in 14%; only 1 of 35 required surgery (epidural abscess); no deaths
Clinical and MRI Findings of Brucellar Spondylodiscitis
- 22 patients with spondylodiscitis among 152 with brucellosis; all had agglutination titres at least 1:160
- Single-level involvement in 95.5% (only 4.5% multilevel)
- All cases showed vertebral and discal contrast enhancement; soft tissue involvement in 8 and abscess in 3
- Epidural extension in 4, posterior longitudinal ligament elevation in 5, root compression in 2
Brucellosis (Landmark Review)
- Authoritative review establishing brucellosis as the commonest zoonosis worldwide
- B. melitensis is the most virulent species; unpasteurised dairy is the dominant route in non-occupational cases
- Osteoarticular disease (spondylitis, sacroiliitis, peripheral arthritis) is the commonest focal complication
- Combination therapy with doxycycline plus an aminoglycoside or rifampicin is required to limit relapse
WHO Joint FAO/WHO Expert Guidance on Brucellosis
- Doxycycline plus rifampicin (or doxycycline plus an aminoglycoside) for at least 6 weeks for uncomplicated disease
- Osteoarticular and focal disease (including spondylitis) requires extended treatment, typically months
- Aminoglycoside-containing regimens may be more effective but are less practical for outpatients
- Combination therapy is essential to prevent relapse