Mild Traumatic Brain Injury in Athletes
- Sport-related concussion is a traumatic brain injury induced by BIOMECHANICAL FORCES - a direct blow to the head, face or neck, or a blow elsewhere with force transmitted to the head - that produces TRANSIENT neurological impairment; it is a FUNCTIONAL disturbance rather than a structural injury, so standard CT and MRI are typically NORMAL, and loss of consciousness is NOT required (it occurs in only a minority).
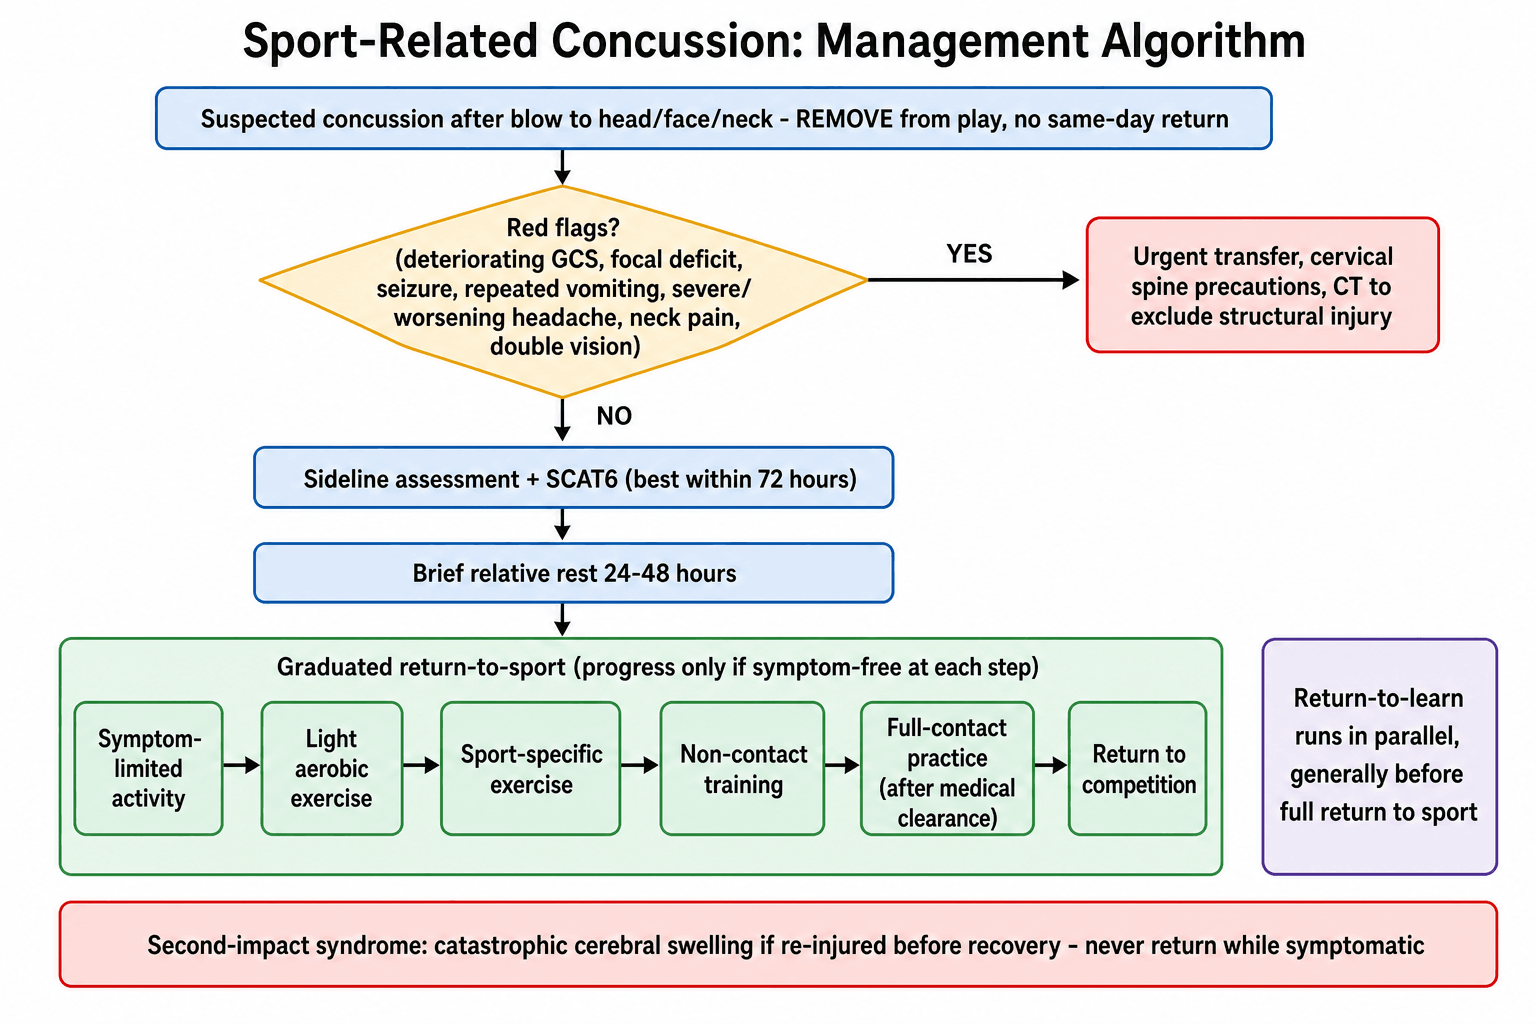
- The IMMEDIATE priority is to REMOVE the athlete from play - the principle is 'if in doubt, sit them out' - with NO SAME-DAY RETURN to play once concussion is suspected, because returning while symptomatic risks worsening injury; a sideline assessment is performed and the athlete monitored, with a brief initial period (about 24-48 hours) of relative physical and cognitive rest before gradually and progressively increasing activity as tolerated.
- ASSESSMENT uses structured tools: a sideline screen and the SCAT6 (Sport Concussion Assessment Tool), which discriminates concussed from non-concussed athletes best within 72 hours of injury with diminishing utility up to 7 days, and is NOT a stand-alone return-to-play test; cognition, balance/postural stability and the oculomotor/cervical/vestibular system are assessed, and serial evaluation tracks recovery.
- RED FLAGS that mandate urgent assessment and CONSIDERATION OF CT (to exclude a structural injury such as a haematoma) include a deteriorating conscious level/GCS, focal neurological deficit, seizure, repeated vomiting, severe or worsening headache, increasing confusion or agitation, neck pain/tenderness, or double vision - concussion is a clinical diagnosis once structural injury is excluded.
- Recovery is managed with a stepwise, criteria-based GRADUATED RETURN-TO-SPORT strategy (progressing through stages from symptom-limited activity and light aerobic exercise to sport-specific training, non-contact then full-contact practice, and finally return to competition) and a parallel RETURN-TO-LEARN pathway; progression occurs only if there is no symptom recurrence at each step, and medical clearance is required before full-contact return.
- The serious RISKS that drive cautious management are SECOND-IMPACT SYNDROME (a rare but catastrophic diffuse cerebral swelling after a second head injury sustained before recovery from the first), PERSISTENT post-concussive symptoms, and the long-term concern of repeated head injury (including chronic traumatic encephalopathy); guidelines (the Concussion in Sport Group consensus) provide the framework, and protocols should be sport-specific and kept up to date - particularly in high-incidence collision/combat sports.
- “Sport-related concussion = FUNCTIONAL TBI from biomechanical force; transient impairment; normal CT/MRI; LOC NOT required.
- “REMOVE from play - 'if in doubt, sit them out'; NO same-day return. Assess with SCAT6 (best within 72h; not a stand-alone RTP test). Red flags (deteriorating GCS, focal deficit, seizure, repeated vomiting, neck pain) → CT.
- “Stepwise GRADUATED return-to-sport + return-to-learn (progress only if symptom-free; medical clearance before full contact). Beware SECOND-IMPACT SYNDROME and repeated injury.
Definition and Immediate Management
What it is. Sport-related concussion is a traumatic brain injury induced by biomechanical forces: a direct blow to the head, face or neck, or a blow elsewhere with the force transmitted to the head. It produces transient neurological impairment and is a functional disturbance rather than a structural injury, so standard CT and MRI are typically normal. Loss of consciousness is not required, and occurs in only a minority.
A clinical diagnosis. Because the injury is functional, concussion is a clinical diagnosis. Before settling on it, the clinician must exclude a structural injury.
Remove from play. Once concussion is suspected the athlete comes off, on the principle 'if in doubt, sit them out', and there is no same-day return. Returning while symptomatic risks worsening the injury and, rarely, the catastrophic second-impact syndrome. A sideline assessment is performed and the athlete is monitored.
Any of these mandates urgent assessment, cervical-spine evaluation and consideration of CT to exclude a structural injury such as a haematoma:
- Deteriorating conscious level or GCS
- Focal neurological deficit
- Seizure
- Repeated vomiting
- Severe or worsening headache
- Increasing confusion or agitation
- Neck pain or tenderness
- Double vision
Rest, briefly. A short initial period of relative physical and cognitive rest, about 24-48 hours, is followed by a gradual, progressive increase in activity as tolerated. The reasons it is kept brief follow in the next section.
The Neurometabolic Cascade: Why a Normal Scan Still Means an Injured Brain
Concussion is a metabolic injury, and the cascade explains almost every clinical rule that follows: why the imaging is normal, why there is a vulnerable window, and why rest is brief rather than absolute.
The ionic flux. Mechanical force stretches axons and depolarises neurons, causing indiscriminate release of excitatory neurotransmitters, principally glutamate. Glutamate acting on NMDA receptors opens channels and produces a massive efflux of potassium and influx of calcium and sodium.
The pumps fight back. The Na⁺/K⁺-ATPase works far above baseline to restore the ionic gradients, and that costs ATP. The brain responds with a short burst of hyperglycolysis, glucose hypermetabolism, in the first minutes to hours.
Supply falls as demand rises. Cerebral blood flow decreases at the same time, so demand and delivery are uncoupled. This mismatch is the energy crisis at the heart of concussion.
Calcium then poisons the mitochondria. Accumulated intracellular calcium impairs oxidative metabolism, and the early hypermetabolism gives way to a prolonged hypometabolism lasting days to weeks. Alongside it runs axonal injury: neurofilament compaction and disrupted axonal transport, without frank transection.
The window of vulnerability. While metabolism is uncoupled the brain tolerates a second insult extremely poorly. This is the physiological basis of second-impact syndrome, and the reason a graduated, symptom-guided return exists at all in place of an arbitrary time-based one.
Why the scan is normal. The abnormality is ionic, metabolic and axonal at a microstructural level, well below the resolution of CT or conventional MRI. A normal scan is the expected finding, and never evidence against the diagnosis.
Why early light activity now beats strict rest. Prolonged inactivity worsens deconditioning, mood and symptom focus, whereas sub-symptom-threshold aerobic exercise appears to help restore autonomic and cerebrovascular regulation. That is why guidance moved from "rest until asymptomatic" to a brief 24-48 hours of relative rest followed by graded activity.
Assessment: the SCAT6 and the Office Tools
The current framework. The tools are versioned to the Amsterdam 2023 (6th) International Consensus Statement on Concussion in Sport, which superseded Berlin 2016. Citing the current statement by name, and knowing that the tools belong to it, is a small thing that reads as current practice. It introduced the present tool set:
- SCAT6 - the acute phase
- SCOAT6 (Sport Concussion Office Assessment Tool) - office assessment and sub-acute follow-up beyond 72 hours
- Child SCAT6 and Child SCOAT6 - the child versions of each, for younger children around ages 8 to 12
- CRT6 - for non-clinicians on the sideline
The SCAT6 on the field. It is a multimodal acute tool, and its immediate on-field screen covers the observable signs, the Maddocks questions (orientation and memory: ground, half, opponent, last score), the Glasgow Coma Scale and a cervical-spine check.
The SCAT6 off the field. The office portion evaluates cognition, balance and the oculomotor, cervical and vestibular system:
- A symptom checklist - the number and severity of symptoms
- A cognitive screen - orientation, immediate memory using a 10-word list to reduce the ceiling effect of the old 5-word list, concentration with digits-backward and months-in-reverse, and delayed recall
- A balance and neurological examination - the modified Balance Error Scoring System and tandem gait
- An oculomotor and cervical screen
What it is not. The SCAT6 supplements clinical judgement and is neither a diagnosis nor a clearance test. It is ideally compared with a baseline, and has maximal utility within 72 hours, diminishing to 7 days. Data remain limited in young children, women and diverse populations.
Graduated Return to Sport and to Learn
The rule. Return to sport is stepwise and criteria-based. The athlete progresses only if there is no symptom recurrence at each step, and drops back a stage if symptoms return.
- Symptom-limited activity
- Light aerobic exercise
- Sport-specific exercise
- Non-contact training drills
- Full-contact practice, only after medical clearance
- Return to competition
Return to learn. A stepwise return to school or work and to cognitive load runs in parallel, and generally comes before full return to sport.
Which protocol. Work within the Concussion in Sport Group consensus, using a protocol that is sport-specific and up to date, particularly in high-incidence collision and combat sports.
Risks: Second Impact, Slow Recovery and Repeated Injury
Second-impact syndrome. A rare but catastrophic diffuse cerebral swelling can follow a second head injury sustained before recovery from the first. It is the central reason no athlete returns while symptomatic.
The expected course. Most concussions resolve within about 2 weeks in adults and about 4 weeks in children and adolescents. Symptoms persisting beyond that window are persisting post-concussion symptoms.
Who recovers slowly. These modifiers predict prolonged recovery:
- A high initial symptom burden
- Previous concussions
- A personal or family history of migraine or headache
- Pre-existing anxiety, depression or other mental-health problems
- Learning disability or ADHD
- Female sex
- Younger (adolescent) age
- Prominent acute dizziness, vestibular or neck symptoms
Rehabilitate early. Strict or prolonged "cocoon" rest can worsen recovery. After only the brief initial relative rest, begin early sub-symptom-threshold aerobic exercise and targeted, active rehabilitation within a multidisciplinary approach, rather than waiting passively:
- Cervical physiotherapy
- Vestibulo-ocular rehabilitation
- Autonomic rehabilitation
- Treatment of headache, mood and sleep
Repeated injury. Counsel the athlete on the long-term concern of repeated head injury, including chronic traumatic encephalopathy.
Mnemonics & Memory Aids
HEADS
Hook:HEADS: Hold them out, Exclude structural injury, Assess with SCAT6, Don't rush (graduated return), Second-impact syndrome.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A player takes a blow to the head and seems dazed. How do you manage the suspected concussion on the sideline?”
“Describe the return-to-sport process after concussion and the main risks.”
Evidence & Key Studies
Acute evaluation of sport-related concussion and the SCAT6 (systematic review)
- The Sport Concussion Assessment Tool (SCAT) discriminates concussed from non-concussed athletes, with maximal utility within the first 72 hours of injury and diminishing utility up to 7 days.
- The SCAT has limited utility as a return-to-play tool beyond 7 days, supporting its use in the acute phase as part of (not a substitute for) clinical assessment; more challenging cognitive tests (e.g. 10-word list) were recommended for the SCAT6.
- Acute assessment spans cognition, balance/postural stability and oculomotor/cervical/vestibular function; data are limited in young children, women and diverse populations.
- Scale of the review: 12,192 articles screened and 612 included - 183 on cognition, 126 on balance, 76 on oculomotor/cervical/vestibular function, 142 on emerging technologies and 23 on the paediatric SCAT.
Return-to-play protocols after sport-related concussion across international sporting organisations
- The Concussion in Sport Group (CISG) consensus provides the scientific basis for managing sport-related concussion, including a graduated return-to-play protocol.
- Twelve international contact, collision and combat sport organisations were examined, but ONLY SIX had developed and published their own concussion guidelines including a return-to-play protocol.
- Among those six, the number of steps was similar and each required at least one medical examination before clearance, but there was high variation in the initial resting period, the use of sport-specific training drills and the total time to complete the protocol.
- THE HEADLINE FINDING IS ONE OF NON-COMPLIANCE: at the study date of 9 September 2023, NONE of the accessible return-to-play protocols had been updated to the latest version of the CISG consensus statement.
The role and time-window of the SCAT/SCAT6 (best within 72 hours, diminishing to 7 days, not a stand-alone return-to-play test) and the assessment domains come from the cited Echemendia systematic review; the graduated return-to-play framework, the requirement for medical examination before clearance, the variation across organisations, and the recommendation for up-to-date sport-specific protocols (especially in high-incidence combat sports) from the cited Prock study. The definition (a functional injury with normal structural imaging, LOC not required), the 'if in doubt, sit them out' / no-same-day-return rule, the red flags for CT, the return-to-learn pathway, and second-impact syndrome are standard, well-established teaching (aligned with the Concussion in Sport Group consensus). (See also our Cervical Spine Injury and Burners and Stingers topics.)