INI1/SMARCB1-Deficient Soft Tissue Sarcoma | The Great Mimic | Distal Upper Limb of Young Adults
- Most common soft tissue sarcoma of the hand and distal forearm in young adults - the classic exam trap
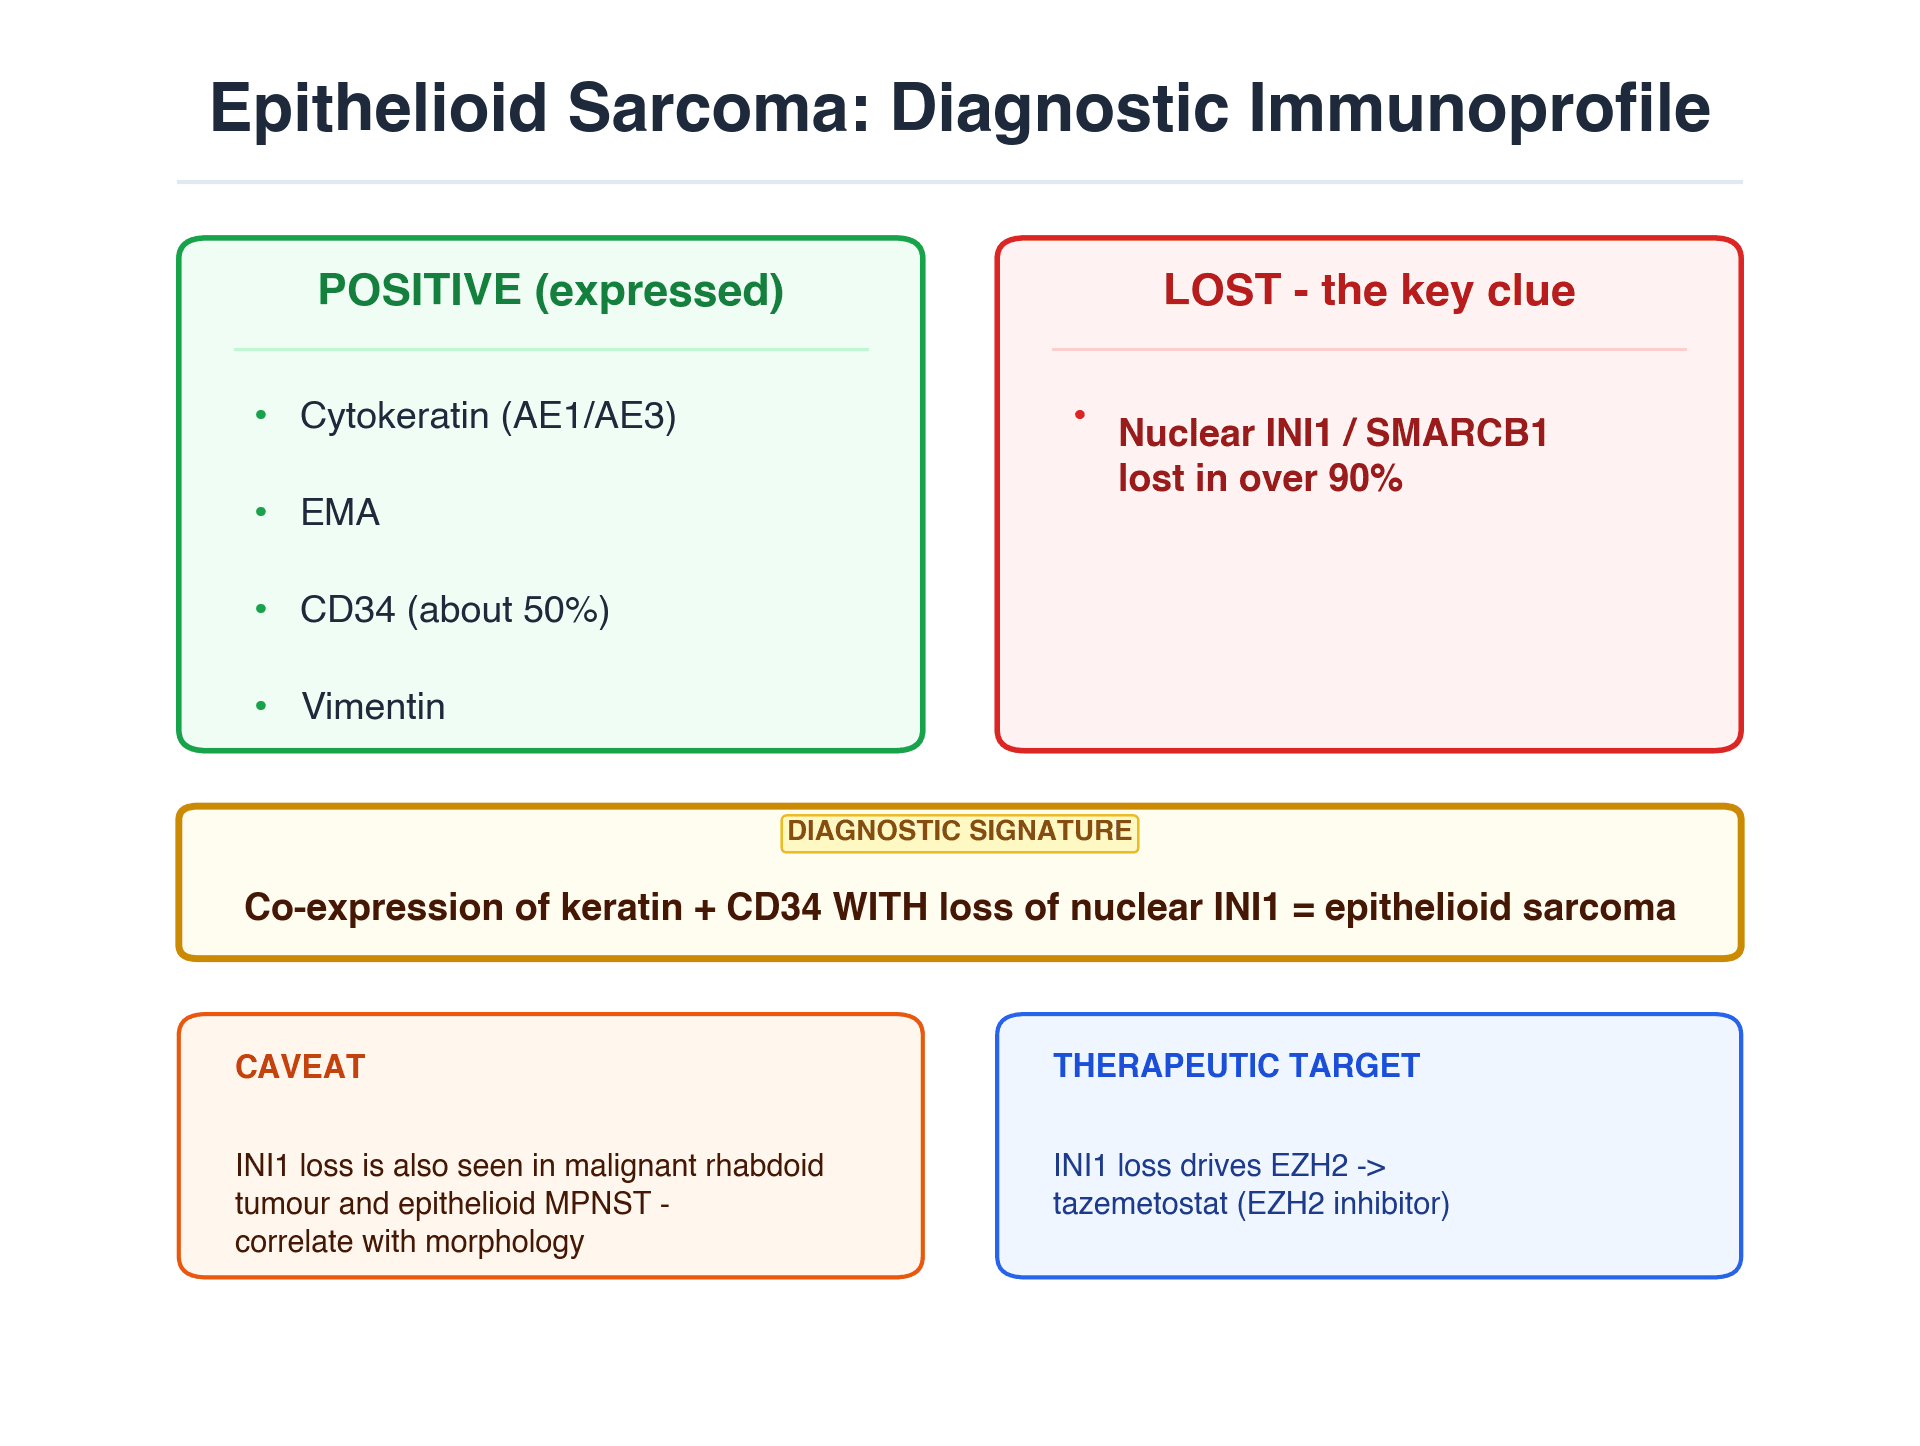
- Loss of nuclear INI1 (SMARCB1) on immunohistochemistry is present in over 90% and is the key diagnostic clue
- Notorious mimic of benign disease (granuloma, abscess, Dupuytren nodule, wart, ulcer) causing long diagnostic delay
- Spreads by three routes: local recurrence, regional lymph nodes (unusual for a sarcoma), and lung
- Treatment is wide excision with negative margins plus radiotherapy; tazemetostat (EZH2 inhibitor) is an option in advanced disease
- “A non-healing ulcer or firm nodule on the hand or forearm of a young adult is epithelioid sarcoma until proven otherwise
- “Unlike most sarcomas, regional lymph node metastasis is a recognised pattern - examine and image the nodes
- “INI1 loss is shared with malignant rhabdoid tumour and epithelioid MPNST, so correlate with morphology and clinical context
- “Late local and distant recurrence is common - this tumour needs prolonged surveillance, not just 5 years
Overview and Epidemiology
Epithelioid sarcoma is a rare malignant soft tissue tumour of uncertain differentiation, best known as the most common soft tissue sarcoma of the hand and distal forearm in young adults and as a notorious mimic of benign disease. The World Health Organization now classifies it among the INI1 (SMARCB1)-deficient tumours, reflecting the loss of nuclear INI1 expression seen in the large majority of cases.
Who gets it. It accounts for under 1% of all soft tissue sarcomas, with a male predominance in most series. The distal (classic) type typically presents at 20-40 years; the proximal type tends to occur in older patients.
Where it arises. Site tracks the variant, and the lesion is frequently superficial.
- Distal upper limb - hand, fingers and forearm, the classic type
- Distal lower limb - foot, ankle and lower leg
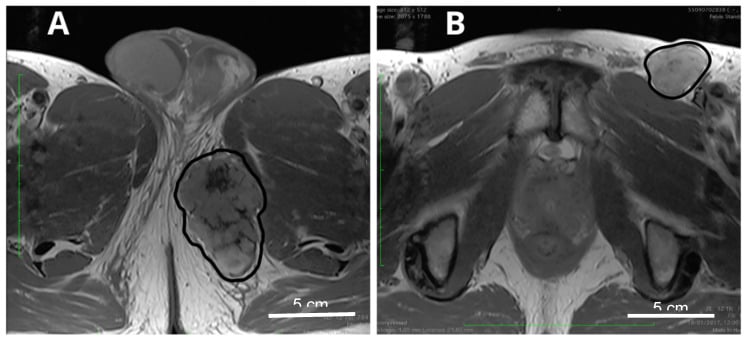
- Proximal and axial sites - pelvis, perineum, genitalia and buttock, the proximal type
- Often dermal or subcutaneous, tracking along fascia and tendon
The delay is the clinical problem. Because it grows slowly and looks unremarkable, patients are repeatedly treated for benign disease for months to years - a granuloma, a chronic abscess, a wart, a Dupuytren nodule or a non-healing ulcer. Any persistent, firm or ulcerating lesion of the distal limb in a young adult must be biopsied rather than observed.
Two variants, not one tumour. Guillou and colleagues defined the proximal-type variant as a distinctive, more aggressive neoplasm showing rhabdoid features, in contrast with the conventional distal type. The pair differ in age, site, architecture and behaviour.
- Distal (classic) type
- Young adults (20-40 years)
- Proximal (large-cell) type
- Older adults (often over 40)
- Distal (classic) type
- Hand, fingers, forearm, foot
- Proximal (large-cell) type
- Pelvis, perineum, genitalia, buttock, deep proximal soft tissue
- Distal (classic) type
- Nodular, granuloma-like with central necrosis
- Proximal (large-cell) type
- Sheets of large rhabdoid/epithelioid cells, multinodular
- Distal (classic) type
- Bland to moderately atypical epithelioid and spindle cells
- Proximal (large-cell) type
- Marked atypia, prominent rhabdoid cells
- Distal (classic) type
- Slow but relentless; high local recurrence
- Proximal (large-cell) type
- More aggressive; earlier and more frequent metastasis
Pathophysiology and Histology
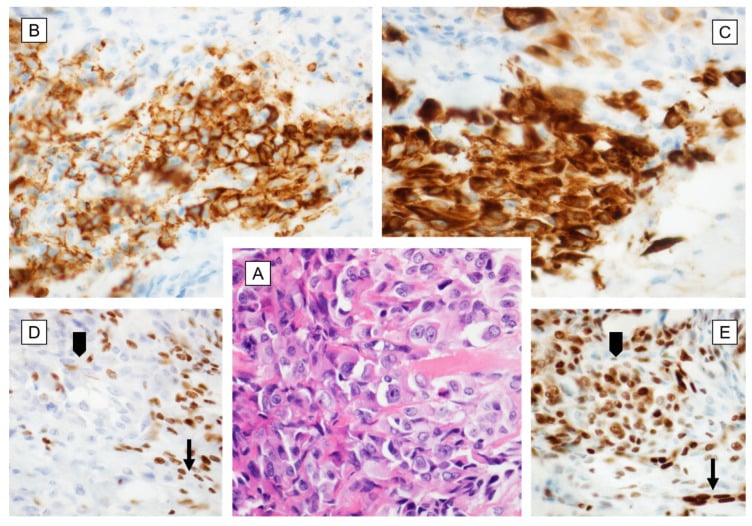
A tumour with an epithelial face. Epithelioid sarcoma is of uncertain differentiation but shows partial epithelial differentiation, co-expressing keratins with the mesenchymal marker vimentin. The morphology carries the same duality, epithelioid cells with a spindled component alongside them.
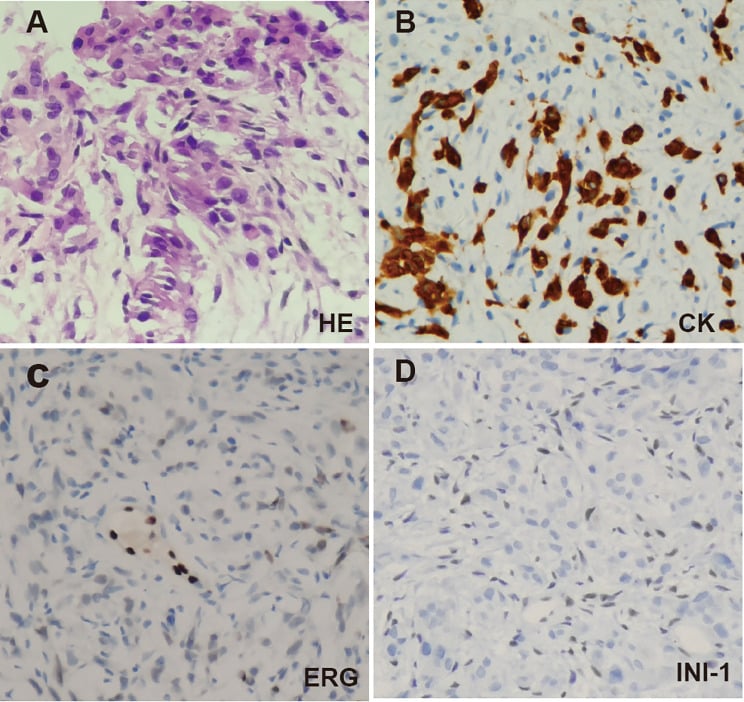
The defining event. Loss of function of SMARCB1 (INI1), a core subunit of the SWI/SNF chromatin-remodelling complex that normally acts as a tumour suppressor. SMARCB1 - also called INI1, SNF5 or BAF47 - is encoded at 22q11.2, and biallelic inactivation leaves no nuclear protein to stain: loss of nuclear INI1 on immunohistochemistry is demonstrable in over 90% of cases.
Why the loss is targetable. SMARCB1 loss removes the normal antagonism of EZH2, a transcriptional repressor, and the tumour becomes oncogenically dependent on it. That dependence is the rationale for the EZH2 inhibitor tazemetostat. A minority of cases retain INI1, and in those other SWI/SNF subunits may be abnormal.
Loss of nuclear INI1 strongly supports epithelioid sarcoma in the right context, but it is not unique to it. Malignant rhabdoid tumour, epithelioid MPNST and a few carcinomas also show INI1 loss. Diagnosis therefore rests on the combination of clinical setting, morphology (epithelioid and rhabdoid cells), keratin/EMA and CD34 co-expression, and INI1 loss together.
Distal type: the granuloma trap. Nodules of tumour cells with central necrosis are the classic architecture, and at low power they resemble a necrotising granuloma such as a rheumatoid nodule or an infection. The cells track along fascia, tendon sheaths and dermis, and that slow infiltrative spread is what makes recurrence so common.
- A mixture of epithelioid and spindle cells, with transition between the two forms; the peripheral spindle-cell component can be conspicuous
- Eosinophilic cytoplasm, with relatively bland to moderate atypia
- Mitoses present, but they may be inconspicuous
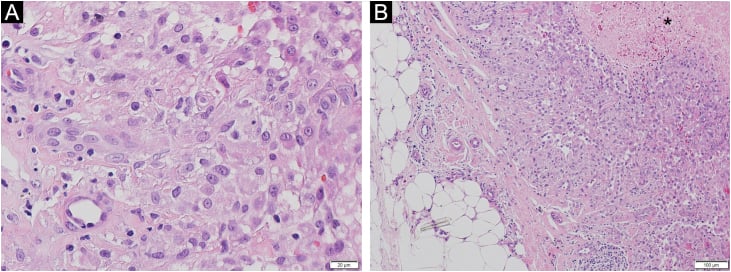
A young adult with a firm hand or forearm nodule reported as granulomatous inflammation deserves a second look with INI1 immunohistochemistry. A limited biopsy of this pseudogranulomatous architecture can be misread as inflammation.
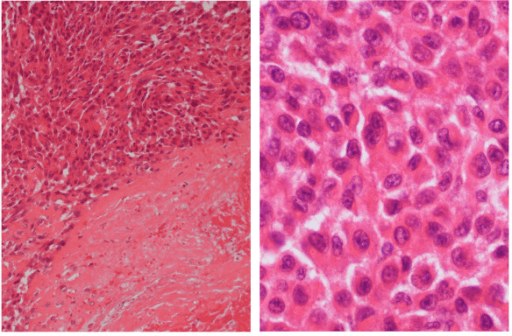
Proximal type: sheets of rhabdoid cells. Deeper and larger multinodular masses of large cells with frequent necrosis, in which the granuloma-like pattern is usually absent. The cells are rhabdoid - eccentric nuclei with inclusion-like cytoplasm - with marked nuclear atypia, prominent nucleoli, and higher grade and mitotic activity, which is where the morphological overlap with malignant rhabdoid tumour comes from.
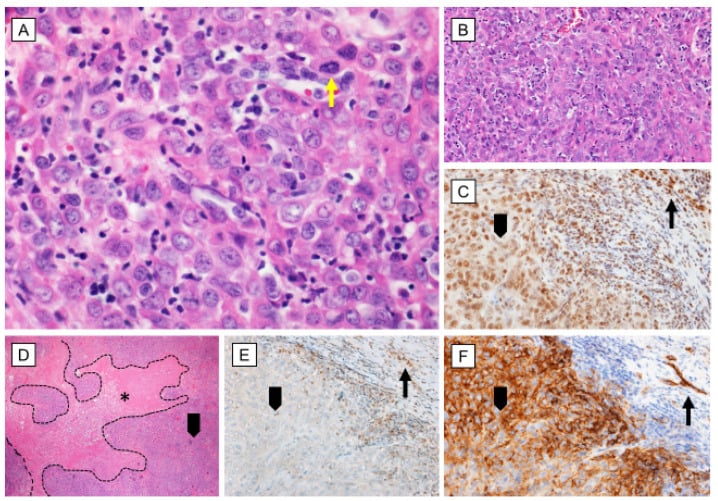
The immunoprofile. One stain is read for loss; the rest are read for expression.
- Typical Result
- Lost in over 90%
- Diagnostic Value
- Key clue - loss supports the diagnosis
- Typical Result
- Positive
- Diagnostic Value
- Epithelial differentiation
- Typical Result
- Positive
- Diagnostic Value
- Epithelial differentiation
- Typical Result
- Positive
- Diagnostic Value
- Mesenchymal origin (co-expressed with keratin)
- Typical Result
- Positive in around half
- Diagnostic Value
- Helps distinguish from carcinoma (carcinomas are CD34 negative)
- Typical Result
- Negative
- Diagnostic Value
- Helps exclude melanoma and many nerve sheath tumours
Keratin and EMA positivity with CD34 positivity and INI1 loss together is highly characteristic, because true carcinomas are almost always CD34 negative. CD34 is variably expressed, though, so a negative result does not exclude epithelioid sarcoma; keratin expression plus INI1 loss and compatible morphology carries more weight.
The differential. The entities that overlap morphologically are separated by the immunopanel and by the clinical setting.
- Overlapping Features
- Nodular pattern with central necrosis
- Key Discriminator
- No cytological atypia, no keratin/CD34, INI1 retained
- Overlapping Features
- Keratin and EMA positive, epithelioid cells
- Key Discriminator
- Carcinomas are usually CD34 negative and retain INI1
- Overlapping Features
- Rhabdoid cells, INI1 loss
- Key Discriminator
- Younger children, deep/axial, no granuloma-like pattern
- Overlapping Features
- Epithelioid cells, can lose INI1
- Key Discriminator
- Arises from nerve/neurofibromatosis, S100 often positive
- Overlapping Features
- Epithelioid cells, atypia
- Key Discriminator
- S100, SOX10 and melanocytic markers positive; INI1 retained
- Overlapping Features
- Epithelioid cells, can express keratin
- Key Discriminator
- Vascular markers (CD31, ERG) positive; INI1 retained
Clinical Presentation
The typical story. The commonest presentation is a firm, painless nodule in skin or subcutis, usually in the hand, fingers or forearm of a young adult, enlarging slowly and sometimes with satellite nodules around it. A non-healing ulcer over such a nodule is the classic picture and the most misleading one.
What should raise suspicion. The history is usually longer than the lesion looks.
- Symptoms for months to years before diagnosis
- A lesion already "treated" as a wart, an abscess, a granuloma or Dupuytren disease
- Recurrence after a presumed benign excision
- Palpable regional lymph nodes
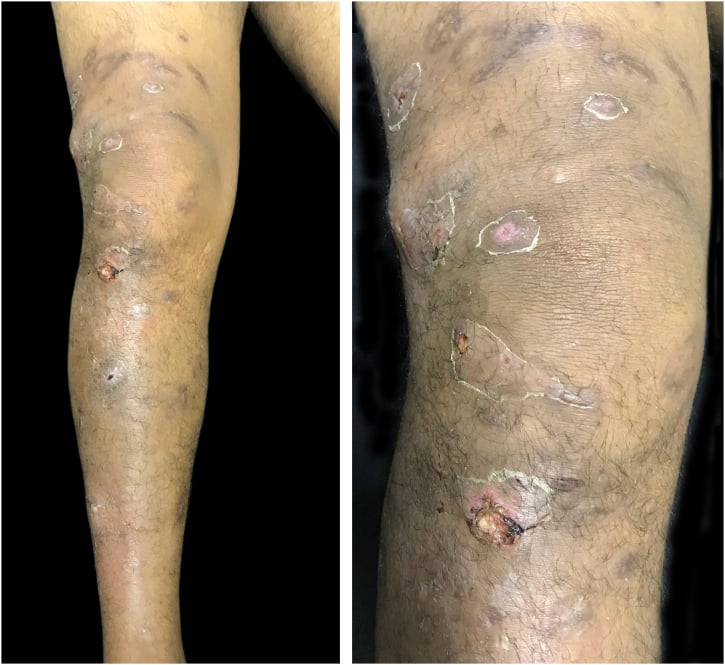
Marginal or piecemeal excision of an unsuspected epithelioid sarcoma is a disaster - it leaves contaminated tissue, seeds the field, and compromises later limb-salvage surgery. Any indeterminate persistent hand or forearm lesion should be imaged and biopsied with a planned tract before any excision is contemplated.
Examination of the lesion. Inspect for nodules, ulceration, the scar of a previous excision, and satellite lesions running along lymphatics or fascia; the site itself is a clue, since a distal limb lesion favours the classic type. Palpate for consistency - firm to hard, and fixed to deep tissue where it is infiltrative, with mild tenderness at most - and for the relationship to tendons and neurovascular structures.
Then examine the nodes, every time. Palpate the draining basin, epitrochlear, axillary or inguinal, because nodal metastasis is a recognised pattern in this tumour, and document any palpable node so it can be staged and biopsied. Finish with neurovascular status distal to the mass and with joint movement and hand function, which is the baseline against which any reconstruction is planned.
Investigations and Imaging
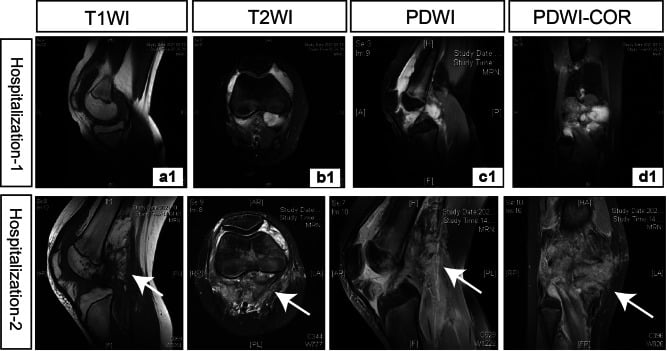
MRI of the whole compartment is the standard for local staging of any suspected soft tissue sarcoma. It defines the tumour, guides a safe biopsy tract and shapes the resection plan.
- T1 - anatomical detail, tumour extent, and the relation to tendons and the neurovascular bundle
- T2 with fat suppression - usually intermediate to high signal, heterogeneous
- Post-contrast - heterogeneous enhancement, sometimes in a nodular or multifocal pattern
- Satellite nodules and tracking along fascia - the clue to infiltrative spread
Plain radiographs remain the screening film for any soft tissue mass. They may show adjacent bone erosion where a superficial tumour abuts bone, in a digit for instance, and calcification is occasionally present. A normal radiograph does not exclude the diagnosis, so move on to MRI.
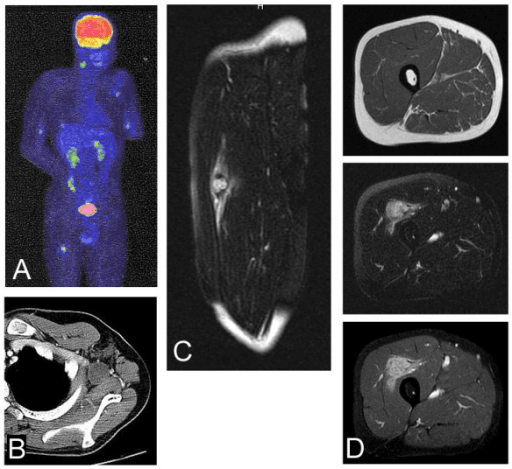
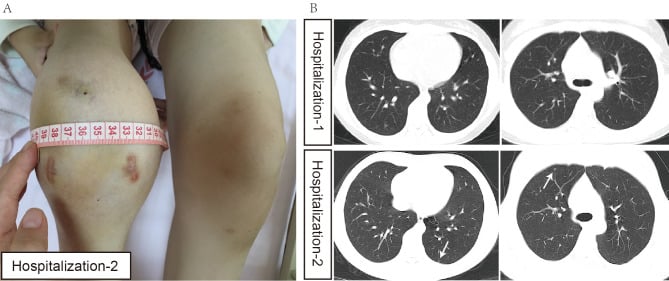
Staging follows the three routes. Epithelioid sarcoma has a distinctive triple pattern of spread, so staging must cover all three rather than the chest alone.
- Assessment
- MRI of the primary site
- Why it matters
- High recurrence rate even after excision
- Assessment
- Clinical exam, nodal ultrasound/MRI, biopsy of suspicious nodes
- Why it matters
- Nodal spread is unusually common for a sarcoma and worsens prognosis
- Assessment
- CT chest
- Why it matters
- Lung is the dominant site of distant metastasis
- Assessment
- FDG-PET/CT in selected cases
- Why it matters
- Detects occult nodal and distant disease
Biopsy and Diagnosis
Core needle biopsy at, or after discussion with, a specialist sarcoma centre is the standard. Plan the tract so that it can be excised en bloc at definitive surgery; the biopsy is part of the operation.
- Use a longitudinal approach on the limb; avoid transverse incisions
- Provide adequate tissue for morphology and immunohistochemistry (including INI1)
- Request INI1/SMARCB1 staining when epithelioid sarcoma is considered
- Never perform an unplanned marginal excision of an undiagnosed lesion
Grading and staging use the same framework as any extremity or trunk soft tissue sarcoma, read with this tumour's habits in mind.
- How it is assessed
- FNCLCC grade (differentiation, mitoses, necrosis)
- Note for epithelioid sarcoma
- Many tumours are high grade, especially proximal type
- How it is assessed
- Size and depth
- Note for epithelioid sarcoma
- Often superficial but infiltrative; size is prognostic
- How it is assessed
- Regional lymph nodes
- Note for epithelioid sarcoma
- Nodal disease (N1) is a recognised pattern and upstages prognosis
- How it is assessed
- Distant disease, chiefly lung
- Note for epithelioid sarcoma
- Lung is the dominant distant site
For most soft tissue sarcomas nodal spread is rare and is treated as advanced disease. In the AJCC 8th edition staging of extremity and trunk soft tissue sarcoma, regional node involvement (N1) is classified as Stage IV, the same category as distant metastasis, which is why nodal status is decisive here. The handful of sarcomas that genuinely metastasise to nodes are worth memorising as a group (CARE): Clear cell sarcoma, Angiosarcoma (including epithelioid variants), Rhabdomyosarcoma, Epithelioid sarcoma - with synovial sarcoma sometimes added. For all of these, nodal examination and imaging are an explicit part of staging, unlike the great majority of soft tissue sarcomas in which nodes are rarely involved.
Because epithelioid sarcoma spreads to nodes, the natural question is whether the clinically and radiologically node-negative patient should have a sentinel lymph node biopsy (SLNB). SLNB is technically feasible and has been studied in the node-metastasising sarcomas (epithelioid and clear cell sarcoma, rhabdomyosarcoma), and it does identify occult nodal disease in a proportion of patients. However, the evidence that it improves survival is weak, it is not part of routine soft-tissue-sarcoma staging, and major guidelines (ESMO, NCCN) do not mandate it. The pragmatic position is meticulous clinical and cross-sectional nodal staging for every patient, biopsy of any suspicious node, and SLNB considered only selectively (often within a sarcoma centre or trial). Confirmed nodal disease is then managed with therapeutic dissection rather than routine elective node clearance.
Management
Complete surgical removal with negative margins offers the best chance of cure. Because epithelioid sarcoma infiltrates and recurs locally, wide excision is preferred and radiotherapy is added for most deep, large or marginally resected tumours. Systemic therapy is reserved largely for advanced or metastatic disease.
Treatment by scenario. Wide local excision with negative margins is the priority in every row of the table below. Biopsy-proven nodal disease adds a therapeutic node dissection at a sarcoma centre, and systemic therapy belongs to unresectable, metastatic or relapsed disease.
- Surgery
- Wide excision with negative margins; limb salvage preferred
- Radiotherapy
- Adjuvant for deep/large tumours or close margins
- Systemic Therapy
- Generally none for small low-risk tumours
- Surgery
- Consider ray amputation or more proximal amputation for clearance
- Radiotherapy
- Pre- or postoperative as indicated
- Systemic Therapy
- Consider in high-risk disease at MDT
- Surgery
- Wide excision of primary plus therapeutic node dissection
- Radiotherapy
- Adjuvant to primary and/or nodal basin
- Systemic Therapy
- Discuss systemic therapy at MDT
- Surgery
- Resection of primary or oligometastases if feasible
- Radiotherapy
- Palliative local control
- Systemic Therapy
- Tazemetostat (EZH2 inhibitor) or anthracycline-based chemotherapy
Plan the resection from the MRI, en bloc. The infiltrative, multinodular pattern demands it rather than shelling out the visible mass.
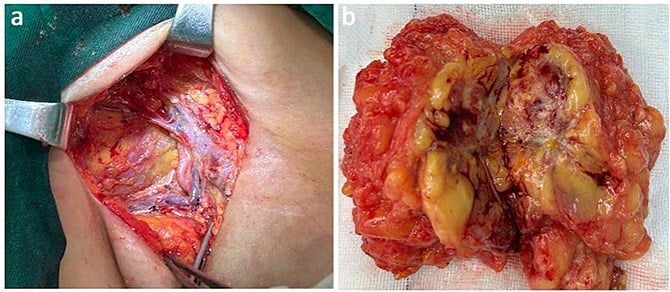
Where radiotherapy fits. It is considered for close or positive margins, for large or recurrent tumours, and in anatomically constrained sites, and it can be delivered stereotactically to oligometastases. It does not replace adequate surgery when a clear margin is achievable.
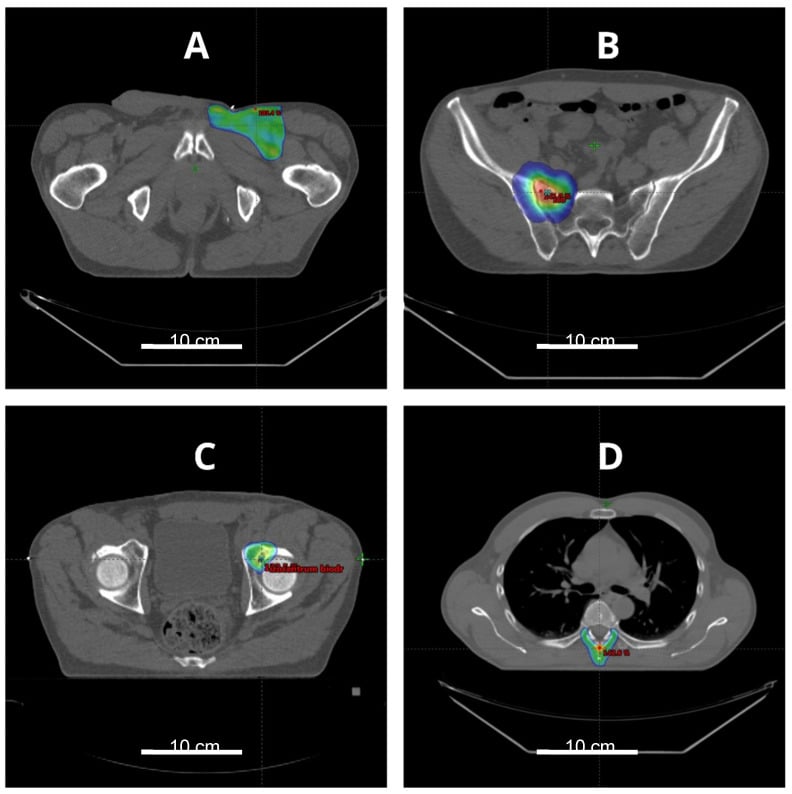
Systemic therapy and the EZH2 target. The dependence of INI1-deficient epithelioid sarcoma on EZH2 has been translated into a licensed targeted therapy. The EZH2 inhibitor tazemetostat was studied in a phase 2 basket of 62 patients with advanced INI1-negative disease: the objective response rate was 15% and median progression-free survival 5.5 months, but the responses that occurred were durable (median duration not reached) and the drug was well tolerated, which is what drove regulatory approval for advanced disease not amenable to complete resection. Say it plainly: tazemetostat is a well-tolerated disease-control drug with a low response rate, not a tumour-shrinking one - and conventional anthracycline-based chemotherapy is in the same position, so the choice in the palliative setting is genuinely open.
Complications and Surveillance
Failure comes by the same three routes as spread, with time added: relapse can arrive years after treatment.
- Frequency / Pattern
- Common, often repeated
- Drivers
- Infiltrative growth, marginal excision, satellite nodules
- Management
- Re-excision with wider margins; amputation if limb salvage fails
- Frequency / Pattern
- Recognised pattern (unusual for a sarcoma)
- Drivers
- Aggressive biology, proximal type, high grade
- Management
- Node biopsy and therapeutic dissection; adjuvant therapy
- Frequency / Pattern
- Dominant distant site
- Drivers
- High-risk and proximal-type tumours
- Management
- Systemic therapy; metastasectomy in selected oligometastatic cases
- Frequency / Pattern
- May occur years after treatment
- Drivers
- Indolent component of tumour biology
- Management
- Prolonged surveillance beyond the usual 5 years
Surveillance must include the regional nodal basin (clinical and imaging) as well as the local site and the chest, because of the triple spread pattern. Late recurrences mean follow-up should continue well beyond five years.
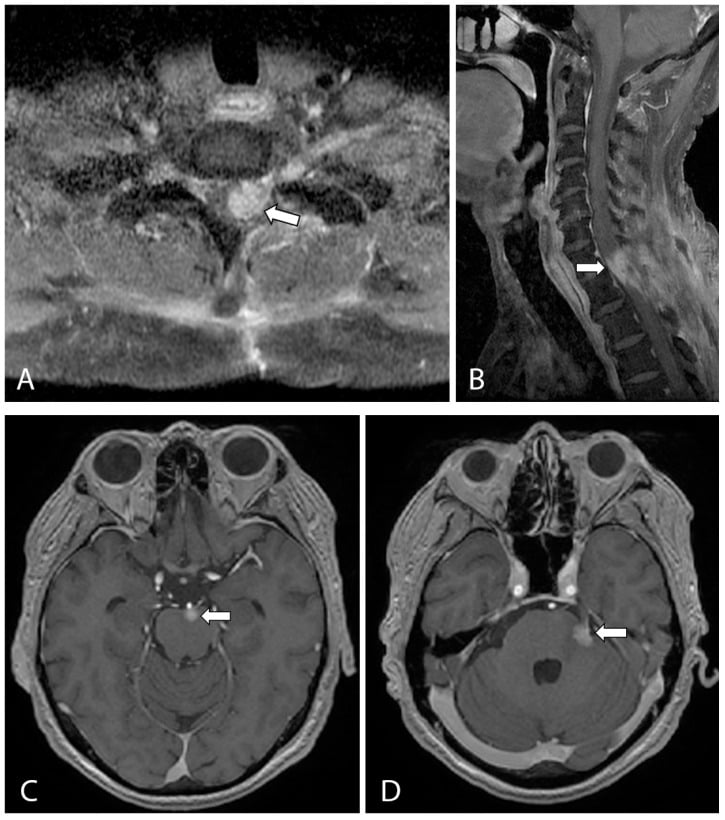
Unusual metastatic sites do occur, and are pursued with symptom-directed cross-sectional imaging.
Prognosis and Outcomes
The factors that predict outcome fall into three groups: what the tumour is (variant, grade, the presence of rhabdoid cells), where it sits (superficial and small against deep and large), and what has happened to it (the margin achieved, the nodes, distant disease).
- Favourable
- Distal (classic) type
- Unfavourable
- Proximal (large-cell) type
- Favourable
- Node negative (N0)
- Unfavourable
- Node positive (N1)
- Favourable
- No metastases
- Unfavourable
- Metastatic (M1)
- Favourable
- Wide negative margin
- Unfavourable
- Marginal/positive margin
- Favourable
- Superficial, small
- Unfavourable
- Deep, large
- Favourable
- Lower grade
- Unfavourable
- High grade with rhabdoid cells
Across series, lymph node or distant metastasis has the most critical impact on survival, and proximal-type disease behaves more aggressively with earlier metastasis and poorer overall survival than the classic distal type.
One reconciliation is worth noticing. The multi-institutional series of 44 patients in the evidence base found that the proximal subtype only trended towards a worse outcome and the difference did not reach significance, while nodal and distant metastasis were independent predictors. The variant colours the prognosis; the metastatic status settles it.
Guidelines, Registries & Global Practice
Global Epidemiology
- Rarity: Under 1% of all soft tissue sarcomas worldwide
- Age: Distal type peaks in young adults; proximal type tends to be older
- Sex: Male predominance in most reported series
- Distal type: A leading hand and forearm soft tissue sarcoma in young adults
- Triple spread: Local recurrence, regional nodes and lung
- Nodal metastasis: Reported in roughly a third of localized cases in tertiary series
- Late relapse: Disease-specific survival falls substantially between 5 and 10 years
- Variant matters: Proximal type carries worse outcomes than distal type
Side-by-Side Principles from Major Sarcoma Frameworks
- Diagnosis
- Refer to a sarcoma centre before biopsy; confirm INI1 loss
- Local Treatment
- Wide excision with radiotherapy for deep/larger tumours; assess nodes
- Systemic / Advanced Disease
- Anthracycline-based chemotherapy; targeted EZH2 inhibition for INI1-deficient disease
- Diagnosis
- Image-guided core biopsy at a sarcoma centre; INI1 testing
- Local Treatment
- Limb-sparing wide excision plus radiotherapy; re-excision for positive margins
- Systemic / Advanced Disease
- Tazemetostat is an option for advanced INI1-deficient epithelioid sarcoma
- Diagnosis
- Mandatory specialist sarcoma MDT before definitive treatment
- Local Treatment
- Centralized surgery and radiotherapy at designated centres
- Systemic / Advanced Disease
- Systemic therapy and trials for advanced disease at specialist centres
Every major framework agrees: any persistent or enlarging deep/atypical soft tissue lesion should be referred to a specialist sarcoma centre before biopsy, diagnosis should include INI1/SMARCB1 testing, and definitive management should be planned by a multidisciplinary sarcoma team. For epithelioid sarcoma specifically, nodal assessment is an explicit part of staging.
High- vs Limited-Resource Practice Variation
- Routine INI1 immunohistochemistry and molecular confirmation
- Centralized sarcoma MDTs with limb-salvage surgery and reconstruction
- MRI staging, CT chest and FDG-PET access
- Availability of tazemetostat for advanced INI1-deficient disease
- Diagnosis may rely on morphology and a limited immunopanel; INI1 not always available
- Later presentation with larger tumours and higher amputation rates
- Restricted radiotherapy and targeted-therapy access
- Telepathology and regional referral networks help bridge expertise gaps
Applicable in any health system:
- Document a clear investigation pathway for any persistent distal-limb nodule or non-healing ulcer (the common delayed-diagnosis pitfall)
- Confirm pre-biopsy staging and that biopsy was planned with the definitive surgeon
- Record that INI1/SMARCB1 testing and nodal assessment were performed
- Evidence of sarcoma MDT discussion before definitive treatment
- Informed consent covering wide excision, possible amputation, radiotherapy and recurrence/metastatic risk
- A written long-term surveillance plan that extends beyond 5 years given late relapse
MCQ Practice Points
Q: What is the characteristic immunohistochemical finding in epithelioid sarcoma? A: Loss of nuclear INI1 (SMARCB1) in over 90% of cases, together with co-expression of cytokeratin/EMA and CD34. CD34 positivity helps distinguish it from carcinoma, which is usually CD34 negative. INI1 loss is shared with malignant rhabdoid tumour and epithelioid MPNST.
Q: What is the most common soft tissue sarcoma of the hand and distal forearm in a young adult? A: Epithelioid sarcoma (distal/classic type). It is the great mimic, often misdiagnosed as a granuloma, abscess, wart or non-healing ulcer, leading to long diagnostic delay.
Q: How does the metastatic pattern of epithelioid sarcoma differ from most soft tissue sarcomas? A: It shows a triple pattern - local recurrence, regional lymph nodes, and lung. Nodal spread is unusual for sarcomas but a recognised feature here, so nodal staging is part of routine workup.
Q: Which targeted agent is approved for advanced INI1-deficient epithelioid sarcoma and why? A: Tazemetostat, an EZH2 inhibitor. Loss of SMARCB1 makes the tumour oncogenically dependent on EZH2, and a phase 2 basket study showed durable responses with good tolerability in advanced disease.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 26-year-old man is referred with a firm 2 cm nodule on the volar aspect of his forearm that has been present for over a year. It was treated as a wart and then a chronic abscess. There is now superficial ulceration. How do you approach this?”
“A 48-year-old woman has a biopsy-proven epithelioid sarcoma of the buttock and perineal region, 9 cm, deep, with rhabdoid cells and loss of INI1. She has a palpable, firm inguinal lymph node. How do you manage her?”
“A 31-year-old man had a finger nodule excised elsewhere and the histology now reports epithelioid sarcoma with positive margins. He has re-presented six months later with new nodules near the scar. How do you proceed?”
Key Epidemiology
- Under 1% of all soft tissue sarcomas - very rare
- Most common soft tissue sarcoma of the hand and distal forearm in young adults (distal type)
- Male predominance; distal type peaks 20-40 years, proximal type older
- The great mimic - often misdiagnosed as granuloma, abscess, wart or non-healing ulcer
Two Variants
- Distal (classic): young adults, hand/forearm, nodular granuloma-like pattern with necrosis
- Proximal (large-cell): older patients, pelvis/perineum/genitalia, rhabdoid cells, more aggressive
- Proximal type metastasises earlier and has worse prognosis
Pathology and Diagnosis
- Loss of nuclear INI1 (SMARCB1) in over 90% - key diagnostic clue
- Co-expression of cytokeratin/EMA and vimentin; CD34 positive in around half
- CD34 positivity helps distinguish from carcinoma (usually CD34 negative)
- INI1 loss is shared with malignant rhabdoid tumour and epithelioid MPNST - correlate with context
Spread and Staging
- Triple pattern: local recurrence, regional lymph nodes, and lung
- Nodal metastasis is unusual for a sarcoma but a recognised feature here - stage the nodes
- MRI of the compartment for local staging; CT chest for lung; FDG-PET in selected cases
- Nodal (N1) and distant (M1) disease are the strongest adverse prognostic factors
Treatment
- Wide local excision with negative margins is the backbone of cure
- Adjuvant radiotherapy for deep/large tumours or close/positive margins
- Therapeutic lymph node dissection for biopsy-proven nodal disease
- Tazemetostat (EZH2 inhibitor) for advanced INI1-deficient disease; anthracycline chemotherapy an alternative
- Avoid unplanned marginal excision - it drives recurrence and compromises limb salvage
Prognosis and Surveillance
- Outcome driven by nodal/distant spread and by variant (proximal worse than distal)
- High local recurrence rate, often repeated
- Late relapse occurs - disease-specific survival falls further beyond 5 years
- Surveillance must cover the local site, the nodal basin and the chest, and continue beyond 5 years
Evidence Base and Key Studies
Definition of Proximal-Type Epithelioid Sarcoma
- Described 18 cases of a distinctive aggressive neoplasm with epithelioid and rhabdoid features, median age 35.5 years
- Most tumours arose in proximal/axial sites (pelvis, perineum, pubic and vulvar region, buttock)
- Cells co-expressed cytokeratin, EMA and vimentin; many were CD34 positive, defining the immunoprofile
- Follow-up showed metastatic dissemination in 6 of 14 patients leading to death in 5, supporting aggressive behaviour
Prognostic Variables in Epithelioid Sarcoma (44 Patients)
- Multi-institutional retrospective study of 44 patients (26 classic-type, 18 proximal-type)
- Overall survival at 5 years was 45% for the whole cohort
- Lymph node (N1) and distant (M1) metastasis were the strongest independent predictors of poor distant metastasis-free and overall survival
- Superficial location and N1 disease independently predicted local recurrence-free survival; proximal subtype trended to worse outcome
Clinical Behaviour and Molecular Markers (116 Patients)
- Database of 116 epithelioid sarcoma and unclassified sarcoma with epithelioid features patients treated since 1992
- Localized epithelioid sarcoma showed 22% local recurrence, 35% nodal metastasis and 41% distant metastasis rates
- Five- and ten-year disease-specific survival were 88% and 43%, underlining a propensity for late relapse
- INI1 loss was significantly more common in epithelioid sarcoma than in unclassified epithelioid sarcomas