Nail Bed Repair and Local Flaps
- Defects less than 1cm with NO exposed bone heal excellently by secondary intention.
- Exposed bone requires flap coverage or shortening.
- The Germinal Matrix produces the nail plate; the Sterile Matrix allows adherence.
- Germinal Matrix scarring causes SPLIT nail.
- Sterile Matrix scarring causes NON-ADHERENT nail.
- A Hook Nail results from loss of bony support to the nail bed tip.
- Subungual hematoma greater than 50% does NOT mandate removal unless nail plate is disrupting the fold.
- “Moberg flap is for the THUMB only (Dorsal blood supply allows volar advancement).
- “Never advance Volar skin on a standard finger greater than 1cm (Necrosis risk).
- “Trephination is for pain relief, not volume reduction.
Overview
Definition. A fingertip injury is one distal to the insertion of flexor digitorum profundus and the extensor tendon. That territory holds two specialised organs, the nail complex and the highly sensate digital pulp, and it is the commonest injury in the hand.
The goal. Treatment aims to restore a functional, sensate and non-painful tip. Flap reconstruction is elegant, but for small defects simple healing by secondary intention often gives the better functional and cosmetic result.
What a reconstructed tip must be. Sensate, with useful tactile gnosis; painless, meaning no neuroma; durable, meaning thick padding; and stable, so the pulp does not shift under pinch. Every option below is judged against those four.
Pathophysiology and Mechanisms
The perionychium. The nail plate is hard keratin. It is made almost entirely by the germinal matrix, the proximal part of the nail bed lying under the fold and extending proximally as far as the insertion of the extensor tendon; it produces 90% of the plate, so injury here stops the nail growing or splits it. The sterile matrix is the distal part of the bed, under the plate and distal to the lunula, and it produces only a thin layer of keratin whose job is to keep the plate stuck to the bed; scar here gives a non-adherent nail.
The surrounding skin has its own names. The hyponychium is the thickened skin at the distal edge and a barrier to infection; the eponychium is the dorsal fold, the cuticle; the paronychium is the lateral fold on each side.
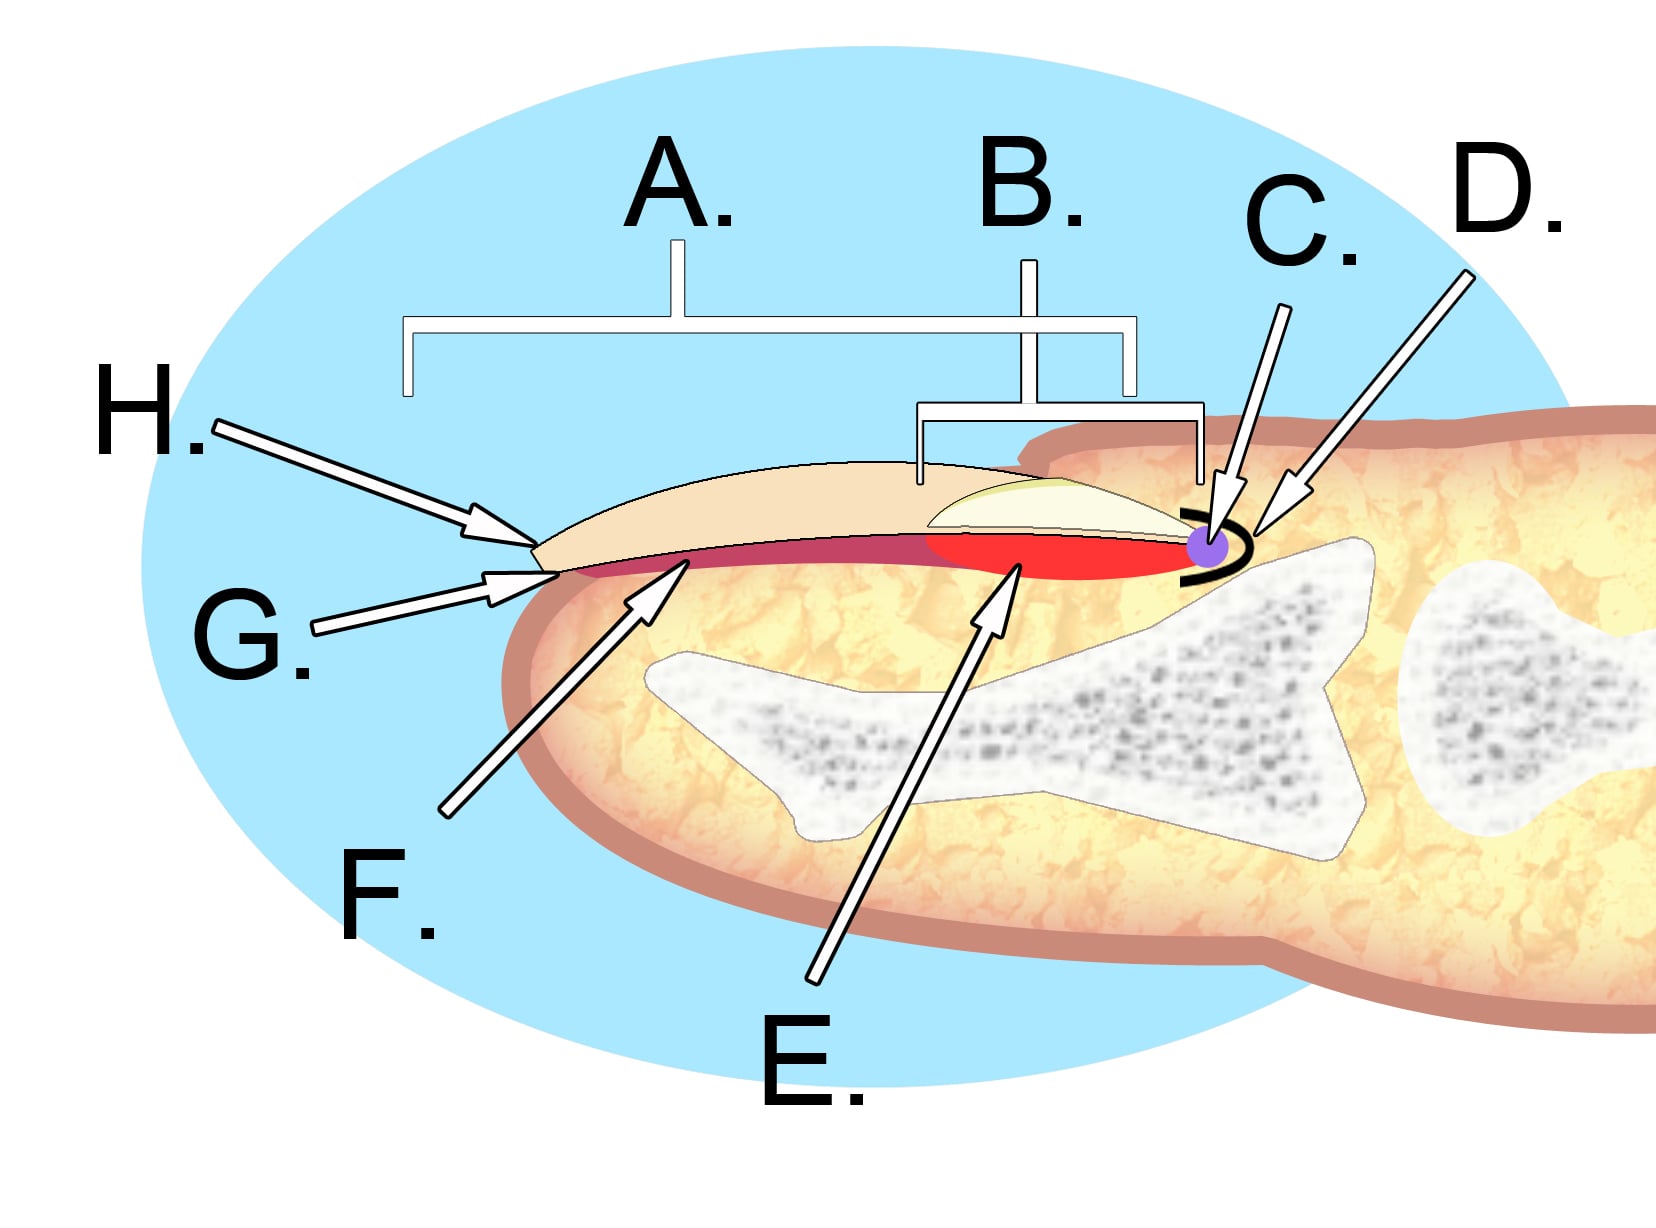
Nail growth. A fingernail grows about 0.1mm a day, roughly 3mm a month, so the whole plate is replaced in about 100 days, three to four months. Toenails grow at half that speed.
The pulp. The pulp is highly specialised skin stabilised by Cleland's and Grayson's ligaments. Its fibrous septae stop the skin shearing under load, and they also contain infection, the pulp abscess or felon. Once the septae are disrupted the pulp moves like a bag of fluid. Sensibility is paramount: two-point discrimination is 2-4mm.
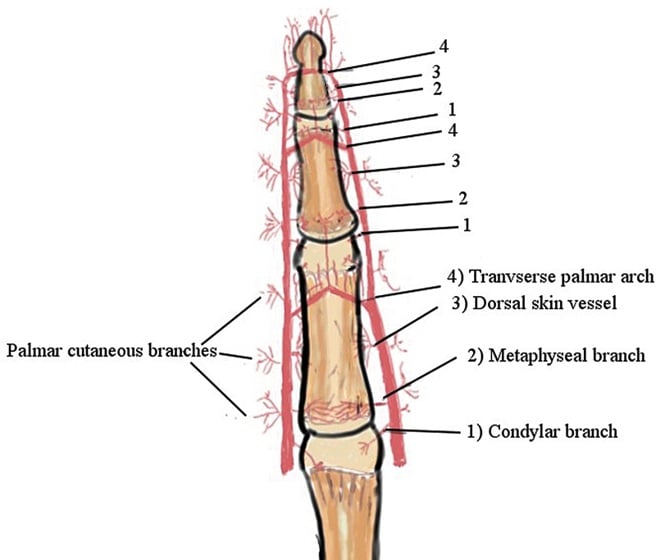
Blood supply. The digital arteries trifurcate at the level of the DIPJ. A dorsal branch supplies the nail matrix, a volar branch the pulp, and an arcade connects the two sides distally. That rich anastomosis is what lets a flap like the Atasoy survive on nothing more than subcutaneous perforators.
Classification Systems
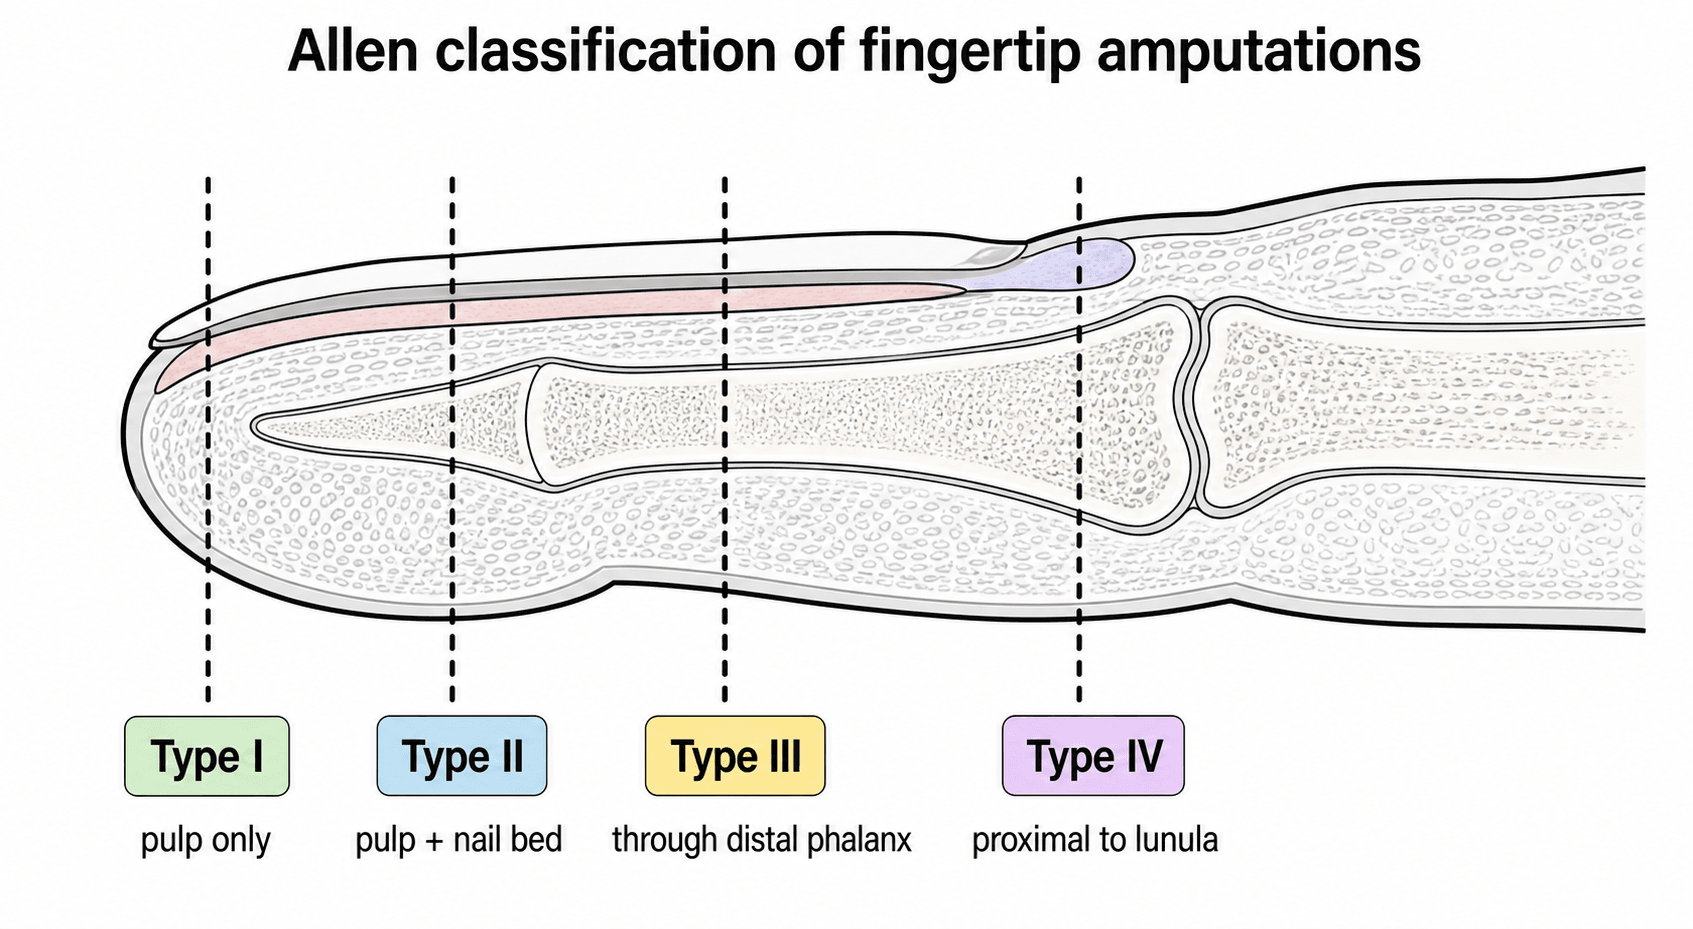
Allen. The level of tissue loss, from distal to proximal, decides how much can be left to heal and how much needs bone or a flap. Types I and II are the most amenable to conservative management; the more proximal the level, the more often bone shortening or flap coverage is needed.
- Level
- Pulp only
- Bone
- No bone exposed
- Level
- Pulp and nail bed
- Bone
- Bone exposed
- Level
- Partial loss of the distal phalanx
- Bone
- Through bone
- Level
- Proximal to the lunula
- Bone
- Germinal matrix lost
Geometry. The angle of the cut decides which local flap, if any, will reach:
- Transverse - a guillotine cut
- Dorsal oblique - more nail lost than pulp; a V-Y flap can be used
- Volar oblique - more pulp lost than nail; harder to treat because there is not enough pulp left for a V-Y
- Lateral - a side slice
Volar oblique injuries have the worst prognosis for local flap coverage.
Clinical Presentation and Assessment
Presentation. The patient arrives acutely after a mechanism they remember clearly: a crush in a door or under a hammer, a sharp laceration from a knife or saw, or an avulsion from a ring or a pull. They report throbbing pain, bleeding and an obvious deformity or loss of tissue. The clinical task is rapid triage into a treatable category: is there exposed bone, is the nail bed disrupted, and is there a concealed tendon injury shown by loss of active DIP flexion or extension?
History. The mechanism predicts the injury: a crush bursts the nail bed, a laceration cuts it cleanly, an avulsion pulls. The rest of the history decides what the patient needs from the tip and how well they will heal.
- Time since injury - clean wounds can be closed up to 12-24 hours
- Occupation - a manual labourer needs a durable tip; a pianist needs sensation and shape
- Hand dominance - the index finger and thumb are critical
- Hobbies - musical instruments, sport, fine motor activities
- Smoking - a risk for flap necrosis, and cessation is critical if a Moberg or Atasoy flap is planned; counsel now
- Diabetes - impaired healing and infection risk
- Medications - anticoagulants, immunosuppressants
Red flags. Each of these needs urgent specialist referral:
- Tendon injury - inability to flex the DIP means a lost FDP, a zone 1 injury
- Jersey finger - FDP avulsion with a bone fragment, seen as a volar fragment on the radiograph
- Mallet finger - extensor avulsion with a DIP droop
- Vascular compromise - a cool, pale or cyanotic digit
- Compartment syndrome - rare in the fingertip; consider it after a severe crush
- High-pressure injection - paint or grease under pressure needs emergent debridement
Examination. Test sensation first, two-point discrimination against a normal of 2-4mm, and document it before any lignocaine goes in. Then perfusion: capillary refill, temperature, and an Allen's test to the digits.
- Bone exposure - look carefully and probe the wound; small exposed tufts may granulate
- Nail bed - subungual haematoma, laceration or avulsion
- Nail plate - intact, lacerated, or avulsed from the fold
- Tendons - confirm FDP and extensor function if the injury is proximal to their insertions
- Defect size - measure it in millimetres; it drives the treatment plan
Assessing a subungual haematoma. Estimate the percentage of the nail involved, decide whether the plate is lacerated or avulsed, check that it is still seated in the eponychial fold, and look for haematoma extending beyond the nail bed. Those four observations, not the size alone, decide whether the nail comes off.
Investigations
Radiographs. PA and lateral views of the finger. The tuft fracture is the common finding after a crush, a comminuted fracture of the distal tip that usually needs no fixation; a shaft fracture may need a K-wire. Look also for the avulsion fractures that mark a tendon injury, an FDP avulsion (jersey finger) or an extensor avulsion (mallet), and for glass or metal foreign bodies.
Ultrasound finds the radiolucent foreign body, a thorn or a splinter of wood, that the radiograph cannot show.
Differential Decision-Making
The "differential" in fingertip trauma is less about disease and more about correctly categorising the injury, because the category dictates the treatment. Misclassification is the commonest source of error.
- Key Discriminator
- X-ray shows comminuted distal tuft
- Pitfall if Missed
- Calling an open tuft # a 'simple cut'
- Action
- Treat as open #: irrigate, repair nail bed
- Key Discriminator
- Plate stable in fold vs avulsed/disrupted
- Pitfall if Missed
- Trephining over a displaced nail bed laceration
- Action
- Stable plate: trephine. Disrupted: remove and repair
- Key Discriminator
- DIP extensor lag vs loss of active DIP flexion
- Pitfall if Missed
- Missing a Zone 1 tendon injury behind a tip wound
- Action
- Examine FDP/extensor before anaesthetic
- Key Discriminator
- Tense, throbbing, fluctuant closed pulp space
- Pitfall if Missed
- Draining a felon too late (osteomyelitis)
- Action
- Incise and drain the septated pulp space
- Key Discriminator
- More nail lost (dorsal) vs more pulp lost (volar)
- Pitfall if Missed
- Planning a V-Y for a volar-oblique defect
- Action
- Volar oblique: cross-finger / homodigital flap
Treatment
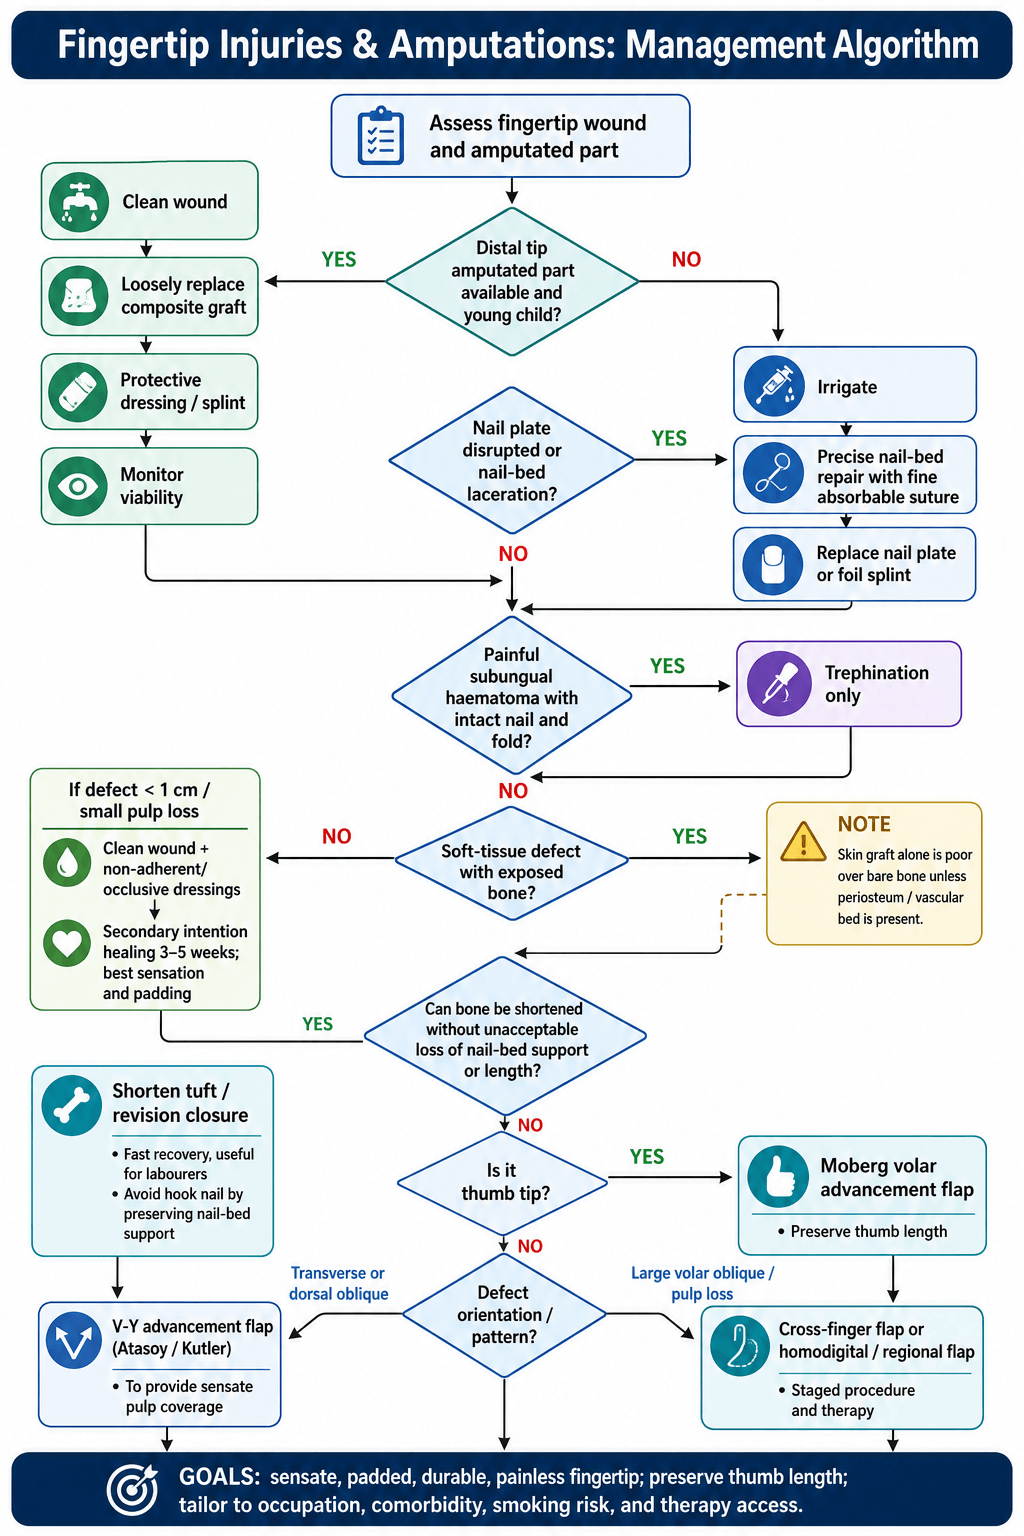
The decision. Two questions sort almost every fingertip: is bone exposed, and is it the thumb?
- No exposed bone and a defect under 1cm - dressings and secondary intention. This gives the best sensation and the best padding.
- Exposed bone - shortening is simple and effective and suits a labourer; a local flap if length must be preserved; a graft takes poorly over bare bone, which needs periosteum to support it.
- The thumb - a distinct entity, in which length is critical and preserving it outweighs cosmetic concerns. The Moberg flap is the answer.
Secondary intention. Clean the wound, apply a non-adherent dressing and change it weekly. Healing takes 3-5 weeks, during which the wound contracts by about 50%; the result is excellent sensation and a durable tip. Exposed bone is the contraindication, because of the risk of osteomyelitis, though tips often granulate over a small exposed tuft. Patience is the treatment, so warn the patient about the "ugly duckling" phase before it arrives.
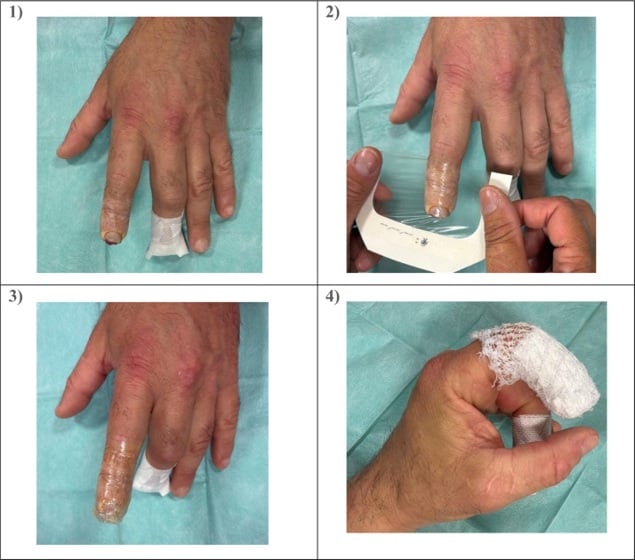
Surgical Considerations
Choosing the flap. The geometry of the defect and the digit choose the flap, and each flap is defined by the vessel it lives on and the direction it moves.
- Indication
- Transverse / Dorsal Oblique
- Vessel
- Subcutaneous perforators
- Movement
- Advancement
- Indication
- Transverse / Volar Oblique
- Vessel
- Lateral digital
- Movement
- Bilateral Advancement
- Indication
- Thumb Tip
- Vessel
- Neurovascular Bundles
- Movement
- Volar Advancement
- Indication
- Volar Oblique / Large
- Vessel
- Dorsal Digital (Donor)
- Movement
- Transposition
The V-Y advancement flap. For the transverse or dorsal oblique amputation. Draw a V on the volar pulp with its apex at the DIPJ crease, so that the scar does not contract across the joint. Cut skin only, then tease the fibrous septae deep to the flap to free it; the base carries the blood supply and must not be undercut. Advance the flap distally over the bone and close it as a Y. It advances about 5-10mm at most.
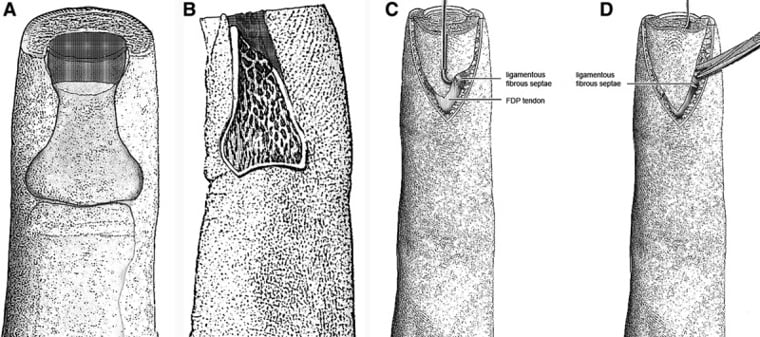
Examiners expect more than the three common flaps. Know where these named options sit on the fingertip reconstructive ladder.
Kutler bilateral V-Y flaps. Two lateral triangular flaps, one on each side, advanced to the midline for a transverse tip amputation. An alternative to the single volar Atasoy flap: less advancement, but a midline closure.
Thenar flap. The injured volar pulp of the index or middle finger is buried into a flap raised from the thenar eminence and divided at about two weeks. It gives good pulp bulk and colour match, but the flexed inset risks a PIP flexion contracture, so it is reserved for younger patients with supple joints.
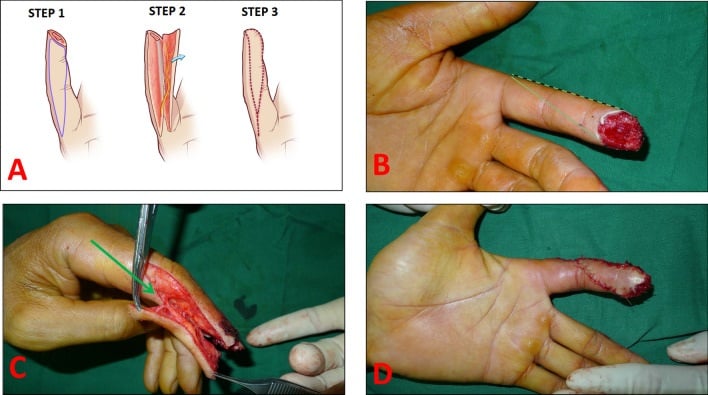
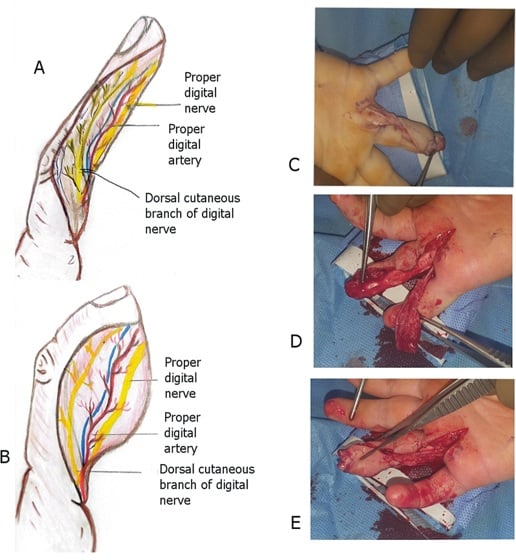
Homodigital (Venkataswami) island flap. An antegrade neurovascular island advanced on one digital artery and nerve of the same finger: sensate, single-stage cover for a volar-oblique defect without sacrificing an adjacent finger.
Littler neurovascular island flap. Sensate skin transferred on its neurovascular pedicle, classically from the ulnar border of the middle or ring finger, to resurface a critical sensory area, especially the thumb pulp. Sensation is at first referred to the donor digit, so cortical re-education is needed.
The reconstructive ladder. Choose the simplest adequate option first: secondary intention or dressing, then local advancement (V-Y, Moberg), then regional (cross-finger, thenar, homodigital island), with distant or free tissue only for the largest composite defects.
Complications
Neuroma. A painful nerve ending. It is resected and the nerve end buried in muscle or bone.
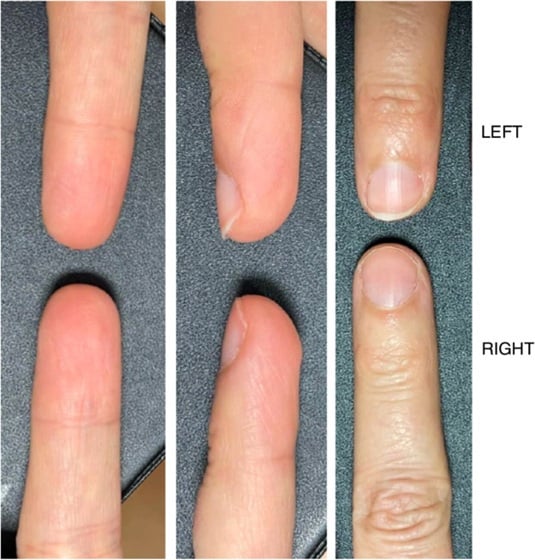
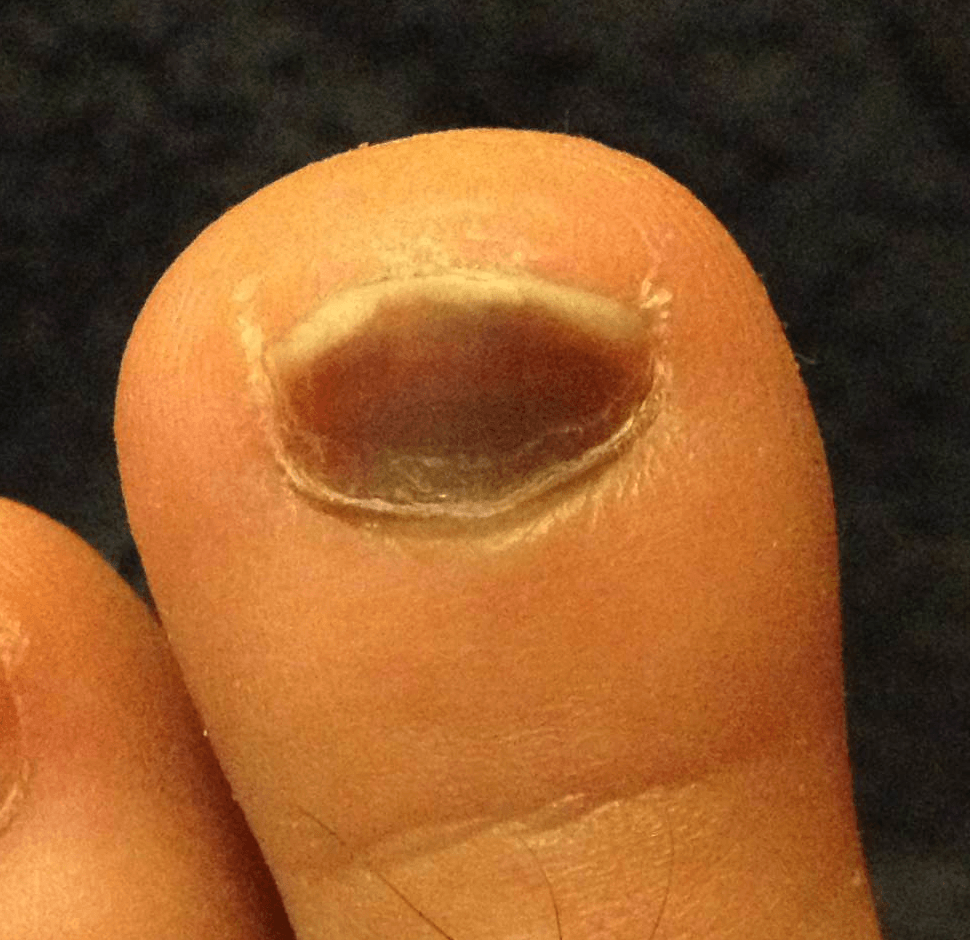
Nail deformity. Scar in the germinal matrix gives a split nail; scar in the sterile matrix gives a non-adherent one. The hook nail is the third pattern and has its own cause and its own prevention.
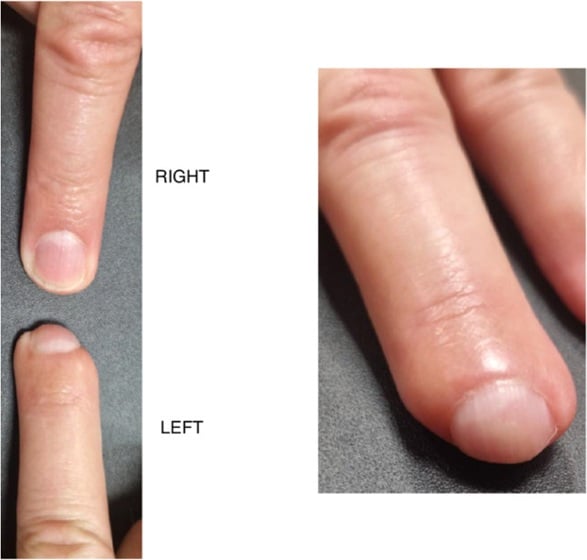
The cause. If the nail bed is pulled tightly over the tip of a shortened distal phalanx, or there is simply not enough bone under it, the bed curves volarly, and as the nail grows it curves round the tip like a parrot's beak. It is difficult to trim and it catches.
The prevention. The bone must support the nail bed fully. If the bone is short, trim the nail bed back to match it or advance bone or soft tissue to support it; never suture the nail bed under tension over the steep cliff of the amputation.
Hypersensitivity is common and is treated with a desensitisation programme of tapping and texture rubbing. Cold intolerance is a persistent problem after replants and flaps.
The composite-graft option for a child's tip sits at the distal end of a larger replantation framework examiners test.
The strong, classic indications for digital replantation are:
- The thumb, at any level (functional priority).
- Multiple digits.
- Any amputation in a child.
- Amputation through the palm, wrist or forearm.
- A clean amputation distal to the FDS insertion (better functional outcome than a single digit amputated within zone 2).
The relative contraindications are:
- A single finger amputated proximal to the FDS insertion in an adult (poor functional return, stiffness, the digit often gets in the way).
- Severe crush or avulsion, multi-level injury, or gross contamination.
- Prolonged warm ischaemia, significant comorbidity, or a patient unable or unwilling to comply with rehabilitation.
The distal tip. Replantation distal to the lunula is technically possible but limited by the lack of a suitable vein for venous outflow, managed with controlled bleeding or leech protocols. In young children a composite graft is the pragmatic, reliable alternative to microsurgical replant. Because digits carry little muscle, ischaemia tolerance is comparatively long, roughly up to about twelve hours warm and twenty-four hours cold.
Rehabilitation
The principle. Early motion is what prevents DIPJ stiffness, and a desensitisation programme graded from soft to rough textures is what prevents a hypersensitive tip. A custom tip guard protects the return to work, work hardening simulates the job, and psychological support is worth offering, because fingertip injuries can be distressing.
- Splint: Aluminium tip protector or thermoplastic cap.
- Wound: Keep dry. Occlusive dressing for secondary intention.
- Nail: Keep stent (nail plate or foil) in place.
- Elevation: Reduce swelling.
- Pain: Simple analgesia. Avoid NSAIDs initially (may affect healing).
- Sutures: Remove non-absorbable sutures (if used).
- Nail stent: Can remove at 3 weeks.
- Desensitisation: Start early tapping/rubbing to prevent hypersensitivity.
- ROM: Mobilise DIPJ. Active flexion/extension.
- Oedema control: Coban wrap if needed.
- Grip exercises: Putty, stress ball.
- Pinch strength: Key pinch, tripod pinch exercises.
- Scar massage: Soften and desensitise scar tissue.
- Light activities: Typing, writing.
- Nail: New nail plate grows in (3-4 months for full replacement).
- Sensation: Returns gradually over 6-12 months.
- Cold intolerance: May persist, improves with time.
- Return to work: Manual workers 4-8 weeks; fine motor 8-12 weeks.
Prognosis
Sensation. Healing by secondary intention gives better sensation, two-point discrimination of 3-4mm, than a graft or a cross-finger flap, which manage 6-8mm. Cold intolerance follows the same pattern: rare after secondary intention, common after a flap.
Appearance. A flap looks better at first, but secondary intention produces a surprisingly normal fingerprint pattern. In the long term, nail deformity is the most common complaint.
Guidelines, Registries & Global Practice
Global Epidemiology
- Burden: The fingertip is the single most commonly injured part of the hand worldwide; distal phalanx/fingertip trauma accounts for a large share of all hand injuries presenting to emergency departments across high- and low-income settings.
- Demographics: Bimodal pattern. A working-age male peak (roughly 20-50 years) driven by machinery, power tools and crush injuries; and a young-child peak (1-4 years) driven by door-crush injuries to the dominant-hand digits.
- Mechanism: Doors are the leading cause in children; industrial machinery, saws and presses dominate occupational injury globally.
- Most-injured digits: Middle and ring fingers (longest, most exposed in grip); the thumb is treated as a distinct priority because of its functional dominance.
Guidelines Compared Side by Side
- BSSH / BOA (UK)
- Not routine after thorough irrigation
- ASSH / AAOS (US)
- Not routine for uncomplicated open distal tuft fracture
- AO / EFORT (Europe)
- Selective; wound toilet emphasised
- BSSH / BOA (UK)
- Decompress if painful; nail removal not mandated by size
- ASSH / AAOS (US)
- Trephination for painful haematoma; repair if plate unstable
- AO / EFORT (Europe)
- Decompress; preserve a stable plate as a biological stent
- BSSH / BOA (UK)
- Conservative / secondary intention favoured
- ASSH / AAOS (US)
- Secondary intention or occlusive dressing
- AO / EFORT (Europe)
- Semiocclusive dressing (Mennen-Wiese tradition)
- BSSH / BOA (UK)
- Local flap or shortening per patient need
- ASSH / AAOS (US)
- Local flap (V-Y, Moberg for thumb), shortening
- AO / EFORT (Europe)
- Reconstructive ladder; homodigital/regional flaps
Registry & Outcome Notes
- Fingertip injuries are not implant procedures, so they do not feature in joint registries (NJR, AJRR, AOANJRR). The evidence base instead rests on RCTs and systematic reviews (antibiotics, glue vs suture, subungual haematoma) and large conservative-management series.
- National hand-trauma networks (e.g. UK BOAST hand-trauma standards, regional trauma datasets) emphasise early senior decision-making and access to hand therapy as the key determinants of outcome.
High- vs Limited-Resource Practice Variation
- High-resource settings: Ready access to operating theatres, microsurgery and dedicated hand therapy enables flap reconstruction, composite grafting in children and formal nail bed repair under loupe magnification.
- Limited-resource settings: Conservative management (secondary intention / semiocclusive dressing) is especially valuable — it is cheap, avoids theatre time, needs no microsurgical skill and reliably restores a sensate, durable pulp for small and moderate defects.
- Universal principles: Tetanus prophylaxis per local immunisation status, meticulous wound toilet, preservation of length (especially the thumb), and early mobilisation to prevent DIPJ stiffness apply everywhere regardless of resource level.
Controversies and Areas of Uncertainty
Repair or decompress the nail bed. Traditional teaching mandated nail removal and formal nail bed repair for any subungual haematoma over 50 percent. Systematic review evidence (Dean et al.) shows no cosmetic advantage of repair over simple decompression when the plate is stable. The pragmatic position is to decompress the painful nail and reserve formal repair for a clearly avulsed or disrupted plate.
Conservative or flap for exposed bone. A small area of exposed bone is not an absolute indication for a flap. Many tips granulate and epithelialise over a small exposed tuft under occlusive dressings, with excellent sensation at the end of it. Flaps preserve length faster but add donor morbidity, stiffness and cold intolerance, so the decision is patient-specific: occupation, length needs and comorbidity.
Composite grafting in adults. Replacing the amputated tip as a composite graft is reliable in young children but unpredictable in adults, where take is poor distal to a few millimetres. There is no firm age cut-off; success falls with age and with a more proximal level of injury.
Antibiotics - how far the evidence goes. The RCT evidence against routine antibiotics applies to clean, well-irrigated open distal phalanx fractures in healthy adults. It should not be extrapolated uncritically to grossly contaminated, bite, farmyard or immunocompromised injuries, where prophylaxis remains reasonable.
MCQ Practice Points
Q: Which part of the nail matrix is responsible for nail plate adherence? A: The Sterile Matrix.
Q: What deformity results from scarring of the germinal matrix? A: Split Nail (as the nail plate is not formed uniformly).
Q: The Moberg flap is contraindicated in which digit? A: The Index Finger (and all except Thumb).
Q: What is the maximum size defect that heals well by secondary intention (if no bone exposed)? A: 1 cm (can heal up to 1.5 cm but slower).
Q: How do you prevent a Hook Nail deformity? A: Ensure adequate bony support for the nail bed. Do not suture nail bed under tension over shortened bone.
Q: For a volar oblique fingertip amputation with exposed bone, which flap is most appropriate? A: Cross Finger Flap (Atasoy V-Y advances less volar tissue; Cross Finger provides volar coverage).
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A carpenter hits his thumb with a hammer. There is a large subungual hematoma (90%) and a transverse laceration through the nail plate. X-ray shows a comminuted tuft fracture. How do you manage this?”
“A chef slices off the tip of his index finger. There is a 1cm x 1cm defect with bone exposed. The cut is transverse. He wants to return to work ASAP.”
“A 2-year-old shuts their finger in a door. The tip is amputated through the nail bed, held on by a bridge of skin. It looks dusky. What do you do?”
“A patient presents 6 months after fingertip amputation with a curved, painful nail that catches on clothing. The tip looks like a parrot's beak. What happened and what are the options?”
Classification
- Allen I: Pulp only
- Allen II: Pulp + Nail
- Allen III: Distal Phalanx
- Allen IV: Proximal to Lunula
Management
- No Bone: Secondary Intention
- Bone Exposed: Atasoy (Transverse), Kutler (Lateral)
- Thumb: Moberg
- Large/Volar: Cross Finger
Nail Bed
- Repair: 6-0 Chromic
- Hematoma: Trephine if painful
- Hook Nail: Prevent by bone support
- Stent: Replace nail plate or foil
Evidence Base
Prophylactic Antibiotics for Open Distal Phalanx Fractures
- Double-blind RCT of flucloxacillin vs placebo in 193 adults with open distal phalanx fracture
- Overall infection rate 4 percent; no osteitis or deep infection in either arm
- 3 of 98 infections with antibiotic vs 4 of 95 with placebo (no significant difference)
- Thorough wound toilet and soft-tissue repair is the key intervention, not antibiotics
2-Octylcyanoacrylate vs Suture for Nail Bed Repair (RCT)
- Prospective RCT, 40 patients: Dermabond (n=18) vs 6-0 chromic suture (n=22)
- Repair time 9.5 min with glue vs 27.8 min with suture (p less than 0.0003)
- No difference in cosmesis, pain or function at 1, 3 and 6 months
- Tissue adhesive is a faster, equally effective alternative to suture
Glue vs Suture Nail Bed Repair in Children (1-year follow-up)
- 74 paediatric nail bed lacerations; glue (n=36) vs absorbable suture (n=38)
- Nail dystrophy 14 percent overall (5 percent major), independent of technique
- Glue repair faster (10.2 vs 20.3 min, p less than 0.001)
- Higher early infection when repaired in ED vs operating room
Management of Acute Subungual Haematoma (Systematic Review)
- Systematic review of subungual haematoma management
- No difference in nail cosmesis between formal nail bed repair and simple decompression
- Complication rates low across all treatment methods
- An acutely painful haematoma should simply be decompressed (trephine or nail removal)
Semiocclusive Dressing for Fingertip Defects (Mennen-Wiese)
- Conservative semiocclusive film dressing for fingertip defects, including some with exposed phalanx
- Series of 200 injuries healed within 20-30 days with weekly undisturbed dressing changes
- Restored bulky pulp, fingerprint pattern and near-normal sensibility (2PD 2-8mm in pooled data)
- Avoids donor-site morbidity of local flaps
The Volar Advancement (Moberg) Flap for the Thumb
- Original description of the volar neurovascular advancement flap for the thumb tip
- Feasible because the thumb retains an independent dorsal blood supply, allowing the volar skin to be elevated on both digital bundles
- Contraindicated in the fingers, where elevating volar skin on both bundles risks dorsal skin necrosis