PIP and DIP Joint Injuries | Management Algorithms | Exam Pearls
- Dorsal PIPJ is most common; treated with early motion and buddy taping.
- Volar PIPJ is rare but critical - central slip injury requires 6 weeks extension splint.
- V-sign on lateral X-ray indicates dorsal subluxation and joint instability.
- Digital blocks are required for reduction and comprehensive stability assessment.
- Complications include permanent fusiform thickening and chronic stiffness.
- “Early motion for dorsal; strict extension for volar. Mismanaging volar causes Boutonnière.
- “Assess collateral stability in 20-30° of flexion after successful reduction.
- “Irreducible dislocations usually implicate volar plate or FDP tendon entrapment.
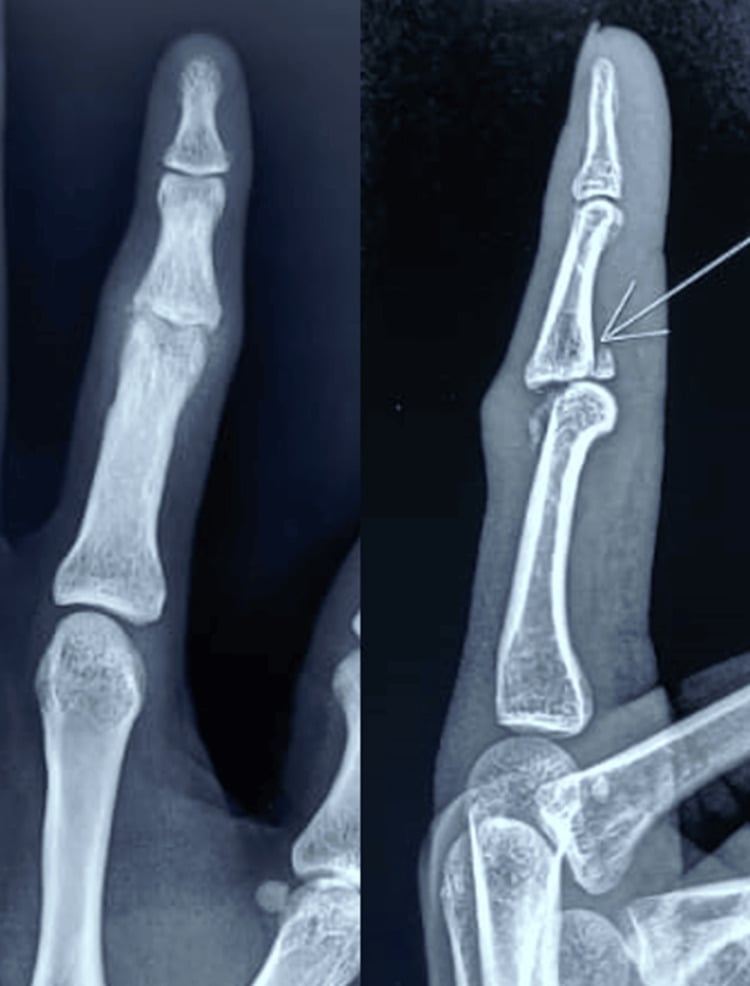
- “Check for 'Volar Plate Sign' - small avulsion fragment from middle phalanx base.
Finger Dislocations
Overview and Epidemiology
Finger dislocations are among the most common hand injuries seen in primary care and emergency departments. The proximal interphalangeal joint (PIPJ), the "workhorse" joint of the finger, is the one most frequently affected.
Mechanism. Ball sports are the most common setting: basketball, football and cricket. The mechanisms are:
- Hyperextension - the most common mechanism, producing dorsal PIPJ dislocation
- Axial loading - the "jammed finger" of sport
- Rotational stress - lateral dislocation with collateral ligament disruption; a rotational force can also dislocate the joint volarly
- Volar displacement - a palm-directed force on a flexed finger, rupturing the central slip
Anatomy & Joint Stabilisers
The PIPJ box. The PIPJ is a bicondylar hinge joint stabilised by a three-sided ligamentous "box". Which wall fails dictates the direction of dislocation and the entire treatment pathway.
- Volar: the volar plate. Fibrocartilage that resists hyperextension, with a thick distal attachment to the base of the middle phalanx and a thin, membranous proximal attachment (the check-rein ligaments)
- Lateral: the collateral ligaments. The proper collateral is the primary lateral restraint and is tightest near full extension; the accessory collateral blends with the volar plate
- Dorsal: the extensor mechanism. The central slip inserts on the dorsal base of the middle phalanx, and the lateral bands run laterally
Which wall fails. The direction of dislocation names the injured wall:
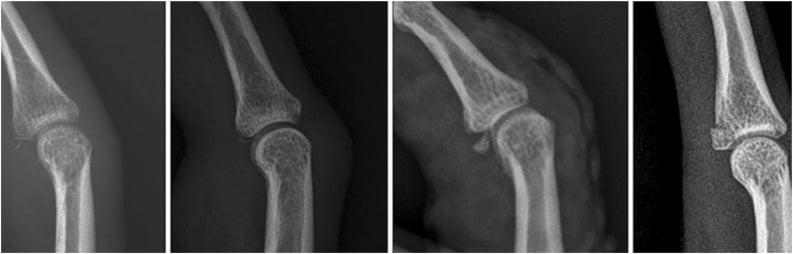
- Dorsal dislocation - the volar plate avulses distally, with or without a small bony fragment (the "volar plate sign")
- Volar dislocation - the central slip ruptures; the rupture is obligatory, hence the risk of boutonnière
- Lateral dislocation - the collateral ligament is disrupted
Classification
By direction. A PIPJ dislocation is named by where the middle phalanx lies relative to the proximal phalanx. Dorsal is the most common; volar is rare and carries the central slip injury; lateral is a collateral ligament disruption with a rotatory component. By joint involvement, a simple dislocation is soft tissue only and a fracture-dislocation carries a bony avulsion.
- Injured Structure
- Volar plate
- Stability
- Usually stable post-reduction
- Injured Structure
- Volar plate + bone
- Stability
- Depends on fragment size
- Injured Structure
- Central slip
- Stability
- Requires extension splinting
- Injured Structure
- Collateral ligament
- Stability
- May have rotatory instability
Fracture-dislocations: the articular-surface rule. The volar lip fragment is measured on the lateral radiograph as a percentage of the articular surface of the middle phalanx.
- Less than 30% - usually stable; extension block splinting
- 30-50% - borderline; may need surgical stabilisation
- Greater than 50% - unstable; requires surgical fixation
The surgical threshold of 40-50% falls inside the borderline band. There, the decision rests on dynamic stability, the stable arc tested under fluoroscopy, rather than on the percentage alone; the Evidence section sets out why no single cut-off settles it.
Clinical Assessment
History. Establish the mechanism, then ask the questions that change management:
- Time since injury
- Previous reduction attempts
- Hand dominance and occupation
Examination. Look for the deformity, dorsal or volar, with swelling and bruising, and check skin integrity: open injuries are common at the DIPJ. Palpate for point tenderness and record neurovascular status, capillary refill and sensation.
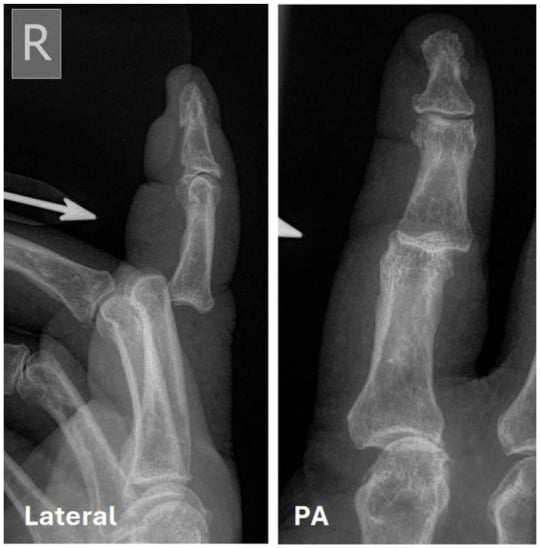
Stability after reduction. Take the finger actively through its full arc and note the angle at which it subluxates. Record the stable arc, and the angle of instability if there is one; the collateral ligaments are stressed separately (see the collateral ligament section). The critical post-reduction checks:
- Can the patient actively extend the PIPJ fully? If so, the central slip is intact
- Does the joint subluxate in extension? If so, it is unstable (V-sign)
- Is there rotatory instability, from a lateral ligament injury?
- Is the joint congruent on a true lateral radiograph after reduction?
The Elson test. It checks central slip integrity after a volar dislocation. Flex the PIPJ to 90° over the edge of a table and ask the patient to extend against resistance. If the central slip is torn, the extensor force is diverted into the lateral bands and the DIPJ goes rigid into extension; a floppy DIPJ means the slip is intact.
Investigations
Radiographs. AP, lateral and oblique views of the affected finger. The true lateral is essential for classification: isolate the finger from its neighbours, direct the beam perpendicular to its lateral aspect, and check that the condyles are superimposed.
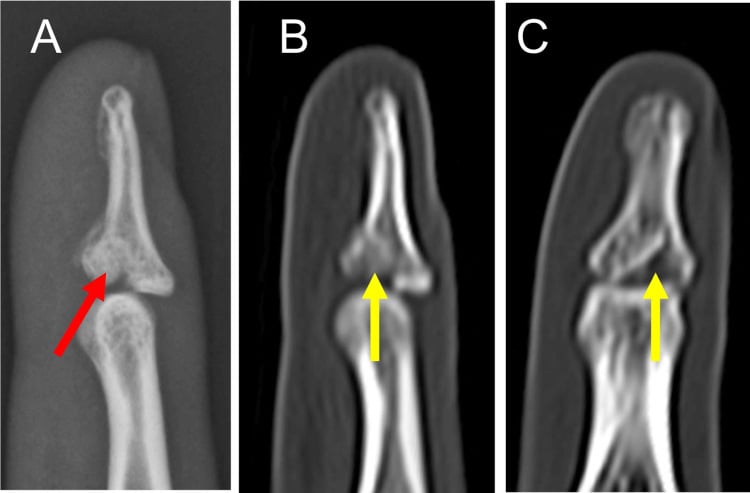
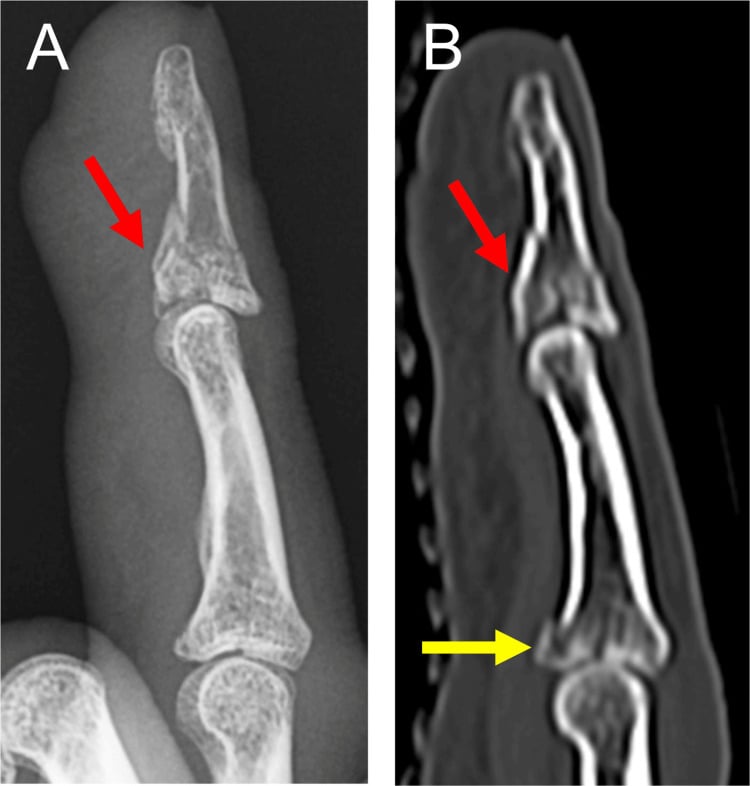
Before and after reduction. The pre-reduction films confirm the direction of dislocation, identify associated fractures and assess joint congruity. The post-reduction films confirm a concentric reduction, look for a V-sign and show where any fracture fragment lies. A small volar plate avulsion fragment is common in dorsal dislocation and is usually treated conservatively if the joint is stable.
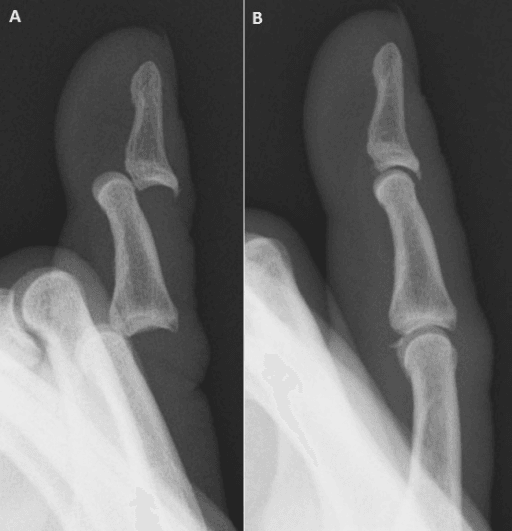
- V-sign - dorsal V-shaped widening of the joint space on the true lateral. It means dorsal subluxation and instability, and triggers extension block splinting or surgery. With the finger in extension the joint should be congruent.
- Parallel articular surfaces - pathognomonic for volar plate interposition (the tendon can also interpose). The joint is irreducible: proceed to open reduction rather than forcing closed reduction.
CT. For complex fracture-dislocations, for measuring the percentage of articular involvement, and for planning surgery on comminuted injuries. It defines a depressed fragment and the remaining joint surface when plain films cannot explain instability or guide fixation.
Fluoroscopic stress views. They assess stability through the range of motion, find the angle at which the joint becomes unstable, and so set the angle of an extension block splint.
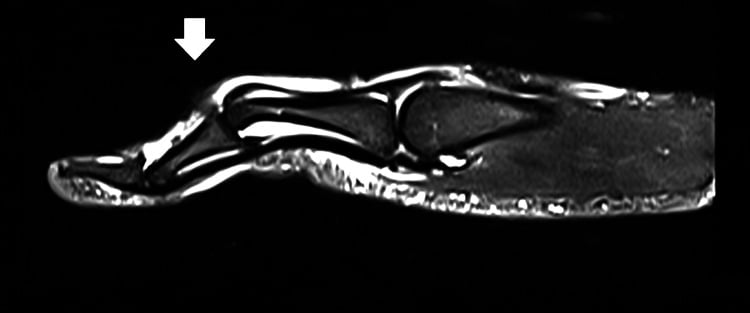
MRI. Not routine after an acute dislocation, but it can define an occult tendon injury when examination is limited or the diagnosis remains uncertain.
Differential Diagnosis
The swollen, deformed or "jammed" finger has several mimics. The key discriminators are the direction of deformity, active extension capacity, joint congruity on a true lateral film, and whether a mechanical block to reduction is present.
- Key clinical sign
- Hyperextended, shortened finger; reduces easily
- Radiograph
- Middle phalanx dorsal; +/- small volar lip fragment
- Distinguishing feature
- Volar plate avulsion; stable after reduction
- Key clinical sign
- PIPJ flexed, DIPJ extended, cannot actively extend PIPJ
- Radiograph
- Middle phalanx volar
- Distinguishing feature
- Obligatory central slip rupture (boutonniere risk)
- Key clinical sign
- Ulnar/radial deviation or rotational malalignment, opens to stress
- Radiograph
- Often congruent; may show condylar avulsion
- Distinguishing feature
- Collateral instability without overt dislocation
- Key clinical sign
- Persistent dorsal subluxation tendency
- Radiograph
- V-sign; volar lip fragment sized on lateral
- Distinguishing feature
- Stability depends on fragment size (30/50 rule)
- Key clinical sign
- Extension lag at PIPJ, no dislocation
- Radiograph
- Normal or small dorsal base avulsion
- Distinguishing feature
- Positive Elson test, joint located
- Key clinical sign
- DIPJ extension lag, droop
- Radiograph
- +/- dorsal distal phalanx fragment
- Distinguishing feature
- DIPJ not dislocated; PIPJ normal
- Key clinical sign
- Skin puckering over palm, MCP hyperextended
- Radiograph
- Sesamoid in joint; parallel surfaces
- Distinguishing feature
- Volar plate buttonholed around metacarpal head
- Key clinical sign
- Focal bony tenderness, deformity
- Radiograph
- Fracture line, joint located
- Distinguishing feature
- No frank dislocation; assess rotation
Management
The principle. Direction decides the regimen: a dorsal dislocation is moved early and a volar one is splinted in extension.
Dorsal PIPJ dislocation.
- Digital block anaesthesia
- Reduce with longitudinal traction and flexion
- Assess stability through the range of motion
- Stable: buddy taping and early motion
- Unstable: extension block splinting
Volar PIPJ dislocation. The central slip is at risk.
- Reduce with traction and extension
- Test active PIPJ extension
- Static extension splint for 6 weeks
- Active DIP flexion exercises during immobilisation
An unstable volar dislocation may need open repair.
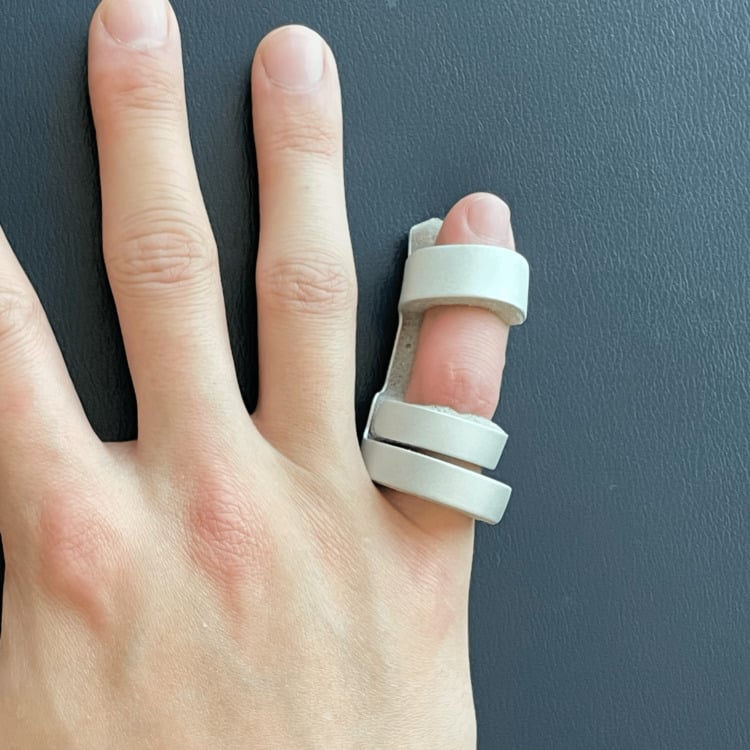
Extension block splinting. For a dorsal fracture-dislocation with less than 50% articular involvement, where the joint is stable in some flexion but unstable in extension.
- Determine the angle of stability under fluoroscopy
- Splint the PIPJ at that angle, typically 30-40° of flexion
- Allow full active flexion
- Radiograph weekly to confirm the reduction
- Reduce the flexion by 10° a week
When to operate.
- Irreducible dislocation (volar plate interposition)
- Fracture involving more than 40-50% of the articular surface
- Persistent instability despite splinting
- Chronic dislocation, more than 3 weeks old
- Failed closed treatment
Surgical Technique
Approaches. The approach follows the structure to be dealt with:
- Volar (Bruner) - preferred for extracting the volar plate
- Dorsal - central slip repair
- Lateral - collateral ligament repair
Open reduction through the volar approach.
- Bruner zigzag incision over the PIPJ
- Identify and protect the neurovascular bundles
- Retract the flexor tendons
- Identify the interposed volar plate
- Extract it and reduce the joint
- Repair the volar plate to bone with suture anchors
Choosing the operation for a fracture-dislocation. Match the procedure to fragment size, comminution and chronicity.
- Indication
- Large fragment fracture-dislocation
- Key Points
- Screws, plate, or K-wires
- Indication
- Comminuted volar lip
- Key Points
- Advance volar plate into defect
- Indication
- Chronic defect greater than 50%
- Key Points
- Autograft from hamate
Volar plate arthroplasty (Eaton-Littler).
- Volar approach to the PIPJ
- Release the A3 pulley if needed
- Advance the volar plate into the articular defect
- Secure it with a pull-out suture or an anchor
- Extension block splinting after surgery
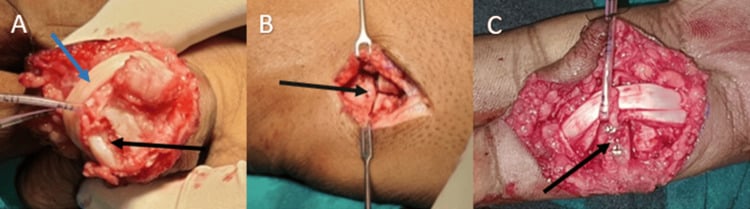
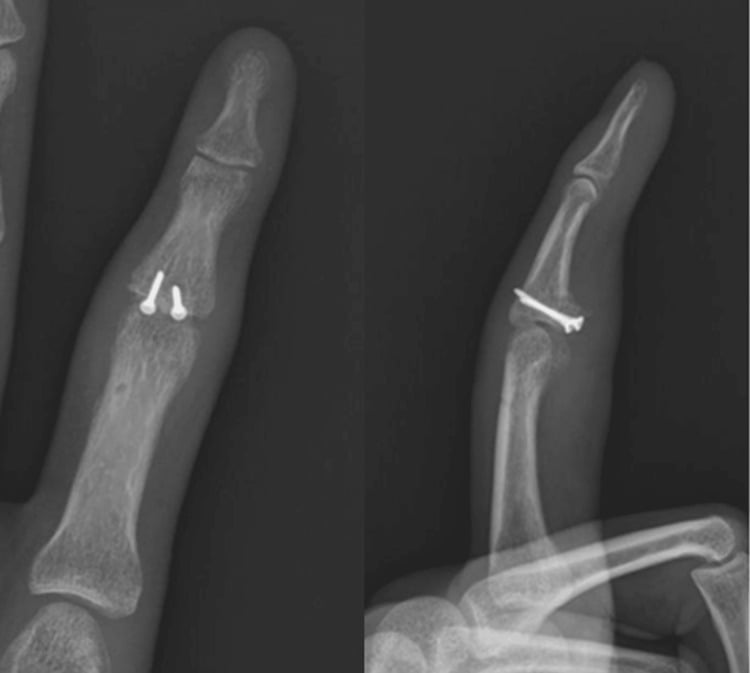
Hemi-hamate arthroplasty. The PIPJ is opened through a volar shotgun exposure, and an osteochondral graft from the hamate reconstructs the deficient volar base of the middle phalanx. Protect both digital neurovascular bundles and avoid proud screws.
- Harvest a size-matched graft from the dorsal hamate
- Contour it to match the base of the middle phalanx
- Fix it with screws or K-wires
- Early protected motion
Dynamic external fixation. Indicated for unstable fracture-dislocations. Ligamentotaxis reduces the fracture while the fixator allows early protected motion; the complications are pin-tract infection and stiffness.
DIP Joint Dislocation
The distal interphalangeal (DIP) joint is dislocated far less often than the PIPJ, but when it happens it is almost always dorsal and frequently open, because the dorsal skin over the joint is thin and closely applied to the extensor mechanism. The usual mechanism is an axial load with hyperextension, classically a ball striking the extended fingertip.
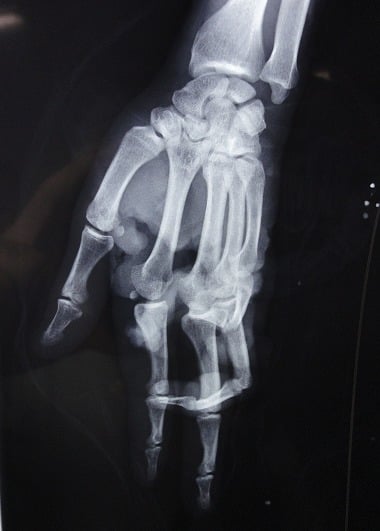
Open until proven otherwise. Even a small dorsal or volar laceration communicating with the joint makes this an open injury. It needs formal irrigation and debridement, tetanus prophylaxis and antibiotics, and reduction in a clean environment rather than a simple bedside reduction in the cubicle. An unrecognised open DIP dislocation risks septic arthritis and osteomyelitis.
Screen the tendons, the nail bed and, in a child, the physis. A lag in active DIP extension suggests a terminal extensor (mallet) injury, developed in the mallet-finger topic; loss of active DIP flexion suggests an FDP avulsion, covered under jersey-finger. Look for a nail-bed laceration. In a child, actively exclude a Seymour-type injury at the nail fold: a displaced physeal fracture of the distal phalanx can masquerade as a DIP dislocation or mallet, and is an open physeal injury requiring nail-plate removal and reduction (see phalangeal-fractures).
Reduction and aftercare. Under digital block, apply longitudinal traction with gentle reversal of the deformity. The reduced DIP is usually stable, since it is unusual for both collateral ligaments and the volar plate to fail together. Splint the DIP, leaving the PIP free, for roughly 2-3 weeks, then move to protected motion: the DIP tolerates short immobilisation, but prolonged splinting causes stiffness.
The irreducible DIP. Rare and, as at the PIPJ, a sign of soft-tissue interposition: most often the volar plate, occasionally the FDP tendon or a trapped sesamoid. It requires open reduction.
PIPJ Collateral Ligament Injury & Lateral Dislocation
Lateral dislocations and isolated collateral ligament ("sprain") injuries of the PIPJ are common and, because they frequently reduce spontaneously on the field, are easily under-treated. The radial collateral is injured more often than the ulnar.
Grading.
- Grade I - sprain, ligament in continuity, stable to stress
- Grade II - partial tear, painful but stable
- Grade III - complete rupture, demonstrably unstable
Stress testing. Apply radial and ulnar deviation stress with the PIPJ in about 20-30° of flexion, which isolates the proper collateral, always comparing with the same finger on the other hand. Lateral opening of more than 20°, or a soft or absent endpoint, indicates a complete (Grade III) rupture. A stress radiograph documents both the angulation and any condylar avulsion fragment.
Management. The overwhelming majority, including reduced lateral dislocations and Grade I-III sprains without a large intra-articular fragment, are stable enough for buddy strapping to the adjacent finger with early motion for 3-6 weeks, and do very well. Surgery is reserved for three situations, the main one a large displaced condylar fragment:
- A displaced condylar avulsion fragment carrying a meaningful portion of the articular surface
- Gross instability
- Soft-tissue interposition blocking reduction
A fixed rotational deformity points to an associated phalangeal or condylar fracture (see phalangeal-fractures) rather than a pure ligament injury. Warn the patient that a lateral PIPJ injury leaves a fusiform, mildly stiff and tender joint for many months, exactly as a dorsal dislocation does.
Complications
Stiffness. The most common complication. Fusiform swelling persists for months, and patients should be warned that the finger may stay permanently thickened. Prolonged immobilisation causes it; early protected motion in dorsal dislocations prevents it.
Boutonnière deformity. PIPJ flexion with DIPJ hyperextension, the result of an untreated central slip injury. It is common after a volar dislocation that is wrongly mobilised, and 6 weeks of extension splinting prevents it. An established deformity may still respond to splinting if treated early (less than 6 weeks); a late or fixed deformity may require surgical reconstruction by central slip repair, lateral band release or tendon reconstruction.
Pseudoboutonnière. A volar plate contracture holds the PIPJ in flexion after prolonged flexion splinting. Unlike the true boutonnière, the DIP is unaffected.
Swan-neck deformity. PIPJ hyperextension with DIPJ flexion, from volar plate laxity. It may follow chronic dorsal subluxation, and proper treatment of the volar plate injury prevents it.
Chronic instability and subluxation. Inadequate healing leaves a joint that stays unstable, which an appropriate duration of splinting prevents. Persistent subluxation shows as a V-sign on the radiograph and may require volar plate reconstruction, or a tenodesis or capsulodesis procedure.
Post-traumatic arthritis. More common after fracture-dislocations, and the risk increases with articular involvement greater than 40%. Severe cases may require arthrodesis.
Postoperative Care
Stable dorsal dislocation. Active motion starts immediately, with the finger buddy-taped to its neighbour. Full range of motion is expected by 4-6 weeks; protect the finger during sport for 6-8 weeks.
Volar dislocation. The extension splint stays on for a minimum of 6 weeks, and progressive PIPJ flexion begins after that.
After surgery. Hand therapy referral is essential, and the protocol runs:
- Extension block splinting for 2-3 weeks
- Progressive extension by 10° a week
- Full motion by 6-8 weeks
- Strengthening at 8-12 weeks
Hand therapy. Therapy addresses oedema, motion and splinting:
- Oedema - elevation for the first 48-72 hours, Coban wrap, active finger pumping exercises
- Motion - tendon gliding, blocked flexion and composite fist-making exercises
- Splints - thermoplastic splints preferred; figure-of-8 splints for collateral injuries; night splinting may continue for 3 months
Counselling. The fusiform swelling persists for 6-12 months, and full range of motion may take 3-6 months. For sport, protective taping is used for 3-6 months with buddy taping during activity, and a finger splint should be considered for contact sports.
Outcomes
Simple dorsal dislocation. An excellent prognosis with early motion: more than 90% achieve functional range of motion. Residual stiffness is common but usually mild, and return to sport comes within 4-6 weeks.
Volar dislocation. Good outcomes if splinted correctly, but a higher complication rate than dorsal, with the risk of boutonnière if treated improperly. Full recovery may take 3-6 months.
Fracture-dislocation. Outcomes depend on articular involvement: the prognosis is good with a fragment less than 30% and guarded with one greater than 50%, and the risk of post-traumatic arthritis increases with severity.
- Good Result Rate
- Greater than 90%
- Main Risk
- Stiffness
- Good Result Rate
- 80-85%
- Main Risk
- Boutonnière deformity
- Good Result Rate
- 60-80%
- Main Risk
- Arthritis, stiffness
Predictors. Favourable factors:
- Early treatment, within 24 hours
- Simple dislocation without fracture
- A patient compliant with therapy
- Young age
Unfavourable factors:
- Delayed presentation, beyond 1 week
- Large articular fragment, greater than 40%
- Open injury
- Associated tendon injury
- Poor compliance with splinting
The chronic or neglected dislocation. Beyond 3 weeks the chance of closed reduction falls, and beyond 6 weeks open treatment is usually required. Contracture and arthritis are more common, and arthrodesis may be needed as salvage.
Function. Grip strength usually recovers well, pinch strength may be reduced, and DASH scores typically normalise by 6-12 months.
Guidelines, Registries & Global Practice
Global epidemiology:
- Finger and hand injuries are among the most common presentations to emergency and acute care worldwide; the PIPJ is the most frequently dislocated digital joint, with dorsal dislocation by far the commonest pattern.
- Peak incidence is in young, active adults; ball and contact sports (basketball, football/soccer, rugby, cricket, volleyball, handball) dominate the mechanism across regions.
- Most simple dorsal dislocations are reduced and managed by emergency physicians or primary care, with specialist hand referral reserved for volar dislocations, irreducible joints and fracture-dislocations.
- Common ground (AAOS / BOA / AO principles)
- Closed reduction + early protected motion (buddy strapping / dorsal block splint)
- Practical note
- Avoid prolonged rigid immobilisation
- Common ground (AAOS / BOA / AO principles)
- Treat as central slip injury: extension splinting ~6 weeks
- Practical note
- Early flexion mobilisation causes boutonniere
- Common ground (AAOS / BOA / AO principles)
- Assess stable arc + fragment size on true lateral
- Practical note
- No fixed percentage cut-off is universally endorsed
- Common ground (AAOS / BOA / AO principles)
- Digital block with plain lidocaine for reduction
- Practical note
- Document neurovascular status before and after
- Common ground (AAOS / BOA / AO principles)
- Early supervised hand therapy improves motion
- Practical note
- Access varies by health system
Unlike arthroplasty of large joints, finger dislocations are not tracked in national joint registries; the evidence base is institutional case series and systematic reviews rather than registry data, which is itself a recognised limitation.
- High-resource settings: ready access to fluoroscopy, hand surgeons, dedicated hand therapy, and implants (suture anchors, mini-screws, dynamic fixators, hemi-hamate reconstruction).
- Limited-resource settings: emphasis on closed reduction, buddy strapping and improvised dynamic external fixation (for example a syringe-and-K-wire construct) which provides comparable function at minimal cost; early motion and patient education remain the highest-value, lowest-cost interventions everywhere.
MCQ Practice Points
Q: What is the mechanism and treatment of dorsal PIP dislocation?
A: Mechanism: Hyperextension injury with axial load, disrupting the volar plate. Most common finger dislocation. The MIDDLE phalanx displaces dorsally relative to the proximal phalanx. Reduction: Digital block, longitudinal traction with gentle flexion. Post-reduction: Assess stability through ROM; If stable to 30° flexion: Buddy taping with early mobilization. If unstable: Extension block splinting (blocking last 20-30° of extension) for 2-3 weeks, progressive extension.
Q: What is a volar PIP dislocation and why is it more concerning than dorsal?
A: Volar PIP dislocation: Middle phalanx displaces volarly; Less common but higher complication rate. Mechanism: Rotatory force or direct blow to extended finger. Central slip disruption is common (risk of boutonniere deformity). Reduction often more difficult (may require open reduction). Post-reduction: Splint PIP in full extension for 6 weeks to protect central slip (opposite of dorsal dislocation protocol). Earlier mobilization risks boutonniere deformity.
Q: What is an irreducible PIP dislocation and what causes it?
A: Irreducible dislocation: Cannot achieve closed reduction due to interposed tissue. Causes: Volar plate interposition (flips proximally, blocks reduction); FDP entrapment (tendon wraps around condyle); Lateral band interposition; Button-holing of condyle through volar plate. Clinical clue: Failed gentle reduction attempts, palpable block to reduction. Treatment: Open reduction through volar or dorsal approach, extraction of interposed tissue, volar plate repair.
Q: How do you assess and manage PIP fracture-dislocations?
A: Assess stability: Lateral X-ray - measure percentage of volar articular surface (middle phalanx) fractured. Less than 30%: Usually stable after reduction - extension block splinting. 30-50%: Borderline stable - may require surgical fixation (hemihamate arthroplasty, volar plate arthroplasty, dynamic external fixator). Greater than 50%: Unstable, high subluxation risk - requires surgical stabilization. V-sign (incongruent joint on lateral view) indicates instability requiring intervention.
Q: What is the treatment for MCP joint dislocation and what makes it complex?
A: Dorsal MCP dislocation: Proximal phalanx dorsal to metacarpal head. Simple: Reducible closed with wrist flexion, MCP hyperextension then flexion. Complex (irreducible): Volar plate interposition, often with metacarpal head button-holed through flexor tendons/lumbricals. Border digits - the index and the little finger - are the ones that classically do this, because the metacarpal head is caught in a noose formed on one side by the lumbrical and on the other by the flexor tendons, with the natatory ligament and superficial transverse metacarpal ligament completing it. Clinical sign: skin puckering over the palm, and the joint sits in slight hyperextension rather than the obvious deformity of a simple dislocation - so a complex dislocation often looks LESS dramatic than a simple one. Sesamoids visible within the joint space on the radiograph are pathognomonic. Contraindication: repeated forceful reduction attempts, which tighten the noose further and can convert a reducible dislocation into an irreducible one. Requires open reduction. If the volar approach is used for an index-finger dislocation, the radial digital nerve is draped directly over the prominent metacarpal head and lies immediately subcutaneous - it is divided by the skin incision if the surgeon cuts without first identifying it, which is the single most quoted hazard of this operation. The dorsal approach avoids that nerve and allows the volar plate to be split longitudinally to free the head, at the cost of poorer access to the interposed flexor tendons.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A goalkeeper presents with a swollen middle finger. Lateral X-ray shows a dorsal dislocation of the PIPJ with a small avulsion fracture at the base of the middle phalanx. Reduction was easy. How do you treat him?”
“A 28-year-old basketball player presents to the emergency department 2 hours after jamming his index finger. Examination shows the PIPJ held in slight flexion with the fingertip pointing volarly. Lateral X-ray confirms volar dislocation of the middle phalanx relative to the proximal phalanx. The ED resident asks you about the best treatment approach. What do you tell them?”
“A 35-year-old presents with a dorsal PIPJ dislocation of his ring finger sustained 4 hours ago. Multiple attempts at closed reduction in the emergency department have failed. X-rays show the middle phalanx remains dorsally dislocated with the PIPJ joint surfaces parallel to each other rather than overlapping. There is no fracture. What is your assessment and management?”
Direction
- Dorsal: Volar plate injury → Early Motion
- Volar: Central Slip injury → Splint Extension (6w)
Irreducible?
- Volar Plate interposition
- FDP tendon entrapment (rare)
- Condyle buttonholing
Evidence, Controversies & Areas of Uncertainty
The evidence base for PIPJ fracture-dislocations is almost entirely Level III-IV; there are no randomised trials comparing surgical techniques, so management remains opinion- and series-driven. Examiners reward candidates who can articulate these grey areas rather than quote a single dogmatic threshold.
Systematic Review: Treatment of Acute PIPJ Fractures & Fracture-Dislocations
- 37 studies, 471 patients, 480 fingers reviewed (Level III).
- Volar plate arthroplasty achieved the greatest postoperative PIPJ arc (90.6 degrees); dynamic external fixation the lowest (79.7 degrees).
- Recurrent pain and osteoarthritis were highest after extension block pinning (38.5% and 46.2%); ORIF had the highest revision rate (19.7%).
- Closed reduction with percutaneous pinning and volar plate arthroplasty gave good outcomes with the lowest complication rates.
Hemi-Hamate Autograft for Unstable Dorsal PIPJ Fracture-Dislocations
- 13 consecutive patients; mean middle phalangeal volar lip involvement 60% (range 40-80%).
- Size-matched dorsal/distal hamate osteoarticular autograft secured with miniscrews reconstructs the cup-shaped middle phalanx base.
- Mean PIPJ arc 85 degrees; grip 80% of the uninjured side; bony union in all patients.
- Recommended when greater than 50% of the volar base is fractured, or when the joint stays unstable despite a smaller fragment.
Hemi-Hamate Arthroplasty: 10-Year Outcomes
- 12 patients (acute and chronic), mean follow-up 10.7 years.
- Mean active PIPJ arc 76.6 degrees; mean QuickDASH 12.7, mean VAS pain 1; grip and pinch comparable to the uninjured hand.
- Radiographic osteoarthritis in 7 of 12 patients and graft resorption in 3, both associated with reduced motion; union rate 91.6%.
- Despite degenerative change, subjective outcomes and strength remained satisfactory at a decade.
Dynamic (Syringe) External Fixation for Comminuted Intra-Articular Hand Fractures
- 27 patients, 29 MCP/PIP joint injuries treated with a low-cost fixator built from a 1-mL syringe and K-wires.
- Dynamic fixation at the PIPJ gave a mean active arc of 80 degrees (static 64 degrees; static-to-dynamic 66 degrees).
- Low complication profile: 3 pin-site infections and 2 loose pins.
- Ligamentotaxis maintains reduction while permitting early motion in highly comminuted patterns.
Extensor (Zone III) Injuries at the PIPJ: Central Slip & Elson Test
- Acute closed central slip injuries are diagnosed clinically with the Elson test once bony injury is excluded.
- Overlooked central slip injury produces a boutonnière deformity within 1-2 weeks (PIPJ extension lag, DIPJ hyperextension).
- Non-displaced central slip avulsions are treated by extension splinting; displaced or complex injuries are surgical.
- Volar PIPJ dislocation should be managed as an acute central slip injury to prevent fixed deformity.
Volar Plate Arthroplasty (Classification & Technique)
- Described advancement of the volar plate into the articular defect for dorsal PIPJ fracture-dislocations.
- Restores a stable concave gliding surface for the proximal phalanx condyles.
- Best suited to acute or chronic injuries with volar lip involvement up to ~40-50% without a reconstructable fragment.
- Remains a recognised option alongside hemi-hamate reconstruction for non-fixable volar base fractures.
PIPJ Stability Criteria (Articular Surface Rule)
- Volar lip fractures involving less than 30% of the articular surface are usually stable after reduction.
- Fractures involving greater than 50% of the articular surface are usually unstable and subluxate.
- The 30-50% range is a 'grey zone' requiring stress testing/fluoroscopy to define the stable arc.
- Foundation for the modern conservative-versus-surgical treatment algorithm.
- Argument A
- Operate at greater than 30-40% (subluxation risk)
- Argument B
- Many 40-50% fragments are stable in flexion and do well with extension block
- Pragmatic position
- Decide on dynamic stability (stable arc), not the percentage alone
- Argument A
- Closed methods avoid surgical morbidity
- Argument B
- Open fixation restores articular congruity in large/displaced fragments
- Pragmatic position
- Reserve open surgery for fragments that are reconstructable and unstable through the functional arc
- Argument A
- Hemi-hamate restores bony contour for greater than 50% defects
- Argument B
- Volar plate arthroplasty avoids donor site, good for moderate defects
- Pragmatic position
- Choose by defect size, comminution and reconstructability
- Argument A
- Allows early motion with ligamentotaxis
- Argument B
- Pin-site morbidity and lower final arc in some series
- Pragmatic position
- Useful for comminuted, non-reconstructable patterns
- Argument A
- Early reconstruction limits contracture/arthritis
- Argument B
- Selected chronic cases tolerate delayed reconstruction
- Pragmatic position
- Beyond ~3-6 weeks expect open treatment and counsel on stiffness
- No single articular-surface percentage reliably predicts instability; dynamic testing of the stable arc is more useful than any fixed cut-off.
- Comparative outcome data between hemi-hamate, volar plate arthroplasty, dynamic fixation and ORIF are retrospective and confounded by injury severity selection bias.
- Long-term hemi-hamate series show acceptable function but frequent radiographic osteoarthritis, so "good clinical outcome" does not equal "normal joint".
References
- Gianakos AL, Yingling J, Athens CM, Barra AE, Capo JT. Treatment for Acute Proximal Interphalangeal Joint Fractures and Fracture-Dislocations: A Systematic Review. J Hand Microsurg. 2020. PMID 33335365. doi:10.1055/s-0040-1713323
- Williams RM, Kiefhaber TR, Sommerkamp TG, Stern PJ. Treatment of unstable dorsal proximal interphalangeal fracture/dislocations using a hemi-hamate autograft. J Hand Surg Am. 2003;28(5):856-65. PMID 14507519. doi:10.1016/s0363-5023(03)00304-6
- Mazhar FN, Noei RR, Zareie B, et al. Long-Term Clinical and Radiological Results of Hemi-Hamate Arthroplasty for PIP Fracture Dislocation. J Hand Surg Am. 2026. PMID 41528296. doi:10.1016/j.jhsa.2025.11.020
- Fleury CM, Yousaf IS, Miles MR, et al. The Syringe External Fixator for Comminuted Intra-Articular Fractures of the Hand. J Hand Surg Am. 2021. PMID 34602335. doi:10.1016/j.jhsa.2021.07.036
- Pillukat T, Windolf J, Schadel-Hopfner M, Fuhrmann RA, van Schoonhoven J. Extensor tendon injuries at the level of the PIP joint. Unfallchirurg. 2021;124(4):265-274. PMID 33616682. doi:10.1007/s00113-021-00984-x
- Eaton RG, Malerich MM. Volar plate arthroplasty of the proximal interphalangeal joint (classic technique). J Hand Surg Am. 1980. (Classic reference)
- Kiefhaber TR, Stern PJ. Fracture-dislocations of the proximal interphalangeal joint: stability criteria. J Hand Surg Am. 1998. (Classic reference)