Candida | Aspergillus | Endemic Mycoses | Cryptococcus | Immunocompromised Hosts
- Candida is most common fungal cause of osteomyelitis - think IV drug users and vertebral involvement
- Tissue biopsy is ESSENTIAL for diagnosis - fungal cultures and special stains (GMS, PAS)
- 1,3-beta-D-glucan serum marker helpful but NOT specific for site of infection
- Prolonged antifungal therapy 6-12 months - much longer than bacterial osteomyelitis
- Surgical debridement often required - antifungals alone frequently insufficient
- “Fungal osteomyelitis has INDOLENT course - delayed diagnosis is common
- “Aspergillus in immunocompromised is aggressive and often fatal without early treatment
- “Coccidioides is endemic to southwestern USA - soil exposure history critical
- “Cryptococcus gattii can affect IMMUNOCOMPETENT patients in endemic regions
Overview and Epidemiology
Fungal osteomyelitis is bone infection caused by pathogenic fungi, typically in an immunocompromised host or after exposure to endemic fungi in specific geographic regions. It is rare, less than 1% of all osteomyelitis, but increasing as the immunocompromised population grows: HIV, transplant recipients and patients on chemotherapy. Candida is the most common cause, 40-60% of fungal osteomyelitis.
Why it is missed. The course is indolent and the symptoms nonspecific, so diagnosis is delayed, on average 6 months from symptom onset. Examiners expect you to recognise the risk factors, order the right investigation, which is tissue biopsy, and know how long treatment takes.
Mortality. Aspergillus mortality is quoted at 50-80%, against 10-20% for the other fungi with treatment. In the 180-case review of Aspergillus osteomyelitis, overall mortality was 25% (see the Evidence Base).
Routes to bone. The fungi use the same three routes as bacteria:
- Haematogenous spread, the most common (Candida, Cryptococcus)
- Direct inoculation, through trauma or surgery
- Contiguous spread from adjacent soft-tissue infection
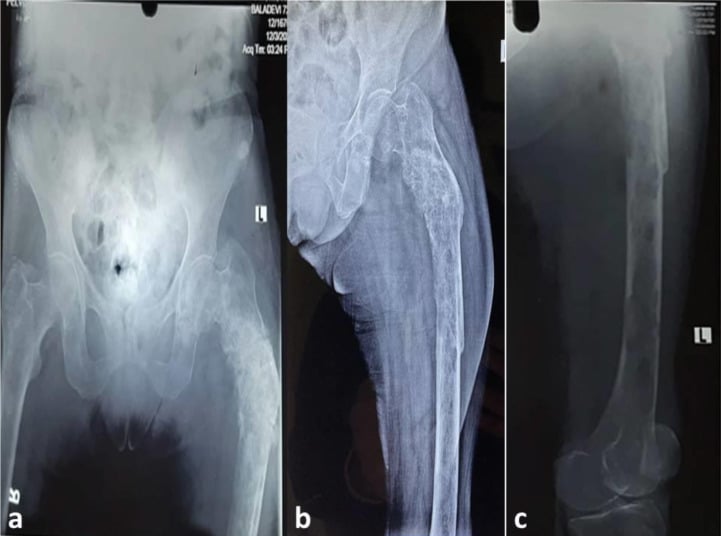
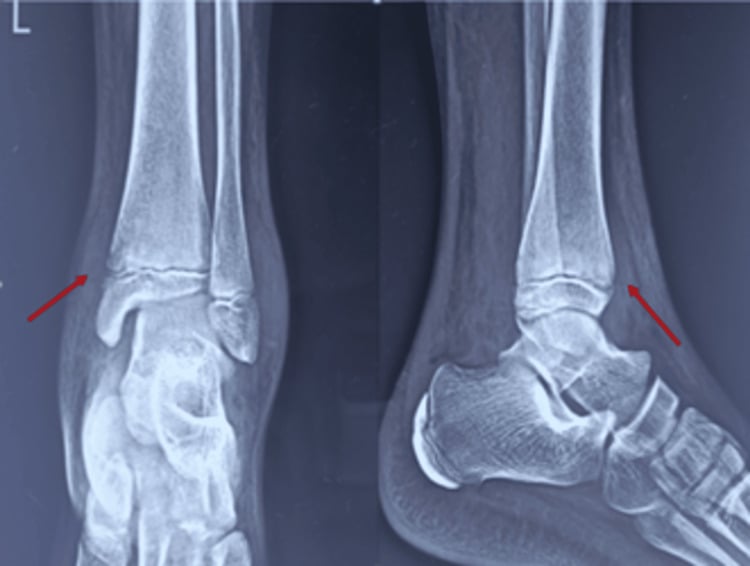
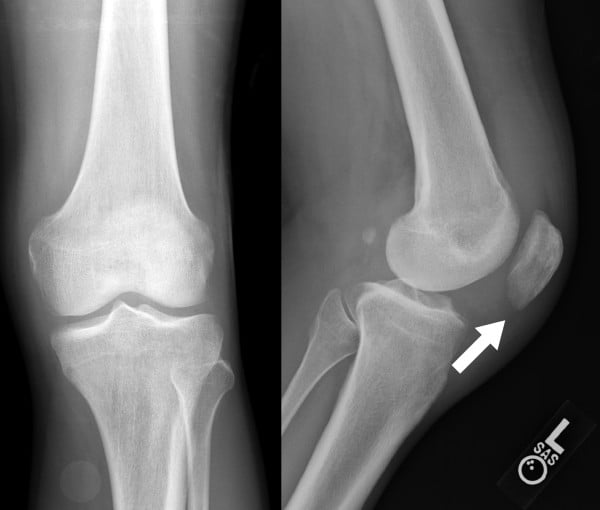
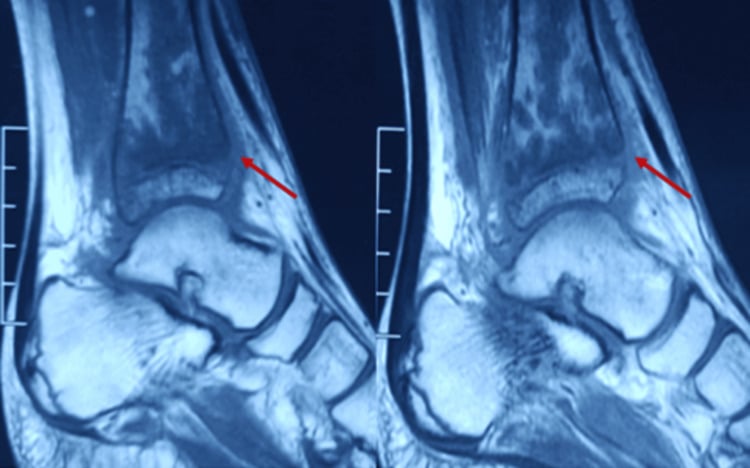
The tissue response. Unlike bacterial osteomyelitis, fungal infection typically provokes granulomatous inflammation with tissue destruction, and imaging shows minimal periosteal reaction.
Who is at risk. Each risk factor points towards particular organisms:
- HIV/AIDS with a CD4 count below 200: Cryptococcus and Histoplasma
- Chemotherapy and haematological malignancy: neutropenia allows fungal invasion, by Aspergillus and Candida; an absolute neutrophil count below 500 is the Aspergillus risk
- Organ transplant: immunosuppression allows opportunistic fungi, with Aspergillus in the first 6 months after transplant
- Chronic oral steroids: cell-mediated immunity is impaired
- Diabetes mellitus: impaired neutrophil function, and a risk for Candida and mucormycosis
- IV drug use: Candida vertebral osteomyelitis
- Central lines, dialysis and TPN: a portal of entry for Candida and a risk of Candida bloodstream infection
- Soil exposure in endemic areas: Coccidioides, Blastomyces and Histoplasma
Microbiology
The organism. C. albicans causes 50-70% of cases; C. tropicalis, C. glabrata and C. parapsilosis make up the rest. Candida is a normal commensal and becomes pathogenic when host defences are impaired.
How it reaches bone. Haematogenous spread from candidaemia, and the vertebra is the most common site. The host shapes the pattern: IV drug users develop it in the lumbosacral spine and the sternoclavicular joint, while patients on TPN or with central lines can seed any bone. The course is indolent, with back pain and a low-grade fever.
Chronic back pain and a low-grade fever in an IV drug user should prompt consideration of Candida vertebral osteomyelitis. Blood cultures are positive in less than 50%, so tissue biopsy is essential.
The organisms side by side. Treatment by organism is set out under Management.
- Risk Factors
- IV drug use, TPN, central lines, neutropenia, diabetes
- Sites
- Vertebrae (most common), sternum, ribs
- Prognosis
- Good if early diagnosis
- Risk Factors
- Neutropenia, transplant, steroids, CGD
- Sites
- Vertebrae, ribs, skull base
- Prognosis
- Poor - high mortality
- Risk Factors
- Endemic SW USA, soil exposure, Filipino/African heritage
- Sites
- Vertebrae, skull, pelvis, ribs, long bones
- Prognosis
- Chronic relapsing course
- Risk Factors
- Endemic Mississippi/Ohio River, soil/wood
- Sites
- Vertebrae, ribs, long bones
- Prognosis
- Good with treatment
- Risk Factors
- Endemic Ohio/Mississippi Valley, bird/bat droppings
- Sites
- Vertebrae, ribs, long bones
- Prognosis
- Good with treatment
- Risk Factors
- HIV/AIDS (neoformans), immunocompetent hosts in endemic regions (gattii)
- Sites
- Vertebrae, skull, long bones
- Prognosis
- Variable - depends on immune status
Clinical Presentation
Symptoms. Pain is the most common symptom (90%): usually dull, aching and progressive, and it may be present for weeks to months before diagnosis. Swelling is variable and often minimal early, and motion is limited if the focus is near a joint. Systemic symptoms are a low-grade fever below 38.5°C that is often absent, night sweats (especially with the endemic mycoses), weight loss, malaise and fatigue.
How it differs from bacterial osteomyelitis. The course is indolent. Symptoms last months rather than weeks before diagnosis, the presentation is less acute, high fever is less common, and CRP and ESR are often only mildly elevated. Failure to respond to antibiotics is the key clue to a fungal cause. How the infection presents varies with the organism and the immune status of the host.
Examination. Locally there is tenderness over the affected bone, soft-tissue swelling that is often subtle, warmth less pronounced than in bacterial infection, reduced movement of adjacent joints and, in chronic cases, a draining sinus. Look beyond the bone for:
- A low-grade fever
- Signs of the underlying immunocompromise
- Lymphadenopathy, with the endemic mycoses
- Pulmonary findings, if the primary infection is in the lung
- Skin lesions of disseminated infection (Blastomyces, Cryptococcus)
When to think fungal. Index of suspicion is key, and any of these should prompt a fungal work-up:
- Osteomyelitis not responding to appropriate antibiotics
- Culture-negative bone infection
- An immunocompromised patient (HIV, transplant, chemotherapy) with a bone lesion
- Travel to an endemic area and bone symptoms
- An IV drug user with vertebral osteomyelitis
Diagnosis
Blood cultures are often negative in fungal osteomyelitis. Serology and beta-D-glucan are nonspecific. Tissue biopsy with fungal stains and culture is ESSENTIAL for diagnosis. Do not delay biopsy - fungal cultures take 4-6 weeks.
Blood tests. None of them replaces tissue.
- Findings
- Mildly to moderately elevated
- Utility
- Nonspecific - lower than bacterial osteomyelitis
- Findings
- Often normal or mildly elevated
- Utility
- May be low in neutropenic patients
- Findings
- Elevated in Candida, Aspergillus, Histoplasma
- Utility
- Nonspecific (see below)
- Findings
- Elevated in Aspergillus
- Utility
- More specific for aspergillosis; serum and BAL
- Findings
- Positive in less than 50% of Candida cases
- Utility
- Often negative - not sufficient to rule out fungal infection
1,3-beta-D-glucan is a cell wall component of most pathogenic fungi (except Cryptococcus and Mucorales). It indicates fungal infection but does NOT identify the organism or site. Tissue diagnosis is still required. False positives occur with haemodialysis, certain antibiotics, and IVIG.
Tissue biopsy, the gold standard. Take tissue by CT-guided or open biopsy, and take several samples: 3 or more increase the yield. Histopathology shows granulomatous inflammation with fungal elements. What to send:
- Fungal culture, which takes 4-6 weeks; do not delay treatment while waiting if suspicion is high
- Bacterial culture
- Histopathology with the special stains GMS (Grocott methenamine silver) and PAS (periodic acid-Schiff)
- PCR, increasingly available for rapid identification
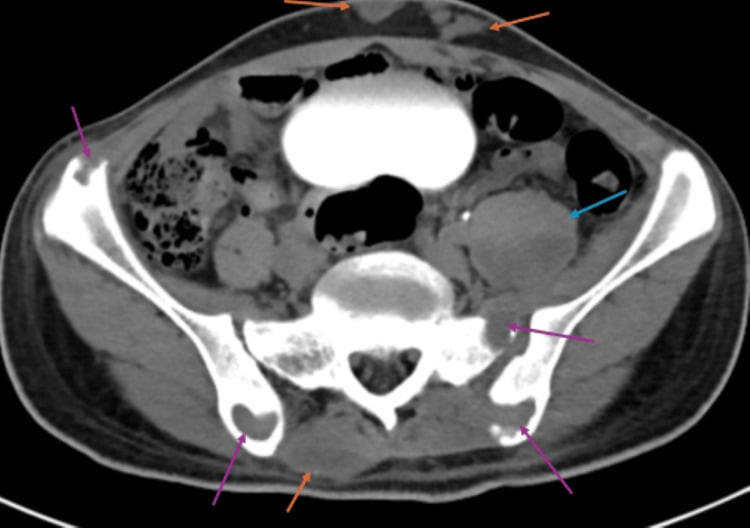
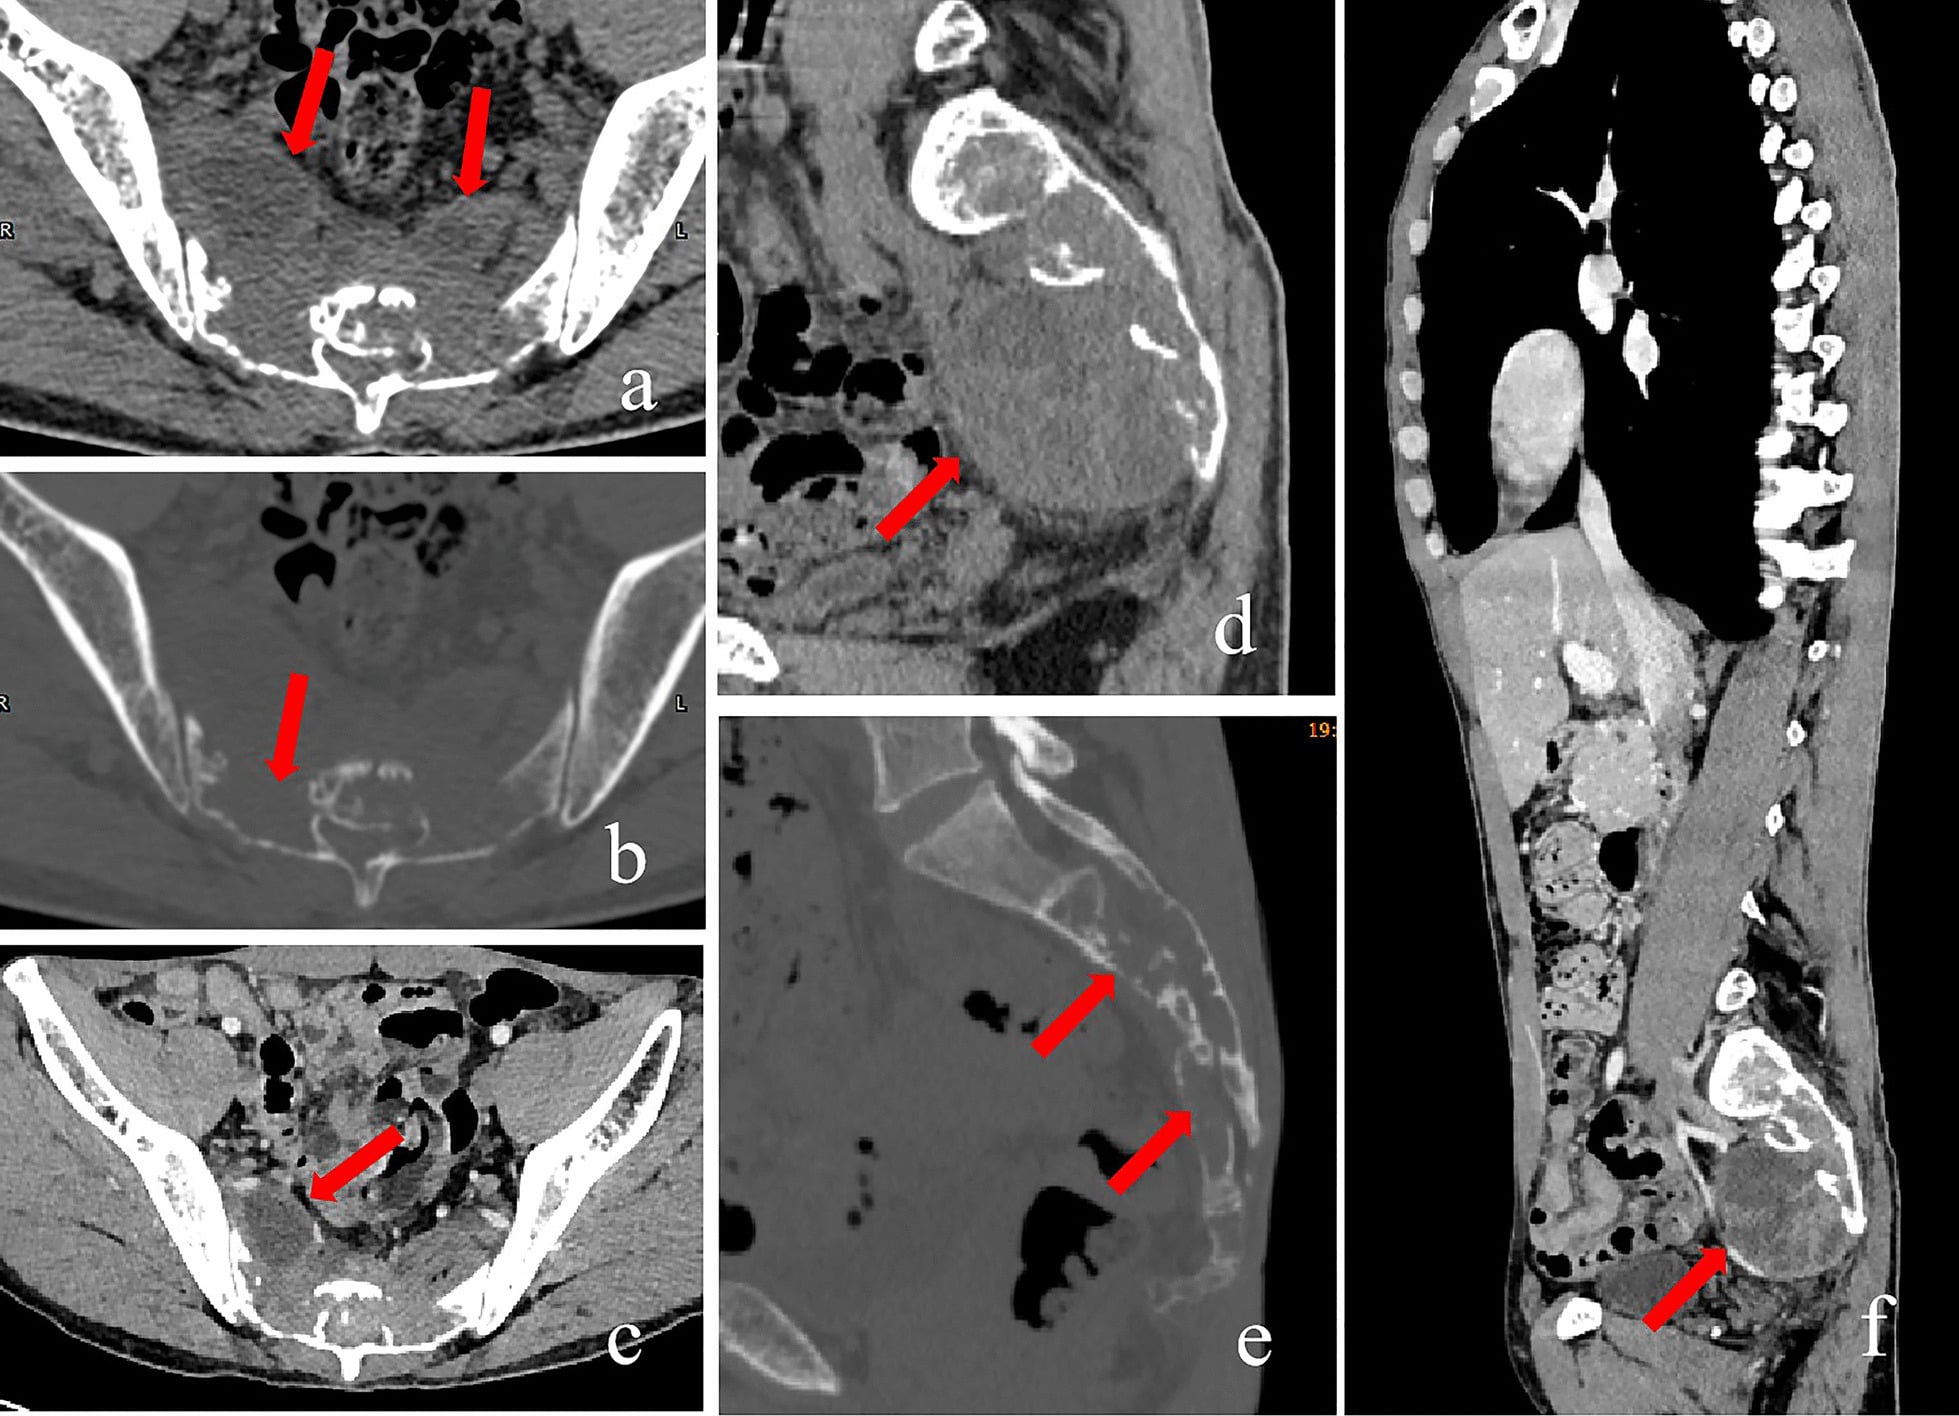
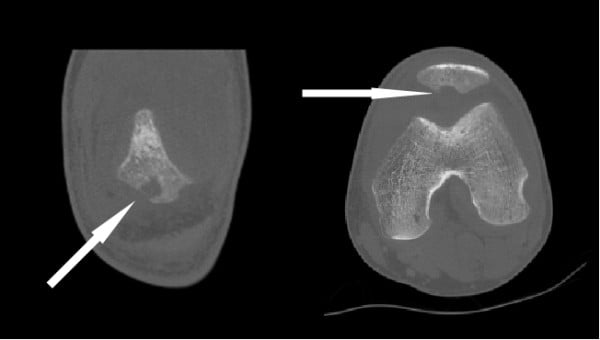
Telling the Fungi Apart on the Biopsy
GMS and PAS stain all fungal walls; add mucicarmine for the cryptococcal capsule. The organisms divide into yeasts, moulds and one dimorphic exception.
Yeasts are round or oval cells:
- Candida: oval budding yeast plus pseudohyphae, which can form in tissue
- Cryptococcus: narrow-based budding yeast with a thick capsule (mucicarmine-positive, clear halo)
- Blastomyces: broad-based budding yeast
- Histoplasma: small intracellular yeast within macrophages
- Sporothrix: cigar-shaped yeast
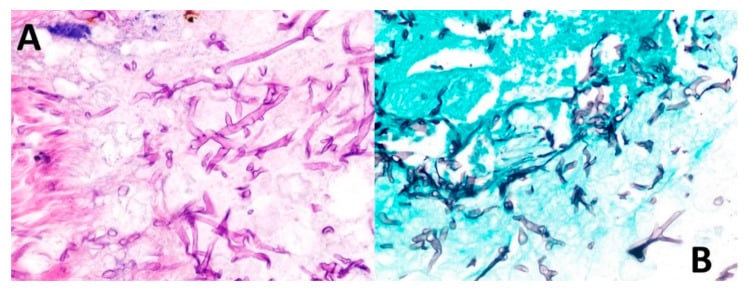
Moulds form hyphae. Aspergillus and the Mucorales are told apart by septation and branching, a distinction that directs very different therapy: voriconazole versus amphotericin.
- Aspergillus: narrow, septate hyphae with acute-angle (45-degree) branching
- Mucorales: broad, aseptate (or sparsely septate), ribbon-like hyphae with wide-angle branching
The dimorphic exception. Coccidioides in tissue forms large spherules packed with endospores, neither a yeast nor a hypha, and they are pathognomonic.
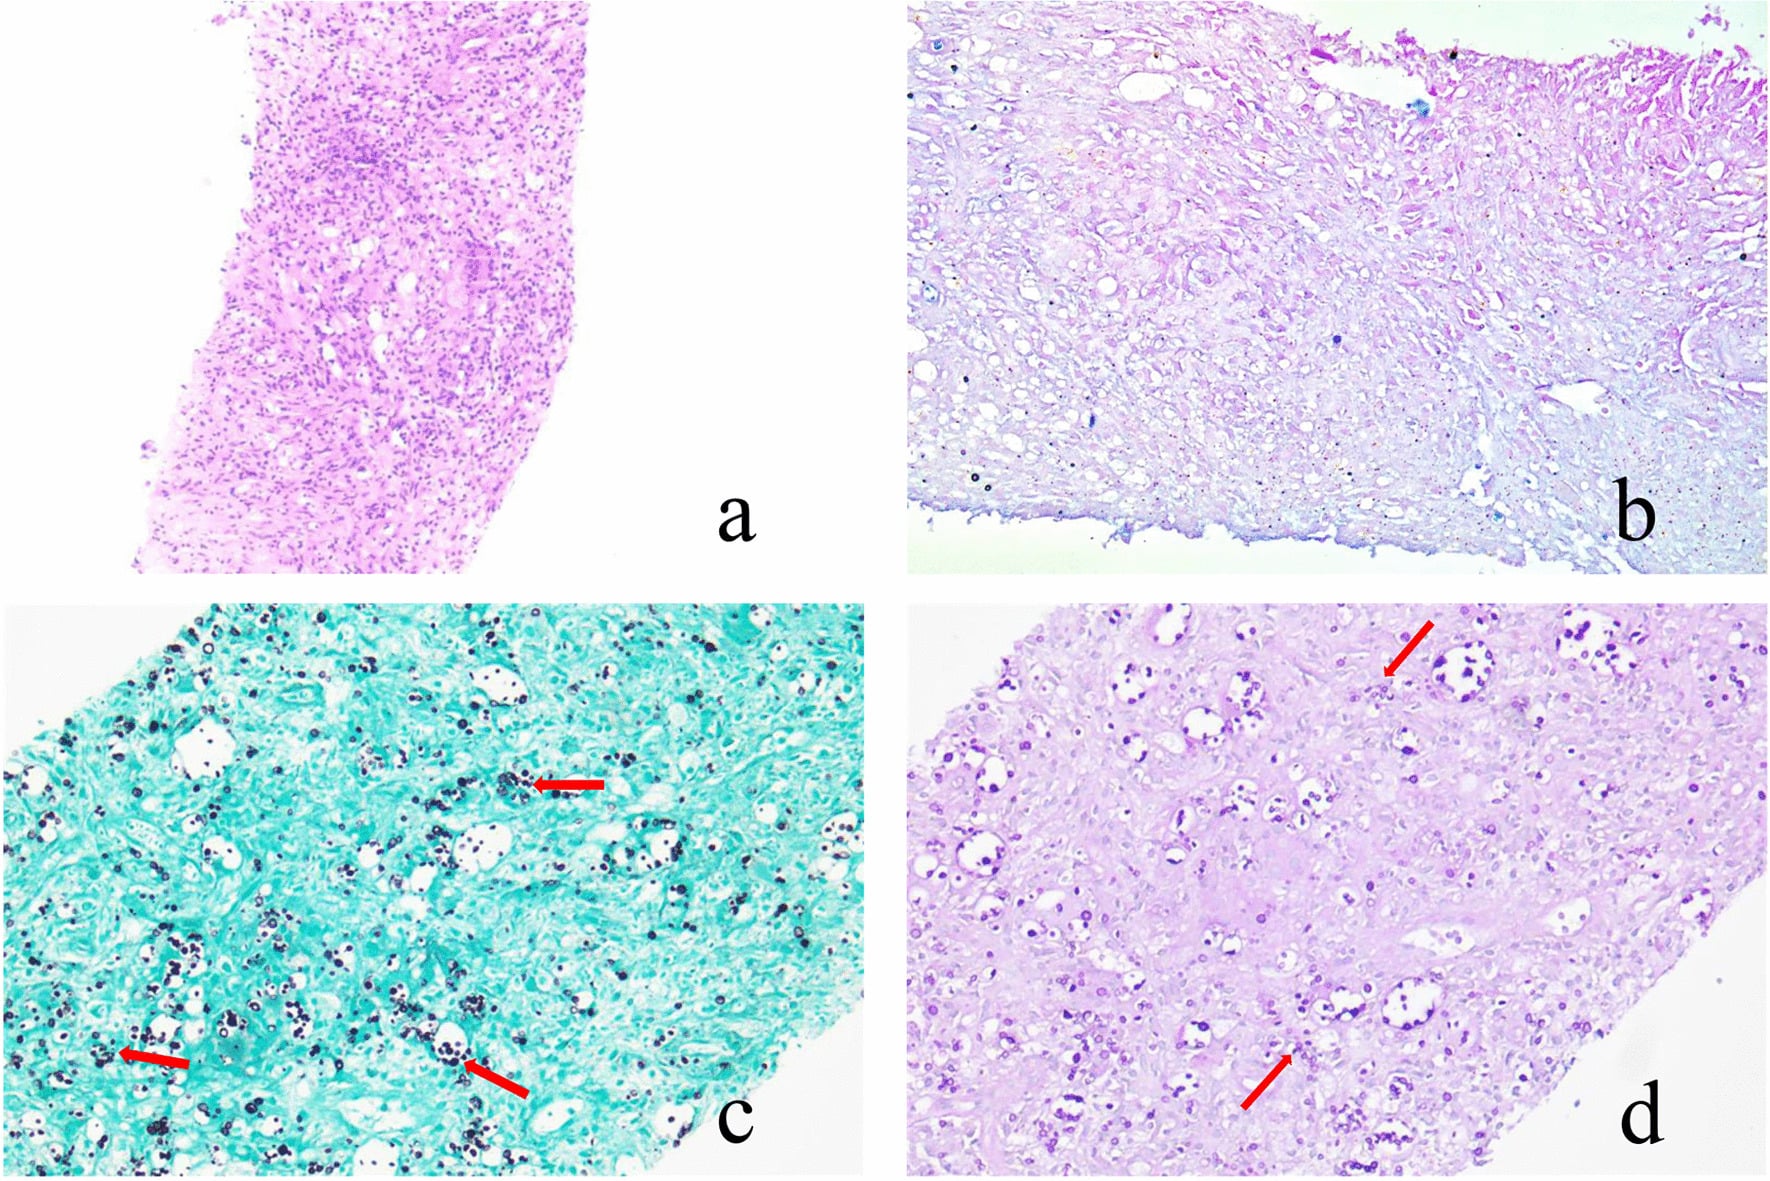
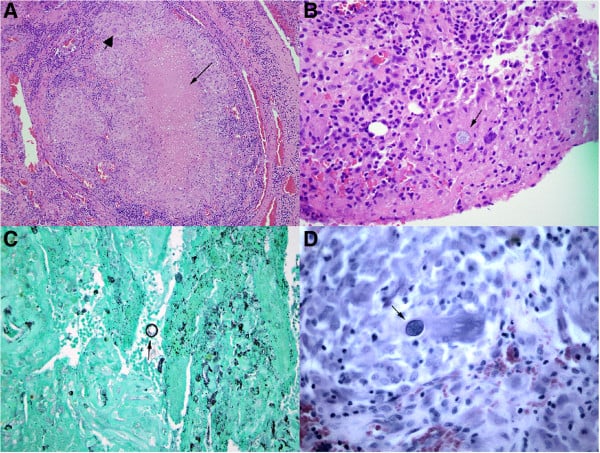
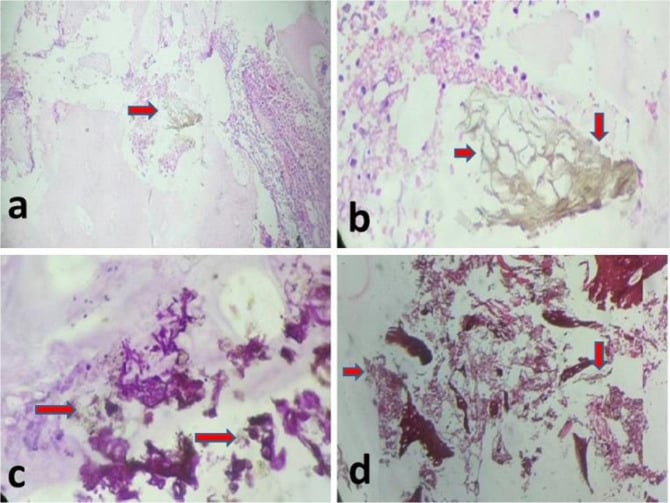
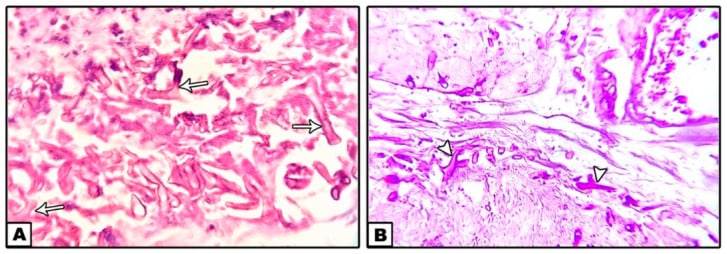
Management
Principles. Treatment is long, and the drug is chosen by the organism:
- Prolonged treatment, 6-12 months minimum, much longer than for bacterial osteomyelitis
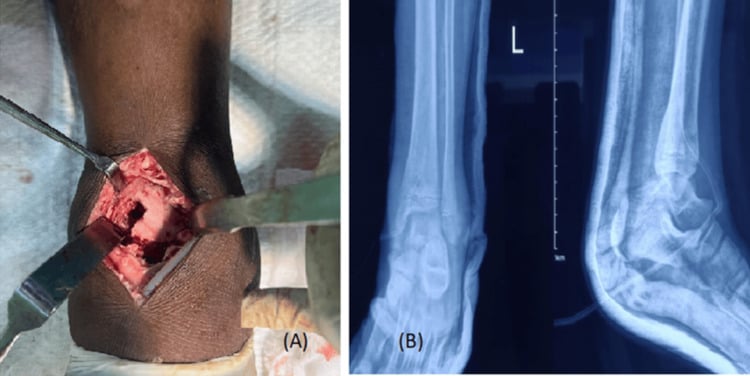
- Source control: surgical debridement is often required
- Treat the underlying immunocompromise to improve host defences
- Monitor drug levels, especially voriconazole and posaconazole
- Watch for toxicity: hepatic, renal, and visual with voriconazole
Duration should be individualised to the clinical and radiological response.
- First-Line Agent
- Fluconazole 400-800mg daily
- Alternative
- Amphotericin B or echinocandin
- Duration
- 6-12 months
- First-Line Agent
- Echinocandin then oral azole
- Alternative
- Amphotericin B
- Duration
- 6-12 months
- First-Line Agent
- Voriconazole 6mg/kg then 4mg/kg BD
- Alternative
- Isavuconazole, liposomal AmB
- Duration
- 6-12 months minimum
- First-Line Agent
- Fluconazole 400-800mg daily
- Alternative
- Itraconazole, amphotericin B
- Duration
- 12+ months, may be lifelong
- First-Line Agent
- Itraconazole 200mg BD
- Alternative
- Amphotericin B induction for severe
- Duration
- 6-12 months
- First-Line Agent
- Itraconazole 200mg BD
- Alternative
- Amphotericin B for severe
- Duration
- 12 months
- First-Line Agent
- AmB + flucytosine induction, then fluconazole 400-800mg daily
- Alternative
- -
- Duration
- 6-12 months, secondary prophylaxis in HIV
The drugs. Fluconazole is first-line for Candida, Cryptococcus and Coccidioides; itraconazole for blastomycosis and histoplasmosis, and as step-down therapy. Amphotericin B is kept for severe or life-threatening infection and for induction.
Candida. Fluconazole 400-800mg daily treats susceptible species. Amphotericin B (deoxycholate or liposomal) is for severe infection or azole resistance, and the echinocandins (caspofungin, micafungin) are the alternative for azole-resistant species. Debridement is recommended for an abscess, instability or poor response. Outcomes are less reassuring than the drug list suggests: in the 207-case review complete response was only 32%, with relapse in 32% of responders, and relapse is driven by inadequate duration.
Aspergillus. Voriconazole is first-line for invasive aspergillosis, including osteomyelitis, and has excellent bone penetration. Isavuconazole is the alternative with better tolerability, and liposomal amphotericin B is for severe disease or voriconazole intolerance. Voriconazole needs care:
- Monitor liver function and visual symptoms
- Drug-drug interactions are common, so check every medication
- Success requires immune recovery: continue until neutrophil recovery and immune reconstitution, and consider secondary prophylaxis
Coccidioides. The course is chronic and relapsing, and immunocompromised patients may need lifelong suppression.
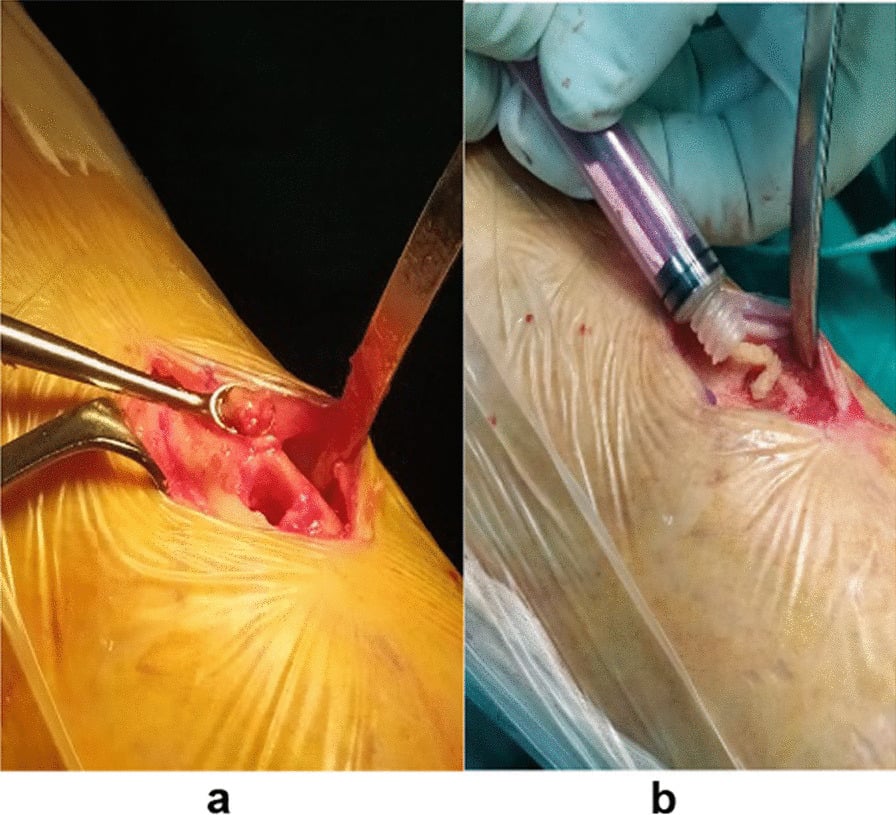
Mucormycosis - the Missing Angioinvasive Mould
The organism and the host. Mucormycosis (Rhizopus, Mucor and related Mucorales) is angioinvasive like Aspergillus, causing vascular thrombosis and tissue infarction and necrosis (black eschar). The classic host has diabetes with ketoacidosis, and neutropenia, transplant, and iron overload or deferoxamine also predispose. It reaches bone from rhino-orbital-cerebral disease (skull base, maxilla) or through a contaminated wound.
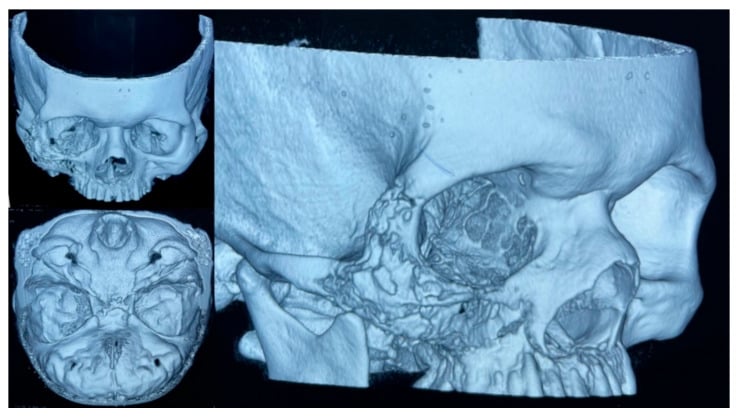
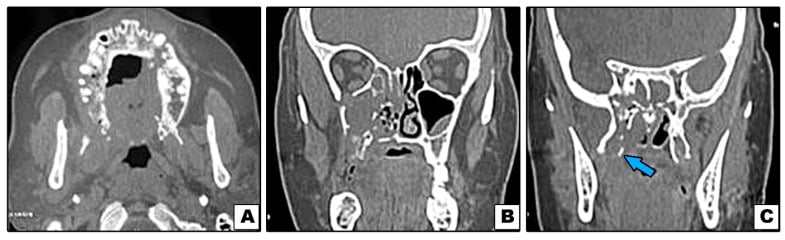
Diagnosis needs tissue. Beta-D-glucan and galactomannan are both negative with Mucorales, so serology does not help. The biopsy separates it from Aspergillus (see Telling the Fungi Apart on the Biopsy).
Treatment is amphotericin and urgent radical surgery, not voriconazole. First-line is liposomal amphotericin B with early, aggressive surgical debridement, because the infarcted tissue is avascular and drugs cannot reach it. Mortality is high.
- Reverse the underlying state: correct ketoacidosis, reduce immunosuppression, stop deferoxamine
- Isavuconazole or posaconazole for step-down or salvage
- Mucorales are intrinsically resistant to voriconazole, so breakthrough mucormycosis can occur in a patient on voriconazole prophylaxis
Guidelines, Registries & Global Practice
Global Epidemiology
Fungal osteomyelitis accounts for under 1% of all osteomyelitis but is rising worldwide with expanding immunocompromised populations and global travel. Geography drives the organism:
- Candida - the leading fungal cause globally; linked to candidaemia, central venous catheters, parenteral nutrition, and injecting drug use.
- Aspergillus - worldwide environmental mould; bone disease clusters in haematology/transplant centres but also occurs after trauma or surgery in immunocompetent hosts.
- Endemic mycoses are geographically anchored: Coccidioides (southwestern USA, Mexico, parts of Central/South America), Blastomyces and Histoplasma (Mississippi/Ohio River valleys, Great Lakes, and focally in Africa/Asia), Talaromyces marneffei (Southeast Asia in advanced HIV).
- Cryptococcus gattii - historically associated with tropical/subtropical regions and eucalyptus, with well-described endemicity in Australia and a notable Pacific Northwest (Vancouver Island) outbreak; unlike C. neoformans it can affect immunocompetent hosts and occasionally causes lytic bone lesions mimicking tumour.
Most fungal osteomyelitis affects immunocompromised hosts, but Cryptococcus gattii can cause osteomyelitis in immunocompetent patients. In any patient from an endemic region (including Australia, the Pacific Northwest, or tropical Asia) presenting with a lytic bone lesion mimicking tumour, keep cryptococcal infection in the differential and obtain tissue.
Major Guidelines Side by Side
- First-Line
- Voriconazole
- Key Recommendation
- Voriconazole primary; isavuconazole or liposomal AmB alternatives; TDM advised; surgery for osteomyelitis
- First-Line
- Voriconazole or isavuconazole
- Key Recommendation
- Concordant with IDSA; strong emphasis on TDM and reversal of immunosuppression
- First-Line
- Fluconazole or echinocandin step-down
- Key Recommendation
- 6-12 months therapy; surgical debridement for extensive disease; remove infected hardware
- First-Line
- Fluconazole 400-800mg/day
- Key Recommendation
- Bone/joint disease 12+ months; surgery for abscess/instability; travel history is key
- First-Line
- AmB + flucytosine induction, fluconazole consolidation
- Key Recommendation
- Long-course azole; secondary prophylaxis in HIV until immune reconstitution
Registry & Surveillance Notes
- No arthroplasty-style registry captures fungal osteomyelitis; the evidence base is pooled international case reviews (e.g. the International Osteoarticular Mycoses Study Consortium series for Candida and Aspergillus).
- National antifungal-resistance surveillance (e.g. CDC, ECDC/EUCAST, and the WHO Fungal Priority Pathogens List, 2022) increasingly tracks azole-resistant A. fumigatus and emerging multidrug-resistant Candida (incl. C. auris) - relevant when empirical azole therapy fails.
High- vs Limited-Resource Practice Variation
- Species identification, susceptibility testing, and PCR widely available
- Therapeutic drug monitoring for voriconazole/posaconazole routine
- Newer agents (isavuconazole, liposomal AmB, echinocandins) accessible
- Image-guided biopsy and MRI standard
- Reliance on histopathology (GMS/PAS) and clinical/travel history
- Fluconazole and amphotericin B deoxycholate are mainstays; deoxycholate AmB toxicity a major issue
- Limited TDM and susceptibility testing
- Endemic mycoses and HIV-associated fungal disease carry higher burden
Across all settings, involve infectious diseases early for organism-directed therapy, duration, and management of drug interactions and toxicity.
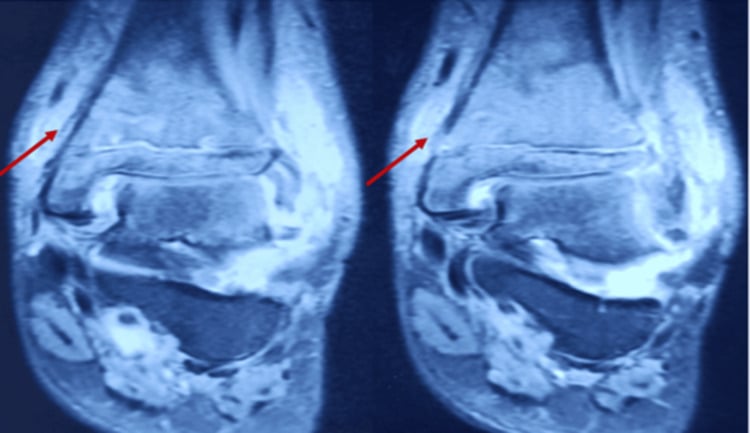
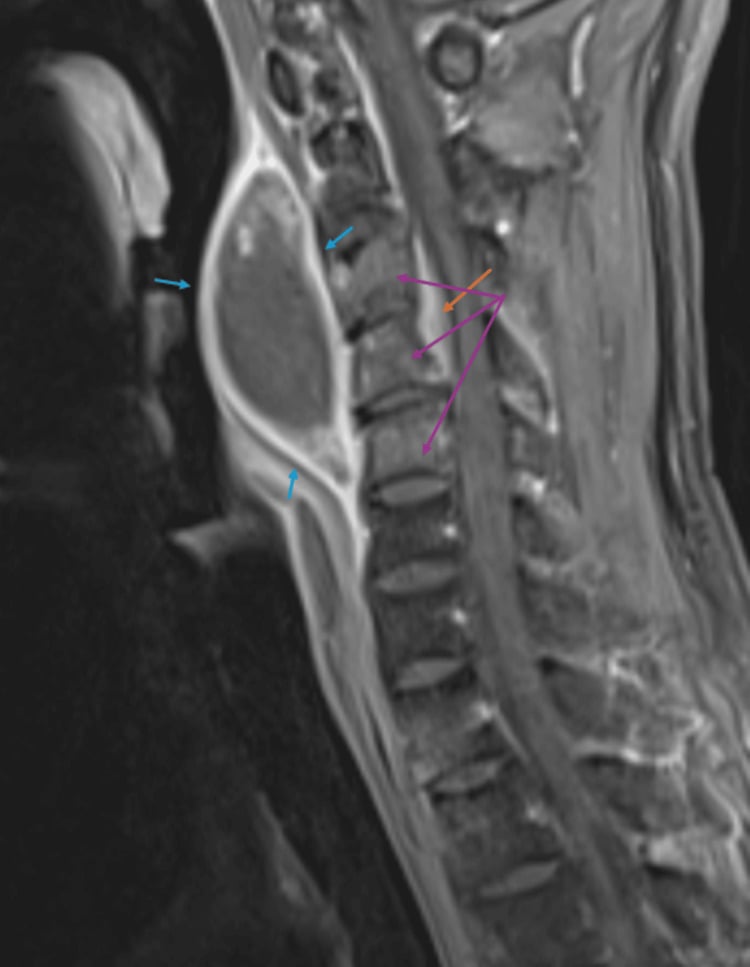
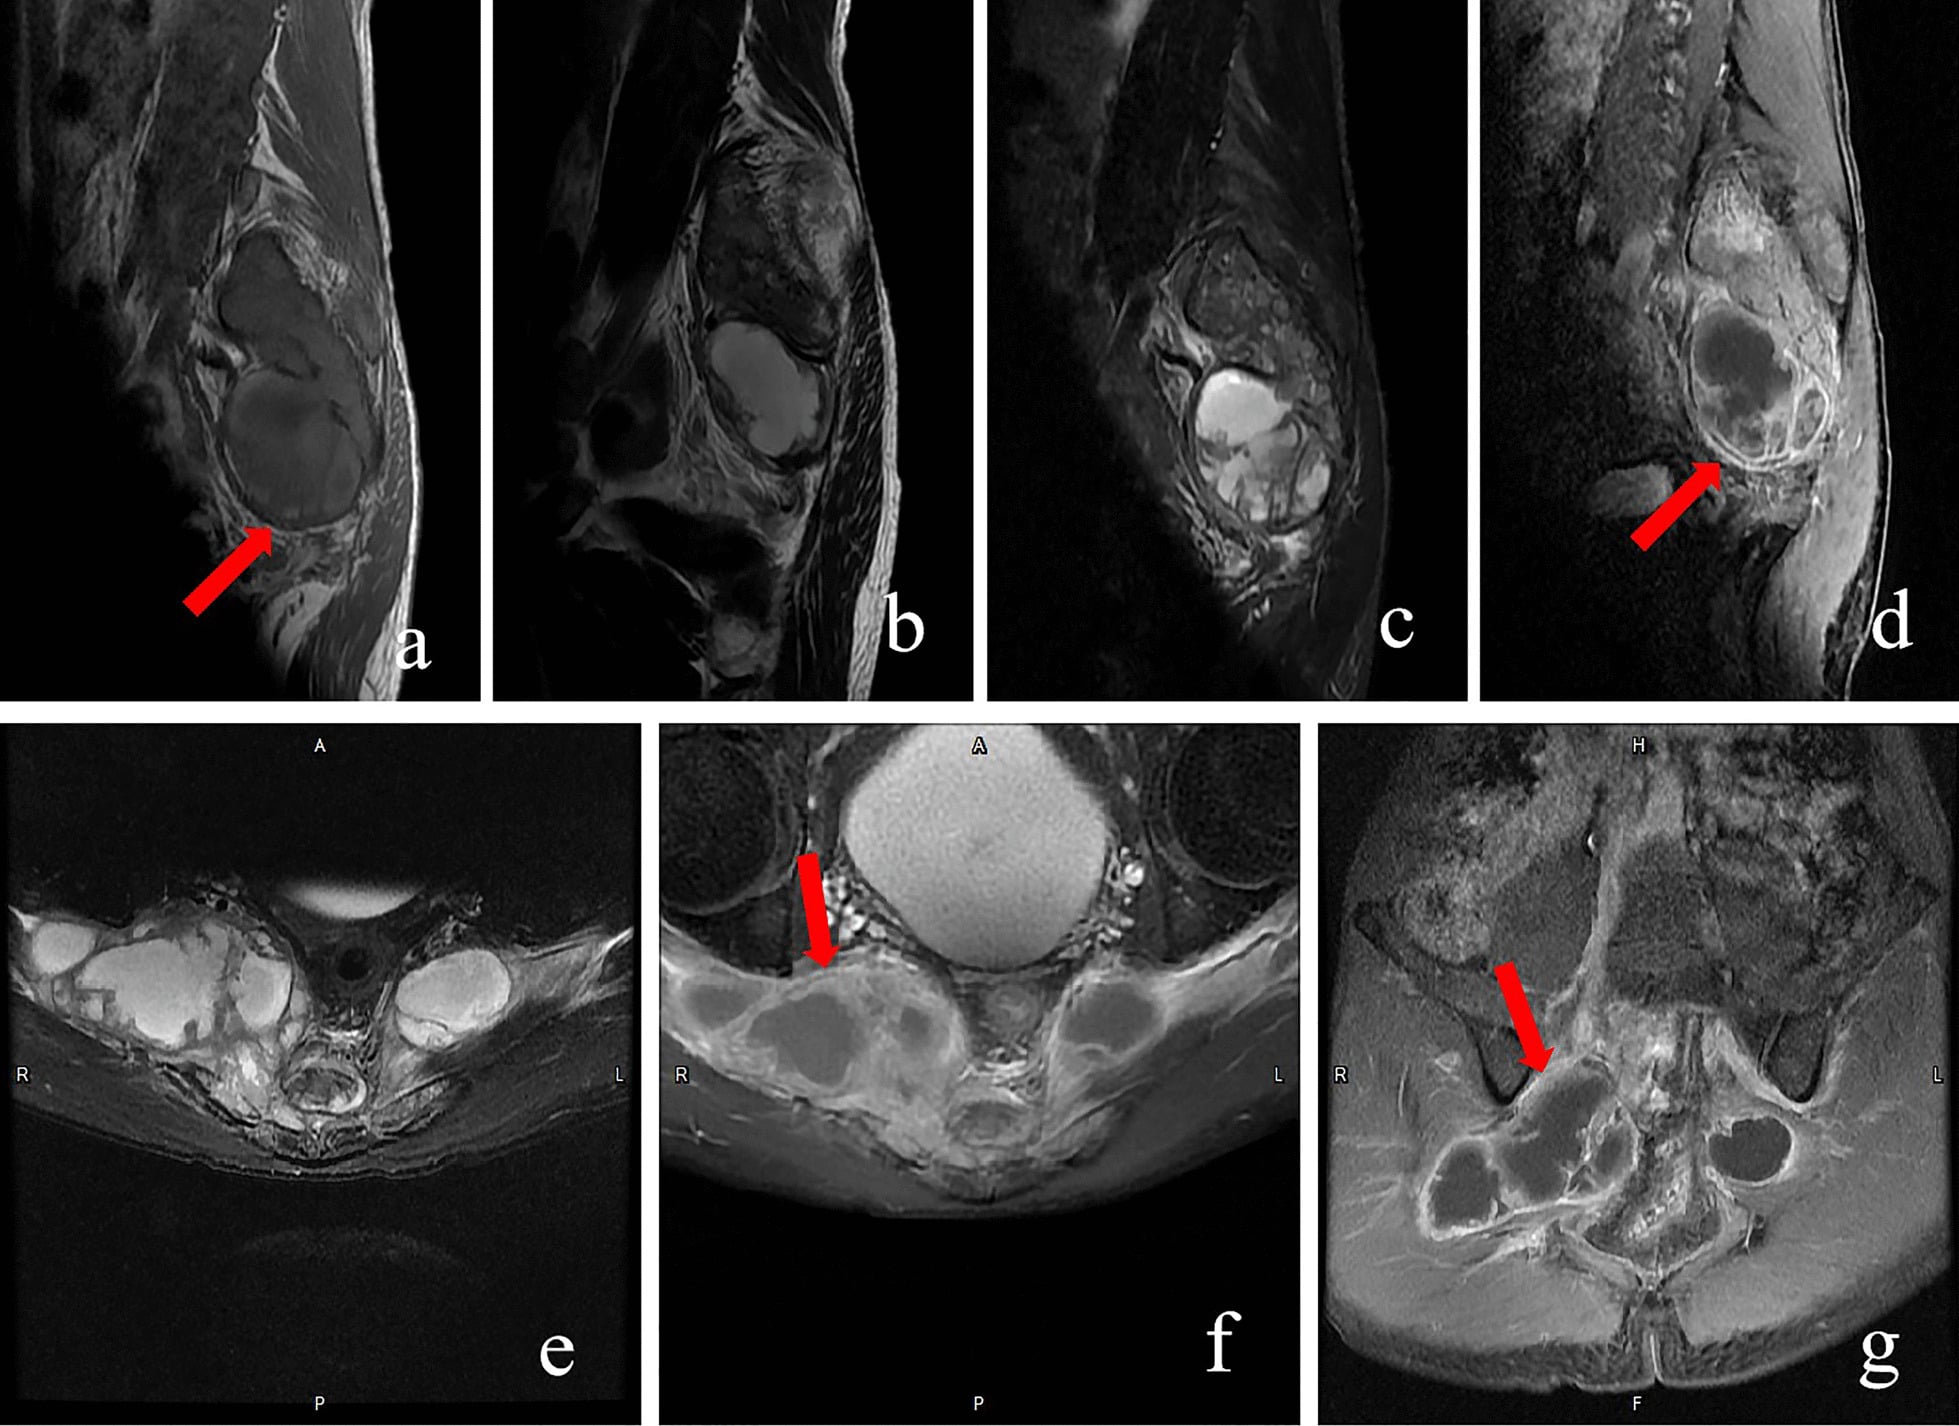
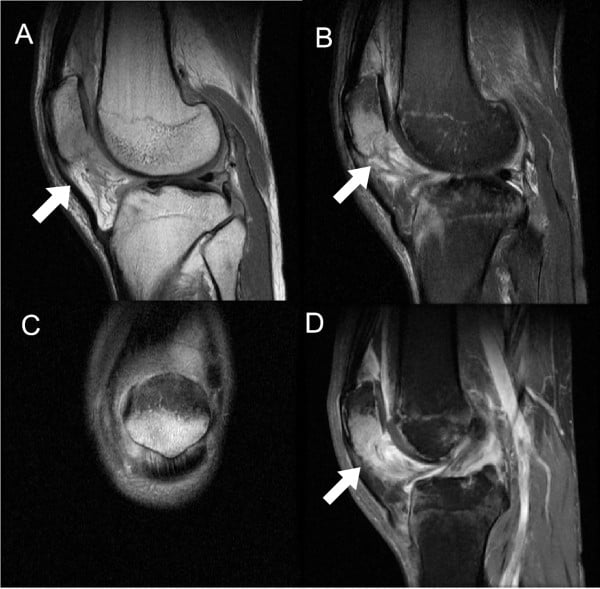
Related pages: Osteomyelitis Pathophysiology is the parent framework, and the contrast is the point - fungal bone infection follows the same routes (haematogenous, contiguous, direct inoculation) but declares itself over months, with an indolent course and normal or near-normal inflammatory markers that make it look like anything except infection. Fungal Spine Infections covers the vertebral disease that dominates the adult series on this page, and Atypical Mycobacterial Infection with Tuberculosis of the Spine (Pott's Disease) and Brucellosis of the Spine are the rest of the chronic granulomatous, culture-negative differential - the single most useful habit on all four pages is to tell the laboratory what you suspect, because none of these organisms grows on a standard five-day plate. Periprosthetic Joint Infection is where Candida arrives on an implant and where the decision to remove the prosthesis is effectively made by the diagnosis, with Biofilm Formation explaining why. Septic Arthritis Pathophysiology matters because Candida septic arthritis coexisted with osteomyelitis in 21% of the largest series. Orthopaedic Antibiotic Therapy and Antibiotic Pharmacology and Resistance carry the azole pharmacology, the therapeutic drug monitoring that voriconazole requires and the interactions that make it difficult in transplant patients. Systematic Approach to Infection Imaging covers the MRI appearances, and Diabetic Foot Infections is the setting in which an indolent, non-healing osteomyelitis most often turns out to be fungal.
Controversies & Areas of Uncertainty
"6-12 months" is convention, not RCT-proven. With complete-response rates around 32% and relapse in roughly a third of responders (Gamaletsou Candida series), the true minimum effective duration - and when to stop in immunocompromised hosts - remains undefined.
Surgery clearly reduces relapse in Aspergillus and improves response in mould infection, but the threshold for debridement in indolent Candida or endemic-mycosis bone disease is not standardised, and selection bias clouds the observational data.
Beta-D-glucan and galactomannan are validated for invasive fungal disease broadly, not for osteomyelitis specifically. Their performance for diagnosing or monitoring bone infection (and whether falling levels reliably signal cure) is unproven.
Azole-resistant Aspergillus fumigatus and multidrug-resistant Candida (including C. auris) challenge the "fluconazole/voriconazole first" paradigm. How best to empirically cover resistant organisms in culture-negative bone disease is an open question.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 35-year-old IV drug user presents with 3 months of progressive lower back pain. MRI shows L2-L3 vertebral osteomyelitis with disc involvement. Blood cultures are negative. He has been on empirical flucloxacillin for 4 weeks with no improvement. What is your differential diagnosis and management plan?”
“A 55-year-old woman 6 weeks post-allogeneic stem cell transplant for AML presents with worsening left shoulder pain and fever. She is on immunosuppression and has been neutropenic. CT shows aggressive destruction of the proximal humerus with soft tissue extension. What organism do you suspect and how would you manage this?”
“A 40-year-old man presents with 4 months of left knee pain. He returned from a 6-month work assignment in Arizona, USA 3 months ago. Imaging shows a lytic lesion in the distal femur. Biopsy shows granulomatous inflammation. What is your diagnosis and management?”
Key Organisms
- Candida = MOST COMMON fungal osteomyelitis overall
- Aspergillus = immunocompromised, aggressive, high mortality
- Coccidioides = SW USA endemic, soil exposure
- Cryptococcus gattii = endemic regions, can affect IMMUNOCOMPETENT
Risk Factors
- Chemotherapy, AIDS/HIV, Neutropenia
- Diabetes, IV drug use, Dialysis/central lines
- Transplant, Oral steroids, Soil exposure, TPN
Diagnosis
- TISSUE BIOPSY is ESSENTIAL - blood cultures often negative
- GMS and PAS stains for fungi
- Fungal culture takes 4-6 weeks
- 1,3-beta-D-glucan = nonspecific, supports diagnosis
- Galactomannan = more specific for Aspergillus
Treatment
- Fluconazole = Candida, Cryptococcus, Coccidioides
- Voriconazole = Aspergillus (first-line)
- Itraconazole = Blastomycosis, Histoplasmosis
- Duration 6-12 MONTHS (much longer than bacterial)
- Surgical debridement often required
Key Exam Points
- INDOLENT course - delayed diagnosis is common
- Think fungal if: culture-negative, not responding to antibiotics
- Aspergillus needs voriconazole plus early surgical review; operate where feasible for source control or stability
- Travel history for endemic mycoses is crucial
Global Practice
- Cryptococcus gattii can affect IMMUNOCOMPETENT hosts in endemic regions
- Endemic mycoses are geographically anchored - take a travel history
- Voriconazole plus early surgical review is the guideline strategy for Aspergillus (IDSA/ESCMID)
- Watch for azole-resistant A. fumigatus and C. auris when empirical azoles fail
Evidence Base
Candida Osteomyelitis: Landmark Analysis of 207 Cases
- Review of 207 evaluable cases (1970-2011); median age 30 years, male:female greater than 2:1
- 90% of patients were NOT neutropenic - immunocompetence does not exclude Candida bone disease
- Hematogenous mechanism in 67%, direct inoculation 25%, contiguous 9%
- Adults: vertebrae most common; children: femur most common; non-albicans species 35%
- Combined surgery plus antifungal in 48%; complete response only 32%; relapse in 32% of responders
Aspergillus Osteomyelitis: Surgery Reduces Relapse
- Review of 180 evaluable protocol-defined cases of Aspergillus osteomyelitis
- Most common sites: vertebrae 46%, cranium 23%, ribs 16%, long bones 13%
- Affected immunocompromised AND immunocompetent hosts (41% had prior fracture, trauma, or surgery)
- Overall mortality 25%; vertebral disease complicated by cord compression in 47%
- Surgery plus antifungal therapy had far fewer relapses than antifungals alone (8% vs 30%, P = 0.006)
IDSA Guideline: Coccidioidomycosis (incl. Bone & Joint)
- 2016 IDSA clinical practice guideline spanning the full spectrum of coccidioidomycosis
- Residence in or travel to endemic areas is the critical element for recognition
- Bone and joint disease requires prolonged oral azole therapy (typically 12+ months)
- Surgical debridement indicated for abscess, bony instability, or failure of medical therapy
- At-risk and immunocompromised patients may need extended or lifelong suppressive therapy
1,3-Beta-D-Glucan for Diagnosis of Invasive Fungal Infection
- Meta-analysis of 16 studies, 2979 patients (594 with proven/probable invasive fungal infection)
- Pooled sensitivity 76.8% and specificity 85.3%; area under summary ROC curve 0.89
- Marked between-study heterogeneity; does not identify specific organism or site
- False positives with haemodialysis, certain antibiotics, and IVIG
- Useful adjunct but does NOT replace tissue diagnosis
Non-Aspergillus Mould Osteoarticular Infection: Combined Medical-Surgical Approach
- Systematic review of 145 osteoarticular infections from non-Aspergillus filamentous fungi (1970-2013)
- 62% immunocompromised; direct inoculation in 54.5% (trauma/puncture in children, prior surgery in adults)
- Scedosporium apiospermum (33%) and Lomentospora prolificans (16%) were the leading moulds
- Combined antifungal therapy plus surgery used in 69%, with overall response in 85.8%
- Single-agent voriconazole achieved response in 94.1% of hyalo-/phaeohyphomycosis cases
IDSA Guideline: Diagnosis & Management of Aspergillosis
- 2016 IDSA practice guideline for the diagnosis and management of aspergillosis
- Voriconazole recommended as primary therapy for invasive aspergillosis, including osteomyelitis
- Isavuconazole and liposomal amphotericin B are recommended alternatives
- Therapeutic drug monitoring of voriconazole advised given variable pharmacokinetics
- Surgery recommended for Aspergillus osteomyelitis and discitis alongside antifungal therapy
Reading the response rates together
Two outcome figures on this page look as though they compare, and they do not. The Candida series reports a complete response in 32%; the non-Aspergillus mould review reports an overall response in 85.8%. Taken at face value this says Scedosporium does better than Candida, which is almost certainly false. Three things separate them:
- Different endpoints. Complete response is a strict endpoint; overall response includes partial responses. They are not the same measurement and cannot be placed side by side.
- Different publication pressures. Both are reviews of published cases, but the rare-mould literature is smaller and newer, so a successfully treated Scedosporium osteomyelitis is a publishable case and a failure often is not.
- Different mechanisms, and therefore different patients. Mould osteoarticular infection is 54.5% direct inoculation - often a healthy child with a puncture wound and one surgically accessible focus. Candida osteomyelitis is two-thirds haematogenous, in patients with lines, prostheses and comorbidity, and frequently in more than one bone.
What both datasets agree on, and what should be carried forward, is the direction of the surgical signal: combined medical and surgical management outperformed antifungal therapy alone in every series here, and relapse is driven by inadequate duration - months, not weeks.