Monosodium Urate | Negatively Birefringent | Needle-Shaped Crystals
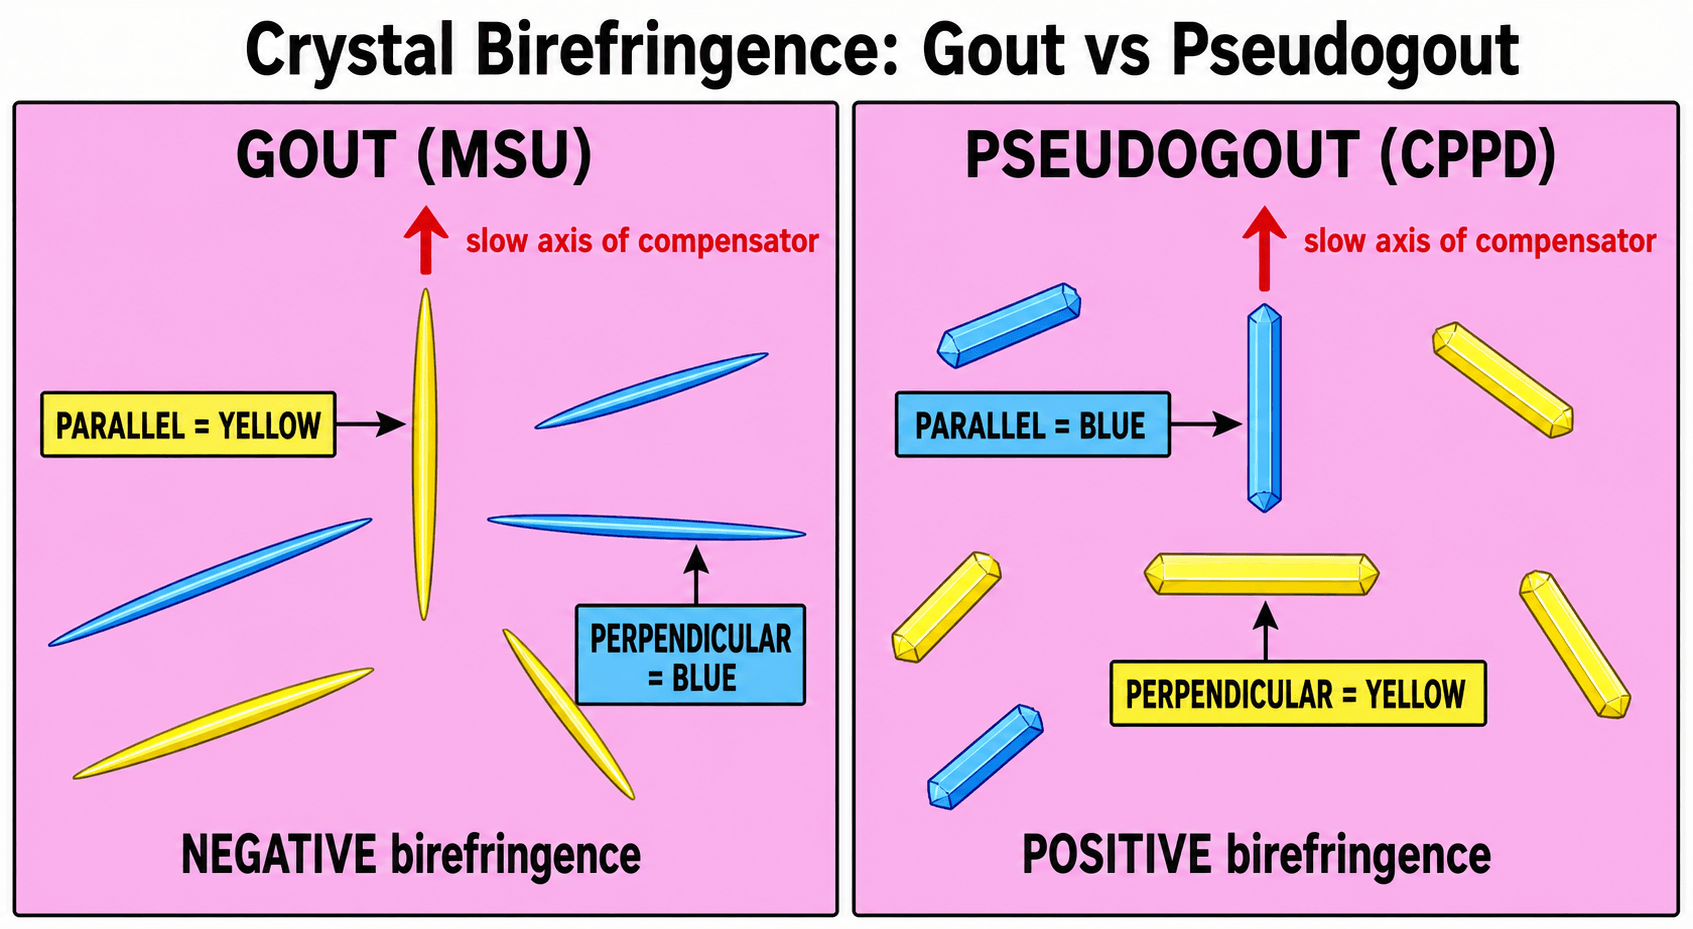
- MSU crystals are needle-shaped and negatively birefringent (yellow parallel to polarizer)
- Podagra (1st MTP involvement) is the classic presentation
- Joint aspiration is gold standard for diagnosis - even during acute attack
- Urate-lowering therapy target is serum urate less than 6 mg/dL (360 micromol/L)
- Surgical indications: mechanical symptoms, ulceration, infection, nerve compression
- “Negatively birefringent = yellow when parallel to polarizer axis
- “Acute attack: do NOT start allopurinol - may prolong attack
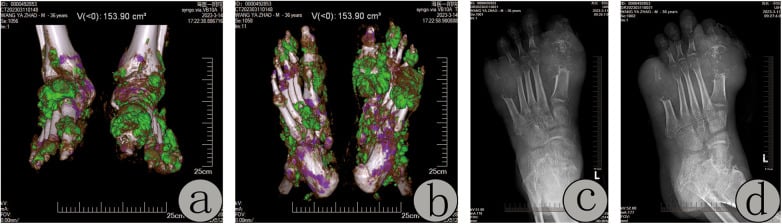
- “Dual-energy CT can identify urate deposits non-invasively
- “Tophi surgery: avoid primary closure over large defects
Overview and Epidemiology
Gout is the most common inflammatory arthritis in adults. It is caused by deposition of monosodium urate (MSU) crystals in joints and soft tissues, and it results from prolonged hyperuricaemia, crystals forming once serum urate exceeds its saturation point.
Who gets it. Prevalence is 1-4% of adults in developed countries, and it is rising with obesity, the metabolic syndrome and an ageing population. Men outnumber women 4:1, a ratio that equalises after the menopause; incidence peaks in men at 40-50 years and in women after the menopause.
Risk factors.
- Dietary: purine-rich foods (red meat, seafood), alcohol (especially beer), fructose-sweetened beverages
- Medications: thiazide diuretics, low-dose aspirin, ciclosporin
- Comorbidities: chronic kidney disease, metabolic syndrome, hypertension, obesity
- Genetic: variants in the urate transporters (URAT1, GLUT9)
Pathophysiology
Production. Uric acid is the end product of purine metabolism in humans. Purines come from the diet (exogenous) and from cellular turnover (endogenous), and xanthine oxidase converts hypoxanthine to xanthine and xanthine to uric acid. Humans lack uricase, the enzyme most mammals use to break uric acid down further, so the pathway stops there.
Excretion. About 70% of uric acid leaves through the kidney, by way of complex tubular handling, and 30% through the gut. The tubular transporters that matter are URAT1 (reabsorption), ABCG2 (secretion) and GLUT9.
Crystal formation. Monosodium urate saturates at 6.8 mg/dL (404 micromol/L). Below that level crystals gradually dissolve; above it they can precipitate in tissue. Several local factors favour crystallisation:
- Lower temperature, which explains the predilection for peripheral joints
- Lower pH (trauma, exercise-induced acidosis)
- Nucleating agents
- Connective tissue matrix components
The inflammatory response. The acute attack is an innate immune reaction to the crystal, run through the NLRP3 inflammasome:
- MSU crystals are phagocytosed by macrophages
- The crystals destabilise lysosomal membranes
- Cathepsin B is released into the cytoplasm
- NLRP3 inflammasome assembly is triggered
- Caspase-1 is activated
- Pro-IL-1beta is cleaved to active IL-1beta
- A massive inflammatory cascade follows
Because the cascade runs through IL-1beta, IL-1 inhibitors (anakinra, canakinumab) are effective in refractory gout.
Resolution. Attacks are self-limiting, settling in 7-14 days. Aggregated neutrophil extracellular traps (NETs) help resolve the inflammation, protein coating of the crystals reduces their immunogenicity, and an anti-inflammatory macrophage phenotype emerges.
Tophus Pathology and Composition
The tophus is the pathological hallmark of chronic gout and the structure the surgeon excises. What it actually is explains both its radiographic appearance and the principle that optimised urate-lowering therapy can dissolve it medically: a tophus is not a simple lump of crystal but an organised, chronic foreign-body granulomatous response to deposited monosodium urate.
Microscopic zones. A mature tophus has three concentric zones:
- Composition
- Densely packed needle-shaped MSU crystals in a protein and lipid matrix
- Significance
- The chalky white material seen at surgery; dissolves when serum urate is held below saturation
- Composition
- Macrophages and multinucleated foreign-body giant cells directly surrounding the crystals, with other inflammatory cells
- Significance
- The active inflammatory interface that drives adjacent bone and cartilage destruction
- Composition
- Fibroblasts, connective tissue and new vessels encapsulating the deposit
- Significance
- Walls the tophus off; the poorly vascularised overlying skin partly explains delayed wound healing after excision
Why tophi are reversible. The crystals are in equilibrium with the serum urate, so sustained urate-lowering therapy below the saturation point lets a tophus slowly dissolve (the target is set lower still when tophi are present; see Management). This is why many surgeons now favour debulking plus optimised medical therapy over aggressive wide excision, which risks an unclosable defect.
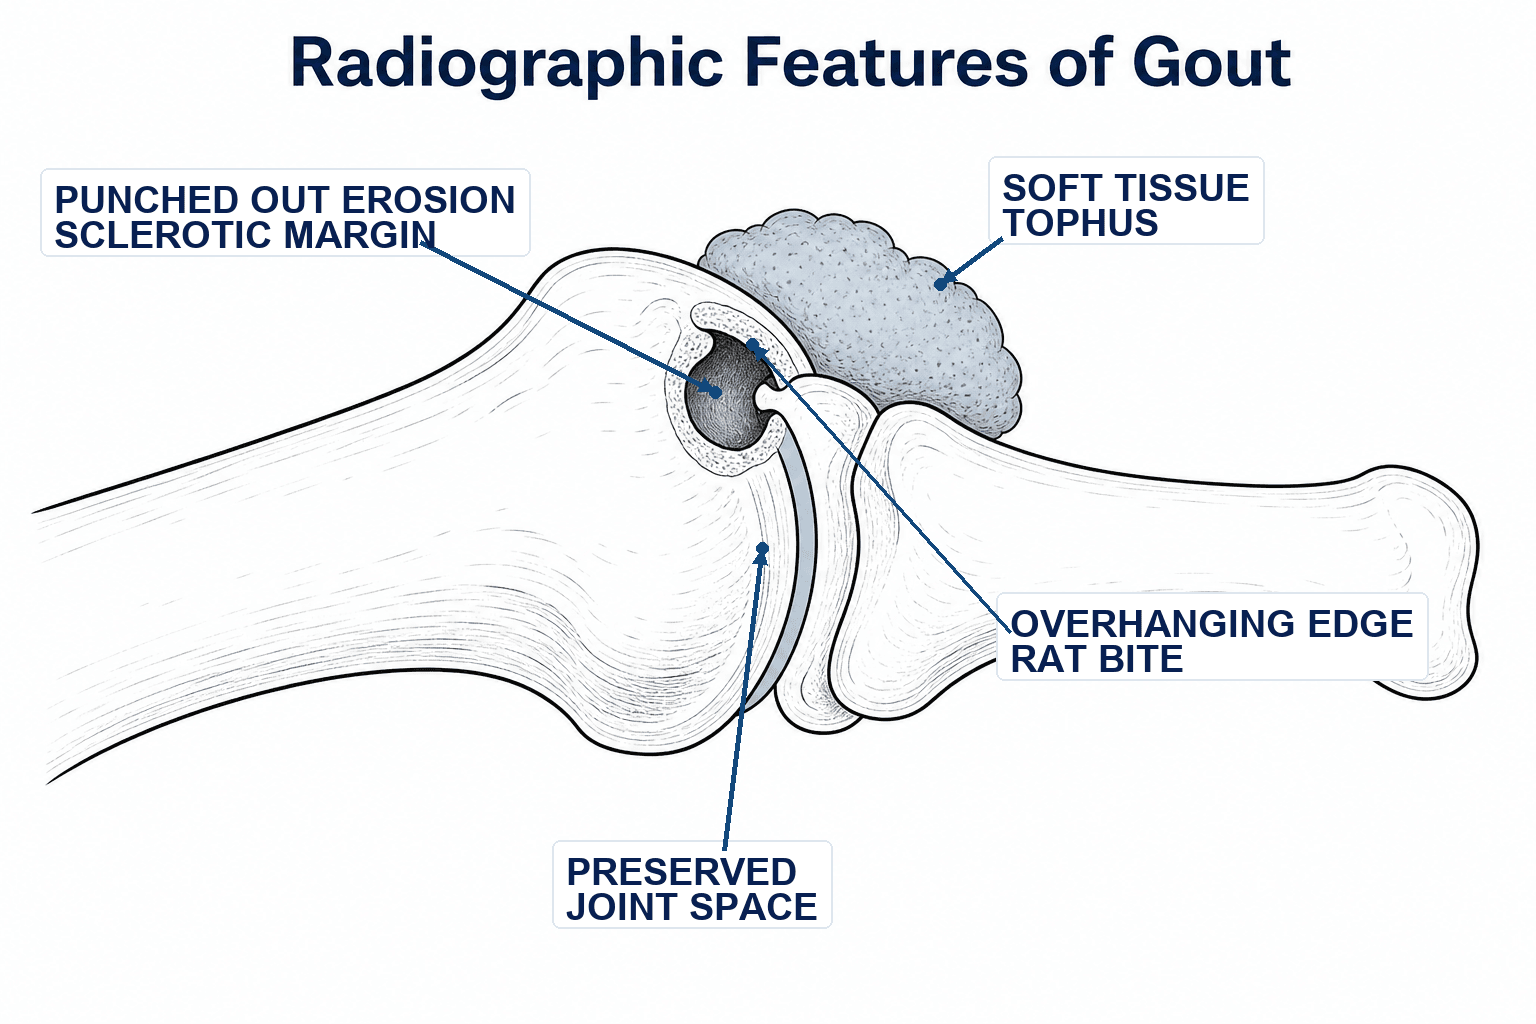
The punched-out erosions with overhanging edges arise at the tophus-bone interface: the cellular corona contains osteoclast-like cells and an inflammatory milieu that drive focal bone resorption, while the encapsulated crystal mass displaces the cortex, producing the characteristic overhanging edge of bone draped over the deposit, with the joint space preserved until late.
Clinical Presentation
The acute attack. Onset is rapid, over 6-12 hours, and often wakes the patient from sleep. The joint is exquisitely painful, to the point that the patient cannot tolerate the bedsheet touching it, and it is erythematous, warm and swollen enough to mimic cellulitis. The first attack is monoarticular in 85-90% of patients.
Where. The first metatarsophalangeal joint, podagra, is the classic site:
- First metatarsophalangeal joint (podagra) - 50% of first attacks
- Ankle and midfoot - 25%
- Knee - 15%
- Wrist, fingers, elbow - 10%
Chronic tophaceous gout. Tophi are chalky deposits of MSU crystals in soft tissue, found most often on the fingers, in the olecranon bursa, in the Achilles tendon and on the ears. The joints develop an erosive arthropathy in which the joint space is preserved initially; the tendon ruptures and nerve compressions of this phase are listed under Complications.
Examination. The acute joint is swollen, erythematous and warm, and so tender that even light touch is painful. Tophi are firm, irregular subcutaneous nodules, white-yellow through the skin, and in advanced cases the skin over them ulcerates.
Investigations
Synovial fluid analysis is the gold standard. Aspirate the joint (or a tophus) and look for MSU crystals under polarised microscopy: needle-shaped and negatively birefringent, yellow when parallel to the compensator slow axis and blue when perpendicular. The white cell count runs at 10,000-70,000/microL, predominantly neutrophils.
Serum urate. A level above the saturation point supports the diagnosis, but the serum urate may be normal during an acute attack (a paradoxical decrease). Send renal function as well, because chronic kidney disease is a common comorbidity, a lipid profile and glucose for the metabolic syndrome, and a full blood count, in which the white cell count is elevated during an attack.
Plain radiographs. Early in the disease they show soft-tissue swelling and normal bone. Established disease produces punched-out erosions with overhanging edges (the "rat bite" or "mouse ear"), a joint space that is preserved, unlike osteoarthritis, and soft-tissue tophi that may calcify.
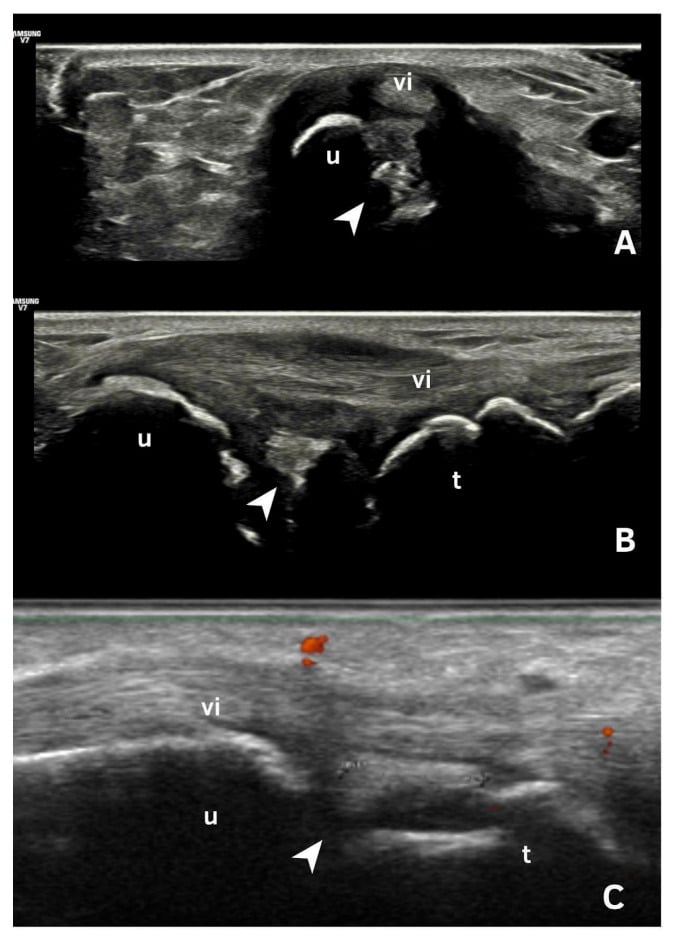
Ultrasound. The double contour sign is a hyperechoic line on the surface of the hyaline cartilage. Aggregates and tophi are also visible, and ultrasound is useful for guided aspiration.
Dual-energy CT. DECT colour-codes urate deposits, typically green, with a pooled sensitivity of about 0.87 and specificity of 0.84 (Ogdie meta-analysis). It is useful when aspiration is not possible and can detect occult tophi, but sensitivity is lower in early or acute gout and with small deposits (false negatives in disease under 6 weeks), and artefacts from the nail bed, skin and beam hardening can mimic urate.
Differential Diagnosis
The single most important mimic of acute gout is septic arthritis. The two can coexist, and a hot, swollen joint must be aspirated to exclude infection before attributing it to crystals.
- Gout (MSU)
- 1st MTP, midfoot, knee
- Pseudogout (CPPD)
- Knee, wrist, MCP
- Septic Arthritis
- Knee, hip; any joint
- Reactive/Psoriatic
- Knee, ankle, sacroiliac
- Gout (MSU)
- Hours, often nocturnal
- Pseudogout (CPPD)
- Subacute over days
- Septic Arthritis
- Hours to days, systemically unwell
- Reactive/Psoriatic
- Days to weeks
- Gout (MSU)
- 10,000-70,000/microL
- Pseudogout (CPPD)
- 10,000-50,000/microL
- Septic Arthritis
- Often greater than 50,000, up to 100,000+
- Reactive/Psoriatic
- 5,000-50,000/microL
- Gout (MSU)
- Needle, negatively birefringent
- Pseudogout (CPPD)
- Rhomboid, positively birefringent
- Septic Arthritis
- None
- Reactive/Psoriatic
- None
- Gout (MSU)
- Negative
- Pseudogout (CPPD)
- Negative
- Septic Arthritis
- May be positive (definitive)
- Reactive/Psoriatic
- Negative
- Gout (MSU)
- Crystals + podagra
- Pseudogout (CPPD)
- Chondrocalcinosis on X-ray
- Septic Arthritis
- Fever, raised CRP, positive culture
- Reactive/Psoriatic
- Enthesitis, skin/eye/GU features
Crystals and sepsis can occur in the same joint. If synovial WBC is very high, the patient is febrile, or CRP is markedly raised, treat as septic arthritis until cultures return - send fluid for urgent Gram stain and culture, not just crystal analysis.
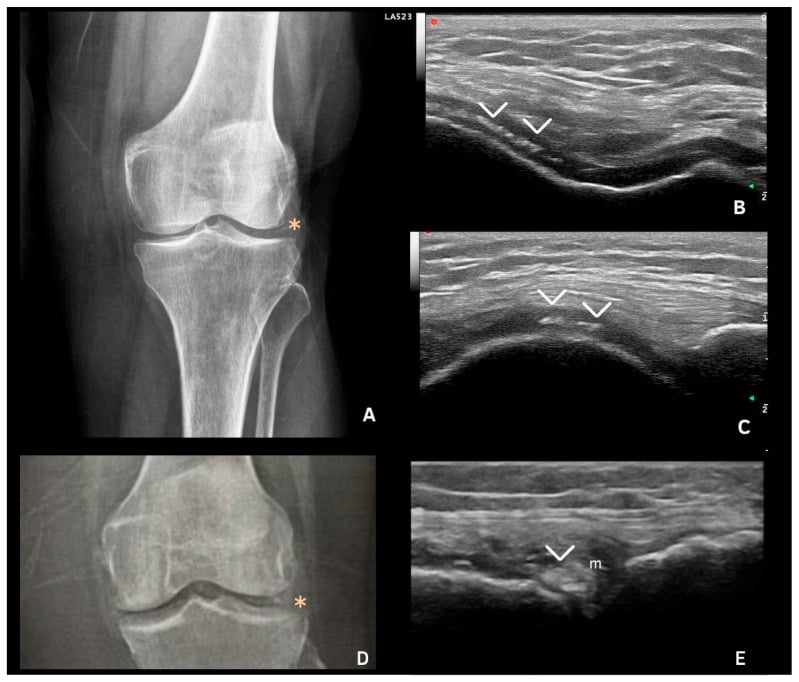
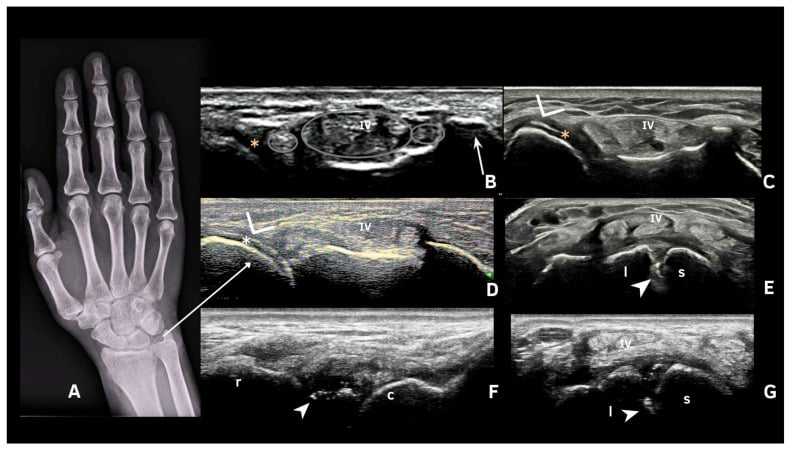
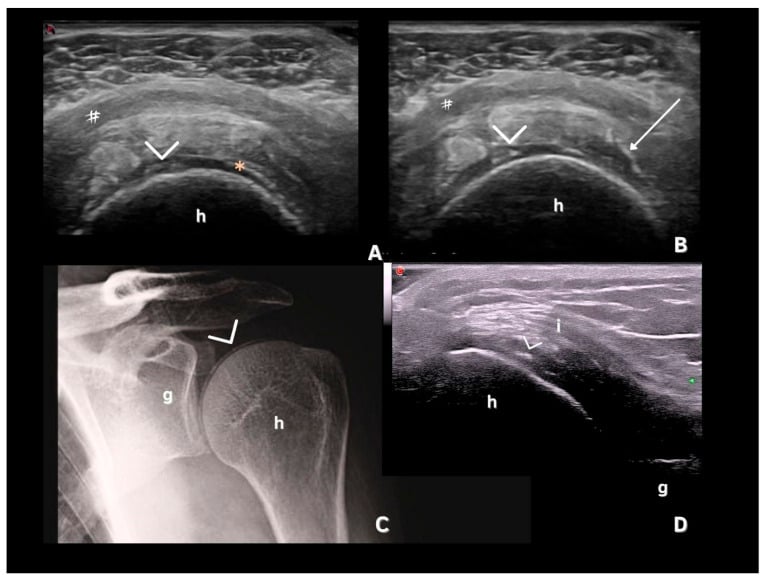
Pseudogout. Calcium pyrophosphate deposition is the crystal mimic to know. Its risk factors are age, osteoarthritis and metabolic disease, and unlike gout it has no specific therapy. Its imaging signature is chondrocalcinosis, shown below in the knee, wrist and shoulder.
Management
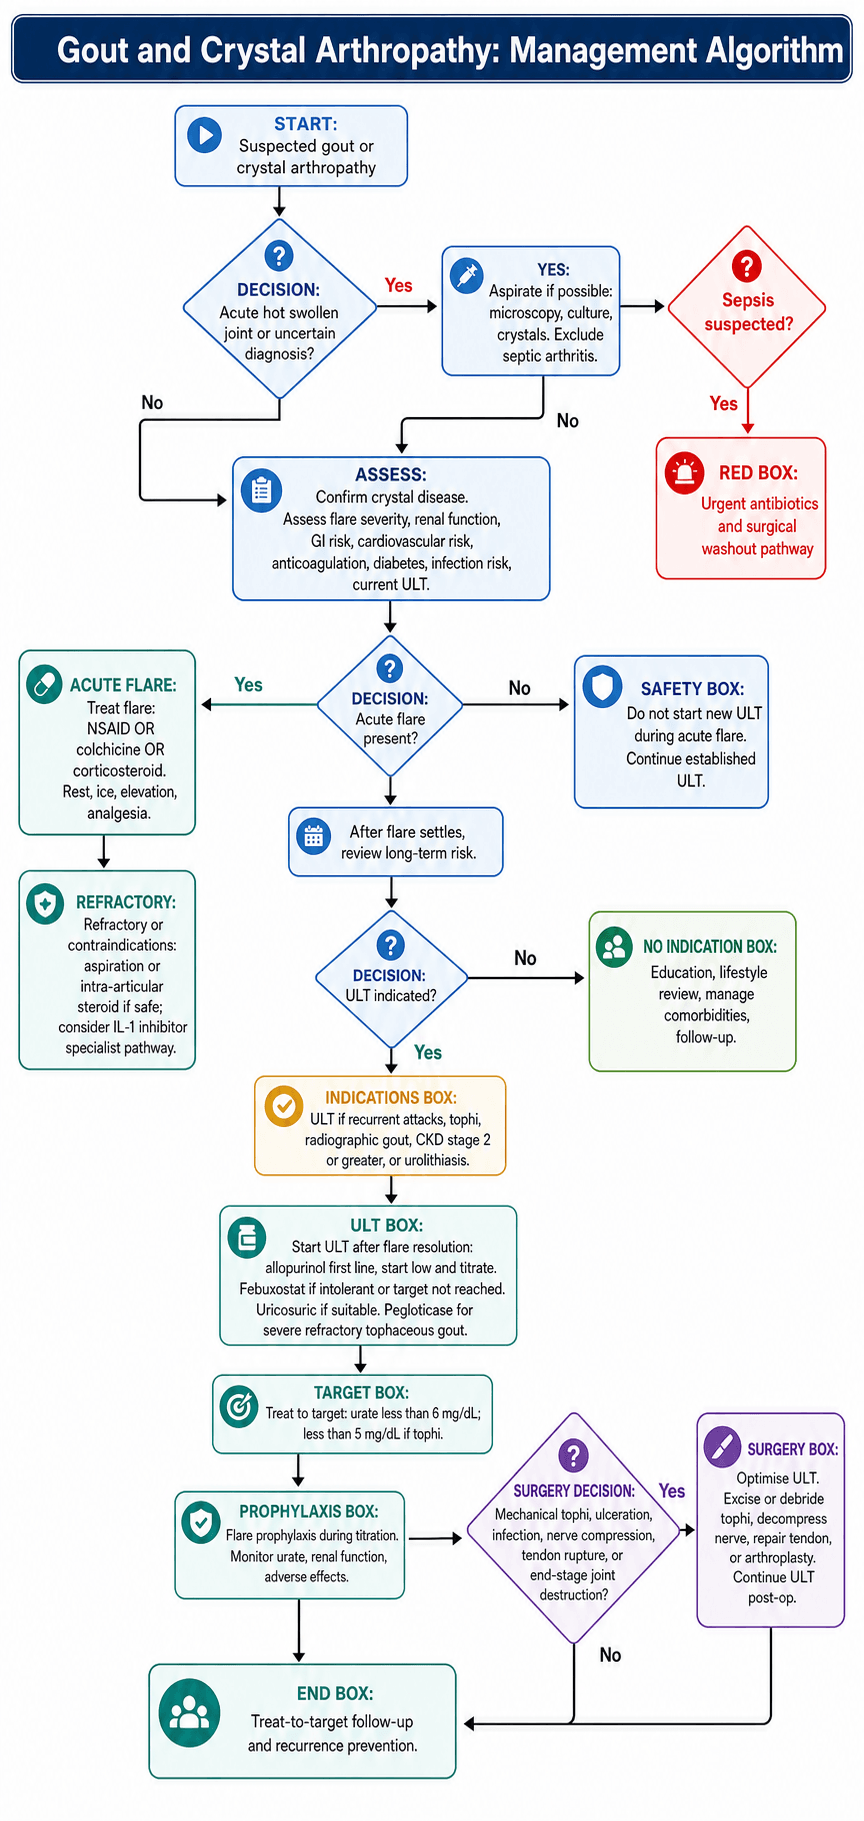
The acute attack. Three first-line options, and one thing not to do.
Starting allopurinol or febuxostat during an acute gout flare can prolong the attack by mobilising urate crystals. Treat the acute attack first, then initiate ULT 2-4 weeks after resolution. If ULT is already established, continue it. The ACR 2020 position, which permits starting allopurinol during a flare with prophylaxis, is discussed under Controversies.
The first-line options:
- NSAIDs: indomethacin 50mg TDS or naproxen 500mg BD, continued until the attack resolves
- Colchicine: most effective within 12 hours of onset. Loading dose 1mg, then 0.5mg one hour later; the low-dose regimen is preferred
- Corticosteroids: prednisolone 30-40mg daily for 5-7 days when the attack is polyarticular or the other agents are contraindicated, or an intra-articular injection for a monoarticular attack when NSAIDs are contraindicated
Refractory cases. IL-1 inhibitors (anakinra) are for patients with contraindications to all of the above. Joint aspiration alone provides significant relief.
Urate-lowering therapy. ULT is indicated for:
- Recurrent acute attacks (2 or more per year)
- Presence of tophi
- Radiographic changes
- Chronic kidney disease stage 2 or greater
- Urolithiasis
The agents.
- Allopurinol: first-line xanthine oxidase inhibitor. Start low (50-100mg, lower in CKD) and titrate to target. Consider HLA-B*58:01 testing before starting in high-risk ethnicities (Han Chinese, Thai, Korean with CKD) to reduce severe cutaneous adverse reactions (SCAR/SJS-TEN)
- Febuxostat: alternative if allopurinol is not tolerated or the target is not reached. More potent urate lowering; cardiovascular safety debated (see Controversies)
- Probenecid / benzbromarone (uricosurics): require adequate renal function and urine output; avoid with urolithiasis. Useful for under-excretors when xanthine oxidase inhibitors fail
- Pegloticase (recombinant uricase): for severe refractory tophaceous gout; rapidly dissolves tophi but immunogenic
The target. Serum urate below 6 mg/dL (360 micromol/L), and below 5 mg/dL if tophi are present, for faster dissolution.
Colchicine: Mechanism, Toxicity and Drug Interactions
Colchicine appears throughout gout management, in acute flares, as prophylaxis when starting urate-lowering therapy and as perioperative cover, yet how it works and why it is dangerous in overdose are commonly examined.
Mechanism. Colchicine is an anti-mitotic alkaloid that binds tubulin and prevents microtubule polymerisation. In gout this disrupts neutrophil function (chemotaxis, adhesion and motility) and impairs assembly and activation of the NLRP3 inflammasome, reducing IL-1beta-driven inflammation. It is anti-inflammatory only: it is not an analgesic and not urate-lowering, so it treats the crystal-induced inflammatory response and does nothing to the serum urate.
Toxicity.
- Effect
- Diarrhoea, nausea, vomiting, abdominal pain
- Note
- Dose-related and the earliest sign of toxicity - the reason low-dose regimens are now standard
- Effect
- Bone-marrow suppression (neutropenia, thrombocytopenia, pancytopenia)
- Note
- A feature of overdose or accumulation in renal or hepatic impairment
- Effect
- Myopathy and axonal neuropathy
- Note
- Especially with chronic use in renal impairment or combined with statins or fibrates
- Effect
- Multi-organ failure; narrow therapeutic index with no effective antidote
- Note
- Acute overdose can be fatal
Drug interactions. Colchicine is metabolised by CYP3A4 and is a substrate of the P-glycoprotein efflux transporter. Co-administration with strong inhibitors of either, clarithromycin and other macrolides, azole antifungals, ciclosporin, verapamil and diltiazem, raises colchicine levels and can precipitate life-threatening toxicity.
Diarrhoea is the warning sign and usually precedes serious toxicity. Reduce the dose in renal or hepatic impairment, halve or avoid it with CYP3A4/P-glycoprotein inhibitors (for example clarithromycin, ciclosporin, verapamil), and never escalate the dose to chase pain: there is no effective antidote.
Surgical Management
Indications. Six situations bring the patient to the surgeon:
- Mechanical symptoms: large tophi limiting joint motion or tendon function
- Skin ulceration over tophi, with the risk of secondary infection
- Secondary infection: debridement of infected tophi
- Nerve compression: carpal tunnel syndrome or ulnar neuropathy from tophi
- Joint destruction: arthroplasty for end-stage arthropathy
- Tendon rupture: repair or reconstruction
MUSICSurgical Indications for Tophi
Hook:When tophi cause problems, it's time to make MUSIC with surgery!
Before the operation. Medical management is optimised first, with ULT established. Assess the viability of the overlying skin and plan the closure before making the incision, and consider staging the procedure for large tophi.
Technique.
- Plan the incision to allow adequate exposure and closure
- Identify and protect the neurovascular structures
- Debulk the tophaceous material - chalky white deposits
- Curette affected bone if it is involved
- Assess tendon integrity
- Irrigate thoroughly
Closure. Close primarily if possible, avoiding tension on the skin. Large defects may need negative pressure wound therapy, and skin grafting or flap coverage may be required.
After the operation. Continue ULT to prevent recurrence, watch the wound as it heals, and start physiotherapy for range of motion.
Complications
Of the disease. The complications extend beyond the joint:
- Chronic erosive arthropathy: joint destruction, subluxation
- Tendon rupture: Achilles, patellar, extensor tendons
- Carpal tunnel syndrome: from tophaceous deposits
- Renal complications: uric acid stones, urate nephropathy
- Cardiovascular disease: an independent risk factor
Of surgery. The skin over a tophus is the recurring problem:
- Wound healing problems: skin necrosis, delayed healing over tophi
- Infection: risk increased with ulcerated tophi
- Recurrence: if ULT is not optimised
- Tendon injury: during tophus excision
Guidelines, Registries & Global Practice
Global Epidemiology
- Prevalence: ranges from under 1% to 6.8% of adults depending on population (Dehlin et al., Nat Rev Rheumatol 2020). Highest in Taiwanese aboriginal, Maori and Pacific Island populations (often greater than 6-10%), where reduced renal urate excretion and genetic urate-transporter variants combine with diet.
- Incidence: 0.58-2.89 per 1000 person-years; rising worldwide with obesity, ageing and metabolic syndrome.
- Sex/age: male predominance roughly 3-4:1, narrowing after menopause; peaks in men aged 40-60.
- Care gap: only one-third to one-half of patients ever receive urate-lowering therapy, and fewer than half adhere - the dominant problem in gout is implementation, not drug efficacy.
Side-by-side Guideline Comparison
- ACR 2020 (US)
- Allopurinol (incl. CKD)
- EULAR 2016 (Europe)
- Allopurinol; adjust dose to renal function
- BSR 2017 (UK)
- Allopurinol first-line
- ACR 2020 (US)
- Below 6 mg/dL (360 micromol/L), treat-to-target
- EULAR 2016 (Europe)
- Below 6 mg/dL; below 5 mg/dL (300) in severe/tophaceous
- BSR 2017 (UK)
- Below 5 mg/dL initially, then below 6 long-term
- ACR 2020 (US)
- May start during a flare (with prophylaxis)
- EULAR 2016 (Europe)
- Start after flare settles, plus prophylaxis
- BSR 2017 (UK)
- Once flare settled
- ACR 2020 (US)
- At least 3-6 months
- EULAR 2016 (Europe)
- At least 6 months
- BSR 2017 (UK)
- Up to 6 months
- ACR 2020 (US)
- Reserve for allopurinol failure (CV caution)
- EULAR 2016 (Europe)
- Second-line; caution if CV disease
- BSR 2017 (UK)
- Second-line if allopurinol intolerant
- ACR 2020 (US)
- Conditional in high-risk groups (e.g. Han Chinese, Thai, Korean CKD)
- EULAR 2016 (Europe)
- Consider in at-risk ethnicities
- BSR 2017 (UK)
- Consider in Han Chinese/Thai/Korean
Registry & Surgical Outcome Notes
- There is no dedicated international gout registry equivalent to arthroplasty joint registries, but national arthroplasty registries (NJR UK, AJRR US, AOANJRR Australia, SHAR Sweden) capture gout as a comorbidity. Crystal arthropathy is associated with modestly higher periprosthetic joint infection and wound-complication rates in some series, reinforcing the value of preoperative urate control.
- Hand-surgery series of tophaceous excision report good functional gain but real risks of delayed wound healing and recurrence if ULT is not optimised.
High- vs Limited-Resource Practice Variation
- Well-resourced settings: ready access to polarised microscopy, ultrasound and DECT; HLA-B*58:01 genotyping where indicated; biologic IL-1 inhibitors (anakinra, canakinumab) for refractory disease.
- Limited-resource settings: diagnosis often clinical or via serum urate; polarised microscopy and DECT may be unavailable. Allopurinol and colchicine are inexpensive and on the WHO model essential-medicines landscape, so treat-to-target ULT remains achievable even where advanced imaging is not. Counterfeit colchicine and lack of monitoring are practical hazards.
- Across all settings, cardiovascular and renal risk screening is integral given the strong, consistent association of gout with CKD and cardiovascular disease.
Controversies & Areas of Uncertainty
Febuxostat cardiovascular safety. CARES (29527974) showed higher all-cause and CV mortality with febuxostat versus allopurinol in patients with established CV disease, prompting an FDA boxed warning. The later EMA-mandated FAST trial (33181081) found febuxostat non-inferior with no excess mortality. The discrepancy (high CARES drop-out and on-treatment versus intention-to-treat handling) leaves the true CV risk unresolved; allopurinol remains the pragmatic first line.
Asymptomatic hyperuricaemia. Routine urate-lowering for asymptomatic hyperuricaemia is not recommended by ACR or EULAR; whether high-risk subgroups (CKD, CV disease) benefit remains debated.
Start ULT during a flare? ACR 2020 permits initiating allopurinol during an acute flare (with prophylaxis) on the basis that it does not prolong the attack; traditional teaching and many other guidelines still defer ULT until the flare settles. Either way, never stop established ULT during a flare.
Surgery for tophi. Timing and technique are not standardised; the case for debulking with optimised ULT rather than wide excision is made under Tophus Pathology.
Diet versus drugs. Dietary modification lowers urate only modestly (roughly 1 mg/dL). It supports but does not replace ULT, and over-emphasis can stigmatise patients and delay effective treatment.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 52-year-old obese man presents with sudden onset severe pain and swelling of his right first MTP joint. He woke at 3am unable to tolerate the bedsheet touching his foot. He drinks beer regularly. Examination shows an exquisitely tender, erythematous, swollen 1st MTP joint.”
“A 65-year-old man with a 15-year history of gout presents with a large tophus over his left olecranon causing skin breakdown. He has limited elbow flexion. Serum urate is 9.2 mg/dL despite allopurinol 300mg daily.”
“You are shown a polarized microscopy image of synovial fluid showing needle-shaped crystals that appear yellow when aligned parallel to the polarizer. What is your diagnosis?”
Crystal Identification
- MSU: Needle-shaped, negatively birefringent (YELLOW parallel)
- CPPD: Rhomboid, positively birefringent (BLUE parallel)
- Mnemonic: 'Yellow Parallel Gout' vs 'Blue Parallel Pseudogout'
Classic Presentation
- Podagra: 1st MTP involvement (50% of first attacks)
- Sudden onset, often nocturnal (3-4am)
- Exquisitely tender - cannot tolerate bedsheet
Imaging Signs
- Punched-out erosions with overhanging edges
- Preserved joint space until late
- Soft tissue tophi may calcify
- DECT shows urate as green
Acute Treatment
- NSAIDs: Indomethacin 50mg TDS or Naproxen 500mg BD
- Colchicine: Low-dose regimen (1mg then 0.5mg)
- Steroids: If NSAIDs/colchicine contraindicated
- DO NOT start allopurinol during acute attack
ULT Targets
- Serum urate less than 6 mg/dL (360 micromol/L)
- Less than 5 mg/dL if tophi present
- Start 2-4 weeks after acute attack resolution
Surgical Indications (MUSIC)
- Mechanical symptoms from tophi
- Ulceration of overlying skin
- Secondary infection
- Impingement on nerves
- Cosmetic concerns
Evidence Base
AGREE Trial - Low-dose vs High-dose Colchicine
- 50% or greater pain reduction at 24h: 37.8% low-dose vs 32.7% high-dose vs 15.5% placebo
- Diarrhoea in 77% of high-dose vs 23% of low-dose patients
- Most effective when started early (within roughly 12-24 hours of flare onset)
CARES Trial - Febuxostat vs Allopurinol CV Safety
- Primary MACE endpoint non-inferior (HR 1.03, upper 98.5% CI 1.23)
- All-cause death HR 1.22 (95% CI 1.01-1.47); CV death HR 1.34 (95% CI 1.03-1.73)
- About 45% of participants discontinued follow-up, a major limitation
Imaging Modalities for Gout Classification (Meta-analysis)
- DECT pooled sensitivity 0.87 (95% CI 0.79-0.93), specificity 0.84 (95% CI 0.75-0.90)
- Ultrasound double contour sign sensitivity 0.83, specificity 0.76
- Most evidence derived from longstanding established disease (mean duration over 7 years) - sensitivity is lower in early gout
Nurse-led Treat-to-Target Care for Gout (RCT)
- Urate target achieved: 95% nurse-led vs 30% usual care (RR 3.18)
- All secondary outcomes (flares, tophi, quality of life) favoured nurse-led care at 2 years
- Education and shared decision-making drove high ULT uptake and adherence
FAST Trial - Long-term CV Safety of Febuxostat
- Primary CV endpoint HR 0.85 (95% CI 0.70-1.03), non-inferior to allopurinol
- No increase in all-cause death (febuxostat 7.2% vs allopurinol 8.6%)
- Open-label design and high discontinuation are limitations, but lower drop-out than CARES
Global Epidemiology of Gout
- Prevalence under 1% to 6.8%; higher in men, with age, and in some ethnic groups (e.g. Taiwanese aboriginal, Maori, Pacific peoples)
- Only one-third to one-half of patients receive ULT; fewer than half adhere
- Established links to CKD and CV disease, plus newer associations (AF, OSA, VTE)
2020 ACR Guideline for the Management of Gout
- Allopurinol preferred first-line over febuxostat (cost and CV safety)
- Start ULT low (allopurinol 100 mg/day or less; lower in CKD) and titrate to target
- Treat-to-target serum urate below 6 mg/dL with serial monitoring