The Rotator Cuff of the Hip
- Originates from the Gluteal Surface of the Ilium (between Anterior and Posterior Gluteal Lines).
- Inserts onto the Lateral and Superoposterior Facets of the Greater Trochanter.
- Innervated by the Superior Gluteal Nerve (L4, L5, S1).
- Damage causes a positive Trendelenburg Sign (Pelvis drops to the CONTRALATERAL side).
- Commonly implicated in Greater Trochanteric Pain Syndrome (GTPS).
- “The 'Safe Zone' for intragluteal injection is the Upper Outer Quadrant (to avoid Sciatic and Superior Gluteal Nerves).
- “Trendelenburg Gait is uncompensated (pelvis drops); Duchenne Gait is compensated (trunk leans to affected side).
- “Tears behave like Rotator Cuff tears: Degenerative, painful, and prone to fatty atrophy.
- “The Superior Gluteal Nerve runs between Gluteus Medius and Minimus.
Overview
The gluteus medius is the "deltoid of the hip": a fan-shaped muscle that covers gluteus minimus and is the primary hip abductor. It is critical to normal gait because it stabilises the pelvis in the coronal plane during the single-leg stance phase of walking, and weakness leads to a Trendelenburg gait. Its anterior fibres also internally rotate and flex the hip; its posterior fibres extend and externally rotate it.
The free-body diagram. The gluteus medius is the key to the single-leg-stance free-body diagram examiners love (Pauwels). In single-leg stance the pelvis pivots about the femoral head, the fulcrum. Body weight acts medially at a long moment arm and the abductors must pull laterally at a short one to keep the pelvis level. Because the body-weight lever arm is roughly 2.5 times the abductor lever arm, the abductors generate about 2.5 times body weight of force, and the resultant hip joint reaction force is about 3 to 4 times body weight in stance and gait, more on stairs or running.
What reduces the joint force and the abductor demand, all relevant in hip arthroplasty:
- A walking stick in the contralateral hand: it acts at a long lever arm and substantially cuts the joint force
- Leaning the trunk over the stance hip: the Duchenne lurch shifts the centre of gravity over the fulcrum
- Increasing femoral offset or lateralising the trochanter, which lengthens the abductor lever arm
- Medialising the acetabular cup, which shortens the body-weight lever arm
What increases it: loss of offset, coxa valga (which shortens the abductor lever arm), obesity, and carrying a load on the ipsilateral side.
This is why restoring offset and a level pelvis matters in arthroplasty, and why a Trendelenburg-positive hip mechanically overloads the joint.
Attachments, Innervation and Relations
Origin. The muscle arises from the outer surface of the ilium between the anterior and posterior gluteal lines, and also from the overlying gluteal aponeurosis, the fascia that covers it.
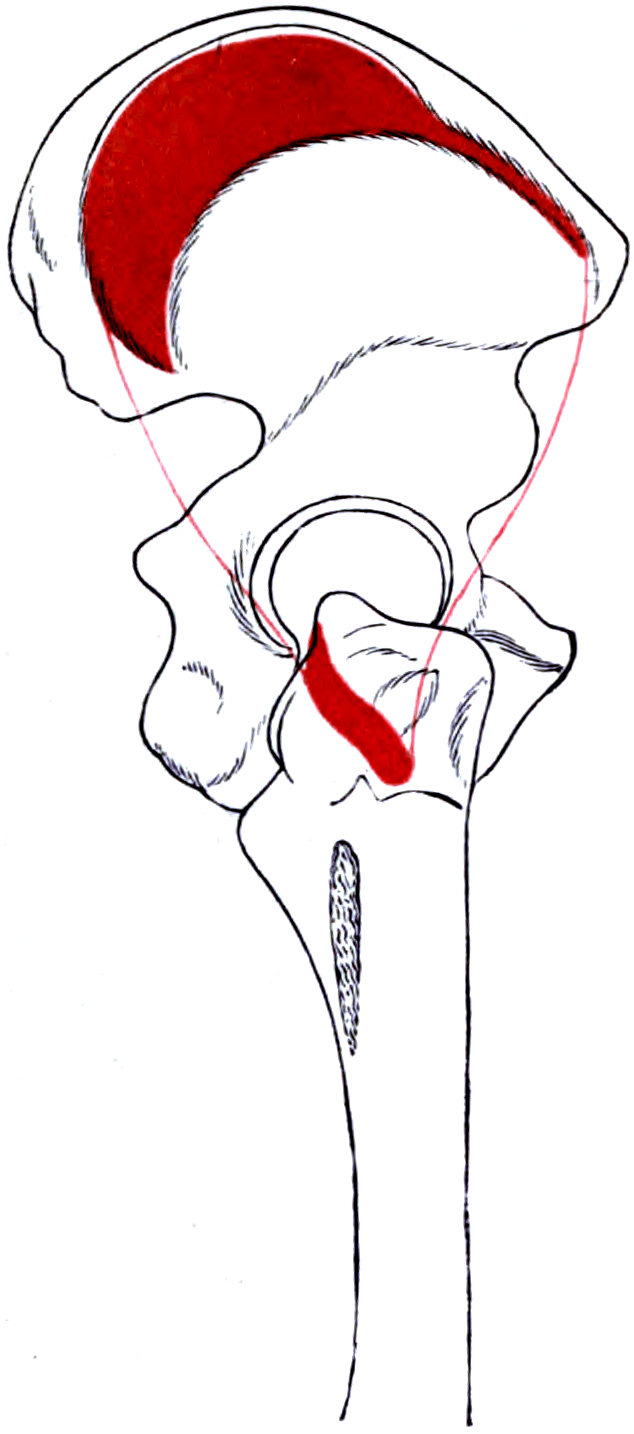
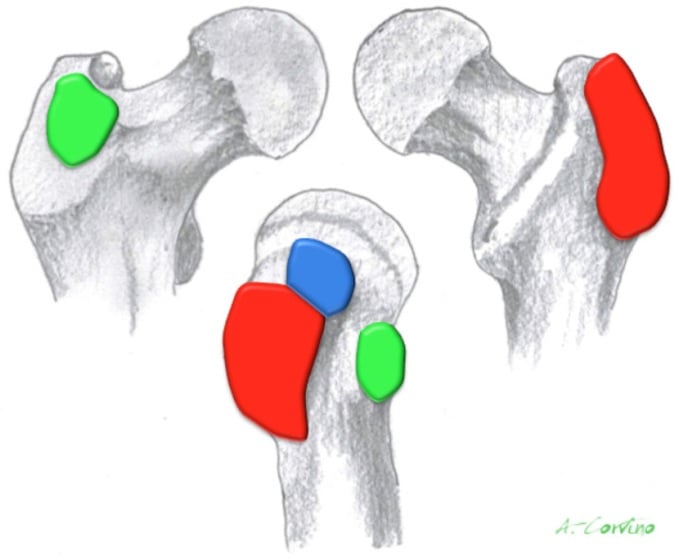
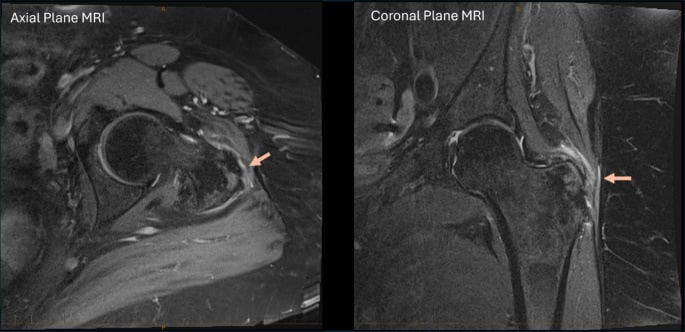
Insertion. The fibres converge into a strong tendon that inserts on the lateral facet and the superoposterior facet of the greater trochanter. On an axial MRI through the trochanter, gluteus minimus attaches to the anterior facet and the principal gluteus medius insertion occupies the lateral facet beneath the iliotibial band, with tensor fasciae latae anteriorly and gluteus maximus posteriorly. That orientation is the map for interpreting axial MRI and planning anchor placement, and the intact facets are the reference against which tendon discontinuity, retraction and abnormal bursal fluid are judged.
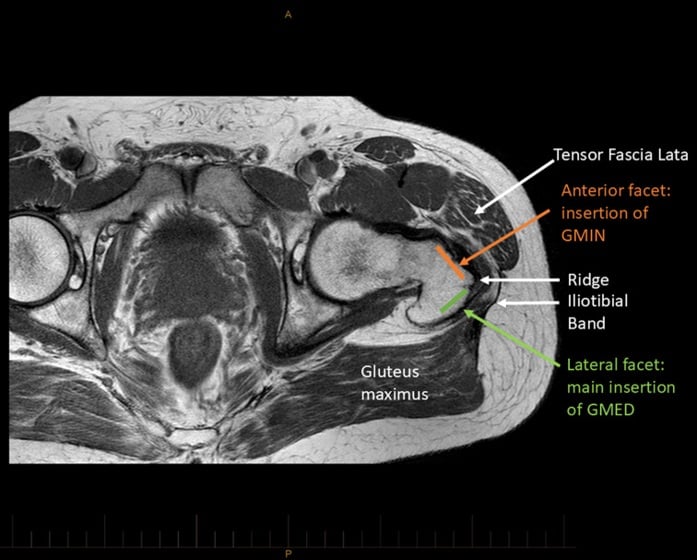
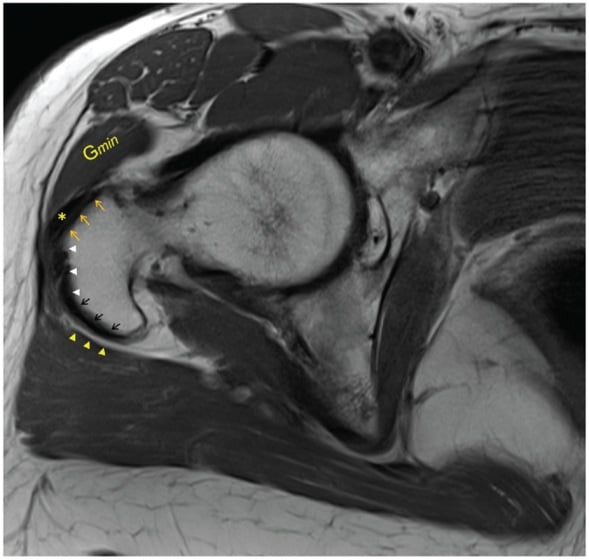
LAMPInsertions on Greater Trochanter
Hook:The facets of the Greater Trochanter.
The bursae. Three peritrochanteric bursae occupy distinct planes. The large trochanteric (subgluteus maximus) bursa lies superficial to the abductor tendons, deep to gluteus maximus; the subgluteus medius bursa lies deep to the medius tendon near its insertion, and the subgluteus minimus bursa deep to the minimus tendon. Naming the involved plane is more precise than calling every lateral-hip fluid collection trochanteric bursitis.
Innervation. The superior gluteal nerve (L4, L5, S1), from the sacral plexus, leaves the pelvis through the greater sciatic foramen superior to piriformis and runs laterally between gluteus medius and gluteus minimus, entering the deep surface of the muscle. It supplies medius and minimus and terminates in tensor fasciae latae. The other named nerves of the region are the inferior gluteal nerve, to gluteus maximus, and the posterior cutaneous nerve of the thigh.
Relations. Gluteus maximus covers the muscle posteriorly and tensor fasciae latae anteriorly; deep to it lie gluteus minimus and the superior gluteal vessels and nerve. The posterior border is the landmark for the posterior approach to the hip, and the anterior border is separated from tensor fasciae latae by the Watson-Jones interval. Below the muscle lie piriformis and the short external rotators (the superior and inferior gemelli, obturator internus, obturator externus and quadratus femoris), with the sciatic nerve emerging beneath piriformis.
- Origin
- Post Ilium/Sacrum
- Insertion
- ITB / Gluteal Tuberosity
- Nerve
- Inferior Gluteal (L5-S2)
- Origin
- Ilium (b/w Ant/Post Lines)
- Insertion
- GT (Lateral Facet)
- Nerve
- Superior Gluteal (L4-S1)
- Origin
- Ilium (b/w Ant/Inf Lines)
- Insertion
- GT (Anterior Facet)
- Nerve
- Superior Gluteal (L4-S1)
- Origin
- ASIS / Iliac Crest
- Insertion
- ITB
- Nerve
- Superior Gluteal (L4-S1)
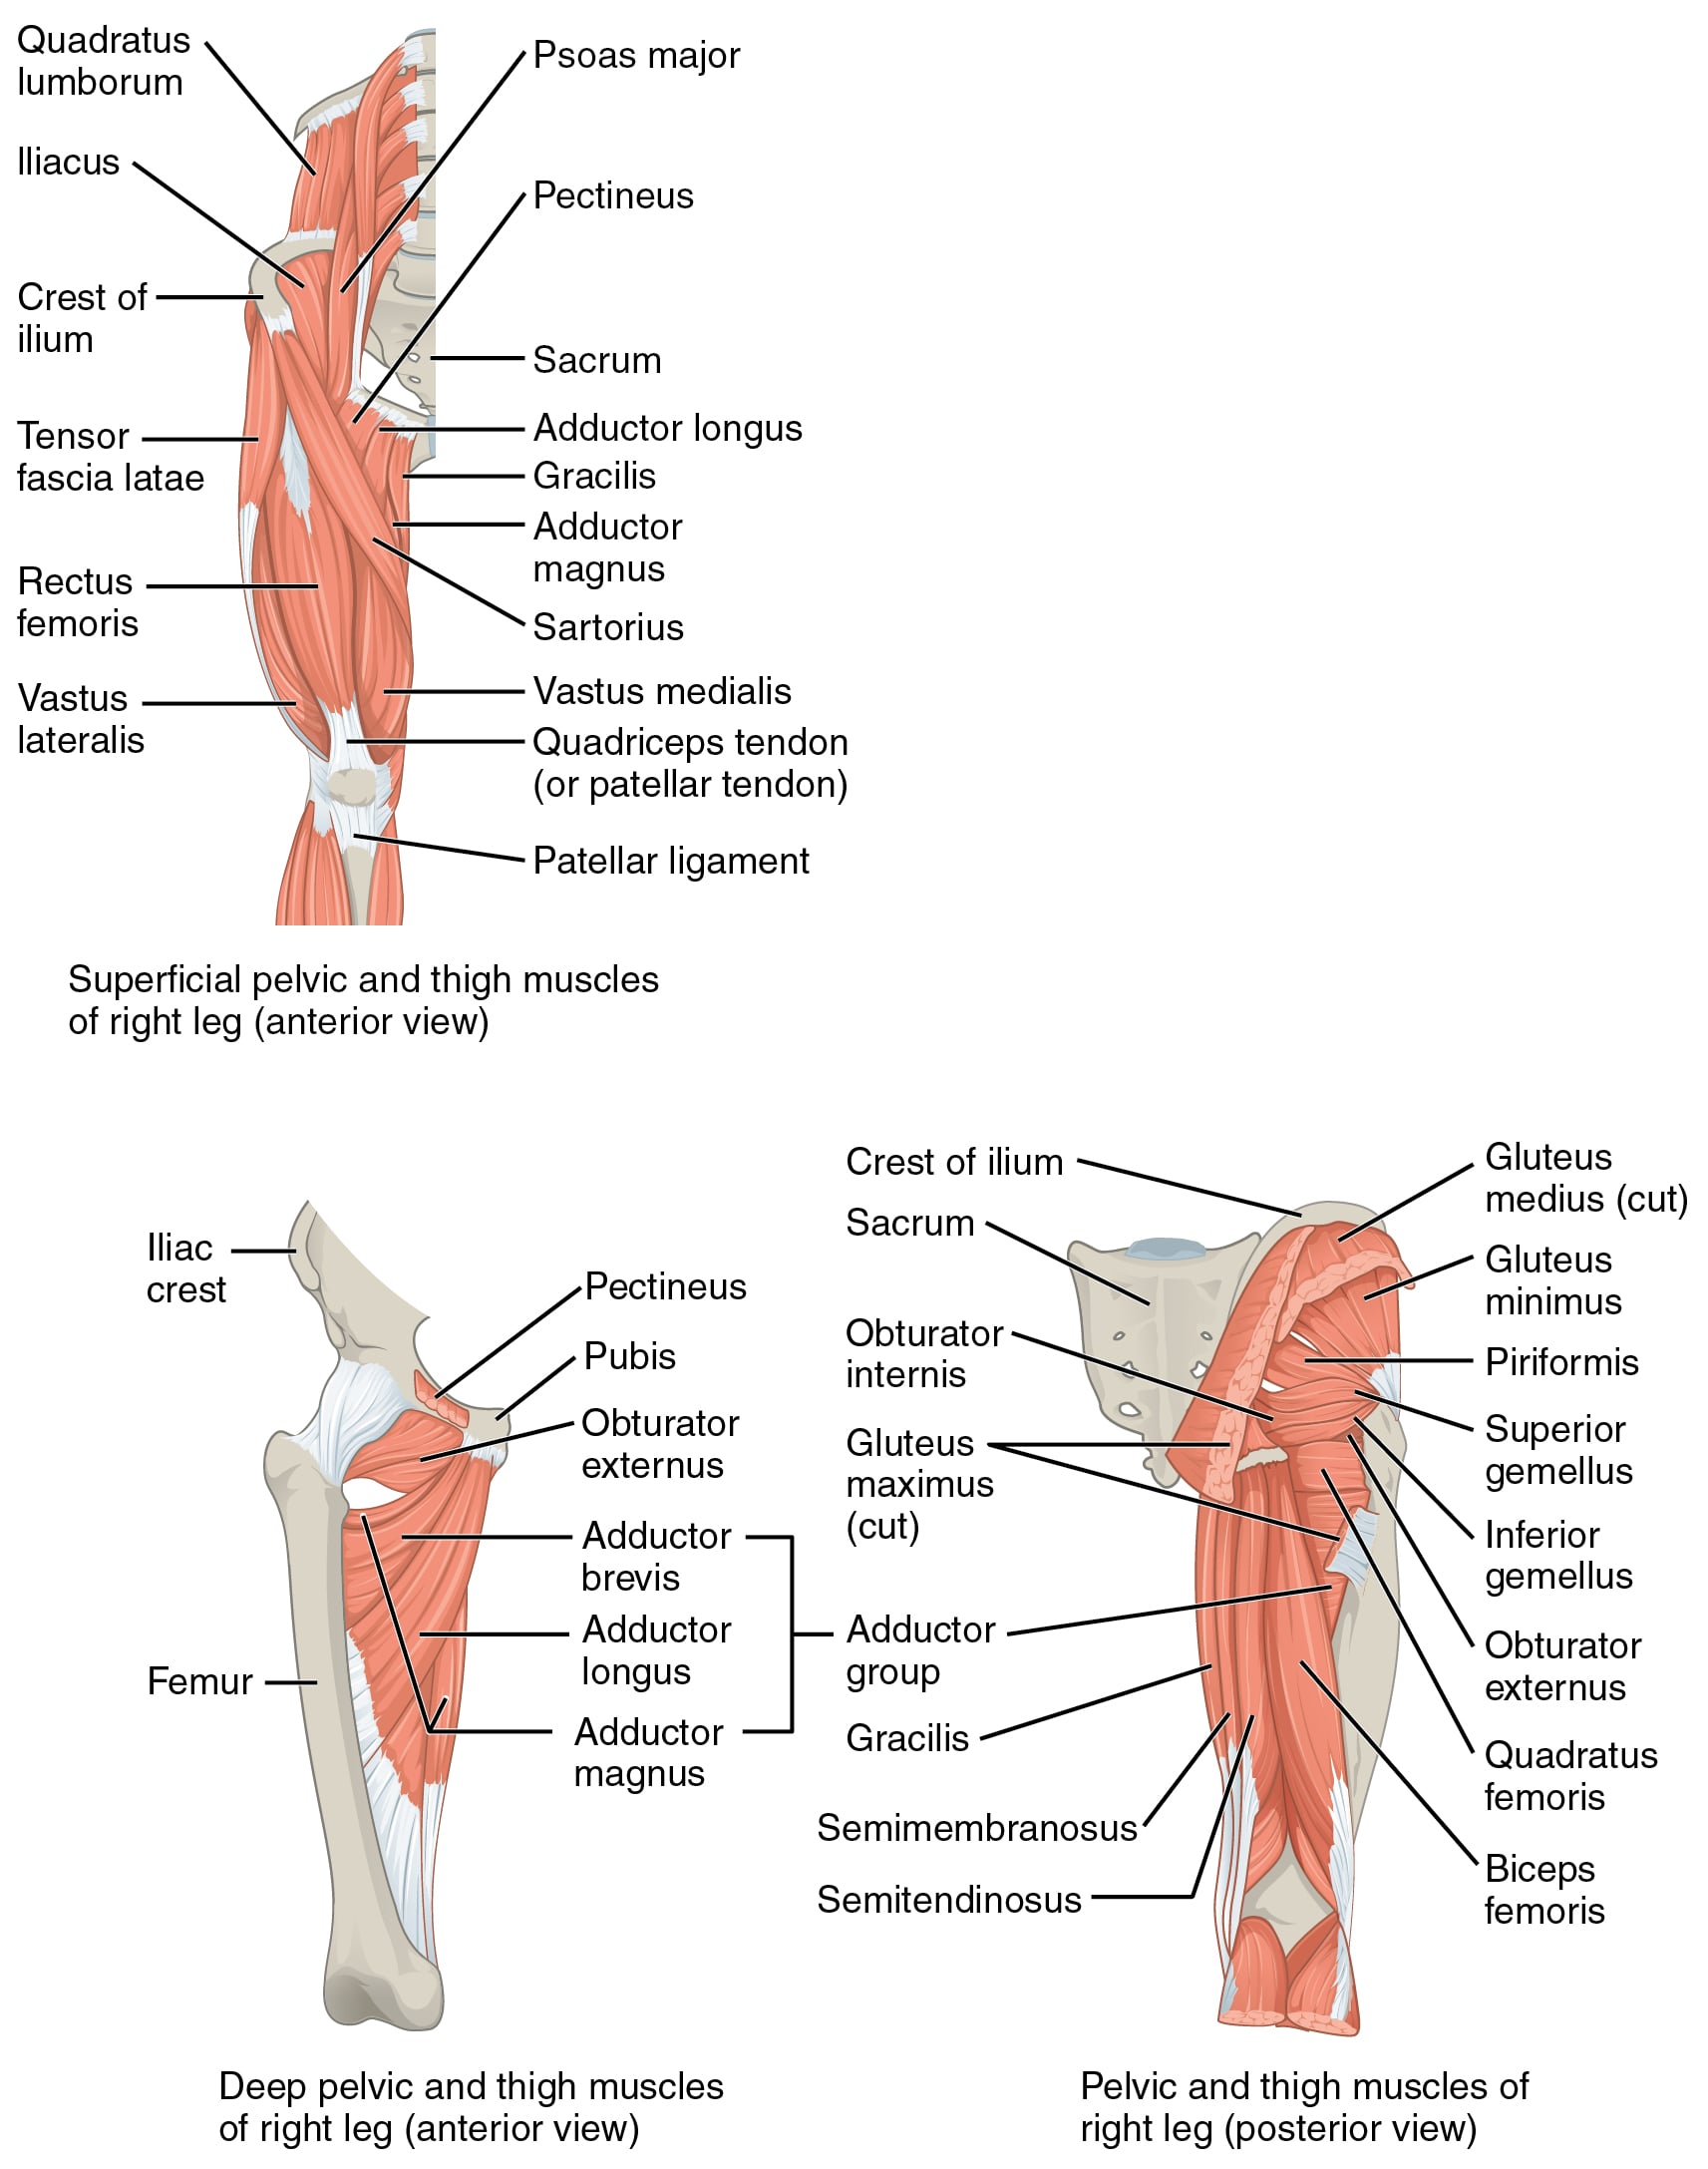
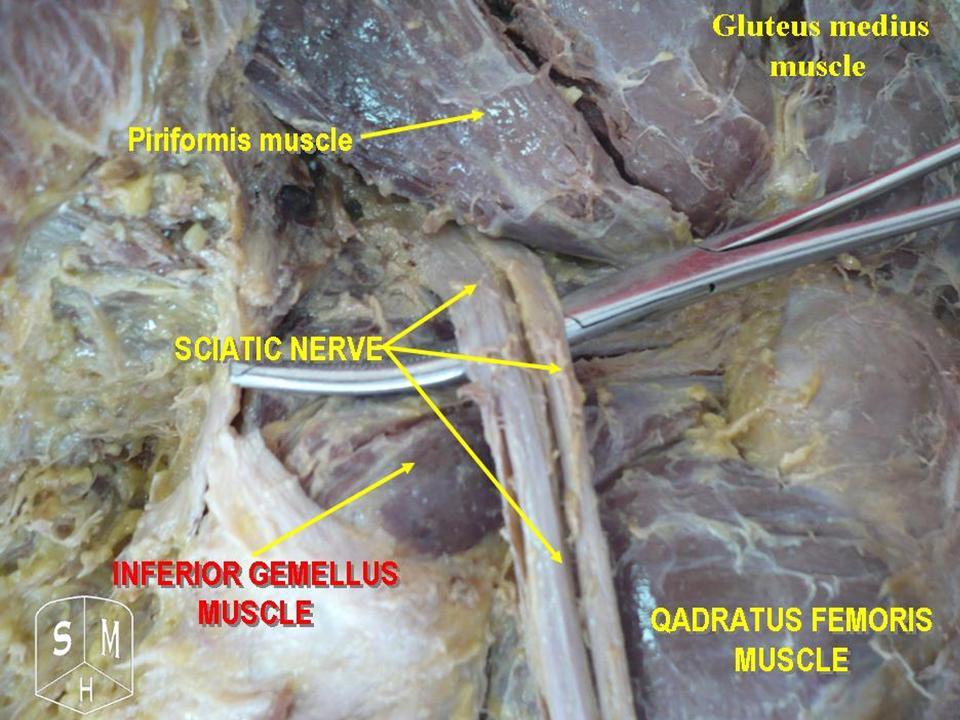
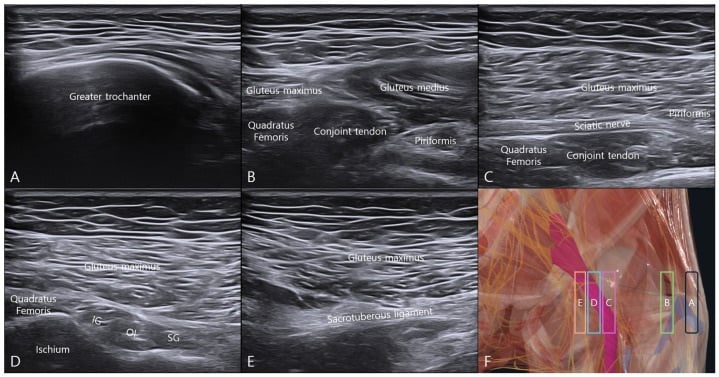
Surface Anatomy
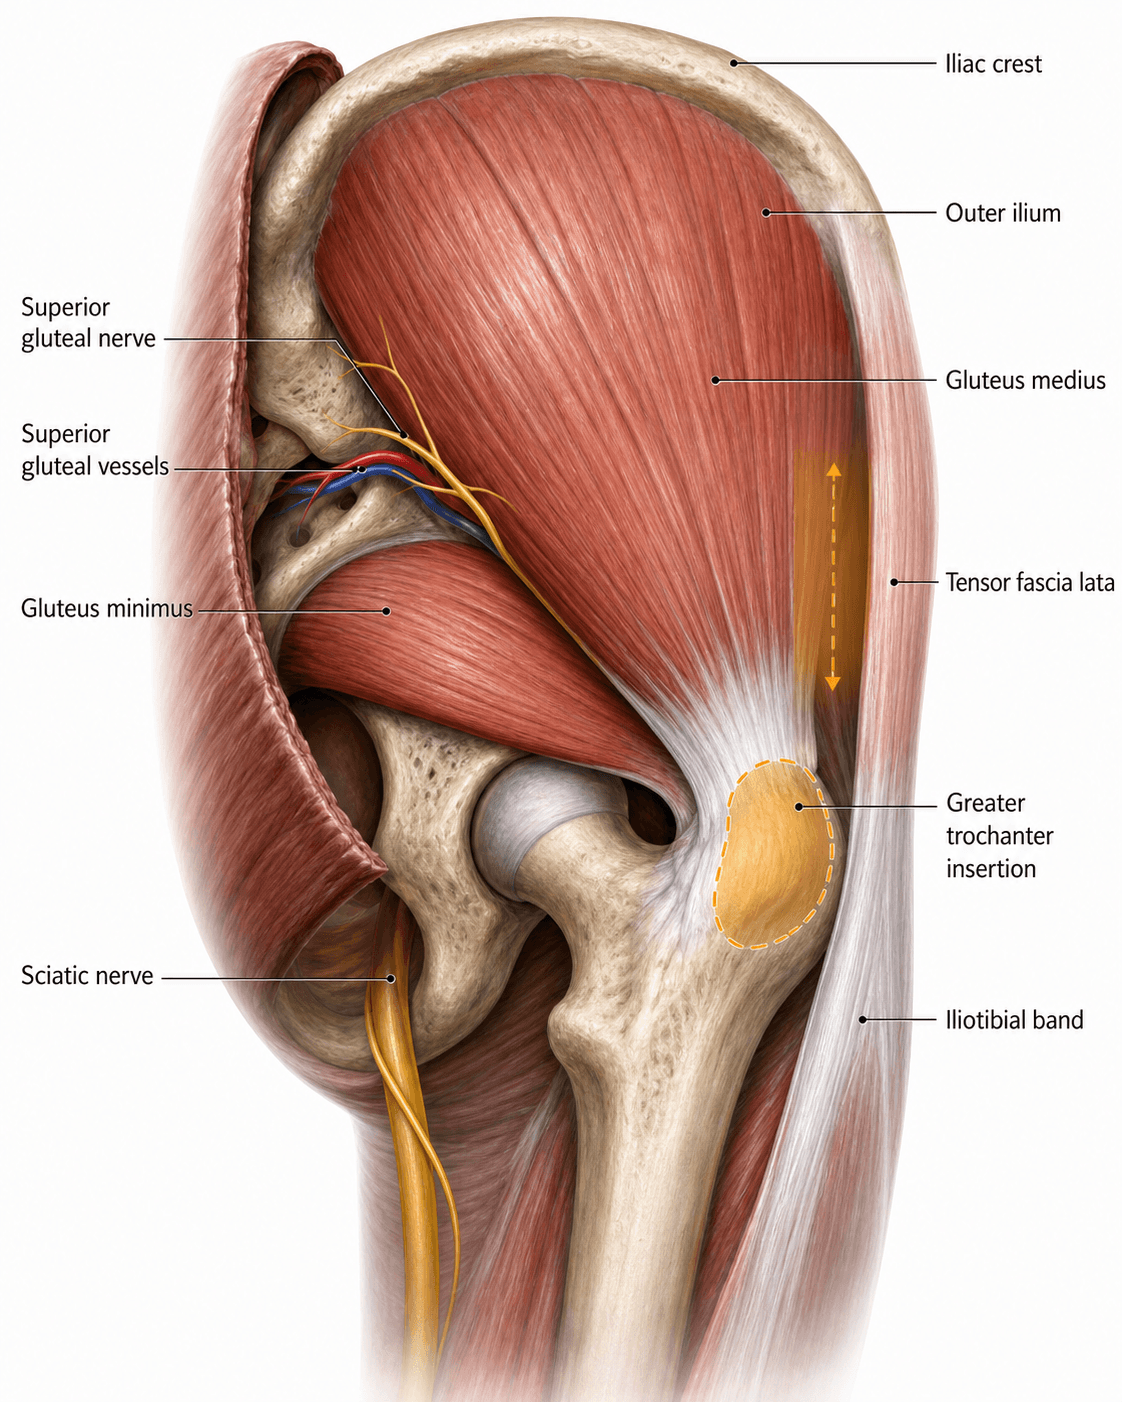
Landmarks. Three palpable landmarks:
- Iliac crest: the superior border of the muscle
- Greater trochanter: the insertion, palpable on the lateral aspect of the hip
- ASIS: the anterior superior iliac spine
Injection safety. Draw a line from the PSIS to the greater trochanter. The injection should be superior and lateral to that line, in the upper outer quadrant, which avoids the sciatic nerve (medial and inferior) and the superior gluteal neurovascular bundle (deep but central). A deep injection, or a retractor wrongly placed in the posterior approach, can cause a sciatic palsy; identifying these landmarks is crucial to safe practice and avoiding iatrogenic nerve injury.
Pathology: GTPS
A spectrum, not a bursitis. Greater trochanteric pain syndrome was formerly called trochanteric bursitis. It is now understood as a spectrum from tendinosis through partial tear to complete tear, the "rotator cuff of the hip", with a pathophysiology similar to shoulder cuff disease. On imaging the tendon, not the bursa, is the key structure to inspect, because GTPS commonly reflects tendinopathy rather than isolated bursitis. Understanding the mechanical overload is key to successful conservative management.
Risk factors. Female sex (a wider pelvis and an increased varus moment), leg-length discrepancy and, above all, ipsilateral knee osteoarthritis, low back pain and iliotibial band tenderness: the neighbouring pathology that alters lower-limb and lumbopelvic mechanics. Obesity is the classic answer here and it is not supported: in Segal's population study BMI dropped out once knee osteoarthritis and back pain were adjusted for (see Global Epidemiology below).
Tears. Degenerative tears are the most common and occur at the insertion, the enthesis; traumatic tears are rare and associated with fractures. Fatty atrophy, graded by Goutallier, predicts poor outcomes after repair, as it does in the shoulder. On MRI, assess both tendons, tear thickness, retraction and muscle quality rather than reporting bursal fluid alone.
Classification Systems
MRI grading of abductor tears. The grade guides the decision between endoscopic repair, open repair and muscle transfer:
- Grade 1: peritrochanteric oedema (bursitis or tendinosis)
- Grade 2: partial-thickness tear
- Grade 3: full-thickness tear, undisplaced
- Grade 4: full-thickness tear with retraction of less than 2cm
- Grade 5: massive retraction of greater than 2cm with fatty atrophy
Tear types. A four-type scheme is also used:
- Type I: tendinosis
- Type II: partial tear
- Type III: full-thickness tear
- Type IV: retracted tear with fatty atrophy
Clinical Assessment
Trendelenburg test. The patient stands on one leg, the affected one. Normally the contralateral pelvis rises, because the abductors of the stance leg pull the ipsilateral pelvis down to level. In a positive test the contralateral pelvis drops: the weakness is in the stance-leg gluteus medius, not the side that falls, which is what "sound side sinks" means. The test must be held for 30 seconds to detect subtle weakness, which shows as fatigue.
Gait. Trendelenburg gait is the uncompensated form: standing on the affected leg, the pelvis drops on the contralateral (unsupported) side with each step. Duchenne gait is compensated: the trunk leans towards the affected side during stance, shifting the centre of gravity and reducing abductor demand. Bilateral weakness produces a waddling gait, often seen in hip dysplasia or myopathy.
Resisted abduction. In lateral decubitus the patient abducts the leg against gravity and resistance. Pain indicates tendinopathy; weakness indicates a tear or a nerve palsy.
The Trendelenburg test is the classic sign but is insensitive for a degenerate tear; examiners reward the more specific tests for gluteal tendinopathy and abductor tears. The hip lag sign and the 30-second single-leg-stance test are highlighted in the Kenanidis review as useful clinical indicators of abductor insufficiency.
- 30-second single-leg-stance test: the patient stands on the affected leg for up to 30 seconds; reproduction of lateral (trochanteric) pain is a sensitive sign of gluteal tendinopathy, distinct from the pelvic drop of a Trendelenburg test
- Hip lag sign: in lateral decubitus the examiner passively holds the hip in extension, abduction and internal rotation with the knee flexed, then asks the patient to hold the leg there; the leg dropping (inability to actively maintain abduction) indicates an abductor tendon tear or insufficiency
- Resisted external-derotation test (Lequesne): with the hip flexed to 90 degrees and externally rotated, the patient actively returns the leg to neutral against resistance; trochanteric pain indicates gluteal tendinopathy
- Palpation of the greater trochanter for point tenderness and a lumbar and neurological screen to exclude L5 radiculopathy complete the examination
Investigations
Radiographs. An AP pelvis is checked for calcification at the insertion (calcific tendonitis) and for avulsion fractures. The fleck sign, a bony fragment superior to the greater trochanter, suggests avulsion.
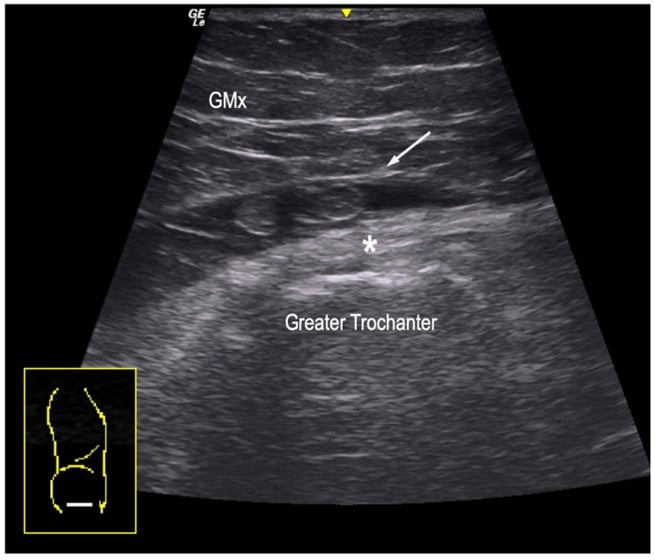
Ultrasound. Excellent for dynamic assessment and for guided injection, and it can visualise fluid in the bursa and tendon tears.
MRI. The gold standard, and its sequences answer two different operative questions: what is torn, and whether the muscle remains worth repairing. T2 fluid signal at the insertion indicates a tear or bursitis. MRI also shows muscle quality and muscle belly atrophy, which raises the question of nerve injury; fatty infiltration is best assessed on the T1 axial sequence. T1 is essential because tendon continuity alone does not establish reparability: severe fatty change predicts limited strength recovery and may shift reconstruction toward transfer or salvage.
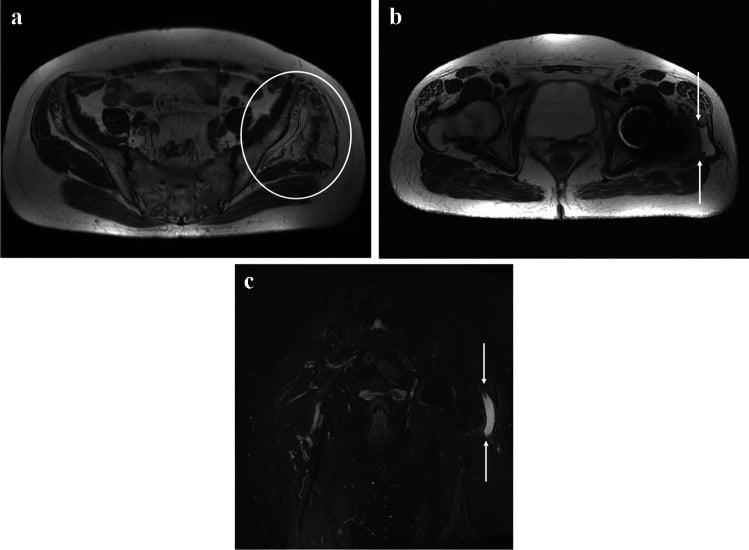
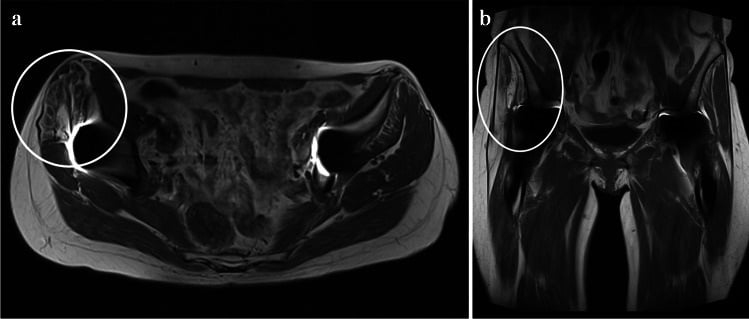
Nerve studies. EMG differentiates an L5 radiculopathy from a superior gluteal nerve palsy. An L5 root lesion also affects tibialis anterior and the peroneals, whereas a superior gluteal nerve palsy is isolated to gluteus medius, gluteus minimus and tensor fasciae latae. Denervation potentials (fibrillations and sharp waves) confirm active axonal loss.
Differential Diagnosis of Lateral Hip Pain
Lateral hip and abductor-region pain has a wide differential. The examiner expects a structured separation of intra-articular, peritrochanteric, neurogenic and referred causes.
- Discriminating Feature
- Point tenderness over greater trochanter; night pain lying on side
- Key Test / Investigation
- Resisted abduction, single-leg stance; MRI/US
- Discriminating Feature
- Groin pain, stiffness, reduced internal rotation
- Key Test / Investigation
- FADIR, AP pelvis radiograph
- Discriminating Feature
- Groin pain, C-sign, younger patient
- Key Test / Investigation
- FADIR, MR arthrogram
- Discriminating Feature
- Radiating pain, neurology in foot (tibialis anterior, peronei)
- Key Test / Investigation
- Neurological exam, lumbar MRI, EMG
- Discriminating Feature
- Pain more distal/lateral with activity
- Key Test / Investigation
- Ober test, clinical
- Discriminating Feature
- Anterolateral thigh burning/numbness (LFCN)
- Key Test / Investigation
- Sensory mapping, nerve block
- Discriminating Feature
- Painless abductor weakness, positive Trendelenburg
- Key Test / Investigation
- EMG isolated to medius/minimus/TFL
Surgical Technique
Anterolateral (Hardinge). Splits the anterior third of gluteus medius and vastus lateralis and gives an excellent view of the acetabulum. The superior gluteal nerve is at risk if the split extends more than 5cm proximal to the tip of the greater trochanter: running it too far risks denervating the anterior tensor fasciae latae and the anterior gluteus medius fibres, and the result is a persistent Trendelenburg limp. At closure, repair the tendon meticulously and restore the abductor sleeve securely to prevent a limp.
Posterior (Moore). Splits gluteus maximus, which is safe, and retracts gluteus medius anteriorly; a retractor that is too vigorous causes a traction injury to the superior gluteal nerve. The posterior approach relies on the integrity of the anterior abductor sleeve for stability.
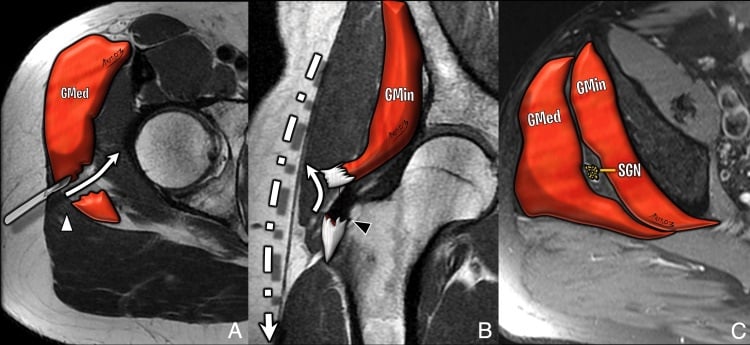
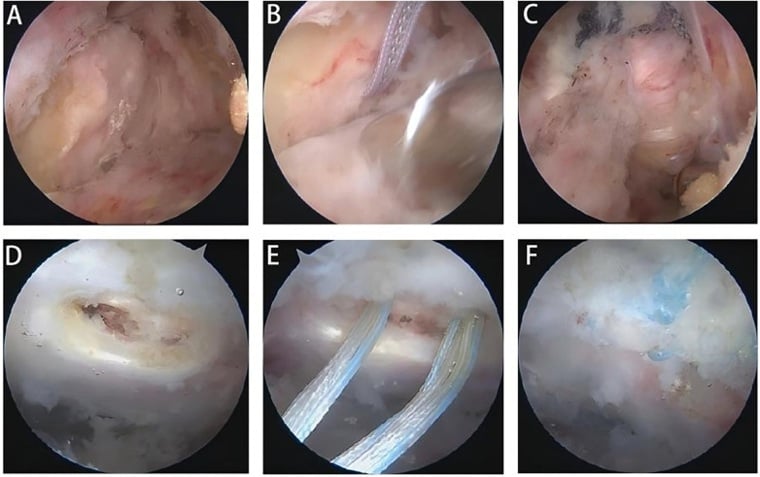
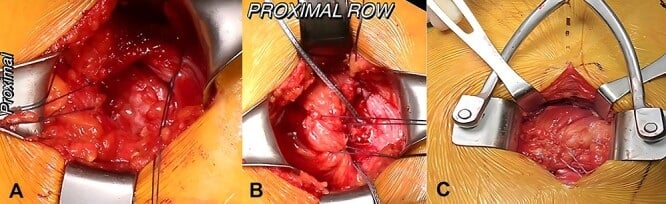
Repair. Open repair uses a lateral incision with anchor fixation into the lateral facet, a double-row equivalent: traction sutures first demonstrate excursion and permit mobilisation, the proximal anchors establish the medial row, and distal anchors then compress the tendon across the greater-trochanter footprint. Endoscopic repair works through the peritrochanteric space, with an anterior portal lateral to the ASIS and a posterior portal at the tip of the greater trochanter. The technique is bursectomy first, identify the tear, decorticate the footprint, then suture anchors; knotless anchors are preferred to reduce prominence over the greater trochanter. The key operative distinction is whether the tendon is detached or retains a superficial layer that can be preserved, in which case a partial tear is treated transtendinously. The repair must be tension-free enough to protect during early rehabilitation.
Complications
A persistent Trendelenburg gait after hip surgery should trigger assessment of tendon continuity, muscle denervation and fatty atrophy rather than being dismissed as routine weakness.
- Persistent limp: failure of the repair or nerve injury
- Nerve injury: superior gluteal (abductor lurch) or sciatic (foot drop)
- Recurrence: re-tear rates are significant, 10-20%
- Heterotopic ossification: especially with lateral approaches

Rehabilitation Protocol
- Phase 1 (0-6 weeks): protected weight bearing on crutches; no active abduction; avoid adduction (crossing the legs), which stretches the repair
- Phase 2 (6-12 weeks): wean the crutches; aqua therapy; isometric abduction
- Phase 3 (3 months onwards): strengthening; return to sport and full activity
Prognosis
Conservative management succeeds in 70-80% of GTPS. Repair gives good pain relief in 90%, but strength recovery is variable and takes longer (1 year). Goutallier 3 or 4 fatty atrophy significantly lowers the success rate.
Clinical Relevance
Treatment by pathology. Surgical intervention is reserved for those who fail 6 months of dedicated rehabilitation.
- Treatment
- Physio, NSAIDs, Injection
- Rationale
- Load management usually successful
- Treatment
- PRP? Shockwave? Repair?
- Rationale
- Conservative first. Repair if failed.
- Treatment
- Endoscopic/Open Repair
- Rationale
- Relieves pain and restores gait
- Treatment
- Gluteus Maximus Transfer
- Rationale
- Salvage for massive retraction
Injections. Corticosteroids provide short-term relief but may weaken the tendon. PRP is controversial but gaining popularity.
Guidelines, Registries & Global Practice
Global Epidemiology
- GTPS affects an estimated 10-25% of patients referred with hip/lateral thigh pain, with a population prevalence around 15% in women aged 50-79 versus roughly 6% in men (Segal NA et al., Arch Phys Med Rehabil 2007).
- Demographics: female predominance (odds ratio 3.37 in Segal's cohort; wider pelvis, larger abductor moment arm), peri- and post-menopausal age, leg-length discrepancy, and - the strongest associations in that multivariate model - ipsilateral knee osteoarthritis (OR 3.47), low back pain (OR 2.79), contralateral knee osteoarthritis (OR 1.74) and iliotibial band tenderness (OR 1.72). The pattern points at altered lower-limb and lumbopelvic mechanics rather than at the trochanter itself, which is why examination of the spine, both knees and gait matters more than another injection into a tender point.
- Two negatives from the same study that are worth carrying, because both are commonly taught as positives. Obesity was NOT independently associated with GTPS once age, sex, ITB tenderness, knee osteoarthritis and back pain were adjusted for (OR 1.10, 95% CI 0.80 to 1.52 comparing BMI ≥30 with under 25) - the apparent link is largely explained by the knee and back pathology that travel with it. And hip internal rotation range did not differ between those with and without GTPS, which is diagnostically useful in the other direction: preserved internal rotation does not argue against GTPS, whereas restricted and painful internal rotation should move hip osteoarthritis up the differential, not down it.
- Abductor tears are increasingly recognised as a degenerative enthesopathy ("rotator cuff of the hip") found incidentally in up to 20% of older women on MRI and in a notable proportion of THA candidates.
Side-by-Side Guideline & Society Positions
- Position on Gluteal Tendinopathy / Abductor Tears
- Staged care: load modification, exercise, then image-guided injection; surgery for refractory tears
- Emphasis
- Evidence-graded conservative-first
- Position on Gluteal Tendinopathy / Abductor Tears
- Physiotherapy-led education plus exercise as first line; caution on repeated corticosteroid
- Emphasis
- Tendon-load rehabilitation
- Position on Gluteal Tendinopathy / Abductor Tears
- Respect superior gluteal nerve safe zone in transgluteal approaches; meticulous abductor repair
- Emphasis
- Surgical safety
- Position on Gluteal Tendinopathy / Abductor Tears
- MRI staging of fatty infiltration before repair; muscle transfer for irreparable tears
- Emphasis
- Prognostic stratification
- The LEAP randomised trial (Mellor R et al., Br J Sports Med 2018) underpins the global shift towards education plus exercise as first-line therapy, outperforming a single corticosteroid injection at one year.
Registry & Approach Notes
- Arthroplasty registries (NJR UK, AOANJRR Australia, AJRR US) track surgical approach but not abductor integrity directly; the posterior approach dominates worldwide, with the direct anterior and lateral (Hardinge) approaches as the main alternatives.
- Comparative MRI data show the transgluteal (Hardinge) approach produces more measurable abductor damage and a higher rate of post-operative limp than the intermuscular direct anterior approach (Bremer AK et al., JBJS Br 2011) - a key trade-off against the Hardinge's low dislocation rate.
High- vs Limited-Resource Practice Variation
- Well-resourced settings: MRI staging, ultrasound-guided injections, endoscopic and arthroscopic abductor repair, and PRP/shockwave for tendinopathy.
- Limited-resource settings: Diagnosis rests on clinical examination (Trendelenburg, resisted abduction, single-leg stance) and plain radiographs; management is predominantly supervised exercise and selective open repair, with MRI and arthroscopy reserved for complex or surgical cases.
Controversies & Areas of Uncertainty
Corticosteroid injections. They provide rapid short-term relief but are inferior to exercise at one year and may be catabolic to tendon. The role and number of injections remains debated, with a clear trend away from repeated steroid (LEAP trial, Mellor 2018).
PRP and orthobiologics. Platelet-rich plasma and other biologics are increasingly used for gluteal tendinopathy, but high-quality comparative evidence is limited and results are inconsistent.
Endoscopic versus open repair. Both achieve good pain relief; endoscopic techniques offer less soft-tissue dissection but have a steep learning curve. No large randomised comparison establishes superiority, and selection (tear size, retraction, atrophy) drives outcomes more than technique.
The "safe zone" myth, and the direction of the risk. The classic 5cm rule is a fixed absolute distance applied to patients of every size, and Ekşioğlu's cadaveric series found the nerve-to-trochanter distance correlates with body height, so the margin is smallest in the shortest patients, who are the ones a 5cm split is most likely to reach. That is the opposite of the intuition that a bigger patient means a deeper, riskier dissection. The same study found the nerve outside the "safe area" in 22% of posterior regions (it was within it in all anterior regions), and its own conclusion is blunt: the safe area is not always safe. Note also that the literature conflicts, since other cadaveric work has found the distance independent of height, so the defensible position is not "worry in short patients only" but do not treat any fixed number as protection: keep the split as distal as the exposure allows, and if you need more proximal access, extend it as an anterior flap off the trochanter rather than by splitting further into the muscle belly.
Surgical approach for THA. The abductor-sparing advantage of the direct anterior approach (less measurable abductor damage on MRI) is weighed against its learning curve and complication profile; no approach is universally superior.
MCQ Practice Points
Q: Injury to the Superior Gluteal Nerve results in which gait deviation? A: Trendelenburg Gait (Uncompensated) or Duchenne Gait (Compensated). It does NOT cause a foot drop (that is Sciatic/Peroneal).
Q: A small bony fleck seen superior to the Greater Trochanter on AP Pelvis X-ray indicates what? A: Avulsion of the Gluteus Medius (or Minimus) insertion. It is the hip equivalent of a Segond fracture (ACL) or bony Bankart (Shoulder).
Q: Onto which facet does the Gluteus Medius primarily insert? A: Lateral Facet. The Minimus inserts on the Anterior Facet.
Q: The safe zone for intragluteal injection to avoid the Sciatic Nerve is? A: Upper Outer Quadrant.
Q: Besides abduction, what is the action of the anterior fibers of Gluteus Medius? A: Internal Rotation and Flexion. Posterior fibers do Extension/ER.
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 70F presents 6 months after a Hardinge approach THR (Total Hip Replacement). She has a persistent limp. Why?”
“50F office worker, localized lateral hip pain, worse at night lying on that side. No trauma. X-ray normal. Diagnosis?”
“You are performing a lateral approach and need to extend your split proximally. How far can you go?”
Anatomy
- Origin: Ilium (Ant-Post Lines)
- Insert: Lateral Facet GT
- Nerve: Sup. Gluteal (L4-S1)
- Action: Abduct + Stabilize
Clinical
- Trendelenburg: Contralateral Drop
- Duchenne: Ipsilateral Lean
- GTPS: Lat Hip Pain
- Resisted Abd: Pain/Weakness
Surgery
- Hardinge: Split less than 5cm
- Repair: Lat Facet Anchor
- Safe Zone: Upper Outer Q
- Nerve @ Risk: Sup Gluteal
Evidence Base
Endoscopic Gluteus Medius Repair Outcomes
- 34 patients (32 women, mean age 57), 10 full-thickness and 24 partial-thickness tears, minimum 2-year follow-up
- Mean VAS pain fell from 6.6 to 2.4 (p less than 0.001) with significant gains across all four hip outcome scores
- 15 of 26 patients (58%) with a pre-operative gait deviation regained a completely normal gait; mean satisfaction 8.5/10
- No difference between suture-bridge and transtendinous techniques; 4 patients progressed to total hip replacement
LEAP Trial: Exercise vs Corticosteroid for Gluteal Tendinopathy
- Three-arm RCT of 204 patients with MRI-confirmed gluteal tendinopathy: education plus exercise (EDX) vs single corticosteroid injection (CSI) vs wait-and-see (WS)
- At 8 weeks, EDX gave the highest success rate on global change (77%) versus CSI (58%) and WS (29%)
- EDX outperformed CSI for both global improvement and pain at 8 weeks
- At 52 weeks EDX remained superior to CSI for global improvement; both beat wait-and-see
Reliability of the Superior Gluteal Nerve 'Safe Area'
- Cadaveric study of 23 hips measuring the distance from the SGN entry point into gluteus medius to the greater trochanter
- Distance correlated significantly with cadaver body height in both anterior and posterior regions
- The nerve lay within the classic 'safe area' in all anterior regions but only 78% of posterior regions
- Since the distance scales with height, a FIXED 5cm rule leaves the least margin in the SHORTEST patients - the nerve sits closest to the trochanter in the smallest hips, not the largest
- The paper's own conclusion: the safe area is not always safe
Greater Trochanteric Pain Syndrome: Epidemiology
- Population-based cross-sectional study of 3026 community-dwelling adults aged 50-79
- Prevalence of GTPS was markedly higher in women (15.0% unilateral, 8.5% bilateral) than men (6.6% and 1.9%); odds ratio for women 3.37
- GTPS was independently associated with iliotibial band tenderness, knee osteoarthritis and low back pain
- Bilateral GTPS correlated with slower walk and chair-stand times
Abductor Preservation: Direct Anterior vs Transgluteal Approach
- Comparative MRI study of 50 hips (25 per group) one year after total hip replacement
- Tendon detachment, partial tears and tendinitis of gluteus medius and minimus were significantly less frequent with the direct anterior approach
- Peritrochanteric bursal fluid and fatty atrophy of the abductors were also reduced with the anterior approach
- No difference in tensor fasciae latae findings between approaches
Lesions of the Hip Abductors: Diagnosis and Management
- Comprehensive review confirming abductor tendinopathy is the commonest cause of lateral thigh pain, more prevalent in women and increasing with age
- MRI is the gold standard and the degree of muscle fatty infiltration has predictive value for repair outcome
- The hip lag sign and 30-second single-leg stance test are useful clinical indicators of abductor insufficiency
- Muscle transfers (gluteus maximus / vastus lateralis) are salvage options for chronic irreparable tears with significant atrophy