Insertional Achilles Tendinopathy | Pump Bump | Retrocalcaneal Bursitis
- Haglund = posterosuperior calcaneal prominence, first described by Patrick Haglund in 1928
- Pump bump = colloquial term for Haglund driven by rigid heel-counter friction in dress shoes
- Three coexisting pathologies: BONY prominence + BURSITIS + TENDINOPATHY
- Eccentric loading (Alfredson) is less effective for insertional than midportion tendinopathy
- Surgical ostectomy typically 3-5 mm; reattach Achilles with suture anchors if tendon detached
- “Lateral X-ray: parallel pitch lines define the Haglund prominence; Fowler-Philip angle over 75 degrees suggests Haglund
- “Two-finger squeeze at the insertion: mediolateral pinch tenderness implicates retrocalcaneal bursa
- “Always assess cavus foot, gastrocnemius equinus, and FHL tendinopathy in the same consultation
- “Central tendon-splitting approach preferred for combined tendon and bony pathology
- “Baxter's nerve (first branch of lateral plantar) entrapment can mimic Haglund — examine the medial heel
Overview and Epidemiology
Haglund syndrome and insertional Achilles tendinopathy are taught together because they coexist in 60-70 percent of posterior heel pain presentations. Insertional tendinopathy accounts for 20-25 percent of all Achilles tendon pain. Distinguishing pure Haglund, which is bone and bursa, from insertional tendinopathy, which is tendon-driven, changes both the conservative algorithm and the surgical plan.
Who. The peak is at 30-50 years, with a second, smaller peak in active adolescents of the Sever type. Women are more often affected, the pump bump coming from rigid heel counters. Runners tend to present with insertional tendinopathy, and walkers in tight dress shoes with Haglund.
Which feet. A cavus foot, a varus heel and a Haglund-shaped calcaneus predispose, and gastrocnemius-soleus equinus increases the impingement.
Burden. 25 percent are chronic after first-line conservative care, and conservative care fails in roughly 25-50 percent of insertional cases; these are the patients who present for a surgical opinion, and 5-10 percent eventually undergo surgery. VISA-A scores are commonly 50-60 out of 100 at presentation.
Anatomy and Pathophysiology
The anatomy. The Haglund deformity is a posterosuperior prominence of the calcaneus at the Achilles insertion. Two bursae lie beside it: the retrocalcaneal bursa between the anterior distal Achilles and the calcaneus, and the subcutaneous bursa between the tendon and the skin.
Haglund syndrome is best understood as a triad:
- Bony: posterosuperior calcaneal prominence (Haglund deformity) impinges on the anterior distal Achilles
- Bursal: retrocalcaneal and (or) superficial subcutaneous bursa inflamed by friction and pressure
- Tendon: insertional Achilles tendinopathy with collagen disorganisation, neovascularisation, and (in chronic cases) calcification
Treating only one component and ignoring the others leads to recurrent symptoms.
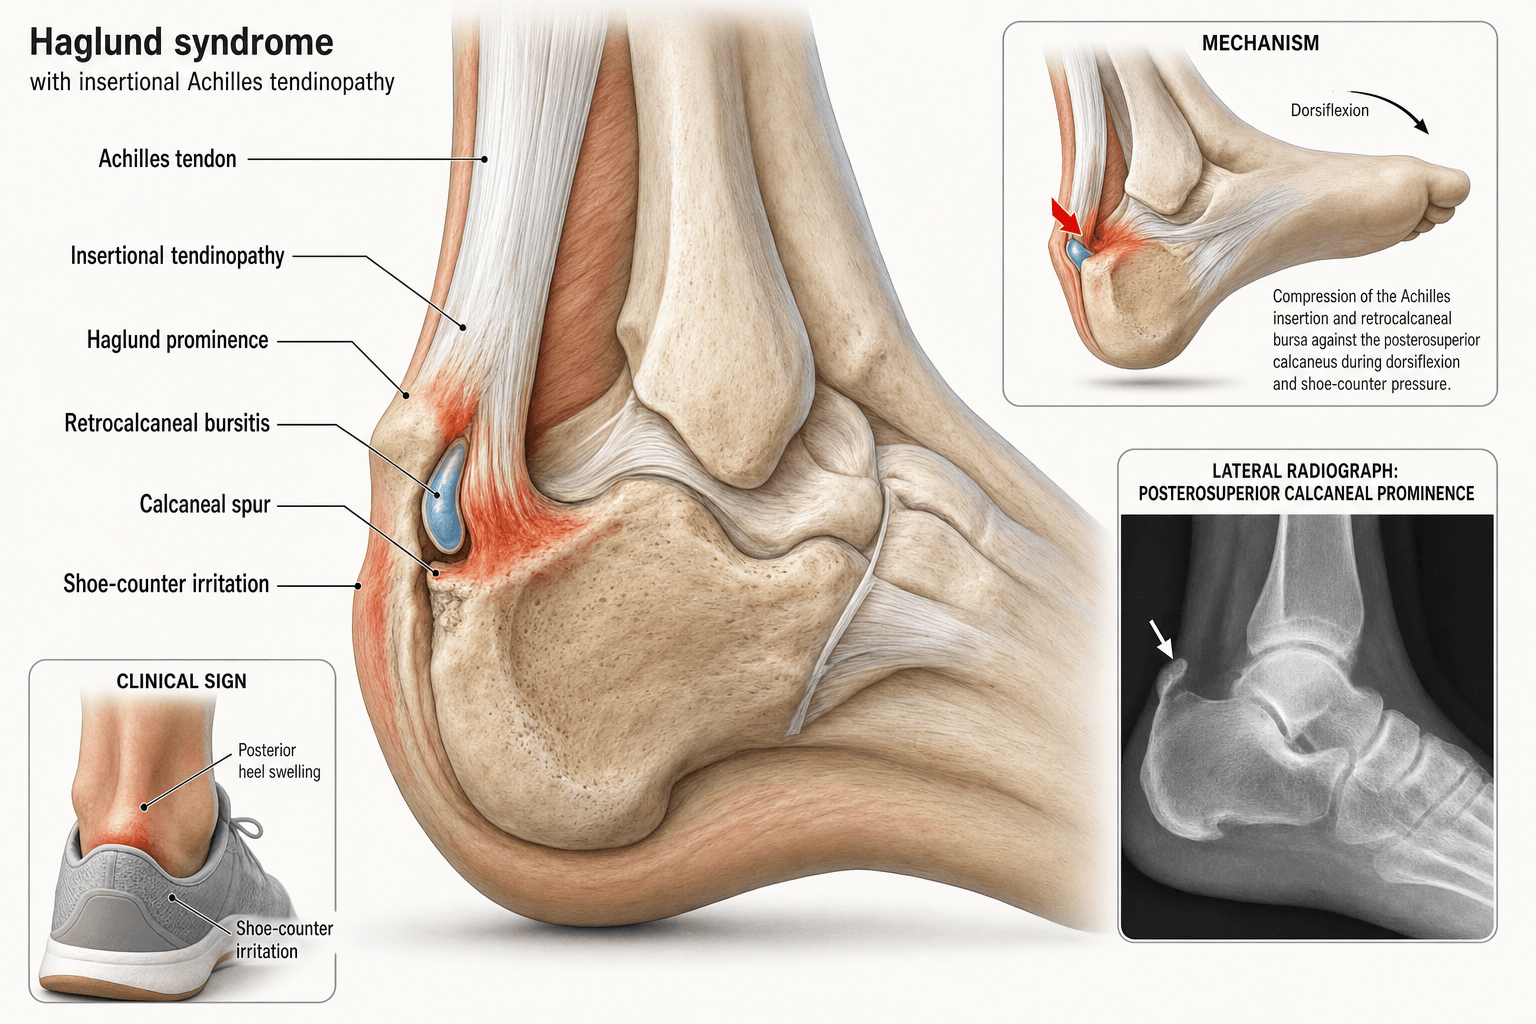
Each component has its own driver, its own histology and its own place on imaging.
- Driver
- Posterosuperior calcaneal shape
- Histology
- Normal bone with prominent convexity
- When Present
- Lateral X-ray, parallel pitch lines
- Driver
- Mechanical impingement in dorsiflexion
- Histology
- Bursal hypertrophy, fibrin, inflammatory cells
- When Present
- MRI: fluid crescent anterior to tendon
- Driver
- Skin pressure from shoe counter
- Histology
- Lobular vascular proliferation
- When Present
- Posterior skin swelling, redness
- Driver
- Repetitive tensile load in hypovascular zone
- Histology
- Disorganised collagen, mucoid change, neovessels
- When Present
- MRI: intrasubstance signal, thickening
- Driver
- Chronic tendinopathy, dystrophic calcification
- Histology
- Hydroxyapatite in degenerated tendon
- When Present
- X-ray: bony spur at insertion
Why the tendon fails. The zone 2-7 cm above the insertion is a watershed area, and the insertional fibres have a separate, poorer blood supply of their own. Under repetitive load, collagen microfailure outstrips repair. Abnormal vessels then grow in with accompanying nerves, which are substance P positive, and these neovessels are the target of sclerosing injections. Calcification is the end-stage finding, often with intratendinous bone formation.
Why the bone impinges. In dorsiflexion the prominent calcaneal corner drives into the anterior Achilles; with equinus, limited dorsiflexion means more impingement per step. A rigid shoe counter compresses the skin and the superficial bursa. Cavus and varus matter because hindfoot varus loads the lateral insertion more.
Classification and Types
The classification that earns its place is by which components are present, because that is what drives the choice between simple ostectomy and combined tendon reconstruction. Retrocalcaneal bursitis can occur without a Haglund prominence, and the tendon can be diseased without a prominent bone.
- Presentation
- Posterior heel pain, no bony lump, painful in tight shoes
- Bone / bursa / tendon
- No Haglund prominence; bursitis on USS or MRI
- Treatment
- Heel lift, open-back shoes, NSAIDs
- Presentation
- Posterosuperior bony bump, painful pump-bump sign
- Bone / bursa / tendon
- Prominent (X-ray, parallel pitch lines); inflamed; normal
- Treatment
- Footwear, heel lift, eccentric, then ostectomy and bursectomy; tendon often preserved
- Presentation
- Bony prominence with insertional Achilles degeneration and bursitis
- Bone / bursa / tendon
- Prominent; inflamed; degenerated
- Treatment
- Ostectomy, debridement, reattachment
- Presentation
- Insertional pain, tender tendon, morning stiffness (MRI or USS)
- Bone / bursa / tendon
- Normal; variable; degenerated or calcified
- Treatment
- Modified eccentric, ESWT; if surgery, debridement only, with tendon detachment and anchor reattachment
- Presentation
- Chronic insertional with calcification or partial tear; MRI shows intrasubstance signal, calcific deposits, partial tear
- Bone / bursa / tendon
- Variable; variable; partial tear plus calcification
- Treatment
- Detachment, debridement, reattachment; FHL transfer if extensive
Clinical Assessment
History. The pain sits at the posterior heel, at or just above the Achilles insertion. It is aggravated by dorsiflexion (stairs, hills), rigid shoe backs and prolonged standing, and relieved by open-back shoes, heel lifts, rest and NSAIDs. Morning stiffness is classic for insertional tendinopathy and not for pure bursitis. Ask about shoe wear (tight dress shoes, ice skates, ski boots) and activity (running mileage, hill work, a sudden spike in load).
Inspection. Look for the posterosuperior bump, erythema, swelling, callus and the pump-bump sign.
Palpation stages the pathology. Where the heel is tender tells you which component is driving it, and the findings are not exclusive, but they help stage the pathology and tailor the imaging:
- Single-finger tenderness at the posterosuperior bony corner suggests Haglund
- Two-finger mediolateral pinch tenderness anterior to the tendon, just above the insertion, suggests retrocalcaneal bursitis; the two-finger squeeze gives a pincer-like tenderness of bursa and tendon
- A tender, thickened tendon, pain on compressing the tendon with the ankle plantarflexed, morning stiffness and a painful heel raise point to insertional tendinopathy
Movement and strength. Measure dorsiflexion and perform the Silfverskiöld test for gastrocnemius equinus. The single-leg heel raise is often weak and painful in chronic tendinopathy.
The Silfverskiöld test separates an isolated gastrocnemius contracture from a combined gastrocnemius-soleus (true ankle) equinus, which changes the operation. Measure passive ankle dorsiflexion with the subtalar joint held neutral (to lock the midfoot), first with the knee extended and then with the knee flexed to 90 degrees. The gastrocnemius crosses the knee; the soleus does not. Dorsiflexion that is restricted with the knee straight but improves markedly with the knee bent = isolated gastrocnemius tightness — the lesion that drives dorsiflexion impingement in Haglund and the indication for a gastrocnemius recession (e.g. Strayer) rather than a tendo-Achilles lengthening. If dorsiflexion remains limited in both knee positions, the soleus is also tight (combined equinus).
Nerves. Palpate the sural nerve and Baxter's nerve at the medial heel.
The first branch of the lateral plantar nerve (Baxter's nerve) runs between the abductor hallucis and quadratus plantae and can be entrapped by a hypertrophied abductor hallucis, presenting as chronic medial heel pain. Distinguishing Baxter's neuropathy from Haglund and insertional tendinopathy matters: nerve-targeted therapy (release) differs from Achilles-targeted therapy. Always examine for Tinel sign over the medial heel, weakness of abductor digiti minimi, and burning paraesthesia.
- Pain site
- Posterosuperior corner
- Discriminating finding
- Visible and palpable bony bump
- Key test
- Lateral X-ray (parallel pitch lines)
- Pain site
- Achilles insertion, centred
- Discriminating finding
- Morning stiffness, tender tendon
- Key test
- MRI: intrasubstance signal at insertion
- Pain site
- Anterior to Achilles, deep
- Discriminating finding
- Pain on deep pinch, no skin redness
- Key test
- MRI: crescent of fluid anterior to tendon
- Pain site
- Posterior, superficial
- Discriminating finding
- Skin erythema, fluctuant swelling
- Key test
- Clinical, ultrasound confirms
- Pain site
- Medial heel, below calcaneus
- Discriminating finding
- Burning, Tinel sign medial heel
- Key test
- EMG, diagnostic injection
- Pain site
- Lateral hindfoot
- Discriminating finding
- Burning, Tinel behind lateral malleolus
- Key test
- Clinical, diagnostic block
- Pain site
- Within tendon substance
- Discriminating finding
- Bilateral, family history of hyperlipidaemia
- Key test
- Lipid panel, MRI
Investigations
The lateral radiograph comes first. A weight-bearing lateral of the ankle or calcaneus. Look for the posterosuperior bony prominence, the parallel pitch lines, the Fowler-Philip angle, intratendinous calcification and a posterior calcaneal cyst. It defines the bone component and guides the ostectomy, and most Haglund decisions can be made on a good weight-bearing lateral with the parallel pitch lines drawn.
Drawing the lines. The parallel pitch lines (Pavlov) are a plantar tangent along the inferior calcaneus and a second line parallel to it through the posterior lip of the talar facet. A posterosuperior corner that projects above the upper line is abnormally prominent, a positive sign: the calcaneus is too tall. The Fowler-Philip angle, between the plantar surface and the posterior surface of the tuberosity, supports a Haglund deformity when it exceeds about 75 degrees, though its sensitivity is limited. A calcaneal pitch over 30 degrees marks a cavus predisposition, so watch for varus overload.
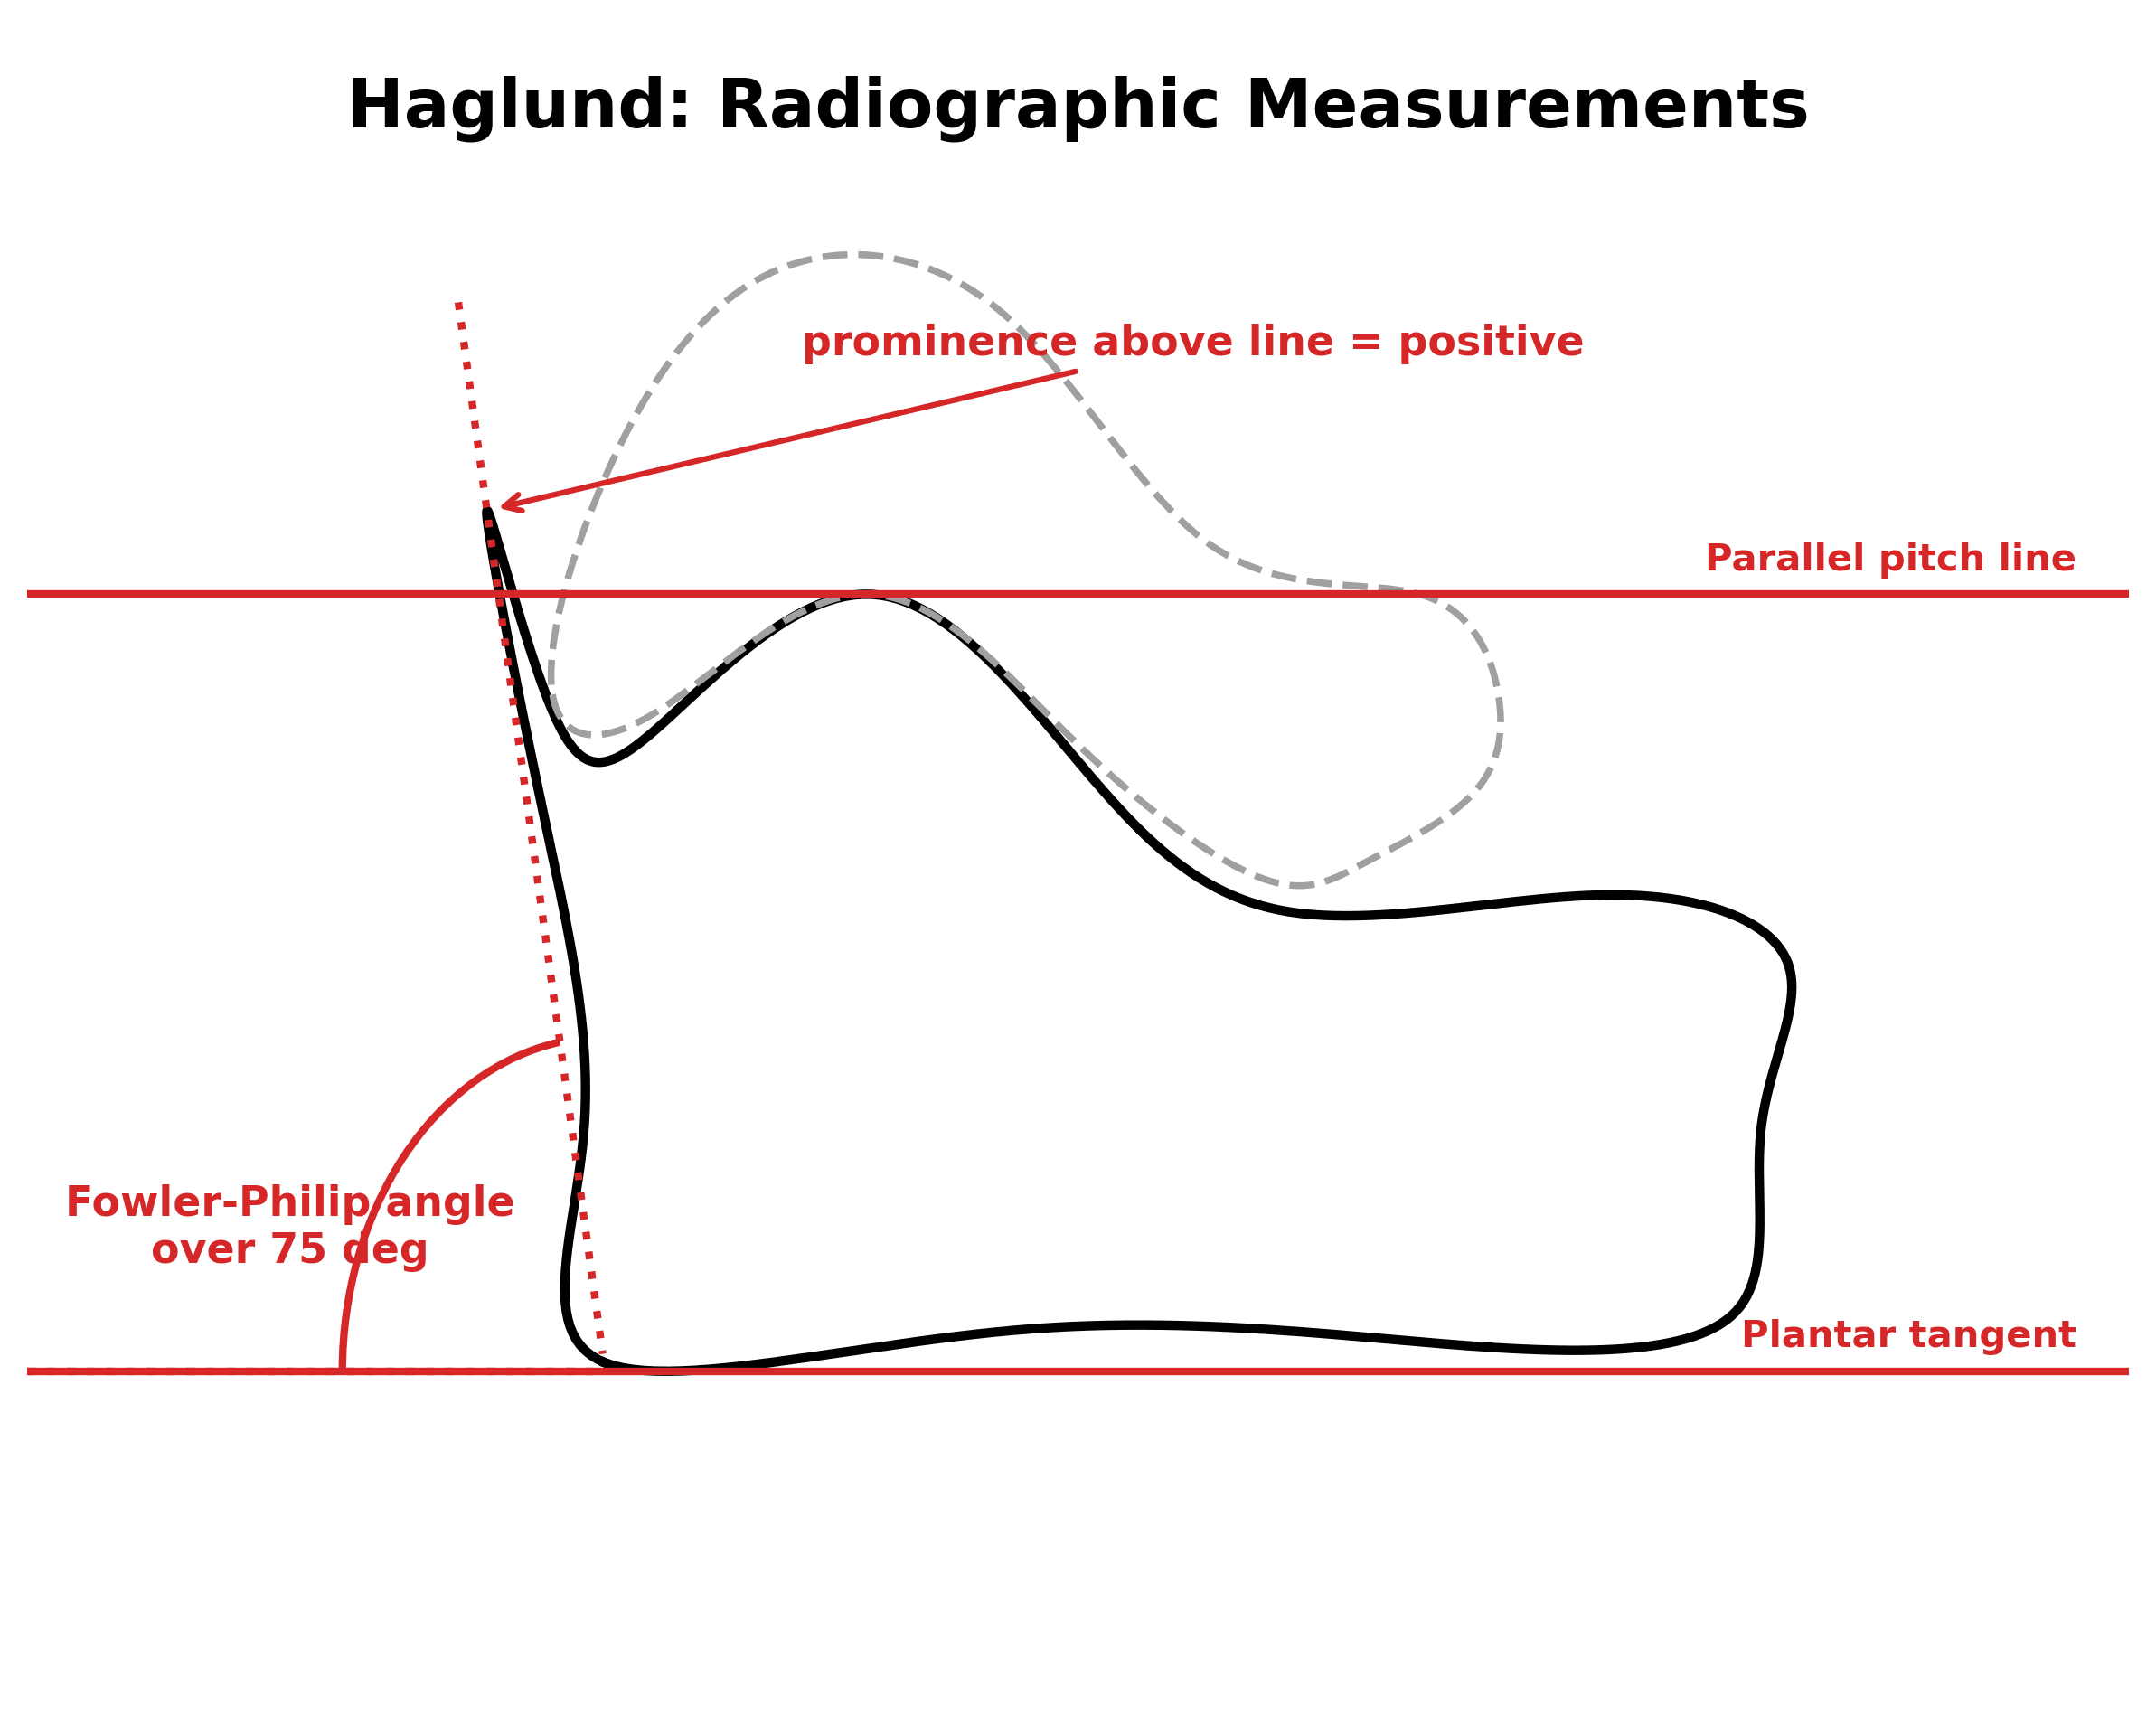
Shape is not the diagnosis. The lines and the angle measure the shape of the heel, and Haglund morphology is common and frequently asymptomatic. In the Fiamengo case-control series in the evidence section, the Fowler-Philip angle did not differ between symptomatic heels and 104 controls; what separated them was the calcaneal step, tendon calcification and calcaneal length. The pitch lines define Haglund and the bone an ostectomy would remove; they do not decide whether to remove it. Use the angles to describe the heel, then let focal tenderness, imaging-confirmed bursitis or insertional tendinopathy, and failure of loading decide whether to operate on it.
Ultrasound. A dynamic assessment of the retrocalcaneal bursa, tendon thickening and neovessels: a bursal fluid crescent, tendon thickening greater than 6 mm, hypoechoic areas and neovascularisation on Doppler. It is operator dependent, but cheap and readily repeatable.
MRI. Reserved for when tendon quality is unclear (chronic cases, failed conservative care, suspected partial tear), for surgical planning, or when the diagnosis is in doubt. Do not MRI every patient with posterior heel pain. It is the best test for tendon quality and partial tears, and shows intrasubstance signal, calcification, partial tear, retrocalcaneal fluid and Kager fat pad oedema.
What each finding changes. Imaging guides the surgical plan more than the clinical examination alone:
- Increased intrasubstance signal at the insertion means tendinopathy or partial tear, and indicates tendon work
- A crescent of retrocalcaneal fluid anterior to the tendon is retrocalcaneal bursitis, and responds to bursectomy
- Intratendinous calcification, bone within the tendon on X-ray, is end-stage tendinopathy and must be debrided
Management Algorithm
The aim. Conservative care is first line, for 6 months, and it has three jobs: settle the bursitis, offload the prominence and restore the tendon's load tolerance.
Conservative Protocol
- Open-back shoes with no rigid counter
- Heel lift of 8-12 mm to reduce dorsiflexion impingement
- Relative rest; avoid hills, stairs and sprinting
- Ice for 15 minutes twice daily
- Alfredson eccentric protocol, modified for insertional disease: flat ground, no step dorsiflexion stretch
- Heavy slow resistance (HSR), 3 sessions per week, as the alternative
- Gastrocnemius stretching: 30-second hold, 3 reps, twice daily
- NSAIDs as a short course for bursitis; avoid long-term use
- ESWT (shockwave): 3 sessions, 2000 pulses, moderate energy
- Sclerosing injections (polidocanol) for neovessels at the anterior tendon
- PRP (autologous blood): 2-3 injections if available, evidence variable
- High-volume stripping for resistant paratendinopathy
- VISA-A score trend: from 50-60 to greater than 70 is considered a good response
- Persistent pain with a low VISA-A: surgical opinion
- Return to running: gradual mileage, no hills initially
The Alfredson protocol. Heavy-load eccentric calf training on a step: 3 sets of 15, twice daily, morning and evening, which is 180 repetitions a day, every day for 12 weeks. The loading is eccentric only.
- Up on both legs, down slowly on one; no concentric-only work
- Continue despite discomfort, which is expected; stop only for sharp pain
- Add resistance, a backpack with weights, once tolerated
- Compliance predicts outcome; it is less effective if not performed daily
The insertional modification. For insertional tendinopathy, do not perform the standard Alfredson heel drop off a step, which loads the insertion in dorsiflexion. Use flat-ground heel drops or isometric contractions for the first 4-6 weeks. The standard protocol works well for midportion tendinopathy but can aggravate insertional symptoms.
When to stop. The threshold is 6 months of structured, compliant conservative care; earlier surgery does not improve outcomes and may worsen them.
The Zadek osteotomy: the tendon-sparing alternative
What it is. A dorsal closing-wedge calcaneal osteotomy (Zadek, also credited to Keck and Kelly), the emerging option that treats the bony geometry without touching the Achilles insertion at all. Removing a dorsally based wedge from the tuberosity reduces the calcaneal pitch and rotates the posterosuperior prominence away from the tendon, so the impinging corner no longer abuts the Achilles, rather than debriding the tendon and its footprint.
Why it appeals. It avoids detaching any part of the insertion, so the question of how much of the footprint can be taken down does not arise, and it needs no anchor reattachment or augmentation.
Zadek (dorsal closing-wedge) osteotomy for insertional Achilles tendinopathy — meta-analysis
- 10 studies, 232 patients undergoing Zadek dorsal closing-wedge calcaneal osteotomy for insertional disease
- Functional scores and pain improved significantly after osteotomy (p less than 0.00001)
- 22 reported complications, all minor - most commonly superficial infection and sural nerve paraesthesia
- The osteotomy reduces the calcaneal pitch and rotates the prominence away from the tendon
- No randomised trial has compared osteotomy with conventional debridement
Complications
- Incidence
- 5-15 percent open, less than 2 percent endoscopic
- Risk Factors
- Posterior wound tension, smoking, steroids
- Management
- Meticulous closure, offload, vascularised flap if needed
- Incidence
- 2-5 percent
- Risk Factors
- Lateral dissection too far
- Management
- Identify and protect; neuroma if cut
- Incidence
- 1-3 percent
- Risk Factors
- Early loading, FHL transfer if extensive debridement
- Management
- Cast, surgical repair if complete
- Incidence
- 5-10 percent
- Risk Factors
- Under-resection of posterosuperior corner
- Management
- Revision ostectomy, MRI to assess
- Incidence
- 10-20 percent
- Risk Factors
- Prolonged immobilisation, over-tight reattachment
- Management
- Physiotherapy, heel raise long term
- Incidence
- 1-2 percent
- Risk Factors
- Prolonged immobility, obesity, OCP
- Management
- Mechanical prophylaxis, consider chemical
- Incidence
- 10-15 percent over 5 years
- Risk Factors
- Cavus, equinus, inadequate rehab
- Management
- Footwear, gastrocnemius lengthening, revision
The posterior approach crosses a watershed area with poor skin vascularity, and wound breakdown is the most common cause of re-operation. Meticulous technique (no skin tension, full-thickness flaps, careful soft tissue handling, offloading) reduces dehiscence. Smokers and diabetics are at the highest risk.
Outcomes and Prognosis
- Time to effect
- 12 weeks
- Success
- 60-70 percent in midportion, 30-50 percent in insertional
- Long-term
- Best in compliant, non-calcified cases
- Time to effect
- 8-12 weeks
- Success
- 50-60 percent improvement in pain scores
- Long-term
- Useful adjunct, not stand-alone in severe cases
- Time to effect
- 6-8 weeks
- Success
- 40-50 percent for neovessel-positive cases
- Long-term
- Evidence still limited
- Time to effect
- 6-9 months
- Success
- 85-90 percent good-to-excellent at 2 years
- Long-term
- Gold standard for failed conservative
- Time to effect
- 3-6 months
- Success
- 80-85 percent for pure Haglund
- Long-term
- Less wound risk, limited for tendon work
Favours good outcome: short symptom duration, single pathology (bone only or tendon only), compliant eccentric loading, normal BMI, non-smoker, no diabetes.
Favours poor outcome: long-standing symptoms, intratendinous calcification, partial tear over 50 percent, smoking, diabetes, obesity, equinus not addressed.
Guidelines, Registries & Global Practice
- Insertional Achilles tendinopathy accounts for 20-25 percent of all Achilles tendon pain in running populations across regions
- Pure Haglund is more common in women wearing rigid dress shoes and in ice-hockey, skiing, and football populations
- Incidence of insertional tendinopathy in runners is roughly 10 percent per year in published cohorts (UK, US, Australian, Dutch registries)
- Bilateral involvement occurs in up to 40 percent of insertional cases — always examine both sides
- High-resource: ESWT, MRI, ultrasound-guided injection, and endoscopic surgery are widely available
- Limited-resource: structured eccentric loading, footwear advice, and open ostectomy remain the backbone
- Universal principle: outcome depends far more on patient compliance with loading and footwear than on the technology used
- Surgery: open central tendon splitting is universally available; endoscopic ostectomy is concentrated in specialist foot and ankle centres
- Diagnosis emphasis
- Clinical diagnosis, lateral X-ray to define Haglund, MRI for surgery planning
- First-line treatment
- Footwear, heel lift, modified Alfredson, ESWT
- Surgery threshold
- Failed 6 months conservative + low VISA-A
- Diagnosis emphasis
- Clinical plus lateral X-ray, MRI for chronic or surgical cases
- First-line treatment
- Activity modification, modified eccentric, ESWT, PRP optional
- Surgery threshold
- Failed conservative with persistent functional limitation
- Diagnosis emphasis
- Combined clinical and imaging diagnosis; ultrasound and MRI equivalent
- First-line treatment
- Eccentric loading, HSR, ESWT, orthotics
- Surgery threshold
- Central tendon splitting with anchor reattachment for combined cases
- Diagnosis emphasis
- Weight-bearing lateral X-ray mandatory; MRI for surgical planning
- First-line treatment
- Eccentric loading, footwear, ESWT
- Surgery threshold
- Open or endoscopic ostectomy based on tendon involvement
There is no dedicated arthroplasty or implant registry for Haglund syndrome (no implants used). The evidence base is dominated by small case series and operative-technique reviews, with only a few high-quality RCTs (Beyer 2015 for HSR vs eccentric; Rompe for ESWT). Registry data from the National Joint Registry (UK), AJRR (US), and AOANJRR (Australia) do not capture this condition. Guidance is therefore principle-based: diagnose with a lateral X-ray, treat the triad, fail conservative for 6 months before surgery, and address equinus when present.
Record in every posterior heel pain consultation:
- Components present (bone, bursa, tendon) with explicit clinical findings
- Silfverskiold test result and equinus assessment
- X-ray findings (parallel pitch lines, Fowler-Philip angle, calcification)
- Conservative plan and duration (footwear, heel lift, modified Alfredson)
- Outcome measure (VISA-A) at baseline and follow-up
- Surgical threshold discussed if conservative fails
Posterior heel pain is a recurring source of complaints worldwide. A clear, well-documented conservative trial protects both patient and clinician.
Controversies & Areas of Uncertainty
The standard Alfredson protocol was designed for midportion disease and may aggravate insertional symptoms because of dorsiflexion loading. Modified flat-ground variants, HSR, and isometrics all have advocates, but no head-to-head trial exists for the insertional subtype.
Endoscopic ostectomy reduces wound complications but limits tendon visualisation. Open central tendon splitting is more versatile for combined cases. Choice is driven by surgeon experience and tendon involvement, not by strong comparative evidence.
FHL transfer is reserved for very large insertional defects (over 50 percent) or revision cases. Outcomes are good but the donor morbidity (loss of hallux plantarflexion strength) is real. Indication is not standardised.
Platelet-rich plasma and autologous blood injections are widely marketed, but the randomised evidence does not show consistent benefit over placebo for insertional tendinopathy. Consider only within trials or for refractory cases after shared decision-making.
MCQ Practice Points
Q: What is the Haglund deformity and where does it sit? A: Posterosuperior bony prominence of the calcaneus at the Achilles tendon insertion. It is the bony component of the Haglund syndrome triad, first described by the Swedish orthopaedist Patrick Haglund in 1928.
Q: How do you define the Haglund deformity on a lateral X-ray? A: Parallel pitch lines (Pavlov). Draw the inferior calcaneal line and a parallel line through the posterior lip of the talar facet. If the bony corner projects above the superior line, the calcaneus is too tall. A Fowler-Philip angle over 75 degrees supports Haglund but is less specific.
Q: Why does insertional Achilles tendinopathy respond less well to standard Alfredson eccentric loading? A: Because the step in the classic Alfredson protocol loads the insertion in maximal dorsiflexion, which compresses the tendon against the posterosuperior calcaneal corner. The modified protocol uses flat-ground heel drops or isometric contractions that avoid this impingement.
Q: What are the components of surgical management for combined Haglund and insertional tendinopathy? A: (1) Posterior midline or paratendinous approach; (2) central tendon splitting; (3) debridement of calcific and necrotic tendon; (4) 3-5 mm calcaneal ostectomy; (5) bursectomy; (6) Achilles reattachment with two suture anchors in equinus; (7) consider gastrocnemius recession for equinus.
Q: What is the minimum duration of structured conservative care before offering surgery? A: At least 6 months of structured, compliant loading (modified eccentric or HSR), footwear modification, ESWT, and activity change. Earlier surgery does not improve outcomes and may worsen them.
Q: How do you distinguish Haglund/insertional tendinopathy from Baxter's nerve entrapment? A: Baxter's nerve (first branch of the lateral plantar) entrapment presents with medial heel burning, Tinel sign over the medial heel, and weakness of the abductor digiti minimi. Haglund/insertional tendinopathy presents with posterior heel pain, bony bump, and tendon tenderness. Nerve-targeted therapy (release) differs from Achilles-targeted therapy.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 38-year-old recreational marathon runner presents with 8 months of posterior right heel pain. He can no longer run uphill without pain. He has tried rest, NSAIDs, and a heel lift. On examination, there is a tender posterosuperior bump, painful mediolateral squeeze at the insertion, and a single-leg heel raise reproduces pain. Silfverskiold is positive for gastrocnemius tightness. Lateral X-ray shows a prominent posterosuperior corner and parallel pitch lines positive. What is your diagnosis and management?”
“A 32-year-old woman presents with 4 months of bilateral posterior heel pain, worse when she wears work heels. She has a visible posterosuperior bump on each heel, erythema over the bump, and tenderness on mediolateral pinch. Single-leg heel raise is mildly painful but strong. Silfverskiold is normal. Lateral X-ray shows a positive parallel pitch lines sign. She has tried gel heel cups. How do you manage this?”
Key Anatomy and Pathology
- Haglund = posterosuperior calcaneal prominence at the Achilles insertion
- Three coexisting pathologies: BONY prominence + BURSITIS + TENDINOPATHY
- Retrocalcaneal bursa lies between anterior Achilles and calcaneus
- Insertional tendon is a watershed area with poor blood supply
Diagnosis
- Lateral X-ray with parallel pitch lines (Pavlov) defines Haglund
- Fowler-Philip angle over 75 degrees supports Haglund
- Two-finger mediolateral squeeze: retrocalcaneal bursitis
- MRI for chronic or surgical cases (tendon quality, partial tear)
Treatment Algorithm
- First line: footwear (open-back), heel lift 8-12 mm, NSAIDs
- Loading: modified Alfredson on flat ground or HSR for 12 weeks
- Adjuncts: ESWT, sclerosing injection for neovessels
- Surgery: ostectomy plus tendon reattachment if conservative fails over 6 months
Eccentric Pearls
- Step Alfredson works for midportion, not for insertional
- Insertional: flat-ground heel drops or isometrics first
- 180 reps per day is the original protocol; HSR is 3 times per week alternative
- Compliance is the strongest predictor of outcome
Surgical Pearls
- 3-5 mm calcaneal ostectomy removes the impinging corner
- Central tendon splitting accesses the insertional pathology
- Reattach with 2 suture anchors in equinus, then bring to neutral in boot
- Address gastrocnemius equinus (Silfverskiold) with recession when positive
Complications
- Posterior wound dehiscence is the most common re-operation cause (5-15 percent open)
- Sural nerve injury 2-5 percent, identify and protect
- Achilles re-rupture 1-3 percent, longer in FHL transfer cases
- Recurrence 10-15 percent over 5 years if equinus and footwear not addressed
Evidence Base and Key Trials
Heavy-load eccentric calf muscle training for the treatment of chronic Achilles tendinosis
- Prospective cohort of 30 recreational athletes with midportion Achilles tendinosis
- Heavy-load eccentric protocol: 180 reps per day (3 sets of 15, twice daily) on a step
- All 30 patients returned to pre-injury activity at 12 weeks with no further pain
- Satisfaction was high despite continued neovascularisation on follow-up imaging
Heavy Slow Resistance Versus Eccentric Training as Treatment for Achilles Tendinopathy: A Randomized Controlled Trial
- RCT of 58 patients with midportion Achilles tendinopathy randomised to Alfredson eccentric or heavy slow resistance (HSR) training
- Both groups improved significantly in VISA-A and pain scores at 12 and 52 weeks
- HSR group had higher patient satisfaction at 52 weeks with only 3 sessions per week
- No difference in pathology thickness on ultrasound between groups at 52 weeks
Surgical strategies: insertional Achilles tendinopathy
- Technique review and clinical series of central tendon splitting with calcaneal ostectomy
- Approach: midline or medial paratendinous, full-thickness flap, longitudinal split of the tendon
- Ostectomy 3-5 mm, debridement of calcific and necrotic tissue, reattachment with two suture anchors
- High satisfaction (greater than 80 percent) in chronic insertional cases failing conservative care
Posterior heel pain associated with a calcaneal step and Achilles tendon calcification
- CASE-CONTROL, not a simple series: 19 symptomatic heels (12 with reviewable radiographs) compared against 104 control cases
- THE FOWLER-PHILIP ANGLE DID NOT DIFFER between symptomatic heels and controls (p greater than 0.05), and the authors write that although a posterosuperior calcaneal prominence is theoretically important, 'it was not in this series'
- What DID separate the groups: a significantly longer horizontal calcaneal length (p less than 0.05), Achilles tendon calcification (p = 0.004) and a posterior calcaneal step (p less than 0.001)
- Described the calcaneal step - an abrupt change in cortical contour at the Achilles insertion - and proposed that the step alters tension within the tendon, causing microscopic injury, reduced vascularity and subsequent calcification or rupture
- Histology: insertional calcification and mucoid degeneration at the bone-tendon junction