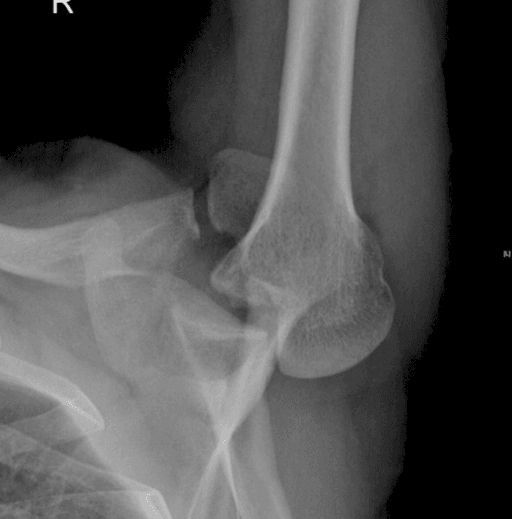
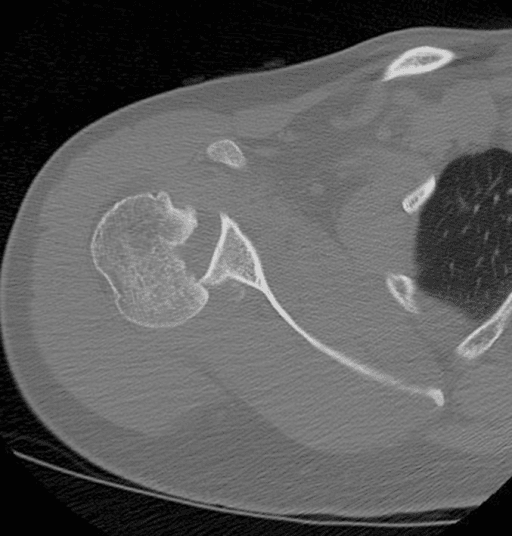
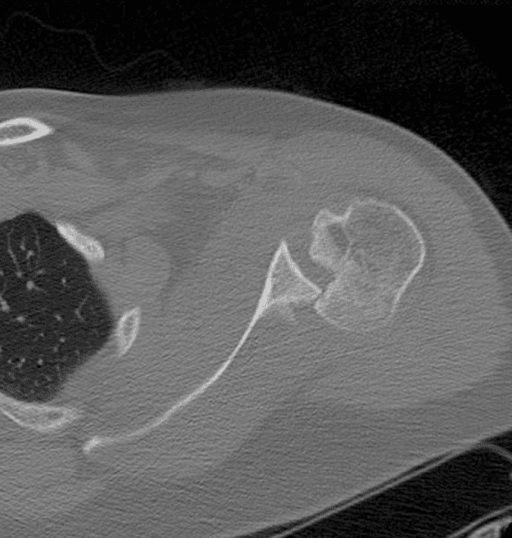
Posterolateral humeral head impression fracture | 40-90% of anterior dislocations
- Impression fracture of posterolateral humeral head from anterior glenoid rim
- Engaging vs Non-engaging lesions (dynamic evaluation)
- Glenoid Track Concept: less than 83% width rule
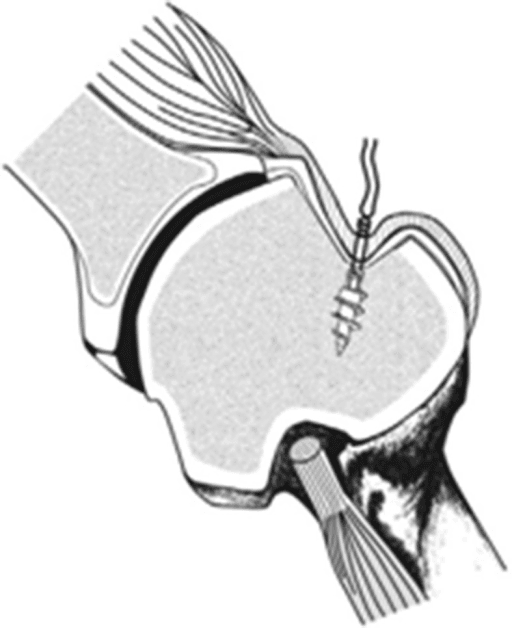
- Remplissage: Infraspinatus capsulotenodesis for off-track lesions
- Associated with Bankart lesions (bipolar bone loss)
- “Look for 'engaging' lesion on exam (Apprehension at lower abduction angles)
- “Stryker Notch View is best X-ray
- “CT with 3D reconstruction is gold standard for quantification
- “Always calculate the Glenoid Track
Overview and Epidemiology
A Hill-Sachs lesion is a compression fracture of the posterolateral humeral head, made when the head is driven against the anterior glenoid rim during an anterior dislocation. It is one half of the "bipolar bone loss" of anterior shoulder instability; the anterior glenoid is the other half.
How common. A Hill-Sachs lesion is present in 40 to 90 percent of first-time anterior dislocations and in up to 90 to 100 percent of shoulders with recurrent instability.
Why it matters. A large or "off-track" lesion engages the anterior glenoid rim in the at-risk position and levers the head out of the socket. A lesion that is missed carries a high risk of recurrence.
Pathophysiology and Mechanisms
Where it forms. The defect sits on the posterolateral aspect of the humeral head, superior to the greater tuberosity. The dislocation is an anterior one with the arm attempting to internally rotate, typically a traumatic abduction and external rotation injury, and the lesion is the dent left when the soft cancellous bone of the head impacts the hard cortical bone of the anterior glenoid rim.
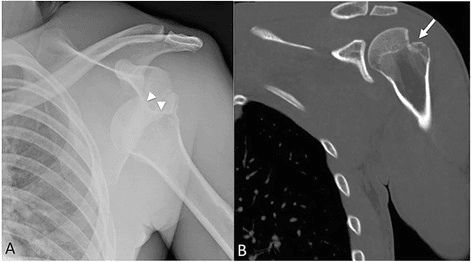
Bipolar bone loss. The Hill-Sachs lesion interacts with any anterior glenoid bone loss (the bony Bankart). It is the combined loss that reduces the arc of stability.
Engagement. In abduction and external rotation, the at-risk position, the perceived width of the glenoid track narrows. If the Hill-Sachs lesion is wide enough to bridge the narrowed track, the anterior glenoid rim falls into the defect, and that levering action forces the humeral head out of the socket.
Classification Systems
The concept (Itoi, Di Giacomo). The glenoid track is the contact zone of the glenoid on the humeral head during abduction and external rotation: the "safe zone" of the head that stays in contact with the glenoid. The "zone of co-existence" is the corollary: the rotator cuff footprint defines the lateral margin of that contact patch, and a Hill-Sachs lesion expands the non-contact zone medially. It is the gold standard for surgical decision-making.
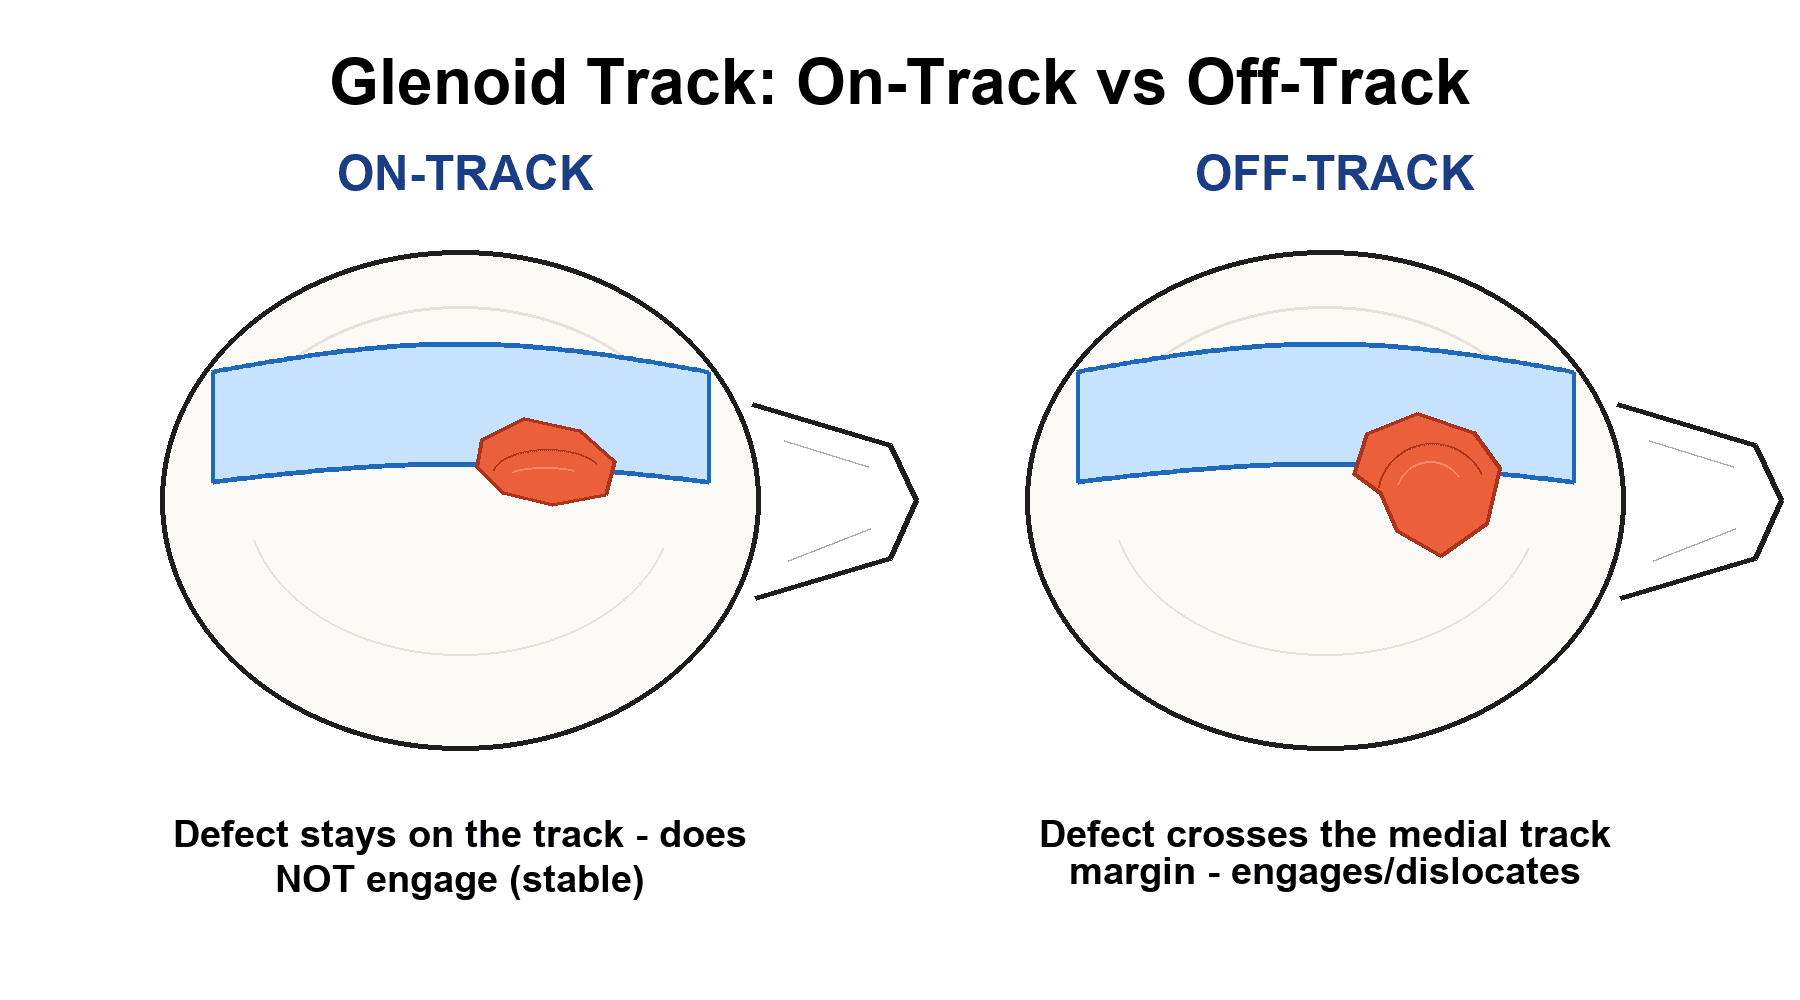
Calculating it. The measurements are made on an en-face 3D CT:
- Measure the glenoid diameter (D) using the inferior circle method
- The expected track is 0.83 x D
- Measure the glenoid defect (d), the linear width of anterior bone loss
- The true track width is (0.83 x D) - d
- Measure the Hill-Sachs interval (HSI), from the rotator cuff footprint to the medial margin of the lesion
- Compare: HSI less than the track and the lesion is covered by the glenoid, on-track; HSI greater than the track and the lesion extends beyond the glenoid rim, off-track
Reading the result. An on-track lesion does not engage, and a standard Bankart repair is usually sufficient. An off-track lesion extends medial to the track, engages the anterior rim in abduction and external rotation, and needs a remplissage or a Latarjet. Forget to subtract d and an unstable lesion is misclassified as stable.
Clinical Assessment
History. A history of recurrent anterior dislocations, and a feeling of the shoulder "locking" or getting stuck in abduction and external rotation.
Examination. The findings to elicit are these:
- Apprehension test: positive in abduction and external rotation
- Relocation test: apprehension relieved by a posteriorly directed force
- Crepitus: may be felt in the mid-range of rotation if the lesion is large
- Engaging sign: symptoms (a clunk or apprehension) reproduced at lower degrees of abduction may suggest an engaging lesion
Engaging is a clinical finding (locking). Off-track is a radiographic calculation. They are related but distinct concepts, and confusing them is a critical exam failure.
Investigations
Radiographs. The standard AP often misses the posterolateral defect, so request the views that profile it:
- AP in internal rotation
- Axillary view
- Stryker notch view: hand on the head, beam tilted 10 degrees cephalad; the best plain view for a Hill-Sachs lesion
- West Point view: the best plain view for glenoid bone loss
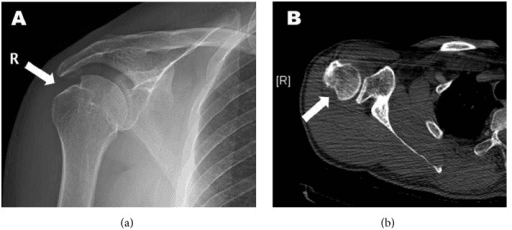
CT. The gold standard for quantifying bone loss; the key CT view is the axioscapular. The protocol is a 3D reconstruction with the humeral head subtracted, which gives the en-face glenoid view on which the track is measured.
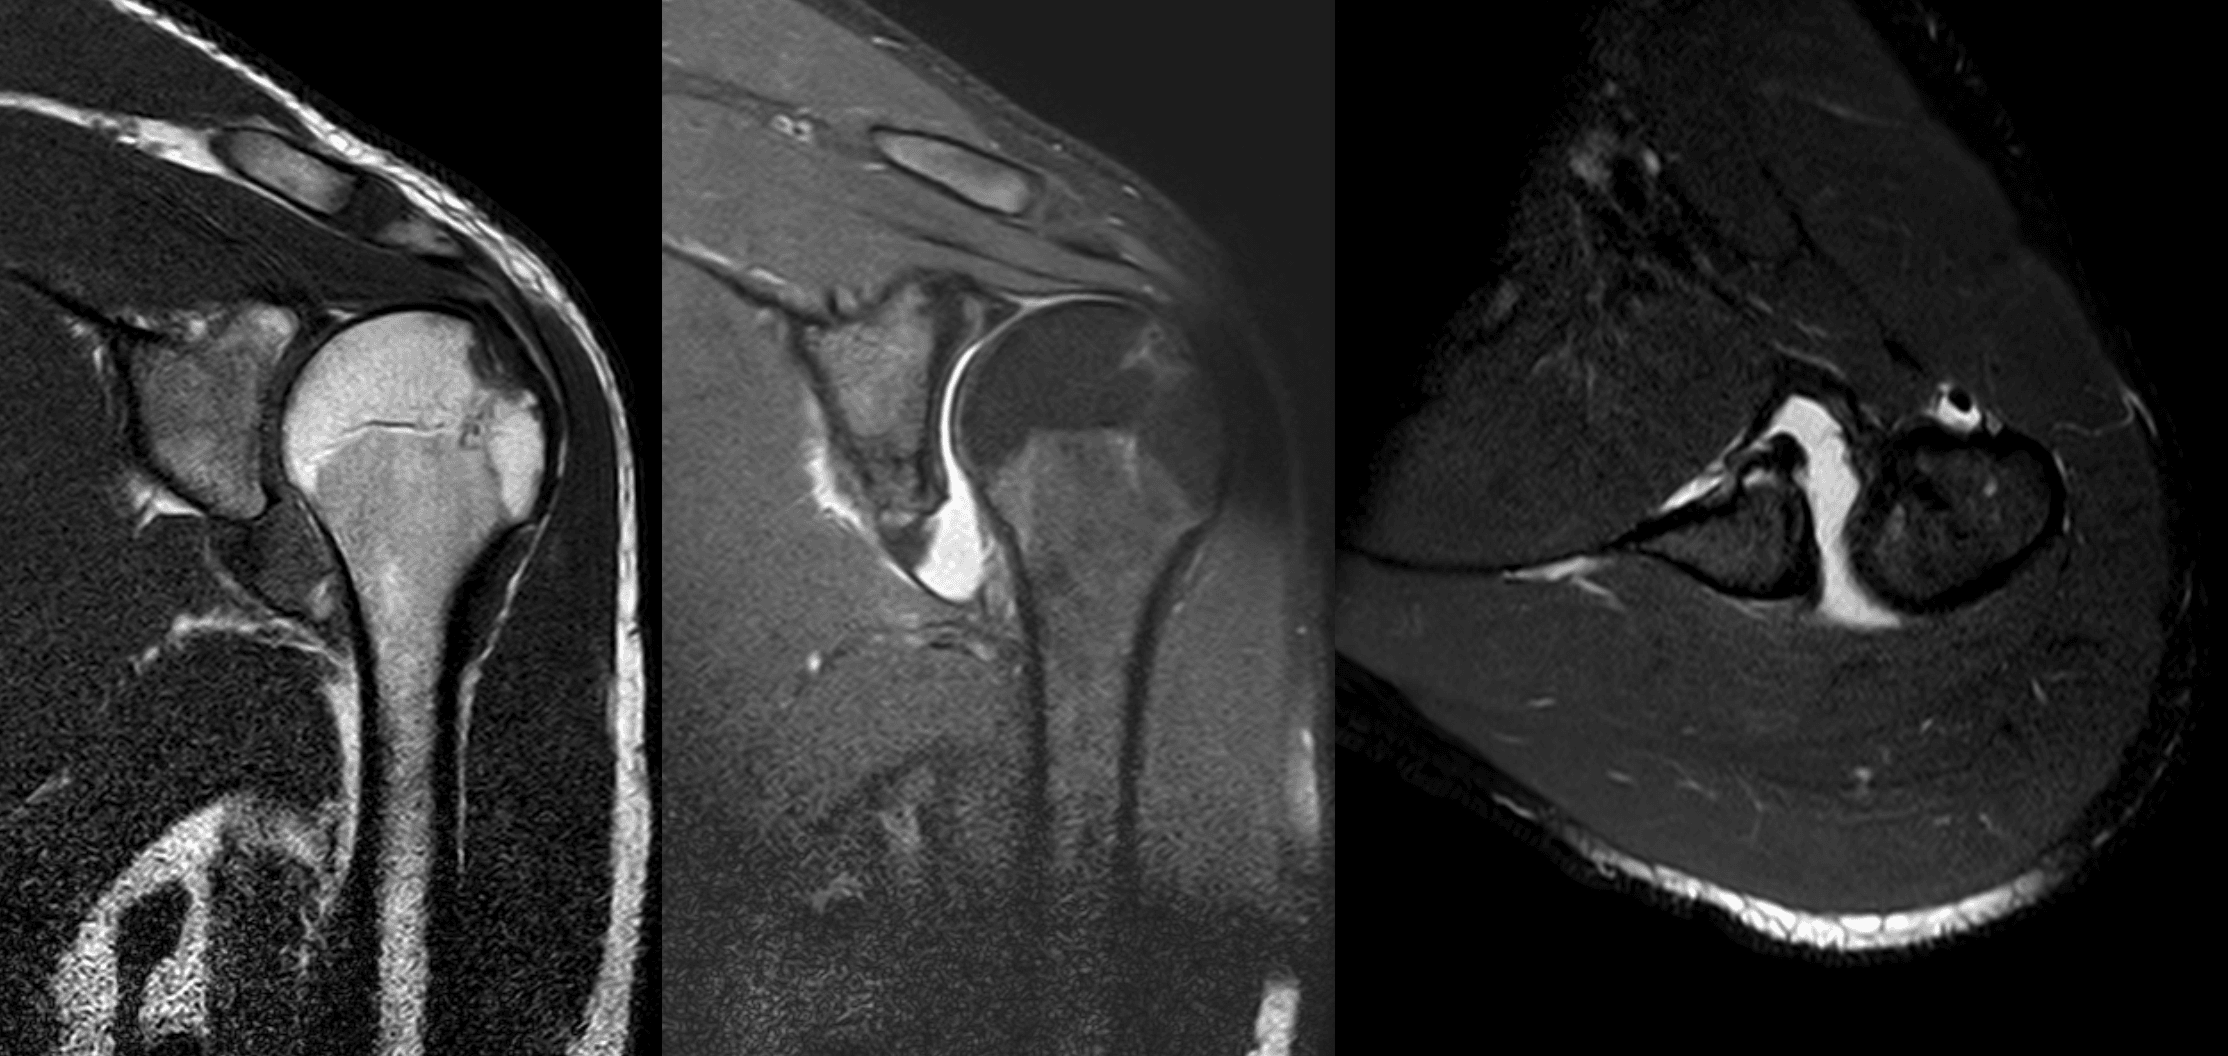
MRI. Its job is the soft tissue: the Bankart lesion and rotator cuff tears. It can estimate bone loss, but CT is superior; on MRI the axial cuts are where the depth of the lesion is seen.
Differential Diagnosis
A posterolateral humeral head defect or a "locking/apprehensive" shoulder is not always a true engaging Hill-Sachs lesion. Distinguish it from the following:
- Mechanism / Location
- Posterolateral head, anterior dislocation
- Key Distinguishing Feature
- Impaction on ANTERIOR glenoid rim; pairs with Bankart lesion
- Mechanism / Location
- Anteromedial head, posterior dislocation
- Key Distinguishing Feature
- Locked internal rotation, classic seizure/electrocution/posterior trauma history
- Mechanism / Location
- Posterolateral, physiological
- Key Distinguishing Feature
- Smooth, at/above cuff footprint, no subchondral break — do not over-call as pathological
- Mechanism / Location
- Variable head location
- Key Distinguishing Feature
- Marrow oedema or collapse on MRI, atraumatic or steroid/alcohol history
- Mechanism / Location
- No bony defect
- Key Distinguishing Feature
- Sulcus sign, hyperlaxity (Beighton), bilateral, no Hill-Sachs
- Mechanism / Location
- Anteroinferior glenoid rim fracture
- Key Distinguishing Feature
- Glenoid defect drives instability; humeral lesion may be small
Management Algorithm
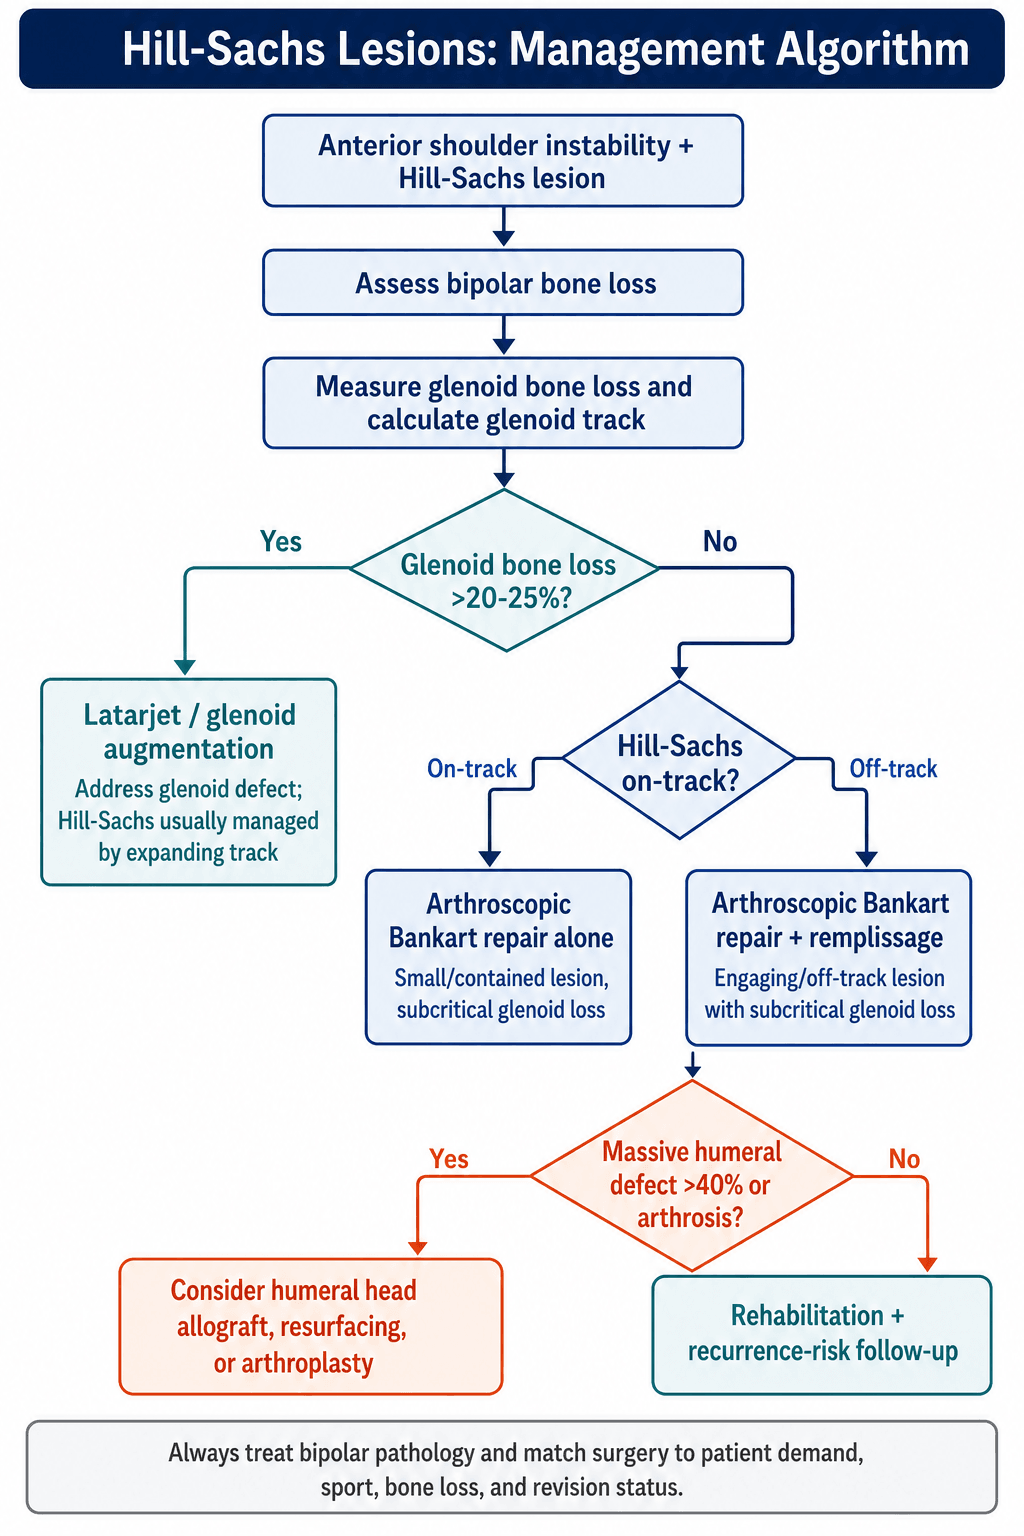
The two questions. The decision is made in order: first the glenoid, then the track. Both bipolar lesions are always addressed.
Step 1: how much glenoid is missing. Glenoid bone loss greater than 20 to 25 percent goes to a Latarjet, regardless of the Hill-Sachs lesion. Less than that, and the track decides. The 20 to 25 percent figure is older teaching; contemporary work puts the point at which recurrence rises as low as 13.5 percent in high-demand athletes, which lowers the threshold for augmentation in that group.
Step 2: is the Hill-Sachs on-track. An on-track lesion is treated with an arthroscopic Bankart repair alone. An off-track lesion is treated with an arthroscopic Bankart repair plus a remplissage; a Bankart repair alone for an off-track lesion has a high recurrence rate.
The options. Chosen by patient demand and bone loss:
- Non-operative: only for low-demand patients and first-time dislocators with small on-track lesions; rarely successful in young active patients
- Arthroscopic Bankart repair: soft-tissue repair only; failure rate high if the lesion is off-track
- Remplissage: infraspinatus capsulotenodesis; "fills" the defect with tendon, making it extra-articular
- Latarjet: coracoid transfer; increases the width of the glenoid track (lengthens the track)
- Humeral head allograft: for massive defects (greater than 40%) where remplissage is insufficient
- Resurfacing arthroplasty: for older patients with degenerative changes
- Remplissage
- Off-track, subcritical bone loss
- Latarjet
- Critical glenoid bone loss (greater than 20%)
- Remplissage
- Check-rein + Fill
- Latarjet
- Triple blocking effect
- Remplissage
- Extra-articular tenodesis
- Latarjet
- Coracoid bone block transfer
- Remplissage
- Arthroscopic (Posterior)
- Latarjet
- Open (Deltopectoral) or Arthroscopic
- Remplissage
- Stiffness, Pain
- Latarjet
- Nerve injury, Graft non-union
- Remplissage
- Low (if indications correct)
- Latarjet
- Lowest (less than 5%)
Humeral-Sided Reconstruction for Large Defects
A minority of lesions are too large or too deep for soft-tissue filling, and there the humeral side itself must be reconstructed rather than filled or made extra-articular. The ladder rises with defect size and articular involvement:
- Option
- Remplissage (infraspinatus tenodesis)
- Principle
- Converts the engaging defect to extra-articular (check-rein + fill)
- Option
- Latarjet / glenoid bone block
- Principle
- Lengthens the glenoid track so the humeral defect no longer engages (no humeral work)
- Option
- Disimpaction and bone grafting
- Principle
- Elevate the depressed articular surface and support it with graft ('raise the dent')
- Option
- Osteochondral / segmental humeral allograft
- Principle
- Reconstructs the articular surface with a size-matched humeral head allograft
- Option
- Partial humeral head resurfacing (metal inlay)
- Principle
- A metal implant fills and resurfaces the engaging defect
- Option
- Arthroplasty (hemi, resurfacing or total shoulder)
- Principle
- Replaces the articular surface when the head is non-reconstructable or arthritic
- Option
- Rotational (proximal humeral) osteotomy (Weber)
- Principle
- Rotates the defect out of the articulating arc — largely abandoned
Most off-track lesions are solved on the soft-tissue or glenoid side. Reserve true humeral reconstruction for the large, deep defect, commonly cited beyond roughly 30 to 40 percent of the head, where filling is mechanically inadequate.
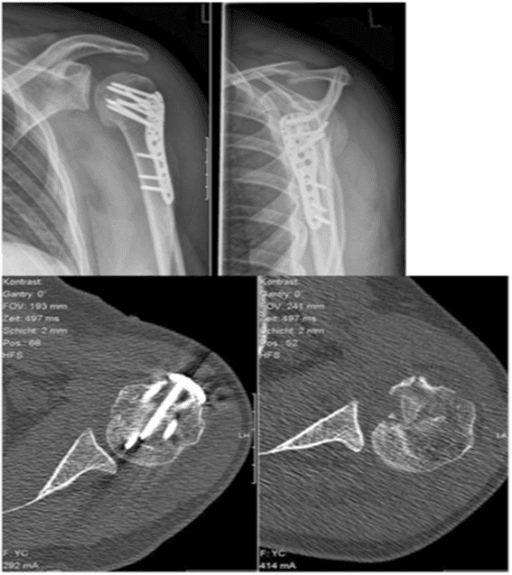
Reverse Hill-Sachs Lesion and the McLaughlin Procedure
The reverse Hill-Sachs (McLaughlin) lesion is the posterior mirror image of the classic defect, and it is examined just as often. It is an impaction fracture of the anteromedial humeral head, made when a posterior dislocation drives the head onto the posterior glenoid rim. The classic causes are the "three E's": Epilepsy (seizure), Electrocution and Extreme trauma.
Why it is missed. The arm is locked in internal rotation and adduction with no external rotation, and the AP film can look near-normal. Look for the "light-bulb" sign of fixed internal rotation, the rim sign and the trough-line sign, and always obtain an axillary view or a CT.
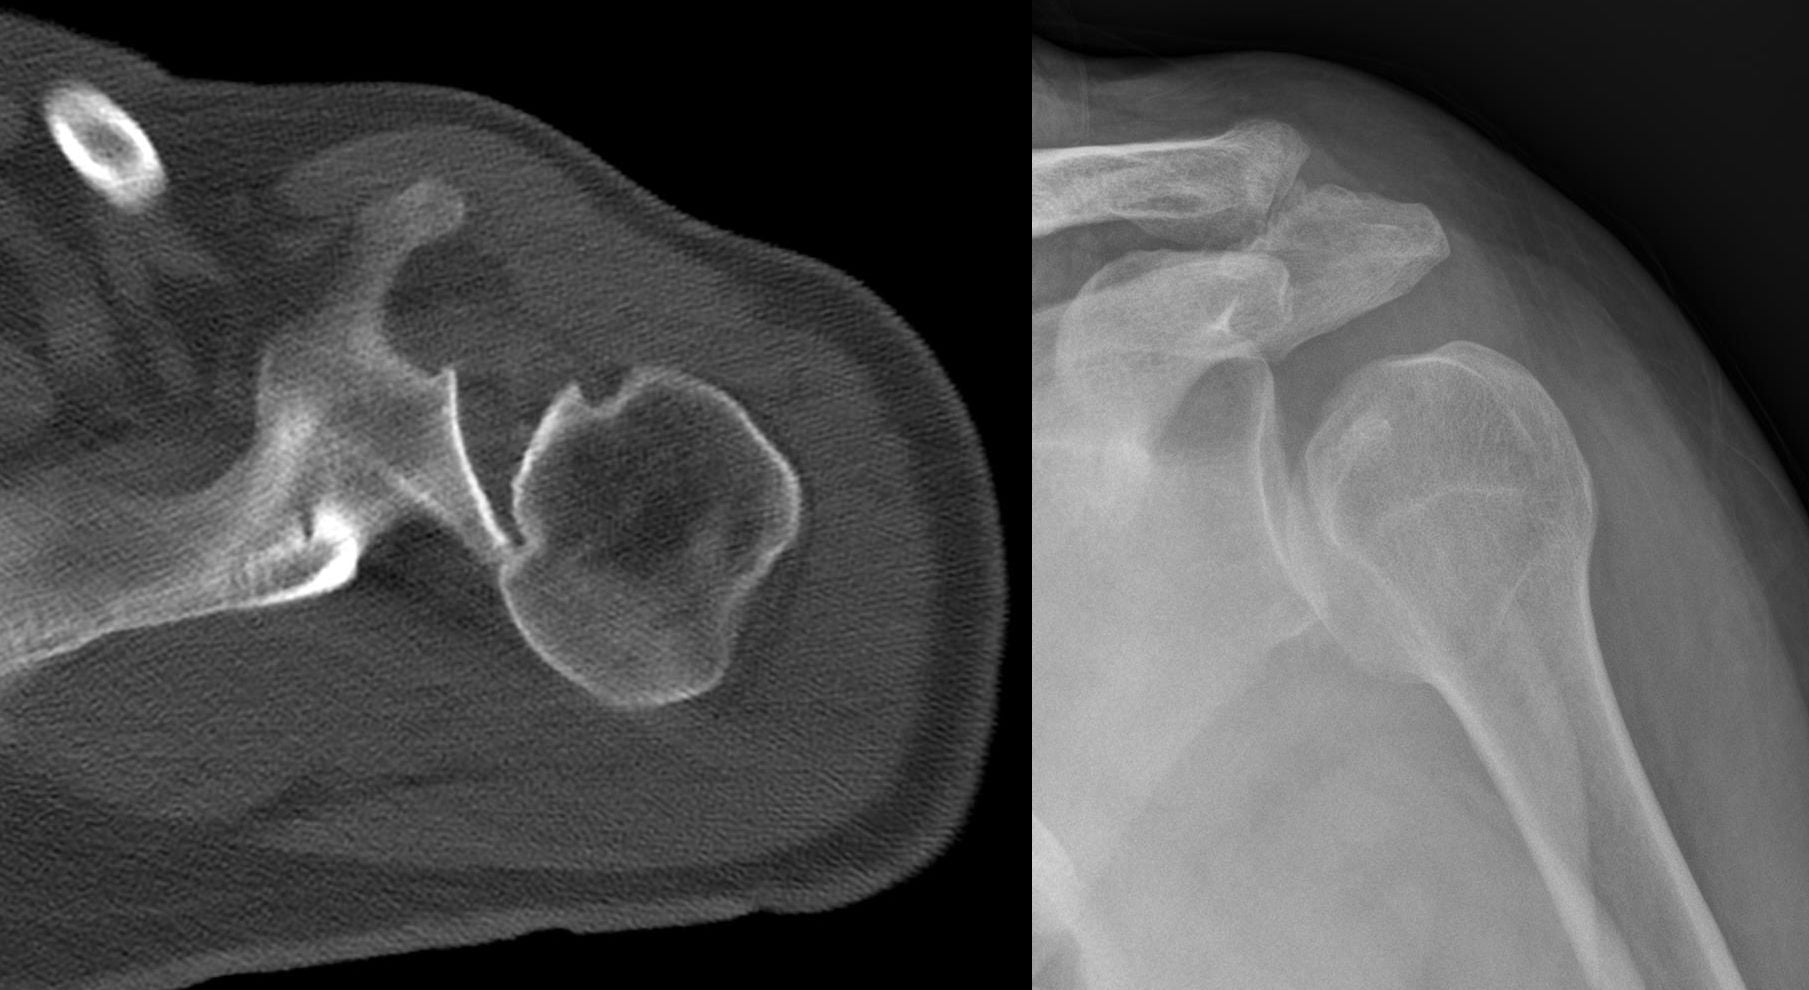
- Hill-Sachs (anterior)
- Posterolateral humeral head
- Reverse Hill-Sachs (posterior)
- Anteromedial humeral head
- Hill-Sachs (anterior)
- Anterior
- Reverse Hill-Sachs (posterior)
- Posterior
- Hill-Sachs (anterior)
- Anterior glenoid rim
- Reverse Hill-Sachs (posterior)
- Posterior glenoid rim
- Hill-Sachs (anterior)
- Traumatic abduction / external rotation
- Reverse Hill-Sachs (posterior)
- Seizure, electrocution, extreme trauma (the three E's)
- Hill-Sachs (anterior)
- Variable; apprehension in abduction / ER
- Reverse Hill-Sachs (posterior)
- Locked INTERNAL rotation and adduction
- Hill-Sachs (anterior)
- Remplissage (infraspinatus tenodesis)
- Reverse Hill-Sachs (posterior)
- McLaughlin (subscapularis transfer) or modified McLaughlin (lesser-tuberosity transfer)
Management by defect size. The reverse lesion is stratified by the proportion of the articular surface involved:
- Under roughly 25 percent: closed reduction and immobilisation (some surgeons brace in slight external rotation); a small, stable, congruent lesion can be managed non-operatively
- Roughly 25 to 50 percent: the McLaughlin procedure, transfer of the subscapularis tendon into the defect so that it fills the engaging notch and blocks re-dislocation; the modified McLaughlin (Neer/Hawkins) transfers the lesser tuberosity with its attached subscapularis into the defect, for bone-to-bone healing
- Over roughly 50 percent, or chronic/locked: disimpaction and bone grafting, segmental osteochondral allograft, partial resurfacing, or arthroplasty in the older or arthritic patient; chronic locked posterior dislocations usually require open reduction and reconstruction
A patient who cannot externally rotate the shoulder after a seizure, electric shock or fall has a posterior dislocation with a reverse Hill-Sachs until proven otherwise. The filling operation mirrors the anterior side: subscapularis into the anteromedial defect, as infraspinatus fills the posterolateral one.
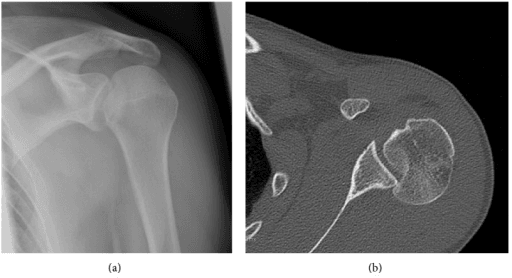
Surgical Technique
History of Shoulder Stabilisation
Bankart describes the essential lesion (labral detachment) and the technique for repair.
Radiographic description of the posterolateral humeral head impression fracture.
Description of coracoid process transfer for bone loss.
Description of open infraspinatus tenodesis for Hill-Sachs lesions.
Description of arthroscopic "Remplissage" (French for "filling").
Itoi and DiGiacomo popularise the biomechanical concept of the Glenoid Track.
The steps. The anchors go in before the Bankart repair; the knots are tied after it:
- Preparation: standard posterior and anterior portals
- Visualisation: view from the anterior portal and debride the Hill-Sachs lesion to fresh bleeding bone (decortication)
- Anchor placement: 1 or 2 suture anchors into the Hill-Sachs defect through a posterior cannula, or percutaneously
- Passage: sutures through the infraspinatus tendon and posterior capsule
- Bankart repair: the standard anterior labral repair is performed first
- Tying: the remplissage sutures are tied posteriorly, blind or visualised, in the subacromial space, which pulls the infraspinatus and capsule into the defect
Ensure good visualisation throughout.
Complications
After remplissage. The complications specific to the tenodesis:
- Stiffness: excessive loss of external rotation if the sutures are tied too tight (a tenodesis effect)
- Pain: posterior cuff pain or infraspinatus spasm (cramping) is common early after surgery
- Recurrent instability: when the glenoid bone loss was underestimated and the track calculation was wrong
- Infraspinatus strength: a minor deficit in external rotation strength, usually clinically insignificant
After Latarjet. The complications are neurological, hardware-related and graft-related:
- Musculocutaneous nerve: the most common nerve injury, about 5 percent, a traction injury during retraction of the conjoined tendon
- Axillary nerve: at risk during the subscapularis split or tenotomy
- Screw breakage or back-out: causes irritation
- Proud screws: "kissing lesions" on the humeral head, leading to rapid arthritis
- Graft problems: non-union (a fibrous union is usually stable) and osteolysis, resorption of the graft
- Recurrence: lower than after a Bankart repair, less than 5 percent, but revision is difficult (Eden-Hybinette)
Any instability surgery. Infection is less than 1 percent for arthroscopy and slightly higher for an open Latarjet. Chondrolysis was historically associated with pain pumps and thermal capsulorrhaphy (radiofrequency shrinkage), both now largely abandoned. Stiffness follows overtightening of the anterior capsule (accessory anteroinferior instability repair).
Postoperative Care and Rehabilitation
The protocol. After a Bankart repair with remplissage the standard protocol is 6 weeks in a sling, protecting both the capsulolabral repair and the tenodesis, before motion and then strength are rebuilt in stages:
- Timeframe
- 0-2 Weeks
- Goals
- Protect Repair, Control Pain
- Restrictions
- Sling 24/7 (except hygiene). No active ER.
- Exercises
- Pendulums, Wrist/Hand ROM, Scapular retraction
- Timeframe
- 2-6 Weeks
- Goals
- Gradual PROM
- Restrictions
- No ER greater than 0° (Protect Remplissage). No Active elevation.
- Exercises
- Passive supine elevation to tolerance. ER to neutral only.
- Timeframe
- 6-12 Weeks
- Goals
- Full AROM
- Restrictions
- Avoid combined Abduction/ER until 10-12 wks.
- Exercises
- Active assist pulleys. Wall walks. Theraband IR/ER (start neutral).
- Timeframe
- 3-6 Months
- Goals
- Rotator Cuff Strength
- Restrictions
- No heavy bench press or wide grip pull-downs.
- Exercises
- Periscapular strengthening. Biceps loading.
- Timeframe
- 6-9 Months
- Goals
- Functional Control
- Restrictions
- Contact sports only after passing clearance test.
- Exercises
- Plyometrics. Sport-specific drills. Tackle practice (late).
External rotation. The infraspinatus tenodesis is under tension in internal rotation, yet it is excessive external rotation that is guarded against, because that is what pulls out the anchors. Most surgeons limit external rotation to neutral for 6 weeks.
Active elevation. Avoided for 6 weeks, to protect the Bankart repair from the shear of the humeral head translating.
Outcomes and Prognosis
Bankart repair alone. For an on-track lesion the success rate is 85 to 90 percent. For an off-track lesion the recurrence rate is high, greater than 20 to 30 percent.
Adding the remplissage. For an off-track lesion, Bankart repair plus remplissage gives success rates that approach those of the Latarjet, 90 to 95 percent, with lower morbidity.
Latarjet. The gold standard for collision athletes and significant bone loss, with greater than 95 percent stability.
Guidelines, Registries & Global Practice
Global Epidemiology
- Anterior dislocation accounts for over 95 percent of glenohumeral dislocations; a Hill-Sachs lesion is present in roughly 40 to 90 percent of first-time anterior dislocations and approaches 90 to 100 percent in recurrent instability.
- Peak incidence is bimodal: young males (15 to 30 years, sport/trauma) and older adults (falls). Young age, male sex, high-demand/contact sport and bipolar bone loss are the dominant risk factors for recurrence.
- Bipolar (combined glenoid plus humeral) bone loss is the single most important predictor of failure after soft-tissue stabilisation across populations.
Society Guidance, Side by Side
- Position on Hill-Sachs / bipolar loss
- Endorses quantified bone-loss assessment (CT/3D) and bony augmentation for critical glenoid loss; supports adding a humeral-side procedure for engaging/off-track lesions.
- Position on Hill-Sachs / bipolar loss
- Stratifies instability by bone loss; recommends arthroscopic Bankart plus remplissage for off-track lesions with subcritical glenoid loss and Latarjet for critical loss or revision.
- Position on Hill-Sachs / bipolar loss
- Frames the glenoid-track concept as the operative decision tool; off-track equals augment (remplissage or glenoid bone block).
- Position on Hill-Sachs / bipolar loss
- Consensus favours track-based decision-making; remplissage increasingly preferred over Latarjet when glenoid stock is adequate, given the lower complication profile.
Registry & High-Level Evidence Notes
- There is no dedicated implant registry for instability (no implant), so evidence is driven by RCTs and cohorts rather than arthroplasty-style registries.
- Convergent message across high-level data (MacDonald RCT; Haroun meta-analysis; Schwihla long-term cohort): address the off-track lesion, and remplissage matches Latarjet stability with fewer complications when glenoid loss is subcritical.
High- vs Limited-Resource Practice Variation
- Well-resourced settings: routine preoperative 3D CT with en-face glenoid reconstruction for track quantification; arthroscopic Bankart plus remplissage is the default for off-track subcritical lesions.
- Limited-resource settings: MRI or plain CT (or even instability radiographs and intraoperative dynamic assessment) may substitute for 3D CT; open Latarjet remains a reliable, instrument-light, single-stage option where arthroscopic remplissage expertise or equipment is unavailable.
Controversies and Areas of Uncertainty
- The 83 percent figure is a population mean, not a hard threshold. The original cadaveric track was 84 plus or minus 14 percent of glenoid width (Yamamoto/Itoi 2007); the working 0.83 multiplier is a convenient approximation. Borderline (near-track) lesions sit in a grey zone where intraoperative dynamic assessment still matters.
- Does off-track status independently predict failure, or is glenoid loss the real driver? Long-term data (Schwihla 2023) show off-track lesions fail isolated Bankart repair at high rates, yet some cohorts (Park 2019) found glenoid defect size, not off-track status per se, was the more reliable predictor once selective remplissage was used. The honest position: bipolar interaction matters, and glenoid loss carries heavy weight.
- Remplissage vs Latarjet for subcritical loss. Meta-analytic data (Haroun 2020) show equivalent stability with fewer complications for remplissage, but Latarjet retains advocates for collision athletes and revision settings. There is no consensus "right answer" — the decision is patient- and surgeon-specific.
- The "subcritical" glenoid threshold is moving. Older teaching used 20 to 25 percent; contemporary work suggests instability and recurrence rise from as little as 13.5 percent in high-demand athletes, lowering the threshold for augmentation.
- Clinical engagement vs radiographic off-track are correlated but not identical. A lesion can be radiographically off-track yet not reproduce clinical locking, and vice versa; relying on one alone risks over- or under-treatment.
MCQ Practice Points
Q: What is the most common pathology associated with a clinically significant Hill-Sachs lesion? A: Anterior labroligamentous complex injury (Bankart lesion), which creates "bipolar bone loss".
Q: How does the Remplissage procedure prevent engagement? A: It converts the intra-articular defect to an extra-articular one (rendering it non-engaging) and provides a "check-rein" effect via the infraspinatus tenodesis.
Q: What is the cutoff for 'Critical' glenoid bone loss requiring a Latarjet? A: Most consensus definitions state greater than 20-25% glenoid width loss, or greater than 13.5% in high-demand contact athletes (Subcritical).
Q: What is the formula for calculating the Glenoid Track? A: Track = (0.83 x Glenoid Diameter) - Glenoid Defect Width (d).
Q: Which imaging modality is essential for quantifying bipolar bone loss? A: 3D CT reconstruction with humeral head and glenoid subtraction.
Hill-Sachs Lesion Viva
Practise clinical reasoning and management decisions out loud
“During an arthroscopy for 'recurrent instability', you see a large posterolateral defect. How do you assess if it's 'engaging'?”
“Describe how you calculate the Glenoid Track on a CT scan.”
“When would you choose a Remplissage over a Latarjet?”
“What specific X-ray views do you order for suspected Hill-Sachs?”
“Define an 'engaging' lesion clinically.”
Key Concepts
- Hill-Sachs interval (HSI) - distance from the rotator cuff insertion to the medial edge of the defect
- Glenoid track - the contact zone of the glenoid on the humeral head, 83% of glenoid width
- Off-track - HSI greater than the glenoid track, meaning the lesion engages
- On-track - HSI less than the glenoid track, meaning the lesion does not engage
- Bipolar loss - combined glenoid and humeral defects raise instability risk more than either alone
Imaging
- Stryker notch view - best plain radiograph for profiling the defect
- Internal-rotation AP - alternative view when a Stryker notch is not available
- 3D CT - the standard for quantifying bone loss and planning surgery
- MRI - assesses the soft-tissue envelope (labrum, rotator cuff)
- Axillary view - demonstrates the relationship of the humeral head to the glenoid
Management Rules
- On-track - standard arthroscopic stabilisation (Bankart repair)
- Off-track with subcritical glenoid loss (less than 20%) - Bankart repair plus remplissage
- Off-track with critical glenoid loss (greater than 20%) - Latarjet
- Revision instability - lower threshold for Latarjet
- An engaging lesion is the clinical counterpart of off-track status
Surgical Details
- Remplissage - infraspinatus tenodesis into the defect
- Anchor position - posterosuperior aspect of the defect
- Latarjet - coracoid transfer working by a triple blocking mechanism
- Sling - 6 weeks in neutral rotation to protect the tenodesis
- Return to sport - 6-9 months for contact athletes
Evidence Base
Yamamoto, Itoi et al. — The Glenoid Track (original cadaveric description)
- Nine fresh-frozen cadaveric shoulders tested in abduction, external rotation and horizontal extension.
- Glenoid contact shifted inferomedial to superolateral on the posterior humeral head, defining a contact zone (the glenoid track).
- Medial margin of the track lay 18.4 plus or minus 2.5 mm from the cuff footprint, equivalent to 84 plus or minus 14 percent of glenoid width.
- A Hill-Sachs lesion extending medial to this margin risks engagement and dislocation.
Di Giacomo, Itoi, Burkhart — On-track vs Off-track concept
- Reframed the 'engaging/non-engaging' lesion as the quantifiable 'on-track/off-track' lesion.
- An off-track lesion extends medial to the glenoid track and will engage the anterior rim; an on-track lesion stays within it.
- Provided a combined radiographic and arthroscopic method integrating bipolar (humeral plus glenoid) bone loss.
- Glenoid bone loss of 25 percent or more (inverted-pear) warrants glenoid bone grafting irrespective of the humeral lesion.
Purchase, Wolf et al. — Original arthroscopic Remplissage
- First formal description of arthroscopic Hill-Sachs 'remplissage' (French for 'to fill').
- Posterior capsule and infraspinatus tendon are tenodesed into the freshened humeral defect using suture anchors.
- Knots are kept extra-articular, converting the engaging intra-articular defect into an extra-articular one.
- The Bankart lesion is repaired after the remplissage anchors are placed.
Arciero et al. — Bipolar bone loss biomechanics
- 3D modelling of 142 instability patients with cadaveric testing of 21 shoulders.
- Medium (50th percentile) Hill-Sachs lesions reduced stability by 22, 43 and 58 percent with 2, 4 and 6 mm glenoid defects respectively.
- As little as a 2 mm glenoid defect with a medium Hill-Sachs lesion compromised an isolated Bankart repair.
- Combined glenoid plus humeral defects act additively (approximately 8 to 15 percent glenoid loss is the relevant threshold).
Evidence Base — Clinical Outcomes
MacDonald et al. — Bankart with vs without Remplissage (RCT)
- 108 patients randomized to arthroscopic Bankart with or without infraspinatus remplissage (Hill-Sachs lesion, glenoid loss under 15 percent).
- Recurrent instability 18 percent (9 of 50) without remplissage vs 4 percent (2 of 52) with remplissage (P = .027).
- Revision surgery: 6 in the no-remplissage group vs 0 with remplissage (P = .029).
- No clinically meaningful difference in patient-reported outcomes; higher re-dislocation risk if lesion 20 mm or more wide or 15 percent or more of humeral head diameter.
Haroun et al. — Remplissage vs Latarjet (systematic review / meta-analysis)
- 4 comparative studies, 379 patients (194 Bankart-remplissage, 185 Latarjet) with engaging lesions and subcritical glenoid loss.
- Comparable recurrent instability (RR 0.72, 95 percent CI 0.37 to 1.41).
- Latarjet carried roughly 7-fold higher overall complication risk (RR 7.37, 95 percent CI 2 to 27).
- No significant difference in Rowe score, VAS pain, or external/internal rotation range of motion.
Schwihla, Wieser et al. — Long-term validation of the track concept
- 163 shoulders after isolated arthroscopic Bankart repair, mean follow-up 124 months.
- Recurrent instability 74 percent in off-track vs 27 percent in on-track lesions (P less than .001).
- Revision for instability 48 percent off-track vs 13 percent on-track (P less than .001).
- Off-track status was the dominant long-term predictor of failure of soft-tissue-only repair.