From Standard Radiographs to Advanced MRI Assessment
- Minimum shoulder trauma series: AP in internal rotation + true axillary lateral. The axillary lateral confirms or excludes dislocation.
- Systematic radiograph reading: ABCS -- Alignment, Bone density, Cartilage spaces, Soft tissues.
- MRI is the gold standard for rotator cuff assessment. Ultrasound is a valid alternative with equivalent sensitivity in experienced hands.
- MR arthrography (direct) is the most accurate test for labral pathology and partial-thickness cuff tears, outperforming non-contrast MRI; joint distension is key to demonstrating capsulolabral detachment.
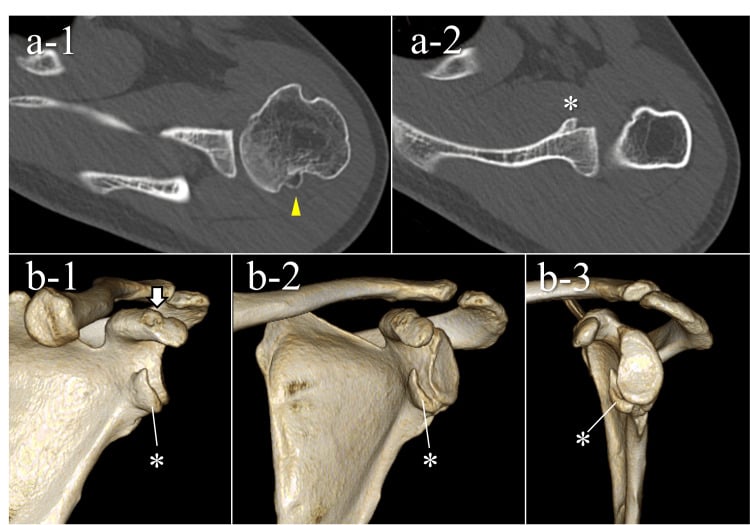
- CT with three-dimensional reconstruction is essential for glenoid bone loss quantification. Loss beyond roughly 20-25% favours a bony procedure (Latarjet), but the threshold is genuinely contested across the range 13.5-25%, and the field is moving towards a bipolar (glenoid-track) assessment rather than a single glenoid number.
- “The Hill-Sachs lesion is best seen on AP internal rotation radiograph. The Bankart lesion (bony) is best seen on Bernageau profile view or CT.
- “Acromion morphology (Bigliani classification): Type I flat, Type II curved, Type III hooked -- Type III associated with impingement.
- “Critical shoulder angle: the NORMAL mean is 33 degrees, so the thresholds sit only 2-3 degrees either side of it - over 35 leans towards cuff tear (84% of such patients were in the cuff-tear group), under 30 towards OA (93% were in the OA group). A measurement error of two degrees moves a patient across a threshold, which is why it needs a true Grashey AP.
- “Rotator cuff tear grading on MRI: high signal on T2 within tendon = tear. Full-thickness: extends from articular to bursal surface.
- “The crescent sign on MRI = high T2 signal at the articular margin of the supraspinatus insertion -- suggests partial articular-surface tear.
Overview
The shoulder is the most commonly imaged upper limb joint in orthopaedic practice, and its pathology runs from acute trauma (dislocation, fracture) to the chronic problems of rotator cuff disease, instability and arthritis. The examination asks the same things of every candidate: describe the standard radiographic views and what each shows, read a shoulder radiograph systematically, choose between MRI, MR arthrography, CT and ultrasound for a given question, and interpret the key MRI findings of cuff tears, labral tears and acromial morphology.
Radiographs first. The workup begins with plain radiographs in virtually all presentations. Advanced imaging (MRI, ultrasound, CT, arthrography) is then selected for the specific clinical question, and knowing which modality best answers which question is the skill being tested.
The two classic traps. Not requesting an axillary lateral in trauma, and so missing a dislocation; and relying on non-contrast MRI to assess the labrum.
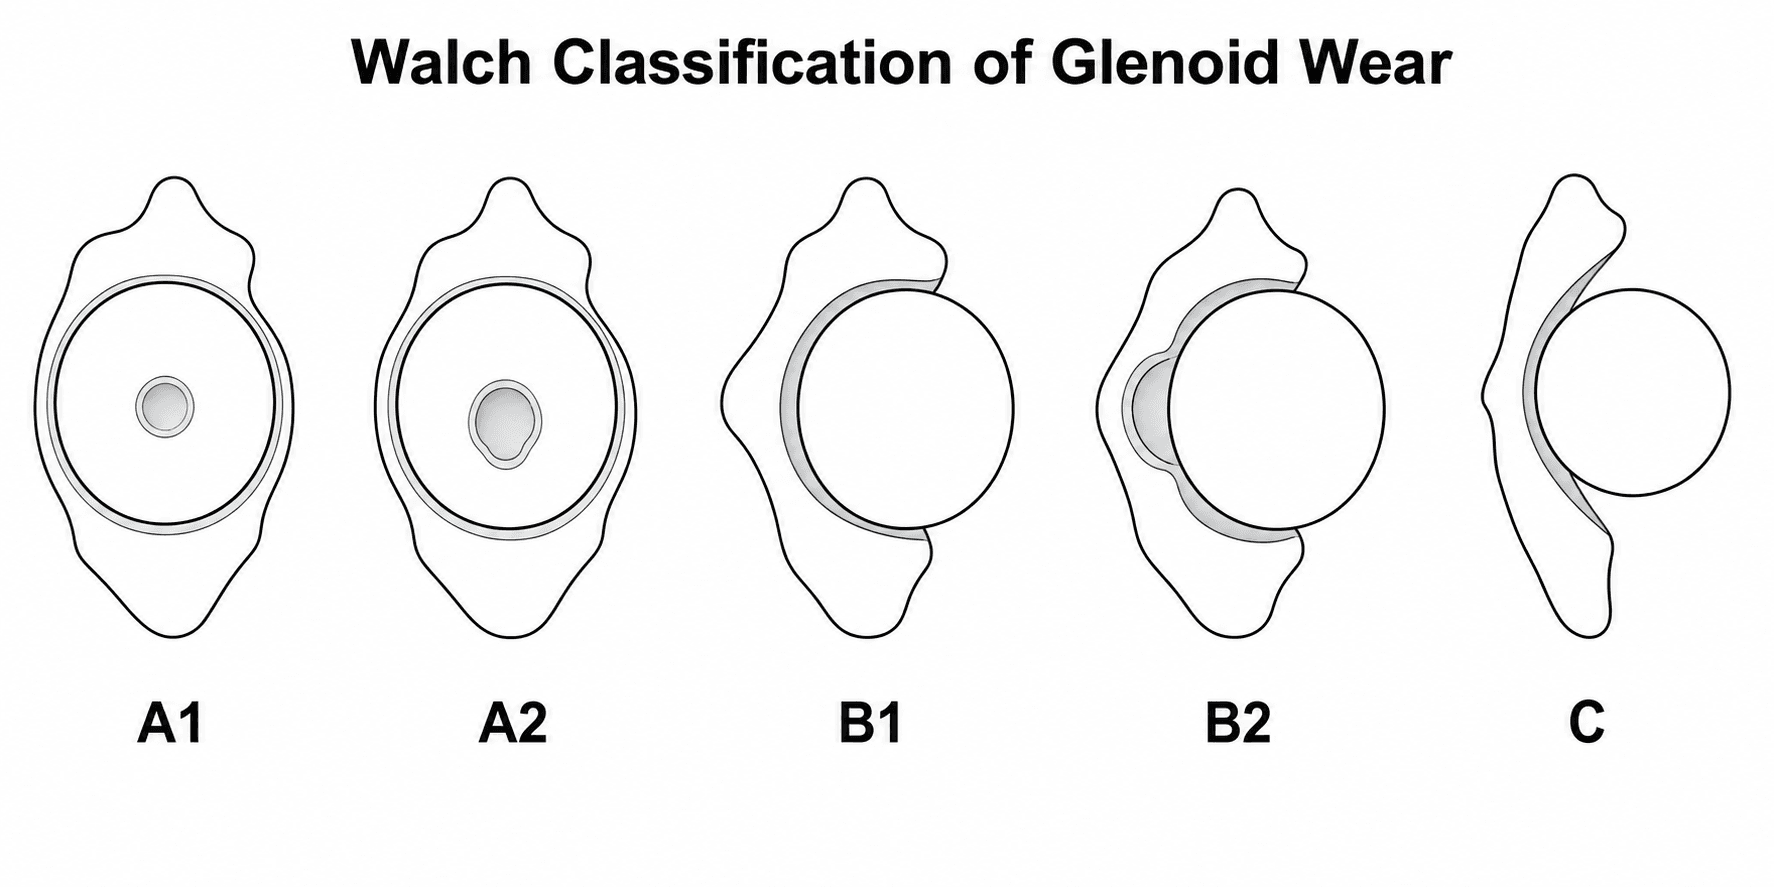
Walch Classification of Glenoid Wear
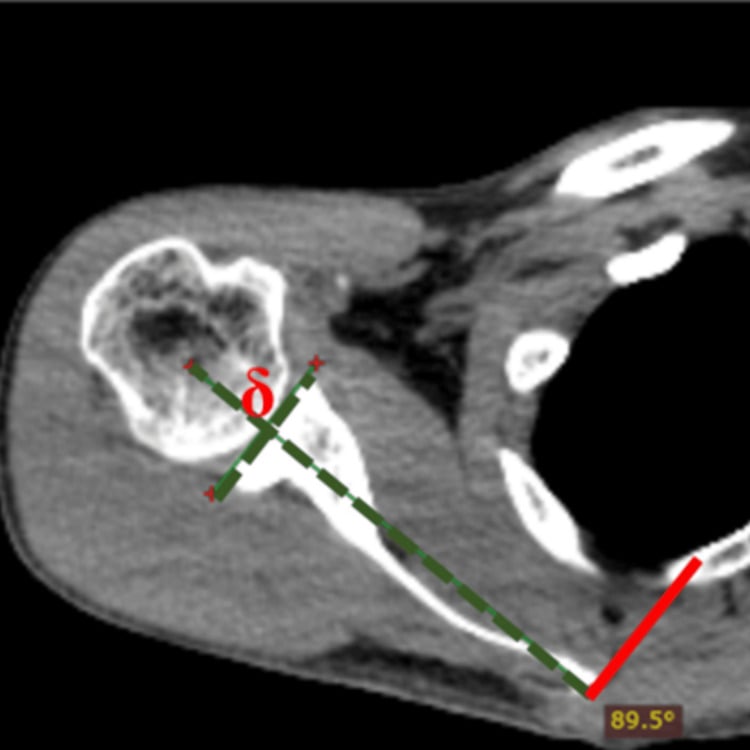
Walch grades the glenoid wear pattern of primary glenohumeral osteoarthritis on the axial CT (or MRI). It matters because glenohumeral arthritis does not wear the socket evenly: the humeral head tends to drift posteriorly, and a socket that has been eroded from behind cannot hold an anatomic component in the position the surgeon intends. The classification is therefore less a description of severity than a prediction of where an implant will fail.
- Glenoid morphology
- Centred humeral head, minor central erosion
- Implication
- Symmetric wear; well suited to anatomic total shoulder arthroplasty
- Glenoid morphology
- Centred head, major central erosion (head cups into the glenoid)
- Implication
- Symmetric but significant medial wear
- Glenoid morphology
- Posterior subluxation with posterior joint-space narrowing/sclerosis, no bone erosion
- Implication
- Asymmetric, early posterior wear
- Glenoid morphology
- Biconcave glenoid — posterior erosion creates a neoglenoid, with retroversion
- Implication
- Posterior wear and instability complicate anatomic arthroplasty
- Glenoid morphology
- Monoconcave but markedly retroverted / posteriorly worn (modified Walch)
- Implication
- Severe retroversion without a frank biconcavity
- Glenoid morphology
- Dysplastic glenoid, retroversion over 25 degrees (congenital)
- Implication
- High fixed retroversion
- Glenoid morphology
- Glenoid anteversion or anterior humeral subluxation (modified Walch)
- Implication
- Anterior wear pattern
Posteriorly worn, retroverted glenoids (B2, B3 and dysplastic C) make anatomic total shoulder arthroplasty prone to component malposition, persistent posterior instability and eccentric 'rocking-horse' glenoid loosening. These patterns push toward an augmented glenoid component, posterior bone grafting, or a reverse shoulder arthroplasty — which is exactly why the Walch type is read off the pre-operative CT.
Choosing the Right Investigation
The hierarchy. MRI is the gold standard for the rotator cuff, and ultrasound is a valid alternative with equivalent sensitivity in experienced hands. Direct MR arthrography is the most accurate test for labral pathology and partial-thickness cuff tears, outperforming non-contrast MRI; joint distension is key to demonstrating capsulolabral detachment. CT with three-dimensional reconstruction is essential for glenoid bone loss quantification.
- First-Line Imaging
- AP + axillary lateral radiographs (MINIMUM 2 views)
- Advanced Imaging
- CT with three-dimensional reconstruction for complex fractures (proximal humerus, glenoid). MRI for associated soft tissue injury after fracture management
- First-Line Imaging
- AP radiograph (acromiohumeral distance, calcification)
- Advanced Imaging
- MRI (gold standard) or USS by experienced operator. MRA if partial tear suspected
- First-Line Imaging
- AP + axillary lateral (Hill-Sachs, bony Bankart)
- Advanced Imaging
- MR arthrography (labral tears, capsular pathology) + CT three-dimensional reconstruction (glenoid bone loss quantification)
- First-Line Imaging
- Zanca view (10-15 degree cephalic tilt AP)
- Advanced Imaging
- MRI for distal clavicle oedema (osteolysis), ligament assessment. Weighted views for instability (controversial)
- First-Line Imaging
- AP radiograph (demonstrates calcification)
- Advanced Imaging
- Ultrasound (confirms location, guides barbotage/aspiration). No MRI needed for isolated calcific tendinitis
- First-Line Imaging
- True AP (Grashey) + axillary lateral
- Advanced Imaging
- CT for glenoid wear pattern (Walch classification) pre-arthroplasty planning. MRI for associated cuff status
Radiographic Assessment
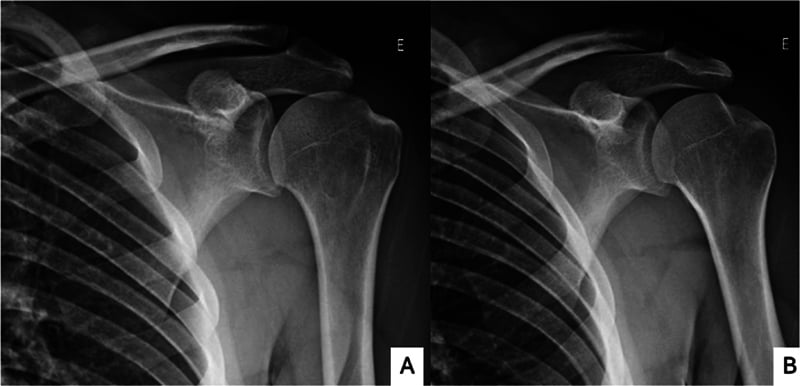
AP in internal rotation. The arm is internally rotated, so the greater tuberosity rotates round to overlap the humeral head. It is the standard screening view and shows the Hill-Sachs lesion, the glenohumeral joint space and the acromial morphology.
AP in external rotation. The arm is externally rotated, which brings the greater tuberosity laterally into profile. It is the best view for tuberosity fractures, and it also shows the bicipital groove and the humeral head articular surface.
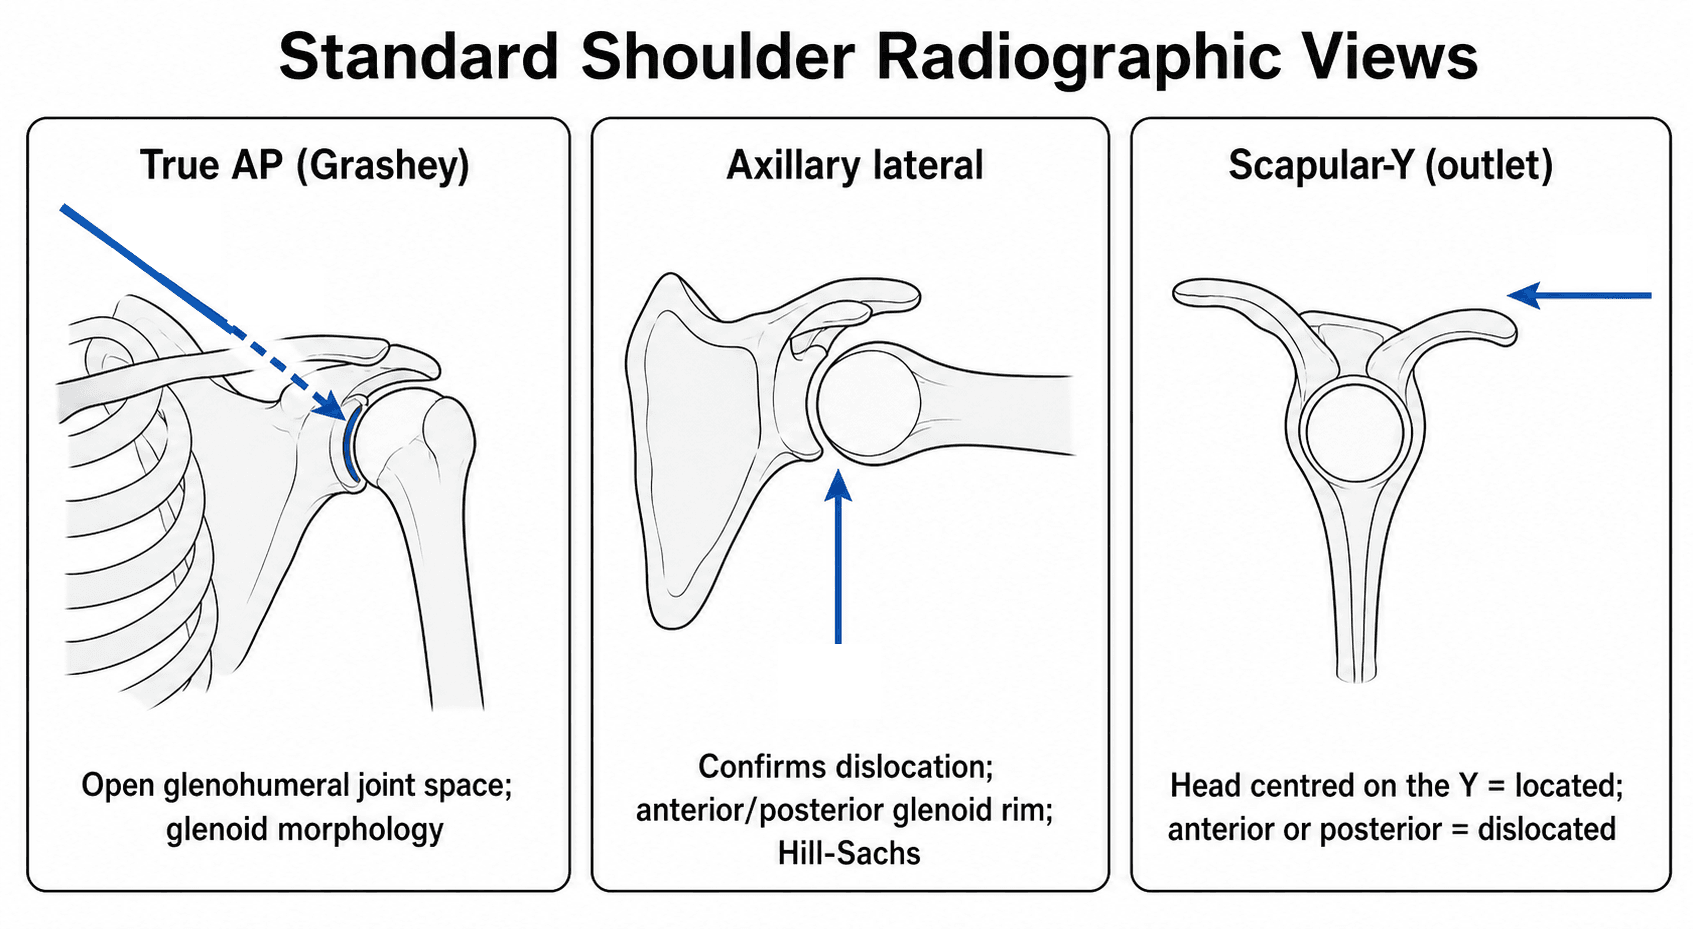
True AP (Grashey view). The beam is angled 40 degrees to align with the plane of the glenohumeral joint, which removes the overlap between humeral head and glenoid. It is the most accurate view for joint space width and glenoid morphology.
Axillary lateral. Essential in trauma, and it must be obtained in every trauma case. The patient is supine or seated with the arm abducted and the beam passes through the axilla from inferior to superior. It is the only reliable view to confirm an anterior or posterior dislocation, and it also shows the anterior and posterior glenoid rim (bony Bankart), the Hill-Sachs lesion and the coracoid process.
West Point view. A modified axillary view taken with the patient prone and the arm abducted, which profiles the anterior glenoid rim and shows a bony Bankart lesion.
Y-view (scapular lateral). The beam is tangential to the scapular spine and the humeral head should sit centred over the glenoid Y: a head anterior to the Y is an anterior dislocation, a head posterior to it a posterior dislocation. It doubles as the supraspinatus outlet view, on which acromial morphology is assessed.
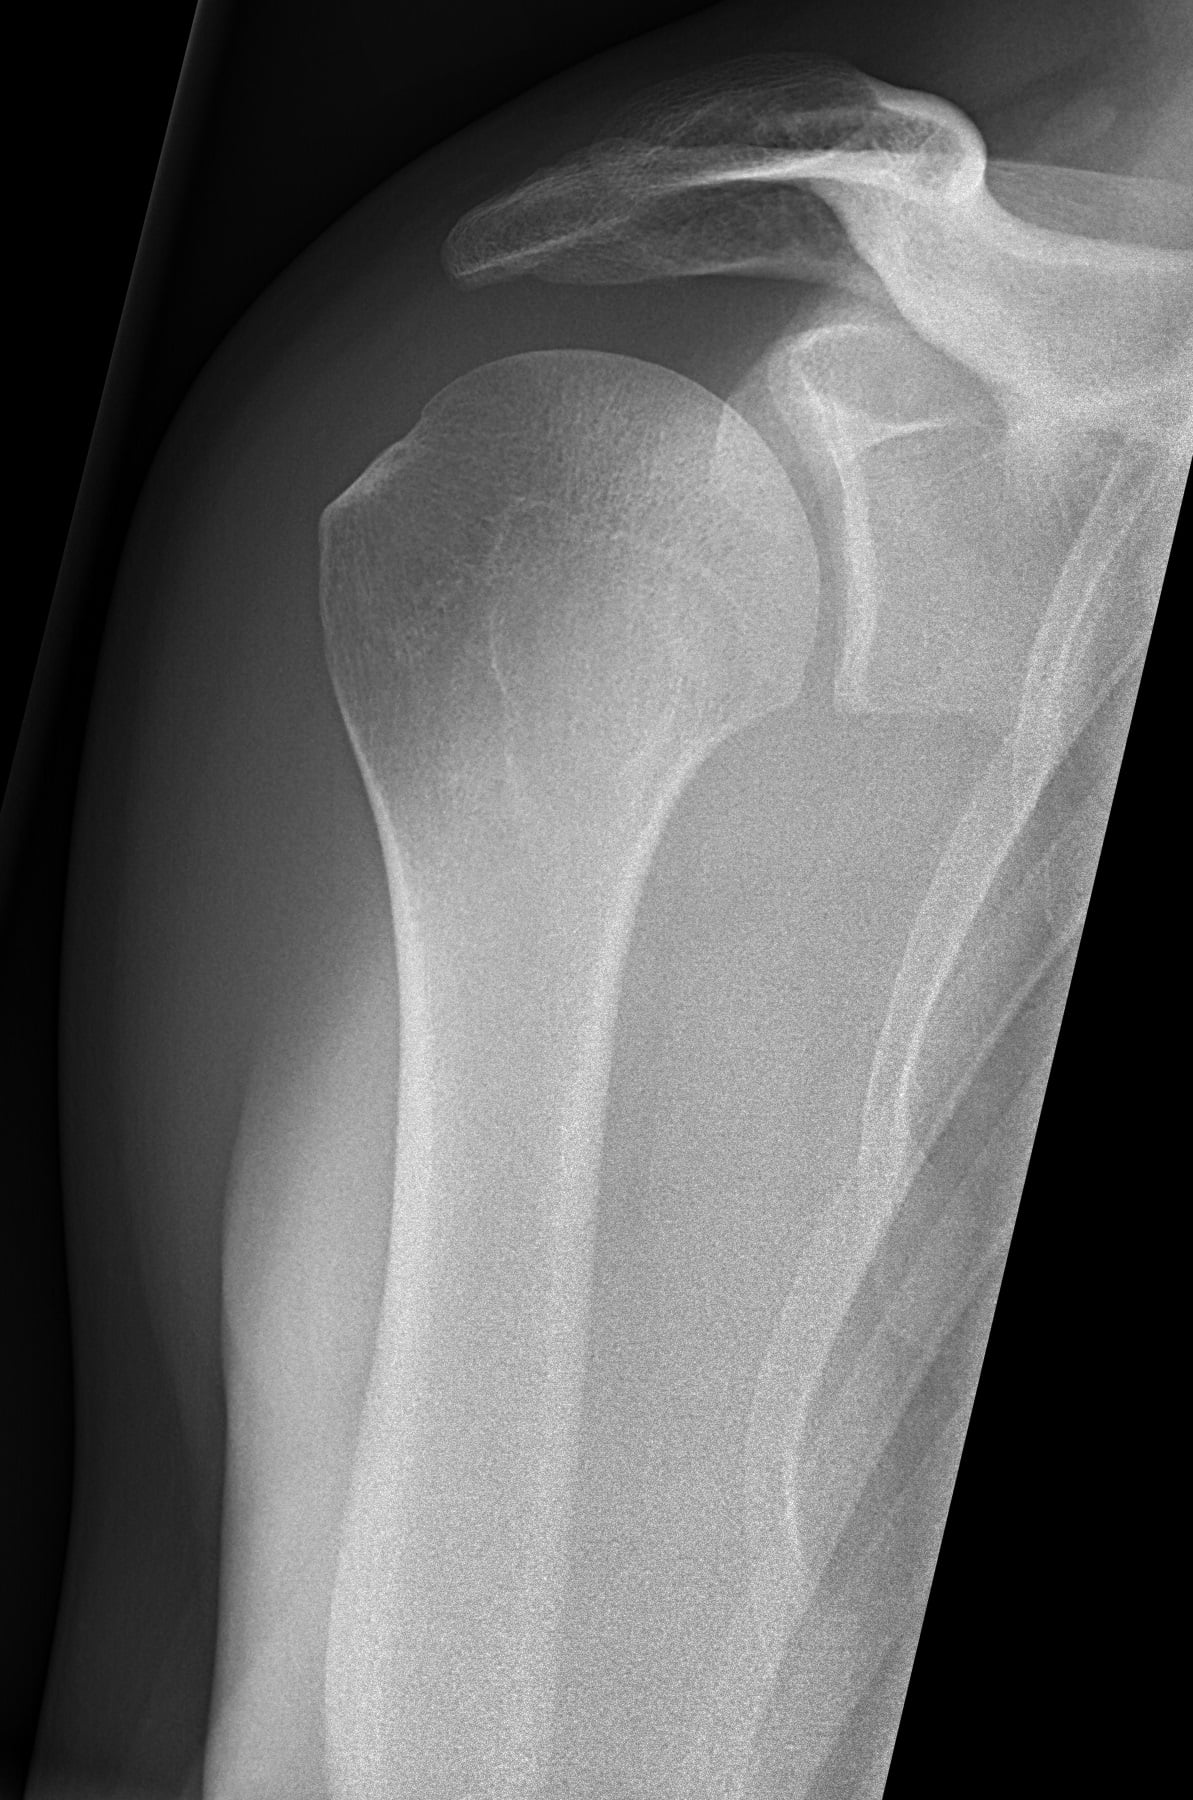
Acromiohumeral distance. Measured on the AP view from the inferior surface of the acromion to the superior surface of the humeral head; normal is more than 7mm. Under 7mm suggests superior migration of the head from a large or massive rotator cuff tear, but it also narrows in cuff-tear arthropathy and inflammatory arthritis, and the measurement shifts with arm rotation and beam angle. The acromioclavicular joint space is normally less than 8mm.
Critical shoulder angle. Glenoid inclination plus lateral acromial extension, measured on a true (Grashey) AP. The normal mean is 33 degrees, and the thresholds sit only 2-3 degrees either side of it: over 35 leans towards cuff tear (84% of such patients were in the cuff-tear group), under 30 towards OA (93% were in the OA group). A measurement error of two degrees moves a patient across a threshold, which is why the view has to be a true AP.
ABCSSystematic Shoulder Radiograph Reading
Hook:Alignment, Bones, Cartilage spaces, Soft tissues: the same order on every film.
MRI Assessment
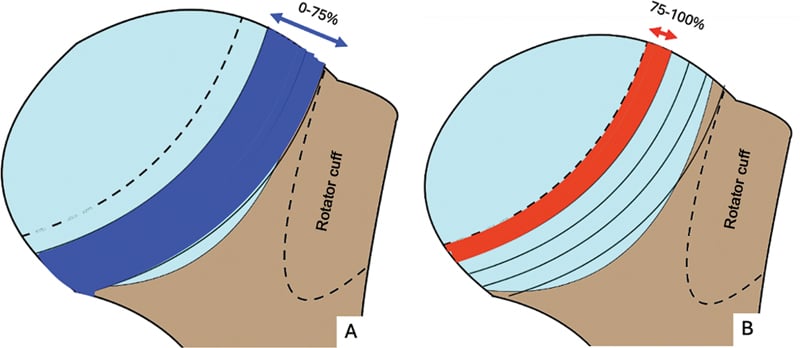
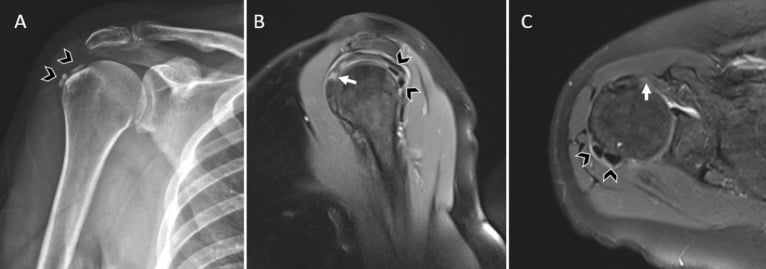
The cuff. On T2 fat-saturated sequences, high signal within the tendon is a tear. A full-thickness tear extends from the articular to the bursal surface. The crescent sign, high T2 signal at the articular margin of the supraspinatus insertion, suggests a partial articular-surface tear, and partial articular-surface tears are best detected on MR arthrography. Measure the gap, the retraction and the fatty infiltration of the muscle (Goutallier classification).
The rotator interval and biceps. Assess the biceps tendon in its groove and the integrity of subscapularis. A subluxed biceps indicates a subscapularis tear.
Impingement. Acromial morphology by the Bigliani classification (Type I flat, Type II curved, Type III hooked, the hooked acromion being the type associated with impingement), an os acromiale, acromioclavicular joint hypertrophy causing outlet stenosis, and subacromial bursitis.
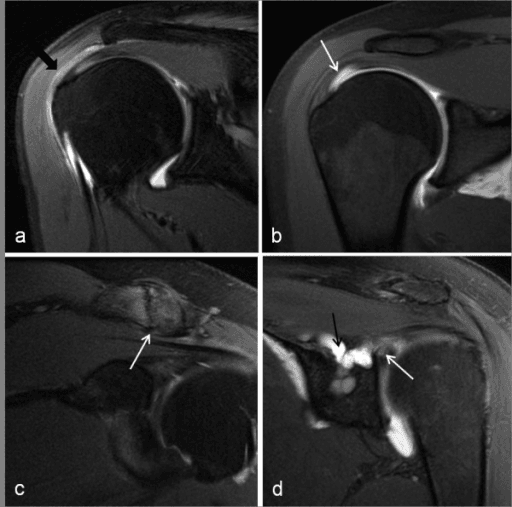
Stability. Labral tears (Bankart, SLAP, HAGL), the integrity of the glenohumeral ligaments and glenoid bone deficiency; the labral lesions are taken one by one in the labral section below.
Tuberosity and bone marrow. Greater tuberosity fractures, the Hill-Sachs defect, bone marrow oedema patterns and avascular necrosis of the humeral head.
Differential Diagnosis on Imaging
Several shoulder conditions overlap clinically; imaging is what separates them. The table gives the discriminating imaging features the examiner expects.
- Key imaging finding
- Fluid-signal gap through the tendon; reduced acromiohumeral distance if massive
- Best modality / pitfall
- MRI or ultrasound; pitfall -- many tears are asymptomatic in older patients
- Key imaging finding
- Dense calcification over the supraspinatus on radiograph
- Best modality / pitfall
- Radiograph plus ultrasound; pitfall -- resorptive (fluffy) phase is most painful
- Key imaging finding
- Often normal radiograph; MR arthrography may show reduced axillary recess volume and rotator-interval/coracohumeral ligament thickening
- Best modality / pitfall
- Clinical diagnosis; imaging mainly excludes mimics
- Key imaging finding
- Anteroinferior labral and bony glenoid defect, posterolateral Hill-Sachs
- Best modality / pitfall
- MR arthrography plus CT for bone loss; pitfall -- normal sublabral variants
- Key imaging finding
- Lightbulb sign on AP, head behind the scapular Y
- Best modality / pitfall
- Axillary lateral is decisive; pitfall -- AP can look near-normal
- Key imaging finding
- Joint-space loss, inferior osteophyte (goat's beard), posterior glenoid wear
- Best modality / pitfall
- Grashey AP plus axillary; CT (Walch) for arthroplasty planning
- Key imaging finding
- Sublabral foramen, Buford complex (cord-like MGHL, absent anterosuperior labrum)
- Best modality / pitfall
- MR arthrography; pitfall -- do NOT call these SLAP/Bankart tears
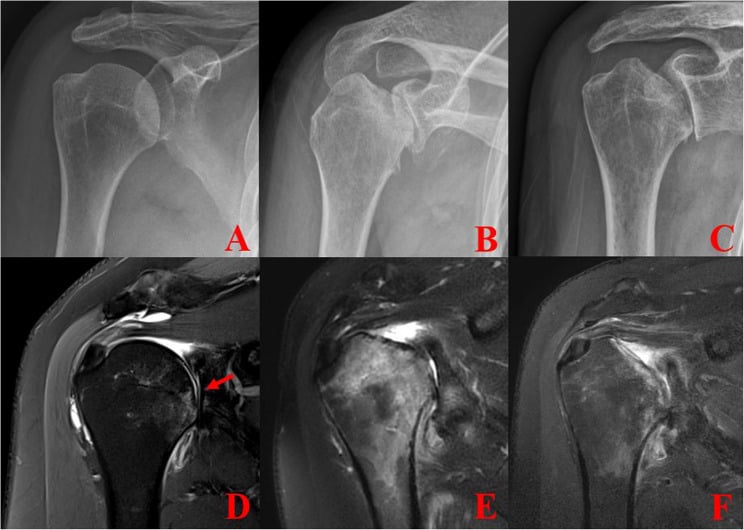
Labral Lesions: SLAP and the Bankart Variants
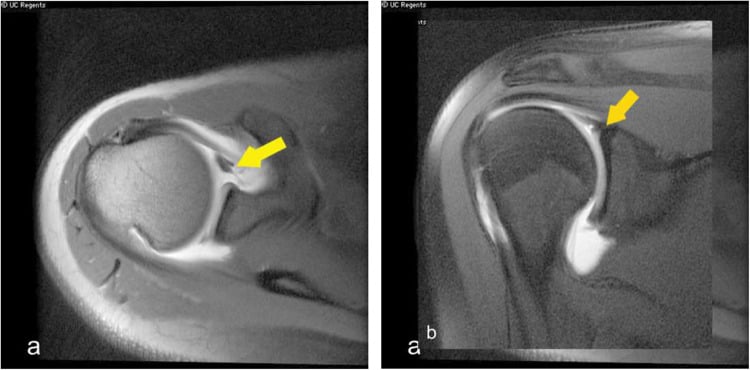
"Labral tear" is not a diagnosis; it is a category containing a dozen lesions that behave differently and are repaired differently. Naming the one in front of you precisely on MR arthrography is what separates a report that guides an operation from one that only confirms there is a problem. The superior labrum is graded by the Snyder SLAP system; the anteroinferior labrum has its own family of named variants, distinguished largely by what happened to the periosteum - whether it tore, stayed intact, or let the labrum heal in the wrong place.
- Lesion
- Fraying/degeneration of the superior labrum, biceps anchor intact
- Note
- Often degenerative; usually debrided
- Lesion
- Detachment of the superior labrum AND biceps anchor from the glenoid
- Note
- The commonest surgical SLAP; anterior, posterior and combined subtypes
- Lesion
- Bucket-handle tear of the superior labrum with an INTACT biceps anchor
- Note
- Displaced fragment may cause mechanical symptoms
- Lesion
- Bucket-handle tear extending INTO the biceps tendon
- Note
- Biceps involvement changes the repair/tenodesis decision
- What it is
- Anteroinferior labrum and IGHL avulsed from the glenoid with periosteal disruption
- Imaging clue
- Contrast tracks under the detached labrum on MR arthrography
- What it is
- Bankart with an anteroinferior glenoid rim fracture
- Imaging clue
- CT for bone-loss quantification. Bone loss costs motion as well as stability - in the cadaveric work behind the threshold, external rotation fell by about 25 degrees for every centimetre of defect after repair
- What it is
- Labrum with INTACT periosteum strips and heals MEDIALISED on the glenoid neck
- Imaging clue
- Medially displaced, rounded labral mass (chronic)
- What it is
- Labrum avulsed but periosteum intact and the labrum non-displaced
- Imaging clue
- Easily missed; the ABER MR-arthrography view lifts it off the glenoid
- What it is
- Anteroinferior labral tear PLUS an articular cartilage injury
- Imaging clue
- Usually stable; look for the cartilage defect
- What it is
- Inferior glenohumeral ligament avulsed from the HUMERAL side (not the glenoid)
- Imaging clue
- 'J sign' on coronal MR arthrography; bony variant is BHAGL
The miss and the over-call. The Perthes lesion is the classic miss because the labrum sits in a near-normal position; the ABER (abduction-external rotation) view tensions the IGHL and reveals contrast under the labrum. The opposite error is calling a normal variant a tear: the sublabral foramen, present in 12-18%, and the Buford complex (a cord-like middle glenohumeral ligament with an absent anterosuperior labrum) must not be reported as a Bankart or SLAP tear.
Guidelines, Registries & Global Practice
Across health systems, shoulder imaging follows the same evidence-based logic: plain radiographs first for nearly all presentations, then advanced imaging targeted to the specific clinical question. What varies between regions is which advanced modality is reached for first, driven by scanner access, sonographer expertise and cost.
Global epidemiology of the questions imaging must answer:
- Rotator cuff disease is the commonest cause of shoulder pain in adults; full-thickness cuff tear prevalence rises steeply with age, exceeding 50% in those over 80, and a large share are asymptomatic -- so imaging findings must always be interpreted against the clinical picture.
- Anterior glenohumeral dislocation is the most common large-joint dislocation; recurrence is highest in young, active patients, which is the group in whom glenoid bone loss and Hill-Sachs assessment most change management.
- Calcific tendinitis affects roughly 3-10% of adults, frequently incidental on radiographs.
- Cuff / impingement
- Radiographs first; MRI or ultrasound both acceptable for cuff tears, with ultrasound endorsed as cost-effective in experienced hands
- Instability / trauma
- Axillary or comparable orthogonal view mandatory; CT for glenoid bone loss in recurrent instability
- Cuff / impingement
- Plain films plus ultrasound as efficient first-line cuff assessment; MRI when ultrasound equivocal or surgery planned
- Instability / trauma
- Two orthogonal radiographs in every dislocation; cross-sectional imaging before stabilisation surgery
- Cuff / impingement
- Imaging focused on fracture characterisation; CT for displaced proximal humeral fractures and articular involvement
- Instability / trauma
- CT with 3D reconstruction for glenoid rim fractures and surgical planning
- Cuff / impingement
- ESSR consensus supports ultrasound as a first-line cuff tool and MR arthrography for partial tears
- Instability / trauma
- Direct MR arthrography favoured for labroligamentous assessment in instability
- Cuff / impingement
- Radiographs initial; MRI without contrast usually most appropriate for cuff/impingement
- Instability / trauma
- MR arthrography most appropriate for instability/labrum; CT for bone loss
Shoulder arthroplasty registries (UK NJR shoulder data, AOANJRR Australia, the Swedish and other national shoulder registries) reinforce why pre-operative imaging matters -- glenoid morphology (Walch classification on CT) and cuff/teres minor status (Goutallier on MRI) predict implant choice between anatomic and reverse arthroplasty and influence revision risk. These registries do not dictate which scan to order but make accurate pre-operative characterisation a quality issue.
Where MRI and skilled musculoskeletal sonography are scarce, radiographs (including dedicated instability views such as the West Point and Bernageau profile) and CT arthrography carry more diagnostic weight, and ultrasound -- being inexpensive, portable and radiation-free -- becomes the dominant cuff tool. In well-resourced centres, non-contrast MRI and direct MR arthrography are the defaults. The exam-correct principle is universal: choose the cheapest test that reliably answers the specific question, and never omit an orthogonal (axillary-equivalent) view in trauma.
Controversies & Areas of Uncertainty
Where bone loss demands a bone block. The glenoid bone-loss threshold for adding a Latarjet to (or instead of) a Bankart repair is debated. Biomechanical and clinical work place it anywhere from about 13.5% to 25%, and the field is moving toward a combined glenoid-plus-Hill-Sachs (bipolar, glenoid-track) assessment rather than a single glenoid number. Subcritical loss (around 13.5-20%) increasingly prompts bony augmentation in high-demand patients.
Acromial morphology, cause or consequence. Whether the Bigliani Type III hook is a developmental driver of impingement or an acquired traction enthesophyte remains unresolved, and the critical shoulder angle has partly supplanted acromial-shape grading as the cuff-risk parameter. Inter-observer reliability for both is only moderate.
Incidental findings and symptoms. Because asymptomatic cuff tears, labral variants and calcium deposits are common, advanced imaging risks over-treatment. The recurring controversy is how much weight to give an imaging abnormality that may not explain the patient's pain.
MRI or ultrasound first. With comparable accuracy for cuff tears, the first-line choice is as much about local resources and sonographer skill as about evidence. Ultrasound's dynamic capability and point-of-care convenience must be weighed against MRI's comprehensive single-study assessment.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 60-year-old woman presents with a 6-month history of progressive shoulder pain and weakness in external rotation. Her AP radiograph shows an acromiohumeral distance of 5mm.”
“A 22-year-old soldier has had three anterior shoulder dislocations. His MRI shows a Bankart lesion. An examiner asks what additional imaging you need for surgical planning.”
“An examiner asks you to compare MRI, ultrasound, and MR arthrography for the assessment of rotator cuff pathology.”
Radiographic Views
- Trauma MINIMUM: AP + axillary lateral (confirms dislocation)
- Hill-Sachs: best on AP internal rotation
- Bony Bankart: best on axillary lateral or West Point view
- True AP (Grashey): best for joint space assessment
- AHD less than 7mm = massive cuff tear with superior migration
Posterior Dislocation — The Classic Miss
- Lightbulb sign: greater tuberosity rotated out of profile, head becomes a symmetric oval
- Rim sign: anterior glenoid rim to humeral head margin over about 6mm
- Trough line: vertical dense line in the MEDIAL head — the reverse Hill-Sachs impaction
- Absent half-moon: normal head/glenoid overlap crescent is lost
- All four follow from fixed internal rotation — but the AXILLARY LATERAL is decisive; use a Velpeau axillary if the arm cannot abduct
ABCS Systematic Reading
- Alignment: GH congruence, AC joint alignment, dislocation
- Bones: cortical outline (fractures), tuberosities, Hill-Sachs
- Cartilage spaces: GH joint space, AHD, AC joint
- Soft tissues: calcification, swelling, periosteal reaction
Advanced Imaging Selection
- MRI: gold standard for cuff assessment, comprehensive evaluation
- USS: equivalent to MRI for full-thickness tears, dynamic, cheaper
- MRA: most accurate for labral tears and partial-thickness cuff tears
- CT three-dimensional: glenoid bone loss quantification (more than 20-25% = Latarjet)
- CT arthrography: MRI alternative + bone detail
Key MRI Measurements
- Goutallier fatty infiltration: 0-4 (3-4 = irreversible, poor prognosis)
- Patte retraction: Stage 1 (at footprint), 2 (humeral head), 3 (glenoid)
- Critical shoulder angle: normal mean 33 degrees; over 35 leans cuff tear, under 30 leans OA — only 2-3 degrees either side of normal, so measurement error matters
- Bigliani acromion: Type I flat, II curved, III hooked (impingement risk)
Evidence Base
MRI vs Ultrasound vs MR Arthrography for Rotator Cuff Tears
- Pooled analysis of 65 studies (surgical reference standard) comparing MRI, MR arthrography and ultrasound for rotator cuff tears.
- MR arthrography was significantly more sensitive AND specific than either MRI or ultrasound for both full- and partial-thickness tears.
- No significant difference between MRI and ultrasound for either tear type. Area under the ROC curve: MRA 0.935, ultrasound 0.889, MRI 0.878.
Goutallier Classification for Fatty Muscle Degeneration
- Preoperative CT graded fatty muscle degeneration in five stages (0-4) in 63 patients before rotator cuff repair, with postoperative review of 57.
- Infraspinatus fatty degeneration worsened with time and, once present, never regressed after repair; it correlated with impaired pre- and post-operative external rotation.
- Infraspinatus degeneration had a strongly negative influence on supraspinatus repair outcome -- the authors concluded it is preferable to operate on wide tears before irreversible muscular damage occurs.
MR Arthrography vs Conventional MR and CT Arthrography
- 100 consecutive post-operative shoulders had conventional MR and MR arthrography on the same patients, all confirmed at arthroscopy.
- MR arthrography detected additional pathology missed by conventional MR -- 12 extra SLAP tears, several anterior/posterior labral tears and 9 extra full-thickness supraspinatus tears.
- In 22 patients with metallic artefact, CT arthrography revealed labral and cuff lesions not visible on MR.
The practical reading is that the choice between MRI and ultrasound is not an accuracy decision — the pooled areas under the ROC curve are 0.878 and 0.889, which is a distinction without a difference — so it should be made on availability, cost, whether dynamic assessment is wanted, and whether a sonographer with genuine musculoskeletal experience is available. Arthrography is where the accuracy gain actually lives (0.935), and it earns its invasiveness only when a partial tear, the labrum, or a post-operative shoulder is the question. Goutallier supplies the reason any of this is urgent: fatty degeneration of the infraspinatus, once established, did not regress after repair, so the imaging is not only diagnosing the tear but timing the operation.