Zone 2 | Metadiaphyseal Junction | Watershed Zone | High Nonunion Risk | Athletes Need Surgery
- Zone 2 location: metadiaphyseal junction extending INTO 4-5 intermetatarsal articulation
- Watershed blood supply - nutrient artery meets periosteal supply = poor healing
- 25-50% nonunion rate with conservative treatment (non-athletes may accept this)
- Athletes require surgery - faster healing, lower nonunion, earlier return to sport
- Screw technique critical - entry at the tip of the tuberosity, engage the far cortex, and use the largest screw the canal accepts (5.5mm or more is advised in elite athletes; a screw too wide for the canal wedges and straightens the curved metatarsal)
- “Jones fracture vs avulsion: Jones extends INTO 4-5 intermetatarsal joint, avulsion proximal to it
- “Watershed zone = poor blood supply = high nonunion = need surgical fixation in athletes
- “Conservative treatment = 6-8 weeks NWB cast = 25-50% nonunion = acceptable in sedentary patients
- “Screw size matters - a large (5.5mm or greater) solid screw is recommended in elite athletes (Hunt & Anderson 2011)
- “Bone graft for Torg Type II-III (delayed/nonunion) presentations
Overview and Epidemiology
The Jones fracture is a fracture at the metadiaphyseal junction of the fifth metatarsal base, Zone 2 of the three proximal zones. Sir Robert Jones described it in 1902, having sustained the injury himself while dancing. It is notorious for its high nonunion rate and prolonged healing time.
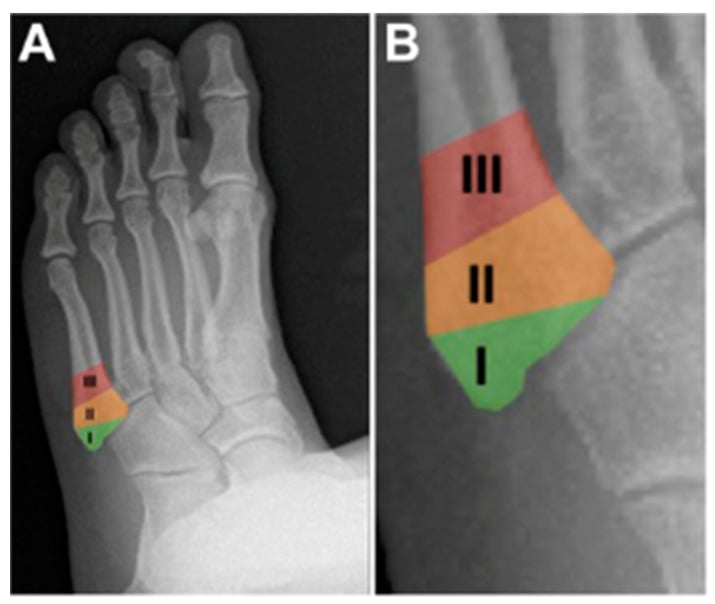
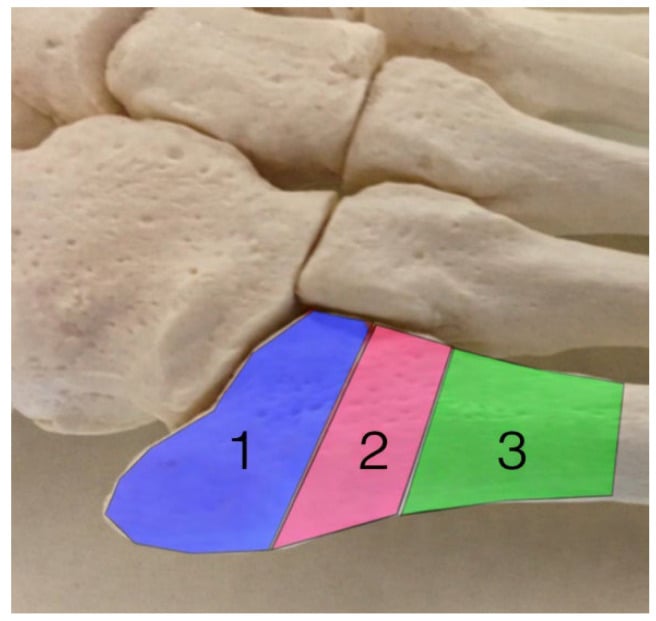
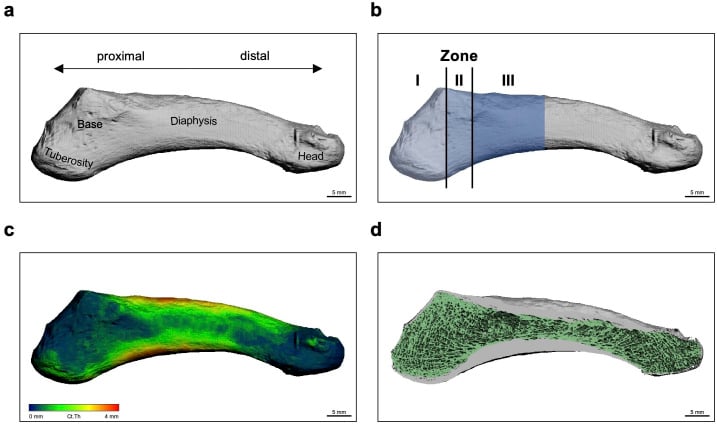
The three zones. The proximal fifth metatarsal is divided into three zones, and the zone is the first thing to settle because the three heal so differently:
- Zone 1 (tuberosity avulsion): extra-articular or involving the metatarsocuboid joint; the most common proximal fifth metatarsal fracture; benign.
- Zone 2 (true Jones fracture): at the metadiaphyseal junction, with the fracture line extending into the fourth-fifth intermetatarsal articulation; lies in the vascular watershed.
- Zone 3 (proximal diaphyseal stress fracture): distal to the 4-5 joint within the proximal 1.5cm of the diaphysis; usually a fatigue or stress injury with prodromal symptoms, and the highest nonunion risk.
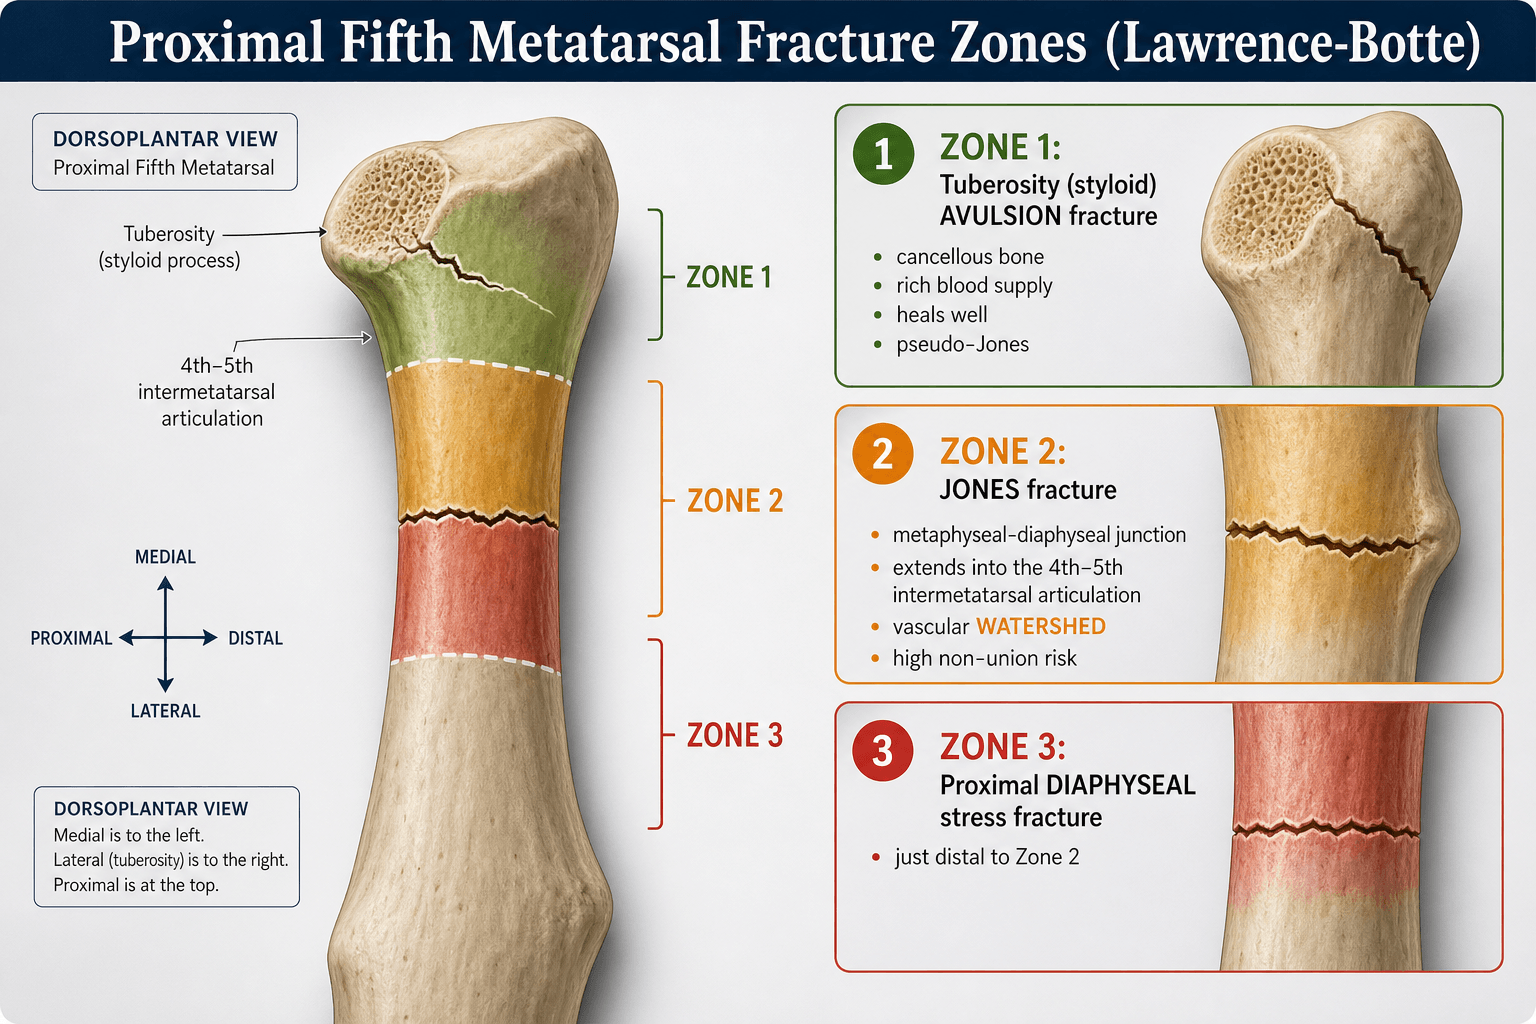
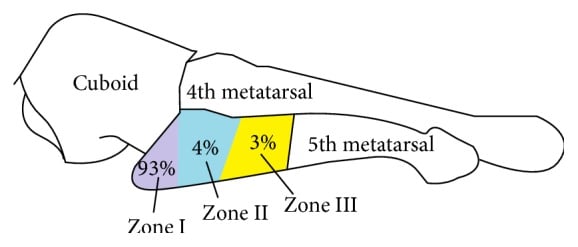
Not everyone draws the line between Zones 2 and 3. Some authors, and the Torg series, argue that the fine anatomical distinction between Zone 2 and Zone 3 matters less than chronicity (sclerosis and canal obliteration) and patient demand, since outcomes track these factors rather than the precise level (Chuckpaiwong 2008).
Who. Peak incidence is in young, active adults, and the injury is strongly associated with running, cutting, pivoting and jumping sports.
Predisposing factors. Cavovarus or hindfoot varus alignment concentrates load on the lateral column, and cavovarus that is not addressed is a recognised cause of refracture. The others are gastrocnemius tightness, metatarsus adductus, a prior fifth metatarsal injury, training-load error and inadequate footwear.
Anatomy/Biomechanics
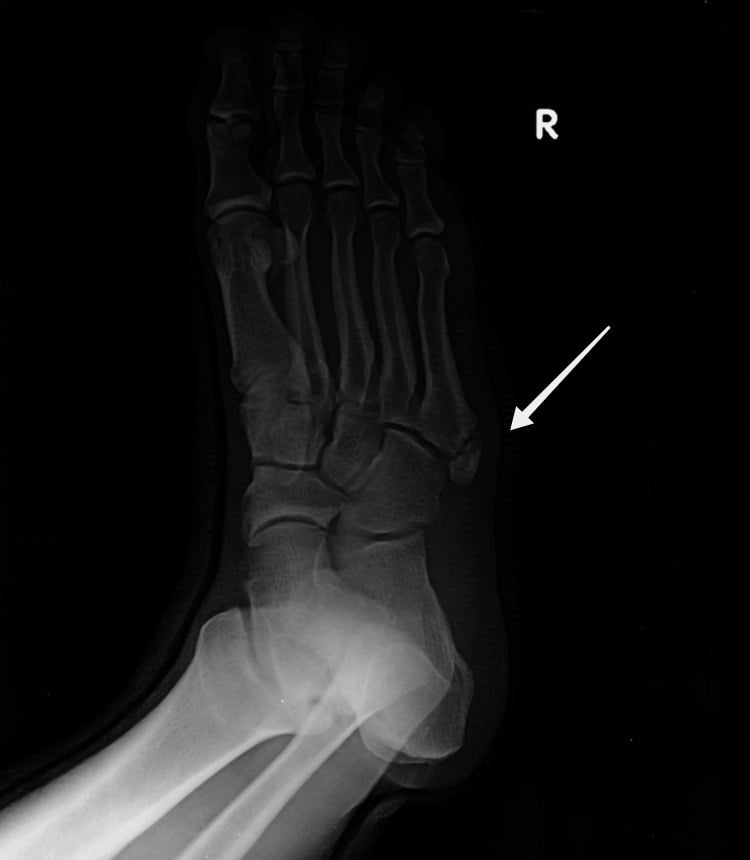
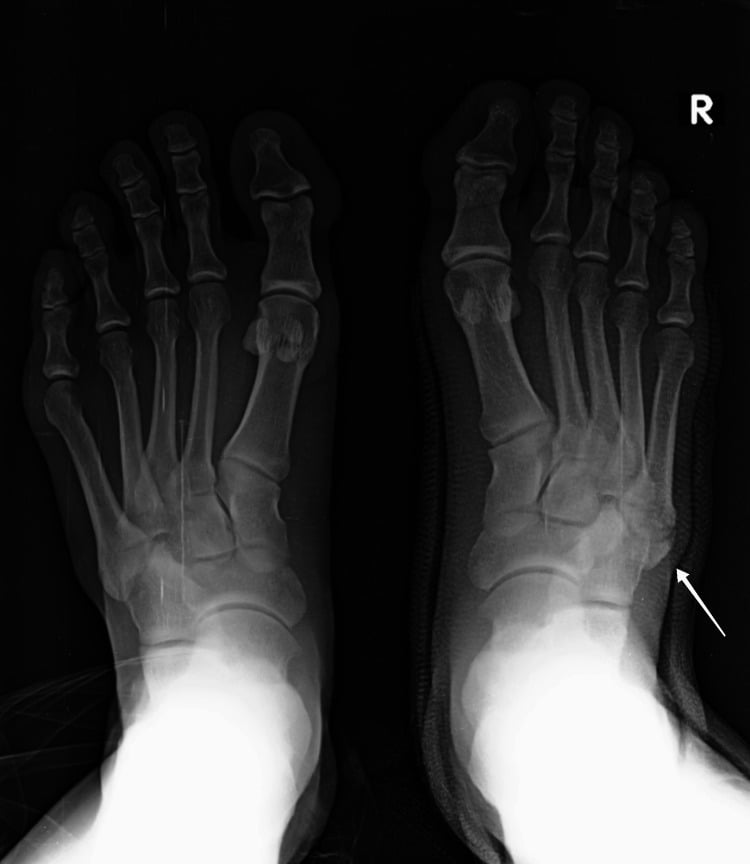
Zone 2 boundaries. Zone 2 runs from the level of the fourth-fifth intermetatarsal articulation proximally to the junction of metaphysis and diaphysis distally. Its defining feature is that the fracture line extends into the 4-5 intermetatarsal joint: a Zone 1 avulsion lies proximal to that joint and a Zone 3 stress fracture distal to it. The question to ask of the radiograph is whether the line enters the 4-5 articulation; if it does, this is a Jones fracture.
- Zone 1 (Avulsion)
- Tuberosity
- Zone 2 (Jones)
- Metadiaphyseal junction
- Zone 3 (Stress)
- Proximal diaphysis
- Zone 1 (Avulsion)
- PROXIMAL to 4-5 IM joint
- Zone 2 (Jones)
- Extends INTO 4-5 IM joint
- Zone 3 (Stress)
- DISTAL to 4-5 IM joint
- Zone 1 (Avulsion)
- Inversion avulsion
- Zone 2 (Jones)
- Adduction force; acute or stress
- Zone 3 (Stress)
- Repetitive loading
- Zone 1 (Avulsion)
- Good (cancellous)
- Zone 2 (Jones)
- Watershed (poor)
- Zone 3 (Stress)
- Periosteal
- Zone 1 (Avulsion)
- Low (under 5%)
- Zone 2 (Jones)
- HIGH (25-50%)
- Zone 3 (Stress)
- Very high (over 50%)
- Zone 1 (Avulsion)
- Almost always conservative
- Zone 2 (Jones)
- Consider surgery; athletes need surgery
- Zone 3 (Stress)
- Usually surgical
- Zone 1 (Avulsion)
- CAM boot 4-6 weeks
- Zone 2 (Jones)
- IM screw fixation
- Zone 3 (Stress)
- IM screw + graft
The watershed. The nutrient artery enters the medial cortex at the proximal metaphysis, metaphyseal arteries supply the proximal cancellous bone, and periosteal vessels supply the diaphysis from distally. Zone 2 is where the nutrient artery supply meets the periosteal supply, so it is relatively avascular compared with Zone 1, which has rich metaphyseal blood, and Zone 3, which has the periosteal supply. The scaphoid waist and the central third of the navicular are the same idea.
Why it matters. Healing potential at the watershed is compromised: the nonunion rate with conservative treatment is 25-50%, union is slower even with appropriate treatment, and a delayed union or nonunion goes on to sclerosis, which is what the Torg Type II and III appearances record.
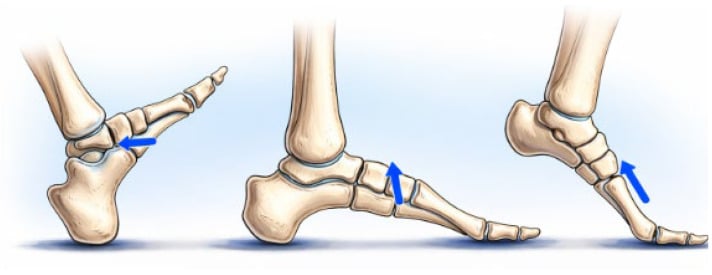
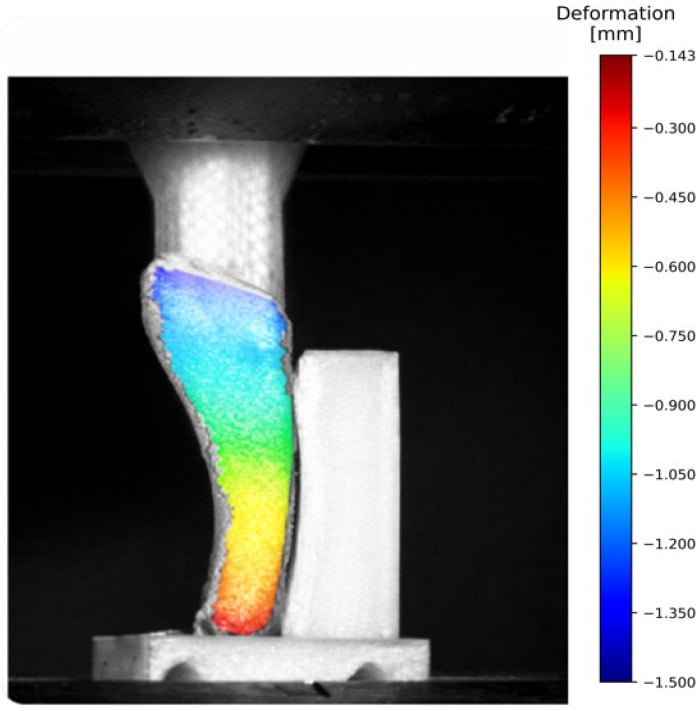
Mechanism. The fifth metatarsal acts as a lever arm during push-off, peroneus brevis creates a bending moment on it, and hindfoot varus overloads the lateral column. Three loads produce the fracture:
- An adduction or inversion load on a planted, plantarflexed forefoot
- Vertical loading with the heel off the ground
- Repetitive stress in athletes, the acute-on-chronic injury of repetitive lateral-column overload
Classification
Torg classification. The Torg classification is the most widely used system for Jones fractures. It is based on radiographic appearance and indicates chronicity, which is what decides whether bone graft will be needed.
- Radiographic Features
- Sharp, well-defined fracture line with a narrow gap; no widening, no periosteal reaction, no medullary sclerosis
- Clinical Scenario
- First-time injury, no prodromal symptoms
- Radiographic Features
- Widened fracture line; periosteal new bone formation; early medullary sclerosis
- Clinical Scenario
- Previous treatment failure common; chronic symptoms
- Radiographic Features
- Complete medullary sclerosis with obliteration of the canal; wide, irregular fracture gap; periosteal reaction or callus
- Clinical Scenario
- Established nonunion, chronic pain
The type maps directly onto the operation, which is set out under Management.
Clinical Assessment
History. Establish whether the onset was acute or insidious, since a prodrome of lateral foot pain points to a chronic component, and ask about activity level (athlete or sedentary, which shapes treatment), any prior fifth metatarsal fracture, and when the symptoms began. The features that flag a chronic component:
- Gradual onset of symptoms before the acute event
- A history of similar pain that resolved
- Prolonged activity-related pain
- Previous treatment for lateral foot pain
Examination. Look for lateral foot swelling and ecchymosis, comparing with the other foot. Palpate the whole fifth metatarsal and the peroneal tendons, and locate the point of tenderness, because it maps to the zone:
- Zone 1: at the tuberosity, at the peroneus brevis insertion
- Zone 2: at the metadiaphyseal junction, 1.5cm distal to the tuberosity
- Zone 3: more distal, along the proximal shaft
The rest of the foot. Assess hindfoot alignment, since varus predisposes to lateral overload; gastrocnemius tightness with the Silverskiold test; ankle stability and lateral ligament integrity; and neurovascular status, which is usually intact.
Differential diagnosis. Lateral foot and fifth metatarsal base pain has several mimics. The discriminators are whether the fracture line involves the 4-5 intermetatarsal articulation and whether an accessory ossicle, with its normal corticated margins, is present.
- Distinguishing Features
- Inversion mechanism; tenderness at peroneus brevis insertion; line proximal to 4-5 joint
- Imaging
- Transverse line at tuberosity, extra-articular or into cuboid joint
- Management
- Almost always conservative; symptomatic boot
- Distinguishing Features
- Acute or acute-on-chronic; line at metadiaphyseal junction into 4-5 joint; watershed zone
- Imaging
- Sharp line (Torg I) to sclerotic canal (Torg III)
- Management
- Screw fixation in athletes; cast option in sedentary
- Distinguishing Features
- Insidious onset, prodromal pain; runners; distal to 4-5 joint
- Imaging
- Periosteal reaction, cortical thickening, sclerosis
- Management
- High nonunion risk - usually screw +/- graft
- Distinguishing Features
- Asymptomatic accessory ossicle; smooth corticated margins
- Imaging
- Rounded ossicle, no acute lucent line
- Management
- No treatment unless symptomatic
- Distinguishing Features
- Pain on resisted eversion; tendon-line tenderness; no bony point tenderness
- Imaging
- Radiographs normal; ultrasound/MRI shows tendon pathology
- Management
- Rehabilitation; surgery for tears
- Distinguishing Features
- Midfoot swelling, plantar ecchymosis; pain on midfoot stress
- Imaging
- Weight-bearing views, fleck sign; CT for occult injury
- Management
- Often surgical - missed Lisfranc causes nonunion and arthrosis
- Distinguishing Features
- Lateral midfoot tenderness over cuboid, not metatarsal base
- Imaging
- Oblique radiograph; CT for nondisplaced
- Management
- Usually conservative
In children and adolescents the fifth metatarsal base has a normal secondary ossification centre (apophysis) at the tuberosity (appears around age 9-14, fuses by around age 14-16). It is oriented longitudinally, parallel to the shaft, with smooth corticated margins, whereas a true fracture line runs transversely across the bone. Never label a normal apophysis a fracture — compare the contralateral foot if unsure. Repetitive traction at the peroneus brevis insertion on this apophysis causes Iselin disease, a traction apophysitis in active adolescents presenting with lateral base tenderness and swelling, managed with activity modification and immobilisation rather than surgery. The os vesalianum is a separate accessory ossicle to distinguish from an acute fracture.
Investigations
Radiographs. Three views, each answering a different question:
- AP foot - the best view for identifying the zone
- Lateral foot - angulation
- Oblique foot - profiles the fifth metatarsal
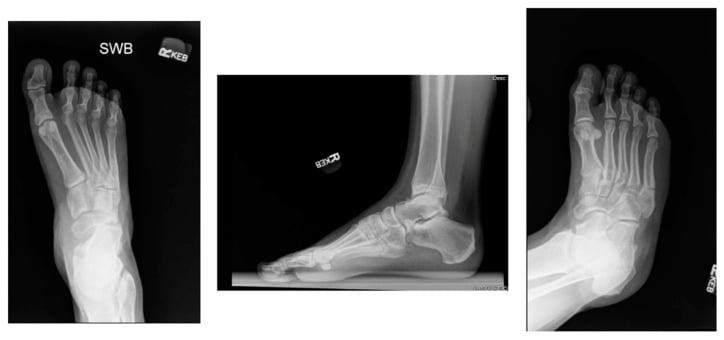
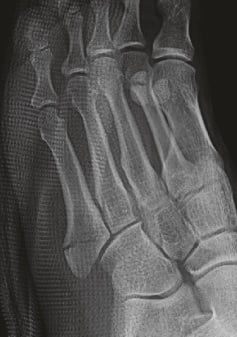
Reading the film. Locate the fracture line relative to the 4-5 joint, then read the fracture for chronicity. The signs that the injury is old, and that bone graft will be needed:
- Sclerotic margins at the fracture site and increased density of the bone ends
- Obliteration of the medullary canal
- A lucent zone around the fracture, with resorption at the fracture edges
- Widening of the fracture line and separation of the fragments
- Periosteal reaction and old callus, the evidence of previous healing attempts
CT. Use it to grade the degree of medullary sclerosis, to plan nonunion surgery, to look for refracture after previous fixation and to assess healing after surgery. It shows canal patency, fracture healing and hardware position.
MRI. Use it for a stress reaction without a fracture line, for soft tissue assessment, for the pattern of marrow oedema and to separate acute from chronic injury. An acute fracture is low signal on T1 and high signal on T2 and STIR, both from marrow oedema; in a chronic fracture the sclerosis is visible.
Management
The decision. Three questions settle it, in order:
- Is the patient an athlete requiring rapid return to sport? Yes: intramedullary screw fixation. No: consider non-operative treatment if the fracture is Torg Type I.
- What is the Torg type? Type I: a screw alone may suffice. Type II: screw, and consider bone graft; some surgeons curet the fracture site; expected healing 10-12 weeks, with a higher refracture risk than Type I. Type III: screw, bone graft and curettage of the medullary canal, which is essential; expected healing 12-16 weeks or more; some use plate fixation if the canal is severely obliterated.
- Has conservative treatment failed? Yes: surgical fixation is mandatory, with bone grafting considered.
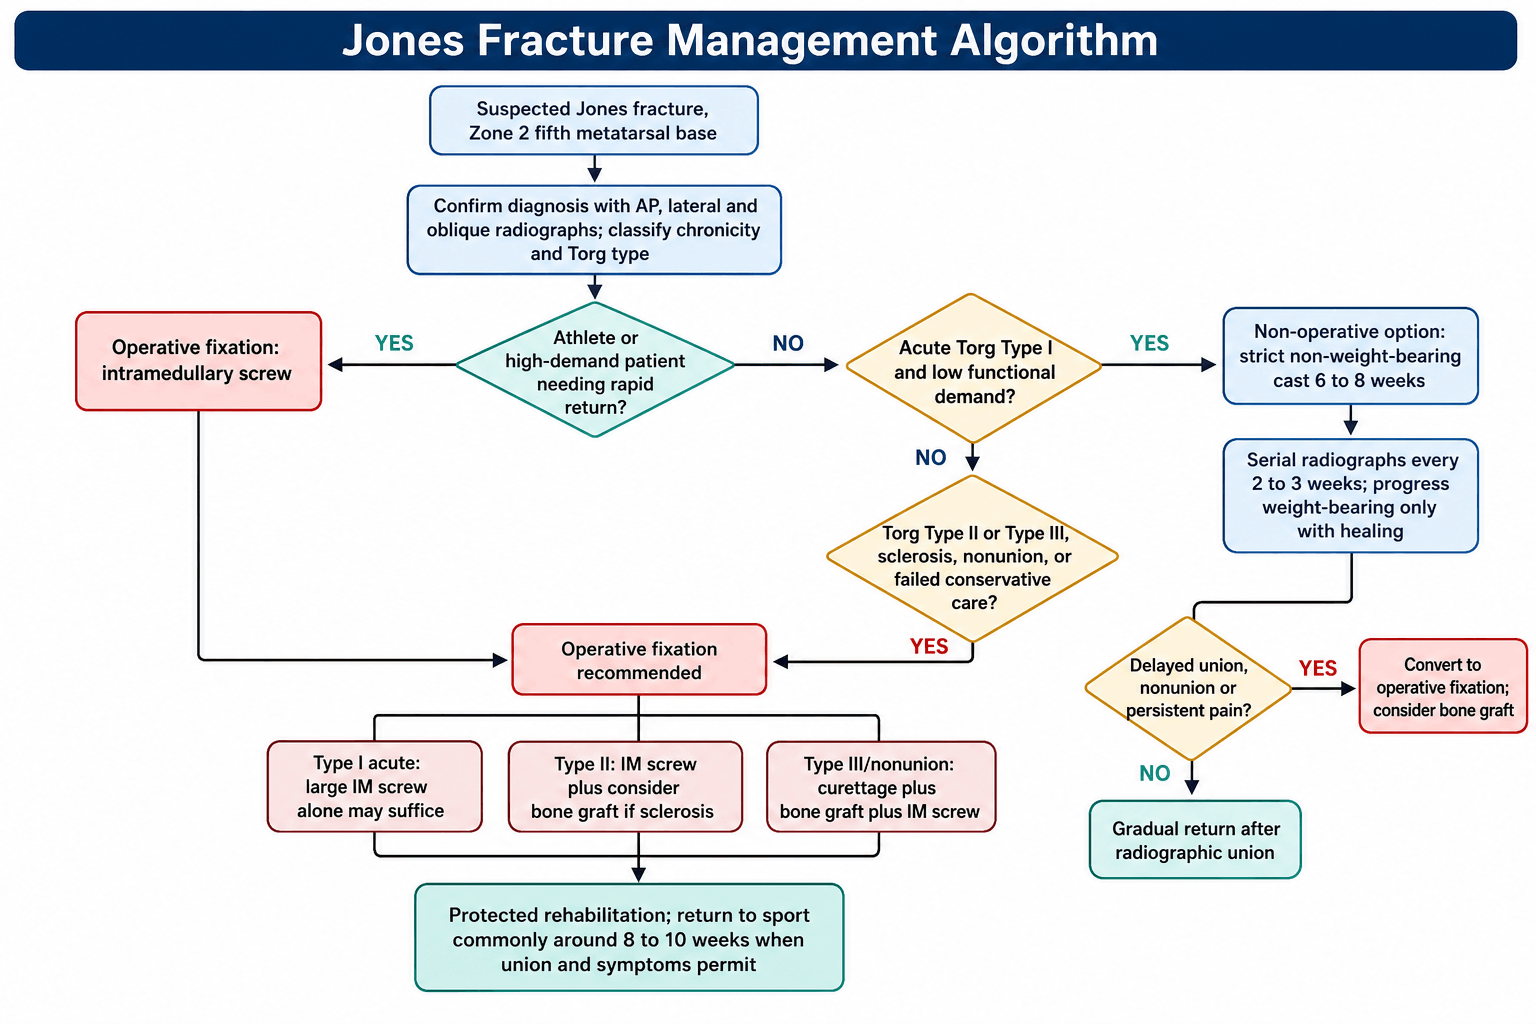
Non-operative treatment. The candidates are sedentary patients with low functional demands and an acute Torg Type I fracture, who accept the 25-50% nonunion risk. The protocol is a short leg cast with strict non-weight-bearing for 6-8 weeks, serial radiographs every 2-3 weeks, and gradual weight-bearing once radiographic healing is seen; total treatment time runs 12-20 weeks, with return to sport at 4-5 months if healing occurs.
Operative treatment. The indications are athletes at any level, high functional demands, Torg Type II or III, failed conservative treatment, and the patient who wants a faster return to activity. Athletes need surgery because it gives union and return to sport in 8-10 weeks against 15 or more, a nonunion rate under 5% against 25-50%, and more predictable healing.
Surgical Technique
Setup and equipment. Supine on a radiolucent table with a bump under the ipsilateral hip, the foot accessible to the C-arm. Have 5.5mm or 6.5mm cannulated screws, guidewires, a cannulated drill and a countersink to hand.
Intramedullary screw fixation.
- Direct lateral incision over the tuberosity, 2-3cm, protecting the sural nerve
- Entry point at the tip of the tuberosity, "high and medial"
- Guidewire under fluoroscopy, confirming a central position
- Measure screw length; ream if needed, overreaming by 0.5mm only
- Insert the largest screw the canal accepts and engage the far cortex, which is the plantar bone
- Final fluoroscopy on AP, lateral and oblique views: adequate compression, no joint penetration, and the head countersunk to avoid prominence
The entry point. Too dorsal places the screw eccentrically; aim for the centre of the medullary canal.
Screw selection. A large, 5.5mm or greater, solid screw is recommended in elite athletes, because undersized hardware is a recognised cause of refracture and nonunion (Hunt and Anderson 2011). Solid screws are biomechanically stronger than cannulated ones, and the screw must cross and compress the fracture and "fit and fill" the canal. Read the 5.5mm figure for what it is, an expert recommendation rather than a tested threshold, and apply it canal permitting: a screw too wide for the canal wedges and straightens the curved metatarsal, so use the largest diameter the canal will accept without doing that.
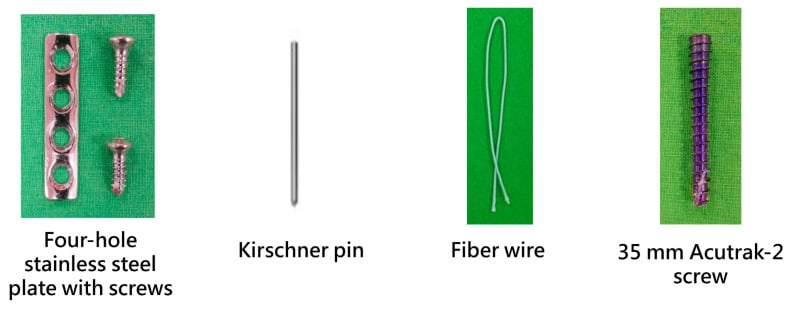
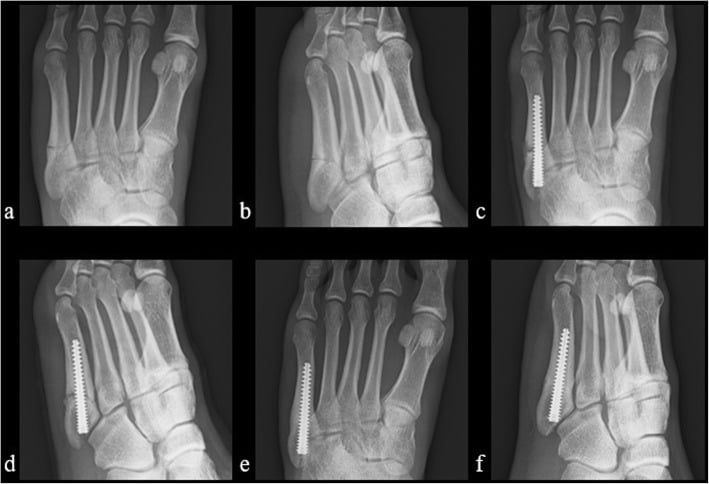
Bone grafting. Required for Torg Type II with significant sclerosis, Torg Type III nonunion and revision surgery. Iliac crest autograft is the gold standard; proximal tibia offers less morbidity, and calcaneus can be taken from the same operative field. Curet the sclerotic bone from the medullary canal, pack morselised graft into the canal and, if wanted, around the fracture site, then insert the intramedullary screw. Where the canal cannot accommodate a screw, plantar plating is the alternative.
Biological adjuncts. Because the watershed biology is the limiting factor, union can be augmented alongside mechanical fixation. Autograft is the gold-standard graft for sclerotic delayed unions and nonunions; bone marrow aspirate concentrate (BMAC) plus demineralised bone matrix (DBM) is a lower-morbidity biological alternative used in elite-athlete series (Hunt and Anderson; Lareau). Low-intensity pulsed ultrasound (LIPUS) and other bone stimulators are non-invasive adjuncts used to promote union, particularly in delayed union or as an add-on after fixation in high-demand athletes; the evidence is supportive but not definitive, so they supplement, never replace, adequate fixation, canal preparation and correction of biomechanical risk (cavovarus, smoking). They are an adjunct, not a primary treatment.
Complications
Nonunion. The risk factors are conservative treatment (the 25-50% rate), Torg Type II or III at presentation, inadequate immobilisation, early weight-bearing, smoking and diabetes. Treatment is surgical fixation with bone graft and curettage of sclerotic bone, with a larger screw or plate fixation considered.
Refracture. The best-evidenced risk factor is early return to sport before radiographic union: Larson's failures returned at a mean of 6.8 weeks against 9 weeks in those who did not fail, and only 1 of 6 failures had complete union when cleared. Elite competition level, hardware removal and residual cavovarus alignment are also implicated. Small screw diameter is widely blamed but poorly evidenced: Larson found no significant difference in screw diameter between failures and successes, so the case for a large screw rests on expert recommendation (Hunt and Anderson) and mechanics rather than comparative data.
Preventing refracture. Delay clearance until complete radiographic union, not merely absence of pain and "progress"; Larson's failures were all asymptomatic and progressing when released. Address cavovarus with an orthosis or a lateralising osteotomy where present, and consider leaving the hardware in place long-term.
Hardware. A prominent screw head may need removal after healing, a screw that backs out requires revision fixation, and breakage is rare with an adequately sized screw.
Sural nerve injury. Caused by an entry point too plantar or by retraction. Prevention is entry at the tip of the tuberosity, careful soft tissue handling and direct visualisation.
Postoperative Care
Rehabilitation. The postoperative timeline, which is also the athlete protocol:
- Weeks 0-2: posterior splint, non-weight-bearing, with elevation and ice for swelling
- Weeks 2-6: CAM boot with progressive weight-bearing in the boot; range-of-motion exercises out of the boot; pool therapy if available
- Weeks 6-8: athletic shoe with full weight-bearing; progressive strengthening including stationary bike and swimming
- Weeks 8-10: sport-specific training with a cutting and jumping progression; return to play when the criteria are met
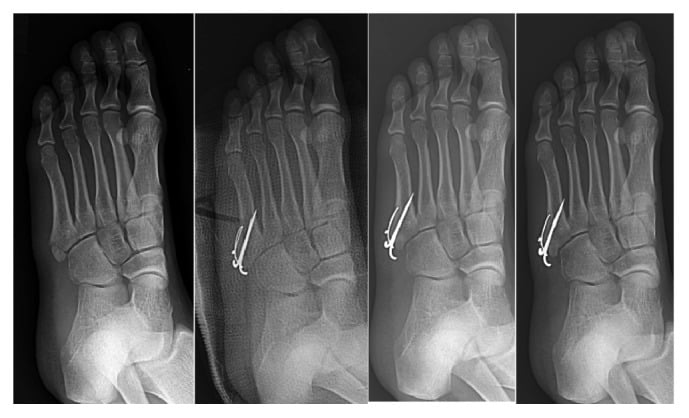
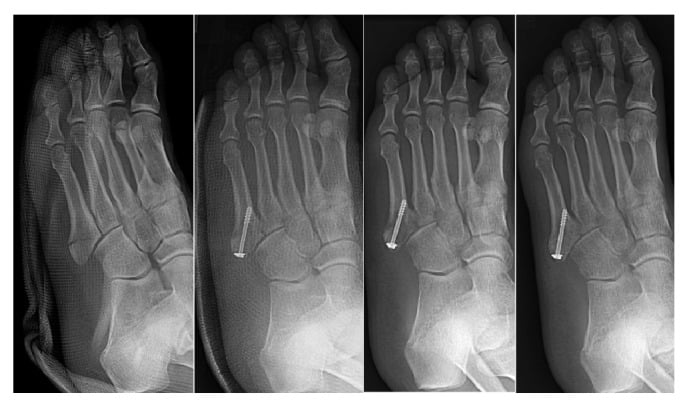
Return to sport criteria. Return to play requires:
- Pain-free with sport-specific activities
- Full range of motion
- Normal strength, demonstrated by the single-leg hop test
- Radiographic evidence of healing with bridging callus
Outcomes/Prognosis
After surgery. The pooled union rate with intramedullary screw fixation in athletes is approximately 97% (Attia 2021 meta-analysis), and return to sport averages 9-10 weeks. The overall refracture rate is approximately 10% in athletic cohorts. Hardware removal is rarely needed unless symptomatic.
Without surgery. Union in a cast is 50-75% for Torg Type I, the refracture risk is higher than after surgery, and the option is best reserved for non-athletes with Type I fractures. Time to union, when it happens, is given as anywhere from 6-12 weeks to 15-20 weeks, and the evidence cards below show why the spread is so wide: Torg's non-weight-bearing cast patients united in a mean of 7 weeks, whereas Mologne's cast arm took a median of 14.5 weeks.
- Union Rate (Non-Op)
- 75%
- Union Rate (Surgical)
- 95%
- Return to Sport
- 8-10 weeks
- Union Rate (Non-Op)
- 50%
- Union Rate (Surgical)
- 90% (with graft)
- Return to Sport
- 10-12 weeks
- Union Rate (Non-Op)
- 25%
- Union Rate (Surgical)
- 85% (with graft)
- Return to Sport
- 12-16 weeks
Guidelines, Registries & Global Practice
Global Epidemiology
Proximal fifth metatarsal fractures are among the most common forefoot injuries, and the Zone 2 (Jones) and Zone 3 (proximal diaphyseal stress) patterns are over-represented in cutting and pivoting field sports worldwide - American football, basketball, soccer, rugby and Australian Rules football. Their disproportionate impact on elite athletes (high-profile in-season injuries in the NFL, NBA and European football) has driven a strong international convergence toward early operative fixation in this population (Attia 2021 meta-analysis; Porter 2017).
Side-by-Side Guidance and Evidence Synthesis
There is no single high-level society practice guideline dedicated to Jones fractures; practice is instead anchored on synthesised evidence and expert consensus. The dominant positions across major bodies and the strongest evidence are summarised below.
- Position
- Recommend surgical IM screw fixation for ALL Jones fractures in athletes; superior return to play, union and time to union vs nonoperative
- Evidence Level
- Level IV systematic review of mostly Level IV studies
- Position
- Early screw fixation halves time to union and return to sport vs casting; 44% cast failure
- Evidence Level
- Level I RCT
- Position
- Acute Zone 2/3: IM screw the standard for active patients; conservative (non-weight-bearing) reasonable for low-demand acute Torg I
- Evidence Level
- Expert consensus / textbook
- Position
- IM screw is the preferred construct; 'fit and fill' the canal; biological augmentation and large solid screws for elite athletes and chronic/sclerotic fractures
- Evidence Level
- Level V expert opinion / narrative review
- Position
- Sedentary patients with acute Torg I may be offered non-weight-bearing immobilisation after counselling on the substantial nonunion risk
- Evidence Level
- Consensus, supported by RCT and meta-analysis
The evidence pyramid for Jones fractures is unusual: a single Level I RCT (Mologne 2005) plus a large meta-analysis (Attia 2021) both point the same way - operative fixation for athletes and active patients, conservative care reserved for low-demand patients who accept a high failure rate. No body recommends routine nonoperative treatment in athletes.
Registry and Real-World Evidence
Unlike arthroplasty, there is no dedicated international Jones-fracture registry; population-level data derive from large athletic cohorts and league injury surveillance (e.g. NFL and professional soccer datasets), which consistently report return-to-play rates above 95% with operative treatment and a persistent refracture rate of roughly 10% (Attia 2021; Lareau 2016). These real-world series confirm that the principal modifiable failure factors are undersized hardware, inadequate biology in sclerotic fractures, uncorrected cavovarus alignment, and premature return to sport before radiographic union (Larson 2002; Hunt and Anderson 2011).
Practice Variation
International practice varies chiefly at the margins rather than the core: the threshold for operating on the recreational or sedentary patient, routine use of biological augmentation (bone marrow aspirate concentrate, demineralised bone matrix, autograft), choice between cannulated and solid screws, and the aggressiveness of return-to-sport timelines. Plantar plating is reserved for revision or canals that cannot accommodate an adequate screw.
Prevention and Modifiable Risk Factors
- Training-load management: avoid rapid increases in cutting, pivoting and lateral-column loading to reduce acute-on-chronic Zone 2/3 stress injury in field-sport athletes.
- Biomechanical correction: address hindfoot varus / cavovarus and gastrocnemius tightness; uncorrected cavovarus is a recognised cause of refracture.
- Footwear: appropriate sport-specific footwear and lateral-support orthoses to offload the lateral column.
- Smoking cessation: smoking impairs union and is a modifiable nonunion risk factor; structured cessation support improves outcomes.
Viva Scenarios
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 22-year-old professional basketball player presents with acute lateral foot pain after landing awkwardly. X-rays show a fracture at the metadiaphyseal junction of the fifth metatarsal with the fracture line extending into the 4-5 intermetatarsal articulation. There is no medullary sclerosis.”
“A 28-year-old recreational runner had a Jones fracture treated conservatively 4 months ago. She remains symptomatic with lateral foot pain on walking. X-rays show widened fracture line with medullary sclerosis but no complete canal obliteration.”
“A 19-year-old soccer player had Jones fracture fixation with a 4.5mm screw 6 months ago. He returned to play at 8 weeks. He now presents with recurrent lateral foot pain. X-rays show a refracture around the previous screw, which remains in place.”
MCQ Practice Points
Q: Where is the Jones fracture located and what distinguishes it from a tuberosity avulsion?
A: Jones fracture is at the metadiaphyseal junction (Zone 2), extending INTO the 4-5 intermetatarsal joint. Tuberosity avulsion (Zone 1) is PROXIMAL to this joint and involves the peroneus brevis insertion.
Q: Why do Jones fractures have a high nonunion rate?
A: The Zone 2 area is a watershed zone where the nutrient artery (entering from medial cortex) meets the periosteal blood supply. This relatively avascular area compromises healing potential.
Q: How does the Torg classification guide treatment?
A: Type I (acute) - screw alone. Type II (delayed union) - screw plus bone graft. Type III (nonunion) - screw plus bone graft plus curettage of sclerotic bone. The classification is based on radiographic appearance.
Q: What is the minimum recommended screw size for Jones fracture fixation and why?
A: A large (minimum 5.5mm) solid screw is recommended, particularly in elite athletes, because undersized hardware is implicated in refracture and nonunion (Hunt and Anderson 2011). Use the largest diameter that fits and fills the canal with threads crossing the fracture.
Q: When can an athlete return to sport after Jones fracture fixation?
A: 8-10 weeks with radiographic evidence of healing (bridging callus across 3 of 4 cortices). Earlier return risks refracture, especially with undersized screws.
Key Numbers
- Zone 2 = Jones fracture location (metadiaphyseal junction)
- 25-50% = Nonunion rate with conservative treatment
- 5.5mm = Minimum recommended screw diameter
- 8-10 weeks = Return to sport after surgical fixation
- 4-5 joint = Fracture extends INTO this joint
Examiner Favorites
- Differentiate Jones from tuberosity avulsion (Zone 1 vs Zone 2)
- Why high nonunion rate? Watershed blood supply
- Describe Torg classification and treatment implications
- Surgical technique for Jones fracture fixation
Common Mistakes
- Confusing Zone 1 (avulsion) with Zone 2 (Jones)
- Using undersized screw (under 5.5mm) leads to refracture
- Treating athletes conservatively
- Not recognizing Torg Type II-III need bone grafting
Exam Day Tips
- Jones = Zone 2 = fracture INTO 4-5 intermetatarsal joint
- Watershed zone = poor healing
- Athletes get surgical fixation
- Torg I = no graft, Torg II-III = bone graft
Evidence Base
Key Evidence
Early Screw Fixation versus Casting for Acute Jones Fractures (RCT)
- 37 patients randomised (19 screw, 18 cast). Cast group had a 44% failure rate (5 nonunions, 1 delayed union, 2 refractures) versus 1 failure in the screw group. Median time to union and return to sport: 7.5 and 8.0 weeks (screw) versus 14.5 and 15.0 weeks (cast).
Intramedullary Screw Fixation of Jones Fractures: Analysis of Failure
- 15 patients after cannulated screw fixation: 6 failures (4 refractures, 2 symptomatic nonunions). Failures were concentrated among elite (Division I/professional) athletes (83% of failures). Return to full activity before complete radiographic union was the dominant predictor of failure.
- THE NEGATIVE FINDINGS MATTER AS MUCH AS THE POSITIVE ONE: there was no significant difference between the failure and non-failure groups in screw diameter, use of bone graft, age of the fracture, patient age or sex. The variable that separated them was timing.
- The numbers make the point starkly: mean time to full activity was 6.8 weeks in those who failed against 9 weeks in those who did not, and only 1 of 6 failures had complete radiographic union before returning, compared with 6 of 7 without complications. Every patient was asymptomatic and 'progressing' radiographically when cleared.
Torg Classification of Fifth Metatarsal Base Fractures
- 46 fractures of the fifth metatarsal base distal to the tuberosity, followed for a mean of 40 months. Defined three radiographic types: acute (narrow line, no sclerosis), delayed union (widened line, intramedullary sclerosis), and nonunion (canal obliterated by sclerotic bone). Of 25 acute fractures, 14 of 15 treated by non-weight-bearing cast healed in a mean of 7 weeks; weight-bearing methods healed only 4 of 10. Nonunions were treated by medullary curettage and inlay bone grafting.
Revision Screw Fixation with Bone Grafting for Nonunion/Refracture in Elite Athletes
- 21 elite athletes with Jones fracture nonunion or refracture treated by revision intramedullary screw fixation with autograft or bone-marrow aspirate plus demineralised bone matrix. All achieved cortical union and returned to their previous level of competition at a mean of 12.3 weeks; only 1 subsequent refracture.
Return to Play in NFL Players After Operative Jones Fracture Treatment
- 25 consecutive NFL players treated with a Jones-specific intramedullary screw plus iliac crest bone marrow aspirate and demineralised bone matrix, bone stimulator and orthoses. Return to play was 100%; among the 9 eligible to return in-season, mean return to play was 8.7 weeks. Three players (12%) refractured and required revision.
Return to Play and Union after Surgery for Jones Fractures: Systematic Review and Meta-analysis
- 22 studies, 646 Jones fractures in athletes. Return to play with intramedullary screw fixation 98.8% versus 71.6% nonoperative; time to return to play 9.6 versus 13.1 weeks. Pooled operative union 97.3% versus 71.4% nonoperative; overall refracture rate 10.2%. The authors recommend surgical fixation for all Jones fractures in athletes.
Distinguishing Jones from Proximal Diaphyseal Fifth Metatarsal Fractures
- 32 Jones and 29 proximal diaphyseal fractures. Clinical outcomes did not differ between the two locations; operatively treated patients returned to sport faster. Operative patients with fracture-site sclerosis or canal obliteration had lower satisfaction and higher complication rates.