Inversion Injury | ATFL Rupture | Brostrom-Gould Repair
- ATFL is injured first in plantarflexion (weakest position)
- Ottawa Ankle Rules reduce unnecessary X-rays by 30-40% (Bachmann, systematic review of 15,581 patients, PMID 12595378)
- Functional rehab is superior to immobilisation (Cochrane)
- Brostrom-Gould repair is the Gold Standard for chronic instability
- Rule out associated injuries: Maisonneuve, Base 5th MT, Osteochondral lesion
- “Don't offer surgery for acute sprains (even Grade III) - evidence supports conservation
- “Identify 'Mechanical' vs 'Functional' instability
- “Always palpate the proximal fibula (Maisonneuve fracture)
- “Prophylactic bracing reduces re-injury by 50%
Lateral Ankle Sprains
Overview and Epidemiology
Lateral ankle sprains are the single most common musculoskeletal injury. Most heal uneventfully, but a significant minority, about 20%, develop chronic ankle instability (CAI): recurrent giving way, pain and potential post-traumatic arthritis.
Pathophysiology and Mechanisms
Mechanism. The ankle is least stable in plantarflexion. The wider anterior talus exits the mortise and the joint relies entirely on its ligaments (the ATFL) for stability, which is why landing from a jump on a plantarflexed foot is the classic mechanism.
The anterior talofibular ligament (ATFL). It runs from the anterior distal fibula to the lateral talar neck and resists anterior translation and inversion in plantarflexion. It is the weakest link, only 2mm thick and often little more than a capsular thickening, and it is injured in 85-90% of sprains.
The calcaneofibular ligament (CFL). It runs from the fibula tip to the lateral calcaneus, deep to the peroneal tendons, and resists inversion in neutral and dorsiflexion. It is injured in 50-75% of severe sprains, usually together with the ATFL.
Order of failure. The ligaments tear in sequence as the force increases:
- ATFL first, in plantarflexion
- CFL second, in neutral or dorsiflexion
- PTFL last, and only with dislocation
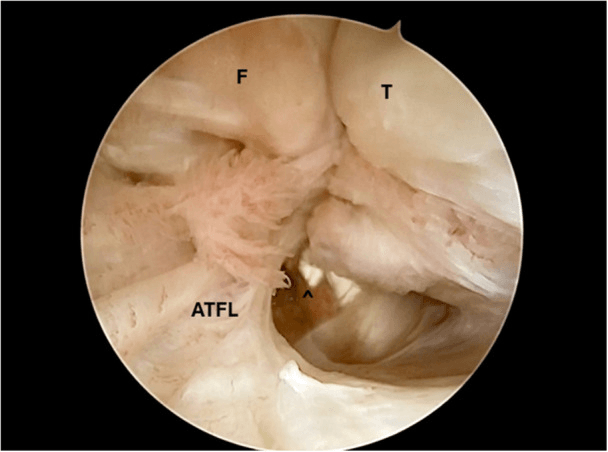
Hindfoot Varus: The Cause of Brostrom Failure You Must Correct
Unrecognised hindfoot varus is the prime cause of recurrent sprains and of Brostrom failure. Correcting the soft tissue without correcting the bone fails.
Why it matters. A subtle cavovarus or isolated hindfoot-varus posture shifts the weight-bearing axis medial to the subtalar joint, so the ground-reaction force continuously inverts the hindfoot and overloads the lateral ligaments. This causes recurrent inversion sprains and places a constant deforming strain on any lateral ligament repair: a tissue-only Brostrom done over an uncorrected varus heel is set up to stretch out and fail.
How to find it. Examine standing hindfoot alignment from behind for heel varus, the "peek-a-boo" medial heel pad and a high arch. The Coleman block test decides whether the varus is forefoot-driven (flexible, with a plantarflexed first ray) or a fixed hindfoot varus, and a weight-bearing hindfoot-alignment radiograph quantifies it. The cavovarus foot itself is covered in the cavovarus-foot topic.
How to correct it. When a varus hindfoot underlies the instability, add a bony realignment to the ligament surgery. A lateralising, closing-wedge (Dwyer) calcaneal osteotomy brings the heel out of varus, with a first-ray dorsiflexion osteotomy if the deformity is forefoot-driven. Correcting the axis offloads and protects the Brostrom repair.
Classification Systems
The acute injury is graded clinically:
- Pathology
- Microscopic tear
- Clinical Findings
- Mild swelling, WB tolerated
- Stability
- Stable
- Rest
- 1-2 weeks
- Pathology
- Partial macroscopic tear
- Clinical Findings
- Moderate swelling, limp
- Stability
- Mild laxity
- Rest
- 2-6 weeks
- Pathology
- Complete rupture
- Clinical Findings
- Severe swelling, Non-WB
- Stability
- Gross instability
- Rest
- 6-12 weeks
Chronic instability (Karlsson). Established instability comes in two forms. Mechanical instability is objective pathological laxity, with a positive anterior drawer or talar tilt. Functional instability is subjective giving way without gross laxity, a proprioceptive or neuromuscular deficit.
The type sets the treatment. Functional instability requires rehabilitation (proprioception). Mechanical instability may require surgical reconstruction if rehabilitation fails. Full assessment and surgical management of established instability is covered in chronic lateral ankle instability.
Clinical Assessment
Look. Egg-shaped swelling over the lateral malleolus is the haematoma sign. Check hindfoot alignment with the patient standing: a varus heel predisposes to recurrent sprains, and has its own section below.
Feel. Palpating for bony tenderness rules out fractures:
- Fibula tip
- Medial malleolus
- Base of the 5th metatarsal (Jones fracture)
- Navicular
- Proximal fibula (Maisonneuve fracture) - always palpate it
The Lisfranc injury of the midfoot and an osteochondral lesion of the talus complete the associated injuries that must not be missed.
Who needs a radiograph. The Ottawa Ankle Rules have a sensitivity of about 100% and reduce unnecessary X-rays by 30-40% (Bachmann, systematic review of 15,581 patients, PMID 12595378). An X-ray is indicated for any of:
- Tenderness at the posterior edge or tip of the lateral malleolus (distal 6cm)
- Tenderness at the posterior edge or tip of the medial malleolus (distal 6cm)
- Tenderness at the navicular
- Tenderness at the base of the 5th metatarsal
- Inability to weight bear for 4 steps, both immediately and in the emergency department
Tenderness anterior to the malleolus, over the ATFL, does not mandate an X-ray.
Move. The stability tests:
- Anterior drawer tests the ATFL; positive with a difference of more than 3mm
- Talar tilt tests the CFL; positive at more than 10°, or a difference of more than 5°
- Squeeze test for the syndesmosis
- Key Feature
- Inversion mech + ATFL tenderness
- Test
- Anterior Drawer
- Management
- Functional Rehab
- Key Feature
- High ankle pain, dorsiflexion pain
- Test
- Squeeze Test
- Management
- Boot/TightRope
- Key Feature
- Bony tenderness, unable to WB
- Test
- X-ray (Ottawa)
- Management
- ORIF vs Boot
- Key Feature
- Snap/Pop, tendon subluxes
- Test
- Resisted Eversion
- Management
- Repair Retinaculum
- Key Feature
- Deep pain, locking, persistent effusion
- Test
- MRI
- Management
- Debridement/Fixation
Generalised Ligamentous Laxity and the Beighton Score
Generalised laxity is a key modifier of both the risk of instability and the surgical plan, so screen every patient with recurrent sprains for it.
The Beighton score. Scored out of 9:
- Passive little-finger (5th MCP) hyperextension beyond 90° - one point each side
- Passive thumb apposition to the forearm - one point each side
- Elbow hyperextension beyond 10° - one point each side
- Knee hyperextension beyond 10° - one point each side
- Palms flat on the floor with the knees straight in forward flexion - one point
A common threshold for generalised joint hypermobility is 5 or more of 9 in adults (higher in children). Accompanied by other features, it should prompt thought of an underlying heritable connective-tissue disorder such as Ehlers-Danlos, covered in that topic.
Why it changes management. Hypermobile patients sprain more easily, develop chronic instability more often and heal a plication less reliably, because a standard Brostrom relies on the patient's own, intrinsically lax, tissue. Hypermobility lowers the threshold to augment the repair (internal brace or suture tape, or in severe cases a graft reconstruction rather than simple plication) and to emphasise lifelong proprioceptive training and bracing.
Investigations
Radiographs. AP, lateral and mortise views, when the Ottawa rules are positive, the patient cannot weight bear or the injury was high impact.
Stress views. Telos stress views apply the anterior drawer and talar tilt thresholds of the clinical examination. They are rarely used now, because of MRI availability and pain.
MRI. MRI is over-used acutely and is not for diagnosing a simple sprain. It shows ligament continuity or thickening, bone bruising and talar dome cartilage defects. The indications:
- Chronic instability when surgery is being considered
- Persistent pain beyond 6 weeks
- Suspected osteochondral lesion (OCL) or peroneal tear
Management Algorithm
- 1Acute Injury
Assess Ottawa Rules
X-ray vs Clinical
- 2Diagnosis
Sprain vs Fracture
Confirm Grade I/II/III
- 3Initial Tx
RICE + Functional Rehab
Early Mobilisation
- 4Review 6w
Pain/Instability?
Yes → MRI / No → Discharge
- 5Chronic
Mechanical Instability + Failed Rehab
Surgical Reconstruction
Acute sprains are treated functionally. Functional rehabilitation, early motion with bracing, is superior to cast immobilisation (Cochrane 2013). Immobilisation should be reserved for severe pain or fractures, and limited to less than 10 days. Even acute Grade III ruptures heal well with functional rehabilitation, so surgery is not offered for acute sprains; it is reserved for chronic instability.
Rehabilitation phases. The functional programme runs in four phases:
- Protection, 0-2 weeks: boot, RICE
- Motion, 2-4 weeks: range of motion, isometric exercises
- Strengthening, 4-6 weeks: peroneals, balance
- Function, from 6 weeks: plyometrics, sport
Surgical Technique
Modified Brostrom-Gould repair. The gold-standard anatomic repair of the ATFL and CFL, reinforced with the extensor retinaculum. Non-anatomic tenodesis is avoided. The steps:
- Approach. A curvilinear anterolateral incision anterior to the fibula, protecting the superficial peroneal nerve (SPN) anteriorly.
- Exposure. Open the capsule, identify the stretched or torn ATFL and CFL remnants and debride their edges.
- Repair. Place suture anchors (or transosseous tunnels) in the distal fibula and plicate the ATFL and CFL pants-over-vest, tightening in slight eversion and dorsiflexion.
- Gould augmentation. Mobilise the inferior extensor retinaculum and advance it superiorly over the repair. This increases strength and limits inversion; check subtalar motion.
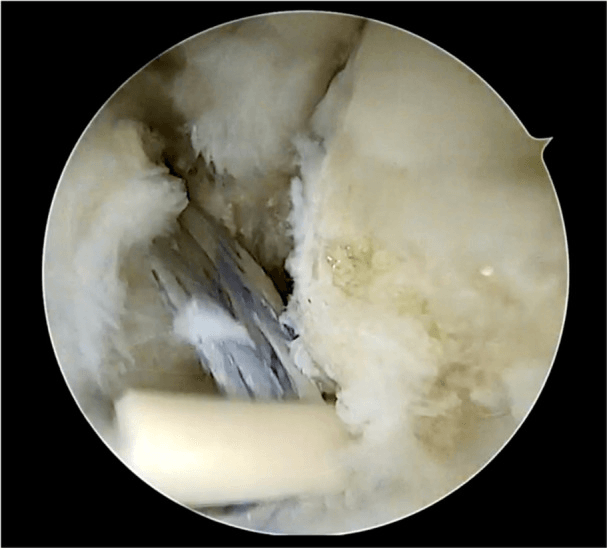
Arthroscopic repair. The anatomic repair can also be performed arthroscopically, reinserting the ATFL at its fibular footprint with a knotless anchor. How it compares with open repair is discussed under Controversies.
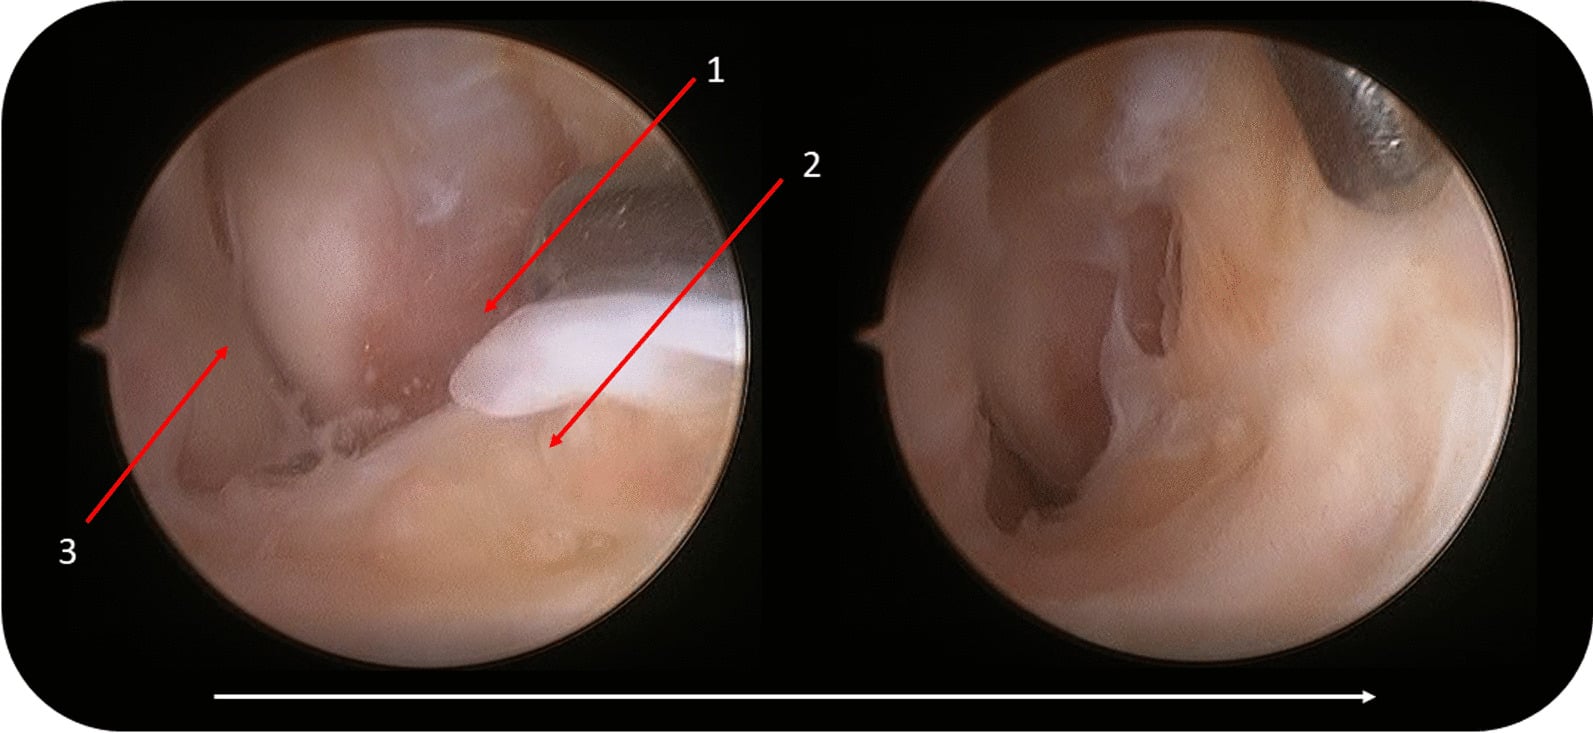
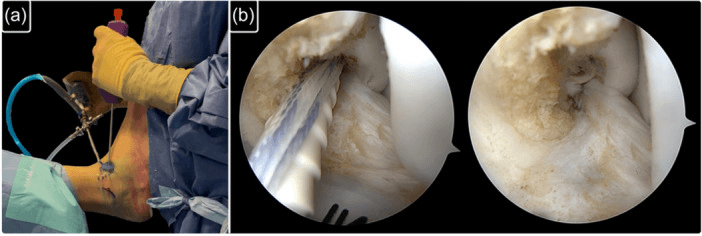
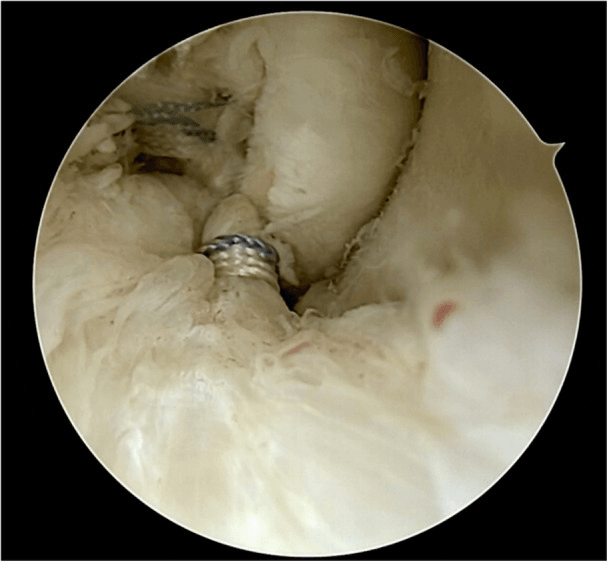
Internal brace augmentation. SwiveLock anchors with FiberTape create a check-rein "seatbelt" over the native repair. It allows earlier mobilisation, but the construct is distinct from native anatomy. The indications:
- Revision
- Generalised ligamentous laxity
- Heavy patient (over 100kg)
- High-demand collision athlete
Complications
Nerve injury. The superficial peroneal nerve is the most common complication (5-10%); its branches cross in the subcutaneous tissue. The sural nerve is at risk with posterior dissection for the CFL.
Recurrence and stiffness. Instability recurs in 5-10%, the failure rate of the repair. Overtightening causes stiffness, with loss of inversion and subtalar motion.
Wound. The skin over the lateral malleolus is thin and dehiscence is a risk. Infection occurs in less than 1%.
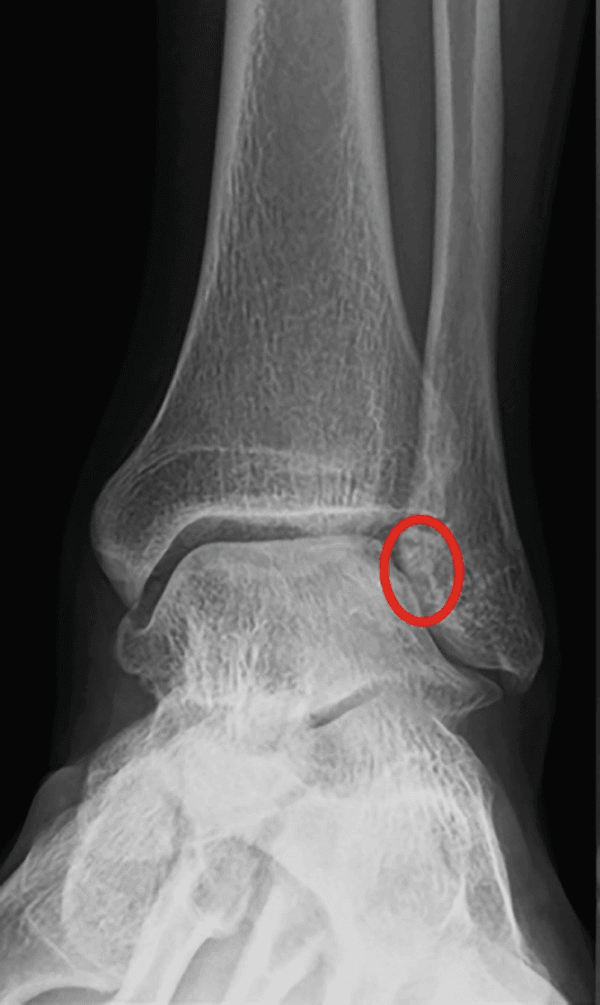
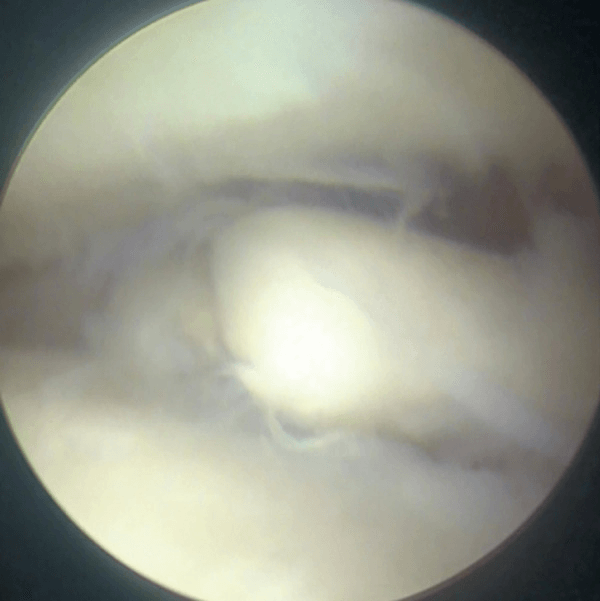
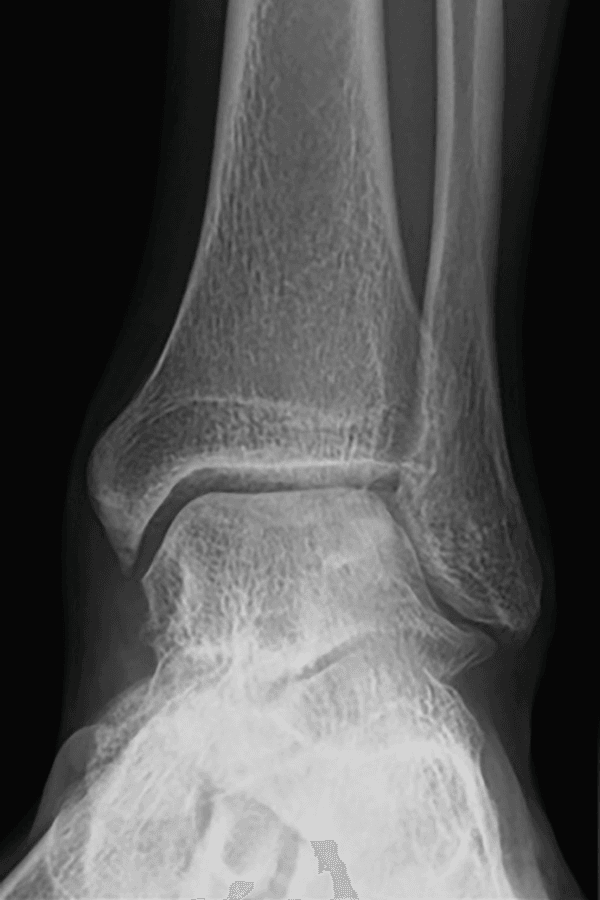
Persistent pain. Persistent pain points to missed pathology: an osteochondral lesion, sinus tarsi syndrome or a peroneal tear.
Postoperative Care
Rehab Protocol
Backslab or moonboot. Non-weight bearing or partial weight bearing. Wound healing is the priority.
CAM boot. Start range of motion (dorsiflexion and plantarflexion). Avoid inversion. Peroneal strengthening.
Lace-up brace. Proprioception training (balance board). Progress to jogging.
Sport-specific drills. Pass functional tests (hop test).
Outcomes and Prognosis
- Success Rate
- 80-90%
- Return to Sport
- 2-6 weeks
- Complications
- 20% Chronic Instability
- Success Rate
- 90-95%
- Return to Sport
- 3-4 months
- Complications
- 5% Nerve Injury
- Success Rate
- 70-80%
- Return to Sport
- 4-6 months
- Complications
- Stiffness/DJD
Guidelines, Registries & Global Practice
Global epidemiology. Lateral ankle sprain is the single most common musculoskeletal injury worldwide, with an estimated incidence of about 2-7 per 1000 person-years in the general population and far higher in court/jumping and field sports (basketball, volleyball, football/soccer). Around 40% present to emergency or primary care. Roughly 1 in 5 (about 20%) progress to chronic ankle instability with recurrent giving-way. There is no implant registry for soft-tissue ankle ligament surgery, so the evidence base is RCTs, cohorts and meta-analyses rather than national registries.
- Imaging
- X-ray only if bony tenderness or unable to weight bear 4 steps
- Acute Treatment
- n/a
- Surgery
- n/a
- Imaging
- Selective radiographs; MRI for persistent pain
- Acute Treatment
- Functional rehab, early weightbearing, proprioception
- Surgery
- Chronic mechanical instability after failed rehab
- Imaging
- Ottawa Rules to limit X-rays
- Acute Treatment
- RICE then early functional rehab; brief support
- Surgery
- Reserved for refractory chronic instability
- Imaging
- Stress US/MRI in chronic cases
- Acute Treatment
- Functional rehab; bracing for high-risk return
- Surgery
- Anatomic repair (Brostrom-Gould) first-line
Ready access to MRI and ultrasound, supervised physiotherapy, suture-anchor and internal-brace constructs, and increasing use of arthroscopic Brostrom in specialist centres.
Greater reliance on Ottawa Rules and clinical examination, functional rehabilitation with low-cost bracing/taping, and transosseous (drill-hole) Brostrom repair where suture anchors are unavailable. Outcomes of anatomic repair remain good without expensive implants.
Controversies & Areas of Uncertainty
Arthroscopic or open Brostrom. Arthroscopic repair shows comparable stability with faster early weightbearing, but there are no long-term trials. Open Brostrom-Gould remains the reference standard until durable data emerge.
Internal brace and suture tape. Augmentation may permit accelerated rehabilitation and protect weak tissue, but it adds cost and a non-anatomic, stiffer construct. The best evidence is for revision, hyperlaxity, high-demand athletes and obesity, not routine primary repair.
Surgery after an acute Grade III rupture. Pihlajamaki's RCT showed lower reinjury after acute repair but more osteoarthritis. The balance of evidence still favours functional treatment first, with surgery reserved for failure.
MCQ Practice Points
Q: What is the most common complication of Brostrom repair? A: Superficial Peroneal Nerve (SPN) injury (neurapraxia or injury). It runs in the subcutaneous tissue superficial to the extensor retinaculum.
Q: Which malleolar zones require X-ray according to Ottawa rules? A: Posterior edge or tip of medial/lateral malleolus (distal 6cm). Tenderness anterior to the malleolus (ATFL site) does NOT mandate X-ray.
Q: What is the primary cause of Brostrom failure? A: Unrecognized Hindfoot Varus. The deformity places constant strain on the repair. A calcaneal osteotomy may be required.
Q: In what order do the lateral ankle ligaments tear with increasing force? A: ATFL → CFL → PTFL. The ATFL is weakest (2mm thick, essentially capsular thickening) and tears first in plantarflexion. The CFL tears second in neutral/dorsiflexion. The PTFL only tears with complete dislocation (strongest ligament).
Q: How do you differentiate mechanical vs functional ankle instability? A: Mechanical instability = objective laxity on examination (positive Anterior Drawer/Talar Tilt). Functional instability = subjective giving way without gross laxity (proprioceptive/neuromuscular deficit). Treatment differs: functional requires rehab; mechanical may need surgical reconstruction if rehab fails.
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“25yo professional field-sport athlete, inversion injury 3 days ago. Swollen, positive anterior drawer. Previous sprains. Wants to play in the finals.”
“28F, recurrent sprains x4/year. Fails physio. MRI shows ATFL tear. Normal alignment.”
“Describe your Brostrom-Gould technique. Where are the dangers? How do you set tension?”
Anatomy
- ATFL: Weakest, injured first (Plantarflexion)
- CFL: Stronger, injured second (Dorsiflexion)
- SPN: Danger structure in approach
- PTFL: Only tears with dislocation (strongest)
Assessment
- Ottawa Rules: Posterior edge tenderness or inability to WB
- Anterior Drawer: ATFL (greater than 3mm diff)
- Talar Tilt: CFL (greater than 10 deg)
- Always palpate proximal fibula (Maisonneuve)
Management
- Acute: Functional Rehab (Brace, Move) superior to Cast
- Chronic: Brostrom-Gould (Anatomic Repair)
- Augmentation: Consider for Hyperlaxity/Heavy patients
- Prophylactic bracing reduces re-injury by 50%
Complications
- SPN Injury (Numbness)
- Recurrence (Varus heel?)
- Stiffness (Overtightening)
- Missed OCL or peroneal pathology
Evidence Base
Functional Treatment vs Immobilisation (Cochrane)
- 21 trials, 2184 participants; functional treatment favoured over immobilisation
- More patients returned to sport long-term (RR 1.86, 95% CI 1.22-2.86) and returned to work sooner (WMD 8.2 days)
- Less persistent swelling and less objective instability on stress X-ray with functional treatment
- Caveat: several differences lose significance when low-quality trials are excluded; this Cochrane review has since been withdrawn pending update, but its functional-over-immobilisation conclusion remains consistent with current society guidance
Anatomic Repair vs Tenodesis (RCT)
- Prospective randomised trial of 40 patients with chronic lateral instability
- Both procedures gave good or excellent stability in over 80% of patients
- Modified Brostrom achieved significantly higher Sefton functional scores than Chrisman-Snook
- Significantly more complications occurred after the non-anatomic Chrisman-Snook tenodesis
Prevention of Recurrent Ankle Sprains
- Critical review of 24 studies on ankle sprain prevention
- Taping, bracing and neuromuscular training all reduce recurrence (relative risks 0.2-0.5 vs control)
- Benefit is driven by previously injured athletes; effect on first-ever sprains is minimal
- Combining an external support (tape or brace) with neuromuscular training gives the best protection
Acute Surgery vs Functional Treatment (RCT)
- RCT of 51 young active men with acute Grade III rupture; mean 14-year follow-up
- All patients in both groups regained their pre-injury activity level; ankle scores and stress radiographs did not differ
- Reinjury was less frequent after surgery (1/15 vs 7/18; risk difference 32%)
- However Grade-II osteoarthritis was seen only in the surgical group (4/15 vs 0/18)
Arthroscopic vs Open Brostrom (Meta-analysis)
- 8 comparative studies, 408 patients (193 open, 215 arthroscopic)
- States that nearly 20% of acute sprains progress to chronic instability requiring surgery
- Arthroscopic repair gave modestly higher AOFAS scores and faster weightbearing (mean 9.0 vs 14.25 weeks)
- Complication rates, talar tilt and anterior drawer were comparable; open Brostrom-Gould remains the reference standard
Society Guidance on Ankle Sprain Care
- Use validated decision rules (Ottawa Ankle Rules) to limit unnecessary radiographs - the evidence behind them is Bachmann's systematic review (PMID 12595378), not any of these societies
- Functional rehabilitation with early weightbearing and proprioceptive training is first-line for acute sprains
- Reserve surgery for chronic mechanical instability that has failed structured rehabilitation
- Recommend bracing/taping plus neuromuscular training for athletes with recurrent sprains