Malignant Smooth-Muscle Sarcoma | Spindle Cells with Blunt-Ended Nuclei | Grade and Size Drive Outcome
- Leiomyosarcoma is a malignant tumour of smooth muscle and is one of the commonest adult soft tissue sarcomas
- Histology shows intersecting fascicles of spindle cells with blunt-ended (cigar-shaped) nuclei and eosinophilic cytoplasm
- Immunohistochemistry is positive for smooth-muscle markers - desmin, smooth muscle actin (SMA) and h-caldesmon
- Tumour grade (FNCLCC) and size are the dominant independent predictors of survival and distant recurrence
- Wide local excision is the curative treatment; chemotherapy is reserved for advanced or selected high-risk disease, not routine adjuvant use
- “Soft tissue leiomyosarcoma is biologically different from GIST - it is NOT KIT/CD117 driven and does not respond to imatinib
- “Retroperitoneal location carries a worse prognosis than extremity disease, largely because of size and margin difficulty
- “Lung is the dominant site of distant metastasis for extremity tumours; liver is important for retroperitoneal and vascular tumours
- “Adjuvant chemotherapy did NOT improve survival in the EORTC 62931 randomised trial of resected soft tissue sarcoma
Overview and Epidemiology
Leiomyosarcoma is a malignant tumour that shows differentiation toward smooth muscle, and it is one of the more common adult soft tissue sarcomas. In soft tissue it arises wherever smooth muscle exists: in the walls of blood vessels, in the dermal arrector pili muscles, in the viscera, and from poorly differentiated mesenchymal cells.
The three clinical groups. The three clinically important groups are:
- Somatic soft tissue of the extremity and trunk - a deep mass, often resectable, with the best access to wide margins
- Retroperitoneal and abdominal - large at diagnosis, with difficult margins and worse survival
- Large vessels, such as the inferior vena cava - arising from the vessel-wall smooth muscle, with distinct behaviour
Do not confuse soft tissue leiomyosarcoma with gastrointestinal stromal tumour (GIST). Historically many gut "leiomyosarcomas" were reclassified as GISTs once KIT/CD117 and DOG1 testing became available. True leiomyosarcoma is KIT-negative, is driven by smooth-muscle biology rather than KIT/PDGFRA mutations, and does not respond to imatinib. Modern leiomyosarcoma series deliberately exclude GISTs.
Who. Most patients are middle-aged to older adults, typically 50-70 years, with a slight overall female predominance that is strong in uterine disease. Leiomyosarcoma makes up roughly 10-20% of adult soft tissue sarcomas. Young patients are uncommon but possible, so consider it in any persistent deep mass.
Where. The extremity and trunk are the common somatic soft tissue site, and these tumours are often deep. The retroperitoneum and abdomen are frequent and prognostically poor, because the tumours are large and the margins hard to obtain. Vascular tumours of the inferior vena cava and other vessels form a distinct group arising from the vessel wall, and cutaneous or subcutaneous tumours are smaller, with a better prognosis when superficial.
Outcome by site. In the MSKCC series of primary leiomyosarcoma the three site groups behaved differently, and the differences are largely explained by size and margins:
- Approximate Share
- About half of primary cases
- Recurrence Pattern
- Distant recurrence around one third
- Prognostic Note
- Best access to wide margins; favourable group
- Approximate Share
- About 40%
- Recurrence Pattern
- Recurrence around half; late recurrence after 5 years
- Prognostic Note
- Worse disease-specific survival, driven by size and margins
- Approximate Share
- About 1 in 10
- Recurrence Pattern
- Recurrence around one quarter
- Prognostic Note
- Intermediate behaviour
Vascular leiomyosarcoma of the inferior vena cava. Leiomyosarcoma is the commonest primary malignant tumour of the inferior vena cava, arising from the vessel-wall smooth muscle, with a marked female predominance. It is classified by the level of caval involvement, which dictates presentation and reconstruction:
- Level I (lower, infrarenal) - below the renal veins. Often presents with leg swelling; the abundant collaterals that develop may allow ligation without reconstruction
- Level II (middle, renal-to-hepatic) - between the renal and hepatic veins, and the commonest level. Renal vein involvement matters, and reconstruction with a graft is often needed to preserve renal outflow
- Level III (upper, suprahepatic) - at or above the hepatic veins, up to the right atrium. Presents with Budd-Chiari syndrome (hepatic venous outflow obstruction); technically the hardest, and may need cardiopulmonary bypass
Management is en bloc resection of the involved caval segment with reconstruction (ring-reinforced PTFE or graft) or ligation, depending on level and collateral development. Prognosis is worse than extremity disease, and the liver and lung are the metastatic sites.
Pathophysiology and Molecular Biology
Genetics. Unlike synovial sarcoma or Ewing sarcoma, leiomyosarcoma has no single recurrent translocation and no pathognomonic fusion gene. It shows a complex, unstable karyotype instead: numerous copy-number changes and chromosomal rearrangements, widespread chromosomal gains and losses, and frequent loss of tumour-suppressor function (for example the RB1 and TP53 pathways). The biology is heterogeneous between uterine and non-uterine tumours.
Why there is no targeted drug. This genomic complexity is typical of the "non-translocation" pleomorphic sarcomas, and it explains why no targeted driver therapy, such as imatinib for GIST, exists. Nor is there a single confirmatory molecular test: the diagnosis combines characteristic histology with a smooth-muscle immunoprofile, set out in the next section, with GIST excluded by KIT and DOG1 for visceral lesions and dedifferentiated liposarcoma with smooth-muscle areas excluded in the retroperitoneum.
Growth and local behaviour. The tumour is an enlarging deep mass, often painless until large, so diagnostic delay is common and any deep mass over 5cm needs urgent imaging. Locally it is infiltrative, pushing and invading along fascial planes, which is why wide margins are essential to control local recurrence.
Spread. Metastasis is predominantly haematogenous and lymph-node spread is uncommon, so staging looks at the lungs, and at the liver for retroperitoneal and vascular tumours. Recurrence can occur beyond 5 years, especially in retroperitoneal disease, and long-term surveillance is mandatory.
Classification and Grading
Histological Diagnosis
Morphology. Leiomyosarcoma is built from long, sweeping fascicles of spindle cells that intersect at roughly right angles. The classic clue is the blunt-ended (cigar-shaped) nucleus, set in brightly eosinophilic, fibrillary cytoplasm; perinuclear vacuoles may be seen. Mitoses are present and atypia varies with grade: higher-grade tumours show pleomorphism and necrosis, with pleomorphic or dedifferentiated areas, and coagulative tumour necrosis contributes to the grade.
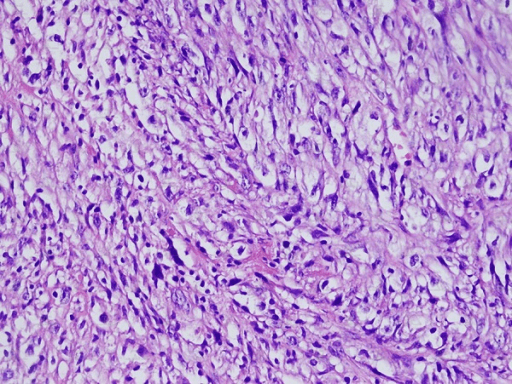
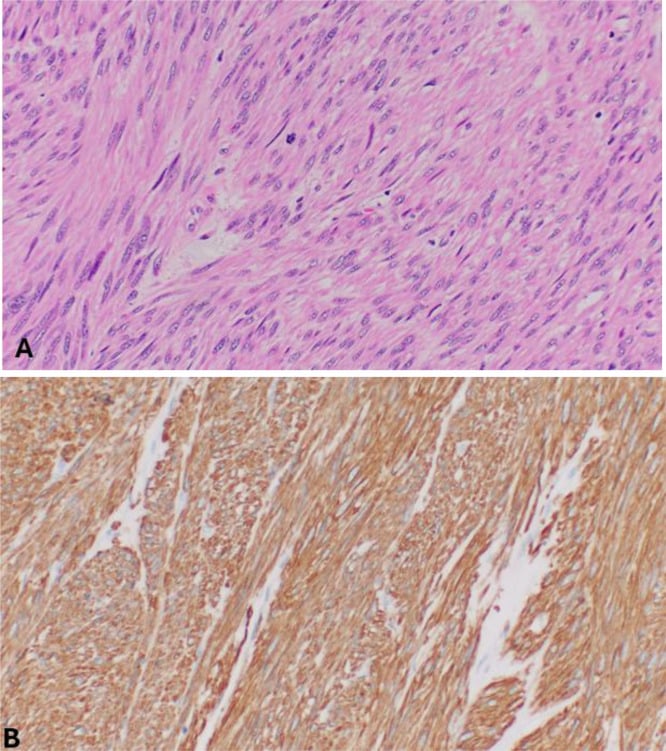
Immunohistochemistry. Smooth-muscle markers establish the line of differentiation, but no single marker is fully specific, so a panel plus morphology is required. Two or more smooth-muscle markers in a pleomorphic spindle-cell tumour are what separate leiomyosarcoma from undifferentiated pleomorphic sarcoma.
- Usual Result
- Positive in most cases
- Diagnostic Value
- Smooth-muscle line; sensitive but not specific
- Usual Result
- Positive in most cases
- Diagnostic Value
- Supports smooth-muscle differentiation
- Usual Result
- Positive
- Diagnostic Value
- More specific smooth-muscle marker
- Usual Result
- Negative
- Diagnostic Value
- Excludes GIST - a critical distinction
- Usual Result
- Occasionally focally positive
- Diagnostic Value
- Diagnostic trap - can mimic carcinoma or synovial sarcoma
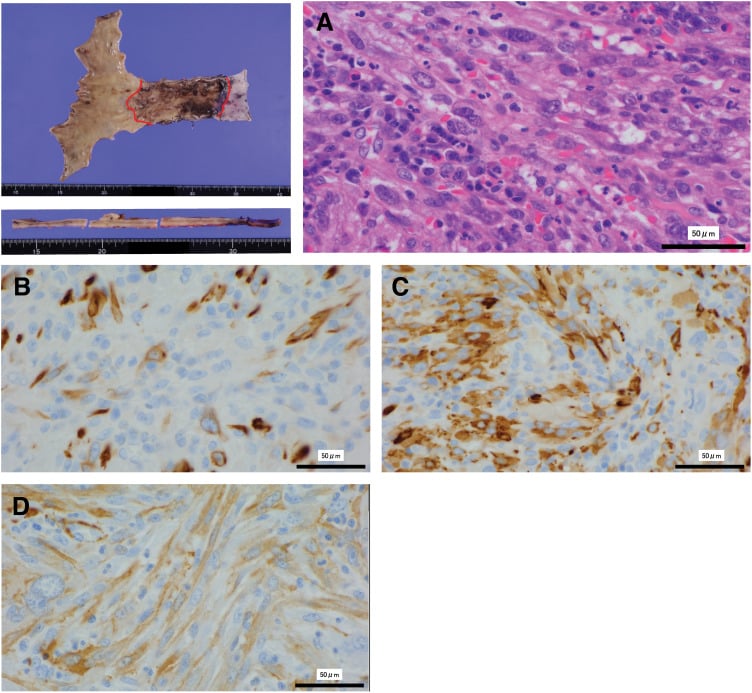
Differential diagnosis. The mimics are separated by site, morphology and a small number of discriminating tests:
- Distinguishing Features
- Gut wall location; spindle or epithelioid cells
- Key Discriminator
- KIT/CD117 and DOG1 positive; responds to imatinib (leiomyosarcoma does not)
- Distinguishing Features
- Retroperitoneal, may have well-differentiated fatty component
- Key Discriminator
- MDM2/CDK4 amplification; sample widely in the retroperitoneum
- Distinguishing Features
- Younger patient, near joints
- Key Discriminator
- SS18-SSX fusion; lacks h-caldesmon
- Distinguishing Features
- Arises from nerve or in NF1; tapered (not blunt) nuclei
- Key Discriminator
- S100 focal, loss of H3K27me3; smooth-muscle markers negative
- Distinguishing Features
- Bland nuclei, no/low mitoses, no necrosis, no infiltration
- Key Discriminator
- Absence of atypia, mitotic activity and tumour necrosis
The retroperitoneal trap. In the retroperitoneum a spindle-cell tumour with smooth-muscle areas may actually be a dedifferentiated liposarcoma, so always consider MDM2/CDK4 testing and sample the specimen widely before committing to a leiomyosarcoma diagnosis.
FNCLCC Histological Grading
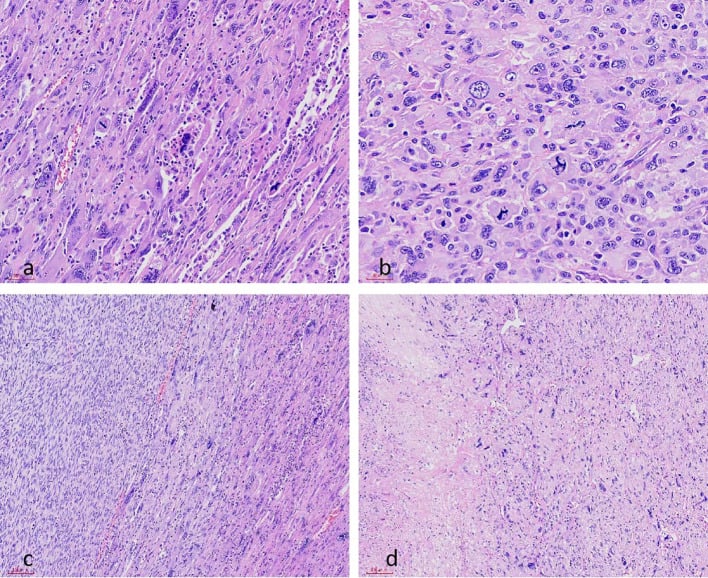
Grade is the single most important histopathological prognostic factor in soft tissue sarcoma. The FNCLCC (French Federation of Cancer Centres) system assigns a grade from a score built on three components, and the total score maps to grade 1, 2 or 3. High grade (grade 3) is independently associated with distant recurrence and death, and grade drives systemic risk far more than tumour size.
- What Is Scored
- How closely the tumour resembles normal adult mesenchymal tissue
- Score Range
- 1 to 3
- What Is Scored
- Mitoses per 10 high-power fields
- Score Range
- 1 to 3
- What Is Scored
- Extent of coagulative necrosis
- Score Range
- 0 to 2
- What Is Scored
- Sum of the three scores maps to grade
- Score Range
- Grade 1, 2 or 3
AJCC Staging (Soft Tissue Sarcoma)
- Grade
- Low (G1)
- Size / Spread
- 5cm or less
- General Outlook
- Favourable
- Grade
- Low (G1)
- Size / Spread
- Greater than 5cm
- General Outlook
- Favourable
- Grade
- High (G2-3)
- Size / Spread
- 5cm or less
- General Outlook
- Intermediate
- Grade
- High (G2-3)
- Size / Spread
- Greater than 5cm (size bands)
- General Outlook
- Higher risk of distant relapse
- Grade
- Any
- Size / Spread
- Nodal or distant metastasis
- General Outlook
- Poor
Retroperitoneal sarcomas use a separate AJCC size-banded staging scheme. Most clinically significant leiomyosarcomas are intermediate to high grade.
Clinical Presentation
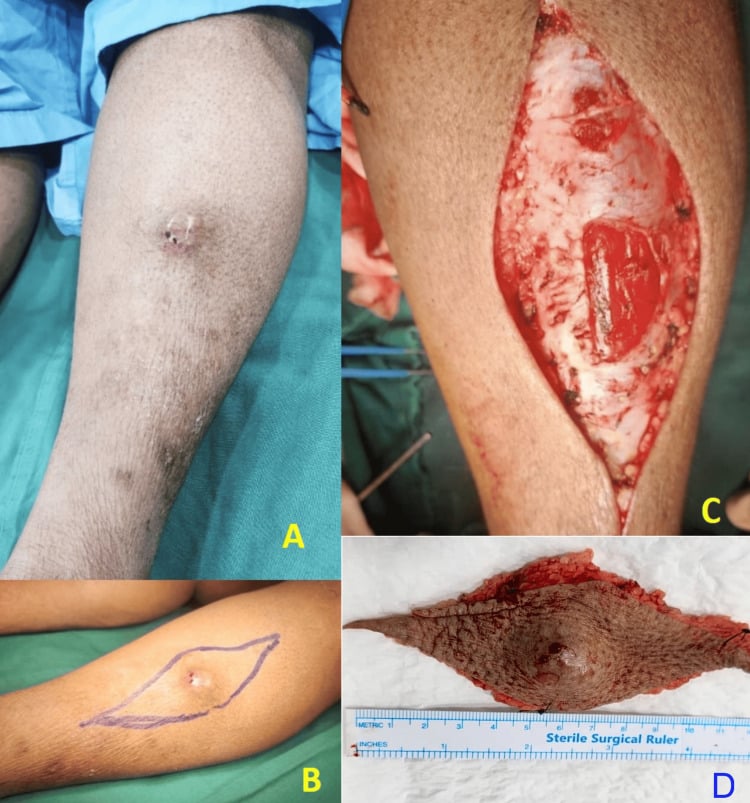
History. Presentation follows the site. An extremity or trunk tumour is an enlarging, often painless deep mass; a retroperitoneal tumour brings vague abdominal fullness, pain and mass effect; a vascular (IVC) tumour presents with leg swelling, Budd-Chiari features or abdominal pain; a cutaneous tumour is a small, firm dermal or subcutaneous nodule.
Red flags. Four features of any soft tissue mass demand attention:
- Size greater than 5cm
- Deep to fascia
- Increasing in size
- New pain in a previously painless lump
Any soft tissue mass that is larger than 5cm, deep to fascia, or enlarging should be regarded as a sarcoma until proven otherwise and referred to a specialist sarcoma service. Reassuring slow growth does not exclude leiomyosarcoma.
Examination. Inspect for the size of the mass and its relation to surface anatomy; skin changes are uncommon unless the tumour is cutaneous or fungating, and limb swelling or venous engorgement occur with vascular tumours. On palpation a deep tumour is firm and often fixed; record its relation to the neurovascular bundle, and tenderness, seen with large or nerve-involving tumours.
Function, nodes and chest. Test the joint range of motion if the mass is periarticular, the distal neurovascular status and the muscle power in the affected compartment. Examine the regional nodes (metastasis there is uncommon, but it is recorded) and the chest, since the lung is the dominant metastatic site. A complete baseline supports later treatment planning.
Investigations and Imaging
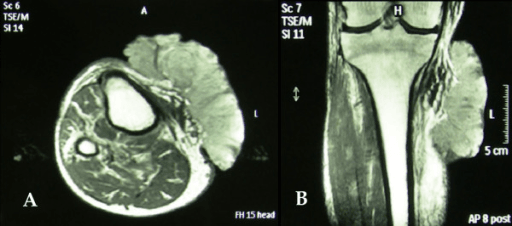
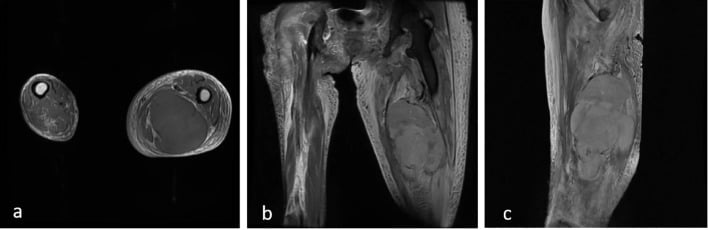
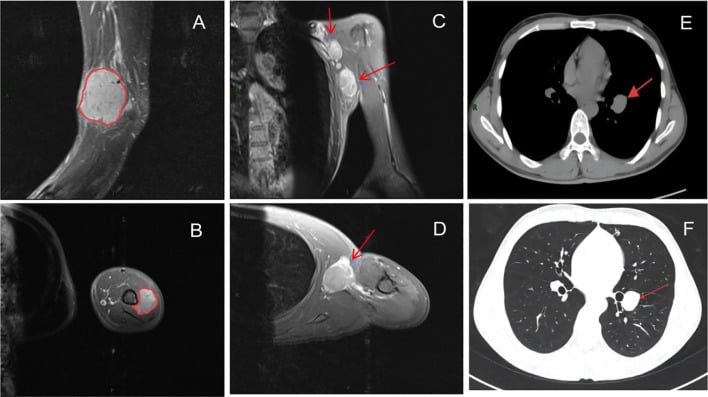
MRI is the gold standard for local staging. MRI of the whole anatomical region defines the tumour and its relations to the neurovascular bundle, bone and compartment boundaries. It is essential before biopsy and surgery, to plan the margins and the biopsy tract so that the tract lies within the resection field. Each sequence answers a question:
- T1-weighted - anatomy and tumour extent
- T2-weighted with fat suppression - heterogeneous high signal
- Post-contrast T1 with fat suppression - heterogeneous enhancement, and may show necrosis
CT for the body cavities and staging. CT chest detects lung metastases, the dominant site for extremity tumours. CT abdomen and pelvis defines retroperitoneal and vascular tumours and detects liver metastases, and CT-guided biopsy is often used for deep retroperitoneal lesions. Stage before definitive treatment so that surgery is not undertaken in unrecognised metastatic disease.
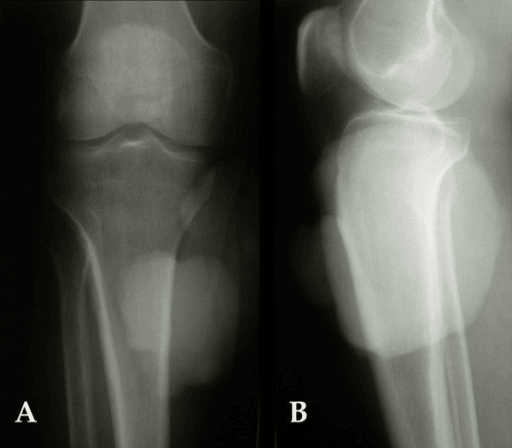
Plain radiographs are a screening step only. They may show a soft tissue density and exclude an obvious bony lesion, but they cannot characterise a soft tissue sarcoma and must be followed by MRI for any significant or deep mass.
Biopsy. The diagnosis is made on tissue, and an ill-planned biopsy jeopardises limb salvage.
- Image-guided core needle biopsy is the standard
- Plan the biopsy tract with the definitive surgeon so it can be excised en bloc
- Refer to a sarcoma centre before biopsy wherever possible
- Never perform an unplanned marginal ("shell-out") excision of an undiagnosed deep mass - it seeds tumour and jeopardises limb salvage
- Send tissue for full immunohistochemistry (desmin, SMA, h-caldesmon, plus KIT/DOG1 and MDM2/CDK4 where relevant)
Management
Wide local excision with negative margins is the only reliable curative treatment for localised leiomyosarcoma. Radiotherapy improves local control for deep or larger extremity tumours. Unlike synovial sarcoma, chemotherapy is not standard adjuvant therapy and is reserved for advanced or selected high-risk disease decided at a multidisciplinary meeting.
The three modalities. Surgery means wide excision with a cuff of normal tissue, the biopsy tract excised en bloc. Radiotherapy is given pre- or post-operatively for deep or larger extremity tumours or for close margins. Systemic therapy is doxorubicin-based for advanced disease and is not routine adjuvant treatment. These principles apply across leiomyosarcoma sites, modified by anatomy, and the intensity of each is set by site, resectability and stage:
- Surgery
- Limb-sparing wide excision (negative margins)
- Radiotherapy
- Pre- or post-operative for deep or larger / close-margin tumours
- Systemic Therapy
- Generally none; consider only in selected high-risk cases
- Surgery
- En bloc resection of tumour with involved adjacent organs
- Radiotherapy
- Role debated; selective use, often pre-operative
- Systemic Therapy
- Not routine adjuvant; individualised
- Surgery
- Vessel resection and reconstruction or ligation
- Radiotherapy
- Selective
- Systemic Therapy
- Individualised
- Surgery
- Metastasectomy for resectable oligometastatic lung disease
- Radiotherapy
- Palliative local control
- Systemic Therapy
- Doxorubicin-based first line; trabectedin, pazopanib and eribulin in later lines - but eribulin's survival benefit is liposarcoma-driven, not established for leiomyosarcoma
Systemic Agents in Advanced Leiomyosarcoma
- Agent(s)
- Doxorubicin (anthracycline) based
- Evidence Summary
- Standard backbone for metastatic soft tissue sarcoma
- Agent(s)
- Trabectedin
- Evidence Summary
- Phase III: improved progression-free survival versus dacarbazine in leiomyosarcoma/liposarcoma
- Agent(s)
- Eribulin
- Evidence Summary
- Phase III OS benefit was pooled, but the pre-planned histology subgroup showed it was driven by liposarcoma (HR 0.51); not established for leiomyosarcoma specifically
- Agent(s)
- Pazopanib (oral TKI)
- Evidence Summary
- PALETTE phase III: improved progression-free survival (4.6 vs 1.6 months) but no overall-survival benefit; standard option for non-adipocytic sarcoma such as leiomyosarcoma
- Agent(s)
- Adjuvant doxorubicin/ifosfamide
- Evidence Summary
- EORTC 62931: no relapse-free or overall survival benefit - not routine
Surgical Technique
Planning. Review the MRI and CT with radiology and the sarcoma MDT to define the tumour extent and its neurovascular relations, confirm the diagnosis and grade on the core biopsy, and plan the resection margins and the reconstruction. Mark the biopsy tract for en bloc excision, plan a longitudinal, extensile incision, and treat drain sites as contaminated. Anticipate the soft tissue defect, arrange flap or graft coverage if needed, and plan vascular reconstruction for vessel-based tumours; good planning underpins both oncological clearance and function.
Exposure and en bloc excision. Through a longitudinal incision incorporating the biopsy tract, gain proximal and distal neurovascular control and confirm the tumour extent against the MRI. Remove the tumour with a cuff of normal tissue and the biopsy tract. Preserve major vessels and nerves if they are not encased, and sacrifice or reconstruct structures where needed for clearance: preserving a nerve that runs through tumour converts a wide margin into a positive one.
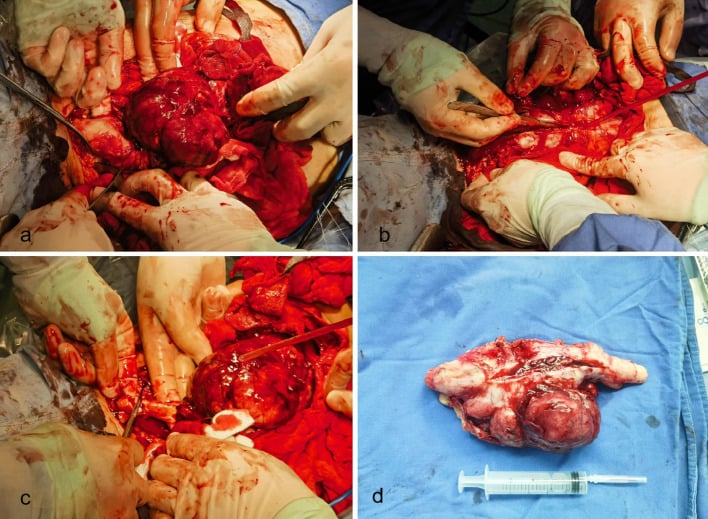
Specimen orientation. Mark the margins with sutures and orient the specimen for pathology, requesting assessment of all margins and the final grade.
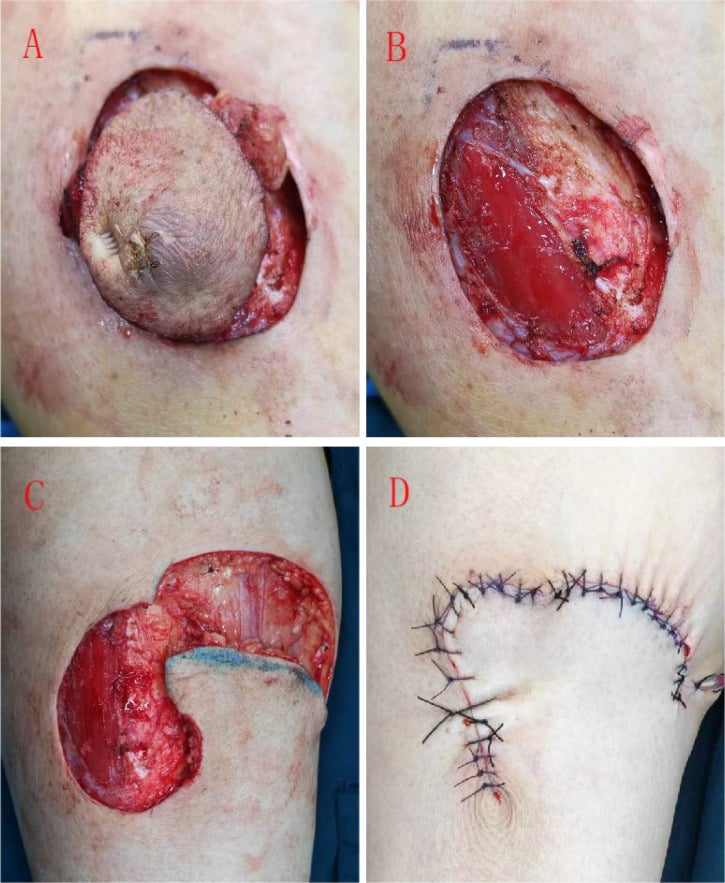
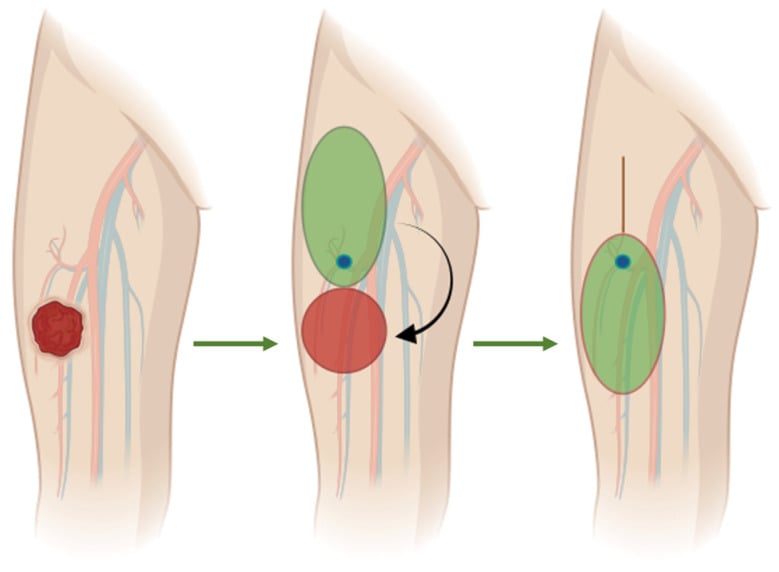
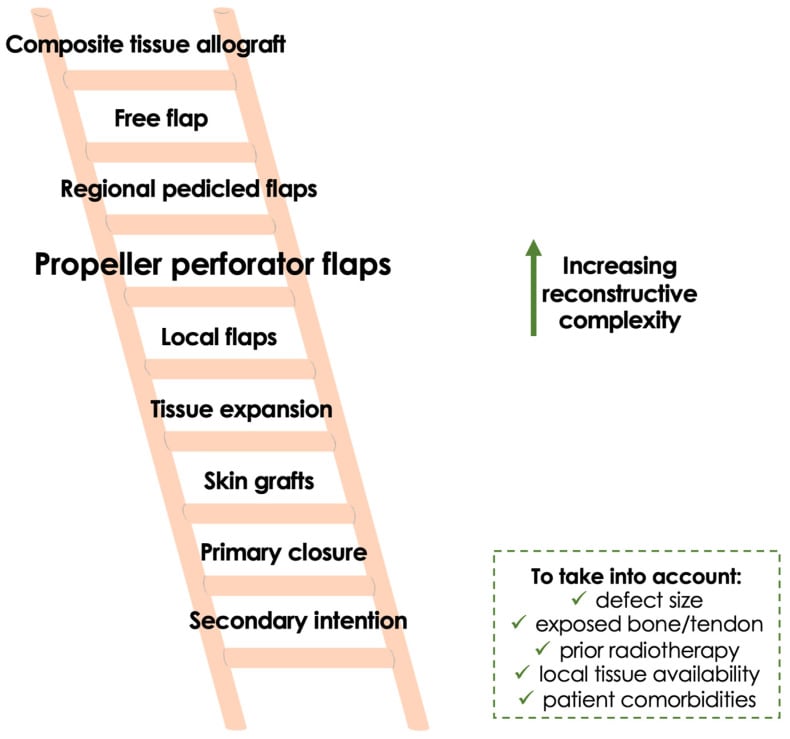
Reconstruction and closure. Close primarily, with a local flap or with free tissue transfer as required; drain the dead space and plan early rehabilitation, because functional reconstruction matters for quality of life. Reconstruction is planned before the excision so that margins are never compromised for closure. The technique is chosen on defect size, exposed bone or tendon, prior radiotherapy, local tissue availability and comorbidity, not on a surgeon's preference for a single method.
Margins and Re-excision
- Local Recurrence Risk
- Lowest
- Action
- Proceed; radiotherapy by risk
- Local Recurrence Risk
- Increased
- Action
- Consider re-excision or radiotherapy boost
- Local Recurrence Risk
- High
- Action
- Re-excision strongly preferred if feasible
- Local Recurrence Risk
- Very high
- Action
- Re-resection mandatory; consider amputation if unachievable
A positive margin is the strongest driver of local recurrence. Where feasible, re-excise to negative margins before adjuvant therapy rather than relying on radiotherapy alone to compensate.
Complications
- Driver
- Positive margins, high grade, large size
- Management
- Re-resection where feasible; radiotherapy
- Driver
- High grade, large size (lung dominant; liver for retroperitoneal/vascular)
- Management
- Systemic therapy; metastasectomy for resectable oligometastatic lung disease
- Driver
- Pre-operative radiotherapy, poor soft tissue coverage
- Management
- Wound care, negative-pressure therapy, flap coverage
- Driver
- Tumour proximity or deliberate sacrifice
- Management
- Reconstruction, physiotherapy, orthotics
- Driver
- Anthracycline (cardiotoxicity), ifosfamide
- Management
- Cumulative-dose limits, cardiac monitoring, supportive care
Prognosis and Outcomes
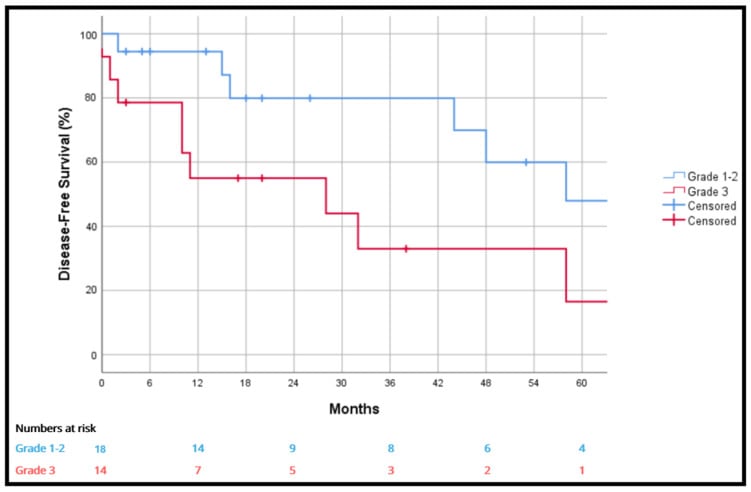
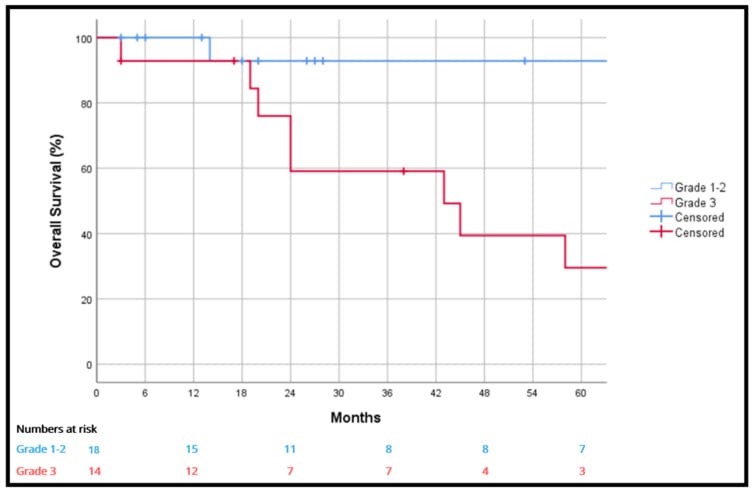
What decides outcome. In primary leiomyosarcoma, multivariate analysis shows that grade and size are the dominant independent predictors of disease-specific survival and distant recurrence, while margin status drives local recurrence. Grade, not size alone, is the variable that changes the systemic treatment discussion. Retroperitoneal tumours do worse than extremity tumours, but much of that difference is explained by their larger size and the difficulty of obtaining clear margins.
- Favourable
- Low grade (G1)
- Unfavourable
- High grade (G3)
- Favourable
- 5cm or less
- Unfavourable
- Greater than 5cm
- Favourable
- Extremity / superficial
- Unfavourable
- Retroperitoneal / deep
- Favourable
- Negative
- Unfavourable
- Positive
- Favourable
- Localised
- Unfavourable
- Metastatic at presentation
GRIMSAdverse Prognostic Factors
Hook:A GRIMS picture means a worse outcome - Grade, Retroperitoneal, Incomplete margins, Measurement large, Spread.
Depth in superficial disease. Superficial leiomyosarcoma is not one entity: the depth relative to the dermis splits it into two prognostically very different tumours, a classic examiner discriminator. Cutaneous (dermal) leiomyosarcoma arises from the arrector pili (pilar) smooth muscle in the dermis; it is essentially non-metastasising, the concern is local recurrence only, the prognosis is excellent and wide local excision is curative, so intensive systemic staging and surveillance are largely unnecessary. Subcutaneous leiomyosarcoma arises from vessel-wall smooth muscle in the subcutis; it behaves like a deep soft tissue sarcoma and does metastasise, to the lung, so it needs wide margins plus staging and long-term surveillance like other deep tumours.
The dividing line is the dermis. A tumour confined to the dermis behaves benignly as far as metastasis is concerned, whereas one that involves or sits beneath the subcutis carries true metastatic risk, and that dichotomy sets the extent of staging, follow-up and counselling.
Surveillance
Follow-up is front-loaded because the risk is, and it never quite ends because the disease can return late. The schedule is a protocol:
Surveillance Schedule
- Clinical review every 3-4 months
- Chest CT for lung metastases
- Local MRI for high-grade or marginal-resection tumours
- Clinical review every 6 months
- Periodic chest imaging
- Local imaging guided by symptoms and risk
- Annual review
- Continue chest (and abdominal for retroperitoneal/vascular) imaging
Leiomyosarcoma can recur late - distant or local recurrence beyond 5 years is well described, particularly for abdominal and retroperitoneal tumours. A written long-term surveillance plan is essential.
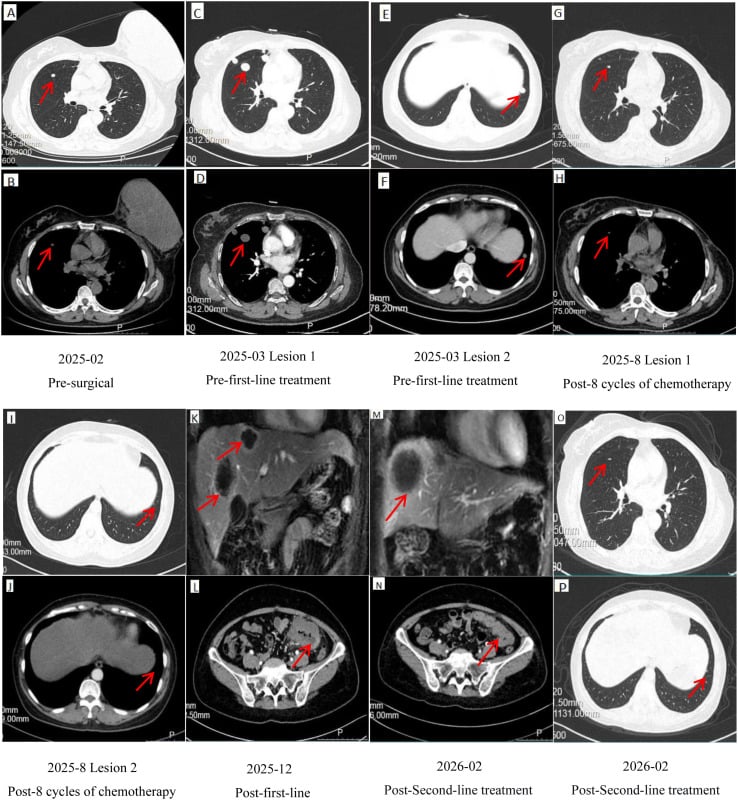
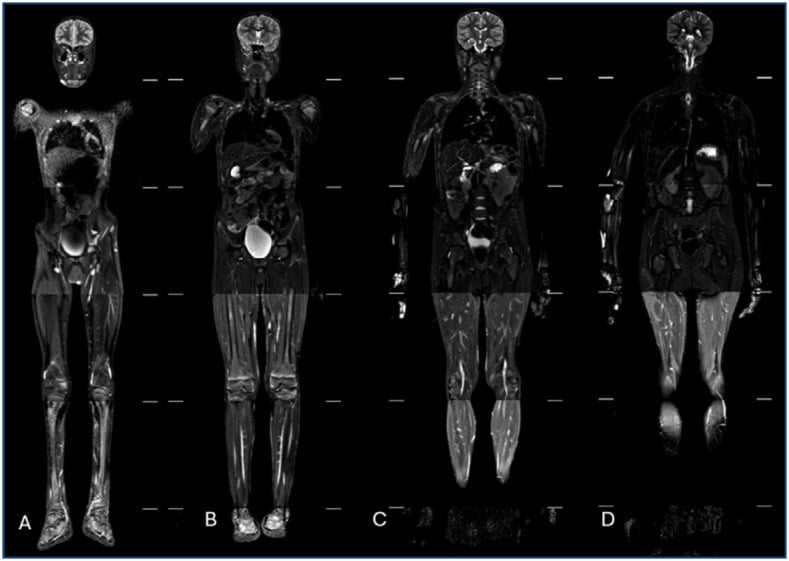
How the imaging is read. Response and progression are judged on the same modality at each timepoint, with identical lung and mediastinal windows, so that small changes in a lesion are measurable; that is how partial response and progression are actually determined. Whole-body MRI is a radiation-sparing follow-up option, particularly in younger patients.
Guidelines, Registries & Global Practice
Global Epidemiology
- Share of sarcomas: Roughly 10-20% of adult soft tissue sarcomas worldwide
- Age: Predominantly middle-aged and older adults (typically 50-70 years)
- Sex: Slight overall female predominance, strongest in uterine disease
- Reclassification effect: True leiomyosarcoma figures rose in clarity once GISTs were separated out
- Drivers: Grade and size dominate survival; margins drive local recurrence
- Site: Retroperitoneal disease does worse than extremity disease
- Spread: Haematogenous (lung dominant; liver for retroperitoneal/vascular); nodes rare
- Late recurrence: Recognised beyond 5 years, especially retroperitoneal
Side-by-Side Guidance from Major Societies
- Diagnosis
- Refer to sarcoma centre before biopsy; core biopsy with immunohistochemistry
- Local Treatment
- Wide excision plus radiotherapy for deep/larger extremity tumours
- Systemic Therapy
- Anthracycline-based for advanced disease; adjuvant individualised, not routine
- Diagnosis
- Image-guided core biopsy at a sarcoma centre; multidisciplinary review
- Local Treatment
- Limb-sparing wide excision with radiotherapy; re-excision for positive margins
- Systemic Therapy
- Doxorubicin first line; trabectedin and pazopanib in later lines for LMS; eribulin's survival benefit is liposarcoma-specific
- Diagnosis
- Mandatory specialist sarcoma MDT before definitive treatment
- Local Treatment
- Centralised surgery and radiotherapy at designated centres
- Systemic Therapy
- Chemotherapy reserved for selected high-risk or advanced cases
- Diagnosis
- Multidisciplinary diagnosis; exclude dedifferentiated liposarcoma
- Local Treatment
- En bloc resection of involved organs at high-volume centres
- Systemic Therapy
- Radiotherapy and chemotherapy individualised
Every major society agrees on three points regardless of region: any suspicious deep or enlarging soft tissue mass should be referred to a specialist sarcoma centre before biopsy, diagnosis should be made by planned core biopsy with immunohistochemistry, and definitive management should be set by a multidisciplinary sarcoma team. The main areas of disagreement are the thresholds for radiotherapy and for any systemic therapy.
High- vs Limited-Resource Practice Variation
- Routine immunohistochemistry (desmin, SMA, h-caldesmon) and exclusion of GIST/dedifferentiated liposarcoma
- Centralised sarcoma MDTs, limb salvage with reconstruction, and specialist radiotherapy
- Access to MRI staging, PET-CT and histology-specific agents (trabectedin; pazopanib for non-adipocytic disease)
- Pulmonary metastasectomy programmes for selected oligometastatic disease
- Diagnosis may rest on morphology and a limited immunohistochemistry panel
- Later presentation with larger tumours; higher amputation rates
- Restricted radiotherapy and systemic-therapy access
- Telepathology and regional referral networks help bridge expertise gaps
Applicable in any health system:
- Document the investigation pathway for any persistent or deep soft tissue mass (mitigates delayed diagnosis)
- Confirm pre-biopsy staging and that the biopsy was planned with the definitive surgeon
- Record exclusion of GIST and, in the retroperitoneum, of dedifferentiated liposarcoma
- Evidence of sarcoma MDT discussion before definitive treatment
- Informed consent covering recurrence and metastatic risk, possible organ or limb sacrifice
- A written long-term surveillance plan, given recognised late recurrence
Controversies and Areas of Uncertainty
Adjuvant chemotherapy. The benefit of adjuvant chemotherapy in resected soft tissue sarcoma remains unproven. The EORTC 62931 randomised trial of doxorubicin plus ifosfamide showed no relapse-free or overall survival benefit, so chemotherapy is not routine and is reserved for selected high-risk cases at MDT discretion.
Histology-driven systemic therapy. Second-line therapy is becoming histology-specific. Trabectedin genuinely has activity in leiomyosarcoma (and liposarcoma). Eribulin is the caution: its phase III survival benefit was driven by the liposarcoma subgroup and is not established for leiomyosarcoma, so quoting it as a leiomyosarcoma agent overstates the evidence. Pazopanib fills part of that gap for non-adipocytic sarcoma, though with progression-free and not overall-survival benefit, and the optimal sequencing remains debated.
Radiotherapy in retroperitoneal disease. Radiotherapy is well established for deep extremity sarcoma, but its role in the retroperitoneum is contested, with trial data showing limited benefit. Use is selective and individualised.
Lung metastasectomy. Resection of resectable, oligometastatic lung disease is widely practised and associated with longer survival in selected patients, but no randomised trial confirms a survival benefit. Patient selection is decisive.
MCQ Practice Points
Q: Which immunohistochemical profile confirms leiomyosarcoma? A: Positive for smooth-muscle markers - desmin, smooth muscle actin (SMA) and h-caldesmon - with characteristic spindle cells showing blunt-ended (cigar-shaped) nuclei. KIT/CD117 is negative, which helps exclude GIST.
Q: What are the dominant independent predictors of survival in primary soft tissue leiomyosarcoma? A: FNCLCC grade and tumour size. Margin status is the key driver of local recurrence. Retroperitoneal site is associated with worse outcome largely because of larger size and margin difficulty.
Q: Is adjuvant chemotherapy standard after resection of localised leiomyosarcoma? A: No. The EORTC 62931 randomised trial of doxorubicin plus ifosfamide showed no relapse-free or overall survival benefit. Chemotherapy is reserved for advanced disease or individualised high-risk cases.
Q: How does soft tissue leiomyosarcoma differ from GIST? A: Leiomyosarcoma is a true smooth-muscle tumour that is KIT-negative and does NOT respond to imatinib. GIST is KIT/DOG1 positive and is treated with imatinib. Many old gut "leiomyosarcomas" were reclassified as GISTs.
Q: What are the dominant metastatic sites in leiomyosarcoma? A: Lung for extremity tumours; liver is also important for retroperitoneal and vascular tumours. Spread is predominantly haematogenous and lymph-node metastasis is uncommon.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 62-year-old man has a 7cm deep, firm, painless mass in the posterior thigh that has been slowly enlarging over six months. How would you investigate and manage him?”
“A 58-year-old woman has a 14cm retroperitoneal mass on CT. Core biopsy reports a high-grade spindle-cell tumour. How do you confirm the diagnosis and plan treatment, and how does this differ from an extremity tumour?”
“A 55-year-old man treated two years ago for a high-grade extremity leiomyosarcoma now has three FDG-avid nodules confined to the right lung on surveillance CT. How do you proceed, and what systemic options exist if surgery is not appropriate?”
Key Epidemiology
- Malignant smooth-muscle sarcoma; roughly 10-20% of adult soft tissue sarcomas
- Typical age 50-70 years, slight overall female predominance
- Three groups: extremity/trunk, retroperitoneal/abdominal, and vascular (e.g. IVC)
- Distinct from GIST - true leiomyosarcoma is KIT-negative
Diagnosis (Morphology plus IHC)
- Intersecting fascicles of spindle cells with blunt-ended (cigar-shaped) nuclei
- Brightly eosinophilic, fibrillary cytoplasm
- Positive: desmin, smooth muscle actin (SMA), h-caldesmon
- Negative KIT/DOG1 excludes GIST; check MDM2/CDK4 in retroperitoneum to exclude dedifferentiated liposarcoma
Grading and Staging
- FNCLCC grade = differentiation + mitotic count + necrosis, mapped to grade 1-3
- Grade is the most important histopathological prognostic factor
- AJCC staging by grade, size and metastasis (separate scheme for retroperitoneum)
- Most clinically significant tumours are intermediate to high grade
Investigation and Biopsy
- MRI is the gold standard for local staging of the mass
- CT chest for lung metastases; CT abdomen/pelvis (and liver) for retroperitoneal/vascular tumours
- Image-guided core biopsy with tract planned by the definitive surgeon
- Never shell out an undiagnosed deep mass - refer to a sarcoma centre first
Treatment
- Wide local excision with negative margins is the curative backbone
- Radiotherapy improves local control for deep or larger extremity tumours
- Adjuvant chemotherapy is NOT routine - EORTC 62931 showed no survival benefit
- Advanced disease: doxorubicin first line, then trabectedin or pazopanib; eribulin is a liposarcoma drug
- Metastasectomy for selected resectable oligometastatic lung disease
Adverse Prognostic Factors (GRIMS)
- Grade high (FNCLCC 3)
- Retroperitoneal / deep site
- Incomplete (positive) margins
- Measurement large (size over 5cm)
- Spread (metastatic at presentation)
Prognosis and Surveillance
- Grade and size are the dominant independent predictors of survival
- Margin status drives local recurrence
- Spread is haematogenous (lung; liver for retroperitoneal/vascular); nodes rare
- Late recurrence beyond 5 years is recognised - long-term surveillance is mandatory
Evidence Base and Key Studies
Predictors of Survival and Recurrence in Primary Leiomyosarcoma
- 353 patients with primary resectable leiomyosarcoma (GISTs excluded) from a prospective database, 1982-2006
- Distribution: 48% extremity, 41% abdominal/retroperitoneal, 11% truncal; 75% high grade, median size 6.0cm
- On multivariate analysis only high grade and size were independent predictors of disease-specific survival
- Late recurrence beyond 5 years occurred in 9% of abdominal/retroperitoneal and 4% of extremity tumours
Prognostic Factors in 1,041 Localised Extremity Soft Tissue Sarcomas
- 1,041 adults with localised extremity soft tissue sarcoma treated at a single institution, prospective data
- 5-year survival 76%; high grade, large size and deep location were adverse for disease-specific survival
- Leiomyosarcoma histology was an independent adverse factor for both distant recurrence and disease-specific survival
- Microscopically positive margins independently predicted local recurrence and tumour-related death
Histological Grading of Soft Tissue Sarcomas (FNCLCC and MIB-1)
- Reviews histological grading as the most important histopathological prognostic factor in soft tissue sarcoma
- Describes the FNCLCC system based on differentiation, mitotic count and tumour necrosis
- Discusses the MIB-1 (Ki-67) proliferation index as an adjunct to grading
- Highlights pitfalls in grade assessment and its relationship to other clinicopathological factors