Hammer Toe | Claw Toe | Mallet Toe | Flexor-Extensor Imbalance
- Flexible vs rigid deformities determine surgical approach - flexible responds to soft tissue, rigid needs bony correction
- Hammer toe affects PIPJ primarily; claw toe involves all three joints with MTPJ hyperextension
- Mallet toe is isolated DIPJ flexion (often traumatic FDL rupture or footwear-related)
- Flexor to extensor transfer (Girdlestone-Taylor) corrects dynamic claw deformity by rebalancing forces
- PIPJ fusion is gold standard for fixed hammer/claw toe - provides stable, pain-free toe in functional position
- “Distinguish flexible (passively correctable) from rigid (fixed) deformities - dictates treatment
- “Claw toe commonly seen in cavus foot, CMT, or diabetes - always examine foot posture and neurology
- “MTPJ synovitis and plantar plate insufficiency cause crossover toe and require MTPJ-level intervention
- “Flexor to extensor transfer only works if MTPJ is passively reducible - otherwise add MTPJ capsule release
Overview and Epidemiology
Lesser toe deformities are common acquired foot problems that cause pain, skin breakdown and functional limitation. They run from flexible, dynamic deformities that respond to soft-tissue procedures to fixed, rigid contractures that need bony surgery. Knowing the biomechanics and exactly which joints are involved is what selects the right operation and makes the correction last.
Who. About 80% of patients are women, which is put down to footwear and ligament laxity, and most are between 30 and 60. High heels, a narrow toe box and shoes that are too short all contribute.
Heredity. The deformity is strongly familial: heritability of lesser toe deformity was 0.49-0.90 in the Framingham Foot Study. That is a population variance statistic, not an individual's risk.
Associations. A cavus foot predisposes to claw toes, and rheumatoid arthritis, diabetes and neurological disease are the systemic associations. The cause guides treatment, so change the footwear, treat the cavus deformity and manage the inflammatory arthritis.
Natural history. Deformities progress from flexible to rigid over years to decades. Early intervention preserves joint motion.
Pathophysiology and Mechanisms
The intrinsic muscles. The lumbricals arise from the FDL tendons and insert into the lateral band of the extensor hood; the plantar and dorsal interossei insert in a similar way. Both groups flex the MTPJ and extend the PIPJ and DIPJ, the opposite of the extrinsic muscles, and the interossei also give mediolateral stability. They are the key stabilisers of the toe, and they are what prevents a claw deformity.
The flexors and the extensor. FDL flexes the DIPJ primarily and the PIPJ secondarily. FDB flexes the PIPJ and inserts on the middle phalanx. Both cross plantar to the MTPJ and can hyperextend it if unopposed. EDL inserts into the extensor hood and extends all three joints; when it dominates it hyperextends the MTPJ and stretches the plantar plate. Balance between flexors and extensors holds the toe in neutral.
When the balance fails. When the intrinsics weaken, in a cavus foot, in neuropathy or under chronic overload, FDL, FDB and EDL dominate and produce the classic claw: MTPJ hyperextension with flexion of the interphalangeal joints. Other drivers contribute:
- Chronic footwear pressure - tight shoes force the toes into a flexed posture
- MTPJ synovitis - inflammatory synovitis weakens the plantar plate
- Progressive contracture - capsular and tendinous contractures become fixed
Classification Systems
A lesser toe deformity is described two ways: by the joints it involves, which names it, and by whether it corrects passively, which decides the treatment.
- MTPJ
- Neutral (0-10° extension)
- PIPJ
- Neutral (0-10° flexion)
- DIPJ
- Neutral
- Primary Imbalance
- Balanced intrinsic/extrinsic
- Clinical Features
- -
- MTPJ
- Normal or slight hyperextension
- PIPJ
- Flexed 30-90° (main deformity)
- DIPJ
- Neutral or extended
- Primary Imbalance
- FDB/FDL dominance over intrinsics
- Clinical Features
- Dorsal PIPJ corn, tip may contact ground
- MTPJ
- Hyperextended 30-60°
- PIPJ
- Flexed 45-90°
- DIPJ
- Flexed 30-60°
- Primary Imbalance
- EDL + FDL dominate, intrinsics absent
- Clinical Features
- Dorsal corns at PIPJ, metatarsalgia, elevated toes
- MTPJ
- Normal
- PIPJ
- Normal
- DIPJ
- Flexed 30-90°
- Primary Imbalance
- FDL tightness or rupture
- Clinical Features
- Tip corn, nail dystrophy, often traumatic
- MTPJ
- Dorsal subluxation
- PIPJ
- Variable flexion
- DIPJ
- Variable
- Primary Imbalance
- Plantar plate attenuation or rupture
- Clinical Features
- Medial deviation, overlaps adjacent toe
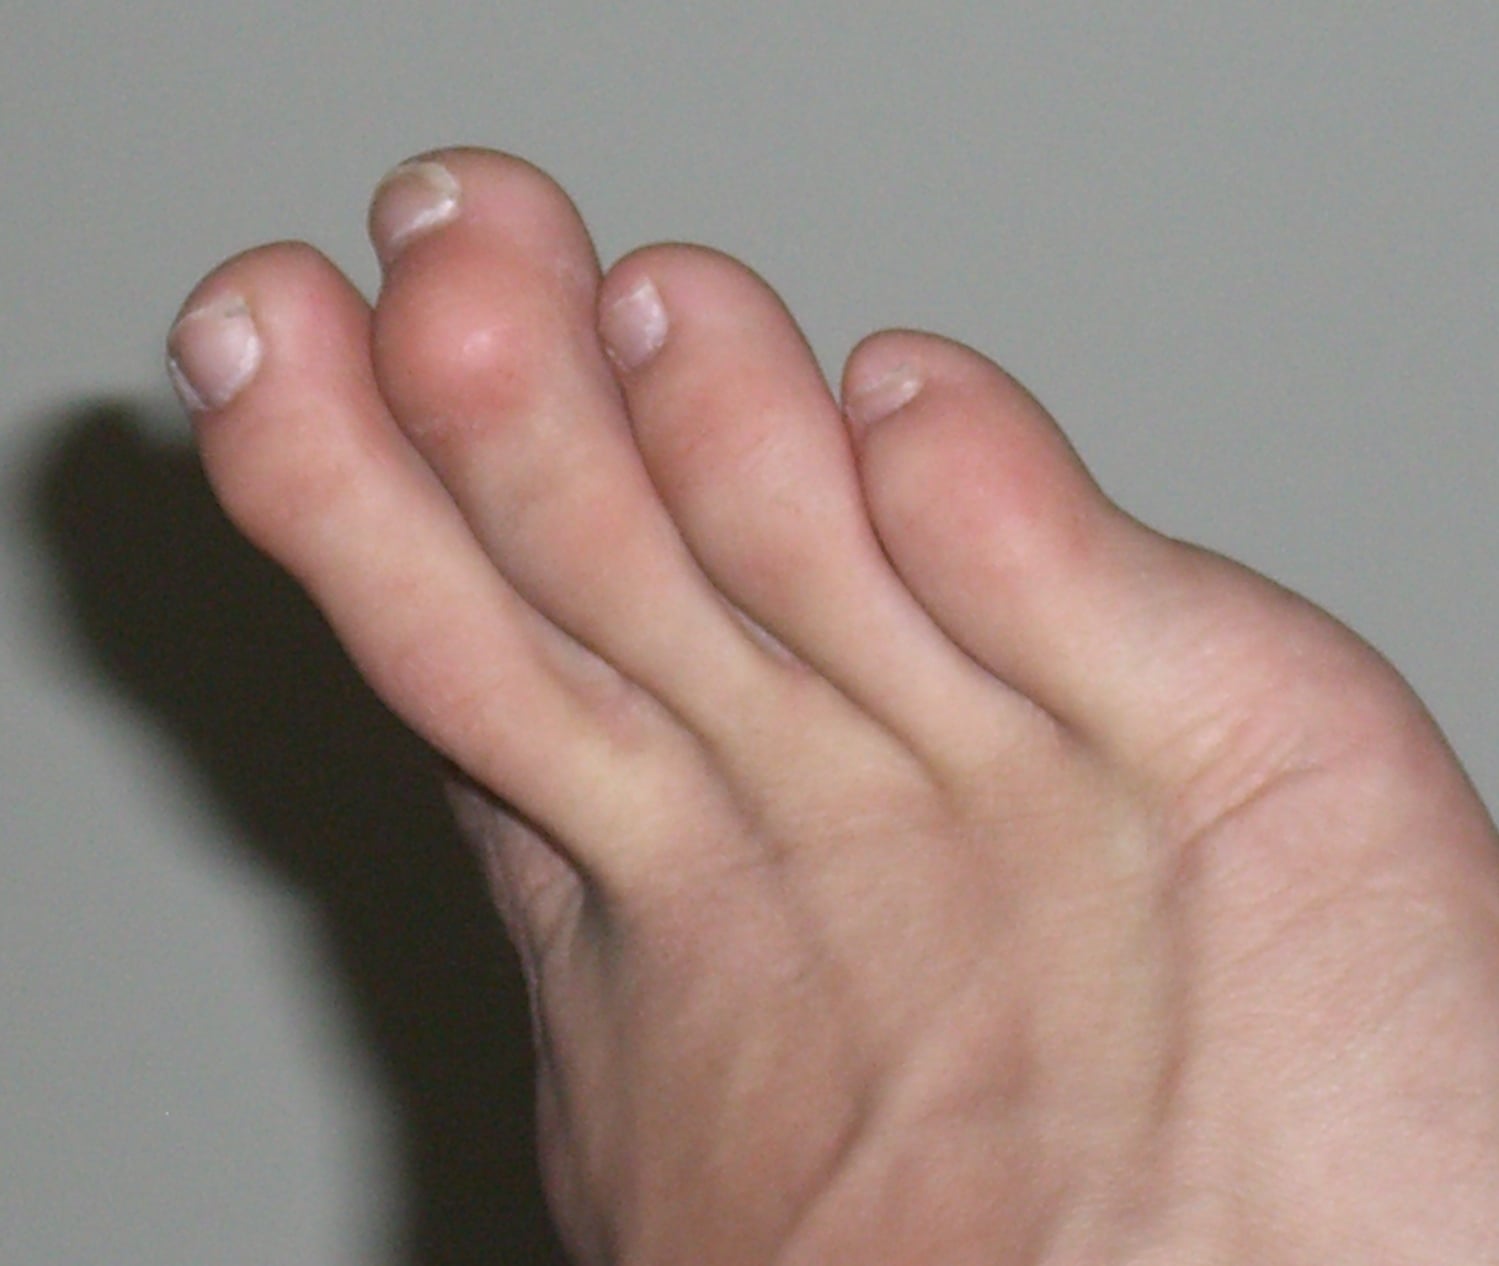
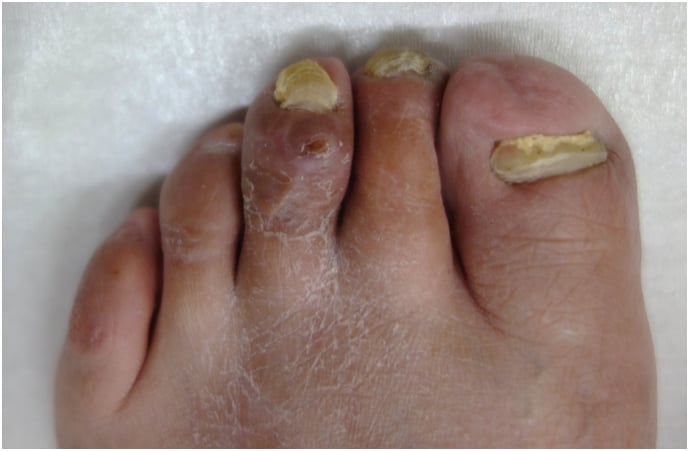
Hammer toe versus claw toe. A hammer toe has a relatively neutral MTPJ with isolated PIPJ flexion. A claw toe adds MTPJ hyperextension, the key differentiator, to flexion at both interphalangeal joints. Claw toes are often bilateral and are associated with cavus foot or neuromuscular disease. Examiners will show images or clinical photographs: identify the MTPJ position first.
Mallet toe. Isolated DIPJ flexion with a normal PIPJ and MTPJ. It can be traumatic, an FDL rupture from stubbing the toe, which may present acutely with pain and inability to flex the DIPJ actively. Or it can be chronic, from tight footwear and FDL contracture, developing gradually under pressure from the toe box; it is usually flexible early.
Clinical Assessment
History. Start with where it hurts: a dorsal corn over the PIPJ, pain at the tip of the toe, or metatarsalgia. Then establish the footwear (tight shoes, high heels, chronic pressure), whether the problem is acute or chronic and flexible or rigid, and what it costs the patient in walking and shoe wear. Numbness points to neuropathy; ask about diabetes, rheumatoid arthritis and Charcot-Marie-Tooth disease. The history reveals the underlying aetiology and the pattern of progression.
Examination. Inspect standing for the deformity pattern, the MTPJ position and the skin. Test flexibility and MTPJ stability, check sensation, pulses and capillary refill, and examine the whole foot for cavus deformity, hindfoot alignment and ankle range of motion.
- Technique
- Manually straighten the toe with MTPJ, PIPJ and DIPJ held neutral
- Positive Finding
- Deformity fully corrects, or persists despite force
- Interpretation
- Corrects: flexible deformity, soft tissue procedure appropriate. Persists: rigid contracture, requires bony surgery
- Technique
- Stabilise metatarsal head, translate proximal phalanx dorsally
- Positive Finding
- Excessive dorsal translation (more than 2mm)
- Interpretation
- Plantar plate insufficiency - crossover toe developing
- Technique
- Palpate plantar aspect of metatarsal heads during stance
- Positive Finding
- Prominent, painful metatarsal head
- Interpretation
- Metatarsalgia from MTPJ hyperextension - address in surgery
Ankle dorsiflexion test (Silverskiold modification). Passively dorsiflex the ankle and watch the toes. If the claw reduces, the deformity is driven by gastrocnemius tightness and FDL/FDB pull; it is flexible and suits flexor tendon release or transfer. If it persists whatever the ankle position, the deformity is fixed at the joint and needs arthrodesis or arthroplasty.
Bilateral claw toes in a young patient suggest underlying neuromuscular disease. Look for pes cavus, a clawed hallux, weak intrinsic muscles and sensory change. Common causes include Charcot-Marie-Tooth disease, polio sequelae, spinal dysraphism and hereditary motor-sensory neuropathy, and the neurological work-up under Investigations is indicated. The underlying cavus and muscle imbalance must be addressed: isolated toe correction will fail without treating the driving pathology.
Investigations
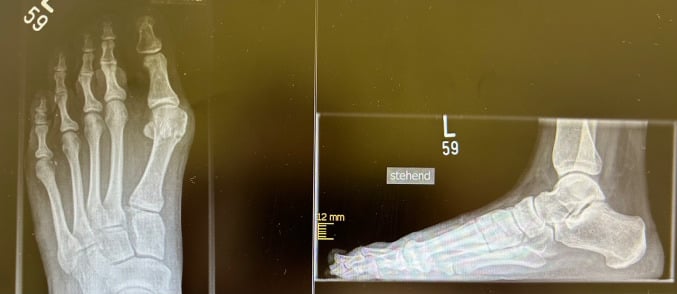
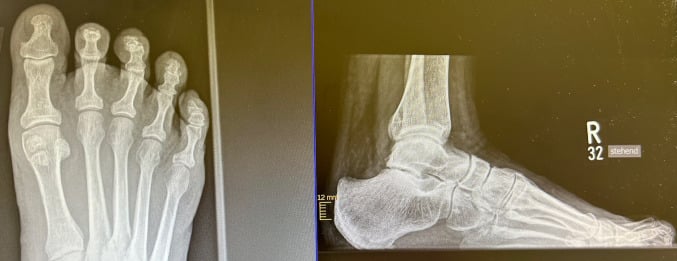
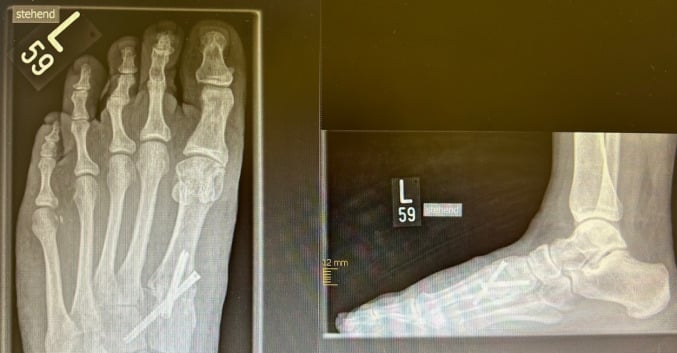
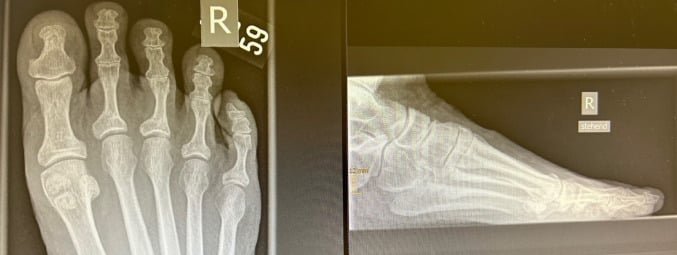
Weight-bearing radiographs. AP, lateral and oblique views of the whole foot are first line, because weight-bearing films show the true functional deformity and how load is distributed across the metatarsals. The AP shows the key pathology, and the lateral shows the degree of PIPJ and DIPJ flexion and confirms the MTPJ dorsiflexion angle. Look for:
- MTPJ alignment and subluxation, the proximal phalanx sitting dorsal to the metatarsal head
- IP joint arthritis or deformity, PIPJ flexion creating a "V" or "Z" shape
- The metatarsal parabola and relative metatarsal lengths
- Pes cavus or planus
- Hallux valgus or rigidus
The long second metatarsal. A long second metatarsal (Morton's foot) increases the risk of a second toe hammer or crossover deformity.
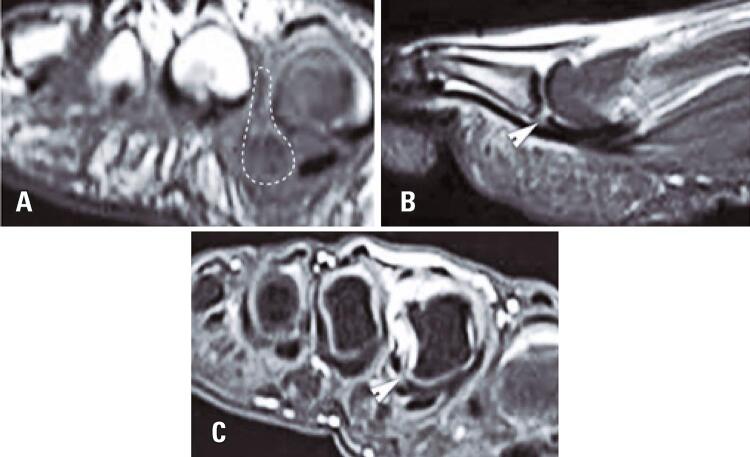
MRI. Indicated when MTPJ pathology is suspected: a plantar plate tear, MTPJ synovitis or a soft-tissue mass. It delineates the plantar plate tear in a crossover toe and so guides repair versus reconstruction. It shows:
- Plantar plate integrity (T2 hyperintensity, discontinuity)
- MTPJ synovitis and effusion
- Collateral ligament injury
- Flexor tendon pathology
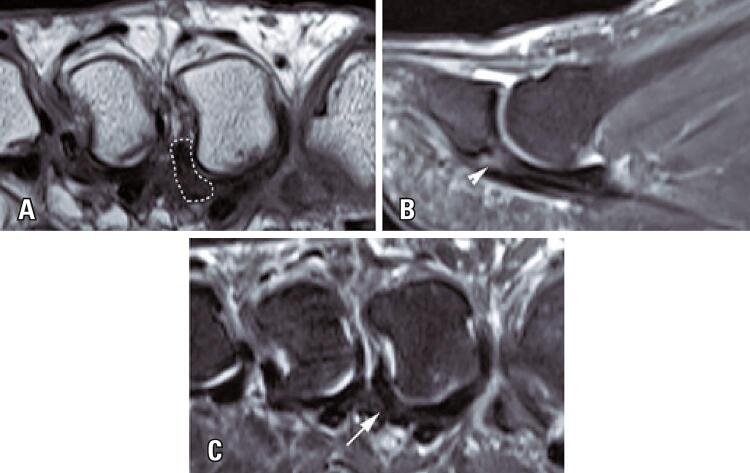
Neurological work-up. When a neuromuscular cause is suspected, identifying it prevents surgical failure and guides comprehensive treatment:
- EMG and nerve conduction studies to identify the peripheral neuropathy pattern
- MRI spine to rule out spinal dysraphism, tethered cord or syrinx
- Genetic testing for CMT if there is a family history and a progressive cavovarus foot
Differential Diagnosis
Not every flexed or painful lesser toe is a primary structural deformity. Getting the diagnosis wrong means operating on the wrong structure, resecting a PIPJ, for example, when the real problem is an interdigital neuroma or MTPJ synovitis.
- Key Distinguishing Features
- Fixed joint posture (PIPJ, all-joint, or DIPJ); dorsal or tip corn
- Investigation
- Weight-bearing radiographs; clinical flexibility test
- Management Pointer
- Soft tissue vs bony correction by flexibility
- Key Distinguishing Features
- MTPJ pain, dorsal drawer positive, deviation/overlap, V-sign
- Investigation
- MRI or ultrasound of plantar plate
- Management Pointer
- Plantar plate repair plus or minus Weil osteotomy
- Key Distinguishing Features
- Burning interspace pain, Mulder click, no fixed joint deformity
- Investigation
- Ultrasound or MRI; diagnostic injection
- Management Pointer
- Footwear, injection, excision - not toe surgery
- Key Distinguishing Features
- Localised MTP head pain, often 2nd ray, adolescent/young adult
- Investigation
- Radiograph - flattening/sclerosis of metatarsal head
- Management Pointer
- Offloading; joint debridement or osteotomy if advanced
- Key Distinguishing Features
- Polyarticular, synovitis, MTPJ erosions, bilateral
- Investigation
- Inflammatory markers, autoantibodies, radiographs
- Management Pointer
- Medical control first; reconstruction when quiescent
- Key Distinguishing Features
- Bilateral claw toes, pes cavus, weak intrinsics, sensory change
- Investigation
- EMG/NCS, MRI spine, genetic testing
- Management Pointer
- Treat cavus and imbalance, not just the toes
- Key Distinguishing Features
- Focal swelling, nail change, erythema, no joint contracture
- Investigation
- Examination, swab/imaging if infection suspected
- Management Pointer
- Treat the lesion or infection directly
Management Algorithm
Who it suits. Non-operative management is the first line for all deformities. It is indicated for:
- Asymptomatic or mildly symptomatic deformities
- Flexible deformities without significant pain
- Patients unwilling or unfit for surgery
- Early-stage crossover toe (Grade 0-I)
These are four parallel measures selected by what is causing the symptom, not four steps in a course. Footwear addresses the shoe pressing on the deformity, padding addresses the corn, taping addresses a flexible deformity only, and activity modification addresses the load. Test flexibility first - the push-up test tells you whether taping and splinting have any chance at all, because none of these measures can reverse a fixed contracture.
Footwear, the foundation. A wide toe box accommodates the deformity and reduces pressure, a low heel reduces forefoot pressure and FDL pull, soft uppers spare the dorsal corn, and adequate length stops the toes jamming into a flexed posture. Around 70% of mild cases improve with shoe modification alone, a high yield for an intervention that costs nothing surgical.
Padding and orthoses, for symptoms only. Dorsal pads protect PIPJ corns from the shoe, silicone or gel sleeves cushion the deformity, toe spacers separate the toes and reduce interdigital corns, metatarsal pads offload the metatarsal heads in metatarsalgia, and arch supports support the medial longitudinal arch in a flexible flatfoot. Padding relieves the symptom without correcting the deformity: it changes where the shoe presses, not where the toe sits. In an insensate diabetic foot a badly placed pad becomes a pressure point the patient cannot feel, so padding must be reviewed rather than simply prescribed.
Taping and splinting, for flexible deformities only. Buddy taping to the adjacent normal toe, dorsal night splints to hold IP extension, and plantar flexion taping to pull the MTPJ into plantarflexion. Taping works only while the deformity is still passively correctable and demands sustained compliance, so long-term efficacy is limited. It holds a position; it does not lengthen a contracted structure.
Activity modification. Avoid prolonged walking or standing, swap impact activities for swimming and cycling, use rest and ice for acute flares, and NSAIDs for the inflammatory pain of MTPJ synovitis. This reduces symptoms but does not alter the progression from flexible to rigid.
Conservative management is palliative, not curative. Flexible deformities may stabilise with footwear and padding, but rigid contractures will not reverse, and once a fixed contracture develops only surgical correction can restore alignment. Conservative care buys time and reduces symptoms, but most symptomatic rigid deformities eventually require surgery, and the patient's expectations must be realistic. Surgery is indicated when conservative measures fail.
Surgical Technique
Girdlestone-Taylor procedure. Indicated for a flexible claw toe with dynamic imbalance, a passively reducible MTPJ and no fixed PIPJ contracture. FDL is harvested, rerouted dorsally through the proximal phalanx and sutured to the extensor hood, which converts the deforming flexor force into a correcting one that plantarflexes the MTPJ and extends the IP joints.
Surgical Steps
Make a 2cm longitudinal plantar incision at the level of the MTPJ crease and identify FDL running deep to FDB. Transect it as far distally as possible, preferably at the DIPJ level, and deliver it proximally into the wound with a haemostat. Distal transection gives enough tendon for the transfer and avoids tethering.
Through a 2cm longitudinal dorsal incision over the proximal phalanx, retract EDL and the extensor hood laterally. Drill two parallel 2.0mm holes from plantar-lateral to dorsal-medial, aiming toward the extensor hood insertion on the mid-proximal phalanx dorsum and taking care not to fracture the thin cortex. The holes carry the tendon from plantar to dorsal, which creates the mechanical advantage.
Thread FDL through the holes with a suture passer or wire loop so that it emerges on the dorsum of the proximal phalanx. Hold the MTPJ in 10-15° plantarflexion with the IP joints in neutral extension, weave the tendon through the extensor hood and suture it to itself with non-absorbable suture (2-0 Ethibond). Tensioning is critical: too tight creates an MTPJ plantarflexion deformity (cock-up toe), too loose allows the claw to recur.
If the MTPJ does not reduce to neutral after the transfer, incise the dorsal capsule transversely and manually plantarflex the joint to neutral. Excessive release risks MTPJ instability. Capsule release is for the borderline case.
Close with 4-0 nylon interrupted sutures, dress with non-adherent gauze and gauze padding between the toes, and splint with buddy tape to the adjacent toe or a plantar-flexion strap. A K-wire is not typically needed because the transfer provides dynamic correction. Splinting maintains the correction while the tendon heals (6 weeks).
Checking the transfer. After suturing, passively flex the ankle: the toe should extend without excessive MTPJ plantarflexion. Inadequate FDL release leaves a tether that prevents full correction. The MTPJ must be passively reducible pre-operatively or the transfer will fail: if it is not, add a capsule release or choose fusion. Several toes can be transferred at once in bilateral claw.
When the PIPJ is rigid. If the PIPJ does not passively extend, the transfer alone will fail, and a PIPJ resection arthroplasty or fusion is added to straighten the toe. The transfer corrects the MTPJ hyperextension and dynamic imbalance; the PIPJ procedure deals with the fixed contracture. Combined procedures are common in moderate-to-severe claw toes with mixed flexible and rigid components.
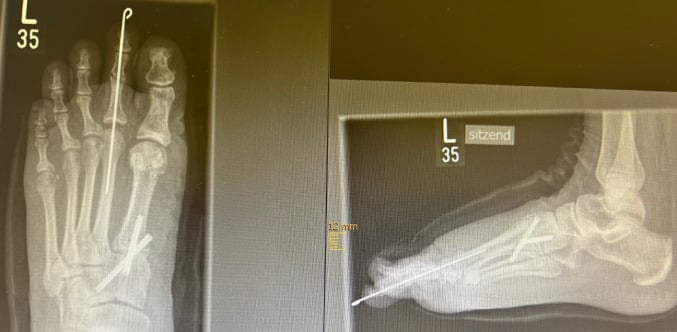
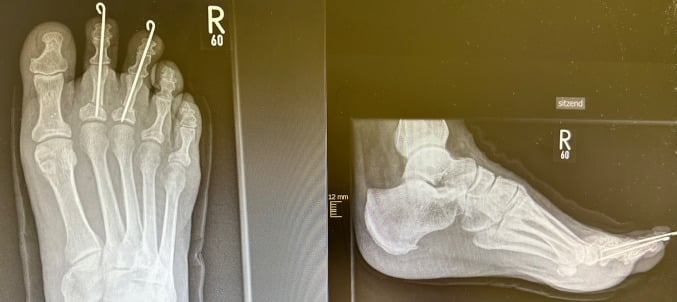
Complications
- Incidence
- Not quantified by any source cited on this page
- Risk Factors
- Inadequate soft tissue release, untreated MTPJ hyperextension, progressive neuromuscular disease
- Management
- Revision surgery - add missing component (fusion if did arthroplasty, transfer if inadequate balancing)
- Incidence
- 5-10%
- Risk Factors
- Inadequate cartilage removal, smoking, poor bone quality, unstable fixation
- Management
- Revision fusion with better fixation (screw instead of K-wire), bone graft if defect
- Incidence
- 5-15%
- Risk Factors
- Improper alignment at surgery (excessive flexion or extension, rotational deformity), K-wire migration, inadequate fixation
- Management
- If symptomatic: revision osteotomy and re-fusion; if asymptomatic: observe
- Incidence
- 10-15%
- Risk Factors
- Excessive bone resection at arthroplasty, loss of structural support
- Management
- Difficult to treat - revision fusion if severe, otherwise conservative management
- Incidence
- 2-5%
- Risk Factors
- Diabetes, neuropathy, smoking, poor hygiene, K-wire left protruding
- Management
- Oral antibiotics, pin removal if around K-wire; most resolve without sequelae
- Incidence
- Under 2%
- Risk Factors
- Diabetes with neuropathy, vascular disease, open wound
- Management
- IV antibiotics, surgical debridement, possible amputation if severe
- Incidence
- Under 1%
- Risk Factors
- Excessive dissection, blind retraction, anatomical variation
- Management
- Digital nerve or artery injury - sensory loss or ischaemia; if toe viable, observe; if ischaemic, may require amputation
- Incidence
- 5-10%
- Risk Factors
- Prolonged immobilisation, excessive scar tissue, K-wire across multiple joints
- Management
- Physical therapy, passive ROM exercises; usually improves over 3-6 months
- Incidence
- 10-20%
- Risk Factors
- Under- or over-tensioning, operating on rigid MTPJ, inadequate FDL release
- Management
- Revision with proper tensioning or convert to MTPJ fusion if joint damage
- Incidence
- 5-15%
- Risk Factors
- Over-correction with toe plantarflexion, unaddressed long metatarsal, adjacent metatarsal overload
- Management
- Orthotic metatarsal padding, if severe: Weil osteotomy of adjacent metatarsal
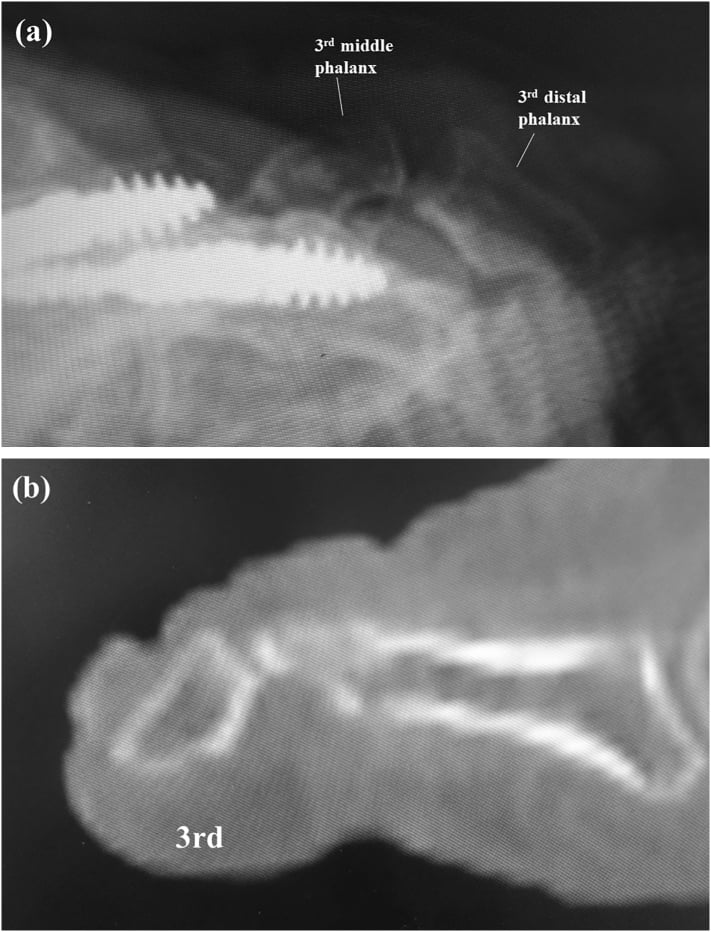
Assess vascular status pre-operatively in all diabetic or elderly patients: palpable pulses, ankle-brachial index (ABI), and transcutaneous oxygen pressure (TcPO2) if there is concern for PAD. Lesser toe surgery has higher complication rates in vascular compromise: wound dehiscence, infection and toe necrosis occur in 10-20% of patients with diabetic neuropathy against under 5% of healthy patients. Consider toe amputation instead of reconstruction if the vascular supply is marginal (ABI under 0.5, TcPO2 under 30 mmHg).
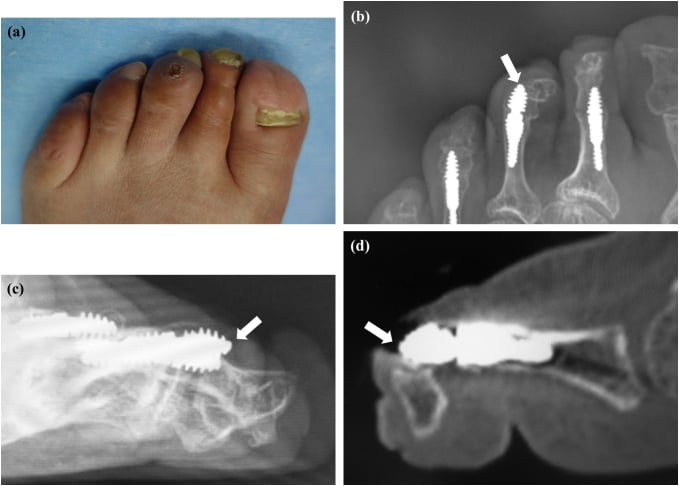
Postoperative Care and Rehabilitation
Recovery Milestones
Multimodal analgesia (oral opioids, NSAIDs, ice, elevation), a bulky dressing with gauze padding between the toes, and a post-op shoe or sandal with buddy taping. Weight-bear on the heel only, non-weight-bearing on the forefoot. Strict elevation above the heart for 23 hours a day for 48 hours, with rest, reduces swelling and promotes early healing.
Inspect the wound at 7-10 days and remove sutures at 10-14 days, with weekly dressing changes and continued buddy taping. Weight-bearing increases gradually to full in the post-op shoe. Start gentle passive range of motion of the unfused joints (MTPJ, non-operated PIPJ), and if a K-wire is present clean it daily with an alcohol swab. Early mobilisation prevents stiffness while protecting the repair.
Remove the K-wire in clinic at 4-6 weeks (no anaesthesia needed; the fusion wire stays 6-8 weeks), then continue buddy taping for a further 2-4 weeks. Move into a wide, stiff-soled athletic shoe and begin active exercises: toe flexion and extension, marble pick-ups. Sedentary work resumes at 2-3 weeks and standing work at 6 weeks.
After a fusion, radiographs at 6 weeks confirm healing. Regular shoes with a wide toe box are allowed, avoiding high heels and narrow shoes; walking, swimming and cycling are permitted but running and jumping are not. Towel curls and resistance-band exercises strengthen the foot intrinsics.
Return to sport and impact activities at 3 months, with a permanent change to supportive, wide toe box shoes and surveillance for recurrent deformity and adjacent toe problems. Most of the final outcome is apparent by 6 months, but full recovery takes 6-12 months and swelling can persist for up to a year.
Setting expectations. Do it before the operation. Lesser toe surgery reliably relieves pain in the cited series (see Outcomes), but the cosmetic result may be imperfect: expect mild swelling for 6-12 months, slight shortening of the toe and some stiffness. Perfect alignment and a completely normal appearance are unrealistic goals, and patients seeking cosmetic perfection may be dissatisfied despite a good functional result. The goal is a pain-free, functional toe that fits in a shoe.
Outcomes and Prognosis
- What the cited evidence shows
- No series cited on this page reports its success or recurrence rate
- Recognised trade-offs
- Simple and quick, but relies on the deformity being genuinely passively correctable
- What the cited evidence shows
- Coughlin, 118 toes at 61 months: 92% pain relief, 84% satisfaction, AOFAS 83; 81% bony union and 19% stable fibrous union
- Recognised trade-offs
- Radiographic alignment good in only 79%, and malalignment was a principal cause of an unsatisfactory result
- What the cited evidence shows
- Arumugam, 1118 toes: union 22-96% across twelve implants, every study at high or critical risk of bias; implants beat K-wire on union but not on function, pain, satisfaction or quality of life
- Recognised trade-offs
- No single fusion rate can be quoted; implant cost is not justified by any patient-noticeable gain
- What the cited evidence shows
- Barbari, 39 feet at 38 months: metatarsalgia and callosities reduced with improved toe shape in most cases - outcomes entirely subjective, no rate calculable
- Recognised trade-offs
- Depends on precise tensioning; the 1984 series predates recognition of plantar plate pathology
- What the cited evidence shows
- Nery, 100 MTP joints: all tear grades improved significantly, but grade IV reached only AOFAS 72 with the least stable joints and poorest toe purchase
- Recognised trade-offs
- Procedure was allocated by tear grade, so grade and operation cannot be separated; all cases also had a Weil osteotomy
- What the cited evidence shows
- No series cited on this page quantifies it
- Recognised trade-offs
- Sacrifices the MTP joint to relieve pain; a salvage decision, not an outcome-led one
Who does well. An isolated flexible deformity in a healthy patient with normal neurovascular status and no underlying systemic disease, corrected by the right procedure with complete releases and stable fixation, in a patient who complies with protected weight-bearing and footwear afterwards. These patients do best, with low recurrence, though no cited series on this page attaches a percentage to that.
Factors associated with higher failure and recurrence rates:
- Inadequate initial correction - incomplete soft tissue release or inadequate bony correction
- Untreated underlying pathology - cavus foot, neuromuscular disease, hallux valgus
- Smoking - impairs bone and soft tissue healing, increases nonunion and infection
- Diabetes with neuropathy - wound healing problems, infection, Charcot risk
- Unrealistic expectations - patients seeking cosmetic perfection rather than functional improvement
- Operating on rigid deformity with soft tissue procedure - flexor transfer on non-reducible MTPJ fails
- Failure to address adjacent pathology - untreated metatarsalgia, long metatarsal, MTPJ instability
Addressing these factors pre-operatively and selecting the appropriate procedure improves outcomes.
Guarded prognosis. Multiple rigid toes needing simultaneous correction, revision of a failed prior procedure, diabetic neuropathy or peripheral vascular disease, progressive neuromuscular disease (CMT, polio) and severe MTPJ instability with plantar plate rupture all do less well, with higher complication and recurrence rates. No cited series on this page quantifies the difference.
Guidelines, Registries & Global Practice
- Prevalence: Lesser toe deformities affect roughly 30% of community-dwelling older adults (Framingham Foot Study - 29.6%)
- Sex: Female predominance (footwear, ligamentous laxity, hormonal factors)
- Heritability: Strong genetic contribution (0.49-0.90), highest after age 70 - not purely footwear-driven
- Associations: Hallux valgus, pes cavus, inflammatory arthritis, diabetic and neuromuscular disease
- Resource setting: Higher symptomatic burden where constrictive footwear is common; neuromuscular causes (leprosy, polio sequelae, untreated CMT) remain relevant in limited-resource regions
Deformity is common, heritable and frequently coexists with hallux valgus - screen the whole forefoot, not just the symptomatic toe.
- No dedicated lesser toe registry: Unlike arthroplasty (NJR, AJRR, AOANJRR), forefoot reconstruction is not captured in implant registries
- Evidence base: Predominantly Level III-IV case series and small systematic reviews; few randomised trials
- Implant data: Intramedullary PIPJ devices show variable union (22-96%) with no proven functional gain over K-wire (Arumugam 2025; Wei 2020)
- PROMs: AOFAS lesser MTP-IP and MOXFQ scores increasingly used to standardise outcome reporting
Quote the evidence honestly in vivas - lesser toe surgery is reliable for pain but lacks high-level comparative data.
- Emphasis
- Stepwise care; flexibility-based algorithm
- Key Practice Point
- Conservative trial first; PIPJ arthrodesis favoured for rigid deformity; plantar plate grading guides MTPJ surgery
- Emphasis
- Shared decision-making, PROMs
- Key Practice Point
- Document MOXFQ; reserve surgery for failed non-operative care; K-wire remains standard, implants not routinely funded
- Emphasis
- Fixation principles
- Key Practice Point
- Stable arthrodesis with adequate cartilage resection and compression; K-wire or intramedullary device acceptable
- Emphasis
- Forefoot reconstruction as a unit
- Key Practice Point
- Address coexisting hallux valgus and metatarsal length (Weil osteotomy) at the index procedure to reduce recurrence
- Emphasis
- Risk stratification, offloading
- Key Practice Point
- Treat clawed toes as ulcer risk; flexor tenotomy to offload tips in neuropathic feet; vascular assessment mandatory
- MRI and ultrasound to grade plantar plate tears pre-operatively
- Choice of intramedullary implants, headless screws and suture anchors available
- Day-case surgery with regional ankle block and structured PROM follow-up
- Multidisciplinary diabetic foot pathways for offloading and prophylactic surgery
Imaging and implant choice are abundant - the constraint is appropriate selection, not access.
- Diagnosis is clinical; plain radiographs guide most decisions
- K-wire fixation and percutaneous flexor tenotomy are mainstay (low cost, reliable)
- Neuromuscular causes (leprosy, polio, untreated CMT) over-represented - treat the driver
- Footwear modification and education are the most cost-effective interventions
Simple, durable techniques (K-wire, tenotomy) and footwear advice deliver most of the benefit at minimal cost.
Counsel and document before surgery:
- Realistic expectations: Functional pain relief is reliable; cosmetic perfection and a completely normal-looking toe are not - swelling may persist 6-12 months
- Recurrence: no source cited on this page reports a recurrence rate; the drivers are untreated MTPJ hyperextension, unaddressed cavus or neuromuscular disease, and inadequate initial correction
- Specific risks: Floppy/short toe from over-resection, nonunion, malunion, stiffness, numbness, infection
- Conservative trial: Confirm an adequate trial of footwear modification and padding (3-6 months)
- Higher-risk feet: Vascular assessment (pulses, ABI, TcPO2) in diabetic or PAD patients; correct site marking for the right toe
Honest expectation-setting and a documented conservative trial are the strongest protections against dissatisfaction and dispute, regardless of health system.
Controversies and Areas of Uncertainty
Fusion or resection arthroplasty for the PIPJ. The trade-offs are set out under Surgical Technique; after arthroplasty, fibrous rather than bony union is common, and over-resection risks a floppy toe. Head-to-head high-level data are limited, so the choice remains surgeon- and patient-specific: age, demand, and whether it is a revision.
Intramedullary implant or K-wire. Implants may improve radiographic union and avoid pin-track problems and a second visit for removal, but two systematic reviews found no functional or satisfaction advantage over K-wire despite far higher cost. The standard of care is not settled and randomised trials are awaited.
Plantar plate repair technique and approach. Dorsal (with Weil osteotomy) versus direct plantar approach, suture anchor versus suture alone, and the role of the flexor to extensor transfer as an adjunct are all debated. Higher-grade tears give less reliable stability whichever technique is used.
Prophylactic surgery in the neuropathic foot. Flexor tenotomy to offload clawed toe tips can prevent or heal apical ulcers in diabetic and neuropathic feet, but timing, patient selection and durability against offloading alone remain uncertain, and have to be balanced against the higher wound and infection risk of operating on an at-risk foot.
When asked about a controversial choice (fusion vs arthroplasty, implant vs K-wire), do not pick dogmatically. State that the evidence is largely Level III-IV, summarise the trade-offs, and frame your answer around the individual patient - flexibility of the deformity, age and demand, bone quality, vascular status, cost/access, and whether it is a primary or revision case. Examiners reward balanced, evidence-aware reasoning over a memorised single answer.
MCQ Practice Points
Q: Which muscle transfer is performed in the Girdlestone-Taylor procedure for flexible claw toe? A: Flexor digitorum longus (FDL) to the extensor hood. The FDL is harvested from its insertion at the distal phalanx, passed through drill holes in the proximal phalanx, and sutured to the extensor hood on the dorsal side. This converts the deforming flexor force into a correcting force that plantarflexes the MTPJ and extends the IP joints. The procedure only works if the MTPJ is passively reducible; rigid MTPJ requires capsule release or bony correction.
Q: What is the key clinical difference between hammer toe and claw toe? A: MTPJ position. Hammer toe has MTPJ in neutral or mild hyperextension with primary deformity at the PIPJ (flexion). Claw toe has MTPJ hyperextension (key distinguishing feature) plus flexion at both PIPJ and DIPJ. Mallet toe is isolated DIPJ flexion. Knowing this distinction guides treatment - hammer toe needs PIPJ correction, claw toe requires MTPJ and IP joint correction.
Q: What is the gold standard surgical treatment for rigid hammer toe? A: PIPJ fusion (arthrodesis). Fusion is the most durable and predictable correction for rigid hammer toe. Be careful with the numbers: the systematic review cited on this page found fusion rates ranging from 22% to 96% across twelve implants with every included study at high or critical risk of bias, so a tight "85-95%" is not defensible. The PIPJ is fused in 15-25 degrees of flexion using intramedullary K-wire or headless screw. Resection arthroplasty (DuVries procedure) is simpler; Coughlin's series showed 81% went on to bony union and 19% to a stable fibrous union, with 92% pain relief - so it is not an inferior operation so much as a different endpoint. For young, active patients, fusion is preferred.
Q: What is the most common cause of floppy toe deformity after hammer toe surgery? A: Excessive bone resection during PIPJ resection arthroplasty. Over-resection of the proximal phalanx head removes structural support, creating a short, unstable toe with loss of ground contact and poor function. The appropriate amount to resect is 3-5mm (the head only). Floppy toe is difficult to treat - prevention is key by performing meticulous arthroplasty or choosing fusion instead for more predictable length preservation.
Q: What is the Silverskiold test in the context of claw toe assessment? A: Passive ankle dorsiflexion test to assess if claw deformity reduces. If the claw toe deformity corrects when the ankle is passively dorsiflexed, it indicates that gastrocnemius tightness and extrinsic flexor (FDL/FDB) pull are driving the deformity - this is a flexible, dynamic deformity amenable to flexor release or transfer. If the deformity persists regardless of ankle position, the contracture is fixed at the joint level and requires bony correction (fusion or arthroplasty). This test guides procedure selection.
Q: What is the recurrence rate of lesser toe deformities after surgical correction? A: Recurrence is real but not reliably quantified for these procedures. No source cited on this page reports a recurrence rate for flexor tenotomy, resection arthroplasty, PIPJ fusion, flexor-to-extensor transfer or crossover toe repair, so avoid quoting a league table of percentages. What the cited evidence does support: Coughlin found roughly a fifth of toes radiographically malaligned after PIPJ resection arthroplasty, and malalignment was a principal cause of an unsatisfactory result. Mechanistically, recurrence follows suboptimal tensioning of a transfer, failure to address an underlying cavus or neuromuscular driver, and inadequate initial correction; diabetes and smoking add wound and healing risk.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 52-year-old woman presents with painful second toe deformity. She has a dorsal corn over the PIPJ that prevents her from wearing closed-toe shoes. On examination, the PIPJ is flexed 45 degrees, the MTPJ is in neutral, and the DIPJ is extended. The deformity passively corrects with manipulation. Weight-bearing foot radiographs show PIPJ flexion with no arthritis. What is your diagnosis and management plan?”
“A 38-year-old man with Charcot-Marie-Tooth disease presents with bilateral claw toes affecting the second through fifth toes. He has pes cavus and metatarsalgia. On examination, the MTPJ is hyperextended 40 degrees, the PIPJ is flexed 60 degrees, and the DIPJ is flexed 30 degrees. The deformity reduces when you passively dorsiflex the ankle (positive Silverskiold test). Walk me through your surgical approach for the flexible claw toe deformity.”
“A 60-year-old woman underwent plantar plate repair and flexor to extensor transfer for Grade II crossover toe 3 months ago. She returns with recurrent medial deviation of the second toe and persistent metatarsalgia. On examination, the second toe is crossing over the hallux again, and there is tenderness at the second MTPJ with positive dorsal drawer test. What has happened and how do you manage this?”
Classification (Joint Involvement)
- Hammer toe = PIPJ flexion (MTPJ normal, DIPJ neutral/extended)
- Claw toe = MTPJ hyperextension + PIPJ flexion + DIPJ flexion (all three joints)
- Mallet toe = DIPJ flexion only (MTPJ and PIPJ normal)
- Crossover toe = MTPJ instability with medial/lateral deviation (plantar plate tear)
Flexibility Assessment (Critical for Treatment)
- Flexible = passively correctable, soft tissue procedure (tenotomy, transfer, lengthening)
- Rigid = fixed contracture, bony procedure (fusion, arthroplasty, osteotomy)
- Silverskiold test = ankle dorsiflexion reduces claw = flexible, gastrocnemius-driven
- MTPJ dorsal drawer = excessive translation = plantar plate insufficiency (crossover toe developing)
Treatment Algorithm
- Flexible hammer toe = flexor tenotomy + extensor lengthening
- Rigid hammer toe = PIPJ fusion (gold standard) or resection arthroplasty
- Flexible claw toe = flexor to extensor transfer (Girdlestone-Taylor) + address cavus
- Rigid claw toe = PIPJ fusion + MTPJ capsule release or shortening osteotomy
- Mallet toe (flexible) = FDL tenotomy; (rigid) = DIPJ fusion
- Crossover toe Grade I-II = plantar plate repair + flexor transfer; Grade III = MTPJ arthroplasty/fusion
Surgical Pearls
- PIPJ fusion: 15-25° flexion, K-wire 6-8 weeks or headless screw (permanent); do NOT quote a single fusion rate - the systematic review on this page reports 22-96% across implants, all studies at high or critical risk of bias
- Flexor to extensor transfer: harvest FDL distally, drill proximal phalanx, tension with MTPJ 10-15° plantarflexion
- Transfer only works if MTPJ passively reduces - if rigid, add capsule release or choose fusion
- Resection arthroplasty: resect only 3-5mm (head of proximal phalanx) - over-resection creates floppy toe
Complications and Management
- Recurrence is real but unquantified in the sources cited here - it follows untreated MTPJ hyperextension, unaddressed cavus and suboptimal tensioning rather than the choice of PIPJ procedure alone
- Floppy toe from over-resection (difficult to treat - prevention key)
- Nonunion 5-10% (inadequate cartilage removal, smoking, poor fixation) - revision with screw or graft
- Transfer failure (under/over-tensioning, operating on rigid MTPJ) - revision or convert to fusion
- Infection higher in diabetes/PAD (8-12% vs 2-5%) - check vascular status pre-op (ABI, TcPO2)
Key Evidence and Outcomes
- PIPJ resection arthroplasty for fixed hammertoe: 81% bony union, 92% pain relief, 84% satisfaction (Coughlin, Dorris & Polk 2000)
- Girdlestone-Taylor flexor-to-extensor transfer: reliable relief of metatarsalgia/callosity in flexible deformity, including the elderly (Barbari & Brevig 1984)
- Plantar plate tears - grade-based protocol with Weil osteotomy improves all grades but higher grades give less stable joints (Nery, Coughlin & Baumfeld 2014)
- Intramedullary implants for PIPJ fusion may improve union over K-wire but functional outcomes are equivocal (Arumugam 2025; Wei 2020)
- Lesser toe deformities affect ~30% of older adults and are strongly heritable (Framingham Foot Study 2013)
Evidence Base and Key Studies
Correction of Clawtoes by the Girdlestone-Taylor Flexor-Extensor Transfer
- Case series of 39 feet in 31 patients (mean age 57.5 years) treated with the Girdlestone-Taylor flexor-to-extensor transfer; mean follow-up 38 months
- Wide variation in aetiology and severity; reduction of metatarsalgia and callosities with improved toe shape achieved in most cases
- Procedure relied on subjective satisfaction, pain relief and recurrence of callosities as outcome measures
- Authors recommended the transfer even in elderly patients, avoiding radical resection or amputation
Operative Repair of the Fixed Hammertoe Deformity
- 63 patients (118 toes) evaluated at mean 61-month follow-up after PIPJ resection arthroplasty with intramedullary K-wire for fixed hammertoe
- Bony fusion of the PIPJ occurred in 81% of toes; the remaining 19% formed a stable fibrous union
- Pain relieved in 92% and subjective satisfaction reported by 84%; mean postoperative AOFAS score 83
- Malalignment and numbness were the principal factors associated with an unsatisfactory result; minor complications in 5%
Prospective Protocol for Surgical Treatment of Lesser MTP Joint Plantar Plate Tears
- 68 patients (100 MTP joints) prospectively graded by an anatomical plantar plate tear classification and treated by a grade-based protocol
- Grade 0-I: radiofrequency shrinkage; Grade II-III: direct plantar plate reinsertion; Grade IV: flexor-to-extensor transfer; all combined with a Weil osteotomy
- Significant improvement in AOFAS, VAS, stability and toe purchase across all grades (P less than .0001)
- Grades I, III and IV had inferior stability and toe purchase versus grades 0 and II; Grade IV achieved only a fair mean AOFAS (72)
Implants for PIPJ Arthrodesis of the Lesser Toes: A Systematic Review
- Systematic review of 12 studies comparing 12 intramedullary implants in 797 patients (1118 toes) for hammer or claw toe PIPJ arthrodesis
- Reported fusion rates ranged widely from 22.2% to 96% depending on implant and study
- Four studies comparing an implant directly with K-wire showed improved union rates with the implant (P less than 0.05)
- Function, pain relief, satisfaction and quality of life all improved but were equivocal between implants and K-wire; all studies were high or critical risk of bias
Ideal Implant Choice for PIPJ Arthrodesis in Hammer/Claw Toe Correction
- Systematic review of 5 studies (1 RCT, 4 case-controlled) comparing K-wires with novel internal fixation devices for PIPJ arthrodesis
- Novel intramedullary devices showed promising union rates compared with K-wires
- No advantage of internal devices over K-wires in pain, patient satisfaction, foot function or complication rates
- Internal devices avoid pin-track issues and the need for later removal but at higher cost
Hammer Toe Correction Using an Absorbable Intramedullary Pin
- 48 PIPJ arthrodeses in 35 patients for fixed rigid hammertoe using a 2-mm absorbable intramedullary pin; mean follow-up 38.5 months
- Procedure described as simple and safe with high patient satisfaction and minimal complications
- No pin-track management or hardware removal required, unlike percutaneous K-wires
- Indicated when the MTPJ is stable, skin is intact and the proximal phalanx canal is 2.0 mm or less; also useful in metal allergy
High Heritability and Prevalence of Lesser Toe Deformities (Framingham Foot Study)
- Population-based study of 1,370 adults (mean age 66 years, 57% women) from the Framingham Foot Study using a validated examination
- Prevalence of lesser toe deformities 29.6% and hallux valgus 31% in this older community-dwelling cohort
- Significant heritability of lesser toe deformity (0.49-0.90 depending on age and sex); 0.65 in those over 70 years
- First demonstration that common forefoot deformities are strongly heritable, not solely footwear-driven