Structure | Composition | Biomechanics | Healing | Graft Incorporation
- Type I collagen (70-80% dry weight) in hierarchical organisation provides tensile strength
- Enthesis has 4 zones: ligament → fibrocartilage → mineralised FC → bone (graded transition)
- Crimping pattern creates toe region of stress-strain curve (0-3% strain, low stiffness)
- Healing phases: inflammatory (0-7d), proliferative (7d-6wk), remodelling (6wk-24mo)
- ACL grafts never achieve full native strength - plateau at 50-70% after 12-24 months
- Intra-articular ligaments (ACL) heal poorly; extra-articular (MCL) heal better
- “Insertion (enthesis) does not regenerate after surgical reconstruction
- “Midsubstance healing stronger than bone-ligament junction in first 8-12 weeks
- “Graft weakening phase occurs at 3-4 months during revascularisation
- “Immobilisation causes rapid strength loss; controlled motion promotes alignment
- “Bony avulsions heal better than midsubstance tears (preserve enthesis)
Overview and Fundamental Concepts
Ligaments are dense connective tissue bands that connect bone to bone, giving a joint stability while permitting controlled physiological motion. Their hierarchical organisation, from nanometre-scale tropocollagen molecules to centimetre-scale anatomical structures, provides exceptional tensile strength along the fibre axis while keeping enough flexibility for joint movement.
What a ligament does. It differs from a tendon, which connects muscle to bone. A ligament provides passive mechanical restraint to joint motion, guides joint kinematics through the arc of motion, contains mechanoreceptors that provide proprioceptive feedback, and behaves viscoelastically, so its mechanical properties depend on the rate of loading.
Functional classification.
- Capsular ligaments: thickenings of the joint capsule (the glenohumeral ligaments)
- Extracapsular ligaments: distinct structures outside the joint (the MCL of the knee)
- Intracapsular ligaments: within the joint but extrasynovial (ACL, PCL)
- Elastic ligaments: high elastin content allowing stretch (ligamentum flavum)
Why it matters. Composition, biomechanics and healing characteristics decide how injury patterns are read, how much healing can be expected, how a reconstruction is designed and how rehabilitation is staged. The same biology drives decision-making across every orthopaedic subspecialty.
Concepts: Composition and Structure
Extracellular Matrix Components
Ligaments are cells embedded in an abundant extracellular matrix, and the composition of that matrix is what healing responses and graft behaviour are interpreted against.
- Percentage
- 60-80% total weight
- Function
- Viscoelasticity, nutrient transport
- Clinical Note
- Dehydration reduces stiffness
- Percentage
- 70-80% dry weight
- Function
- Tensile strength, structural framework
- Clinical Note
- Decreased in healing tissue
- Percentage
- Under 10% normal
- Function
- Compliance, early healing
- Clinical Note
- Increases to 30% in scar then decreases
- Percentage
- 1-3% dry weight
- Function
- Collagen organisation, compression resistance
- Clinical Note
- Decorin, biglycan regulate fibrillogenesis
- Percentage
- 1-5% (70% in LF)
- Function
- Elastic recoil
- Clinical Note
- Ligamentum flavum has unique high content
- Percentage
- Under 5%
- Function
- Cell adhesion, matrix organisation
- Clinical Note
- Fibronectin, laminin, fibrillin
Type I collagen. A triple helix of two alpha-1 chains and one alpha-2 chain, organised into hierarchical bundles with a crimping pattern. It gives high tensile strength but is weak in compression. Fibroblasts synthesise it in response to mechanical loading, and lysyl oxidase cross-links it to form pyridinoline links.
Type III collagen. Present in small amounts in the normal ligament (under 10%), it rises during healing to as much as 30% at 6-8 weeks. Its fibrils are more compliant and smaller in diameter than Type I. It should fall again during remodelling, but in scar tissue that fall is incomplete, and a persistently raised Type III fraction is the signature of incomplete maturation.
Proteoglycans. The small leucine-rich proteoglycans decorin and biglycan regulate collagen fibril diameter and spacing, and resist compressive forces through osmotic swelling. They increase in healing ligaments, and their age-related decrease may contribute to injury susceptibility. Around them, a ground substance of glycosaminoglycans and hyaluronic acid provides hydration, lubrication and spacing.
Cellular Components
Fibroblasts make up 90-95% of ligament cells. They synthesise collagen (Types I and III) and the matrix proteins, respond to mechanical loading through mechanotransduction, and in the mature ligament lie aligned along the primary lines of stress. They carry receptors for TGF-β, PDGF and IGF-1, and during healing their numbers rise to a peak at 2-3 weeks.
The remaining 5-10% are specialised populations:
- Chondrocytes at the fibrocartilaginous insertions (enthesis)
- Synovial cells in intra-articular ligaments (ACL, PCL)
- Vascular endothelial cells in the epiligament and midsubstance
- Nerve endings and mechanoreceptors (proprioception)
- Mast cells and inflammatory cells (injury response)
Hierarchical Structure
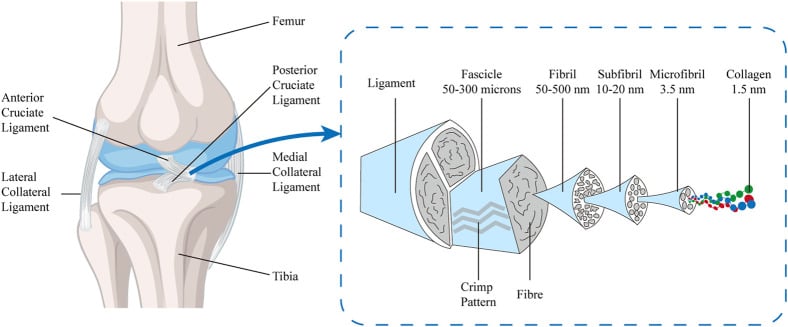
Ligaments are organised across seven orders of magnitude, from nanometres to centimetres, an arrangement that optimises mechanical performance while still allowing biological remodelling.
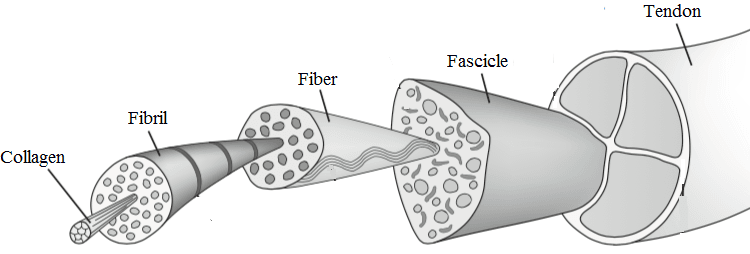
Tropocollagen (1-10 nm). The basic molecule: three alpha chains, each a left-handed polyproline helix, wound into a right-handed superhelix 300 nm long and 1.5 nm in diameter. Glycine at every third position allows the chains to pack tightly. It is synthesised intracellularly and secreted as procollagen.
Microfibril (5-20 nm). Five tropocollagen molecules, 5 nm across, in a staggered quarter-stagger arrangement. The stagger creates the characteristic 67 nm D-period banding, with gap and overlap regions visible on electron microscopy. Initial enzymatic cross-linking happens here, and the microfibril is the basic unit of fibril assembly.
Subfibril (10-20 nm). Assembled microfibrils with increasing cross-links. Diameter varies with collagen type and tissue; lateral fusion creates larger-diameter structures, and cross-linking density rises with maturation.
Fibril (50-500 nm). Bundles of subfibrils, visible on light microscopy, carrying the wavy crimping pattern with its 20-100 micrometre period. Diameter correlates with mechanical properties, cross-linking provides the tensile strength, and the crimp is what allows initial low-stiffness loading.
Fascicle (50-300 micrometres). Bundles of fibrils wrapped by an endoligament sheath, and the functional unit of ligament mechanics. The sheath carries blood vessels and nerves and allows the fascicles to glide against one another.
Ligament (millimetre to centimetre). Multiple fascicles wrapped by the epiligament make the gross anatomical structure. The vascular supply runs in the epiligament and endoligament, and mechanoreceptors within it provide proprioceptive feedback.
Cross-Linking
Enzymatic cross-links. Lysyl oxidase converts lysine and hydroxylysine residues to reactive aldehydes, and the mature products are pyridinoline (PYD) and deoxypyridinoline (DPD). These links provide mechanical stability and tensile strength, and they increase with age and tissue maturation. They are reduced in healing tissue, which is part of why it is weaker, and once disrupted by injury they cannot reform.
Non-enzymatic cross-links. Advanced glycation end-products (AGEs) accumulate with age and contribute to age-related stiffening and embrittlement. The process is accelerated in diabetes, which may predispose to injury.
Synthesis. Fibroblasts make pre-pro-alpha chains, then proline and lysine residues are hydroxylated by prolyl hydroxylase and lysyl hydroxylase, both of which require vitamin C (ascorbate) as a cofactor. The chains glycosylate, form the triple-helical procollagen, are secreted, have their propeptides cleaved to tropocollagen, self-assemble, and are finally cross-linked by lysyl oxidase, a copper-dependent enzyme. The cofactors and the inherited defects of this pathway are heavily examined because they explain why some patients have weak, lax, injury-prone ligaments.
- Scurvy (vitamin C deficiency): impaired prolyl and lysyl hydroxylation gives an unstable triple helix - fragile collagen, capillary fragility, poor wound healing and weak ligament and bone matrix
- Defective lysyl oxidase cross-linking: copper deficiency (Menkes disease) and lathyrism (beta-aminopropionitrile) both impair cross-linking and weaken connective tissue
- Ehlers-Danlos syndromes: classical type (COL5A1/COL5A2) and vascular type (COL3A1) cause ligamentous hypermobility and laxity, recurrent dislocation, poor-quality surgical tissue and higher graft-stretch and failure risk; the vascular type has friable vessels demanding surgical caution
- Osteogenesis imperfecta (COL1A1/COL1A2): defective Type I collagen gives bone fragility with ligamentous laxity
- Marfan syndrome (fibrillin-1, FBN1): fibrillin is not collagen, but the result is still ligamentous laxity and joint instability
Enthesis: The Ligament-Bone Interface
The insertion, or enthesis, is a specialised transitional structure that minimises stress concentration at the interface between compliant ligament and stiff bone. The whole graded transition occurs over less than 1 mm.
Zone 1 - ligament. Dense regular connective tissue with aligned Type I collagen fibres parallel to the direction of loading and a high fibroblast density, continuous with the ligament midsubstance.
Zone 2 - uncalcified fibrocartilage. A gradual transition zone in which chondrocytes within lacunae appear, Type II collagen increases alongside Type I, and proteoglycan content rises. This is the zone that resists the compressive forces of oblique loading.
Zone 3 - mineralised fibrocartilage. Calcium phosphate is deposited as hydroxyapatite crystals, and a basophilic tidemark is visible on histology. Type X collagen is present as the marker of mineralisation. This zone carries the sharp gradient in elastic modulus and anchors the collagen fibres to bone.
Zone 4 - bone. Subchondral and trabecular bone, into which Sharpey fibres penetrate to provide mechanical anchorage. Its vascular supply nourishes the enthesis.
LFMBFour Zones of Enthesis - LFMB
Hook:LFMB - Ligament Fades into Mineralised Bone through graded zones!
Why the gradient exists. Elastic modulus rises from 100-400 MPa in ligament to 10-20 GPa in bone, a factor of 50-100 across less than a millimetre. A step change of that size would concentrate stress and fail at the interface; the graded fibrocartilage zones spread it, and resist the shear and compressive stresses that arrive with it.
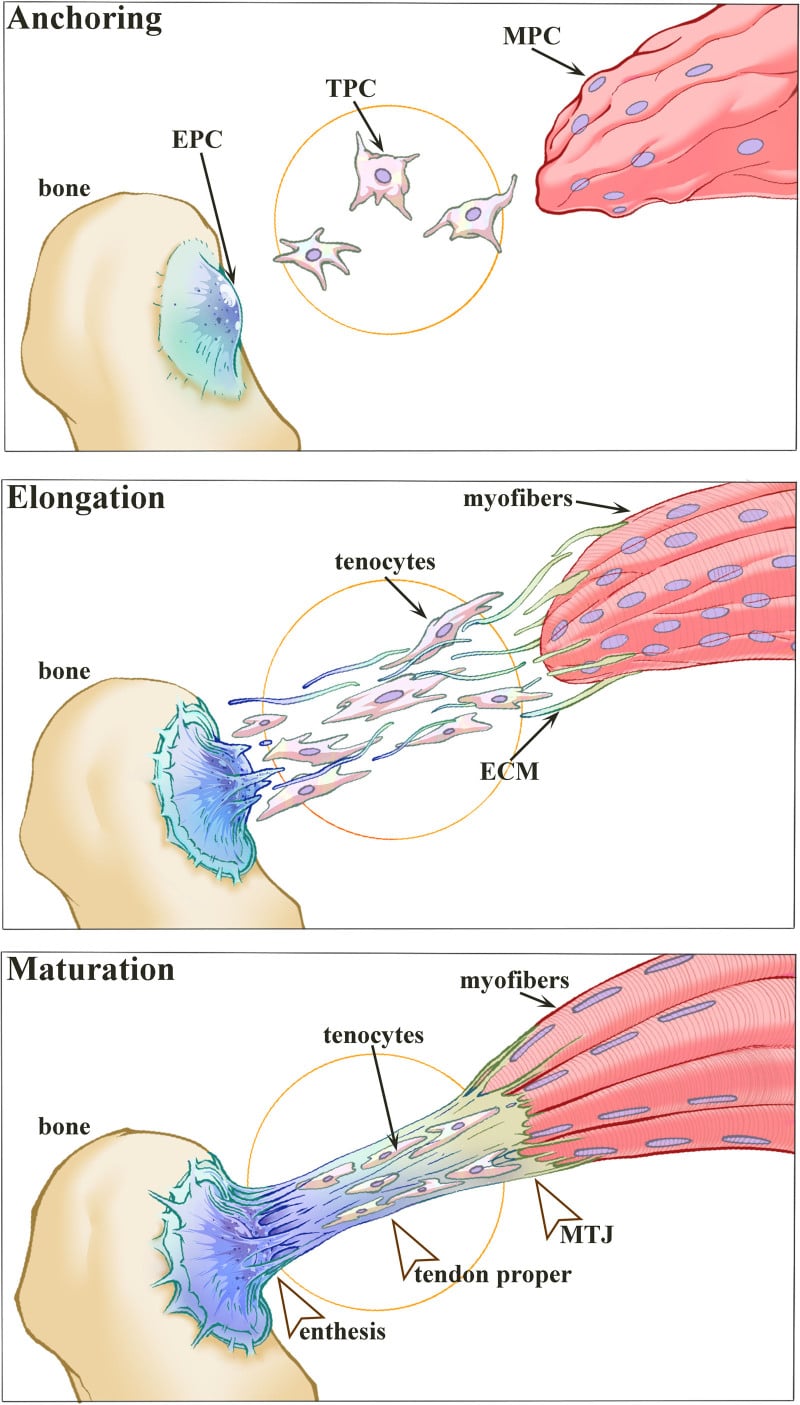
The enthesis does not regenerate after surgical reconstruction. Bone tunnel healing creates fibrovascular scar tissue, not the native four-zone enthesis, which is why ligament-to-bone healing is the weakest link in ACL reconstruction during the first 8-12 weeks. Bony avulsion fractures preserve the enthesis and heal through vascular cancellous bone, so they heal better than midsubstance tears: the biological insertion remains intact.
Who fails where. The weakest element in the chain changes with age. In the young, bone is weaker than the enthesis and the ligament, so the injury is a bony avulsion; in adults, age-related collagen weakening makes the ligament the weakest link and the tear is midsubstance; in the elderly, the enthesis may fail with degeneration, and osteoporotic bone may fail, so avulsions reappear.
Mechanical Properties and Biomechanics
Ligaments have a characteristic non-linear stress-strain curve, and every part of it can be read off the hierarchical structure and the crimp.
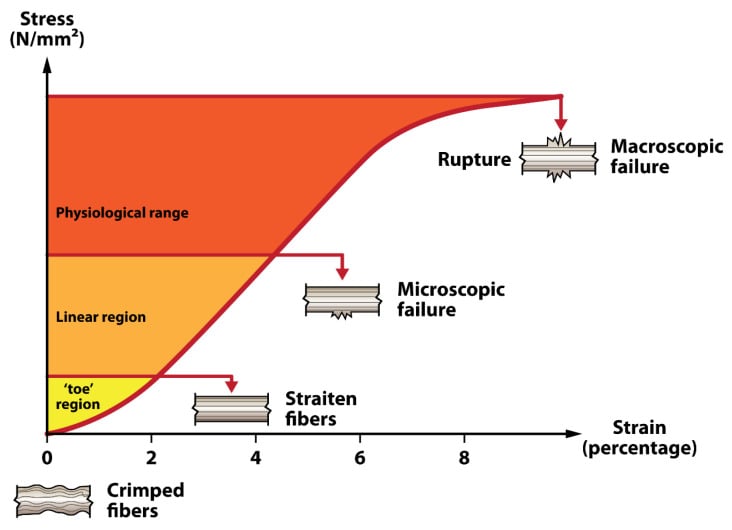
Toe region (0-3% strain). Stiffness is low and the curve is non-linear because the crimps are straightening without the collagen molecules being stretched. This is the physiological loading range for normal activities: it allows joint motion without generating high resistance, and it protects against impact loading.
Linear region (3-8% strain). Once the crimps are fully extended the collagen fibres bear the load directly and the ligament is stiff and linearly elastic, with an elastic modulus of 100-400 MPa depending on the ligament. Deformation is reversible if the load is removed before the yield point, and most ligament function occurs in the transition from toe to linear.
Yield point and plastic deformation (4-8% strain). Microstructural damage begins as interfibrillar sliding, the crimp pattern is disrupted, and the deformation becomes permanent. This is the clinical "sprain", a subfailure injury: partial recovery is possible but the mechanical properties are reduced, and continued loading may take it on to complete failure.
Failure region (over 8% strain). Macroscopic fibre failure and complete rupture, at an ultimate tensile stress of 20-100 MPa depending on the ligament. Which element gives way follows the age pattern described for the enthesis: midsubstance in adults, avulsion in children and the elderly, the enthesis itself with degeneration.
- Failure Load (N)
- 2160 (young)
- Stiffness (N/mm)
- 242
- Ultimate Stress (MPa)
- 38
- Clinical Note
- Falls to 658N in the 60-97 year age band
- Failure Load (N)
- 2000
- Stiffness (N/mm)
- 295
- Ultimate Stress (MPa)
- 28
- Clinical Note
- Thicker cross-section than ACL
- Failure Load (N)
- 3000
- Stiffness (N/mm)
- 140
- Ultimate Stress (MPa)
- 39
- Clinical Note
- Broad insertion distributes load
- Failure Load (N)
- 1500
- Stiffness (N/mm)
- 160
- Ultimate Stress (MPa)
- 45
- Clinical Note
- More prone to bony avulsion
- Failure Load (N)
- 2900
- Stiffness (N/mm)
- 660
- Ultimate Stress (MPa)
- 63
- Clinical Note
- Common ACL graft - high strength
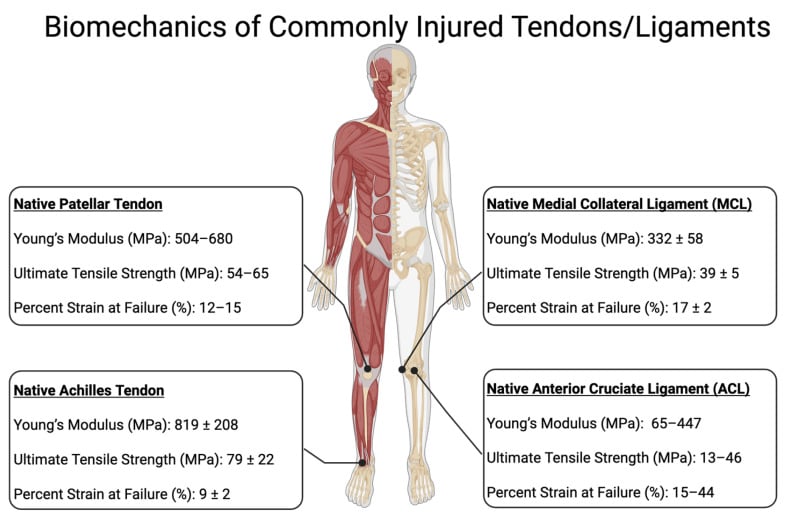
Viscoelastic Behaviour
Ligaments are viscoelastic: their mechanical response depends on the rate and duration of loading, not only its magnitude. Four phenomena follow, and each has a clinical face.
Creep. Deformation increases under a constant load over time, which is why joint laxity increases during prolonged static positioning. It recovers partially with rest, and the recovery is itself time-dependent.
Stress relaxation. At a fixed elongation the initially high stress gradually falls, as fluid is exuded and the fibres reorient. This is the phenomenon at work during graft tensioning in ACL reconstruction.
Hysteresis. The loading and unloading curves do not overlap, and the area between them is energy dissipated in the cycle, a protective mechanism. Hysteresis reduces with repetitive cycling, which is what preconditioning means.
Strain rate sensitivity. Faster loading produces a higher apparent stiffness; slower loading allows more viscoelastic deformation. It matters for the difference between dynamic and static testing and for reading the injury mechanism, and high-energy injuries may produce different patterns from low-energy ones.
Warm-up reduces injury risk by preconditioning ligaments through repetitive low-load cycling, which reduces hysteresis and optimises the viscoelastic response. Cyclic loading during rehabilitation promotes optimal collagen fibre alignment along stress lines (mechanotransduction). Creep during surgery explains why joint distraction increases over time with a constant retractor force.
Factors Affecting Mechanical Properties
Age. Strength peaks at 30-40 years and declines significantly after 50, as the cross-links change. The ACL's failure load falls from 2160 N at 22-35 years to 658 N at 60-97 years. With ageing the tissue becomes stiffer but its ultimate strength is reduced.
Sex. Females have 10-15% lower tensile strength, with hormonal influences, and a higher ACL injury risk, to which neuromuscular factors also contribute. Menstrual cycle phase may affect collagen synthesis.
Physical conditioning. Exercise increases collagen synthesis and cross-sectional area, and training raises the failure load by 10-20%. Immobilisation does the reverse and quickly: a 50% reduction in strength by 8 weeks.
Differential Diagnosis: Distinguishing Ligament Failure Patterns
When a ligamentous injury is suspected, the biology above explains why the failure pattern differs by age and loading, and which entities mimic a midsubstance tear.
- Typical patient / mechanism
- Adult, tensile overload
- Site of failure
- Within ligament substance
- Healing / management implication
- Intra-articular (ACL) heals poorly; extra-articular (MCL) heals by scar
- Typical patient / mechanism
- Child/adolescent or elderly
- Site of failure
- Bone at the enthesis (enthesis preserved)
- Healing / management implication
- Heals well by bone healing; fix if displaced - near-normal strength
- Typical patient / mechanism
- Older, chronic overload
- Site of failure
- Enthesis fibrocartilage (degenerative, not inflammatory)
- Healing / management implication
- Load management; degenerative process, limited self-repair
- Typical patient / mechanism
- Younger, inflammatory, often HLA-B27
- Site of failure
- Inflamed enthesis / synovio-entheseal complex
- Healing / management implication
- Rheumatological - DMARD/biologic therapy, not surgical
- Typical patient / mechanism
- Generalised hypermobility (e.g. Ehlers-Danlos)
- Site of failure
- Abnormal collagen / cross-linking diffusely
- Healing / management implication
- Higher recurrent instability and graft-stretch risk
Ligament Proprioception and Mechanoreceptors
Ligaments are not purely passive restraints. They are sensory organs that drive joint proprioception and protective neuromuscular reflexes, and the four mechanoreceptor types of the Freeman and Wyke classification lie mainly in the subsynovial tissue near the insertions:
- Ruffini endings - slow-adapting, low-threshold: joint position and static stretch
- Pacinian corpuscles - fast-adapting, low-threshold: acceleration, vibration and dynamic movement
- Golgi tendon organ-like receptors - slow-adapting, high-threshold: tension and the extremes of motion
- Free nerve endings - nociception, becoming active in inflammation
The ligamento-muscular reflex. Afferents from the ACL trigger a protective hamstring contraction, so the ACL contributes to dynamic stability and not only passive restraint.
After rupture. ACL rupture causes deafferentation and loss of proprioception, which contributes to functional instability and to quadriceps and hamstring neuromuscular dysfunction. Reconstruction restores mechanical stability, but proprioceptive recovery is incomplete because graft reinnervation is partial and delayed; that is part of the rationale for prolonged neuromuscular rehabilitation before return to sport, and for remnant-preserving (footprint-preserving) ACL reconstruction, which aims to retain the native mechanoreceptors and aid reinnervation.
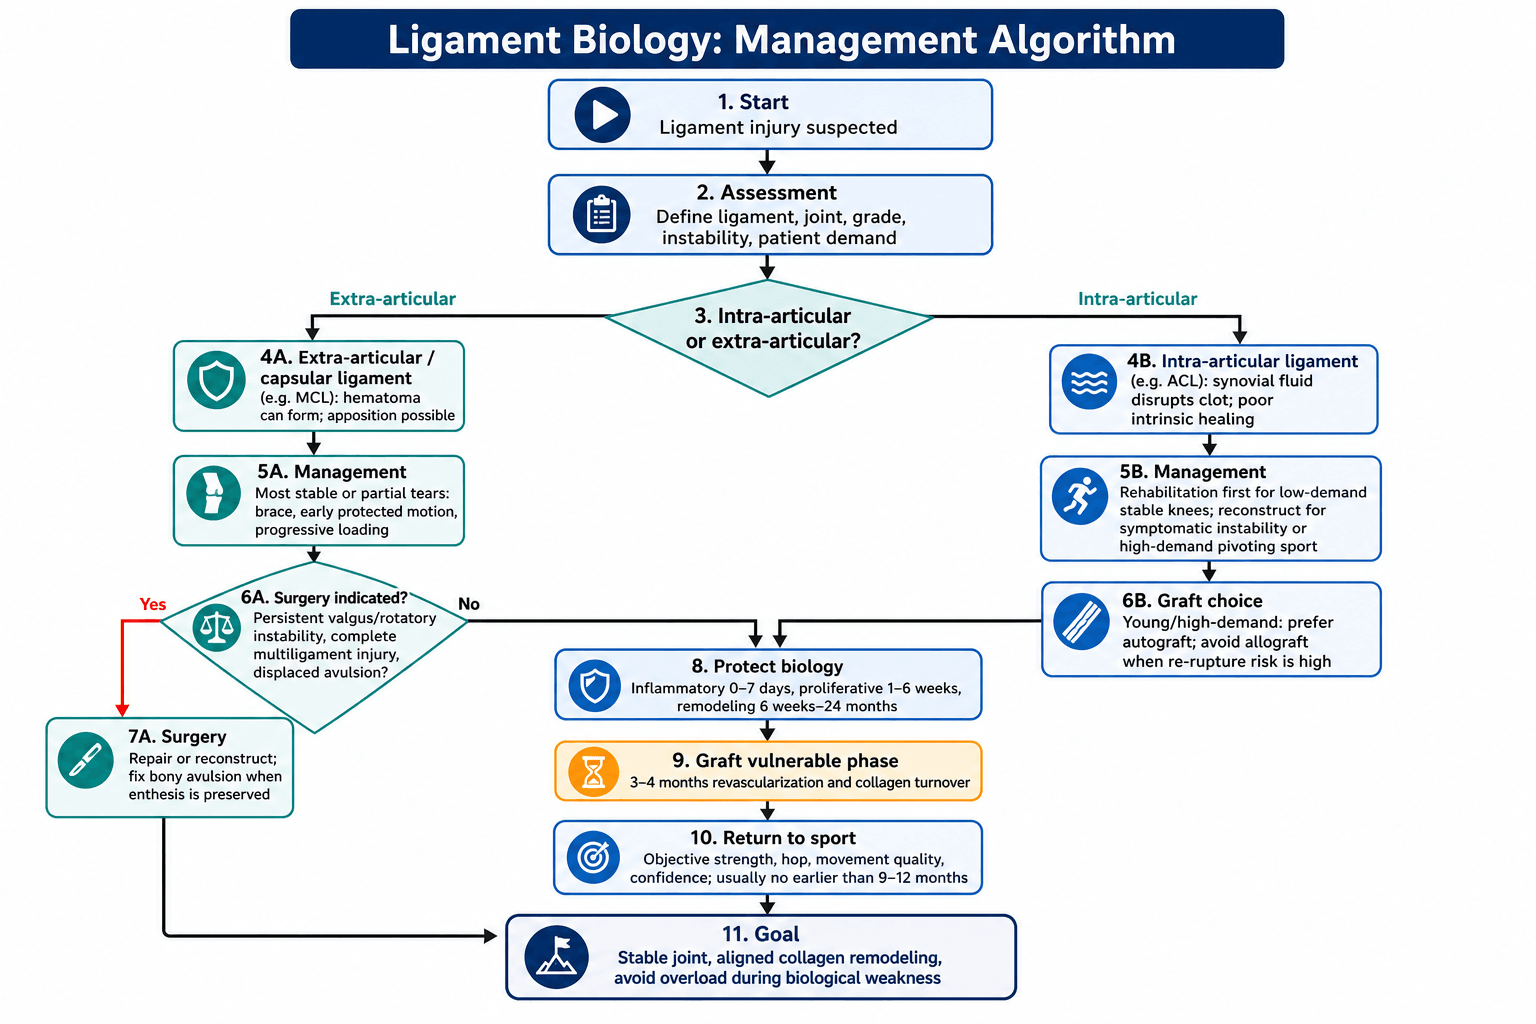
Management Algorithm
Clinical Relevance: Healing and Reconstruction
Ligament Healing and Remodelling
Three Phases of Healing
Ligament healing follows a predictable sequence, but it is prolonged and it is incomplete. Unlike bone, a ligament does not return to its native structure or full strength, and a midsubstance tear heals poorly because the tissue is dense and relatively avascular.
A haematoma forms at the injury site and platelets activate and degranulate. Neutrophils infiltrate first, peaking at 24-48 hours, then macrophages, peaking at 48-96 hours, which debride the necrotic tissue.
The platelets and inflammatory cells release the growth factors that set up repair: PDGF for fibroblast chemotaxis, TGF-β for collagen synthesis, VEGF for angiogenesis, together with IL-1 and TNF-α. The fibrin clot is the initial scaffold, granulation tissue begins to form, and mechanical strength is very low, under 10% of normal.
Fibroblasts proliferate and migrate into the injury, cellularity peaks at 2-3 weeks and then gradually declines, and myofibroblasts appear and contract the wound. New vessels grow in from the epiligament and bone.
The matrix they lay down is abundant, disorganised Type III collagen, which may reach 30% of the collagen against under 10% in the normal ligament, and proteoglycan content is increased. Strength rises but stays low, 10-30% of native by 6 weeks, stiffness is far below normal, and the tissue is vulnerable to re-injury if it is overstressed.
Type III collagen is gradually replaced by Type I, the fibres align along the lines of stress through mechanotransduction, and cross-linking increases with pyridinoline and deoxypyridinoline. Cellularity and vascularity fall back towards normal.
Strength rises along an asymptotic curve and plateaus at 50-70% of native tissue; stiffness increases but remains below normal, and the crimp pattern is only partially restored and irregular, which is why the healed tissue is less compliant. Collagen organisation stays more random than native, Type III persists at higher levels and cross-link density stays lower, and that is the biology behind the persistent laxity and re-injury risk. Rehabilitation therefore protects the tissue during the proliferative phase and applies controlled stress during remodelling to promote alignment.
IPRHealing Phases - IPR
Hook:IPR - Injury Provokes Repair but takes 12-24 months to complete!
Intra-articular versus extra-articular. The ACL and PCL heal poorly because of the synovial fluid environment: it dilutes the haematoma and washes away the fibrin clot, the growth factors are dispersed rather than concentrated at the injury, synoviocytes release proteases that degrade the matrix, and the mechanical stability is inadequate to keep the torn ends apposed. The MCL and LCL heal more reliably because a stable haematoma forms, the local growth factor milieu is preserved and there is less mechanical disruption. That is the biology behind managing grade 1-2 MCL injuries conservatively while ACL tears require reconstruction.
ACL Graft Remodelling (Ligamentisation)
The biological incorporation of the graft is what postoperative rehabilitation and patient counselling are built on, and it takes far longer than the patient feels it does.
Early incorporation (0-8 weeks). The autograft remains viable: human biopsies show living fibroblasts from 3 weeks, and it remodels without passing through a frankly necrotic stage (Rougraff 1993, in the evidence below). The "central necrosis then creeping substitution" sequence is the animal model and should not be quoted as established human fact. An allograft is different: processing and freezing devitalise it, so it starts acellular and must be repopulated, and the necrosis-and-repopulation model genuinely applies. In this phase the bone tunnel is the weakest link, as a fibrovascular interface forms rather than a native enthesis; the graft's initial strength is high but falls as remodelling begins, so aggressive loading is avoided to protect the bone-graft interface.
Revascularisation (8-12 weeks). Blood vessels grow into the graft from the synovium and the bone tunnels, synovial cells migrate in and produce a hypercellular synovial response, and inflammatory cells infiltrate. This is the start of the graft weakening phase, in which mechanical properties transiently decrease; the graft is at its most vulnerable at 3-4 months, a paradox because the patient by then looks recovered.
Cellular remodelling (3-12 months). Fibroblasts replace the synovial cells and collagen turns over, old fibres degraded and new ones synthesised, with gradual realignment along the lines of stress. The Type I proportion rises, cellularity falls towards that of a normal ligament, and strength increases but remains below the native ACL.
Maturation (12-24 months). Histological appearance approaches that of native ligament, the crimp pattern is partially restored, and cross-linking increases, but strength plateaus at 50-70% of the intact ACL. Rougraff's biopsy series found grafts ligamentous by every histological criterion only by 3 years, and Claes found no consensus on the precise time frame of the stages in humans, so the phase boundaries are guides rather than fixed dates. Neuromuscular recovery may be the limiting factor for function, and return to full pivoting sport is 9-12 months at minimum.
Bone tunnel healing. The tunnel heals with an initial fibrovascular scar, not a four-zone enthesis; Sharpey-like fibres develop by 8-12 weeks and provide mechanical anchorage that is weaker than native. Tunnel widening is common, a biological remodelling response. An interference screw provides stability during early healing, whereas suspensory fixation relies on the strength of the graft-fixation construct.
Graft Biology and Surgical Considerations
Autograft Options
- Advantages
- High strength (2900N), bone-bone healing (8-12wk), rigid fixation
- Disadvantages
- Anterior knee pain (20-30%), patellar fracture risk, kneeling discomfort
- Remodelling Timeline
- Faster bone healing, plateau 12-18mo
- Advantages
- Low donor morbidity, high strength (4000N), larger diameter
- Disadvantages
- Slower bone-tendon healing, fixation challenges, hamstring weakness
- Remodelling Timeline
- Slower integration, plateau 18-24mo
- Advantages
- Large, strong graft, minimal morbidity, partial bone block option
- Disadvantages
- Less studied, potential extensor lag if overharvested
- Remodelling Timeline
- Similar to patellar tendon, 12-18mo
Allograft Considerations
What it offers. No donor site morbidity, a shorter operative time, less postoperative pain, and availability of larger grafts, which matters in multi-ligament reconstruction.
What it costs. A disease transmission risk that is screened for but not zero; slower revascularisation and incorporation; processing by irradiation or chemicals that may weaken the graft; a higher failure rate in young, active patients under 25; and a low-grade immune response that does not cause rejection but slows healing.
Autograft versus allograft biology. The autograft revascularises earlier, at 8-10 weeks, against 10-14 weeks for the allograft, which must first be repopulated. Both plateau below native strength, but the autograft may reach its plateau faster, by 3-6 months. Clinical outcomes are similar, but autograft is preferred in the young, active patient, and in revision the MARS cohort showed that autograft cuts the rerupture risk.
Processing. The method used to prepare the allograft changes its biology:
- Fresh-frozen: minimal processing, fastest incorporation, the standard choice
- Irradiated (over 2.5 Mrad): weakens collagen, slower incorporation
- Chemically processed (proprietary): variable effects on strength and biology
Synthetic Grafts
Permanent synthetic ligaments. Historically poor outcomes, with wear debris, synovitis and failure. They lack biological integration and their stress shielding prevents graft remodelling, so they have been generally abandoned except in specialised cases.
Synthetic scaffolds (investigational). These give temporary mechanical support during healing and are designed to degrade as native tissue regenerates, promoting cell infiltration and matrix deposition. Clinical efficacy is not yet proven.
Growth Factors and Biological Augmentation
The growth factors of ligament healing, each with the job it does:
- PDGF: fibroblast chemotaxis and proliferation
- TGF-β: collagen synthesis, matrix production
- VEGF: angiogenesis, vascular invasion
- IGF-1: cell proliferation, matrix synthesis
- BMP-12/13: tendon and ligament differentiation
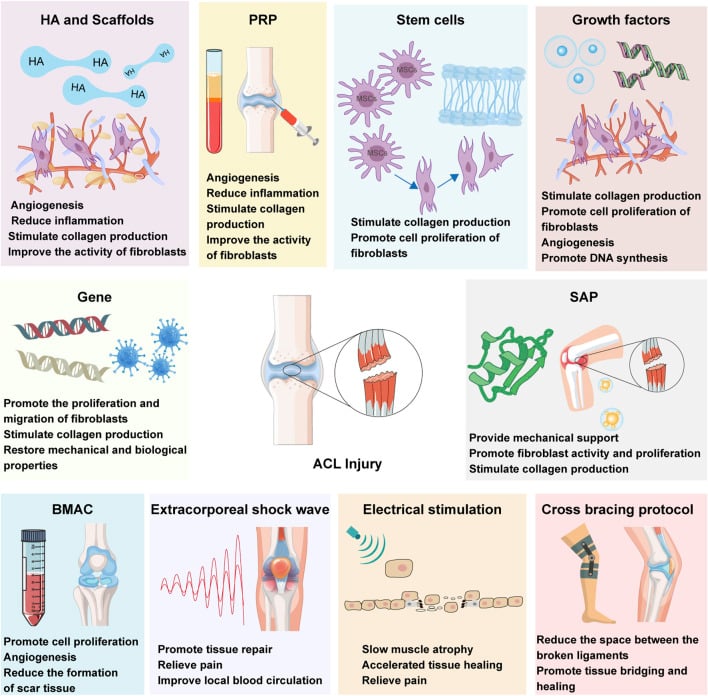
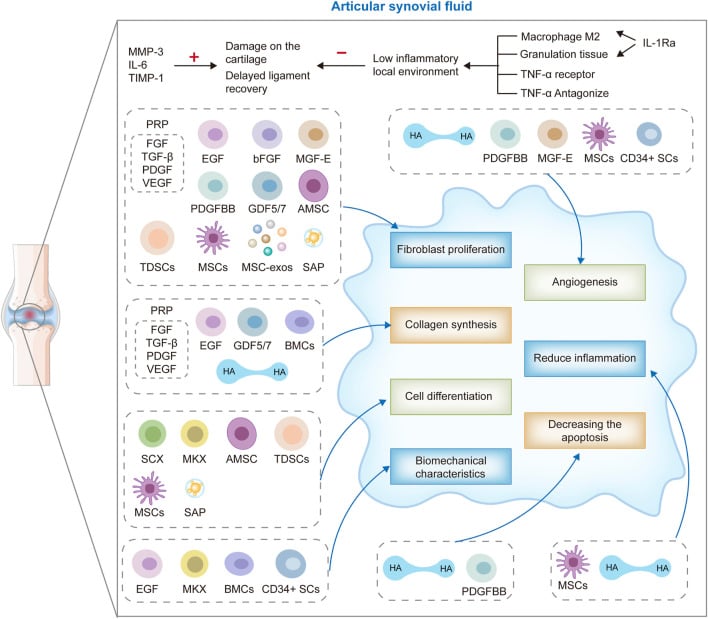
Clinical applications, all investigational. Platelet-rich plasma has variable evidence and is not standard of care; stem cell augmentation is early research and not proven effective; and growth factor injections carry a risk of ectopic ossification with BMPs.
Mechanical augmentation. Suture tape augmentation of an ACL reconstruction provides temporary mechanical support while the graft remodels and may reduce early graft elongation. It does not replace the need for an adequate graft and adequate fixation.
Guidelines, Registries & Global Practice
Global Epidemiology
Ligament injury - dominated clinically by ACL rupture - is a worldwide burden, and the figures below are population- or registry-derived rather than estimates.
- Figure
- 68.6 per 100,000 person-years
- Population / Source
- US population-based, Sanders 2016 (PMID 26920430)
- Figure
- 81.7 vs 55.3 per 100,000
- Population / Source
- Same cohort (PMID 26920430)
- Figure
- 19-25 yrs (241.0 per 100,000)
- Population / Source
- Same cohort (PMID 26920430)
- Figure
- 14-18 yrs (227.6 per 100,000)
- Population / Source
- Same cohort (PMID 26920430)
- Figure
- 160,353 over 2001-2020; up 82% (peak 10,011 in 2017)
- Population / Source
- Campbell 2024, privately-insured cohort (PMID 39135546)
- Figure
- 64% male / 36% female
- Population / Source
- Same cohort (PMID 39135546)
The female adolescent peak (14-18 yrs) and the rising surgical rate across all ages are consistent international findings, underpinning sex-specific neuromuscular prevention programmes and service planning.
Guideline & Registry Positions (Side-by-Side)
- Position relevant to ligament biology & ACLR
- Autograft favoured over allograft in young/active patients to reduce re-rupture; emphasises function- and time-based return to sport
- Evidence basis
- Clinical practice guideline + cohort data
- Position relevant to ligament biology & ACLR
- ACL reconstruction reserved for symptomatic instability or failed rehabilitation; structured rehabilitation first-line for many tears
- Evidence basis
- Guideline / consensus (Level 1-2)
- Position relevant to ligament biology & ACLR
- Graft remains ultrastructurally distinct after ligamentization; protect graft through maturation; individualise graft choice
- Evidence basis
- Systematic review evidence, Claes 2011 (PMID 21515806)
- Position relevant to ligament biology & ACLR
- Autograft 2.78x less re-rupture than allograft at revision; soft-tissue and BPTB equivalent
- Evidence basis
- Prospective cohort, Level 2 (PMID 25274353)
- Position relevant to ligament biology & ACLR
- Track graft type, re-revision and patient-reported outcomes to monitor practice variation
- Evidence basis
- Registry data
Practice Variation
- Graft choice varies by region: hamstring autograft predominates in much of Europe and Australasia, while bone-patellar tendon-bone retains strong support in North America; allograft use is higher in older or revision populations and lower in young athletes owing to re-rupture risk.
- Operative vs non-operative thresholds differ: UK and Scandinavian practice apply a rehabilitation-first pathway for many ACL tears, whereas earlier reconstruction is more common in high-demand athletes and in systems with rapid access to surgery.
- Return-to-sport criteria are converging on a minimum of roughly 9-12 months plus objective functional and psychological testing, reflecting graft-maturation biology rather than symptom resolution alone.
Exam Relevance
- Ligament biology is a core basic-science viva topic: examiners probe hierarchical structure, the four-zone enthesis, stress-strain curve regions and the healing phases.
- High-yield testable points: Type I collagen dominance, crimping and the toe region, the graft weakening phase, and the intra-articular versus extra-articular healing distinction with its management consequences.
MCQ Practice Points
Q: What percentage of ligament dry weight is Type I collagen?
A: 70-80%. Type I collagen provides tensile strength and is the predominant structural protein. Type III collagen is present in smaller amounts (under 10% in normal ligaments) and increases during healing (up to 30%) but should decrease with remodeling. Persistent Type III elevation indicates incomplete maturation of scar tissue.
Q: What are the four zones of the fibrocartilaginous enthesis from ligament to bone?
A: Ligament → Fibrocartilage → Mineralized Fibrocartilage → Bone (remember LFMB). This graded transition minimizes stress concentration at the insertion site. Zone 2 (fibrocartilage) resists compressive forces, Zone 3 (mineralized FC) provides biomechanical gradient, and Zone 4 (bone) anchors via Sharpey fibers.
Q: What percentage of native ligament strength do healed ligaments typically achieve after complete remodeling?
A: 50-70% even after 12-24 months of remodeling. Scar tissue has disorganized collagen, increased Type III collagen, reduced crimp pattern, and fewer mature cross-links compared to native tissue. This incomplete restoration explains persistent laxity risk after ligament injuries and why grafts never achieve 100% native strength.
Q: Why does the MCL heal more reliably than the ACL after injury?
A: MCL is extra-articular - stable hematoma forms, growth factors concentrate at injury site, mechanical apposition can be maintained with bracing. ACL is intra-articular - synovial fluid dilutes hematoma, washes away growth factors, synoviocytes release proteases that degrade matrix, mechanical instability prevents apposition. This biological difference explains conservative MCL treatment versus surgical ACL reconstruction.
Q: What causes the toe region of the ligament stress-strain curve?
A: Straightening of crimped collagen fibrils without stretching the collagen molecules themselves. The crimping pattern (wavy appearance with 20-100 micrometer period) allows initial loading at low stiffness (0-3% strain). Once crimps fully extend, the linear region begins (3-8% strain) where collagen fibers resist tension directly with high elastic modulus (100-400 MPa).
Q: When does the graft weakening phase occur after ACL reconstruction?
A: 3-4 months post-reconstruction during the revascularization phase. As blood vessels grow into the graft from synovium and bone tunnels, there is hypercellular response and active collagen turnover. Mechanical properties transiently decrease during this phase despite clinical appearance of recovery. This is a critical vulnerable period requiring continued activity restrictions.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“Examiner presents a stress-strain curve for a ligament and asks: Explain the four regions of this curve and how they relate to the hierarchical structure of ligaments.”
“A 22-year-old professional footballer had ACL reconstruction with hamstring autograft 4 months ago. He has regained full range of motion and muscle strength, and wants to know when he can return to competitive football. Explain the biological basis for the timeline you recommend.”
“Examiner asks: Why do we typically manage isolated MCL injuries conservatively while ACL tears require surgical reconstruction? Explain the biological basis for this difference in treatment approach.”
“Examiner shows a diagram of the ligament-bone insertion and asks: Describe the structure of the enthesis and explain why bony avulsion fractures heal better than midsubstance ligament tears.”
Composition
- Type I collagen: 70-80% dry weight (main structural protein, tensile strength)
- Type III collagen: under 10% normal (increases to 30% in healing, should decrease)
- Water: 60-80% total weight (viscoelasticity, nutrient transport)
- Proteoglycans: 1-3% (decorin, biglycan - organize fibrils, resist compression)
- Elastin: 1-5% (70% in ligamentum flavum - unique elastic ligament)
- Cells: 90-95% fibroblasts, 5-10% chondrocytes/synovial/vascular cells
Hierarchical Structure
- Tropocollagen: 300nm × 1.5nm triple helix (3 alpha chains, basic unit)
- Microfibril: 5 staggered tropocollagen, 67nm D-period banding pattern
- Subfibril: 10-20nm assembled microfibrils, cross-linking begins
- Fibril: 50-500nm bundles with crimping pattern (20-100 micrometer period)
- Fascicle: Fibril bundles + endoligament sheath (functional unit)
- Ligament: Fascicle groups + epiligament (macroscopic structure)
Four-Zone Enthesis (LFMB)
- Zone 1 - Ligament: Dense regular CT, aligned Type I collagen
- Zone 2 - Fibrocartilage: Chondrocytes appear, Type II increases, resists compression
- Zone 3 - Mineralized FC: Hydroxyapatite crystals, tidemark, Type X collagen
- Zone 4 - Bone: Sharpey fibers anchor ligament, vascular supply
- Function: Graded modulus (100-400 MPa → 10-20 GPa) minimizes stress concentration
- Clinical: Does not regenerate after surgery, bony avulsions heal better
Stress-Strain Curve Regions
- Toe (0-3% strain): Crimp straightening, low stiffness, physiological loading
- Linear (3-8% strain): Collagen fibers resist directly, modulus 100-400 MPa
- Yield (4-8% strain): Microstructural damage, permanent deformation, sprain
- Failure (over 8% strain): Macroscopic rupture, UTS 20-100 MPa
Mechanical Properties
- ACL: 2160N failure load (young), 242 N/mm stiffness, 38 MPa UTS
- PCL: 2000N failure, 295 N/mm stiffness, thicker than ACL
- MCL: 3000N failure, 140 N/mm stiffness, broad insertion distributes load
- Patellar tendon: 2900N failure, 660 N/mm stiffness (common ACL graft)
- Viscoelastic: Creep, stress relaxation, hysteresis, strain rate dependent
- Age: Strength peaks 30-40 years, ACL drops 70% by age 60-97
Healing Timeline (IPR)
- Inflammatory (0-7 days): Hematoma, neutrophils, macrophages, PDGF/TGF-β/VEGF
- Proliferative (7d-6wk): Fibroblasts, Type III collagen (up to 30%), neovascularization, strength 10-30%
- Remodeling (6wk-24mo): Type I replaces Type III, alignment, cross-linking, strength plateaus 50-70%
- Incomplete restoration: Disorganized collagen, persistent Type III, reduced cross-links
ACL Graft Remodeling (4 Phases)
- 0-8 weeks: Avascular graft, bone tunnel weakest link, protect interface
- 8-12 weeks: Revascularization from synovium/bone tunnels, hypercellular response
- 3-4 months: GRAFT WEAKENING PHASE - critical vulnerable period despite clinical recovery
- 3-12 months: Cellular remodeling, collagen turnover, strength increases gradually
- 12-24 months: Maturation, histology approaches native, plateaus at 50-70% strength
- Return to sport: Minimum 9-12 months based on biology, not subjective recovery
Intra-Articular vs Extra-Articular Healing
- Intra-articular (ACL, PCL): Poor healing - synovial fluid dilutes hematoma, disperses growth factors, proteases degrade matrix, mechanical instability
- Extra-articular (MCL, LCL): Better healing - stable hematoma, concentrated growth factors, vascular supply, mechanical protection possible
- Clinical: MCL grades 1-2 conservative, ACL requires reconstruction
- Bony avulsion: Excellent healing - preserves enthesis, cancellous bone vascularity
Key Exam Numbers
- Type I collagen: 70-80% dry weight
- Water content: 60-80% total weight
- Healing strength: 50-70% native maximum
- ACL young adult: 2160N failure (drops to 658N by age 60-97)
- Graft weakening: 3-4 months post-reconstruction
- Return to sport: 9-12 months minimum
- Enthesis transition: Under 1mm distance, 50-100× modulus increase
Evidence Base
Human Patellar Tendon Autograft Ligamentization (Landmark Biopsy Study)
- 23 patients biopsied 3 weeks to 6.5 years post-reconstruction - patellar tendon autograft is viable as early as 3 weeks (may not pass through a frankly necrotic stage)
- Stage of rapid remodelling over the first year: fibroblast count and neovascularity rise while the proportion of mature collagen falls (correlates with the graft weakening phase)
- Maturation stage over the subsequent 2 years with declining cellularity and maturing collagen matrix
- By 3 years grafts were ligamentous by all histological criteria, but full ligamentization takes as long as 3 years
Age-Related Changes in ACL Mechanical Properties (Landmark Cadaveric Study)
- 27 paired cadaver knees in three age bands - younger (22-35), middle (40-50) and older (60-97 years)
- Femur-ACL-tibia complex ultimate load and linear stiffness fell significantly with specimen age
- Younger specimens (anatomical orientation): linear stiffness 242 plus or minus 28 N/mm and ultimate load 2160 plus or minus 157 N - higher than previously reported baselines
- Structural properties were higher in the anatomical than tibial loading orientation, informing graft selection targets
MCL Heals by Scar Formation - Never Reaches Normal (Landmark Study)
- Complete midsubstance MCL gaps in a rabbit model heal by distinct bridging scar over time, not by true ligament regeneration
- Gap bridging is rapid, but subtle changes in the healing tissue continue for many months
- The ligament scar remains structurally, chemically and mechanically abnormal even at long-term follow-up
- Improvement plateaus, suggesting the scar may never approach normal ligament characteristics without treatment
Enthesis Structure-Function and Stress Dissipation (Landmark Review)
- Fibrocartilaginous entheses are sites of stress concentration where the graded soft-to-hard tissue transition dissipates load and limits fibre bending at the bone interface
- Enthesis fibrocartilage is normally avascular and adapts to mechanical load; the surrounding 'enthesis organ' (fat pad, bursa, adjacent bone) jointly dissipates stress
- Most insertional enthesopathies in sport are degenerative rather than inflammatory
- Entheses have limited intrinsic capacity for self-repair, relevant to surgical reattachment
Ligamentization of the Human ACL Graft (Systematic Review)
- Systematic review of human graft biopsy studies - a free tendon graft replacing the ruptured ACL undergoes a biological process termed 'ligamentization'
- The graft remains viable throughout; mature grafts may histologically resemble native ACL
- Ultrastructural differences in collagen fibril diameter distribution persist - the graft never fully replicates native ACL architecture
- No consensus exists on the precise time frame of the ligamentization stages in humans
Graft Choice in Revision ACL Reconstruction (MARS Cohort)
- Prospective multicentre cohort of 1205 revision ACL reconstructions (48% autograft, 49% allograft) followed to 2 years
- Autograft predicted superior 2-year IKDC and KOOS sport and quality-of-life subscale scores
- Graft rerupture occurred in 37 of 1112 patients (3.3%): autograft revision was 2.78 times less likely to rerupture than allograft (95% CI 1.01-7.69)
- No difference in rerupture between soft-tissue and bone-patellar tendon-bone grafts
Population Incidence of ACL Tears and Reconstruction (21-Year Study)
- Population-based study of 1841 new isolated ACL tears (1990-2010) - overall age- and sex-adjusted incidence 68.6 per 100,000 person-years
- Higher in males than females (81.7 versus 55.3 per 100,000)
- Peak incidence at 19-25 years in males (241.0 per 100,000) and at 14-18 years in females (227.6 per 100,000)
- Rate of ACL reconstruction increased significantly over time across all age groups