Magnetic Resonance for Orthopaedic Surgeons
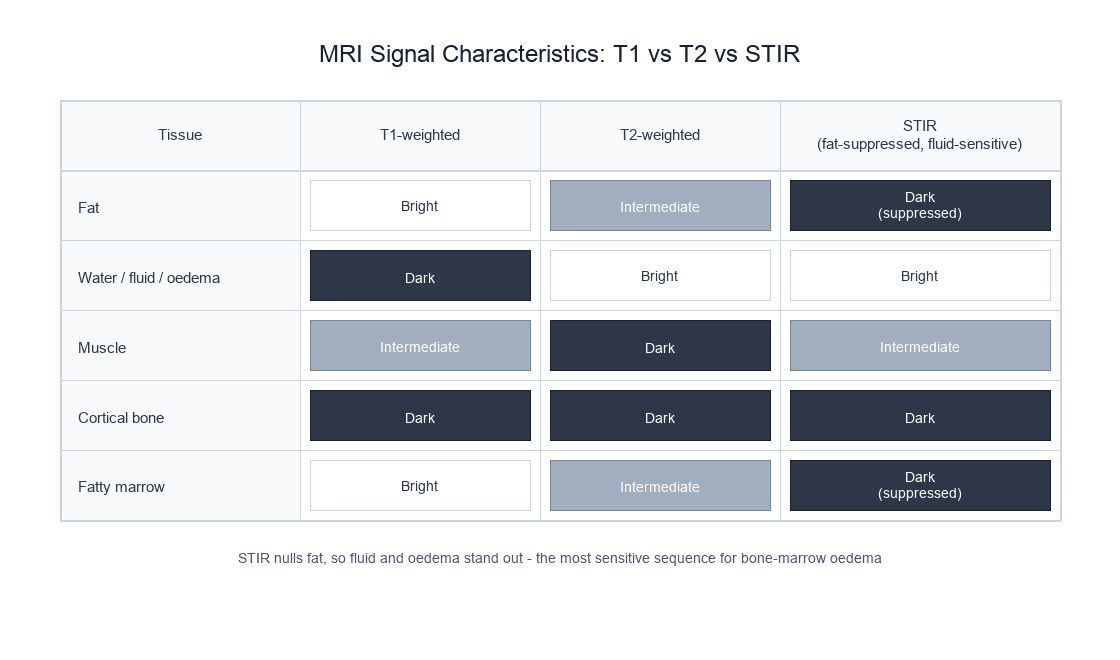
T1-weighted: Fat = bright, Muscle = grey, Water = dark, Bone cortex = dark (no signal)
T2-weighted: Water = bright, Fat = intermediate, Muscle = dark, Bone cortex = dark
STIR: Water/oedema = bright, Fat = suppressed (dark), Pathology highlighted
T1 + Gadolinium: Enhancing tissue = bright (tumour, infection, synovitis)
Key: The appearance of a tissue on MRI depends on the pulse sequence used — the same tissue can appear different on T1 vs T2
- MRI uses strong magnetic fields and radiofrequency pulses — NO ionising radiation. Safe for repeated imaging.
- Signal comes from hydrogen protons (H+) in water and fat, which are abundant in all musculoskeletal tissues.
- T1 relaxation (longitudinal recovery) determines signal differences based on molecular environment: fat is bright, water is dark on T1.
- T2 relaxation (transverse decay) determines signal based on free water content: water is bright, fat is intermediate on T2.
- MRI is the reference test for soft tissue assessment - ligaments, tendons, cartilage, bone marrow oedema, infection - but put a number on it: against arthroscopy its pooled accuracy for knee internal derangement is around 85 percent, so roughly one study in seven is called wrongly and a confident clinical examination is not overruled by an equivocal scan.
- “T1-weighted: fat = bright white, muscle = grey, water/fluid = dark. Best for anatomy and fat-containing pathology.
- “T2-weighted: water/fluid = bright white, fat = intermediate grey, muscle = dark. Best for pathology detection (oedema, effusion, tears).
- “STIR/fat-suppressed T2: suppresses fat signal to highlight oedema — the most sensitive sequence for bone marrow oedema.
- “Gadolinium shortens T1, making enhancing tissue bright on T1-weighted images — used for tumour, infection, and synovitis assessment.
- “MRI contraindications: cardiac pacemakers (non-MRI-conditional), cochlear implants, ferromagnetic foreign bodies, certain vascular clips.
Overview
Magnetic resonance imaging (MRI) is the gold standard imaging modality for soft tissue assessment in orthopaedic practice. Plain radiography and CT rely on ionising radiation and differential X-ray absorption; MRI uses strong magnetic fields and radiofrequency (RF) pulses and builds its image from the behaviour of hydrogen protons within tissue. The result is unparalleled soft tissue contrast, between ligament, tendon, cartilage, muscle, fat and fluid, that CT cannot reliably provide, and no radiation exposure.
When MRI is the test. Its multiplanar capability and freedom from ionising radiation make it particularly valuable in paediatric imaging and for serial monitoring, and safe for children and pregnant patients. It is the modality of choice for:
- Ligament and tendon injuries (ACL, rotator cuff, Achilles)
- Meniscal pathology
- Articular cartilage: MRI is the only non-invasive modality that directly images cartilage thickness and integrity
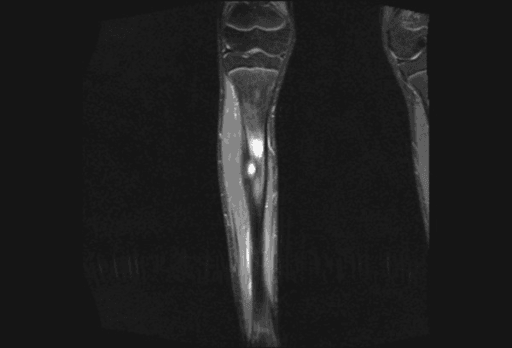
- Bone marrow oedema from occult fractures, stress reactions and contusions, which STIR and fat-suppressed sequences uniquely detect
- Avascular necrosis, which marrow signal change reveals months before plain radiographs
- Soft tissue and bone tumour characterisation
- Infection: osteomyelitis and septic arthritis
- Spinal cord and nerve root assessment
- Paediatric musculoskeletal conditions
When CT is better. MRI has inferior spatial resolution for cortical bone compared with CT, and there are questions CT answers better:
- Complex fracture characterisation (acetabulum, tibial plateau, calcaneus)
- Cortical bone detail and fracture lines
- Preoperative 3D planning
- Lung metastasis screening
- Calcification patterns (tumour matrix, CPPD)
- Patients with MRI contraindications
- Acute trauma where speed is critical
Limitations. Acquisition is long (20-45 minutes). Claustrophobia, contraindications in patients with certain implants, significant metal artefact from orthopaedic hardware and high cost are the other principal limitations.
MRI Physics Fundamentals
The signal source
Hydrogen. The MRI signal originates from hydrogen protons (H+), the most abundant MRI-visible nuclei in the body because water (H2O) and fat (CH2) are everywhere in tissue. Each proton has spin angular momentum, which gives it a small magnetic moment: every proton is a tiny bar magnet.
Net magnetisation. Outside a magnetic field those moments point randomly and cancel each other out. Inside the scanner's main field (B0, typically 1.5 or 3 Tesla) they align either parallel to it, the low-energy state taken by a slight majority, or anti-parallel, the high-energy state. That small excess of parallel protons is the net magnetisation vector, and it is what the scanner measures.
Precession and the Larmor equation
Precession. Aligned protons do not sit still. They precess, wobbling around the direction of B0 as a spinning top wobbles around the gravitational axis, at a frequency set by the Larmor equation, ω = γ × B0, where γ is the gyromagnetic ratio, 42.58 MHz/T for hydrogen. At 1.5T protons precess at approximately 63.87 MHz and at 3T at approximately 127.74 MHz, and this is the frequency the radiofrequency pulse must have to excite them.
Excitation and relaxation
T1, longitudinal recovery. An RF pulse tilts the net magnetisation vector away from the B0 axis. The protons then gradually recover their longitudinal magnetisation along B0, releasing energy to the surrounding molecular lattice, which is why T1 is also called spin-lattice relaxation. T1 is the time constant for 63% recovery of the longitudinal magnetisation.
Why fat is bright on T1. Recovery is fast when protons can hand their excess energy to the lattice efficiently, and that happens when molecular tumbling frequencies match the Larmor frequency. Fat molecules tumble close to it, so fat has a short T1 (approximately 250 ms at 1.5T), recovers quickly and appears bright. Small, rapidly tumbling water molecules transfer energy poorly, so water has a long T1 (approximately 2500 ms at 1.5T) and appears dark; muscle lies between the two and appears grey. T1-weighted images give excellent anatomical detail because fat draws natural high-contrast boundaries between structures.
T2, transverse decay. At the same time, the transverse magnetisation created by the RF pulse decays as protons lose phase coherence with each other through interactions between neighbouring protons, which is why T2 is also called spin-spin relaxation. T2 is the time constant for the transverse magnetisation to decay to 37% of its initial value, and the rate depends on how homogeneous the local magnetic field around each proton is.
Why water is bright on T2. Rapidly tumbling water molecules average out local field inhomogeneities and keep phase coherence for a long time, so free water (effusion, oedema, CSF) has a long T2 (approximately 2500 ms), retains signal and appears bright. Fat has an intermediate T2 (approximately 80 ms) and appears intermediate grey; muscle dephases rapidly through complex molecular interactions, has a short T2 (approximately 35 ms) and appears dark. Cortical bone has essentially no mobile protons and a very short T2, so it is a signal void on every sequence. Because inflammation, oedema, tears and infection all raise tissue water content, T2-weighted images are the pathology sequences.
TR and TE: the parameters that control weighting
Intrinsic versus operator. T1 and T2 are intrinsic tissue properties; you cannot change them. What the operator controls are two timing parameters that decide how much T1 or T2 contrast appears in the final image: the repetition time (TR) and the echo time (TE).
TR controls T1 weighting. TR is the time between successive RF excitation pulses, so it governs how much longitudinal recovery is allowed before the next pulse. A short TR catches fat recovered and water not, exaggerating the differences in T1 recovery; a long TR lets nearly all tissues recover fully and erases them.
TE controls T2 weighting. TE is the interval between the RF pulse and sampling of the echo, so it governs how much transverse decay has occurred before the signal is read. A long TE lets short-T2 tissues decay away while long-T2 water still gives signal, maximising T2 contrast; a short TE samples before much decay and erases T2 differences.
- TR
- Short (~400-700 ms)
- TE
- Short (~10-20 ms)
- Contrast source
- Differences in T1 recovery (fat bright, water dark)
- TR
- Long (~2000-4000 ms)
- TE
- Long (~80-120 ms)
- Contrast source
- Differences in T2 decay (water bright)
- TR
- Long (~2000-4000 ms)
- TE
- Short (~10-20 ms)
- Contrast source
- Minimises both T1 and T2 effects - contrast reflects proton (water) density
- TR
- Long, with inversion pulse
- TE
- Long, TI ~150-170 ms at 1.5T
- Contrast source
- Inversion time chosen to null fat; fluid-sensitive and fat-suppressed
The two-line rule. Short TR = T1, long TE = T2. If you remember one thing about weighting, remember that TR drives T1 contrast and TE drives T2 contrast. Proton-density images deliberately pair a long TR with a short TE so that neither relaxation dominates and the signal mainly reflects how many protons are present, which is why PD is the workhorse for menisci and cartilage.
Spatial encoding: turning signal into an image
Gradients. Relaxation explains contrast; a separate set of principles explains how the scanner knows where each signal came from. Three orthogonal gradient coils superimpose a small, linear, position-dependent variation onto the main B0 field, so that the Larmor frequency now varies with position. Each gradient has one job:
- Slice selection: applied during the RF pulse, so only the slice whose Larmor frequency matches the RF bandwidth is excited; gradient steepness and RF bandwidth set slice thickness and position
- Frequency encoding (readout): applied during signal sampling, so precession frequency varies along one in-plane axis and position along that axis is encoded as signal frequency
- Phase encoding: a brief gradient applied before readout imparts a position-dependent phase shift along the perpendicular axis; the sequence is repeated many times with stepped phase-encode strengths to build up the second spatial dimension
k-space. The acquired data fill a matrix called k-space, the spatial-frequency domain, and a two-dimensional inverse Fourier transform of it reconstructs the anatomical image. The centre of k-space carries image contrast (low spatial frequencies, overall signal) and the periphery carries fine detail and edges (high spatial frequencies), a fact that underpins fast-imaging and artefact behaviour.
Why it matters for artefacts. Encoding fixes the direction an artefact takes. Each phase step is a separate acquisition, so movement between steps smears that axis: motion and pulsation artefacts propagate along the phase-encode direction, while chemical-shift misregistration occurs along the frequency-encode direction. Knowing which gradient does what lets you swap the phase and frequency directions to move an artefact away from the area of interest.
Key MRI Sequences
The sequences you will be shown, what each makes bright, and what each is for:
- Signal Characteristics
- Fat = bright, Muscle = grey, Water = dark, Cortex = dark
- Best For
- Anatomical detail, fatty infiltration, subacute haemorrhage, post-gadolinium enhancement
- Signal Characteristics
- Water = bright, Muscle = dark, Cortex = dark. Fat is intermediate on conventional spin echo but stays bright on the fast spin echo used clinically (see below)
- Best For
- Pathology detection: effusions, oedema, meniscal tears, ligament injuries
- Signal Characteristics
- Between T1 and T2; intermediate contrast
- Best For
- Meniscal tears (gold standard), cartilage assessment, ligament detail
- Signal Characteristics
- Fat signal suppressed; water/oedema = very bright
- Best For
- Bone marrow oedema (most sensitive), occult fractures, stress reactions, tumour spread
- Signal Characteristics
- Similar to STIR but uses chemical fat saturation instead of inversion
- Best For
- Bone marrow oedema, ligament tears, tendon pathology
- Signal Characteristics
- Enhancing tissue = bright on T1; non-enhancing = dark
- Best For
- Tumour vascularity, infection (abscess rim), active synovitis, post-operative assessment
- Signal Characteristics
- Susceptibility sensitive; blooming of haemosiderin and calcification
- Best For
- Haemosiderin (PVNS), calcification, cartilage surface (T2*-weighted GRE)
Why fat suppression is needed at all
Conventional versus fast spin echo. The classic teaching table says fat is intermediate on T2, and on a conventional spin-echo acquisition that is true. But almost no musculoskeletal MRI is acquired that way. Clinical scanning uses fast (turbo) spin echo, FSE/TSE, which replaces the single refocusing pulse with a train of them, collects several lines of data per excitation, and cuts a twenty-minute sequence to two or three minutes.
What the speed costs. The rapid succession of refocusing pulses disrupts the J-coupling between lipid protons and lengthens fat's effective T2, so on FSE T2 fat does not go intermediate; it stays bright. A fluid-sensitive sequence in which fat is also bright cannot show you marrow oedema, because the oedema you are hunting is surrounded by fat that is just as white. This is the reason fat suppression exists, and it is the answer to "why did you ask for a STIR?"
Two other FSE consequences. The echo train causes some blurring of fine detail, because echoes late in the train are collected with decayed signal. And FSE is markedly less sensitive to susceptibility than gradient echo, which is why FSE is the sequence of choice around metal and why you switch to GRE when you actually want blooming to find haemosiderin in PVNS.
STIR versus fat-suppressed T2. Both highlight oedema by removing the fat signal, but they work differently. STIR uses an inversion pulse to null fat and suppresses it uniformly across the entire field of view, which makes it more reliable at field boundaries and around metal. Fat-suppressed T2 uses chemical fat saturation, which is faster but less uniform near metal and at the edges of the field. For bone marrow oedema detection, STIR is generally preferred as the more sensitive and robust sequence.
Gadolinium Contrast
How it works. Gadolinium-based contrast agents (GBCAs) are paramagnetic substances that shorten T1 relaxation time, so tissue that takes up contrast appears bright on T1-weighted post-contrast images. Given intravenously, gadolinium distributes through the vascular compartment and into the interstitium of tissues with disrupted capillary barriers.
- What Enhancement Shows
- Viable tumour enhances; necrotic/cystic areas do not
- Clinical Value
- Distinguishes solid from cystic components; guides biopsy site; monitors treatment response
- What Enhancement Shows
- Abscess shows rim enhancement; phlegmon enhances diffusely
- Clinical Value
- Distinguishes drainable abscess from phlegmon; identifies extent of infection
- What Enhancement Shows
- Active enhancing synovium (thickened, vascular)
- Clinical Value
- Distinguishes active inflammatory synovitis from chronic effusion in rheumatoid arthritis
- What Enhancement Shows
- Enhancement pattern around implants; recurrent vs scar tissue
- Clinical Value
- Recurrent tumour enhances; post-surgical scar shows progressive enhancement pattern
- What Enhancement Shows
- Dilute intra-articular gadolinium outlines labrum, cartilage, ligaments
- Clinical Value
- Gold standard for labral tears (hip and shoulder), SLAP lesions, and loose body detection
TISGadolinium Enhancement
Hook:TIS: gadolinium lights up Tumour, Infection, and Synovitis — the three main indications for contrast MRI in orthopaedics.
Nephrogenic Systemic Fibrosis (NSF): Gadolinium-based contrast agents can cause NSF in patients with severe renal impairment (eGFR below 30 mL/min/1.73m²). NSF is a serious, potentially fatal fibrosing condition affecting the skin, joints, and internal organs. Group II GBCAs (macrocyclic agents: gadobutrol, gadoterate, gadoteridol) are considered safer and preferred. Always check renal function (eGFR) before administering gadolinium. NSF risk with macrocyclic agents is considered negligible.
MRI Artefacts
The common artefacts, what causes each, how it looks and how to reduce it:
- Cause
- Ferromagnetic and paramagnetic implants distort the local magnetic field
- Appearance
- Signal void with surrounding signal pile-up (blooming); geometric distortion
- Reduction Strategies
- Metal artefact reduction sequences (MAVRIC-SL, SEMAC); wider bandwidth; spin echo over gradient echo; lower field strength
- Cause
- Fat and water protons precess at slightly different frequencies
- Appearance
- Bright/dark bands at fat-water interfaces in the frequency-encoding direction
- Reduction Strategies
- Wider receiver bandwidth; fat suppression sequences; swap phase/frequency directions
- Cause
- Patient movement during the long acquisition
- Appearance
- Ghosting (periodic repeating copies) in the phase-encoding direction
- Reduction Strategies
- Motion correction algorithms, breath-holding (not applicable for extremities), faster sequences, patient education
- Cause
- Structures oriented at 55 degrees to B0 exhibit artificially increased signal
- Appearance
- Tendon or ligament appears abnormally bright, simulating pathology
- Reduction Strategies
- Confirm on long-TE T2, where it should not persist; reposition if possible
- Cause
- Incomplete sampling of sharp signal transitions
- Appearance
- Alternating bright and dark lines parallel to high-contrast interfaces
- Reduction Strategies
- Increase matrix size; occurs at spinal cord-CSF boundary simulating syrinx
Magic angle. This is a common source of false positive findings. When a tendon (Achilles, supraspinatus, patellar) or ligament is oriented at approximately 55 degrees to the main magnetic field, the normally dark structure appears bright on short-TE sequences (T1, PD) and mimics tendinopathy or a tear. Two things keep you from the misdiagnosis: the abnormal signal should not persist on T2-weighted images with a long TE, and clinical correlation is essential.
Systematic Approach
A structured approach to MRI interpretation ensures comprehensive assessment and prevents missed pathology. Apply this checklist to every orthopaedic MRI:
- What to Assess
- Confirm which sequences are present: T1, T2, PD, STIR, post-gadolinium
- Key Considerations
- Each sequence provides different information — you cannot interpret pathology from a single sequence alone
- What to Assess
- Use T1-weighted images as the anatomical reference: identify all structures
- Key Considerations
- Fat is bright, providing natural contrast. Excellent for cortical bone margins, fatty marrow, and anatomical orientation
- What to Assess
- Scan fluid-sensitive sequences for oedema, effusion, and soft tissue injury
- Key Considerations
- Bright signal on STIR/fat-suppressed T2 indicates pathology: oedema, tears, inflammation, fluid
- What to Assess
- Cross-reference findings on both sequences to characterise the underlying tissue
- Key Considerations
- Read the combination against the T1/T2 signal differential table above
- What to Assess
- Review axial, sagittal, and coronal images systematically
- Key Considerations
- Certain pathology is best seen in specific planes (e.g., meniscal tears on sagittal, ACL on sagittal)
- What to Assess
- Do not forget periarticular structures: bursae, nerves, muscles, vessels
- Key Considerations
- Common exam trap: focusing on the joint while missing a nerve sheath tumour, muscle denervation oedema, or Baker cyst
Signal Differential: Reasoning from T1/T2 Behaviour
Reason, do not recite. A common viva task is to be shown a lesion described by its T1 and T2 signal and asked for a differential. Reasoning from the two-by-two of signal behaviour is more reliable than memorising lists, because each combination reflects a tissue property: fat, free water, fibrous or calcified tissue, blood-product stage, or paramagnetic material.
- Underlying Property
- Fat or fat-containing tissue
- Typical Differentials
- Normal fatty marrow, lipoma, intraosseous lipoma, well-differentiated liposarcoma component, subacute haematoma (methaemoglobin)
- Underlying Property
- Free water / oedema
- Typical Differentials
- Joint effusion, cyst, abscess, bone marrow oedema, acute tumour-associated oedema, soft tissue oedema, simple ganglion
- Underlying Property
- Low mobile-proton or paramagnetic content
- Typical Differentials
- Cortical bone, calcification, mature fibrous tissue/scar, haemosiderin (PVNS, chronic haematoma), gas, dense sclerosis, flow void
- Underlying Property
- Paramagnetic or proteinaceous material
- Typical Differentials
- Melanin (melanoma metastasis), proteinaceous/haemorrhagic cyst, subacute clot in specific phases, high-protein collection
- Underlying Property
- Vascularised/enhancing tissue
- Typical Differentials
- Viable tumour, active synovitis, abscess rim, granulation tissue, recurrent tumour (vs non-enhancing scar)
Anchor marrow on T1. Loss of the normal bright fatty marrow signal on T1 is one of the most reliable signs of marrow-replacing pathology (tumour, infection, infiltration). Relying on STIR or fluid-sensitive sequences alone is a common error: they are sensitive but non-specific. Low T1 (marrow replacement) plus high STIR is far more concerning than high STIR with preserved T1, which often reflects benign oedema.
Guidelines, Registries & Global Practice
Global Epidemiology of MRI Utilisation
MRI use has grown steadily worldwide and varies enormously by health-system resourcing. OECD data show MRI examinations ranging from over 140 per 1,000 population per year in the highest-utilising systems (e.g. Germany, United States, France) to a small fraction of that in many low- and middle-income countries, where scanner density may be fewer than one unit per million population. Musculoskeletal indications (knee, spine, shoulder) consistently rank among the most common reasons for outpatient MRI in high-income systems, and concerns about over-utilisation of knee and lumbar spine MRI have driven multiple "choosing wisely" type initiatives.
Side-by-Side Guideline Comparison
- Domain
- Appropriateness & contrast safety
- Key Position
- Appropriateness Criteria for MSK indications; Manual on Contrast Media stratifies gadolinium agents into Group I/II/III and recommends Group II macrocyclic agents for at-risk patients
- Domain
- MR safety zones
- Key Position
- Four-zone access control, designated MR Safety Officer/Medical Director, and labelling terminology (MR-safe, MR-conditional, MR-unsafe)
- Domain
- Requesting & reporting
- Key Position
- iRefer referral guidance promotes appropriate use; emphasises clinical correlation to avoid over-investigation of incidental findings
- Domain
- Protocols & arthrography
- Key Position
- European Society of Musculoskeletal Radiology protocol recommendations standardise joint-specific sequences and MR arthrography technique
- Domain
- Linear gadolinium agents
- Key Position
- EMA suspended most linear GBCAs for general use; FDA retained them with class warnings on gadolinium retention — a genuine regulatory divergence
- Domain
- Hardware imaging
- Key Position
- Device-specific MR-conditional labelling (field strength, SAR, gradient limits) governs whether and how implanted patients can be scanned
Practice Variation: High- vs Limited-Resource Settings
- High-resource settings: ready access to 1.5T and 3T, dedicated MSK coils, metal-artefact reduction sequences (MAVRIC-SL, SEMAC), and outpatient MR arthrography. The challenge is appropriate use and managing incidental findings, not access.
- Limited-resource settings: scanners may be few, geographically concentrated, and predominantly low-field (0.2-0.5T) or older 1.5T units. Ultrasound and plain radiography carry more diagnostic load, and MRI is reserved for cases that will change management (tumour, infection, surgical planning). Point-of-care and emerging low-field portable MRI (around 0.06T) may improve access in future.
- Regulatory divergence: the EMA-FDA split on linear gadolinium agents means the agents available to a clinician depend on jurisdiction; macrocyclic agents are the global default where choice exists.
MRI itself has no registry in the way arthroplasty does. The relevant "registry-level" evidence is implant MR-conditional labelling and pharmacovigilance reporting of gadolinium-associated NSF and retention.
Controversies & Areas of Uncertainty
Gadolinium retention. Deposition in the brain (notably the dentate nucleus and globus pallidus), bone and skin is documented even with macrocyclic agents, and is greater with linear agents. No definite clinical syndrome has been proven, but the uncertainty drove the EMA to suspend most linear agents while the FDA retained them with warnings. The pragmatic position: use macrocyclic agents, give contrast only when it changes management, and use the lowest effective dose.
1.5T versus 3T. 3T offers higher signal-to-noise and resolution but increases susceptibility artefact (worse around metal), chemical shift and specific absorption rate. For most native-joint musculoskeletal imaging 3T is advantageous; for imaging around implants 1.5T, or dedicated metal-artefact sequences, is generally preferred. Field strength is an indication-specific choice, not a universal "higher is better".
MR arthrography versus high-resolution MRI. Direct MR arthrography remains the reference for labral and SLAP lesions, but improving 3T conventional and indirect arthrographic techniques narrow the gap. The trade-off is invasiveness and a small infection or reaction risk against incremental sensitivity, and practice varies widely between centres and countries.
Over-utilisation and incidental findings. The high sensitivity of MRI is a double-edged sword: degenerative meniscal and labral signal, disc bulges and marrow oedema are frequently found in asymptomatic individuals. Imaging without a clear clinical question risks over-diagnosis and inappropriate surgery, so clinical correlation is mandatory, a recurring examiner theme.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“An examiner asks you to explain why fat appears bright on T1-weighted MRI images.”
“A 35-year-old runner presents with medial tibial pain. Plain radiographs are normal. You request an MRI.”
“You request a knee MRI for a patient with a previous knee arthroplasty and new onset pain. The MRI shows significant metal artefact.”
Signal Basics
- Signal source: hydrogen protons (H+) in water and fat
- Larmor equation: frequency = 42.58 MHz/T x field strength
- No ionising radiation — safe for children, pregnant patients, serial monitoring
- 1.5T and 3T are standard clinical field strengths
T1 vs T2 Signal
- T1: Fat = bright, Water = dark, Muscle = grey
- T2: Water = bright, Muscle = dark. Fat is intermediate on CONVENTIONAL spin echo but stays BRIGHT on the fast spin echo used clinically (J-coupling disrupted by the echo train) — which is exactly why fat suppression exists
- FSE also blurs fine detail slightly and is LESS susceptibility-sensitive than GRE — hence FSE around metal, GRE when you want blooming (PVNS haemosiderin)
- STIR: Water/oedema = bright, Fat = suppressed (most sensitive for marrow oedema)
- Cortical bone = dark signal void on ALL sequences
Key Sequences
- T1 = anatomy and fat; T2/STIR = pathology and oedema
- Proton Density = gold standard for meniscal tears
- T1 + Gadolinium = tumour, infection, synovitis (TIS)
- GRE = haemosiderin (PVNS) and cartilage surface
Gadolinium Safety
- NSF risk with severe renal impairment (eGFR less than 30)
- Group II macrocyclic agents (gadobutrol, gadoterate) are safest
- Always check eGFR before gadolinium administration
- Brain deposition reported — clinical significance uncertain
Metal and MRI
- Use spin echo over gradient echo near metal
- 1.5T produces less artefact than 3T
- MAVRIC-SL and SEMAC are dedicated metal artefact reduction sequences
- STIR provides more uniform fat suppression near metal than chemical fat saturation
Evidence Base
MRI of the Musculoskeletal System
- Comprehensive reference for MRI protocol selection and image interpretation in orthopaedic practice.
- Details the optimal sequences for each anatomical region including shoulder, knee, hip, spine, and extremities.
- Provides systematic interpretation frameworks with pathological correlations validated against surgical and arthroscopic findings.
MRI versus Arthroscopy for Knee Internal Derangement
- Systematic review (Coleman methodology) taking arthroscopy as the reference standard for meniscal and cruciate pathology.
- MRI is highly accurate for diagnosing meniscal and ACL tears and is the most appropriate screening tool before therapeutic arthroscopy.
- Diagnostic performance varies by structure (medial vs lateral meniscus vs ACL), with pooled accuracy around 85%.
MRI for Osteomyelitis Underlying Diabetic Foot Ulcers
- Pooled MRI sensitivity 0.90 and specificity 0.79 for osteomyelitis beneath diabetic foot ulcers.
- MRI was the most accurate imaging test, outperforming plain radiography (sensitivity 0.54), bone scan, and leukocyte scan.
- A positive probe-to-bone test (sensitivity 0.60, specificity 0.91) is moderately predictive and complements MRI.
MRI Detection of Avascular Necrosis of the Femoral Head
- Landmark MR-CT correlation establishing MRI as a sensitive method for early diagnosis of femoral head AVN.
- A peripheral low-signal margin on MRI corresponded to the sclerotic rim seen on CT in 95% of lesions (the substrate of the classic double-line sign).
- CT depicted subchondral fractures more clearly than MRI, remaining valuable for staging collapse.
Clinical MRI evidence supports its role as the primary soft tissue imaging modality.