Lateral Ankle Pain | PB More Common | Debridement vs Reconstruction
- Peroneus brevis tears more commonly than peroneus longus (PB subjected to higher friction against fibula)
- 80% association with lateral ankle instability - always assess and repair ATFL/CFL concomitantly
- Longitudinal split tears most common pattern (within tendon substance, parallel to fibres)
- Under 50% debride, over 50% reconstruct - critical threshold for preserving function
- SPR (superior peroneal retinaculum) injury allows subluxation - must repair if torn
- “PB compressed between PL and fibula at retromalleolar groove - highest stress zone
- “Low-lying PB muscle belly extends into retromalleolar groove - anatomical variant predisposing to tears
- “Painful arc sign: Pain at fibula tip with active eversion through range = peroneal pathology
- “MRI: highly specific but only moderately sensitive for PB tears (Park 2012: sensitivity ~44-50%, specificity ~99%) - a normal scan does not exclude a tear
Overview and Epidemiology
Peroneal tendon tears are a commonly missed cause of lateral ankle pain, often misdiagnosed as a chronic ankle sprain. The tendons are critical for hindfoot eversion and lateral ankle stability, and an untreated tear leads to progressive weakness, recurrent instability and functional limitation. Early recognition and the right operation, debridement for minor tears and reconstruction for major ones, achieve 80-90% good outcomes and prevent chronic disability.
Who. Active adults aged 30-40, with an equal sex distribution, in contrast to tibialis posterior tendon dysfunction, which is female-predominant. Peroneal tears account for 11-37% of chronic lateral ankle pain, and 10-15% of patients have contralateral involvement.
The association that shapes management. 80% of patients with a peroneal tear have lateral ankle instability, meaning ATFL/CFL insufficiency, and it has to be looked for and treated alongside the tear.
Risk factors. Chronic lateral ankle instability is the most significant.
- Extrinsic - chronic lateral ankle instability, recurrent inversion ankle sprains, high-level sport (basketball, soccer, tennis), and steroid injections, which have a degenerative effect on tendon
- Intrinsic - a low-lying peroneus brevis muscle belly, a shallow retromalleolar groove with less fibular containment, and cavovarus hindfoot alignment, which increases peroneal load
Anatomy and Pathophysiology
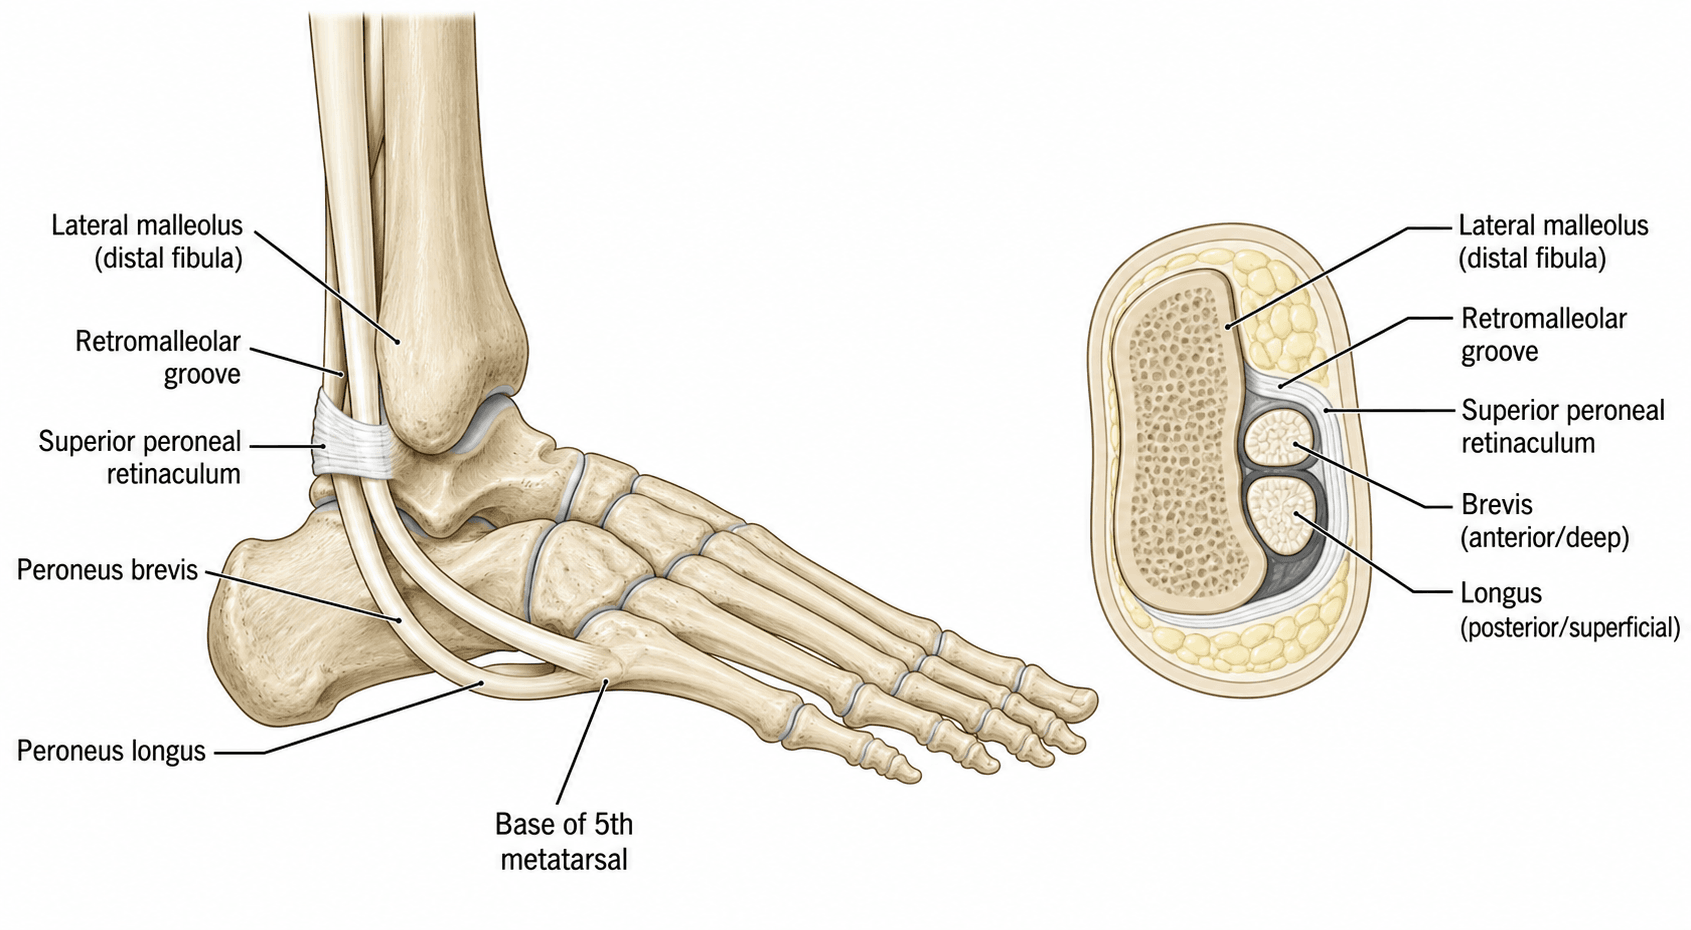
Two tendons in one groove. Both tendons pass behind the lateral malleolus in the retromalleolar groove, held there by the superior peroneal retinaculum (SPR). In the groove the peroneus brevis runs anterior to the peroneus longus, so the brevis is compressed between the fibula in front and the longus behind. That compression, with the tendon's excursion during hindfoot inversion and eversion, creates a high-friction zone, and it is why PB tears are far more common than PL tears.
- Anatomical Detail
- Origin: Distal 2/3 lateral fibula. Insertion: Styloid 5th MT base. Position: ANTERIOR at retromalleolar groove.
- Clinical Significance
- Insertion avulsion = 5th MT base fracture.
- Anatomical Detail
- Origin: Proximal 2/3 lateral fibula. Insertion: Plantar 1st MT base + medial cuneiform. Position: POSTERIOR at groove.
- Clinical Significance
- Less commonly torn (protected position). Runs under cuboid tunnel (can develop os peroneum pathology).
- Anatomical Detail
- Fibular sulcus behind lateral malleolus. Depth varies (shallow groove = subluxation risk).
- Clinical Significance
- Highest stress point for PB. Shallow groove variant predisposes to subluxation and SPR tears.
- Anatomical Detail
- Fibrous band from lateral malleolus to calcaneus. Holds peroneal tendons in retromalleolar groove.
- Clinical Significance
- Tear = peroneal subluxation (tendons pop anteriorly with eversion). Must repair if torn.
- Anatomical Detail
- From calcaneus to inferior extensor retinaculum. Stabilises tendons at lateral calcaneus.
- Clinical Significance
- Rarely torn. Secondary stabiliser after SPR.
What the tendons do. The peroneus brevis is the primary everter of the hindfoot, the longus secondary, and both resist inversion in stance to stabilise the lateral ankle. The longus also contributes to plantarflexion through its plantar first metatarsal insertion, and depresses the first ray, which locks the transverse tarsal joint. Both muscles are supplied by the superficial peroneal nerve, which exits the leg's anterior compartment.
In gait. In stance the peroneals contract eccentrically to resist inversion; in swing they evert the foot in preparation for heel strike. When the lateral ligaments are insufficient the peroneals compensate for them, so chronic ankle instability increases peroneal load.
How the brevis splits. The tear is a degenerative lesion of chronic friction and compression, and it develops in sequence:
- PB is compressed between the fibula and PL
- Excursion during inversion-eversion creates friction
- Chronic microtrauma degenerates the tendon
- A longitudinal split develops, parallel to the fibres
- The split propagates with continued stress
Friction damages the tendon within its substance and the split follows the fibre direction, so the tear runs lengthways. The Achilles, by contrast, usually ruptures transversely.
The low-lying brevis belly. Normally only tendon occupies the groove. In 20-30% of the population the brevis muscle belly extends into it, increasing compression and the risk of a tear.
The peroneus quartus. An accessory muscle present in roughly 10-22% of the population. It usually arises from the peroneus brevis (or the distal fibula) and most often inserts onto the retrotrochlear eminence of the calcaneus, when it is termed the peroneocalcaneus externus. As an extra structure in the groove it increases the volume the SPR must contain; the crowding raises compression on the brevis and can stretch the SPR or render it incompetent, predisposing to PB splits and to subluxation.
On MRI the quartus appears as an additional muscle and tendon posteromedial to the peroneal tendons. Recognising it before surgery explains the crowding.
Three anatomical variants crowd the retromalleolar groove and predispose to peroneus brevis tears and subluxation: a low-lying PB muscle belly, a peroneus quartus accessory muscle, and a shallow (convex) fibular groove. All act by the same mechanism, increased compression and a stretched, incompetent superior peroneal retinaculum. At surgery, excising an accessory or low-lying muscle belly helps decompress the groove.
Classification Systems
Longitudinal split tears. Sobel et al (Foot & Ankle, 1992) first described the mechanism and longitudinal-split pattern of peroneus brevis tears, the eponymous "Sobel" lesion. Krause and Brodsky (Foot Ankle Int, 1998) then defined the surgical grade in clinical use, based on the percentage of cross-sectional area involved. It is the most commonly used surgical grading, and the grade decides between debridement and reconstruction (see Management Algorithm).
- Tear Description
- Longitudinal split involving under 50% of tendon width
- Tendon Integrity
- Over 50% healthy tendon remaining - adequate function
- Tear Description
- Longitudinal split involving over 50% of tendon width
- Tendon Integrity
- Under 50% healthy tendon - inadequate to maintain function
- Tear Description
- Complete tendon rupture with retraction
- Tendon Integrity
- No continuity - direct repair impossible
Under 50% tear, enough healthy tendon remains that debridement alone, excising the diseased portion, preserves function. Over 50%, debridement would leave inadequate bulk and reconstruction is required: tubularisation, allograft or tenodesis. The threshold rests on biomechanical studies showing that removing over 50% of tendon width significantly impairs eversion strength.
Tear patterns. The split is one of several patterns, and each has its own typical site and treatment.
- Description
- Split parallel to tendon fibres, within substance
- Typical Location
- Retromalleolar groove (PB compressed between PL and fibula)
- Management
- Sobel grading (I-III) determines debridement vs reconstruction
- Description
- Incomplete tear through tendon thickness (superficial surface involved)
- Typical Location
- Retromalleolar groove, often posterior surface of PB
- Management
- Debridement of frayed tissue, usually under 50% involvement
- Description
- Full-thickness tear with retraction, gap present
- Typical Location
- Any location, but most common at retromalleolar groove
- Management
- Allograft reconstruction or tenodesis to PL
- Description
- Tendon tear at insertion site (PB = 5th MT styloid, PL = 1st MT base)
- Typical Location
- PB insertion more common (5th MT base avulsion = Jones fracture)
- Management
- Surgical repair with suture anchors or bone tunnel
- Description
- Thickened synovial sheath without actual tendon tear
- Typical Location
- Retromalleolar groove (chronic friction)
- Management
- Synovectomy (debulk synovium), assess for underlying tear
Painful os peroneum syndrome (POPS). The os peroneum is a sesamoid in the peroneus longus tendon, and POPS is the spectrum of PL pathology around it. It is the peroneus longus counterpart to the peroneus brevis split tear, and explains why a normal-looking brevis does not exclude peroneal pathology.
- Acute os peroneum fracture, or diastasis of a multipartite os peroneum, with sudden plantar-lateral midfoot pain
- PL tendinosis or a partial or complete tear at or distal to the os peroneum, often from attrition against the cuboid or a hypertrophied peroneal tubercle
- Chronic plantar-lateral foot pain along the PL course, with tenderness over the os peroneum
On radiographs, proximal migration of the os peroneum (sitting more proximal than expected, away from the cuboid) indicates a complete distal peroneus longus rupture: the sesamoid is pulled proximally because the distal tendon no longer anchors it. Distal migration or diastasis of a bipartite os peroneum suggests a tear proximal to the sesamoid. A smooth, well-corticated bipartite os peroneum is a normal variant, whereas irregular fragments with surrounding oedema suggest an acute fracture.
Clinical Assessment
History. The pain is lateral, posterior to the lateral malleolus, and usually chronic, lasting months to years. The mechanism is recurrent inversion ankle sprains, often treated conservatively and misdiagnosed as sprains. Patients describe weakness of eversion and difficulty on uneven ground, and popping or snapping suggests a torn SPR with the tendons subluxing over the fibula.
Examination. Look for swelling posterior to the lateral malleolus, with ecchymosis if the injury is acute, and feel for tenderness along the tendons and thickening at the retromalleolar groove. Resisted eversion is weak and painful compared with the other side. A Grade I tear gives lateral ankle pain, mild weakness and a palpable, tender brevis; a Grade II tear significant weakness, a feeling of instability and a thickened brevis; and a complete Grade III rupture severe weakness, with no eversion against resistance.
- Technique
- Patient actively everts foot against examiner resistance
- Positive Finding
- Weakness and pain posterior to lateral malleolus
- Significance
- Indicates peroneal tendon pathology (tear or tenosynovitis)
- Technique
- Patient actively everts foot through full range of motion
- Positive Finding
- Pain specifically at fibula tip during mid-range eversion
- Significance
- Highly specific for peroneal tendon pathology at retromalleolar groove
- Technique
- Ankle in dorsiflexion and eversion, palpate tendons at fibula
- Positive Finding
- Palpable pop or snap as tendons sublux anteriorly over fibula
- Significance
- SPR tear - requires SPR reconstruction ± fibular groove deepening
- Technique
- Knee flexed 90°, pull talus anteriorly with ankle in neutral
- Positive Finding
- Excessive anterior translation compared to contralateral (over 3mm)
- Significance
- ATFL insufficiency - must repair concomitantly with peroneal surgery
- Technique
- Ankle in neutral, invert hindfoot and assess for excessive tilt
- Positive Finding
- Talar tilt over 10° more than contralateral
- Significance
- CFL insufficiency - consider anatomical ligament reconstruction
Always perform the anterior drawer and talar tilt tests. A positive test indicates a ligament injury that needs repair at the same operation as the tendon; the consequences of missing it are set out under Management.
Differential diagnosis. The retromalleolar pain of a peroneal tear shares its territory with instability, subluxation and several bony and neural causes.
- Distinguishing Features
- Chronic retromalleolar pain and swelling, weak/painful resisted eversion, positive painful arc, history of recurrent inversion sprains
- Key Investigation
- MRI (specific, moderately sensitive) ± dynamic ultrasound; surgical confirmation
- Distinguishing Features
- Audible/palpable snapping of tendons anteriorly over the fibula with dorsiflexion-eversion; acute injury often a forced dorsiflexion
- Key Investigation
- Dynamic ultrasound (real-time subluxation); MRI for SPR/fleck sign
- Distinguishing Features
- Recurrent giving-way and inversion sprains, positive anterior drawer/talar tilt - coexists with peroneal tears in a high proportion
- Key Investigation
- Clinical instability tests; stress radiographs; MRI
- Distinguishing Features
- Pain along the plantar-lateral cuboid (PL course); os peroneum tenderness; may follow PL tear
- Key Investigation
- Radiographs (os peroneum, proximal migration); MRI/CT
- Distinguishing Features
- Acute traumatic onset, point tenderness just below/anterior to lateral malleolus, often missed on plain films
- Key Investigation
- CT (radiographs frequently negative)
- Distinguishing Features
- Pain over the sinus tarsi anterolateral to the lateral malleolus, hindfoot instability sensation
- Key Investigation
- Diagnostic injection; MRI
- Distinguishing Features
- Burning/neuropathic pain and altered sensation over the lateral foot, positive Tinel, no eversion weakness
- Key Investigation
- Clinical examination; diagnostic nerve block; nerve studies
- Distinguishing Features
- Stiffness, deep aching, mechanical symptoms, often post-traumatic; tenderness over joint line not tendon
- Key Investigation
- Weight-bearing radiographs; CT for impingement
Investigations
Plain radiographs. They are not diagnostic for tendon tears, but they rule out bony pathology. Take ankle AP, lateral and mortise views and foot AP, lateral and oblique views, and look for:
- 5th MT base avulsion fracture (PB insertion tear)
- Os peroneum fracture or displacement
- Calcaneofibular distance (SPR avulsion may show a fleck sign)
- Cavovarus alignment, which predisposes to peroneal overload
MRI. The imaging investigation of choice, and its performance must be known: it is highly specific but only moderately sensitive for peroneus brevis tears. Park 2010 reported sensitivity 83.9% and specificity 74.5% for peroneal tendinopathy overall; Park 2012, with surgery as the reference standard, found only 44% sensitivity (99% specificity) for PB interstitial tears. A positive scan is reliable, but a normal scan does not exclude a tear, and in a clinically suspicious ankle with a negative MRI, dynamic ultrasound or surgical exploration may still be warranted.
What MRI is for. It characterises tear morphology, shows associated pathology (lateral ligaments, SPR, bone oedema), and guides preoperative planning. Obtain axial, sagittal and coronal sequences; the axial images at the retromalleolar groove are critical.
- Longitudinal split - linear high T2 signal within the tendon substance, parallel to its long axis; the tendon may appear thickened
- Partial tear - high signal at the tendon surface, not extending through the substance
- Complete rupture - tendon discontinuity, a gap and retracted ends
- Tenosynovitis - fluid surrounding an intact tendon without intrasubstance signal; the tendon may be thickened
- SPR tear - discontinuity of the retinaculum, fluid in the peroneal sheath
- Associated findings - lateral ligament (ATFL/CFL) tears, bone marrow oedema
Dynamic ultrasound. It can show subluxation in real time during eversion, it is less expensive than MRI, and it has none of MRI's contraindications, such as implant compatibility. It is, however, operator-dependent, less sensitive than MRI for intrasubstance tears, and cannot assess bone marrow oedema or deep structures. Consider it if MRI is unavailable or contraindicated, or to assess dynamic subluxation.
Management Algorithm
Treatment follows the grade of the tear, on the principle of treating the tear and its cause: instability, subluxation and hindfoot varus.
- Conservative Options
- Immobilisation 4-6 weeks, PT, NSAIDs, activity modification
- Surgical Indications
- Failure of 6 months conservative treatment
- Surgical Procedure
- Tenosynovectomy (debulk thickened synovium), assess for underlying tear
- Conservative Options
- Conservative rarely successful if true tear present
- Surgical Indications
- Persistent pain, functional limitation despite 3-6 months conservative
- Surgical Procedure
- Debridement of diseased portion OR tubularisation (side-to-side repair)
- Conservative Options
- Conservative ineffective (inadequate tendon bulk)
- Surgical Indications
- Diagnosis confirmed on MRI
- Surgical Procedure
- Tubularisation if sufficient tissue OR allograft reconstruction OR tenodesis to PL
- Conservative Options
- Conservative ineffective
- Surgical Indications
- Diagnosis confirmed clinically and on MRI
- Surgical Procedure
- Allograft interpositional graft OR tenodesis PB to PL (sacrifice brevis function)
- Conservative Options
- Conservative fails to address ligamentous pathology
- Surgical Indications
- ATFL/CFL insufficiency (anterior drawer, talar tilt positive)
- Surgical Procedure
- Peroneal surgery + anatomical lateral ligament reconstruction (Brostrom or augmented)
Conservative management. Indicated for mild tears (Grade I under 25% width), tenosynovitis without a structural tear, or a patient unfit for surgery.
- Weeks 0-6 - CAM boot or short leg cast, weight-bearing as tolerated in the boot; ice 15-20 minutes QID for the first 2 weeks, NSAIDs if there is no contraindication, elevation
- Weeks 6-12 - lateral support ankle brace; physiotherapy for range of motion (dorsi/plantarflexion, inversion/eversion); resistance-band eversion strengthening from week 8-10; balance-board proprioception
- Weeks 12-16 - progressive strengthening, gradual sport-specific return, brace for sport, avoid repetitive eversion stress
- Long term - brace for high-risk activities, maintenance strengthening and proprioception, lateral heel wedge if cavovarus, review if symptoms recur
Results. Conservative success for peroneal tears is poor compared with other tendinopathies: 60-70% for tenosynovitis without a structural tear, 30-40% for Grade I tears and under 20% for Grade II-III. Peroneal tears are degenerative splits within a high-friction zone, and continued use perpetuates them, so most Grade I-III tears ultimately need debridement or reconstruction.
Grade I. Debridement alone is usually sufficient under 25%; between 25% and 50%, tubularisation (side-to-side repair of the split) gives a more robust repair.
Grade II. Debride the diseased tissue first, then judge how much healthy tendon remains. If a tube of adequate diameter (over 50% of normal) can be made, tubularise; if the tissue is inadequate, reconstruct with allograft. Tenodesis to PL is an option for low-demand patients.
Grade III. An allograft interpositional graft is preferred for active patients, and tenodesis of PB to PL is acceptable for the low-demand or elderly. FHL transfer is an option in a young active patient if allograft is unavailable. The choice rests on age, activity level, graft availability and the surgeon's preference and experience.
- Indication
- Grade II with adequate tissue to bring edges together
- Advantages
- Preserves native tissue, simple technique, good outcomes if sufficient bulk
- Disadvantages
- Only works if enough tendon present to create tube - not for complete ruptures
- Indication
- Grade II-III with inadequate tissue for tubularisation, gap present
- Advantages
- Restores length and bulk, high strength, no donor site morbidity
- Disadvantages
- Cost of allograft, theoretical disease transmission risk (very low), integration time
- Indication
- Grade III complete rupture, elderly or low-demand patient
- Advantages
- Simple, no graft needed, PL sufficient for some eversion
- Disadvantages
- Sacrifices PB function, less eversion strength, not ideal for young active patients
- Indication
- Grade III complete rupture, young active patient
- Advantages
- Restores active eversion, FHL is nearby, minimal donor morbidity
- Disadvantages
- Technically demanding, requires separate medial incision for FHL harvest
If the tear proves at operation to involve over 50% of the width, debridement alone is inadequate: tubularise if there is enough tissue to bring the edges together, otherwise reconstruct with allograft. Patients who undergo excessive debridement (over 50% removed) develop persistent weakness and often require revision surgery.
The lateral ligaments. Assess the ATFL with the anterior drawer and the CFL with the talar tilt test. Stress radiographs help if the diagnosis is uncertain (talar tilt over 10° = CFL tear), and MRI confirms the ligament tears, the ATFL most commonly, with the CFL often involved. If instability is present, the ligaments are reconstructed at the same operation as the tendon.
- Brostrom repair - direct anatomical repair, the primary choice if tissue quality is good
- Brostrom-Gould augmentation - Brostrom reinforced with the inferior extensor retinaculum
- Allograft reconstruction - poor tissue quality or a revision case
If lateral ankle instability is present but not repaired, the peroneal tendons remain overloaded, compensating for the insufficient ligaments. The result is recurrent peroneal tears (up to 50% without ligament repair), persistent symptoms and poor patient satisfaction. Combined surgery achieves 80-85% good outcomes against 50-60% for peroneal surgery alone in the setting of instability.
Surgical Technique - Detailed Steps
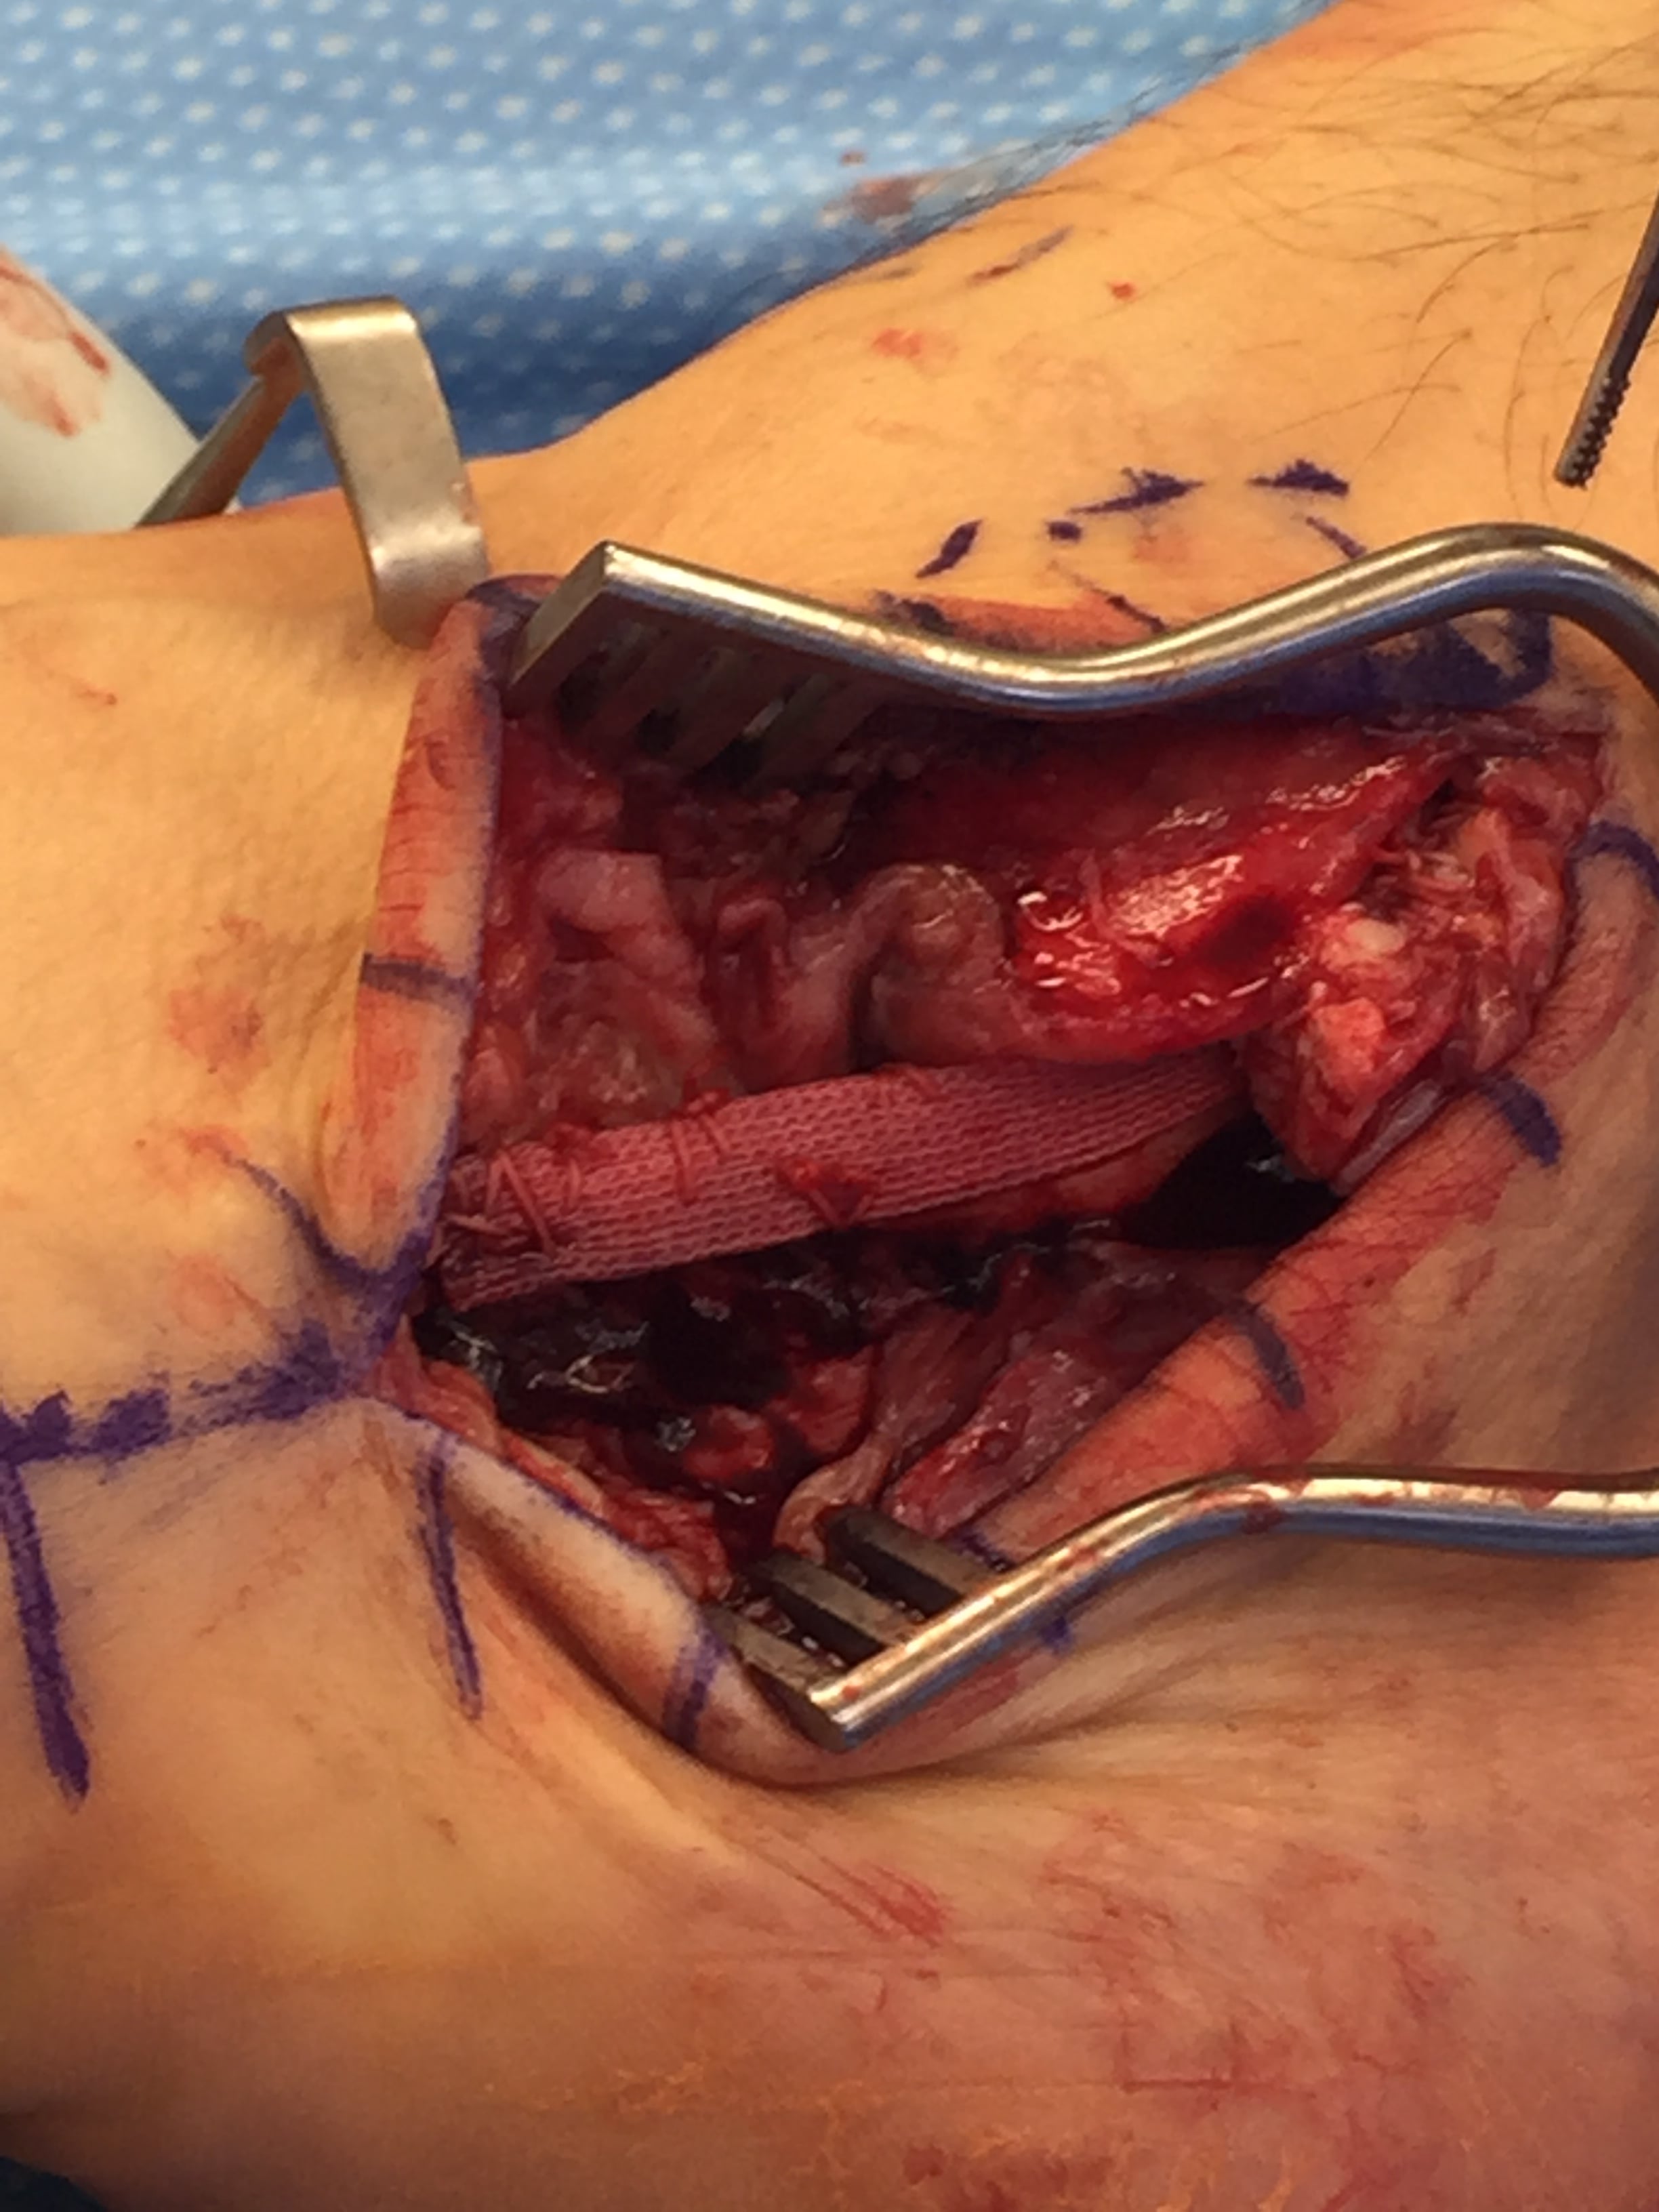
Position. Supine or lateral decubitus; some surgeons prefer lateral for easier access to the lateral ankle. If supine, place a bump under the ipsilateral hip (internal rotation improves lateral access) and a sandbag or bolster under the operative ankle, and pad the sacrum and contralateral heel. If lateral, lie the patient operative side up on a beanbag or lateral positioner with an axillary roll, and pad the axilla, the down hip and the fibular head (common peroneal nerve). All bony prominences are padded.
Tourniquet and draping. A thigh tourniquet inflated to 300mmHg after exsanguination by elevation or Esmarch; typical tourniquet time is 60-90 minutes. Drape the foot and ankle free so they can be manipulated to assess peroneal excursion and lateral stability. A C-arm is available if needed, but usually is not required.
Incision. Curvilinear along the posterior border of the fibula, starting 6cm proximal to the fibula tip, curving posterior to the lateral malleolus and extending 2-3cm distally along the lateral calcaneus. It is 6-10cm long depending on the extent of pathology; the exposure for debridement is 6-8cm, centred over the retromalleolar groove.
Sural nerve. It runs posterior to the incision, coursing along the lateral ankle, and may branch at this level. Identify it in the subcutaneous tissue and protect it with a retractor, or dissect it and retract it posteriorly; injury leaves numbness of the lateral foot.
Opening the sheath. Incise the superficial fascia to reach the peroneal sheath, the fibrous tunnel containing PB and PL, whose roof at the fibula is the SPR, and palpate the tendons to confirm the level. Incise the SPR and sheath longitudinally for the full length of the exposure. If the tendons pop anteriorly, the SPR is torn.
Identifying the tendons. The brevis is anterior and the longus posterior. Confirm by following them distally, the brevis to the fifth metatarsal base laterally and the longus plantar under the cuboid: repairing the wrong tendon fails the operation.
Inspecting and grading. Examine both tendons. A longitudinal split shows as separation within the tendon substance, and degenerative tear edges are friable and yellow. Grade the tear (Sobel I-III, by % width), check the SPR, and assess the depth of the retromalleolar groove, since a shallow groove predisposes to subluxation.
Complications
- Incidence
- 10-15% at 5 years
- Risk Factors
- Inadequate debridement, uncorrected lateral instability, excessive activity too early
- Management
- If symptomatic: Revision surgery with allograft reconstruction + lateral ligament repair
- Incidence
- 5-10%
- Risk Factors
- SPR not repaired or repair failure, shallow fibular groove
- Management
- Revision SPR reconstruction ± fibular groove deepening
- Incidence
- 2-5% temporary, 1% permanent
- Risk Factors
- Direct injury during dissection, nerve branches variable
- Management
- Prevention: Identify and protect. Treatment: Observation (most recover), neurolysis if persistent
- Incidence
- 5-8%
- Risk Factors
- Thin skin over lateral ankle, tension, smoking
- Management
- Superficial: Local care. Deep: Debridement, VAC, possible flap
- Incidence
- 10-15%
- Risk Factors
- Excessive debridement (over 50% removed), inadequate reconstruction, allograft failure
- Management
- PT for strengthening. If severe: Revision with allograft reconstruction or tenodesis
- Incidence
- 2-5%
- Risk Factors
- More common after foot/ankle surgery
- Management
- Early PT, desensitisation, gabapentin, stellate ganglion block
- Incidence
- 10-20%
- Risk Factors
- Prolonged immobilisation, adhesions within peroneal sheath
- Management
- Aggressive PT, rarely require sheath release
Preventing recurrence. Uncorrected lateral ankle instability is the most common cause of recurrent peroneal tears (see Management Algorithm). The other preventable causes are dealt with at and after the index operation:
- Repair the SPR if torn, to prevent subluxation
- Debride all diseased tissue; incomplete debridement leaves recurrent pathology
- Immobilise appropriately after surgery to protect the repairs (see Rehabilitation)
- Address cavovarus alignment if present, with a lateral heel wedge or calcaneal osteotomy
Postoperative Care and Rehabilitation
After debridement or tubularisation.
- Weeks 0-2 - short leg splint kept dry, NWB with crutches or a walker, elevation, ice and DVT prophylaxis; at the week-2 review remove the splint, check the wound and change to a CAM boot (removable for hygiene)
- Weeks 2-6 - NWB in the boot for the full 6 weeks
- Weeks 6-8 - partial weight-bearing in the boot (25-50% body weight); gentle ankle range of motion (dorsi/plantarflexion); no forced eversion until week 10
- Weeks 8-12 - full weight-bearing in the boot; resistance-band eversion strengthening and proprioception; wean from the boot to a supportive shoe and ankle brace
- Week 12 onwards - shoe and brace for activities, progressive and sport-specific strengthening, return to full activity at 4-6 months, and a brace long term for high-risk sports
Why six weeks. Tubularisation sutures achieve biological strength at 6-8 weeks, and early weight-bearing risks re-tearing at the repair site; an SPR repair, if performed, also needs 6 weeks to heal. Patients who bear weight early have higher recurrent tear rates, 20-30% against under 10% with compliant NWB.
After allograft reconstruction.
- Weeks 0-6 - strictly NWB in a cast or boot; elevation, ice, DVT prophylaxis
- Weeks 6-10 - partial weight-bearing (25-50% body weight) in the boot; gentle range of motion, avoiding forced eversion
- Weeks 10-12 - full weight-bearing in the boot; range of motion and light strengthening
- Weeks 12-16 - wean from boot to shoe and brace; progressive strengthening and proprioception
- 4-6 months - gradual return to sport, with a brace for high-risk activities; full strength typically returns by 6 months
Allograft tendon undergoes biological incorporation over 12-16 weeks. For weeks 0-4 the graft is acellular, with no blood supply, and held only by its sutures; over weeks 4-12 host cells invade it (revascularisation, remodelling); by weeks 12-16 incorporation is complete. Early stress risks graft failure before integration, so allograft needs a minimum of 6 weeks NWB, often extended to 8 weeks in heavy or non-compliant patients.
After SPR repair. Immobilise in slight plantarflexion and inversion, which reduces tension on the repair. The patient is NWB for 4-6 weeks and avoids forced eversion until 12 weeks.
After combined lateral ligament repair. 4-6 weeks NWB protects both the peroneal and the ligament repairs, followed by progressive weight-bearing in the boot over weeks 6-10 and physiotherapy for range of motion and strengthening from week 10-12. Return to sport is at 4-6 months, when both have healed.
Outcomes and Prognosis
- Success Rate
- 80-90% good outcomes
- Patient Satisfaction
- 85-90% satisfied
- Return to Activity
- 4-6 months
- Notes
- Best outcomes if under 25% tear, lateral instability addressed
- Success Rate
- 75-85% good outcomes
- Patient Satisfaction
- 80-85% satisfied
- Return to Activity
- 4-6 months
- Notes
- Effective if adequate tissue for side-to-side repair
- Success Rate
- 75-85% good outcomes
- Patient Satisfaction
- 75-85% satisfied
- Return to Activity
- 6-8 months
- Notes
- Longer recovery than debridement, graft incorporation time
- Success Rate
- 70-80% pain relief
- Patient Satisfaction
- 70-80% satisfied
- Return to Activity
- 6-8 months
- Notes
- Sacrifice of PB function, lower eversion strength, acceptable for low-demand patients
- Success Rate
- 80-85% good outcomes
- Patient Satisfaction
- 85-90% satisfied
- Return to Activity
- 6-8 months
- Notes
- Combined procedure has better outcomes than peroneal surgery alone if instability present
Predictors of poor outcome. These are the risk factors for a poor result after peroneal tendon surgery:
- Lateral ankle instability not addressed - 50% recurrence if instability is not repaired
- SPR not repaired - recurrent subluxation, progression of pathology
- Workers' compensation - lower satisfaction, prolonged recovery
- Smoking - impaired wound and tendon healing
- Advanced degenerative tears - Grade III complete ruptures have lower success than Grade I-II
- Delayed diagnosis - chronic tears (over 6 months) are more degenerate, with worse tissue quality
Patients with several risk factors may benefit from earlier surgical intervention and from counselling towards realistic expectations.
Long-term results. After debridement or tubularisation, 75-80% maintain a good outcome at 5 years; 10-15% develop recurrent tears or progression, and 5-10% need revision. After allograft reconstruction, 70-80% maintain a good outcome at 5 years; 15-20% have graft-related problems (failure, persistent weakness), and 10-15% need revision.
Return to sport. Among recreational athletes, 70-80% return to the same level, 15-20% to a lower level, and 5-10% are unable to return. Among high-level athletes, 60-70% return to elite competition, recovery is longer (6-8 months minimum), and returning too early raises the risk of recurrence. Long-term brace use is recommended for pivoting sports such as basketball, soccer and tennis.
Guidelines, Registries & Global Practice
Peroneal tendon pathology is a worldwide and frequently missed cause of chronic lateral ankle pain. There is no high-level (Level I) randomised evidence and no formal national-society guideline dedicated to peroneal tendon tears in any health system - management is built on Level III-IV cohorts, expert consensus and the principle of treating the tear and its cause (instability, subluxation, hindfoot varus).
Global Epidemiology (PubMed-backed)
- Figure
- Peroneal pathology found in a high proportion at surgery (e.g. 31/82 ankles, ~38%, on MRI-surgical correlation)
- Source / Population
- Park 2010, chronic-instability cohort (Korea)
- Figure
- Peroneus brevis far exceeds peroneus longus; concomitant PL+PB tears are recognised but uncommon
- Source / Population
- Sobel 1992; Krause & Brodsky 1998; Redfern & Myerson 2004
- Figure
- Active adults, commonly mid-30s (mean 36-39 years across surgical series)
- Source / Population
- Redfern & Myerson 2004; Park 2012
- Figure
- Chronic lateral ligament instability, SPR incompetence/subluxation, hindfoot/cavovarus alignment, low-lying PB belly, peroneus quartus
- Source / Population
- Sobel 1992; Park 2010; Redfern & Myerson 2004
Guidance and Consensus Across Regions
- Position
- No condition-specific clinical practice guideline; covered within general foot & ankle / tendon-disorder education. Practice driven by expert series.
- Evidence Level
- Expert/consensus (no CPG)
- Position
- No dedicated NICE guidance or BOAST for peroneal tendon tears; managed under general soft-tissue ankle injury and chronic lateral ankle pain pathways with MRI and physiotherapy-first principles.
- Evidence Level
- Expert/consensus (no CPG)
- Position
- Provides surgical technique and approach guidance (retromalleolar exposure, SPR repair, groove deepening) rather than a treatment guideline.
- Evidence Level
- Technique reference
- Position
- Echoes the international consensus on lateral ankle instability (e.g. ESSKA-AFAS): inspect and address peroneal pathology when operating on the unstable lateral ankle.
- Evidence Level
- Consensus (Level V)
- Position
- Trial of conservative care first (immobilisation, physiotherapy); surgery for refractory symptoms; grade by cross-sectional area (under vs over 50%); always correct instability/subluxation/varus.
- Evidence Level
- Level III-IV cohorts
Unlike arthroplasty or fracture fixation, peroneal tendon surgery is not captured by national joint or implant registries (NJR, AJRR, AOANJRR, SHAR, NZJR). The evidence base is therefore institutional case series and systematic reviews rather than registry data - candidates should be explicit that the recommendations rest on lower-level evidence, which is itself an examinable point.
Global Practice Variation
- Routine MRI ± dynamic ultrasound before surgery
- Allograft and tendon-transfer reconstruction freely available for Grade II-III tears
- Combined peroneal + anatomical lateral-ligament reconstruction performed in a single sitting
- Tendoscopic/minimally invasive techniques increasingly used
- Greater reliance on clinical diagnosis and ultrasound where MRI access is limited
- Autograft (e.g. hamstring/FHL transfer) preferred where allograft is unavailable or unaffordable
- Tenodesis to peroneus longus favoured as a simple, graft-free salvage
- Longer conservative trials due to access/waiting-time constraints
Whatever the health system, the standard of care is the same:
- Always assess for and correct lateral ankle instability - uncorrected instability is the leading driver of recurrent tears.
- Trial appropriate conservative care first (immobilisation, physiotherapy, activity modification) for tears amenable to it.
- Grade by cross-sectional area - under 50% debride/tubularise, over 50% reconstruct or tenodese.
- Repair the SPR / address subluxation and any hindfoot varus to remove the causative mechanical load.
- Counsel realistic recovery - protected weight-bearing for several weeks and 4-6 months to sport, with return-to-work planning for manual workers.
- Protect the sural nerve during the retromalleolar approach (~2-5% transient injury).
MCQ Practice Points
Q: At the retromalleolar groove behind the lateral malleolus, which peroneal tendon runs anterior and which runs posterior? A: Peroneus brevis (PB) runs anterior, peroneus longus (PL) runs posterior. This anatomy is critical because PB is compressed between the fibula (anteriorly) and PL (posteriorly), creating a high-friction zone. This is why PB tears are far more common than PL tears - PB subjected to higher stress from compression and friction.
Q: What is the critical threshold in Sobel classification that determines whether debridement alone is sufficient or reconstruction is required? A: 50% of tendon width. Sobel Grade I (under 50% width tear) can be treated with debridement alone because over 50% healthy tendon remains, which is adequate to maintain eversion function. Sobel Grade II (over 50% width tear) requires reconstruction (tubularization, allograft, or tenodesis) because under 50% healthy tendon remains after debridement, which is inadequate for function. This 50% threshold is based on biomechanical studies showing significant impairment when over 50% of tendon is removed.
Q: What percentage of peroneal tendon tears are associated with lateral ankle instability, and why is this clinically important? A: 80% of peroneal tendon tears occur with lateral ankle instability (ATFL/CFL insufficiency). This is clinically critical because: (1) Surgeons must assess for lateral instability in all peroneal tear patients (anterior drawer, talar tilt tests); (2) Failure to address lateral instability leads to 50% recurrent tear rate because the peroneals remain overloaded (compensating for insufficient ligaments); (3) Combined peroneal reconstruction + lateral ligament repair achieves 80-85% good outcomes vs only 50-60% for peroneal surgery alone if instability present.
Q: What is the diagnostic accuracy of MRI for peroneal tendon tears, and what is the characteristic MRI appearance of a longitudinal split tear? A: MRI is the imaging investigation of choice but candidates should know it is highly specific yet only moderately sensitive for peroneus brevis tears - Park 2010 reported sensitivity 83.9% / specificity 74.5% for tendinopathy overall, while Park 2012 (surgical reference standard) found only 44% sensitivity but 99% specificity for PB interstitial tears. A positive scan is reliable; a normal scan does not exclude a tear. Characteristic appearance of a longitudinal split tear: linear high T2 signal within the tendon substance, oriented parallel to the long axis of the tendon. This is distinct from complete rupture (gap with discontinuity) and tenosynovitis (fluid surrounding an intact tendon without intrasubstance signal). Axial images at the level of the retromalleolar groove are most useful.
Q: A patient has a Sobel Grade II peroneal brevis tear (65% width involved) and positive anterior drawer test. What is the appropriate surgical treatment? A: Allograft reconstruction of peroneus brevis + lateral ligament reconstruction (Brostrom). Rationale: (1) Grade II tear (over 50% width) requires reconstruction - debridement would leave inadequate tendon bulk; (2) Allograft reconstruction (Pulvertaft weave) restores tendon continuity and bulk; (3) Positive anterior drawer indicates ATFL insufficiency - MUST repair lateral ligaments concomitantly (Brostrom or augmented Brostrom-Gould) to prevent recurrent tears; (4) Failure to address instability leads to 50% recurrence rate.
Q: What is the most common cause of recurrent peroneal tendon tears after surgical treatment? A: Uncorrected lateral ankle instability. Peroneal tears have 80% association with lateral ankle instability (ATFL/CFL insufficiency). If the lateral ligaments are not repaired at the time of peroneal surgery, the tendons remain overloaded (compensating for the insufficient ligaments), leading to recurrent tears in up to 50% of cases. Other causes include inadequate debridement of diseased tissue, superior peroneal retinaculum not repaired (subluxation causes recurrent trauma), and excessive early activity. Prevention requires assessment for instability (anterior drawer, talar tilt) and concomitant lateral ligament reconstruction if present.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 35-year-old recreational basketball player presents with chronic lateral ankle pain for 8 months. He has a history of multiple ankle sprains. Pain is posterior to the lateral malleolus, worse with activity. On examination, he has tenderness along the peroneal tendons, weakness with resisted eversion, and positive anterior drawer test. How would you assess and manage this patient?”
“You are performing peroneal tendon surgery via retromalleolar approach. After opening the peroneal sheath, you identify a longitudinal split tear of the peroneus brevis. How do you assess the severity intraoperatively, and what are your surgical options based on different tear grades?”
“A patient returns 18 months after peroneal tendon debridement surgery with recurrent lateral ankle pain and weakness. Examination reveals tenderness over peroneals and positive anterior drawer test. MRI shows recurrent longitudinal tear of PB, now involving 60% of tendon width. How do you manage this complication?”
Key Anatomy
- PB runs ANTERIOR to PL at retromalleolar groove - PB compressed between fibula and PL = high friction
- PB insertion = 5th MT styloid (avulsion = Jones fracture). PL insertion = plantar 1st MT base + medial cuneiform
- Superior peroneal retinaculum (SPR) = holds tendons in retromalleolar groove, tear = subluxation
- Low-lying PB muscle belly = anatomical variant (20-30%), muscle extends into groove = increased compression = tear risk
- Sural nerve = posterior to retromalleolar incision, variable branches at ankle = injury risk 2-5%
Classification - Sobel Grading
- Grade I = under 50% width tear = debridement or tubularization
- Grade II = over 50% width tear = reconstruction (allograft or tenodesis to PL)
- Grade III = complete rupture with retraction = allograft reconstruction or tenodesis
- CRITICAL THRESHOLD: 50% width - under 50% debride, over 50% reconstruct
- Longitudinal split pattern = degenerative tears parallel to fibers (not traumatic transverse ruptures)
Surgical Algorithm
- 80% association with lateral ankle instability - MUST assess (anterior drawer, talar tilt) and repair ATFL/CFL if present
- Grade I under 25%: Debridement alone. Grade I 25-50%: Tubularization (side-to-side repair)
- Grade II-III: Allograft reconstruction (Pulvertaft weave) or tenodesis PB to PL (low-demand)
- SPR torn: Repair with suture anchors to fibula (prevents subluxation)
- Combined surgery (peroneal + lateral ligament) = 80-85% success vs 50-60% peroneal alone if instability present
Surgical Pearls
- Retromalleolar approach: Protect sural nerve (posterior to incision), open peroneal sheath longitudinally
- Assess severity intraoperatively: Grade by % width, debride diseased tissue first then assess remaining healthy tissue
- Tubularization: Side-to-side with 2-0 or 3-0 absorbable suture, creates single tubular tendon
- Allograft: Pulvertaft weave 3-4 passes, tension in PF/eversion, non-absorbable suture, NWB 6 weeks for incorporation
- SPR repair mandatory if torn: Suture anchors to fibula or periosteal flap augmentation
Complications
- Recurrent tear: 10-15% - most common cause is uncorrected lateral instability (50% recurrence if not repaired)
- Sural nerve injury: 2-5% temporary, 1% permanent - protect during retromalleolar exposure
- Persistent subluxation: 5-10% - SPR not repaired or repair failure, requires revision SPR reconstruction
- Persistent weakness: 10-15% - excessive debridement (over 50%), inadequate reconstruction, allograft failure
- Wound complications: 5-8% - thin skin over lateral ankle, smoking risk factor
Evidence Base and Key Trials
Sobel: Dynamics of Peroneus Brevis Splits - Mechanism and Classification
- Anatomic and histologic study proposing the mechanism and classification of peroneus brevis longitudinal splits
- Splits develop from chronic mechanical attrition at the fibular groove - PB is splayed against the sharp posterior fibular edge by peroneus longus compression
- Superior peroneal retinaculum laxity allowing subluxation is central to the pathomechanism
- Predisposing anatomic factors: shallow (convex) fibular groove, low-lying PB muscle belly, peroneus quartus
- This paper is the origin of the eponymous Sobel description of PB split tears
Krause & Brodsky: Peroneus Brevis Tears - Grading and Surgical Reconstruction
- Clinical series of 20 patients - largest of its kind at the time - defining the widely used surgical grading
- Grade 1: under 50% of cross-sectional area damaged - debridement and tubularisation repair
- Grade 2: over 50% of cross-sectional area destroyed - excision of damaged segment and tenodesis to peroneus longus
- Both groups must additionally be augmented by stabilising the causative subluxation (SPR)
- Mean postoperative AOFAS score 85; good-to-excellent results in the majority but prolonged recovery
Redfern & Myerson: Management of Concomitant Peroneus Longus and Brevis Tears
- 28 patients (29 feet) with combined PL and PB tears, mean follow-up 4.6 years
- Surgical algorithm based on whether a functioning tendon remains, mobility of the muscle, ankle stability and heel position
- 9/28 had hindfoot varus or cavovarus; 8/28 had mechanical ankle instability
- Mean postoperative AOFAS 82; 91% achieved normal or moderate peroneal strength
- Conclusion: address the primary or contributing cause (instability, subluxation, hindfoot varus) at the time of tendon repair
Demetracopoulos: Long-Term Results of Debridement and Primary Repair
- 34 patients with PB and/or PL tears treated by debridement and primary repair (single surgeon, 1994-2008)
- 18 followed for a mean of 6.5 years (range 2-14 years)
- Mean VAS pain improved from 39 to 10; LEFS improved from 45 to 71 (both p under 0.001)
- 17 of 18 returned to full sporting activity without limitation
- No reoperations or operative failures over the study interval
Park: Reliability of MRI for Peroneal Tendinopathy in Chronic Lateral Ankle Instability
- 82 ankles with chronic lateral ankle instability had preoperative MRI compared with operative findings
- Sensitivity 83.9%, specificity 74.5% for peroneal tendinopathy overall
- Positive predictive value 66.7%, negative predictive value 88.4%, accuracy 78.0%
- Low-lying muscle belly and peroneus quartus frequently identified as associated variants
- Conclusion: MRI is useful but often equivocal - thorough clinical examination remains essential
Park: Accuracy of MRI vs Surgery for Characterising Peroneal Tendon Disorders
- 97 patients with chronic lateral ankle instability had MRI followed by surgery (reference standard), two blinded readers
- For PB interstitial tears: sensitivity 44%, specificity 99%
- For PB swelling: sensitivity 50%, specificity 99%
- MRI of chronic peroneal pathology is diagnostically specific but NOT sensitive
- Tempers the common teaching that MRI is highly sensitive for peroneal tears
Oden: Classification of Peroneal Tendon Dislocation
- Describes tendon injuries about the ankle resulting from skiing, including peroneal tendon dislocation
- Presents four types of peroneal tendon dislocation and related problems
- The four-grade scheme modifies the earlier Eckert and Davies classification of SPR injury
- Forms the basis of the still-cited Oden grading of peroneal subluxation/dislocation
- Mechanism is forced dorsiflexion with reflex peroneal contraction