ECM Macromolecules | 28 Collagen Types | GAG Side Chains | Triple Helix Structure
- Collagen is most abundant protein in mammals (25-35% of total body protein)
- Triple helix structure - Gly-X-Y repeat with glycine every third residue
- Proteoglycans consist of core protein with GAG side chains
- Aggrecan is major cartilage proteoglycan, decorin binds collagen
- Hydroxylation requires Vitamin C - scurvy impairs collagen synthesis
- “Type I collagen mutations cause osteogenesis imperfecta
- “Type II collagen mutations cause chondrodysplasias
- “Lysyl oxidase creates crosslinks (requires copper)
- “GAG side chains on proteoglycans attract water via negative charge
Overview
Collagen and proteoglycans are the major components of the extracellular matrix in connective tissues, including bone, cartilage, tendon, ligament and skin. Collagen is the most abundant protein in mammals, 25-35% of total body protein, and provides the structural framework and tensile strength of those tissues. Proteoglycans are core proteins carrying negatively charged glycosaminoglycan (GAG) side chains that attract water, and aggrecan is the major proteoglycan of cartilage.
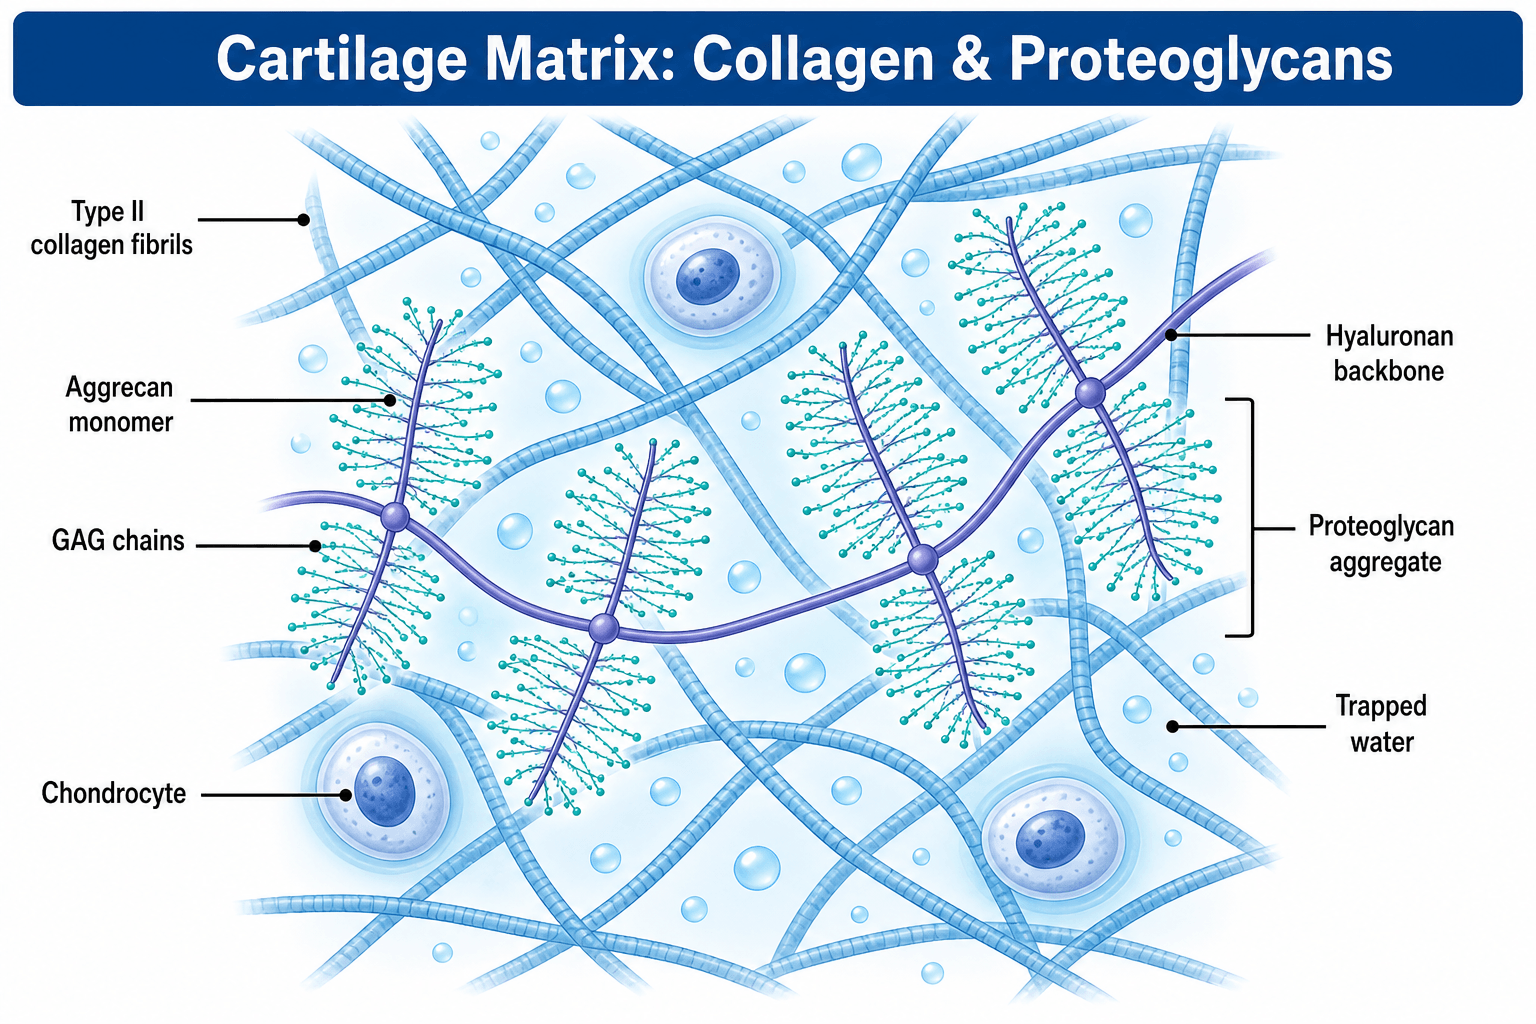
Why the chemistry matters. Mutations in the collagen genes cause heritable disease, and collagen structure explains the mechanism; the disorders are set against each collagen type below. Osteoarthritis involves proteoglycan loss and disruption of the collagen network, and intervertebral disc degeneration involves aggrecan degradation, so the pathology can only be understood against the normal structure.
Healing. Collagen synthesis is essential for fracture healing, tendon repair and wound closure. Type III collagen appears early in healing and is later replaced by Type I, and factors that impair collagen synthesis, such as vitamin C deficiency and medications, delay healing.
Biomaterials. Collagen-based scaffolds are used in cartilage repair and tissue engineering, and their design is informed by collagen structure, crosslinking and degradation.
Elastin
The third matrix macromolecule. Elastin completes the set. It is the structural protein responsible for elastic recoil in tissues that must stretch and rebound: the ligamentum flavum, aorta, skin and lung. The ligamentum flavum is the most elastin-rich ligament, roughly 80% elastin, which is why it stays taut and does not buckle into the spinal canal.
Assembly. Soluble tropoelastin is secreted and deposited onto a scaffold of fibrillin-1 microfibrils, then crosslinked into the insoluble polymer by lysyl oxidase, the same copper-dependent enzyme used for collagen, through the unique desmosine and isodesmosine crosslinks.
Disease. Fibrillin-1 (FBN1) mutations cause Marfan syndrome, the microfibril defect dysregulating TGF-beta signalling. Elastin (ELN) defects cause cutis laxa and supravalvular aortic stenosis (Williams syndrome), and failure of copper-dependent crosslinking (Menkes, lathyrism) weakens elastin as well as collagen.
Collagen: Molecular Structure
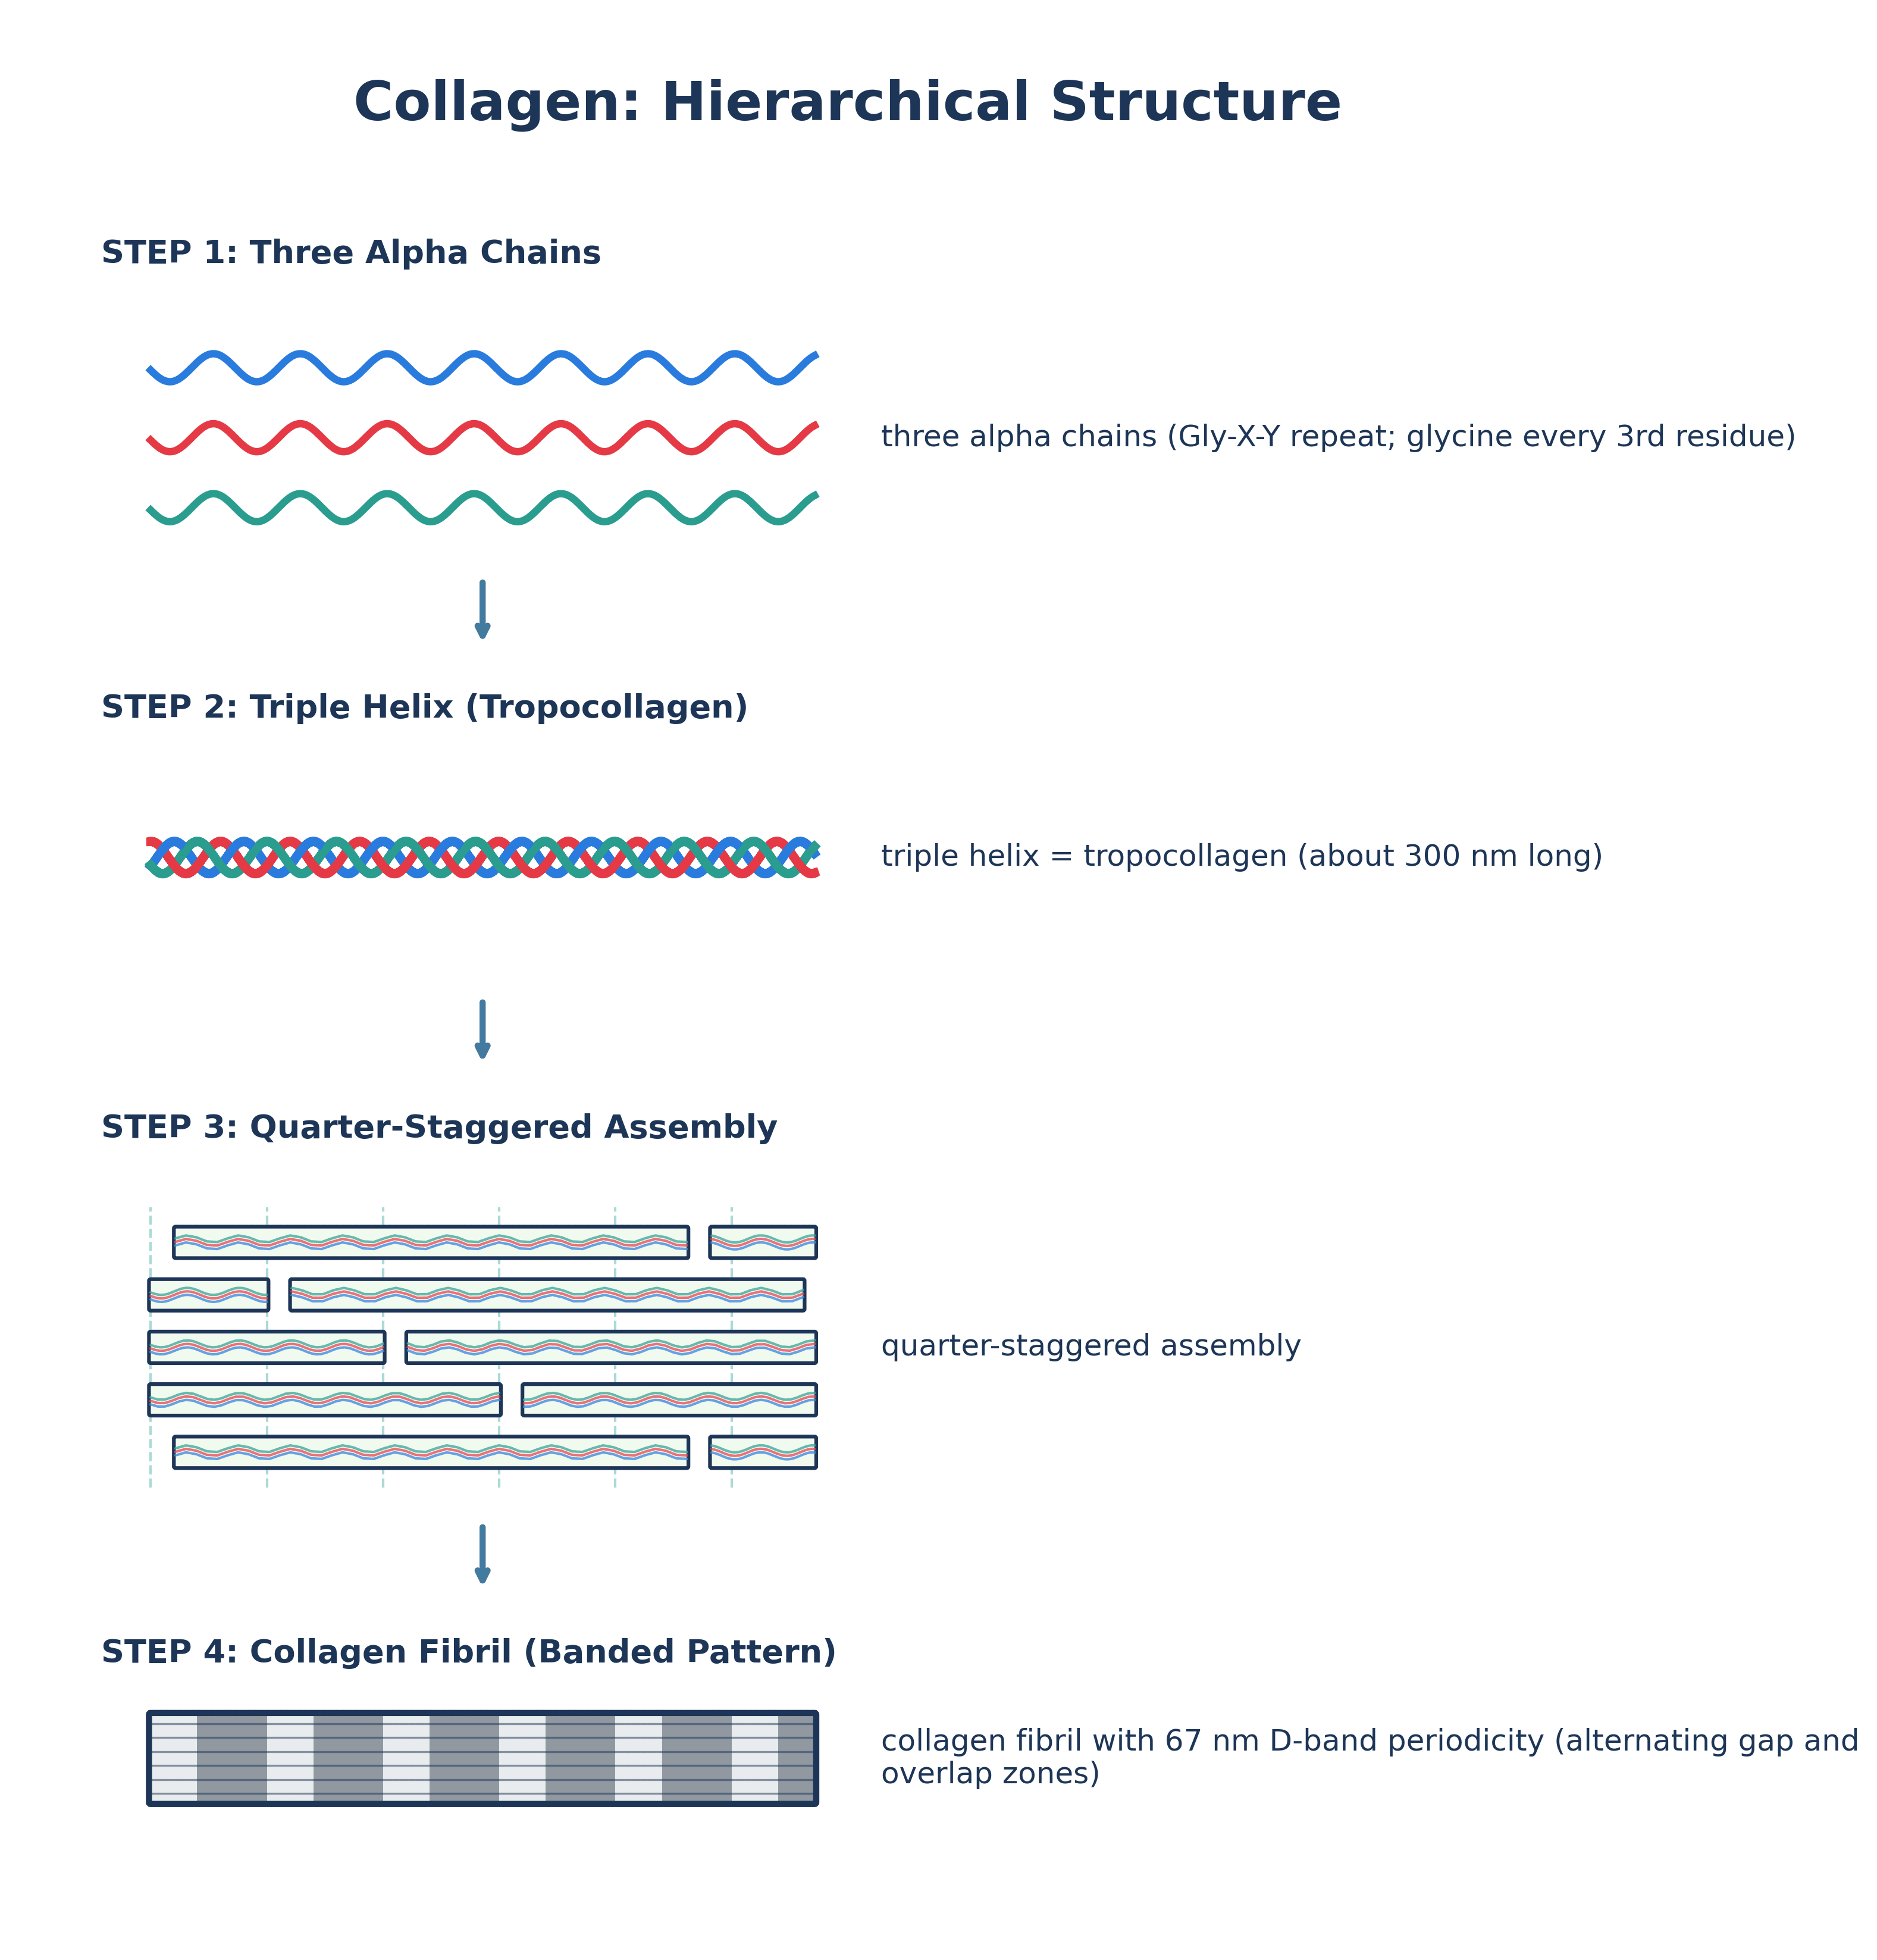
Collagen is built as a hierarchy, from alpha chain to triple helix, fibril and fibre.
The triple helix
The Gly-X-Y repeat. Glycine sits at every third residue. It is the smallest amino acid and the only one small enough to fit in the centre of the helix, so any other amino acid in the glycine position disrupts it. The X position is often proline (28%) and the Y position often hydroxyproline (38%), and both stabilise the helix.
Left-handed chains, right-handed helix. Each alpha chain is a left-handed helix of the polyproline II type, with three residues per turn, an extended structure unlike the compact alpha-helix. Three chains wrap round one another into a right-handed triple helix, with the glycines along the central axis. There are no hydrogen bonds within a chain; the hydrogen bonds run between chains.
The tropocollagen molecule. The finished molecule is 300 nm long, 1.5 nm in diameter and about 300 kDa. Type I has two alpha-1(I) chains and one alpha-2(I), while Type II has three identical alpha-1(II) chains, a homotrimer.
Glycine substitutions in Type I collagen cause osteogenesis imperfecta. A larger amino acid in the glycine position, such as serine or cysteine, disrupts the helix and the bones become brittle, and the location of the mutation affects severity. Mutations replacing glycine also cause EDS.
Biosynthesis
Inside the cell, then outside. The first four steps take place within the cell, in the rough endoplasmic reticulum (RER) and Golgi, and the last three in the matrix. Two steps depend on a cofactor, vitamin C for hydroxylation and copper for crosslinking, and each deficiency has its disease.
Collagen Synthesis and Assembly
Pro-alpha chains are translated from mRNA on ribosomes, and a signal peptide directs them into the RER. Each chain carries N-terminal and C-terminal propeptides that will be cleaved later.
In the RER, prolyl hydroxylase converts proline to hydroxyproline and lysyl hydroxylase converts lysine to hydroxylysine. Both require vitamin C (ascorbic acid) as cofactor. Hydroxyproline stabilises the triple helix, and hydroxylysine provides the sites for glycosylation and crosslinks.
Glucose and galactose are added to hydroxylysine residues in the RER and Golgi apparatus.
Three pro-alpha chains assemble into the procollagen triple helix in the RER and Golgi. The C-terminal propeptides direct alignment and initiate helix formation, and the helix zips up from the C-terminal to the N-terminal end.
Procollagen is secreted from the cell in secretory vesicles, and procollagen peptidases cleave the N-terminal and C-terminal propeptides. What remains is tropocollagen, the mature collagen molecule.
Tropocollagen molecules self-assemble into quarter-staggered fibrils, a spontaneous process driven by entropy and electrostatic forces.
Lysyl oxidase, a copper-dependent enzyme, oxidises lysine and hydroxylysine to the aldehydes allysine and hydroxyallysine. These condense to form covalent crosslinks between molecules, Schiff bases and aldol crosslinks, which stabilise the fibrils and provide tensile strength.
Scurvy. Vitamin C deficiency impairs prolyl and lysyl hydroxylase activity, and scurvy affects all collagen types. Collagen is still synthesised but lacks adequate hydroxyproline, so the triple helix is unstable and denatures at body temperature. It presents with bleeding gums, poor wound healing and, in children, bone abnormalities, and is treated with vitamin C supplementation.
Fibrils and fibres
The quarter-stagger. Tropocollagen molecules align with a 67 nm stagger, the D-period. The offset leaves alternating gap zones (0.6D) and overlap zones (0.4D).
The D-band. On electron microscopy the stagger shows as the D-band, dark overlap zones alternating with light gap zones, and staining with phosphotungstic acid enhances it. The banding is the characteristic feature that identifies a collagen fibril.
In bone, hydroxyapatite crystals nucleate in the gap zones of collagen fibrils, 40 nm gaps in each 67 nm D-period. This explains why collagen is essential for bone mineralisation, and why the mineral deposits in bone are organised and aligned with the direction of the fibrils.
Fibril diameter. Fibrils measure 20-500 nm across depending on the tissue. Type I fibrils are 50-200 nm and Type II fibrils smaller, at 20-40 nm. In cross-section the molecules are organised in quasi-hexagonal packing.
Fibrils into fibres. Fibrils bundle into collagen fibres micrometres in diameter, visible under light microscopy. The orientation of the fibres determines the anisotropy of the tissue.
Crosslinks
Immature crosslinks. Lysyl oxidase oxidises lysine to allysine, an aldehyde, which condenses to form dehydrolysinonorleucine (DHLNL) and lysinonorleucine (LNL). These are reducible Schiff bases, formed immediately.
Mature crosslinks. Pyridinoline (PYD) and deoxypyridinoline (DPD) develop over weeks to months. They are trifunctional, connecting three molecules, and are more stable and give greater tensile strength. They are found in bone, cartilage and dentin.
Crosslinks as markers. Urinary PYD and DPD are markers of bone resorption: released during bone turnover, they are not metabolised. They are elevated in osteoporosis, Paget disease and metastases.
Lathyrism. Lysyl oxidase requires copper. Copper deficiency, or inhibition by beta-aminopropionitrile (from the sweet pea, Lathyrus), prevents crosslinking: the fibrils form but are weak and soluble, and the result is lathyrism, with skeletal abnormalities, vascular rupture and poor wound healing. Penicillamine also interferes with crosslinking.
Major Collagen Types
28 collagen types have been identified. Those that matter in orthopaedics are Types I, II, III, IV, V, IX, X and XI. Type I predominates in bone and tendon (90%), and Type II is the collagen of hyaline cartilage.
Families. Collagens are grouped by the structures they form:
- Fibril-forming: Types I, II, III, V, XI, which form D-banded fibrils
- FACIT (fibril-associated collagens with interrupted triple helices): Types IX, XII, XIV
- Network-forming: Types IV, VIII, X, in basement membranes and specialised networks
- Anchoring fibrils: Type VII, at the epidermis-dermis junction
- Transmembrane: Types XIII, XVII, XXIII
- Structure
- Fibril-forming [α1(I)]₂α2(I)
- Tissue Distribution
- Bone, tendon, ligament, skin, dentin
- Function
- Tensile strength, structural support
- Clinical Significance
- OI: mutations in COL1A1, COL1A2
- Structure
- Fibril-forming [α1(II)]₃
- Tissue Distribution
- Hyaline cartilage, vitreous humor, nucleus pulposus
- Function
- Tensile strength in cartilage
- Clinical Significance
- Chondrodysplasias, early OA
- Structure
- Fibril-forming [α1(III)]₃
- Tissue Distribution
- Blood vessels, skin, reticular fibers, healing tissue
- Function
- Elastic recoil, early wound healing
- Clinical Significance
- Vascular EDS (Type IV EDS)
- Structure
- Network-forming [α1(IV)]₂α2(IV)
- Tissue Distribution
- Basement membranes (all)
- Function
- Filtration barrier, cell attachment
- Clinical Significance
- Alport syndrome (kidney, ear, eye)
- Structure
- Fibril-forming [α1(V)]₂α2(V)
- Tissue Distribution
- Bone, cornea, with Type I
- Function
- Regulates Type I fibril diameter
- Clinical Significance
- Classical EDS (with Type I)
- Structure
- FACIT [α1(IX)]α2(IX)α3(IX)
- Tissue Distribution
- Cartilage, vitreous, with Type II
- Function
- Links Type II fibrils, resists shear
- Clinical Significance
- Multiple epiphyseal dysplasia
- Structure
- Network-forming [α1(X)]₃
- Tissue Distribution
- Hypertrophic cartilage (growth plate)
- Function
- Endochondral ossification
- Clinical Significance
- Schmid metaphyseal chondrodysplasia
- Structure
- Fibril-forming [α1(XI)]α2(XI)α3(XI)
- Tissue Distribution
- Cartilage, vitreous, with Type II
- Function
- Regulates Type II fibril diameter
- Clinical Significance
- Stickler syndrome (with Type II)
Proteoglycans and Glycosaminoglycans
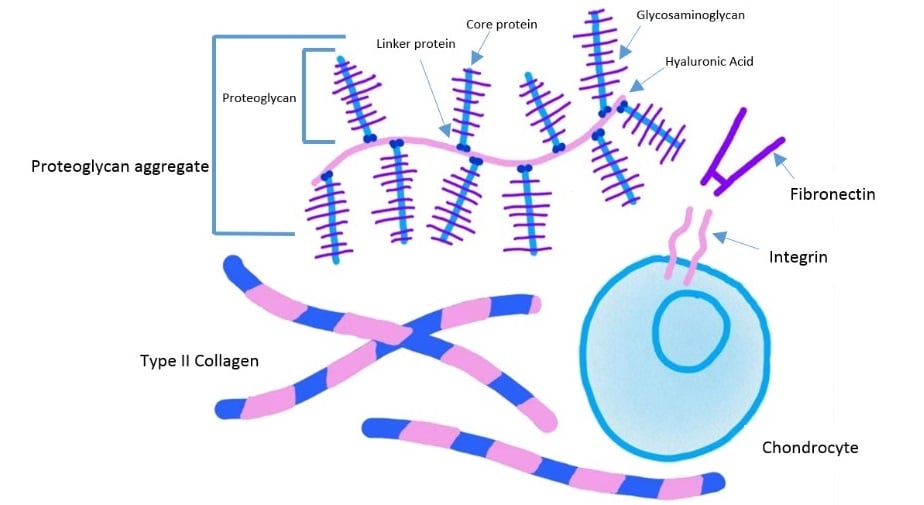
A proteoglycan is a core protein with covalently attached GAG side chains. Cartilage has the highest proteoglycan content, 4-7% of its wet weight.
Structure
Core protein and chains. The core protein is synthesised on ribosomes and varies in size, and the GAG chains are synthesised in the Golgi and attached to it. Proteoglycans vary in size and GAG composition with the function of the tissue, from small decorin through perlecan to aggrecan, the largest.
The attachment. GAGs attach to serine residues on the core protein through a tetrasaccharide linker, xylose-galactose-galactose-glucuronic acid. Keratan sulfate is the exception, attached to serine or threonine via N-acetylgalactosamine.
Glycosaminoglycans
The chains. GAGs are unbranched polysaccharides built from repeating disaccharide units.
- Disaccharide Repeat
- GlcUA-GalNAc
- Sulfation
- 4-sulfate or 6-sulfate
- Location
- Cartilage, bone, tendon
- Function
- Hydration, compression resistance
- Disaccharide Repeat
- Gal-GlcNAc
- Sulfation
- 6-sulfate
- Location
- Cartilage, cornea
- Function
- Hydration, increases with age
- Disaccharide Repeat
- IdoUA-GalNAc
- Sulfation
- Variable sulfation
- Location
- Skin, blood vessels, heart valves
- Function
- Collagen fibril organization
- Disaccharide Repeat
- GlcUA/IdoUA-GlcNAc
- Sulfation
- High sulfation (N, 2-O, 6-O)
- Location
- Basement membranes, cell surface
- Function
- Growth factor binding, anticoagulation
- Disaccharide Repeat
- GlcUA-GlcNAc
- Sulfation
- None (no sulfate)
- Location
- Synovial fluid, cartilage, vitreous
- Function
- Aggregation backbone, lubrication
Further points for each GAG:
- Chondroitin sulfate is the most abundant in cartilage, as the 4-sulfate (CS-A) or 6-sulfate (CS-C)
- Keratan sulfate has no uronic acid, carrying galactose instead
- Dermatan sulfate contains iduronic acid and binds decorin (regulating collagen fibrillogenesis)
- Heparan sulfate binds growth factors such as FGF and VEGF
- Hyaluronan is the only non-sulfated GAG, is not attached to a core protein, and is synthesised at the cell surface
Why the charge matters. Sulfate (SO₄⁻) and carboxyl (COO⁻) groups give GAG chains a high fixed negative charge density. That charge creates a Donnan osmotic pressure that draws water and cations (Na⁺, Ca²⁺) into the tissue, and in cartilage the resulting swelling pressure provides compressive stiffness.
The major proteoglycans
Aggrecan. The largest proteoglycan, 2-3 million Da, has a 220-250 kDa core protein carrying about 100 chondroitin sulfate and about 60 keratan sulfate chains. It provides the compressive stiffness of cartilage, and it turns over slowly, with a year-long half-life.
The aggregate. 50-100 aggrecan molecules bind a central hyaluronan backbone, up to 4000 nm long, through their G1 domains, and link protein (40-45 kDa), found only with aggrecan, stabilises the binding. The aggregate reaches 50-200 million Da, and its osmotic swelling pressure resists compression.
The aggrecan core protein is organised into domains:
- G1: binds hyaluronan
- Interglobular domain (IGD): the proteolysis site
- G2: function unclear
- Chondroitin sulfate-attachment regions and a keratan sulfate-attachment region
- G3: C-terminal, lectin-like
Aggrecanases (ADAMTS-4, ADAMTS-5) cleave aggrecan in the IGD in osteoarthritis, releasing the CS-rich portion. The result is cartilage proteoglycan loss, reduced compressive stiffness and increased water content (early OA on MRI).
Decorin and biglycan. Both are small leucine-rich proteoglycans (SLRPs) with a 40 kDa core that regulate collagen fibrillogenesis. Decorin, in tendon, ligament, bone and cartilage, carries one dermatan sulfate or chondroitin sulfate chain, 90-140 kDa in total. It binds Type I and II collagen fibrils, regulates fibril diameter and spacing, and has anti-fibrotic properties. Biglycan, in bone and tendon, carries two such chains and binds growth factors (TGF-β, BMPs).
Perlecan. A large modular proteoglycan of basement membranes, with a 470 kDa core and multiple heparan sulfate chains. It serves filtration and acts as a growth factor reservoir, binding growth factors and regulating angiogenesis.
Versican. A large chondroitin sulfate proteoglycan, abundant in loose connective tissue, with a role in cell adhesion and migration.
Lubricin
Boundary lubrication. Lubricin (proteoglycan-4, PRG4, also called superficial zone protein, SZP) is a mucinous proteoglycan, distinct from the large aggregating aggrecan, secreted by superficial-zone chondrocytes and synovial lining cells. Its central mucin domain carries O-linked GAG-like sugars that make it amphiphilic, so it adsorbs to the cartilage surface and provides boundary lubrication. That is the dominant lubrication mode at low velocity and high load, protecting the surface where a fluid film cannot form, and it works alongside hyaluronan and interstitial fluid pressurisation.
When it fails. Loss-of-function PRG4 mutations cause camptodactyly-arthropathy-coxa vara-pericarditis (CACP) syndrome, with congenital joint contractures and non-inflammatory arthropathy. Lubricin depletion is implicated in post-traumatic and osteoarthritic surface wear.
Differential Diagnosis: Heritable Collagen/ECM Disorders
Glycine substitutions, defective hydroxylation/crosslinking, and proteoglycan-processing defects all converge on connective-tissue fragility but differ in the molecule affected and the dominant phenotype. This table is high-yield for distinguishing the classic ECM diseases in a viva.
- Molecule / Gene
- Type I collagen (COL1A1/COL1A2)
- Defect Mechanism
- Glycine substitution or haploinsufficiency
- Key Clinical Clue
- Fragile bones, blue sclerae, dentinogenesis imperfecta
- Molecule / Gene
- Type III collagen (COL3A1)
- Defect Mechanism
- Reduced/abnormal type III collagen
- Key Clinical Clue
- Arterial, bowel and uterine rupture; thin translucent skin
- Molecule / Gene
- Type V collagen (COL5A1/COL5A2)
- Defect Mechanism
- Disordered type I fibril regulation
- Key Clinical Clue
- Skin hyperextensibility, atrophic scars, hypermobility
- Molecule / Gene
- Type II collagen (COL2A1)
- Defect Mechanism
- Defective cartilage collagen
- Key Clinical Clue
- Short stature, myopia/retinal detachment, early OA
- Molecule / Gene
- Type IV collagen (COL4A3-5)
- Defect Mechanism
- Defective basement-membrane network
- Key Clinical Clue
- Haematuria/renal failure, sensorineural deafness
- Molecule / Gene
- Hydroxyproline (acquired)
- Defect Mechanism
- Vitamin C deficiency → no prolyl hydroxylation
- Key Clinical Clue
- Perifollicular haemorrhage, gum bleeding, poor healing
- Molecule / Gene
- Lysyl oxidase activity (ATP7A, copper)
- Defect Mechanism
- Copper deficiency → no crosslinking
- Key Clinical Clue
- Kinky hair, vascular tortuosity, bone fragility
- Molecule / Gene
- GAG-degrading enzymes (e.g. IDUA)
- Defect Mechanism
- Lysosomal GAG accumulation
- Key Clinical Clue
- Dysostosis multiplex, stiff joints, organomegaly
Guidelines, Registries & Global Practice
Global Relevance and Epidemiology
- Collagen and proteoglycan biochemistry is core basic-science content across all major fellowship examinations.
- Osteoarthritis, the dominant downstream disease of proteoglycan/collagen failure, affects an estimated 500+ million people worldwide and is a leading global cause of years lived with disability.
- Heritable disorders provide the natural "knockout" experiments: OI incidence is roughly 1 in 15,000-20,000 births; EDS collectively around 1 in 5,000.
Side-by-Side Guidance (ECM-Targeted OA Therapies)
- Glucosamine & Chondroitin
- Not recommended (strong, against)
- Intra-articular Hyaluronic Acid
- Not recommended for routine knee OA
- Glucosamine & Chondroitin
- Do not offer for OA
- Intra-articular Hyaluronic Acid
- Do not offer for OA management
- Glucosamine & Chondroitin
- Not recommended for disease modification
- Intra-articular Hyaluronic Acid
- Conditional/uncertain; context-dependent
- Glucosamine & Chondroitin
- Prescription crystalline glucosamine sulfate viewed more favourably
- Intra-articular Hyaluronic Acid
- May be considered as add-on in some algorithms
Registry & Practice Variation
- Joint registries (NJR UK, AJRR US, AOANJRR Australia, Swedish/Norwegian registries) capture the end-stage arthroplasty outcomes of cartilage matrix failure and increasingly track cartilage-repair and biologic procedures.
- High-resource settings: access to cell-based cartilage repair (ACI/MACI), osteochondral grafting and quantitative MRI of cartilage matrix (T1rho, dGEMRIC) for early matrix assessment.
- Limited-resource settings: emphasis on conservative load management, weight optimisation and addressing nutritional collagen cofactors (vitamin C, copper) where deficiency is endemic; advanced biologics are often unavailable.
Controversies & Areas of Uncertainty
Glasson's mouse data established ADAMTS5 as the dominant aggrecanase in rodents, but the relative contribution of ADAMTS4 versus ADAMTS5 in human disease remains debated, complicating translation of selective inhibitors.
GAG-precursor supplements are widely consumed, yet high-quality trials and meta-analyses show inconsistent, at best small, effects on pain and no convincing structure modification. Major guidelines (e.g. OARSI, NICE) do not recommend them for disease modification.
Despite a coherent biological rationale (restoring synovial HA), pooled evidence for clinically meaningful benefit in knee OA is weak and contested; recommendations differ markedly between societies.
Beyond collagen volume, the ratio of enzymatic (pyridinoline) to non-enzymatic advanced-glycation-end-product crosslinks is increasingly implicated in age- and diabetes-related bone fragility, but is not yet a routine clinical metric.
MCQ Practice Points
Q: What is the predominant proteoglycan in articular cartilage and its function?
A: Aggrecan is the major proteoglycan, attached to hyaluronic acid via link protein forming large aggregates. Contains glycosaminoglycan (GAG) side chains (chondroitin sulfate, keratan sulfate). Highly negatively charged, attracting water creating osmotic swelling pressure that resists compressive loads. Loss of aggrecan is early OA feature.
Q: What is the distribution of collagen types in articular cartilage?
A: Type II collagen: 90-95% of cartilage collagen, provides tensile strength. Type IX: Cross-links Type II fibrils. Type XI: Regulates fibril diameter. Type VI: Pericellular matrix around chondrocytes. Fibrocartilage (meniscus, labrum) contains Type I collagen. OA involves shift from Type II to Type I.
Q: What is the water content of articular cartilage and its significance?
A: Articular cartilage is 65-80% water by weight. Water content highest in superficial zone, lowest in deep zone. Creates biphasic viscoelastic behavior - fluid pressurization under load. Water bound to proteoglycans (fixed charge density). Dehydration decreases compressive stiffness. OA shows increased water content paradoxically.
Q: What are the structural zones of articular cartilage?
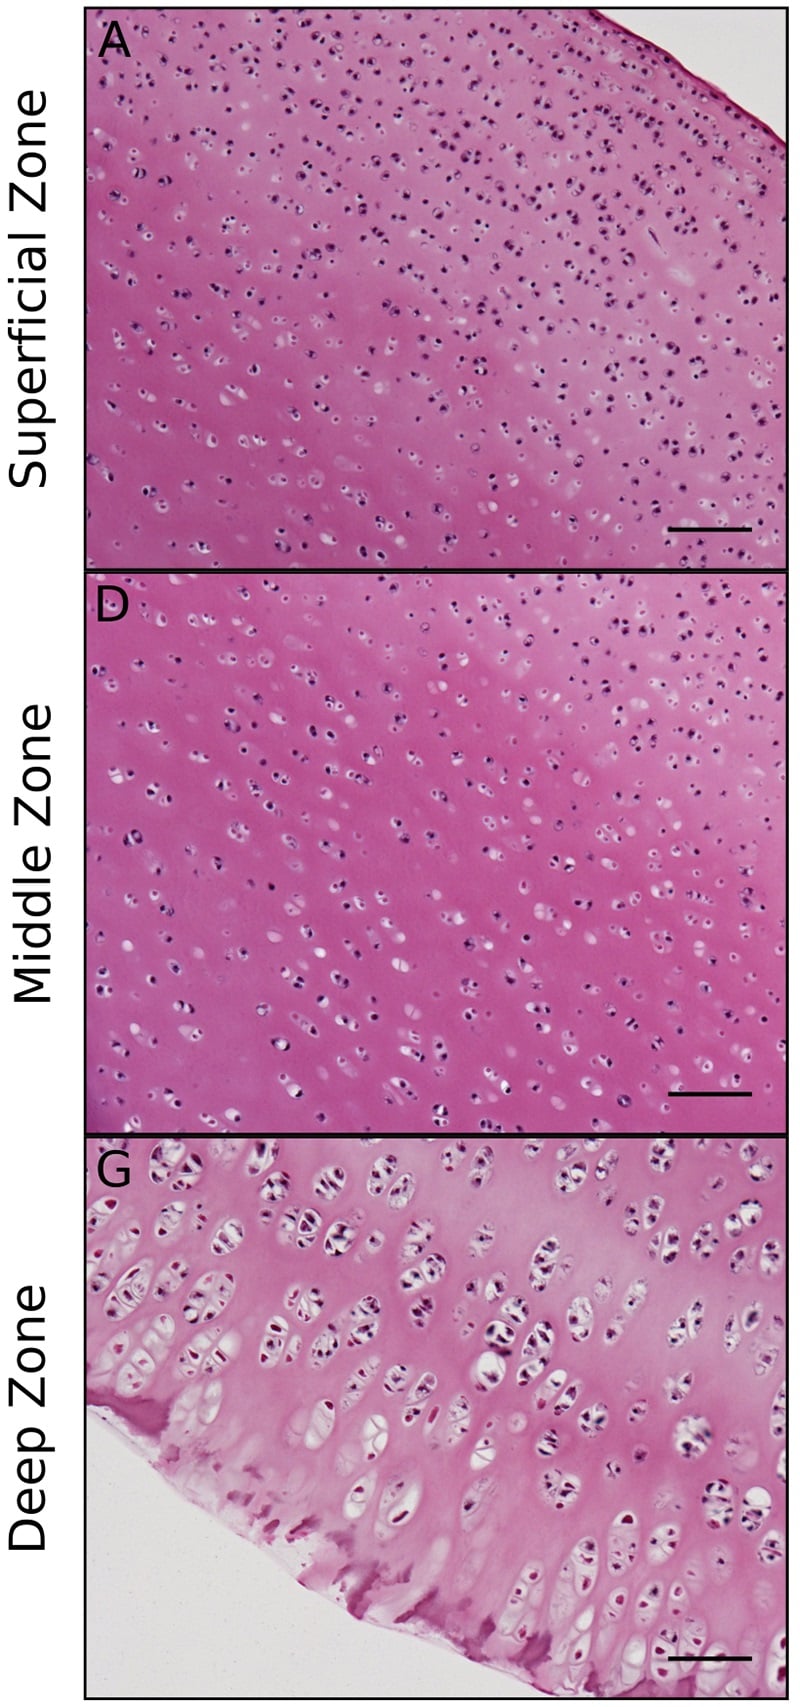
A: Superficial zone (10-20%): Collagen parallel to surface, highest water, flattened chondrocytes, lubricin secretion. Middle/transitional zone (40-60%): Random collagen orientation. Deep zone (30%): Collagen perpendicular, highest proteoglycan, columns of chondrocytes. Calcified zone: Anchors to subchondral bone via tidemark.
Q: What is the triple helix structure of collagen?
A: Three polypeptide chains (α-chains) wind into right-handed triple helix. Stabilized by glycine at every third position (smallest amino acid fits helix center). Proline and hydroxyproline provide rigidity. Hydroxyproline requires Vitamin C (scurvy causes collagen defects). Cross-linking between molecules provides tensile strength.
Basic Science Viva Scenarios
Practise clinical reasoning and management decisions out loud
“Describe the structure of the collagen triple helix. What is the significance of the Gly-X-Y repeat?”
“Describe the steps of collagen biosynthesis from translation to fibril formation. Where are crosslinks formed and why are they important?”
“Describe the structure of aggrecan. How does it provide compressive stiffness in articular cartilage?”
Collagen Triple Helix
- Gly-X-Y repeat: glycine every 3rd residue (small enough for helix center)
- X = proline (28%), Y = hydroxyproline (38%)
- Three alpha chains: right-handed superhelix, 300 nm length, 1.5 nm diameter
- Type I: [α1(I)]₂α2(I), Type II: [α1(II)]₃ homotrimer
Collagen Biosynthesis
- Hydroxylation: Prolyl/lysyl hydroxylase (requires Vitamin C cofactor)
- Triple helix: C-terminal propeptides initiate assembly
- Propeptide cleavage: Procollagen → tropocollagen (300 nm)
- Fibril assembly: Quarter-stagger creates 67 nm D-band
- Crosslinks: Lysyl oxidase (requires copper) creates pyridinoline, deoxypyridinoline
Major Collagen Types
- Type I: Bone, tendon, ligament (90% of body collagen), OI mutations
- Type II: Hyaline cartilage, nucleus pulposus, chondrodysplasia mutations
- Type III: Blood vessels, skin, healing tissue, vascular EDS
- Type IV: Basement membranes (network-forming), Alport syndrome
Proteoglycan Structure
- Core protein + GAG side chains (chondroitin sulfate, keratan sulfate, etc)
- Aggrecan: 2-3 MDa, ~100 CS + ~60 KS chains
- Aggregates: 50-100 aggrecans bind hyaluronan via link protein (40-45 kDa)
- Decorin: Small (90-140 kDa), binds collagen, regulates fibril diameter
GAG Types
- Chondroitin sulfate (CS): GlcUA-GalNAc, 4- or 6-sulfate, cartilage/bone
- Keratan sulfate (KS): Gal-GlcNAc, 6-sulfate, cartilage (increases with age)
- Dermatan sulfate (DS): IdoUA-GalNAc, decorin GAG, regulates collagen
- Heparan sulfate (HS): High sulfation, basement membranes, growth factor binding
- Hyaluronan (HA): No sulfate, not protein-bound, aggregation backbone
Proteoglycan Function
- Fixed negative charge (SO₄⁻, COO⁻) attracts water via Donnan equilibrium
- Swelling pressure (0.1-0.3 MPa) provides compression resistance
- Collagen network constrains proteoglycan swelling (prestress)
- Aggrecan in cartilage: highest in deep zone (50-60 mg/mL)
Clinical Correlations
- Scurvy: Vitamin C deficiency → no hydroxyproline → unstable collagen
- Lathyrism: Lysyl oxidase inhibition (or Cu deficiency) → no crosslinks
- OI: Type I collagen mutations (glycine substitutions) → brittle bones
- OA: Aggrecanase (ADAMTS-4,5) cleaves aggrecan IGD → proteoglycan loss
- Urinary PYD/DPD: Bone resorption markers (crosslinks released)
Evidence Base
Collagen Structure and Stability
- Collagen is a right-handed bundle of three left-handed polyproline II-type helices
- Stereoelectronic effects and preorganisation (not just hydrogen bonding) drive triple-helix stability
- Hydroxyproline in the Y position stabilises the helix via inductive/stereoelectronic effects
- Self-assembly of type I tropocollagen reproduces native fibril properties in synthetic systems
Proteoglycan Form and Function: A Comprehensive Nomenclature
- Defines 43 distinct proteoglycan-encoding genes grouped into 4 classes by location
- Classes: intracellular, cell-surface, pericellular and extracellular proteoglycans
- Aggrecan (extracellular, modular) provides compressive stiffness in cartilage
- Small leucine-rich proteoglycans (decorin, biglycan) regulate collagen fibrillogenesis and signalling
Osteogenesis Imperfecta (Disease Primer)
- ~85% of OI is caused by dominant mutations in the type I collagen genes COL1A1 or COL1A2
- Mutations affect collagen quantity (haploinsufficiency, milder) or structure (glycine substitutions, more severe)
- Recessive, dominant and X-linked defects in collagen processing/modification and osteoblast genes cause the remaining cases
- Extra-skeletal features include blue sclerae, dentinogenesis imperfecta, hearing loss and cardiovascular involvement
The Role of Aggrecan in Normal and Osteoarthritic Cartilage
- Aggrecan bears chondroitin sulfate and keratan sulfate chains and aggregates with hyaluronan via link protein
- Both aggrecanases (ADAMTS) and matrix metalloproteinases cleave aggrecan, but at distinct sites
- Inflammation and overloading upregulate aggrecanolytic enzymes, depleting aggrecan in OA
- Synovial-fluid aggrecan fragments serve as a marker of ongoing cartilage destruction
Deletion of Active ADAMTS5 Prevents Cartilage Degradation (Landmark)
- First single-gene deletion shown to abrogate cartilage destruction in a model of OA
- Mice lacking the ADAMTS5 catalytic domain were protected after surgical joint destabilisation
- Identified ADAMTS5 (aggrecanase-2) as the primary aggrecanase in murine OA
- Established the aggrecanase IGD cleavage site as a rational therapeutic target
The 2017 International Classification of the Ehlers-Danlos Syndromes
- Replaced the 1998 Villefranche six-type nosology with 13 recognised EDS subtypes
- Most subtypes arise from defects in collagen genes or collagen-modifying enzymes
- Molecular confirmation is required for all subtypes except hypermobile EDS (clinical diagnosis)
- Vascular EDS (type III collagen / COL3A1) carries the highest risk of arterial and visceral rupture