Congenital Popliteal & Multiple Webbing
- A pterygium is a congenital flexor-surface web holding a joint in fixed flexion; it contains shortened skin, fascia and neurovascular structures
- Popliteal pterygium syndrome is autosomal dominant (IRF6, allelic with Van der Woude) and multisystem: popliteal web and fixed knee flexion with clefting, genital, syndactyly and foot anomalies
- Escobar (multiple pterygium) syndrome is autosomal recessive (CHRNG): webs across multiple joints, with scoliosis
- The sciatic nerve is often shortened and superficial within the web; it usually limits correction and is at risk during release
- Staged release (Z-plasty, band excision, graded soft-tissue release) with rehabilitation; do not force one-stage extension
- Correction is obtainable but not durable: 6 of 8 children needed re-correction at a mean of 3-4 years
- No guideline exists: the pooled world literature is about 58 patients and 87 limbs
- “Posterior tibial subluxation or dislocation (5 in the largest series) was associated with recurrence every time: it is the warning sign.
- “Pooled comparison: Ilizarov = best mobility, most sessions, highest complication rate; femoral shortening osteotomy = fewest sessions, no reported complications (uncontrolled).
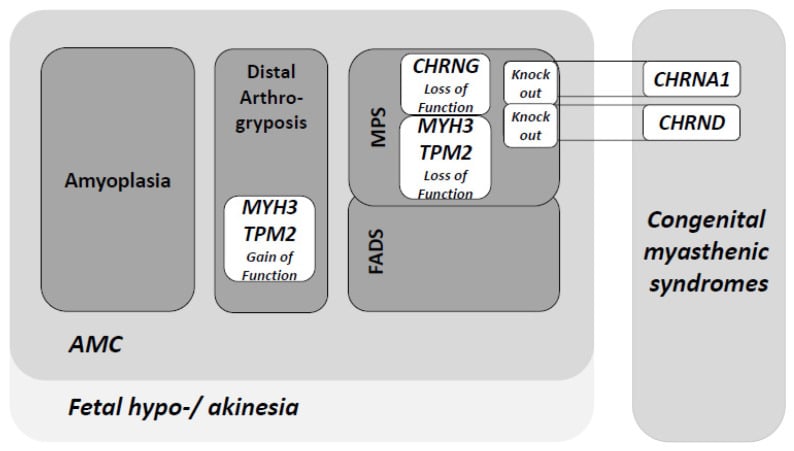
- “Escobar: loss of fetal acetylcholine-receptor function → fetal akinesia → contractures and pterygia (the fetal akinesia deformation sequence).
What a Pterygium Is
A pterygium is a congenital skin and soft-tissue web that bridges the flexor aspect of a joint and tethers it in fixed flexion. The pterygium syndromes are a group in which such webs cause congenital contractures. The orthopaedic difficulty is what the web contains: shortened skin, fascia, muscle and tendon and, critically, neurovascular structures.
Popliteal pterygium syndrome (PPS). A rare autosomal-dominant condition caused by IRF6 mutations and allelic with Van der Woude syndrome. A popliteal web produces a fixed flexion deformity of the knee, and the company it keeps makes PPS a multisystem syndrome, not just a knee problem. It commonly comes with:
- Orofacial clefting: cleft lip or palate, lower-lip pits
- Genital anomalies
- Syndactyly
- Foot deformity, such as equinovarus
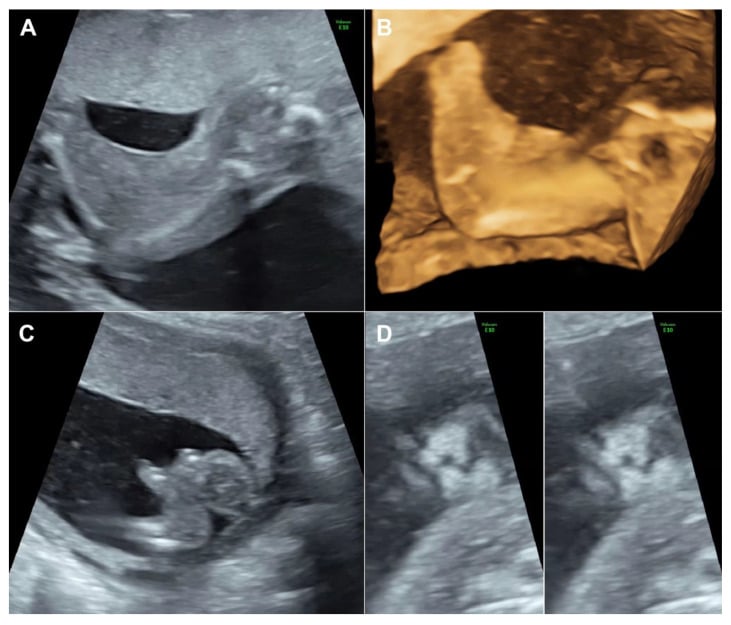
Multiple pterygium syndrome (Escobar). Webs cross multiple joints (neck, axilla, antecubital fossa and popliteal fossa) with multiple congenital contractures, scoliosis, short stature and characteristic facies. It is a distinct, more generalised entity than PPS, and a lethal antenatal form also exists.
The Genetics of Escobar Syndrome
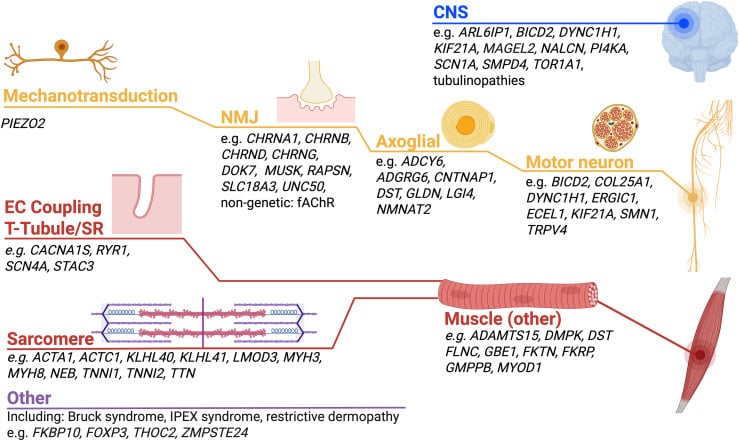
The gene. Escobar syndrome is autosomal recessive, caused by mutations in CHRNG, the gene for the gamma subunit of the fetal acetylcholine receptor (AChR). This is the receptor used at the neuromuscular junction before birth, later replaced by the adult epsilon-subunit receptor. Both gene and inheritance differ from popliteal pterygium syndrome.
Why the webs form. Loss of fetal AChR function impairs fetal neuromuscular transmission and reduces fetal movement (akinesia). Joints held immobile in utero develop contractures and pterygia across their flexor surfaces. The webs are part of the fetal akinesia deformation sequence, with pulmonary hypoplasia, micrognathia, intrauterine growth restriction (IUGR) and, antenatally, cystic hygroma/polyhydramnios.
The lethal end. Lethal multiple pterygium syndrome is the severe end of the same fetal-akinesia and AChR-deficiency spectrum, caused by CHRNG and other fetal-AChR-pathway genes. Severe akinesia and pulmonary hypoplasia cause fetal or neonatal death.
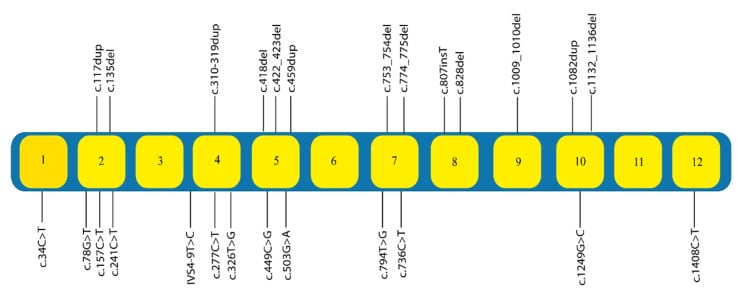
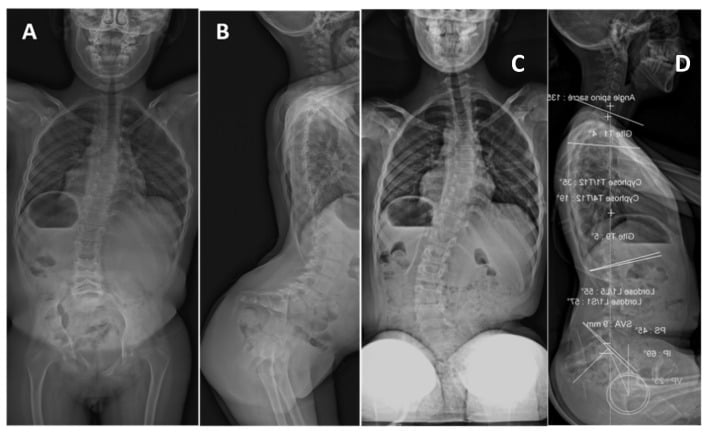
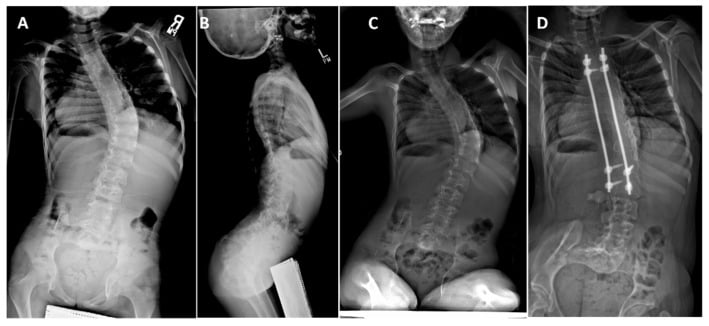
Assessment
Assess the whole child, not just the web:
- The contracture
- The soft-tissue deficiency
- The neurovascular anatomy, with imaging or angiography as needed
- The associated anomalies: clefting, genital, foot
- The genetic diagnosis
The team. Care is multidisciplinary: plastic and orthopaedic surgery, genetics with counselling, and management of the cleft and genital anomalies.
The Nerve in the Web
The anatomy. The neurovascular bundle, including the sciatic nerve and the popliteal vessels, is often shortened and abnormally placed. It lies superficially within the web, often along its free edge.
Why it limits correction. The structure that limits straightening the knee is usually the shortened nerve rather than the skin or fascia, and the nerve is at risk during release. Full correction in one stage is often impossible for that reason, so correction is gradual or staged, towards realistic functional goals.
Straightening the knee fully in a single stage risks traction injury to the nerve and vascular compromise. Identify and protect the neurovascular bundle at every stage, and sometimes accept a degree of residual flexion to preserve nerve function.
Correcting the Knee When the Nerve Is the Limit
There is no guideline. The entire world literature on correcting a popliteal pterygium amounts to roughly 58 patients (87 limbs) pooled from 32 mostly single-case publications. Both the 2024 meta-analysis and the largest case reports state explicitly that no treatment guideline or classification exists. Any confident algorithm offered in a viva should be framed as reasoning from principles, not as established practice.
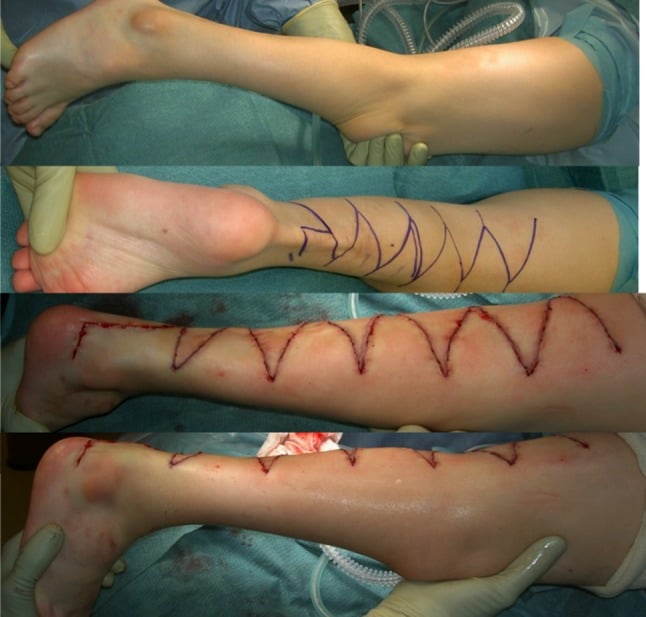
Soft-tissue release. Posterior release remains the foundation of most reconstructions, done in stages with rehabilitation. It combines skin lengthening by multiple Z-plasty or local flaps, excision of the fibrotic band, graded release of the contracted soft tissues and correction of the associated foot deformity, with the neurovascular bundle protected throughout and addressed where the shortened nerve is the limit. In the pooled data, isolated skin and soft-tissue procedures and hamstring release each improved the flexion contracture and mobility, and each required several procedures to do so.
Gradual correction with an Ilizarov frame. Because the sciatic nerve cannot be acutely stretched, a circular fixator distracts the knee straight gradually over weeks. In the largest PPS-specific series (8 children, 11 knees, treated 1986-2007, follow-up 1-21 years), complete extension was achieved in every knee. The pooled meta-analysis found the fixator gave the best knee and ankle mobility but carried the highest number of surgical sessions and the highest complication rate of any modality.
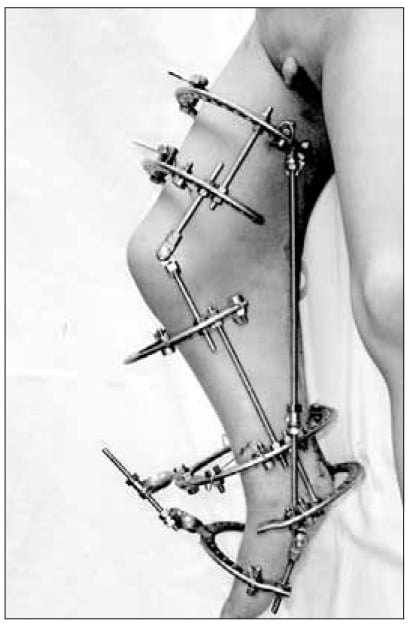
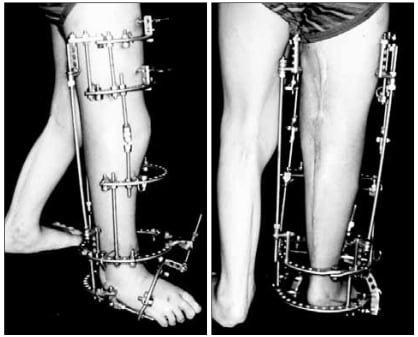
The price is recurrence. In the same series 6 of the 8 children needed the whole correction repeated, at a mean interval of 3-4 years. Five developed posterior tibial subluxation or frank dislocation (four partial, one complete), every one of them associated with recurrence. A separate Ilizarov series of severe congenital knee flexion reported pin-track and skin complications in every patient and concluded that minor recurrence must be expected in all cases. Only 2 of its 8 patients had PPS, the rest having arthrogryposis or tibial hemimelia, so it cannot be quoted as PPS-specific.
Correction is reliably obtainable but not reliably durable. Prepare the family for repeat surgery, and watch the knee for posterior subluxation as the sign that the deformity is returning.
Femoral shortening (extension) osteotomy. Shortening the femur lets the knee extend without stretching the fixed-length neurovascular bundle, trading limb length for extension and nerve safety. In the pooled comparison it achieved correction with the fewest sessions and no reported complications, the single most favourable signal in the dataset. The numbers behind it are small and uncontrolled, so this is a promising comparison, not proven superiority.
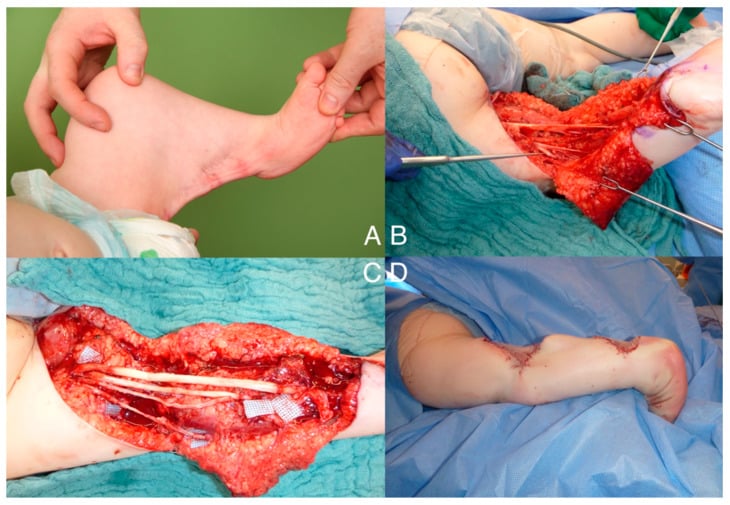
Microsurgical nerve and vessel lengthening. Interposition grafting (vein graft to the popliteal artery, autograft and allograft to the tibial and peroneal nerves) has been reported to allow correction of an 80-degree contracture in a one-year-old, with free walking and restored touch sensibility at three years. A foot orthosis was still needed for the resulting leg-length difference. An intraneural fascicular-shifting lengthening technique has also been described. Both rest on single cases, and the meta-analysis classed nerve surgery as having too little data to compare.
Salvage. For a severe unreconstructable or failed knee, arthrodesis or, rarely, amputation or knee disarticulation may be needed for bracing or prosthetic fitting. Again, the reported cases are too few to quantify.
Mnemonics & Memory Aids
PTERYGIUM
Hook:PTERYGIUM: Popliteal web, Tethered flexor surface, Escobar (multiple), Reconstruct in stages, don't Yank (nerve in web), Genetics IRF6, Investigate associations.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A child has a web across the back of the knee holding it flexed, with a cleft lip. What is the diagnosis and what is the key surgical consideration?”
What they are
- Pterygium = congenital flexor-surface web producing a fixed flexion deformity
- Web contains shortened skin, fascia AND neurovascular structures
- Group of congenital-contracture syndromes
Popliteal pterygium syndrome
- Autosomal dominant (IRF6; allelic with Van der Woude)
- Popliteal web + fixed knee flexion
- Orofacial clefting/lip pits, genital anomalies, syndactyly, foot deformity
The surgical key
- Sciatic nerve/neurovascular bundle shortened + abnormally superficial within the web
- The shortened nerve (not skin) usually limits correction and is at risk
- Plan staged/gradual correction; don't force one-stage extension
Management
- Staged release: multiple Z-plasty/flaps, fibrotic-band excision, graded contracture release
- Correct associated foot deformity; protect (and lengthen) the nerve as needed
- Multidisciplinary (plastics/orthopaedics/genetics); Escobar = autosomal recessive CHRNG, multi-joint webs + scoliosis
Outcomes - know these numbers
- No guideline or classification exists; pooled literature ~58 patients / 87 limbs from 32 mostly single-case reports
- Ilizarov: complete extension in all 11 knees of the largest series, BUT 6 of 8 children needed re-correction at mean 3-4 years
- 5 posterior tibial subluxations/dislocations, every one associated with recurrence - the warning sign
- Pooled: fixator = best mobility, most sessions, highest complications; femoral osteotomy = fewest sessions, no reported complications (uncontrolled)
- Microsurgical nerve/vessel grafting: free walking + restored touch sensibility at 3 years in a single case
Evidence & Key Studies
Comparative analysis of surgical treatment modalities for a popliteal pterygium: a meta-analysis
- PRISMA meta-analysis of the entire field: 183 papers screened, data extracted from 32 articles, yielding just 58 patients and 87 limbs - the whole reported world experience of treating a popliteal pterygium.
- Ilizarov fixator gave improved knee and ankle mobility postoperatively but had a relatively high number of surgical sessions and high complication rates. Femoral osteotomy achieved successful correction of knee posture with fewer sessions and no reported complications.
- Isolated skin/soft-tissue procedures and hamstring release both improved contracture and mobility but required several procedures each. Nerve surgery and amputation had too little data to compare.
- The authors conclude that no classification or guideline for treating this deformity exists and that further research is needed - so no modality can be presented as standard of care. Limitations: the pooled units are overwhelmingly single cases, published across four decades with no common outcome measure, no control arm and inevitable publication bias toward success.
Popliteal pterygium knee contracture: treatment with the Ilizarov technique
- Consecutive series of 8 children (11 knees) with popliteal pterygium syndrome treated at a single Paris centre between 1986 and 2007; preoperative knee flexion 40-120 degrees, with contracture over 90 degrees in 10 of the 11 knees. Follow-up 1-21 years.
- Complete extension was obtained in ALL cases by gradual Ilizarov correction - the popliteal cutaneous band and the shortened sciatic nerve were confirmed as what made realignment complex.
- RECURRENCE WAS THE RULE, NOT THE EXCEPTION: 6 of the 8 children required the correction to be repeated by the same technique, at a mean interval of 3-4 years.
- Four progressive partial posterior tibial dislocations and one complete dislocation occurred during follow-up - every one of them associated with recurrence of the flexion contracture, so the subluxing knee is the warning sign that the deformity is coming back.
- Limitations: retrospective, single centre, 8 patients across a 21-year era spanning changes in technique, no comparison group and a follow-up range (1-21 years) so wide that the recurrence rate is almost certainly an underestimate for the shortest-followed children.
Orthopaedic surgical management of complicated congenital popliteal pterygium syndrome
- A SINGLE CASE REPORT (level V), not a series - it demonstrates that the described approach is possible, and can say nothing about how often it succeeds.
- In that patient the sciatic nerve was shortened within the web and required a fascicular-shifting lengthening technique; correction used staged multiple Z-plasty and fibrotic-band excision with meticulous protection of the neurovascular bundle.
- Associated anomalies (undescended testes, syndactyly, foot deformity) required additional staged soft-tissue reconstruction - underscoring the multisystem, staged nature of management.
Walking ability after microsurgical reconstruction of paediatric popliteal pterygium syndrome
- Single case report: a one-year-old with a unilateral 80-degree knee flexion contracture, treated by large Z-plasty, vein grafting to lengthen the popliteal vessels, autograft and allograft lengthening of the tibial and peroneal nerves, and capsular and tendon releases.
- At three years the child walked freely, touch sensibility of the foot was restored and perfusion remained stable through growth; a foot orthosis was still required to balance the leg-length difference and support the midfoot deformity.
- The authors state plainly that no established treatment guidelines exist for PPS and that care must be individualised - one case cannot establish that microsurgical lengthening is preferable to gradual correction or femoral shortening.
The pooled modality comparison, the total of 58 patients and 87 limbs, and the statement that no classification or guideline exists come from the Aman meta-analysis (DOI). The recurrence in 6 of 8 children at a mean 3-4 years and the five posterior tibial subluxations/dislocations come from Solignac (DOI). The microsurgical nerve and vessel grafting outcome at three years comes from Aman's case report (DOI), and the fascicular-shifting technique from Hasan (DOI) - both single cases. The observation that every patient developed pin-track and skin complications, and that minor recurrence should be expected in all, comes from Leonchuk's Ilizarov series of severe congenital knee flexion (DOI), in which only 2 of 8 patients had PPS - it is quoted here as related evidence, not as PPS-specific data. The IRF6 genetics (allelic with Van der Woude), the orofacial-clefting and genital associations, the CHRNG basis of Escobar syndrome, and the anatomy of the shortened, superficially placed neurovascular bundle are standard, well-established teaching.
Be clear about what does not exist. There is no randomised or even prospectively controlled trial in this condition, no validated classification of pterygium severity, no agreed threshold of residual flexion that constitutes success, and no published surveillance interval for recurrence or posterior tibial subluxation. Every comparison above is between small uncontrolled case collections published across four decades.